⚠ Evidence warning: Clinical trials or other evidence do not support the claims that testosterone at female replacement doses adds 1 to 2 pounds of lean mass over 6 to 12 months, that compounded 1% cream is the closest thing to standard of care in the U.S., and that the goal is a total testosterone of about 50 to 70 ng/dL. This page keeps it as a report of what people, websites or other media say.
Testosterone Therapy for Women
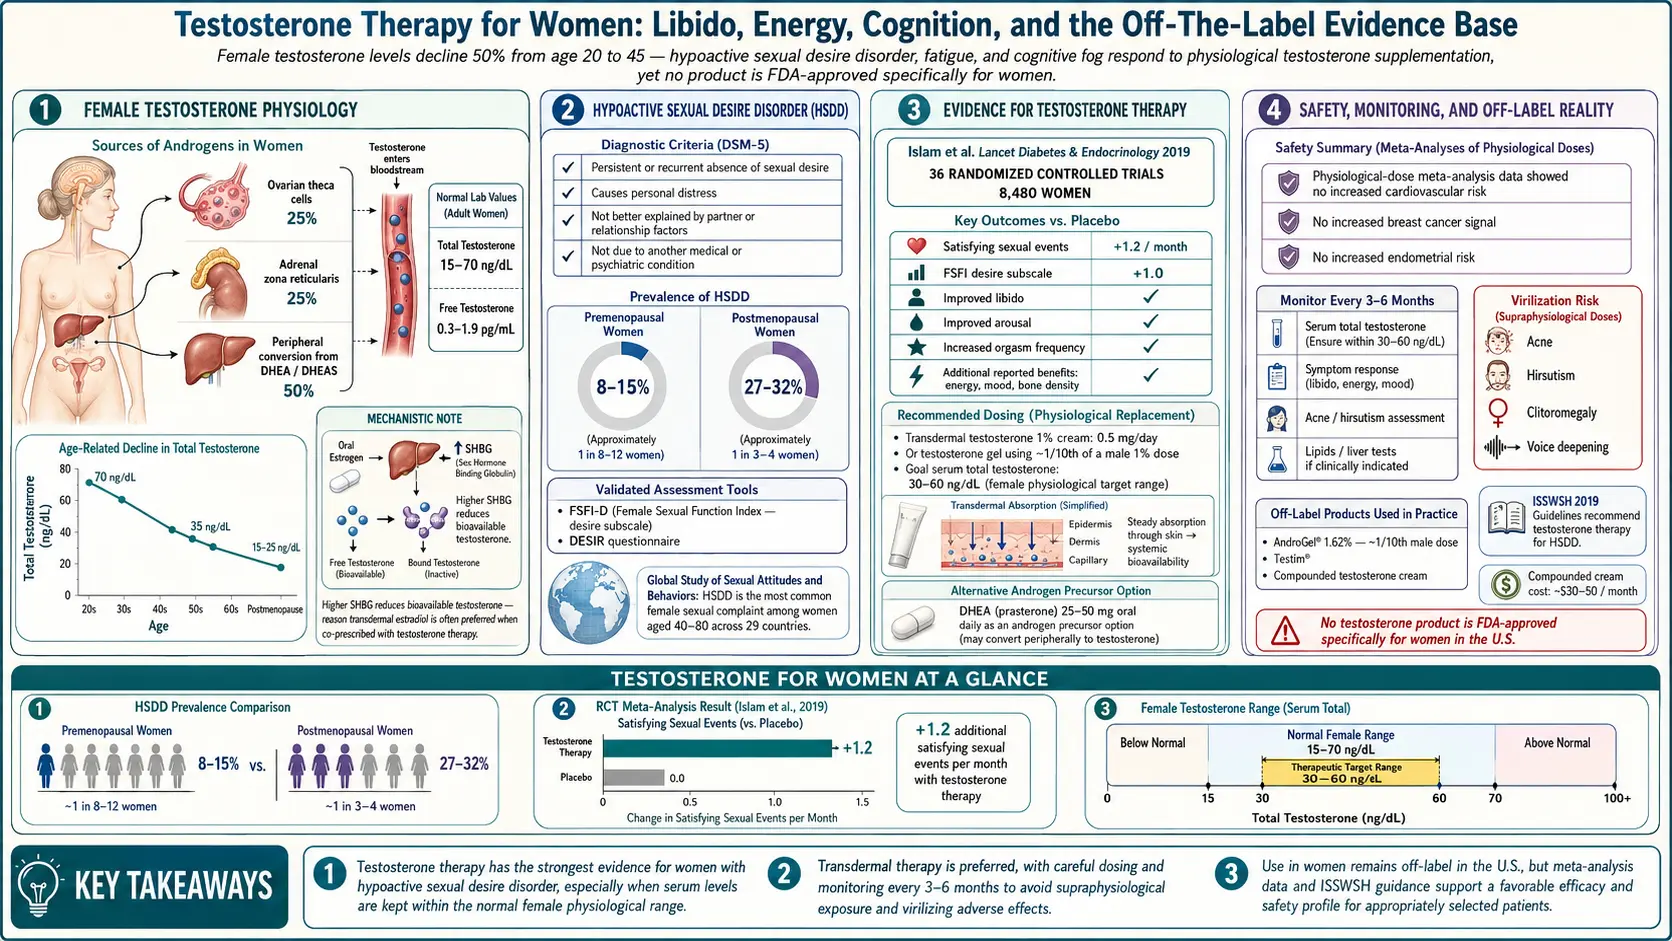
Testosterone is usually framed as a male hormone, but women make it too — and they need it. Ovaries and adrenal glands produce small amounts throughout a woman's life, and circulating total testosterone sits in a range roughly one-tenth of a man's. That small amount powers libido, energy, muscle maintenance, bone density, and mood stability. Between the ages of 20 and 40, a woman's circulating androgen levels fall by about 50%, driven mostly by declining adrenal DHEA production. Natural menopause drops levels further, and surgical removal of both ovaries (bilateral oophorectomy) cuts testosterone roughly in half overnight.
When symptoms of low testosterone become disruptive — most consistently, a distressing loss of sexual desire — carefully dosed testosterone replacement can help. The current evidence base, summarized in the 2019 Global Consensus Position Statement, supports one indication only: Hypoactive Sexual Desire Disorder (HSDD) in postmenopausal women. Use for energy, mood, muscle tone, and cognition is common in practice but rests on thinner evidence and requires honest informed consent.
This article walks through who is actually a candidate, what products clinicians prescribe (and why there is still no U.S. Food and Drug Administration-approved female testosterone product in the U.S.), what doses the trials and guidelines describe, what is monitored, and what the guidelines say about delivery forms — particularly compounded pellets.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- Why Female Testosterone Matters
- No Testosterone Product Is FDA-Approved for Women in the U.S.: HSDD Is the One Evidence-Based Use
- Off-Label Use for Energy, Mood, and Muscle
- Products and Dosing — The U.S. Workaround
- What the Guidelines and Reports Say About Compounded Pellets
- Monitoring: Labs, Schedule, and Targets
- Side Effects and Red Flags
- Why DHEA Is Not a Reliable Substitute
- Regulatory History: The Women’s Testosterone Patch and the Pellet Lawsuits
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
Why Female Testosterone Matters
A healthy young woman's total testosterone usually runs 20–70 ng/dL, with free testosterone around 0.3–1.9 pg/mL. About half comes from the ovaries (both direct testosterone secretion and conversion from ovarian precursors) and half from the adrenal glands via DHEA and androstenedione. Unlike estrogen, which drops off a cliff at menopause, testosterone declines gradually over decades. By the time a woman reaches 40, her androgen pool is roughly half of what it was at 20.
Two events accelerate the decline:
- Natural menopause reduces ovarian output further, but postmenopausal ovaries keep producing some androgens for years. Women who enter menopause later and keep their ovaries often maintain better testosterone levels than those who do not.
- Bilateral oophorectomy (surgical removal of both ovaries) abruptly eliminates the ovarian contribution. Circulating testosterone falls by roughly 50% within days. Women who have this surgery before natural menopause often describe a profound drop in libido, energy, and sense of well-being that standard estrogen replacement does not fully fix.
Testosterone in women influences:
- Sexual desire, arousal, and orgasm frequency. The most robust clinical effect.
- Muscle mass and strength. Modest but measurable effects on lean body mass.
- Bone density. Likely contributes alongside estrogen; see Bone Loss Prevention and hormone replacement therapy (HRT).
- Mood and energy. Often reported by patients, less consistently demonstrated in trials.
- Cognition. Evidence is weak and inconsistent.
No Testosterone Product Is FDA-Approved for Women in the U.S.: HSDD Is the One Evidence-Based Use
The Global Consensus Position Statement on the use of testosterone therapy for women, published in 2019 and endorsed by eleven major menopause and endocrine societies worldwide, concluded that the only evidence-based indication is Hypoactive Sexual Desire Disorder (HSDD) in postmenopausal women.
HSDD is a clinical diagnosis with three components:
- Persistent or recurrent absence of sexual thoughts, fantasies, or desire for sexual activity.
- The change causes personal distress or relationship strain. (Low desire without distress is not a disorder.)
- Other causes — depression, relationship conflict, medications (especially selective serotonin reuptake inhibitors (SSRIs)), untreated thyroid or estrogen deficiency, pelvic pain, genitourinary syndrome of menopause — have been considered and addressed.
That last point matters. The consensus statement says that other factors contributing to female sexual dysfunction must be identified and addressed before testosterone therapy is started. In practice this means estrogen deficiency and vaginal dryness are treated first (see GSM and Vaginal Estrogen), antidepressants that blunt libido are reviewed, and depression and relationship factors are looked for. Testosterone helps the woman whose estrogen is already optimized and whose desire is still missing.
The consensus statement explicitly does not recommend testosterone for premenopausal women, for general well-being, for cognition, or for "anti-aging." It also does not endorse blood-testosterone levels as a diagnostic criterion — HSDD is diagnosed clinically, and many women with low desire have "normal" lab values.
What the trials found. A 2019 meta-analysis pooled 36 randomised trials with 8,480 women. Compared with placebo or a comparator (such as estrogen, with or without a progestogen), testosterone raised the number of satisfying sexual events in postmenopausal women by about 0.85 per month, and improved desire, arousal, orgasm, pleasure, responsiveness and self-image while lowering sexual concerns and distress. Women on testosterone were more likely to report acne and hair growth, no serious adverse events were recorded, and an overall increase in weight was recorded. Taken by mouth, testosterone raised LDL cholesterol and lowered HDL cholesterol; given through the skin (patch or cream) it did not. No effects were reported on body composition, muscle and bone, or memory and thinking, though few women contributed data on those outcomes. The authors concluded that testosterone is effective for postmenopausal women with low sexual desire causing distress, with non-oral routes preferred.
Off-Label Use for Energy, Mood, and Muscle
In practice, many clinicians — especially in menopause-focused and "hormone optimization" clinics — prescribe testosterone for symptoms beyond HSDD: fatigue, brain fog, depressed mood, loss of muscle tone, and waning motivation. Some women describe a genuine improvement on low-dose therapy; others do not.
The honest summary of the evidence:
- Energy and mood: Randomized trials show a small average effect that barely separates from placebo. A responsive subset probably exists but is hard to predict up front.
- Muscle and body composition: At physiologic female replacement doses, lean mass gains are modest (on the order of 1–2 pounds over 6–12 months). The 2019 meta-analysis of 36 randomised trials found no effect of testosterone on body composition, though the number of women with data on it was small, and it recorded an overall increase in weight. Supraphysiologic doses produce more muscle but also virilizing side effects.
- Cognition and memory: Conflicting trial results; the 2019 meta-analysis found no effect on cognitive measures, from a small number of women.
- Bone density: The 2019 meta-analysis found no effect on musculoskeletal measures, again from a small number of women; estrogen remains the dominant driver.
Off-label prescribing is legal and common. Clinicians who prescribe it this way describe it as a trial based on biological plausibility and symptoms rather than strong trial evidence, reassessed after three to six months and stopped if there is no clear improvement.
Products and Dosing — The U.S. Workaround
There is currently no U.S. Food and Drug Administration-approved testosterone product for women in the United States. Every woman on testosterone therapy in the U.S. is using either a male product at a fraction of the male dose, or a compounded preparation made by a specialty pharmacy. Australia has an approved testosterone 1% cream formulated for women; in the U.K. a testosterone gel made for men is used off-label. The 2019 consensus statement notes that the trials behind its recommendations used approved products at doses that keep blood levels in the premenopausal range, and states: “There is an unmet need for the provision and approval of testosterone treatments specific to women.” Where no approved female product is available, it calls off-label prescribing of an approved male formulation reasonable, provided hormone levels are kept in the physiologic female range. U.S. clinicians work with three practical options:
- Compounded testosterone 1% cream, 0.5 g daily. This delivers roughly 5 mg of testosterone per day, which is the dose most closely matching the Australian women’s cream and the trial literature. Applied to the inner thigh, outer arm, or lower abdomen — rotating sites. This is the most commonly prescribed U.S. option and is the closest thing to "standard of care." The 2019 consensus panel recommended against the use of compounded testosterone: it states that compounded “bioidentical” testosterone “cannot be recommended for the treatment of HSDD because of the lack of evidence for efficacy and safety, unless an authorized equivalent preparation is not available,” and that a compounding pharmacy used in that case should meet purity and Good Manufacturing Practice standards. Cost: $30–$80/month from compounding pharmacies.
- Testosterone gel 1% made for men, tiny dose. A 1% gel delivers 10 mg per 1 g of product, so women use roughly 0.5 g (half a pump, or a pea-sized amount) daily — about one-tenth of a man's starting dose. Advantage: an approved product (approved for men), made under the same quality control as any brand drug. Disadvantage: not designed for this use, awkward measuring, insurance often denies for female patients.
- Compounded testosterone troches (lozenges) or sublingual drops. Less predictable absorption than transdermal. Practitioners describe them as a second-line option when skin reactions rule out creams.
The 2019 consensus states that use of any testosterone preparation that results in supraphysiologic concentrations (above the female range), including testosterone injections and — as detailed in the next section — testosterone pellets, is not recommended. It also states that oral testosterone is not recommended because of its adverse effects on HDL and LDL cholesterol; oral methyltestosterone also carries liver-toxicity concerns.
A starting protocol many U.S. practitioners describe. Compounded 1% testosterone cream, 0.5 g applied to the inner thigh every morning (the consensus position on compounded products is given above). Baseline labs first (total testosterone, free testosterone, SHBG, CBC, lipid panel). Recheck testosterone levels at 3–6 weeks to confirm the dose is in range, then every 6 months. Reassess symptoms at 3 months — if there is no meaningful improvement in libido (for HSDD) or energy/well-being (off-label) by 6 months, these practitioners describe tapering and stopping.
What the Guidelines and Reports Say About Compounded Pellets
Testosterone pellets — small crystalline implants inserted under the skin of the hip or buttock every 3–4 months — are heavily marketed in the U.S. They are convenient (no daily routine), and each insertion is a separately billed clinic procedure, often paid in cash.
The problems are real:
- Non-physiologic peaks. Pellets deliver a high initial surge that can push testosterone well above the female reference range for weeks. Supraphysiologic levels cause the side effects discussed below and are associated with higher discontinuation rates.
- No off-switch. If a woman develops acne, scalp hair loss, voice changes, or clitoral enlargement, the pellet cannot be removed easily. She has to wait months for the hormone to wear off. A cream can be stopped the same day.
- Unregulated compounding. Pellet dosing varies from pharmacy to pharmacy. Studies of commercial pellet products have documented wide variation in actual hormone content versus label claims.
- Higher adverse event rates. Peer-reviewed case series and U.S. Food and Drug Administration (FDA) adverse-event reports have linked pellet therapy to excess rates of acne, hirsutism, voice deepening, and alopecia compared with transdermal preparations.
- Insertion-site complications. Infection, pellet extrusion, and scarring.
The 2019 Global Consensus Position Statement — endorsed by the Endocrine Society, The North American Menopause Society (now The Menopause Society) and nine other societies — states that use of any testosterone preparation that results in supraphysiologic concentrations, “including pellets and injections, is not recommended.”
Monitoring: Labs, Schedule, and Targets
Testosterone therapy is not "set and forget." The goal is to bring levels into the upper quartile of the normal female range — roughly a total testosterone of 50–70 ng/dL for most assays — and to stay there. The 2019 consensus states that dosing should be limited to achieving testosterone levels in the physiologic premenopausal range. It describes measuring a baseline total testosterone before starting, a repeat level 3–6 weeks after starting, and a total testosterone every 6 months to screen for overuse, along with checks for signs of androgen excess. It also states that a blood total testosterone level should not be used to diagnose HSDD.
Baseline labs (before starting):
- Total testosterone (ideally by LC-MS/MS for accuracy at low female levels)
- Free testosterone (calculated or direct)
- Sex hormone binding globulin (SHBG) — often elevated by oral estrogen, which lowers free testosterone
- Estradiol and follicle-stimulating hormone — to confirm menopausal status and estrogen adequacy
- Complete blood count (CBC) — baseline hematocrit
- Lipid panel — testosterone can nudge high-density lipoprotein (HDL) down at higher doses
- Liver enzymes — baseline only; transdermal testosterone is liver-neutral
See Lab Tests: Hormone Panel for details on how each is drawn and interpreted.
Follow-up schedule:
- 3–6 weeks after starting: Total and free testosterone. Adjust dose if needed.
- 3 months: Symptom reassessment. Honest check: is libido/energy/mood better? If nothing has changed, the therapy is not working.
- Every 6 months thereafter: Total testosterone, free testosterone, SHBG. Annual complete blood count and lipid panel.
Timing of the blood draw matters. For transdermal cream or gel, draw the lab before that day's application to catch a steady-state trough. For an AM application, a morning lab before the dose is ideal.
The oral estrogen trap. Women on oral estradiol (versus patch or gel) develop a liver-driven rise in SHBG that binds up circulating testosterone, lowering the free fraction even when total testosterone looks fine. For a woman taking oral estrogen who still has low libido, practitioners describe switching to a transdermal estrogen (see Estradiol Formulations) as an option tried before starting testosterone.
The 2021 guideline. The International Society for the Study of Women’s Sexual Health (ISSWSH) published a clinical practice guideline on systemic testosterone for HSDD in women in 2021, building on the 2019 consensus. It recommends systemic transdermal testosterone for women with HSDD not mainly caused by changeable factors such as relationship or mental health problems, and reports that the available research supports a moderate benefit, with no serious adverse events at physiologic doses but long-term safety not established. It states that a total testosterone level is not used to diagnose HSDD but serves as a baseline for monitoring, that government-approved transdermal male products can be used cautiously at doses suited to women, that levels are monitored to stay in the premenopausal range, and that compounded products cannot be recommended because of the lack of efficacy and safety data. It adds that limited data also support use in late-reproductive-age premenopausal women.
Side Effects and Red Flags
At true physiologic replacement doses — meaning blood levels stay within the normal female range — serious side effects are uncommon. Problems generally appear when dosing drifts above the female range, as with pellets or overly enthusiastic cream dosing.
Common and mostly dose-dependent:
- Acne. Often the first signal of too much testosterone. Appears on the chin, jawline, and back. Reversible with dose reduction.
- Increased facial and body hair. Thickening of existing hair on the chin, upper lip, and abdomen. Usually mild at physiologic doses; more marked with pellets.
- Oily skin and scalp.
- Mild fluid retention.
Uncommon but important — signs of too much testosterone:
- Voice deepening or hoarseness. This can be permanent even after stopping therapy. It is the single most feared side effect and one of the strongest arguments against pellet dosing.
- Clitoromegaly (clitoral enlargement). Also potentially permanent if dosing stays supraphysiologic for long enough.
- Scalp hair thinning (androgenic pattern). Thinning at the crown and temples.
- Mood irritability, aggression.
What the consensus reports on side effects. The 2019 consensus states that at doses that keep blood levels in the premenopausal range, testosterone is linked to mild increases in acne and body or facial hair growth in some women, “but not with alopecia, clitoromegaly, or voice change.” Oral testosterone worsened HDL and LDL cholesterol, while non-oral forms showed no statistically significant effect on cholesterol over the short term, and testosterone was not linked to higher blood pressure, blood sugar or HbA1c. Safety data for physiologic doses are not available beyond 24 months of treatment.
Breast cancer and cardiovascular outcome data on testosterone in women remain limited. The 2019 consensus states that available data suggest short-term transdermal testosterone therapy does not impact breast cancer risk, and that randomised-trial data are insufficient to assess long-term breast cancer risk. Women with a prior diagnosis of breast cancer were excluded from the randomised trials for HSDD, and the consensus advises caution with testosterone use in women with hormone-sensitive breast cancer. See hormone replacement therapy Risks for the broader hormone-therapy risk picture.
Why DHEA Is Not a Reliable Substitute
DHEA (dehydroepiandrosterone) is an adrenal steroid that the body can convert, in small amounts, into testosterone and estrogen. Because it is sold over-the-counter as a supplement, many women try it as a "natural" alternative to prescription testosterone. It mostly doesn't work, for three reasons:
- Unpredictable conversion. How much DHEA becomes testosterone depends on enzyme activity that varies widely between women. Some women convert efficiently and may see modest effects; most don't.
- Supplement quality is wildly inconsistent. Independent testing has repeatedly found commercial DHEA products containing anywhere from 0% to 150% of the labeled dose. A product whose content varies this much cannot be dosed reliably.
- Evidence in postmenopausal women with HSDD is negative. Randomized trials of oral DHEA for postmenopausal low libido have mostly failed to show benefit over placebo.
The one scenario where DHEA has solid evidence is intravaginal DHEA (prasterone vaginal insert) for genitourinary syndrome of menopause — and that is a local effect on vaginal tissue, not a systemic testosterone substitute. For systemic androgen replacement, the trials and guidelines describe prescription testosterone at a measured dose.
Regulatory History: The Women’s Testosterone Patch and the Pellet Lawsuits
A testosterone patch for women, since withdrawn, was developed by a consumer-goods manufacturer for postmenopausal HSDD, studied most famously in the 2005 trial led by James Simon and colleagues. The trial showed a statistically significant improvement in satisfying sexual events versus placebo. In 2004 the U.S. Food and Drug Administration declined to approve the patch, citing concerns about long-term cardiovascular and breast safety given the absence of extended follow-up. Europe approved it in 2006, but the product was withdrawn from the European market in 2012 for commercial reasons after slow uptake. No direct successor has been submitted for U.S. approval, leaving compounded and off-label male products as the only clinical options.
Meanwhile, the testosterone pellet industry has faced a string of lawsuits. Multiple U.S. cases have alleged patient harm from supraphysiologic testosterone levels — permanent voice changes, severe acne, hair loss, and mood disturbance — after pellet insertion at clinics. Settlements and ongoing litigation underscore the regulatory gap: compounded pellets are not U.S. Food and Drug Administration-approved, the compounding pharmacies that make them operate under lighter oversight than brand manufacturers, and the clinics inserting them often have financial incentives that tilt toward more frequent and higher-dose insertions.
The practical takeaway for patients: the absence of a U.S. Food and Drug Administration-approved female testosterone product does not mean testosterone therapy for women is unsafe. It means the delivery system matters enormously. A measured, daily, reversible, transdermal dose — monitored with labs — is a very different therapy than a 4-month pellet implant.
Key Research Papers
- Davis SR, Baber R, Panay N, Bitzer J, Perez SC, Islam RM, et al. Global Consensus Position Statement on the Use of Testosterone Therapy for Women. J Clin Endocrinol Metab. 2019;104(10):4660-4666. — PubMed PMID: 31498871
- Islam RM, Bell RJ, Green S, Page MJ, Davis SR. Safety and efficacy of testosterone for women: a systematic review and meta-analysis of randomised controlled trial data. Lancet Diabetes Endocrinol. 2019;7(10):754-766. — PubMed PMID: 31353194
- Parish SJ, Simon JA, Davis SR, Giraldi A, Goldstein I, Goldstein SW, et al. International Society for the Study of Women's Sexual Health Clinical Practice Guideline for the Use of Systemic Testosterone for Hypoactive Sexual Desire Disorder in Women. J Sex Med. 2021;18(5):849-867. — PubMed PMID: 33814355
- Simon J, Braunstein G, Nachtigall L, Utian W, Katz M, Miller S, et al. Testosterone patch increases sexual activity and desire in surgically menopausal women with hypoactive sexual desire disorder. J Clin Endocrinol Metab. 2005;90(9):5226-5233. — PubMed PMID: 16014407
- Wierman ME, et al. Androgen therapy in women: a reappraisal — an Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2014. — doi:10.1210/jc.2014-2260
- Davis SR, et al. Testosterone for low libido in postmenopausal women not taking estrogen. N Engl J Med. 2008. — doi:10.1056/NEJMoa0707302
- Glaser RL, Dimitrakakis C. Reduced breast cancer incidence in women treated with subcutaneous testosterone, or testosterone with anastrozole: a prospective, observational study. Maturitas. 2013;76(4):342-349. — PubMed PMID: 24028858
PubMed Topic Searches
For current peer-reviewed work on female testosterone therapy, dosing, and safety:
- Testosterone therapy for postmenopausal HSDD
- Transdermal testosterone dosing in women
- Testosterone pellet therapy in women — adverse effects
- Testosterone therapy in women and breast cancer risk
- SHBG, oral estrogen, and free testosterone
- DHEA supplementation and postmenopausal sexual function
- Oophorectomy and androgen deficiency
- Testosterone patch trials in women
Connections
- Reproductive Medicine
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Estradiol Formulations: Patch, Gel, Oral Routes
- Hormone Replacement Therapy Risks: Breast Cancer, Clots and Stroke
- Bone Loss Prevention and Hormone Replacement Therapy
- Hormone Panel
- Genitourinary Syndrome of Menopause and Vaginal Estrogen
- Depression
- Micronized Progesterone vs Synthetic Progestins
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
- Perimenopause Symptom Tracker and Hormonal Testing
- Perimenopause
- Menopause and Hormone Replacement Therapy
- Testosterone
- DHEA-S
- Acne
- Lipid Panel
- Insomnia
- Cardiovascular Disease