Bisphosphonates — Alendronate, Risedronate, Zoledronate
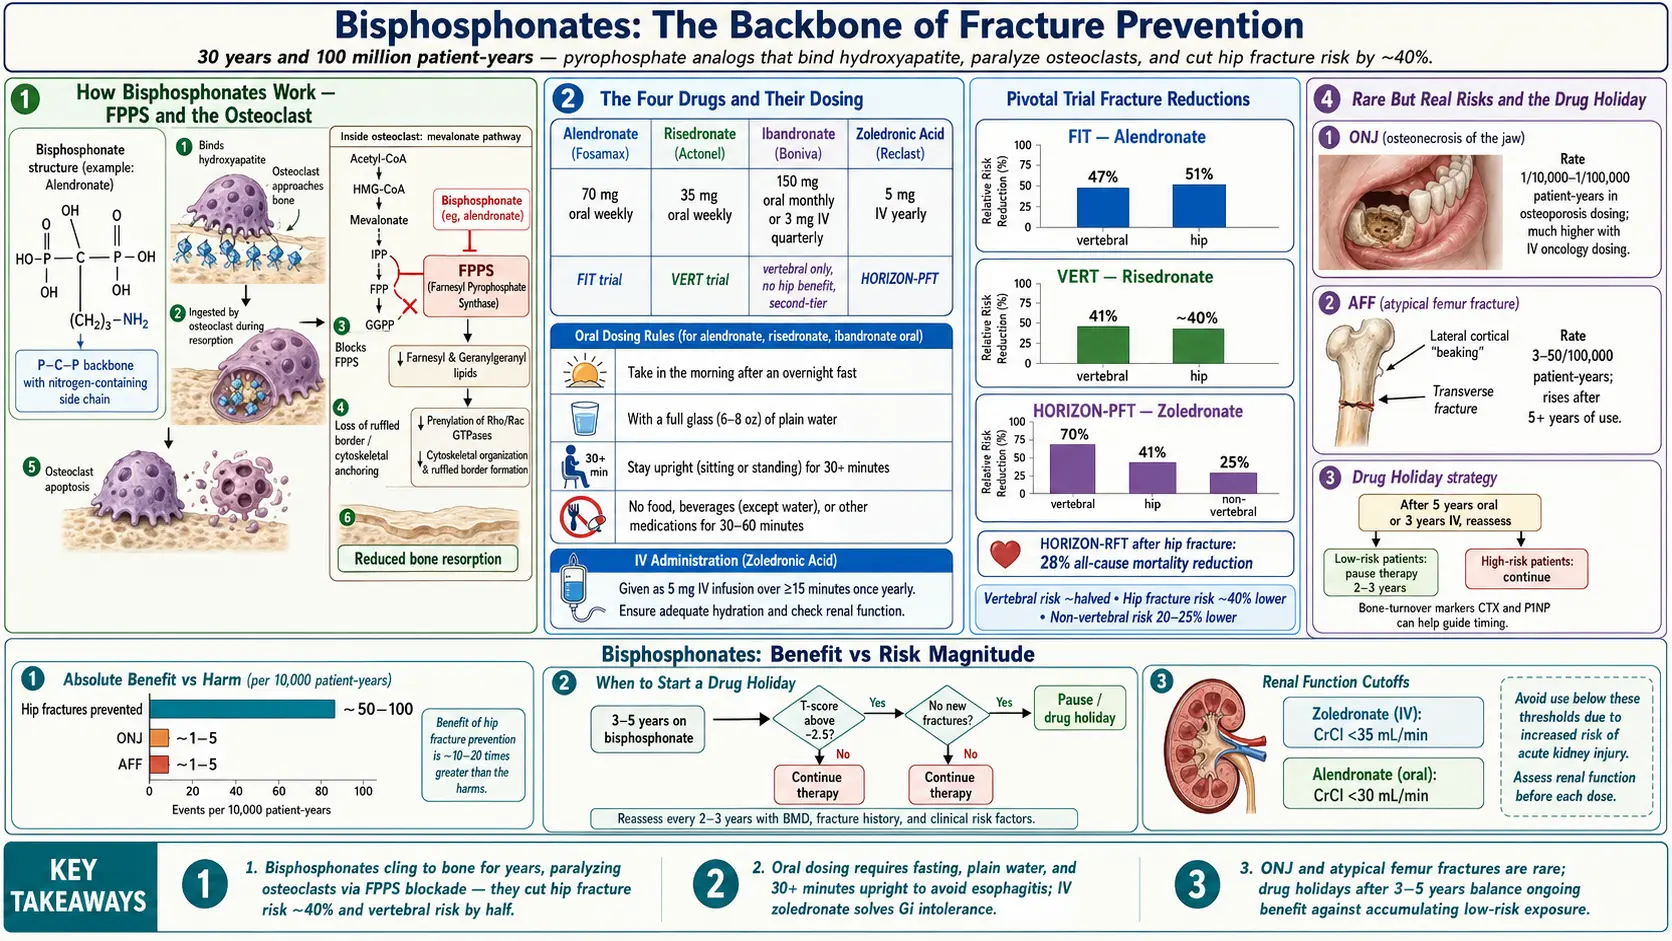
Table of Contents
- The Short Version
- How Bisphosphonates Work
- The Drugs in the Class
- The Pivotal Trials — What the Evidence Actually Shows
- Who the Guidelines Name for Treatment
- Oral Dosing Rules — Why They Matter
- Intravenous Zoledronic Acid — What to Expect
- Gastrointestinal Side Effects — Alendronate and Risedronate
- Acute-Phase Reaction with Intravenous Dosing
- Osteonecrosis of the Jaw (ONJ)
- Atypical Femur Fracture (AFF)
- The Drug Holiday — When to Stop and Restart
- Renal Dosing and Hypocalcemia
- Cost, Coverage, and Practical Logistics
- Questions Worth Raising With a Clinician
- Key Research Papers
- Connections
- Featured Videos
The Short Version
Bisphosphonates are the most prescribed, most studied, and cheapest class of osteoporosis drugs in the world. They have been on the market since 1995 (alendronate was the first), and more than a hundred million patient-years of follow-up now sit behind them. Used correctly, they cut the risk of a spine fracture roughly in half and the risk of a hip fracture by about 40%. They cost pennies a day as generics. They are the backbone of fracture prevention for most postmenopausal women and older men with osteoporosis.
They are also the drug class patients are most afraid of — because of two rare but real complications (jaw osteonecrosis, atypical femur fracture) that get splashed across news headlines whenever a lawsuit is filed. The goal of this page is to put the numbers side by side: the fractures these drugs prevent versus the complications they can cause, the dosing rules that separate patients who tolerate them from patients who hate them, and the strategy — called a "drug holiday" — that modern specialists use to capture the benefit without stacking up the long-term risk.
How Bisphosphonates Work
Your skeleton is not static. Specialized cells called osteoclasts chew away old bone. Other cells called osteoblasts lay down new bone in the crater behind them. In a healthy adult, the two crews are roughly balanced. After menopause (when estrogen drops) or with aging, the osteoclasts get louder and the osteoblasts fall behind. Bone mass drops roughly 1–2% a year. Given enough time, a spine vertebra or a hip neck becomes thin enough that a modest fall — or just bending to pick up a grocery bag — cracks it.
Bisphosphonates interrupt the osteoclast side of that equation. Structurally they are chemical cousins of pyrophosphate, a naturally occurring molecule that latches onto the hydroxyapatite mineral crystals that form bone. Because of that affinity, a bisphosphonate swallowed or infused today will cling to the inside surface of your bones for years. When an osteoclast arrives to dissolve that patch of bone, it swallows the drug along with the mineral.
Inside the osteoclast, the nitrogen-containing bisphosphonates (alendronate, risedronate, ibandronate, zoledronate) block an enzyme called farnesyl pyrophosphate synthase (FPPS). FPPS sits in the mevalonate pathway — the same pathway that statins interrupt higher up. Blocking it starves the osteoclast of the geranylgeranyl and farnesyl lipids it needs to anchor its cell-internal scaffolding (the "ruffled border" that dissolves bone, and small GTPase signaling proteins like Rho and Rac). Without those anchors, the osteoclast cannot do its job. It becomes functionally paralyzed and eventually dies by apoptosis.
The net effect: bone resorption slows dramatically, formation catches up, and measured bone density rises 4–8% over three years at the spine. More importantly, the fracture risk falls within the first 6–12 months of treatment — faster than you might expect given how slowly density changes — because the drug also seems to repair the microarchitecture and reduce the kind of microscopic stress cracks that precede a full fracture.
The Drugs in the Class
Four bisphosphonates are U.S. Food and Drug Administration-approved for osteoporosis. A fifth (pamidronate) is used for Paget's disease and cancer-related bone problems but not first-line osteoporosis.
- Alendronate. Oral tablet, 70 mg once weekly. The most prescribed osteoporosis drug in the world. Sold as a generic. Pivotal trial: FIT.
- Risedronate (immediate-release and delayed-release forms). Oral tablet, 35 mg once weekly (also 150 mg monthly, and a delayed-release version that can be taken with food). Generic. Slightly easier on the stomach than alendronate for some patients. Pivotal trial: VERT.
- Ibandronate. Oral 150 mg monthly or intravenous (IV) 3 mg every 3 months. Convenient dosing, but the evidence base is weaker: ibandronate clearly reduces vertebral fractures but has never convincingly shown a hip-fracture benefit. Many specialists consider it a second-tier choice.
- Zoledronic acid (5 mg yearly for osteoporosis; the same drug is given at 4 mg in cancer care). Intravenous infusion, 5 mg once yearly over 15–30 minutes. The most potent of the four, and the only option if you cannot tolerate oral dosing or have chronic gastrointestinal (GI) disease. Pivotal trial: HORIZON-PFT.
For most new patients, the practical choice is between oral alendronate or risedronate (cheap, self-administered) and intravenous zoledronate (annual infusion, supervised). There is no good head-to-head evidence that one is meaningfully more effective than the others at preventing fractures — the choice comes down to tolerance, convenience, and cost.
The Pivotal Trials — What the Evidence Actually Shows
Three randomized controlled trials established the modern fracture-prevention numbers that every later guideline is built on.
FIT — Alendronate
The Fracture Intervention Trial (Black et al., 1996 and Cummings et al., 1998) randomized about 6,500 postmenopausal women with low femoral-neck bone density to alendronate or placebo for three to four years. In the arm with established vertebral fractures at baseline, alendronate cut the risk of a new vertebral fracture by 47% and cut hip fractures by 51%. In the arm without prior vertebral fractures, vertebral fractures fell by about 44% but the absolute numbers were small.
VERT — Risedronate
The Vertebral Efficacy with Risedronate Therapy trials (Harris et al., 1999; Reginster et al., 2000) enrolled women with at least one prior vertebral fracture. In the North American trial alone (Harris et al., 1999), 2,458 women were randomized; over three years, risedronate 5 mg a day reduced new vertebral fractures by 41% (11.3% vs 16.3%) and non-vertebral fractures by 39% (5.2% vs 8.4%). A separate hip-fracture trial (HIP, McClung 2001) showed about a 40% hip-fracture reduction in women selected for low hip bone density.
HORIZON-PFT — Zoledronic Acid
The Health Outcomes and Reduced Incidence with Zoledronic Acid Once Yearly Pivotal Fracture Trial (Black et al., N Engl J Med, 2007) randomized 7,765 postmenopausal women with osteoporosis to a 15-minute 5 mg infusion once a year versus placebo for three years. Vertebral fractures fell by 70%, hip fractures by 41%, and all non-vertebral fractures by 25%. Serious atrial fibrillation (an irregular heartbeat) occurred more often with zoledronic acid: in 50 women versus 20 on placebo (P<0.001). A companion trial (HORIZON-RFT, Lyles et al., 2007) in patients who had just had a hip fracture repaired showed a 35% reduction in new clinical fractures and a 28% reduction in all-cause mortality — the only osteoporosis trial to show a clear survival benefit.
Zoledronate in Older Women with Osteopenia
A six-year New Zealand trial (Reid et al., N Engl J Med, 2018) tested zoledronate in 2,000 women aged 65 or older with osteopenia — bone density below normal but not in the osteoporosis range (T-score −1.0 to −2.5). The women received four 5 mg infusions 18 months apart, or saline. A fragility fracture occurred in 122 women on zoledronate and 190 on placebo (hazard ratio 0.63); 15 women needed to be treated to prevent a fracture in one woman. Vertebral fractures were also lower (odds ratio 0.45).
The headline numbers to keep in mind: bisphosphonates cut vertebral fracture risk roughly in half, hip fracture risk by about 40%, and non-vertebral fracture risk by about 20–25%. That is a big effect size for a cheap generic medicine.
Who the Guidelines Name for Treatment
The American College of Physicians (ACP) 2023 living guideline (Qaseem et al., 2023) makes these recommendations:
- Bisphosphonates first for postmenopausal women diagnosed with osteoporosis (strong recommendation, high-certainty evidence), and for men diagnosed with osteoporosis (conditional recommendation, low-certainty evidence).
- Denosumab second, for people who have contraindications to bisphosphonates or side effects from them (conditional recommendation).
- Romosozumab or teriparatide, followed by a bisphosphonate, only for women with osteoporosis at very high risk of fracture (conditional recommendation).
- An “individualized approach” on whether to start a bisphosphonate in women over 65 with low bone mass (osteopenia) (conditional recommendation, low-certainty evidence).
Treatment criteria used in other U.S. guidance (not part of the ACP recommendations) include:
- A DEXA T-score of −2.5 or lower at the spine, total hip, or femoral neck.
- A history of a fragility fracture (hip or vertebra) regardless of T-score.
- A T-score between −1.0 and −2.5 (osteopenia) plus a FRAX 10-year major-fracture risk of 20% or higher, or a 10-year hip-fracture risk of 3% or higher. See the FRAX article for how to run your own numbers.
- Certain high-risk situations regardless of baseline T-score: long-term glucocorticoid therapy (prednisone 7.5 mg/day or more for three months or longer), aromatase-inhibitor treatment for breast cancer, androgen-deprivation therapy for prostate cancer.
Low blood calcium has to be corrected before treatment starts (the alendronate and zoledronic acid labels both list hypocalcemia as a contraindication), and the zoledronic acid label calls for a creatinine (kidney function) test before every dose. Clinicians also commonly check 25-OH vitamin D, and often thyroid-stimulating hormone (TSH) and a celiac screen, to catch common secondary causes of bone loss. A baseline DEXA scan is used for tracking.
Oral Dosing Rules — Why They Matter
Oral bisphosphonates are notoriously poorly absorbed. Less than 1% of a swallowed dose ever makes it into the bloodstream, and any food, coffee, tea, mineral water, calcium, iron, or juice taken nearby will knock absorption to essentially zero. The label’s standard rules exist for exactly that reason:
- First thing in the morning, on an empty stomach. No food, no coffee, no vitamin, no other pill for at least an hour beforehand.
- The tablet is swallowed whole with a full 6–8 oz glass of plain water. Not bottled mineral water (the dissolved calcium and magnesium bind the drug). Not coffee, tea, or juice.
- The person stays fully upright — sitting, standing, or walking — for at least 30 minutes. The alendronate label says not to lie down for at least 30 minutes and until after the first food of the day.
- Food, any other drink and other medicines wait 30 minutes (60 for ibandronate).
Why so strict? Bisphosphonates are caustic to the lining of the esophagus. If a tablet sticks on the way down — which happens disturbingly often when people take it with a sip of water and lie back in bed — it can cause a chemical burn, an ulcer, or in rare cases an esophageal stricture. The 30-minute upright rule gives the tablet time to clear into the stomach, where the acidic environment neutralizes the contact risk.
A routine people describe: a fixed weekly day tied to an existing ritual — on Saturday morning, the water, a kitchen timer set for 30 minutes, then coffee. Patients who skip the rules almost always end up with either bad heartburn (and quit the drug) or no benefit (because they took it with coffee and never absorbed it).
Intravenous Zoledronic Acid — What to Expect
Zoledronate bypasses the stomach entirely. The infusion is a once-a-year event, usually done in a rheumatologist's or oncologist's office, a hospital infusion suite, or — increasingly — a primary care office. Total chair time is about 45 minutes: intravenous line placement, 15–30 minutes of drip, a brief observation period, and out.
What the zoledronic acid label and the jaw-osteonecrosis consensus describe before the first infusion:
- Fluids. The label says patients must be well hydrated before the infusion, and its patient information lists drinking at least 2 glasses of fluid, such as water, within a few hours before it, to reduce the risk of kidney problems.
- Normal calcium. The label says low blood calcium must be treated before the drug is given. A 25-OH vitamin D below 30 ng/mL is commonly corrected first.
- Acetaminophen. The label says acetaminophen given after the infusion may reduce the flu-like acute-phase symptoms (see below).
- Dental work. The 2015 international consensus lists treating or stabilizing mouth disease before starting as a prevention step, so planned extractions or implants are usually done before starting.
Zoledronate is the go-to if you cannot tolerate oral dosing, have severe reflux or a history of esophageal disease, have problems with adherence (skipping doses), or simply prefer "once a year and done." Efficacy is at least as good as oral alendronate — arguably better for vertebral fracture reduction.
In the HORIZON pivotal trial, serious atrial fibrillation (an irregular heartbeat) was reported in 50 women on zoledronic acid versus 20 on placebo (P<0.001). The later trial in people who had just had a hip fracture repaired (HORIZON-RFT, Lyles et al., 2007) found similar rates of atrial fibrillation and stroke in both groups.
Gastrointestinal Side Effects — Alendronate and Risedronate
The most common reason people abandon oral bisphosphonates is upper-GI irritation: heartburn, acid regurgitation, mid-chest burning after swallowing the pill, nausea, or a vague dull discomfort behind the breastbone. Real population-based studies put the incidence of meaningful gastrointestinal symptoms around 10–20% in the first year, though in randomized trials the rate is much closer to placebo because enrollees were pre-screened for pill tolerance.
Approaches described for people with stomach symptoms:
- Checking that all four dosing rules are being followed.
- Delayed-release risedronate, which is designed to bypass the esophagus and release in the small intestine; it can be taken immediately after breakfast.
- A change from alendronate to immediate-release risedronate — some patients tolerate one and not the other despite identical mechanism.
- Intravenous zoledronate when symptoms persist.
Serious esophagitis, esophageal ulcer, or stricture happens in fewer than 1 in 1,000 treated patients, almost always in people who did not follow the dosing rules or who had pre-existing reflux or esophageal motility problems. The alendronate label lists abnormalities of the esophagus that delay emptying, such as stricture or achalasia, as contraindications, and calls for caution in people with active upper gastrointestinal problems such as known Barrett's esophagus, trouble swallowing, other esophageal disease, gastritis or ulcers.
Acute-Phase Reaction with Intravenous Dosing
About one in three first-time zoledronate recipients develops what feels like a 24-to-72-hour flu: low-grade fever, muscle aches, bone aches (sometimes quite severe), headache, fatigue. This is the acute-phase reaction and it is a real pharmacological effect, not an allergy. Nitrogen-containing bisphosphonates trigger a burst of interleukin-6 and gamma-delta T-cell activation — the same inflammatory signaling that makes a flu infection feel terrible.
In the main trial on the zoledronic acid label, fever was reported in 18% of patients after the infusion, muscle aches in 9%, flu-like symptoms in 8%, headache in 7% and joint pain in 7%. Most symptoms began within the first 3 days and usually resolved within 3 days of onset, but could take up to 7–14 days; they became less common with later doses. In a second trial, where patients were given acetaminophen at the time of the infusion and for the next 72 hours as needed, fever was reported in 7% and joint pain in 3%. Measures described for blunting it:
- Acetaminophen: the label says acetaminophen after the infusion may reduce the incidence of these symptoms.
- Plenty of fluids.
- Scheduling the infusion late in the week, so the flu-like days fall on the weekend, is a practical step people describe.
A handful of patients have an acute-phase reaction bad enough that they refuse a second infusion. For those patients, oral alendronate or denosumab (see the denosumab article) are the alternatives used.
Osteonecrosis of the Jaw (ONJ)
ONJ is the complication patients fear most because of the lawsuit advertising. Here are the honest numbers.
ONJ is a patch of exposed jaw bone that will not heal, usually in the lower jaw, usually after a tooth extraction or implant placement. In cancer patients receiving high-dose monthly intravenous bisphosphonates (zoledronate at 4 mg every 3–4 weeks for bone metastases), the 2015 international consensus (Khan et al.) puts the incidence at 1–15%. In osteoporosis patients on standard doses (weekly oral or yearly intravenous), the incidence is orders of magnitude lower: most studies put it between 1 in 10,000 and 1 in 100,000 patient-years. The same consensus estimates 0.001% to 0.01% in osteoporosis patients, only marginally higher than in the general population (under 0.001%). Other risk factors it lists include glucocorticoid use, jaw bone surgery, poor oral hygiene, chronic inflammation, diabetes, ill-fitting dentures and anti-angiogenic cancer drugs.
To put that in context: the lifetime risk of a hip fracture after age 65 without treatment is roughly 1 in 6 for a woman and 1 in 20 for a man. Hip fractures kill about 20% of people who sustain them within a year. Those are the two numbers set against each other when the drug is weighed.
Prevention steps in the 2015 consensus and in common dental practice:
- A dental check before starting a bisphosphonate, with any extractions, implants, periodontal surgery, or deep cleaning done first.
- Good oral hygiene — brushing twice daily, flossing, twice-yearly cleanings.
- When a tooth extraction is needed during therapy, the dentist and oral surgeon are told about the drug. Most will proceed — routine extractions on osteoporosis-dose bisphosphonate patients almost always heal normally. Some will ask for a short drug hold around the procedure, though the evidence that this helps is thin.
- Exposed bone, a non-healing socket, or unexplained jaw pain are the warning signs of ONJ.
Atypical Femur Fracture (AFF)
AFF is a transverse or short-oblique fracture of the femoral shaft (the middle of the thighbone), not the usual hip-neck spot. It is distinct from ordinary hip fractures: it is almost always preceded by weeks or months of a dull, aching pain in the thigh or groin, often bilateral, worse with weight-bearing. On X-ray there is a characteristic thickening of the lateral femoral cortex (the outside edge of the bone) called "beaking."
With bisphosphonate treatment the risk climbs with duration of exposure. A study of 1,835,116 people over 45 in one California health system (Dell et al., 2012) found 142 atypical femur fractures, 128 of them in people who had taken a bisphosphonate. The rate was about 1.8 per 100,000 per year with 0.1–1.9 years of use, rising to 113 per 100,000 per year with 8–9.9 years of use. The absolute risk is still small, but the curve bends sharply upward after roughly the 5-year mark. That single fact is what drives the modern "drug holiday" strategy.
A larger 2020 study of 196,129 women aged 50 or older taking bisphosphonates in the same health system (Black et al., 2020) found 277 atypical femur fractures. Compared with less than 3 months of use, the risk was about 9 times higher (hazard ratio 8.86) at 3 to 5 years and about 44 times higher (hazard ratio 43.51) at 8 years or more, and it fell rapidly after the drug was stopped. Asian women had a higher risk than White women (hazard ratio 4.84). In the authors’ model, after 3 years of use 149 hip fractures were prevented while 2 bisphosphonate-associated atypical fractures occurred among White women, compared with 91 prevented and 8 atypical fractures among Asian women.
New thigh or groin pain while on a bisphosphonate is the warning sign of this fracture. A femur X-ray (or, for better sensitivity, magnetic resonance imaging (MRI) of both thighbones) is how a stress reaction is found. Catching a stress reaction before it propagates into a completed fracture is the whole point of surveillance.
The Drug Holiday — When to Stop and Restart
Because bisphosphonate molecules persist in bone for years after the last dose, the anti-fracture effect does not simply vanish when you stop the drug. Modern practice takes advantage of that residual effect to cap total exposure and reduce the long-term AFF and ONJ risk.
The rough algorithm (based on ASBMR 2016 guidance and American College of Physicians 2023 update):
- Reassess at 5 years for oral bisphosphonates (alendronate, risedronate), or at 3 years for intravenous zoledronate.
- At that point, check DEXA, run FRAX, and review fracture history.
- Low to moderate risk (T-score above −2.5, no new fractures on treatment, FRAX below intervention thresholds): stop for 2–5 years, rescan every 1–2 years, and restart if bone density drops or a fracture occurs.
- High risk (T-score still −2.5 or lower, prior hip or vertebral fracture, ongoing glucocorticoids, or new fractures on therapy): continue for up to 10 years oral or 6 years intravenous, then reassess. Some of these patients will be switched to a different class (denosumab, teriparatide, or romosozumab) rather than held on bisphosphonates indefinitely.
A drug holiday is not permanent. The AFF risk falls back toward baseline within about a year of stopping, but fracture-prevention benefit also fades over 2–5 years. Your clinician is balancing those two curves. The worst outcome is patients who "just stop" on their own and never get rescanned, then show up five years later with a new vertebral fracture.
Renal Dosing and Hypocalcemia
Bisphosphonates are cleared by the kidneys. When kidney function falls, the drug sticks around longer and its effect on bone and on blood calcium intensifies. Standard cutoffs, as the alendronate and zoledronic acid labels give them — by creatinine clearance (worked out from a blood creatinine test with the Cockcroft-Gault formula), not by estimated glomerular filtration rate (eGFR):
- Zoledronic acid: the label calls for creatinine clearance to be calculated, from actual body weight, before every dose. The drug is contraindicated when creatinine clearance is below 35 mL/min or there is evidence of acute kidney injury. No dose change is made at 35 mL/min or above.
- Alendronate: the label says it is not recommended when creatinine clearance is below 35 mL/min, because of lack of experience with it in kidney failure. No dose change is needed between 35 and 60 mL/min.
- Below these cut-offs: denosumab is the usual alternative since it is cleared by the reticuloendothelial system rather than the kidney — but it carries its own hypocalcemia risk in advanced chronic kidney disease (CKD), which is why nephrologists usually supervise it.
Before any bisphosphonate dose, serum calcium has to be in range — both labels list low blood calcium (hypocalcemia) as a contraindication — and 25-OH vitamin D is usually checked too. Treating a hypocalcemic patient with a bisphosphonate can drop the calcium further into a symptomatic range (tingling, cramps, tetany, seizures). The standard pre-treatment baseline is calcium 8.5–10.2 mg/dL and 25-OH vitamin D of at least 30 ng/mL. Intakes commonly cited for people on therapy are 1,200 mg of calcium and 800–1,000 international units (IU) of vitamin D daily, mostly from food. See the calcium and vitamin D article for food sources and supplement strategy, or the calcium mineral page for background.
Cost, Coverage, and Practical Logistics
Alendronate and risedronate are sold as generics.
Zoledronate infusion is covered under Medicare Part B (not Part D) as a physician-administered drug. Total charge to the patient after Medicare is typically $0–$150 depending on supplemental coverage. Commercial insurance usually covers it with prior authorization, which your prescriber's office handles.
Two logistic problems come up often: (1) lab work (calcium, vitamin D, creatinine) that is not recent — within 3 months for intravenous dosing — can lead the infusion center to cancel the infusion; (2) missed-infusion lapses are a common reason for breakthrough fractures, which is why people book the yearly zoledronate at the same time each year (e.g., every November).
Questions Worth Raising With a Clinician
- What is my 10-year FRAX-estimated fracture risk, and what would it be on treatment?
- Have we checked for secondary causes of osteoporosis (celiac, hyperparathyroidism, low testosterone, multiple myeloma) before committing to long-term bisphosphonate therapy?
- Is my vitamin D level at least 30 ng/mL?
- Oral versus intravenous — given my gastrointestinal history and ability to follow the dosing rules, which makes more sense?
- When should we plan a drug holiday, and what will trigger restarting?
- Do I need a pre-treatment dental visit, and do I have any planned oral surgery that should happen first?
- If I develop new thigh or groin pain, what is the plan to check for a stress reaction?
Key Research Papers
Pivotal randomized fracture trials (FIT, VERT, HORIZON-PFT, HORIZON-RFT), the FLEX long-term extension that informs drug-holiday decisions, and ASBMR / ACP / Endocrine Society task-force statements on atypical femur fractures, osteonecrosis of the jaw, and treatment duration.
- Black DM, Cummings SR, Karpf DB, et al. Randomised Trial of Effect of Alendronate on Risk of Fracture in Women with Existing Vertebral Fractures (Fracture Intervention Trial). Lancet. 1996;348(9041):1535–1541. — doi:10.1016/S0140-6736(96)07088-2
- Cummings SR, Black DM, Thompson DE, et al. Effect of Alendronate on Risk of Fracture in Women with Low Bone Density but without Vertebral Fractures (FIT II). JAMA. 1998;280(24):2077–2082. — doi:10.1001/jama.280.24.2077
- Harris ST, Watts NB, Genant HK, et al. Effects of Risedronate Treatment on Vertebral and Nonvertebral Fractures in Women with Postmenopausal Osteoporosis (VERT-NA). JAMA. 1999;282(14):1344–1352. — doi:10.1001/jama.282.14.1344
- Black DM, Delmas PD, Eastell R, et al. Once-Yearly Zoledronic Acid for Treatment of Postmenopausal Osteoporosis (HORIZON-PFT). New England Journal of Medicine. 2007;356(18):1809–1822. — doi:10.1056/NEJMoa067312
- Lyles KW, Colón-Emeric CS, Magaziner JS, et al. Zoledronic Acid and Clinical Fractures and Mortality After Hip Fracture (HORIZON-RFT). New England Journal of Medicine. 2007;357(18):1799–1809. — doi:10.1056/NEJMoa074941
- Black DM, Schwartz AV, Ensrud KE, et al. Effects of Continuing or Stopping Alendronate After 5 Years of Treatment: The Fracture Intervention Trial Long-term Extension (FLEX). JAMA. 2006;296(24):2927–2938. — doi:10.1001/jama.296.24.2927
- Black DM, Reid IR, Boonen S, et al. The Effect of 3 Versus 6 Years of Zoledronic Acid Treatment of Osteoporosis: A Randomized Extension to the HORIZON-Pivotal Fracture Trial. Journal of Bone and Mineral Research. 2012;27(2):243–254. — doi:10.1002/jbmr.1494
- Adler RA, El-Hajj Fuleihan G, Bauer DC, et al. Managing Osteoporosis in Patients on Long-Term Bisphosphonate Treatment: Report of a Task Force of the American Society for Bone and Mineral Research. Journal of Bone and Mineral Research. 2016;31(1):16–35. — doi:10.1002/jbmr.2708
- Shane E, Burr D, Abrahamsen B, et al. Atypical Subtrochanteric and Diaphyseal Femoral Fractures: Second Report of a Task Force of the American Society for Bone and Mineral Research. Journal of Bone and Mineral Research. 2014;29(1):1–23. — doi:10.1002/jbmr.1998
- Khan AA, Morrison A, Hanley DA, et al. Diagnosis and Management of Osteonecrosis of the Jaw: A Systematic Review and International Consensus. Journal of Bone and Mineral Research. 2015;30(1):3–23. — doi:10.1002/jbmr.2405
- Qaseem A, Hicks LA, Etxeandia-Ikobaltzeta I, et al. Pharmacologic Treatment of Primary Osteoporosis or Low Bone Mass to Prevent Fractures in Adults: A Living Clinical Guideline From the American College of Physicians. Annals of Internal Medicine. 2023;176(2):224–238. — doi:10.7326/M22-1034
- Eastell R, Rosen CJ, Black DM, Cheung AM, Murad MH, Shoback D. Pharmacological Management of Osteoporosis in Postmenopausal Women: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology & Metabolism. 2019;104(5):1595–1622. — doi:10.1210/jc.2019-00221
- Reid IR, Horne AM, Mihov B, et al. Fracture Prevention with Zoledronate in Older Women with Osteopenia. New England Journal of Medicine. 2018;379(25):2407–2416. — doi:10.1056/NEJMoa1808082
- Dell RM, Adams AL, Greene DF, et al. Incidence of Atypical Nontraumatic Diaphyseal Fractures of the Femur. Journal of Bone and Mineral Research. 2012;27(12):2544–2550. — doi:10.1002/jbmr.1719
- Black DM, Geiger EJ, Eastell R, et al. Atypical Femur Fracture Risk versus Fragility Fracture Prevention with Bisphosphonates. New England Journal of Medicine. 2020;383(8):743–753. — doi:10.1056/NEJMoa1916525
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Rheumatology
- Bone Remodeling & Calcium Balance — interactive animation
- Calcium
- Osteoporosis
- DEXA Scan: T-Score and Z-Score
- Denosumab, Romosozumab and Teriparatide
- Calcium, Vitamin D and Protein Intake
- FRAX Risk Assessment
- Secondary Osteoporosis Causes
- Weight-Bearing and Resistance Exercise
- Fracture Prevention and Fall Risk
- Postmenopausal Osteoporosis and Hormone Therapy
- Vitamin D3
- Vitamin K
- Magnesium
- Arthritis
- Estimated Glomerular Filtration Rate
- Hyperparathyroidism
- Bone Loss Prevention and Hormone Replacement Therapy
- Vitamin K2 and Bone Health