⚠ Evidence warning: Clinical trials or other evidence do not support the claims that vaginal estrogen treatment is remarkably safe and in most cases transforms symptoms within weeks, and that hyaluronic acid suppositories are the best of the non-hormonal options. This page keeps it as a report of what people, websites or other media say.
Genitourinary Syndrome of Menopause & Vaginal Estrogen
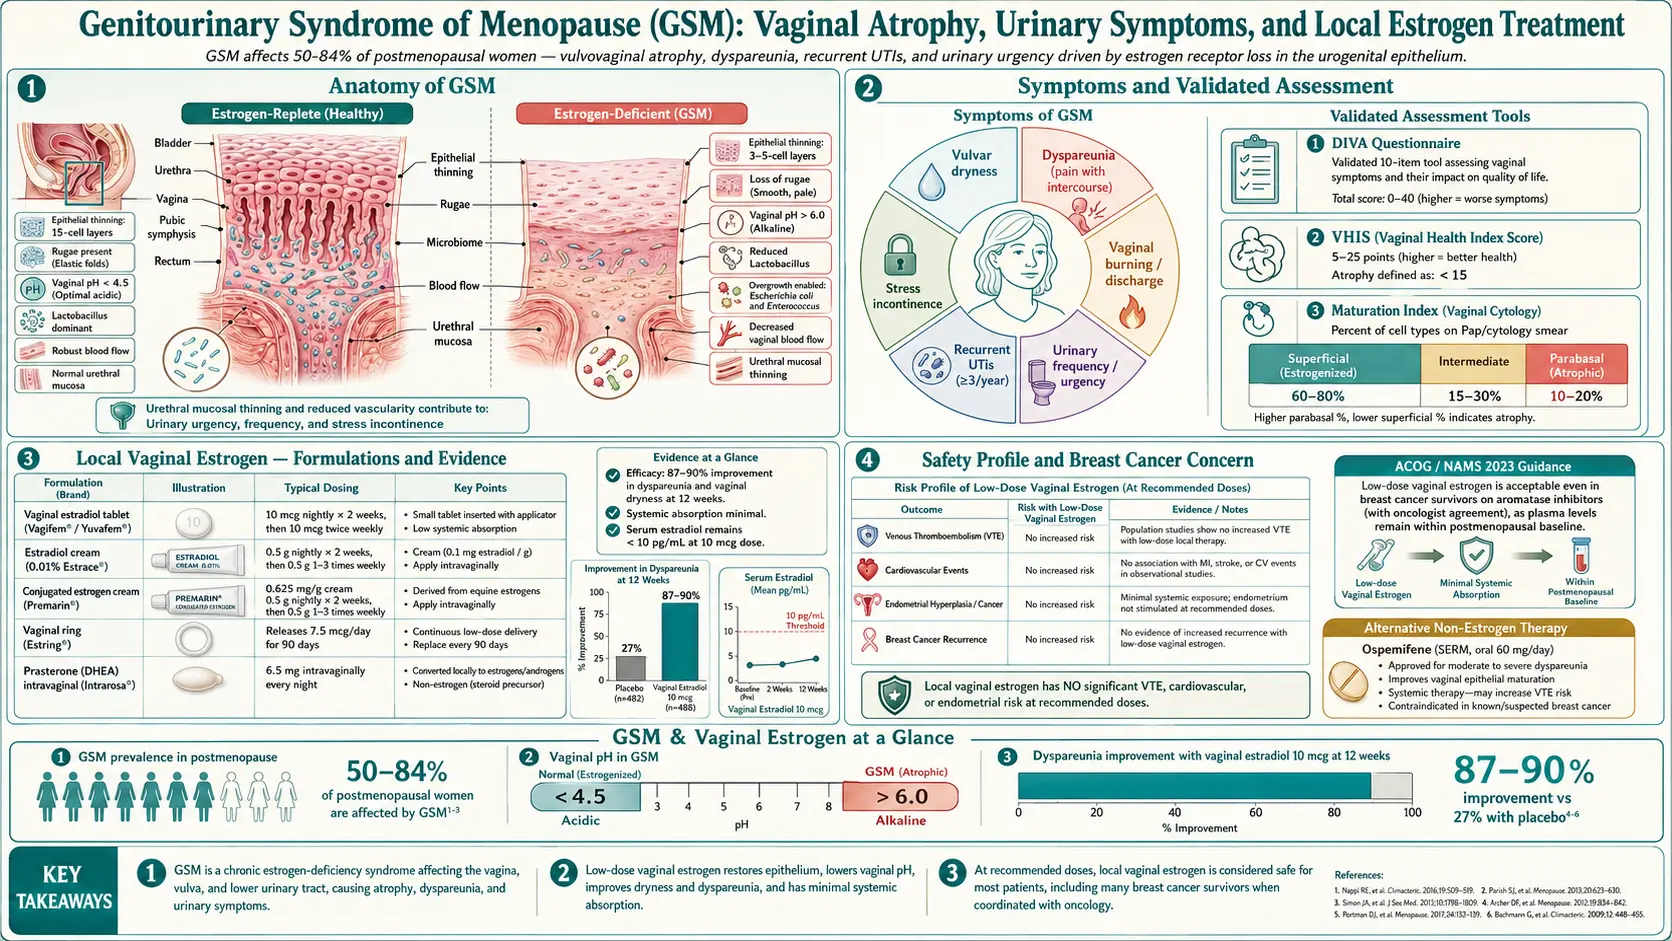
If sex hurts, if you are peeing every two hours, if you keep getting urinary tract infections (UTIs), if you feel dry and raw and nobody in medicine seems to take it seriously — this page is for you. Genitourinary Syndrome of Menopause (GSM) is the most under-treated, over-tolerated problem in women's health. It is common, it is progressive, and it is treatable. The treatment is cheap, remarkably safe, and in most cases transforms symptoms within weeks. The main prescription treatment, low-dose vaginal estrogen, is inexpensive in generic form, and a large observational study found no raised risk of breast cancer, stroke or blood clots with it — although one 12-week placebo-controlled trial found that a placebo gel eased symptoms about as much (both studies are described below). Primary care misses it constantly. This article explains what GSM is, the specific products and doses used, the cost and insurance realities, and the nuances — including the breast cancer conversation — that shape the decision.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- From "Vaginal Atrophy" to GSM — Why the Name Changed
- Prevalence and the Progressive Nature of GSM
- Symptoms — The Full List No One Tells You
- What the Exam Shows
- Vaginal Estrogen Formulations and Doses
- Non-Estrogen Prescription Options: DHEA and Ospemifene
- Safety, Breast Cancer, and the Aromatase Inhibitor Nuance
- How Long to Use It (Spoiler: Indefinitely)
- Cost, Insurance, and Ways to Get It
- Non-Hormonal Moisturizers, Lubricants, and Pelvic Floor PT
- Laser and Radiofrequency Devices — The Evidence
- Why Primary Care Keeps Missing This
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
From "Vaginal Atrophy" to GSM — Why the Name Changed
For decades the textbook term was vulvovaginal atrophy (VVA) or "atrophic vaginitis." Both names were terrible. "Atrophy" sounds like shriveling; "vaginitis" implies infection. Neither captured the urinary half of the problem, and both were embarrassing enough to make patients and doctors sidestep the conversation.
In 2014, a joint consensus conference of the International Society for the Study of Women's Sexual Health (ISSWSH) and The North American Menopause Society (NAMS) published a new umbrella term: Genitourinary Syndrome of Menopause (GSM). The name reflects biology — estrogen receptors are densely packed not just in the vagina but in the vulva, urethra, bladder trigone, and pelvic floor. When estrogen drops, all of those tissues thin, lose collagen, lose blood flow, and change pH. Calling the problem "vaginitis" hid most of it.
The shift matters practically. If you describe "burning with urination" and "having to go every hour" to your doctor, you may be sent home with antibiotics and a clean urinalysis for the fifth time. If you describe the same symptoms as GSM, a menopause-literate clinician recognizes the pattern immediately and treats the estrogen deficit, not an imaginary infection.
Prevalence and the Progressive Nature of GSM
Studies put GSM prevalence at roughly 50–80% of postmenopausal women. The range is wide because women under-report. In symptom surveys that name the specific problems (dryness, painful sex, urinary urgency), rates cluster near the top of that range.
Two critical differences from hot flashes (vasomotor symptoms, VMS):
- GSM is progressive. Without treatment, symptoms get worse over time, not better. Year five postmenopause is usually worse than year one.
- GSM does not "burn out." Hot flashes typically wane after 7–10 years (though a substantial minority of women have VMS for life). GSM does not fade with time. An 80-year-old has more atrophy than she did at 55.
Put plainly: untreated GSM usually gets worse over the years rather than better. This is the message primary care most often fails to deliver.
Symptoms — The Full List No One Tells You
GSM is not just "dryness." Patients are often relieved to see the whole picture written down:
Vulvovaginal symptoms:
- Dryness, even when aroused.
- Dyspareunia — pain with penetrative sex, ranging from a raw sandpaper sensation to sharp tearing.
- Itching or burning of the vulva, sometimes mistaken for chronic yeast infection.
- Loss of labial fullness; the labia minora may shrink or fuse.
- Narrowing and shortening of the vaginal canal.
- Spotting or bleeding after intercourse (postcoital bleeding). A first episode is checked by clinicians for other causes, but the most common reason in postmenopausal women is friable atrophic tissue.
- Reduced lubrication, loss of arousal, decreased orgasm intensity.
Urinary symptoms:
- Urgency — the sudden, can't-wait feeling.
- Frequency — voiding more than every 2 hours in the day.
- Dysuria — burning with urination, often with a sterile urine culture.
- Nocturia — waking more than once a night to pee.
- Recurrent urinary tract infections, especially the pattern of true urinary tract infections two to four times a year.
- Stress incontinence that worsens postmenopause.
Any combination of these, especially the recurrent-UTI pattern in a postmenopausal woman, is the pattern that points to GSM, which can be checked for before another round of antibiotics.
What the Exam Shows
A clinician trained to look for GSM will see a combination of:
- Pale, thin vaginal walls with loss of the normal ridges (rugae).
- Petechiae or small abrasions from minor friction.
- A vaginal pH above 5.0 (normal premenopausal is 3.5–4.5). A simple pH strip at the bedside is diagnostic.
- Shortened vaginal length, narrowed introitus.
- Labial involution.
- Urethral caruncle or prolapsed, red urethral mucosa at the meatus.
Not all of these findings are needed for a diagnosis of GSM. Symptoms alone — especially dyspareunia plus an elevated pH — are enough for clinicians to start treatment.
Vaginal Estrogen Formulations and Doses
Vaginal estrogen is the gold standard treatment. It works because it restores estrogen receptors in the exact tissue that is symptomatic, with almost no drug reaching the bloodstream. Multiple formulations exist — any of them can work, and preference is usually about delivery method and cost.
What is not known. In a 12-week trial of 302 postmenopausal women with moderate to severe symptoms (Mitchell 2018), one group used a low-dose 10 mcg estradiol vaginal tablet, one used an over-the-counter vaginal moisturizer and one used a placebo tablet plus a placebo gel. All three groups improved by about the same amount: the severity of each woman's most bothersome symptom (scored 0–3) fell by 1.4 with estradiol, 1.2 with the moisturizer and 1.3 with placebo. The authors concluded that neither the estradiol tablet nor the moisturizer gave additional benefit over the placebo tablet and gel. This leaves open how much of the relief women feel comes from the estrogen itself and how much from regularly using any lubricating gel.
Estradiol Vaginal Cream
- Dose: 0.5–1 g intravaginally. Loading phase: nightly for 2 weeks. Maintenance: 2–3 nights per week.
- Pros: Cream lets you spread a small amount on the vulva and urethra too — helpful for burning and urinary symptoms.
- Cost: Generic estradiol cream runs $50–$200 per 42.5 g tube, which lasts many weeks at maintenance doses. Discount-card services and manufacturer coupons often bring it to $30–$60.
Conjugated Estrogens Vaginal Cream
- Dose: 0.5–1 g intravaginally, same 2-week load then 2–3 times weekly.
- Note: Derived from pregnant mare urine; effective but usually more expensive than generic estradiol. Many clinicians default to estradiol vaginal cream.
Estradiol Vaginal Tablet and Estradiol Vaginal Softgel Insert
- Dose: 10 mcg tablet or insert, nightly for 2 weeks, then twice weekly.
- Pros: Pre-measured, no drip, no mess. The single most popular option for women who dislike cream.
- Cost: Brand-name estradiol vaginal tablets run $200–$350 per 24-pack; generic estradiol vaginal tablets are often $50–$120 with coupons. The estradiol vaginal softgel insert is usually brand-priced.
Low-Dose Estradiol Vaginal Ring
- Dose: One soft silicone ring inserted like a diaphragm and left in place for 90 days, then replaced.
- Pros: Absolutely the lowest-effort option — four insertions a year. Not felt during sex by most couples (and easy to remove temporarily). Excellent for women with dexterity or memory issues.
- Cost: $300–$600 per ring retail; typically one of the better-covered products on insurance because cost-per-month is modest.
- Note: A different, higher-dose systemic estradiol vaginal ring exists for hot flashes (VMS); unlike the low-dose local ring, that one calls for a progestogen in women who have a uterus.
Non-Estrogen Prescription Options: DHEA and Ospemifene
Prasterone (DHEA) Vaginal Insert
- Dose: 6.5 mg vaginal insert, once nightly (no maintenance step-down).
- Mechanism: DHEA is converted locally inside vaginal cells into both estrogen and testosterone. Serum hormone levels remain in the postmenopausal range.
- When useful: Women who do not want an estrogen label on their prescription, or who find that estrogen alone does not fully restore comfort (the local testosterone contribution seems to help some patients).
- Cost: $250–$500 per month retail; manufacturer copay cards can reduce this substantially. Insurance coverage varies.
Ospemifene — Oral Selective Estrogen Receptor Modulator (SERM)
- Dose: 60 mg orally once daily with food.
- Mechanism: A SERM — acts like an estrogen on vaginal tissue but behaves differently at breast and other sites.
- Indication: Moderate to severe dyspareunia from GSM, in women who cannot or will not use vaginal products.
- Trade-offs: Oral route means measurable systemic exposure. Small increase in VTE (blood clot) risk. Some women get hot flashes on it. Not first-line when a vaginal option is acceptable.
- Cost: Roughly $200–$450 per month retail.
Safety, Breast Cancer, and the Aromatase Inhibitor Nuance
The systemic absorption from low-dose vaginal estrogen is extremely small. Across every formulation at standard maintenance doses, serum estradiol stays within the normal postmenopausal range. For this reason:
- Vaginal estrogen does NOT require progestogen coverage in women with a uterus, at standard low doses. This is a formal position of NAMS and ACOG. If you hear otherwise, the clinician is extrapolating inappropriately from systemic hormone replacement therapy (HRT) guidance.
- There is no measured increase in breast cancer risk in observational data, including large analyses of the Women's Health Initiative observational cohort (Crandall 2018).
- There is no measured increase in endometrial cancer, VTE, stroke, or cardiovascular events at standard doses.
- In that Women's Health Initiative Observational Study (Crandall 2018; 45,663 women aged 50–79 who did not use systemic estrogen, followed for a median of 7.2 years), women with a uterus who used vaginal estrogen cream or tablets had no significantly different risk of stroke, invasive breast cancer, colorectal cancer, endometrial cancer or blood clots in the lungs or legs than non-users, and had lower risks of coronary heart disease, fracture and death from any cause. In women who had had a hysterectomy, none of these risks differed between users and non-users. The authors called the findings reassuring about the safety of treatment; as an observational study, it shows associations rather than proving cause.
For women with a history of breast cancer, the picture is more nuanced but still reassuring:
- ACOG and NAMS both endorse vaginal estrogen as an option for breast cancer survivors with bothersome GSM that has not responded to non-hormonal measures — after a conversation with their oncologist.
- For women on tamoxifen, vaginal estrogen is generally considered compatible (tamoxifen blocks any estrogen effect at breast tissue).
- The genuinely debated group is women on aromatase inhibitors (anastrozole, letrozole, exemestane). These drugs depend on keeping systemic estradiol as close to zero as possible. Even tiny bumps from vaginal estrogen are a theoretical concern. The data we have (including the low-dose ring and tablet) show minimal serum rise, but the decision is individualized. Many oncologists now accept low-dose vaginal estrogen for AI patients with severe GSM; others prefer a non-hormonal or DHEA trial first. This is a conversation, not a blanket rule.
How Long to Use It (Spoiler: Indefinitely)
Because GSM is progressive and estrogen deficiency never reverses on its own, treatment is typically lifelong. Symptoms return within weeks to months of stopping. This is not a failure — it is how the biology works. Using a vaginal insert twice a week at age 75 is as appropriate as it was at age 55.
There is no cumulative-dose ceiling, no "I should take a break" rule, and no expiration on benefit. The safety data out to 10+ years remain reassuring.
Cost, Insurance, and Ways to Get It
Cost is the single biggest barrier after clinician unfamiliarity. Routes people use:
- Discount-card services list cash prices for generic estradiol cream and generic estradiol vaginal tablets. The cash discount often beats the insurance copay.
- Generic versions. Generic estradiol cream and generic estradiol vaginal tablets contain the same estradiol as the brand-name products and work the same way, at lower cost.
- Manufacturer copay cards exist for several brand-name products, including the estradiol vaginal softgel insert, the prasterone (DHEA) vaginal insert, ospemifene and the low-dose estradiol vaginal ring.
- Insurance appeals. When insurance rejects the ring, a clinician can document that cream or tablets were tried first or ruled out. Most denials are reported to be reversed on appeal.
- Compounding pharmacies offer estradiol creams at sometimes lower cost, but quality and dose consistency are variable. Compounded creams have not gone through U.S. Food and Drug Administration approval the way the approved products have.
- Telehealth menopause services can prescribe vaginal estrogen in most U.S. states for a flat consult fee, which is often the fastest route when primary care is unhelpful.
Non-Hormonal Moisturizers, Lubricants, and Pelvic Floor PT
Many women use these alongside vaginal estrogen, and they are the mainstay for women who cannot use hormones.
Vaginal Moisturizers (Regular Use)
In the one large placebo-controlled trial of a vaginal moisturizer (Mitchell 2018, described above), an over-the-counter moisturizer used for 12 weeks did no better than a placebo gel.
- Hyaluronic acid suppositories — the best of the non-hormonal options — a hyaluronic-acid vaginal moisturizer, inserted as one suppository every 2–3 days. Users report symptom relief. ~$55 for a month.
- Polycarbophil gel — a bioadhesive polycarbophil vaginal moisturizer, one applicator every 2–3 days. $15–$25 for a month's supply.
- Coconut oil — inexpensive short-term moisturizer applied externally to the vulva. Fine for occasional use; not a substitute for a vaginal moisturizer for internal symptoms, and it can degrade latex condoms.
Lubricants (Used During Sex)
Lubricants are separate from moisturizers: they are used at the time of sex, usually generously.
- Water-based — condom-safe, washes off. Can dry out mid-session and is then reapplied.
- Silicone-based — longer-lasting and often used for painful sex (dyspareunia). Silicone lubricant is not compatible with silicone toys.
- Glycerin-heavy lubricants can worsen yeast infections, and warming or flavored products are irritants to thin tissue.
Pelvic Floor Physical Therapy
A massively under-used resource. A pelvic floor PT can address the hypertonic (tight, guarded) pelvic floor that develops after months of painful sex, treat urinary urgency, and guide vaginal dilator use to rebuild a narrowed canal. Insurance usually covers it under a standard PT benefit. One or two visits plus a home program often produces outsized gains on top of vaginal estrogen.
Laser and Radiofrequency Devices — The Evidence
Fractional CO2 lasers and radiofrequency devices have been heavily marketed as "non-hormonal GSM fixes." The short version:
- Small uncontrolled studies show symptom improvement.
- The sham-controlled trial (Li 2021, JAMA): 85 postmenopausal women in Sydney received three fractional CO2 laser treatments or three sham treatments, 4–8 weeks apart, without knowing which. At 12 months there was no significant difference from sham treatment in symptom severity, quality of life, the Vaginal Health Index or vaginal tissue samples (78 women completed follow-up).
- The laser-versus-estrogen trial (VeLVET, Paraiso 2020, Menopause): this trial had no sham arm; it compared fractional CO2 laser with estrogen vaginal cream. Of 69 women enrolled, 62 completed 6 months (30 laser, 32 estrogen). Both groups improved by a similar amount (85.8% of laser and 70% of estrogen users rated themselves "better or much better", not a statistically significant difference). Enrollment was closed early when the FDA required the sponsor to obtain an Investigational Device Exemption.
- The U.S. Food and Drug Administration (FDA) issued a warning in 2018 about the marketing of "vaginal rejuvenation" devices for GSM, noting safety concerns and lack of robust evidence.
- Cost is $1,500–$3,000 for a three-session course, rarely covered by insurance.
Laser may eventually find a legitimate niche, particularly for breast cancer survivors who cannot use any hormone. So far, the one sham-controlled trial found no benefit over sham at 12 months, and a laser course costs far more than generic vaginal estrogen.
Why Primary Care Keeps Missing This
You are not imagining it. The pattern is real and has specific causes:
- Training gap. The average U.S. medical resident receives less than one hour of menopause education. Most graduating OB/GYNs and family physicians have never been shown how to counsel on vaginal estrogen.
- The WHI misread. The 2002 Women's Health Initiative headlines scared a generation of clinicians off all estrogen, including local low-dose vaginal estrogen that has nothing to do with WHI findings. Many clinicians still conflate the two.
- The U.S. Food and Drug Administration black-box label. Every vaginal estrogen product carries a class-wide boxed warning copied from systemic hormone replacement therapy, despite the evidence showing local therapy has none of those risks. Patients see the label and assume the worst.
- Time and discomfort. GSM requires a pelvic exam, a frank sexual history, and a 10-minute counseling conversation — not possible in a 15-minute visit.
- Urinary tract infection (UTI) reflex. Recurrent urinary symptoms get treated as bacterial infections even when cultures are negative, because antibiotics are a faster disposition than a menopause workup.
When primary care does not treat GSM, other routes exist: a menopause-certified clinician (NAMS certification "MSCP" or "NCMP"), a telehealth menopause service, or a urogynecologist. GSM is a treatable condition, not an unavoidable part of aging.
Key Research Papers
- Portman DJ, Gass ML. Genitourinary syndrome of menopause: new terminology for vulvovaginal atrophy from ISSWSH and NAMS. Menopause. 2014;21(10):1063–1068. — the naming consensus paper. — doi:10.1097/GME.0000000000000329
- The 2020 genitourinary syndrome of menopause position statement of The North American Menopause Society. Menopause. 2020;27(9):976–992. — doi:10.1097/GME.0000000000001609
- Crandall CJ, et al. Breast cancer, endometrial cancer, and cardiovascular events in participants who used vaginal estrogen in the Women's Health Initiative Observational Study. Menopause. 2018;25(1):11–20. — the large reassuring safety cohort. — doi:10.1097/GME.0000000000000956
- Mitchell CM, et al. Efficacy of vaginal estradiol or vaginal moisturizer vs placebo for treating postmenopausal vulvovaginal symptoms: a randomized clinical trial. JAMA Intern Med. 2018;178(5):681–690. — neither the estradiol tablet nor the moisturizer beat placebo. — doi:10.1001/jamainternmed.2018.0116
- Li FG, et al. Effect of fractional carbon dioxide laser vs sham treatment on symptom severity in women with postmenopausal vaginal symptoms: a randomized clinical trial. JAMA. 2021;326(14):1381–1389. — the sham-controlled laser trial. — doi:10.1001/jama.2021.14892
- Paraiso MFR, Ferrando CA, Sokol ER, Rardin CR, Matthews CA, Karram MM, Iglesia CB. A randomized clinical trial comparing vaginal laser therapy to vaginal estrogen therapy in women with genitourinary syndrome of menopause: The VeLVET Trial. Menopause. 2020;27(1):50–56. — laser vs estrogen cream, no sham arm. — PubMed PMID: 31574047
- ACOG Committee Opinion No. 659: The use of vaginal estrogen in women with a history of estrogen-dependent breast cancer. Obstet Gynecol. 2016;127(3):e93–e96. — doi:10.1097/AOG.0000000000001351
PubMed Topic Searches
For current peer-reviewed literature:
- Genitourinary syndrome of menopause
- Vaginal estrogen safety and breast cancer
- Low-dose vaginal estradiol and systemic absorption
- Prasterone (DHEA) and dyspareunia
- Ospemifene for vulvovaginal atrophy
- Recurrent UTI and vaginal estrogen
- Fractional CO2 laser for vaginal atrophy (randomized trials)
- Hyaluronic acid vaginal moisturizers
- Aromatase inhibitors and vaginal estrogen
- Pelvic floor PT for dyspareunia
Connections
- Reproductive Medicine
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Micronized Progesterone vs Synthetic Progestins
- Estradiol Formulations: Patch, Gel, Oral Routes
- Hormone Replacement Therapy Risks: Breast Cancer, Clots and Stroke
- Testosterone Therapy for Women
- Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
- Perimenopause Symptom Tracker and Hormonal Testing
- Bone Loss Prevention and Hormone Replacement Therapy
- Perimenopause
- Menopause and Hormone Replacement Therapy
- Hormone Panel
- DHEA-S
- Testosterone
- Urinary Tract Infections
- Depression
- Insomnia
- Cardiovascular Disease
- Osteoporosis
- Menopause — the underlying estrogen decline that thins genitourinary tissue.