Nutrient Gaps: Magnesium, Vitamin D, B12, Iron in Fibromyalgia
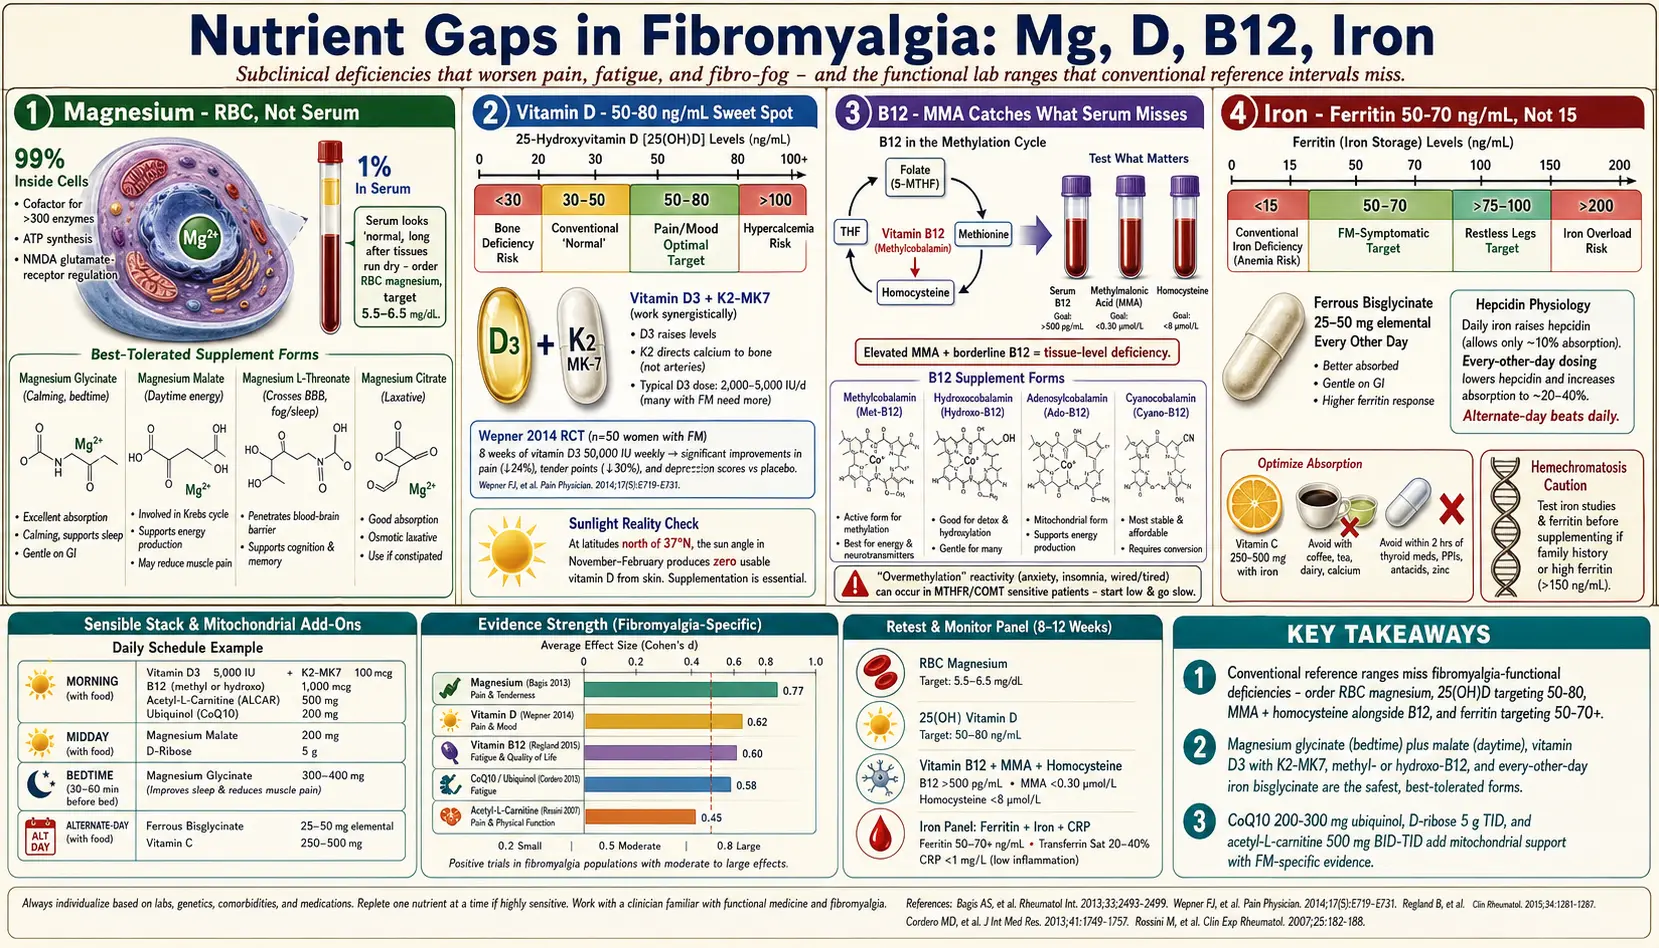
Table of Contents
- Why Nutrients Matter in Fibromyalgia
- Magnesium — The Most Commonly Missed Mineral
- Vitamin D — Pain, Mood, and the 50–80 Target
- Vitamin B12 — Why Serum Alone Misses Deficiency
- Iron and Ferritin — The >50–70 Sweet Spot
- Coenzyme Q10, Ribose, and Acetyl-L-Carnitine
- Combined Protocols Practitioners Describe
- Conditions and Medicines That Raise Concerns
- Key Research Papers
- Connections
- Featured Videos
Why Nutrients Matter in Fibromyalgia
If you have fibromyalgia, you have probably been told that "all your labs are normal." That phrase hides a lot. Standard lab panels catch frank deficiencies — anemia so severe your red cells are small and pale, vitamin D so low you are approaching osteomalacia, B12 so low your tongue is sore. They do not catch the subclinical gaps that quietly worsen fatigue, pain, and fibro fog in people whose cellular chemistry is already struggling.
Four nutrients come up over and over in careful fibromyalgia workups: magnesium, vitamin D, vitamin B12, and iron. None of them is a cure. Clinicians who work on these gaps argue that a low level of any one of them makes symptoms worse than they need to be, in a way no medication or exercise plan fully compensates for, and that correcting a documented gap is among the cheapest, lowest-risk steps available. It is often skipped because a green checkmark appeared next to a reference range that was never designed with chronic-pain patients in mind.
This article walks through each nutrient: why it matters, which lab actually answers the question, which foods help, which supplement forms exist, and what doses studies and clinicians have used. It also covers three "energy-metabolism" add-ons — coenzyme Q10 (CoQ10), D-ribose, and acetyl-L-carnitine — where the evidence is smaller.
Magnesium — The Most Commonly Missed Mineral
Why it matters. Magnesium is a cofactor for more than 300 enzymes, including every step that makes adenosine triphosphate (ATP) (cellular energy), every reaction that moves calcium out of muscle cells after contraction, and the N-methyl-D-aspartate (NMDA) glutamate receptor, which sits at the center of central sensitization. Low magnesium leaves N-methyl-D-aspartate receptors "unplugged" and more excitable — exactly the state fibromyalgia patients are trying to calm down. It also drives up muscle tone, promotes tension headaches, worsens sleep, and amplifies anxiety.
Bagis and colleagues (2013) divided 60 premenopausal women with fibromyalgia into three groups for 8 weeks: magnesium citrate 300 mg/day, amitriptyline 10 mg/day, or both. Serum and red-cell magnesium were lower in the women with fibromyalgia than in 20 healthy controls. Magnesium citrate alone reduced tender-point counts, the tender-point index, and fibromyalgia-impact and depression scores; the authors concluded that on its own it was effective only on tender points and the intensity of fibromyalgia, but that combined with amitriptyline it was effective on all measures.
The lab trap. Serum magnesium is unreliable. Only about 1% of your body's magnesium lives in the blood; the rest is locked inside cells and bone. The body guards serum magnesium tightly, pulling from bone if it has to, so serum looks "normal" long after tissues have run dry. If your doctor orders serum magnesium and it reads 2.0 mg/dL, that tells you almost nothing.
RBC magnesium (red blood cell magnesium) measures what is actually inside a cell and tracks tissue status far better. Clinicians who use it aim for the upper half of the reference range, roughly 5.5–6.5 mg/dL. Where RBC magnesium is unavailable, a 24-hour urinary magnesium or a magnesium-loading test is a distant second. Serum is a last resort, and these clinicians treat serum readings in the lower third of the range as presumptively insufficient.
Food sources. Pumpkin seeds, almonds, cashews, spinach, Swiss chard, black beans, edamame, dark chocolate (70%+), avocado, and mackerel. A handful of pumpkin seeds is roughly 150 mg; a cup of cooked spinach is about 160 mg. Most American diets deliver 200–250 mg per day; the Recommended Dietary Allowance (RDA) is 310–420 mg, and practitioners report that many fibro patients feel best closer to 500–600 mg total intake (food plus supplement).
Supplement forms — this matters a lot.
- Magnesium glycinate (bisglycinate). Bound to the amino acid glycine. Described as highly absorbed, calming (glycine itself is a mild inhibitory neurotransmitter), and gentle on the gut; it is the form practitioners most often use in fibromyalgia. Doses described: 200–400 mg elemental magnesium at bedtime.
- Magnesium malate. Bound to malic acid, a Krebs-cycle intermediate. Many fibro patients use it for daytime energy and muscle pain. Doses described: 200–400 mg elemental, often split morning and midday.
- Magnesium L-threonate. Described as the form that crosses the blood-brain barrier best. Small trials suggest cognitive and sleep benefit. Expensive. It is the form used when fibro fog and brain-based symptoms dominate. Doses described: 1,500–2,000 mg of the threonate compound (about 140–200 mg elemental) at night.
- Magnesium citrate. Well-absorbed, cheap, but laxative at higher doses — an effect used when constipation is also a problem.
- Magnesium oxide. The form in most drugstore multivitamins. Poorly absorbed (roughly 4%) and mostly acts as a laxative, which makes it a poor fit for tissue repletion.
- Topical magnesium chloride (Epsom salt baths, magnesium oil). Absorption is modest but real, and many patients find a warm Epsom bath helpful during flares even if the mineral uptake is small.
Doses and cautions. Practitioners describe starting at 200 mg elemental at bedtime and building up, and backing off or switching from citrate to glycinate/malate if stools loosen. The upper tolerable limit from supplements is 350 mg/day per the U.S. Institute of Medicine — but that limit is based on laxative effect, not toxicity, and well-tolerated doses of 400–600 mg are routine in fibromyalgia practice. In chronic kidney disease (estimated glomerular filtration rate (eGFR) <45), magnesium above 250 mg/day is a matter for medical supervision, because failing kidneys cannot clear magnesium and toxicity becomes possible. Interactions: magnesium reduces absorption of some antibiotics (fluoroquinolones, tetracyclines) and thyroid medication — doses are usually separated by 4 hours.
Vitamin D — Pain, Mood, and the 50–80 Target
Why it matters. Vitamin D is not really a vitamin; it is a steroid hormone with receptors on nearly every immune cell, muscle cell, and many pain-processing neurons. Low vitamin D is associated with diffuse musculoskeletal pain, low mood, poor sleep, and cytokine shifts that overlap with the fibromyalgia profile. Wepner and colleagues (2014) published a double-blind randomized trial of vitamin D supplementation in fibromyalgia patients with baseline 25(OH)D below 32 ng/mL; the treatment arm (titrated to 32–48 ng/mL) showed significantly reduced pain on a visual analog scale compared with placebo.
The lab. The test that reflects status is 25-hydroxyvitamin D [25(OH)D], not 1,25-dihydroxyvitamin D. 25(OH)D is the storage form and reflects your total supply; 1,25-D is an active hormone tightly controlled by the kidney and tells you little about status.
Conventional labs flag deficiency only below 20 or 30 ng/mL. That is a bone-health threshold. For pain and mood, most integrative clinicians target 50–80 ng/mL (125–200 nmol/L). Many fibromyalgia patients feel best near the middle of that range. The same clinicians keep levels under 100 ng/mL, comfortably away from hypercalcemia risk.
Food and sunlight. Food alone rarely gets you there. Wild salmon, sardines, mackerel, egg yolks, and cod liver oil are the usable sources; fortified milk and cereals provide trivial amounts. Sunlight on bare skin (arms and legs, midday, no sunscreen, 10–20 minutes for fair skin, longer for darker skin) drives endogenous production from April to October in the continental U.S. Latitude above roughly 37°N (San Francisco, Richmond, Denver) produces no usable vitamin D from November through February regardless of how sunny the sky looks.
Supplement form. Vitamin D3 (cholecalciferol) raises 25(OH)D more reliably than D2 (ergocalciferol). Practitioners often pair it with vitamin K2 (menaquinone-7 (MK-7), 90–180 mcg/day), on the reasoning that K2 directs calcium to bones and teeth and away from arteries and soft tissue, particularly when D is pushed above 50 ng/mL. Both are fat-soluble and are absorbed with fat (a meal with oil, butter, or avocado); absorption collapses on an empty stomach.
Doses. A ramp integrative clinicians describe for an adult with baseline 25(OH)D of 20–30 ng/mL: 5,000 international units (IU) of D3 plus 100 mcg K2-MK7 daily with the largest meal, with a retest at 8–12 weeks and adjustment after that. If baseline is under 20 ng/mL, some clinicians load with 10,000 international units/day for 8 weeks before dropping to maintenance. Maintenance once in the 50–80 range is usually 2,000–5,000 international units/day depending on body size, latitude, skin color, and sun habits.
Cautions. Hypercalcemia is the real risk at sustained high doses, which is why clinicians recheck 25(OH)D and a serum calcium (or ionized calcium) after dose changes. For comparison, the U.S. Institute of Medicine's 2011 report set the tolerable upper intake level for vitamin D — the most a day not expected to cause harm over the long term — at 4,000 IU for everyone aged 9 and older. The 5,000 and 10,000 IU doses described above are higher than that, and the report notes that the risk of harm begins to rise once intake goes past it. High-dose D carries particular risk in sarcoidosis, granulomatous disease, lymphoma, primary hyperparathyroidism, or a history of kidney stones — these conditions can convert 25-D to active 1,25-D unchecked — so in those conditions high doses are more likely to push blood calcium too high. Thiazide diuretics (water pills used for blood pressure, such as hydrochlorothiazide) add to that: the hydrochlorothiazide drug label says they lower the calcium lost in urine and can raise blood calcium slightly. MedlinePlus notes that most people with high blood calcium (hypercalcemia) have no symptoms, which is why it is found on blood tests; when there are signs, they include nausea or vomiting, poor appetite, constipation, more thirst and more frequent urination, muscle weakness or twitches, and tiredness or confusion.
Vitamin B12 — Why Serum Alone Misses Deficiency
Why it matters. B12 is essential for myelin repair, red-cell production, and the methylation reactions that recycle homocysteine and keep neurotransmitters (serotonin, dopamine, norepinephrine) flowing. Regland and colleagues have repeatedly documented elevated cerebrospinal-fluid homocysteine in fibromyalgia and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) patients — a functional signature of B12 and folate undersupply even when serum B12 looks normal. In a 2015 cross-sectional survey, Regland's team reviewed 38 patients with myalgic encephalomyelitis (with or without fibromyalgia) who had been on B12 injections at least once a week, with oral folic acid, for six months to several years; the good responders had used more frequent injections and higher B12 doses for longer, and higher daily amounts of oral folic acid.
The lab trap. Serum B12 is a poor screen. The U.S. reference range (typically 200–900 pg/mL) was set against frank megaloblastic anemia, not neurological or fatigue symptoms. Japan and most European countries flag anything under 500 pg/mL as deficient, and functional medicine clinicians often target >550–600 pg/mL. Worse, serum B12 can look high while tissue B12 is low — circulating analog B12, liver disease, and certain supplements can all inflate the number.
Functional deficiency is caught by adding methylmalonic acid (MMA) and homocysteine. Methylmalonic acid accumulates when B12 is truly low in the cell. Homocysteine rises when either B12 or folate is insufficient. An elevated methylmalonic acid with a borderline-low B12 means tissue-level deficiency regardless of what the serum says — and it is common in fibromyalgia.
Food sources. B12 is found only in animal foods: clams, liver, sardines, salmon, beef, eggs, dairy. Vegans rely on supplements for B12; long-term vegans without supplementation almost always develop deficiency eventually. Older adults lose stomach acid and intrinsic factor with age, so absorption drops even on a meat-heavy diet — the U.S. National Institutes of Health (NIH) estimates up to 20% of adults over 60 have some degree of B12 malabsorption. Long-term use of proton-pump inhibitors (omeprazole, esomeprazole), H2 blockers, and metformin also depletes B12, and B12 is commonly monitored in long-term users.
Supplement forms.
- Methylcobalamin (methyl-B12). The active coenzyme form. Absorbed well sublingually. Preferred by many clinicians, especially for neurological symptoms.
- Hydroxocobalamin. The form used in European and some U.S. clinical practice. Long-lasting in tissue; easier on sensitive people who react poorly to methylated B-vitamins. Often given as an intramuscular injection (1 mg weekly or monthly).
- Adenosylcobalamin. The mitochondrial form; sometimes paired with methyl-B12 for energy-forward protocols.
- Cyanocobalamin. The cheapest form and the one in most multivitamins. Your body must strip the cyanide group and convert it. Works for most people; some practitioners prefer other forms for people with MTHFR, COMT, or detox concerns.
The methylation caveat. A subset of patients — often carriers of COMT or methylenetetrahydrofolate reductase (MTHFR) variants — feel anxious, wired, or irritable on high-dose methyl-B12 or methyl-folate. This is sometimes called "overmethylation." Practitioners describe switching such patients to hydroxocobalamin, starting much lower (250–500 mcg rather than 1,000–5,000), and using a small amount of folate as folinic acid rather than L-methylfolate — matching the form to the person's biochemistry rather than stopping B12.
Doses. Oral repletion regimens described for fibromyalgia with borderline labs use 1,000–5,000 mcg methyl-B12 or hydroxo-B12 sublingually daily for 8–12 weeks, a retest of methylmalonic acid and homocysteine, and then a maintenance dose (500–1,000 mcg daily or several times per week). When methylmalonic acid stays elevated on oral therapy, intramuscular hydroxocobalamin (1 mg weekly for 8 weeks, then monthly) is described as more reliable.
Iron and Ferritin — The >50–70 Sweet Spot
Why it matters. Iron is the core of hemoglobin (oxygen transport), myoglobin (oxygen storage in muscle), and several enzymes that make dopamine and serotonin. Low iron — even without anemia — causes fatigue, restless legs, cold extremities, brain fog, thinning hair, and exercise intolerance. Women of reproductive age, heavy menstruators, frequent blood donors, and anyone with gut bleeding or celiac disease are at high risk, and fibromyalgia patients cluster in those categories.
The lab trap. Hemoglobin can still be "normal" long after iron stores are exhausted. The key test is ferritin, which measures stored iron. The U.S. reference range runs from roughly 15 to 200 ng/mL, and most labs flag "normal" above 15. That is a starvation threshold.
For fibromyalgia symptoms, most functional and sleep-medicine clinicians target ferritin above 50–70 ng/mL; for restless legs, the neurological target is often >75–100 ng/mL. Patients at 20 ng/mL are technically "normal" but functionally iron-depleted and often exhausted.
A full iron panel covers ferritin, serum iron, TIBC (total iron binding capacity), transferrin saturation, and C-reactive protein (CRP). Ferritin rises with inflammation, so a "normal" ferritin in someone with an elevated C-reactive protein can mask real deficiency — the transferrin saturation (normally >20%) helps sort this out.
Food sources. Heme iron (red meat, liver, shellfish, sardines) absorbs roughly 15–35%. Non-heme iron (lentils, beans, spinach, pumpkin seeds, dark chocolate) absorbs only 2–20% and drops further in the presence of tea, coffee, calcium, or whole grains. Pairing non-heme sources with vitamin C (peppers, citrus, kiwi) two- to three-folds absorption.
Supplement forms.
- Ferrous bisglycinate (iron chelate). Described as the best-tolerated form: gentle on the gut, minimal constipation, good absorption; the usual first choice. Doses described: 25–50 mg elemental iron every other day.
- Ferrous sulfate. Cheap and effective but notorious for nausea, constipation, and black stools. Works, but many patients abandon it.
- Ferrous fumarate and ferrous gluconate. Middle-ground tolerability.
- Heme iron polypeptide. Derived from animal hemoglobin; highly absorbed, expensive.
- Intravenous (IV) iron (iron sucrose, ferric carboxymaltose). For patients who cannot tolerate oral iron, have malabsorption, or need rapid repletion. Requires a prescriber and infusion setup.
Doses. Absorption studies favor every-other-day dosing of 50–100 mg elemental iron rather than daily. A dose of iron temporarily spikes a hormone called hepcidin that blocks the next day's absorption, so daily dosing is less efficient than alternate-day. Iron is absorbed best with vitamin C, on an empty stomach if tolerated, away from coffee, tea, dairy, calcium supplements, and thyroid medication; ferritin is usually rechecked at 8–12 weeks.
Cautions. Iron supplementation without a lab showing a need carries real risk. Iron overload (hemochromatosis) is common — roughly 1 in 200 people of Northern European descent carry two HFE mutations — and extra iron in someone who already has plenty damages the liver, pancreas, and heart. The risk is greatest for men and postmenopausal women, in whom low ferritin is normally confirmed before supplementing.
Coenzyme Q10, Ribose, and Acetyl-L-Carnitine
Beyond the big four, three mitochondrial-support nutrients have fibromyalgia-specific evidence worth knowing about.
Coenzyme Q10 (ubiquinone / ubiquinol). Coenzyme Q10 shuttles electrons through the mitochondrial electron transport chain. Cordero and colleagues have reported that fibromyalgia patients have lower coenzyme Q10 levels in blood mononuclear cells; in their 2013 randomized, placebo-controlled trial of 20 patients, 300 mg/day for 40 days reduced fibromyalgia-impact scores, pain, fatigue, morning tiredness, and tender points compared with placebo. Supplement doses described are 200–300 mg/day, often as ubiquinol (the reduced, better-absorbed form) with a fatty meal. Statins deplete coenzyme Q10, which makes the question more relevant for people taking one.
D-Ribose. A five-carbon sugar that is the backbone of adenosine triphosphate itself. Teitelbaum's open-label, uncontrolled pilot study in 41 patients with fibromyalgia and/or myalgic encephalomyelitis/chronic fatigue syndrome, at 5 g three times daily, reported significant improvement in energy, sleep, mental clarity, pain intensity, and well-being, with an average 45% increase in energy and a 30% improvement in overall well-being. Evidence quality is modest (no large placebo-controlled trials); the intervention is cheap and was well tolerated in the pilot. Caveat: it is a sugar and can temporarily lower blood glucose, which matters most for people with diabetes or a tendency to hypoglycemia; taking it with food is the usual approach in that case.
Acetyl-L-Carnitine (ALCAR). Shuttles fatty acids into mitochondria for beta-oxidation. A 2007 randomized, double-blind trial by Rossini and colleagues in 102 fibromyalgia patients gave two 500 mg capsules a day plus one 500 mg intramuscular injection for 2 weeks, then three 500 mg capsules a day for 8 weeks. Tender points and total pain-threshold scores improved equally on acetyl-L-carnitine and placebo up to week 6, then kept improving only on acetyl-L-carnitine, with a significant difference at week 10; depression and musculoskeletal pain also improved more than on placebo. The oral amounts in the trial were 500 mg two to three times daily. Some people find it stimulating late in the evening.
Combined Protocols Practitioners Describe
Practitioners who treat documented gaps in fibromyalgia describe combined starting protocols along these lines, drawn from the doses in the sections above:
- Morning, with breakfast: Vitamin D3 5,000 international units + K2-MK7 100 mcg, methyl- or hydroxo-B12 1,000 mcg sublingual, acetyl-L-carnitine 500 mg, coenzyme Q10 (ubiquinol) 200 mg.
- Midday, with lunch: Magnesium malate 200 mg elemental, D-ribose 5 g (mixed into water or tea).
- Bedtime: Magnesium glycinate 300–400 mg elemental.
- Alternate days, away from coffee/dairy/thyroid meds: Ferrous bisglycinate 25–50 mg elemental + vitamin C 250–500 mg (only if ferritin is low).
Such protocols retest at 8–12 weeks — RBC magnesium, 25(OH)D, serum B12 plus methylmalonic acid and homocysteine, ferritin plus iron panel plus C-reactive protein — and adjust doses based on results, not symptoms alone. Nutrient repletion is usually slow; real tissue-level changes take 3–6 months, not 3–6 days.
Conditions and Medicines That Raise Concerns
- Chronic kidney disease. Magnesium, potassium, and high-dose D all carry added risk when the kidneys are failing; these are decisions for the nephrologist.
- Hemochromatosis, HFE carriers, frequent transfusions. Iron supplementation carries real risk here; the threshold practitioners use is a recent ferritin under 50 ng/mL.
- Sarcoidosis, granulomatous disease, lymphoma, primary hyperparathyroidism, history of kidney stones. High-dose vitamin D can provoke hypercalcemia.
- Pregnancy and breastfeeding. RDAs change; these decisions belong with the obstetrician.
- Thyroid medication, fluoroquinolone or tetracycline antibiotics, bisphosphonates. Their absorption falls when taken with magnesium, iron, or calcium; doses are usually separated by at least 4 hours.
- Proton-pump inhibitors, metformin, anticonvulsants. Long-term use depletes B12 and magnesium — a reason for annual testing.
- Overmethylation reactivity. People who feel anxious, jittery, or sleepless on methyl-B12 or L-methylfolate are usually switched to hydroxocobalamin and folinic acid at lower doses.
Practitioners who work on these gaps test before treating, start low, and recheck after 8–12 weeks. Fibromyalgia is not cured by any single supplement, and the trials above are small; the safety limits for each nutrient are in its Cautions paragraph above.
Key Research Papers
- Bagis S, et al. Is magnesium citrate treatment effective on pain, clinical parameters and functional status in patients with fibromyalgia? Rheumatol Int. 2013. — doi:10.1007/s00296-011-2334-8
- Wepner F, et al. Effects of vitamin D on patients with fibromyalgia syndrome: a randomized placebo-controlled trial. Pain. 2014. — doi:10.1016/j.pain.2013.10.002
- Regland B, et al. Response to vitamin B12 and folic acid in myalgic encephalomyelitis and fibromyalgia. PLoS ONE. 2015. — doi:10.1371/journal.pone.0124648
- Cordero MD, et al. Can coenzyme q10 improve clinical and molecular parameters in fibromyalgia? Antioxid Redox Signal. 2013. — PubMed PMID: 23458405
- Rossini M, et al. Double-blind, multicenter trial comparing acetyl l-carnitine with placebo in the treatment of fibromyalgia patients. Clin Exp Rheumatol. 2007. — PubMed PMID: 17543140
- Stoffel NU, et al. Iron absorption from oral iron supplements given on consecutive versus alternate days. Lancet Haematol. 2017 (alternate-day iron dosing). — Search PubMed
- Ross AC, Manson JE, Abrams SA, et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. The Journal of Clinical Endocrinology and Metabolism — PubMed PMID: 21118827
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on nutrient status in fibromyalgia and related chronic-pain syndromes:
- PubMed: Fibromyalgia and magnesium
- PubMed: Fibromyalgia, vitamin D, and pain
- PubMed: Fibromyalgia, B12, and homocysteine
- PubMed: Fibromyalgia, ferritin, and iron status
- PubMed: Fibromyalgia and coenzyme Q10
- PubMed: Fibromyalgia and acetyl-L-carnitine
- PubMed: Fibromyalgia, D-ribose, and chronic fatigue
- PubMed: RBC magnesium and tissue status assessment
- PubMed: Methylmalonic acid and functional B12 deficiency
- PubMed: Alternate-day iron dosing and hepcidin
Connections
- Orthopedics
- Magnesium
- Fibromyalgia Overview
- Iron
- Vitamin B12
- Vitamin D3
- Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overlap
- Low-Dose Naltrexone for Fibromyalgia
- Sleep and Non-Restorative Sleep
- ACR 2016 Diagnostic Criteria
- Central Sensitization Explained
- Small-Fiber Neuropathy Overlap
- Exercise Pacing and Graded Movement
- Chronic Fatigue Syndrome
- Homocysteine
- Calcium
- Vitamin B12 Test
- Fatigue
- Magnesium Glycinate