Small Intestinal Bacterial Overgrowth (SIBO)
Deep-Dive Articles
SIBO is a big topic, and most people land here mid-journey — you’ve already heard of it and want to dig deeper. The eight articles below each focus on one part of the puzzle: how it’s diagnosed, how it’s treated, and why it keeps coming back. Start with whichever piece matches where you are right now.
Hydrogen vs. Methane vs. Hydrogen Sulfide
The three SIBO subtypes explained in plain language — why hydrogen and hydrogen sulfide are linked with diarrhea and methane with constipation, and why the gas pattern on the breath test is used in choosing treatment.
Read the deep dive →Breath Test Guide
Lactulose vs. glucose vs. three-gas testing: how the tests differ, what the 2017 North American Consensus says about preparation and positive results, how the curves are read, and why false negatives and false positives happen.
Read the deep dive →Low-FODMAP Diet
The complete food list, the three phases (elimination, reintroduction, personalization), and why it is not described as a long-term diet. A symptom-control tool, not a cure.
Read the deep dive →Elemental Diet
The 2-week liquid-only diet absorbed high in the small intestine, so that little reaches bacteria further down. Commercial vs. homemade, cost, palatability, and the results reported (80% at 14 days and 85% by 21 days in a 2004 Pimentel study).
Read the deep dive →Rifaximin for SIBO
Doses on the label and in SIBO studies, why methane studies tested rifaximin plus neomycin, approved uses and off-label status, safety, and what studies report after a first course does not work.
Read the deep dive →Herbal Antimicrobials
Berberine, oregano oil, allicin, neem — what the Chedid 2014 chart review found (46% vs. 34% negative breath tests, a difference that was not statistically significant), the commercial blends it used, and what is and is not known about doses and rotation.
Read the deep dive →Prokinetics & Relapse Prevention
Why SIBO comes back (43.7% at 9 months in one cohort) — and the migrating motor complex (MMC) that prokinetics aim to restore. Low-dose naltrexone, prucalopride, low-dose erythromycin, ginger, and meal spacing.
Read the deep dive →Root Causes
Post-infectious IBS, anti-vinculin antibodies, Ehlers-Danlos/hypermobility, ileocecal valve issues, thyroid slowdown, PPIs, abdominal adhesions — the conditions linked with SIBO and with its return after treatment.
Read the deep dive →IMO: Methane Overgrowth & Constipation
Why rifaximin alone cleared methane in only 28% in one chart review, and the neomycin and lovastatin approaches.
Read the deep dive →Interactive Visualization The Gut Barrier & Your Microbiome Watch fibre become butyrate and butyrate tighten the gut wall — then starve the microbes and see them eat your mucus layer instead. Launch →
Table of Contents
1. Overview
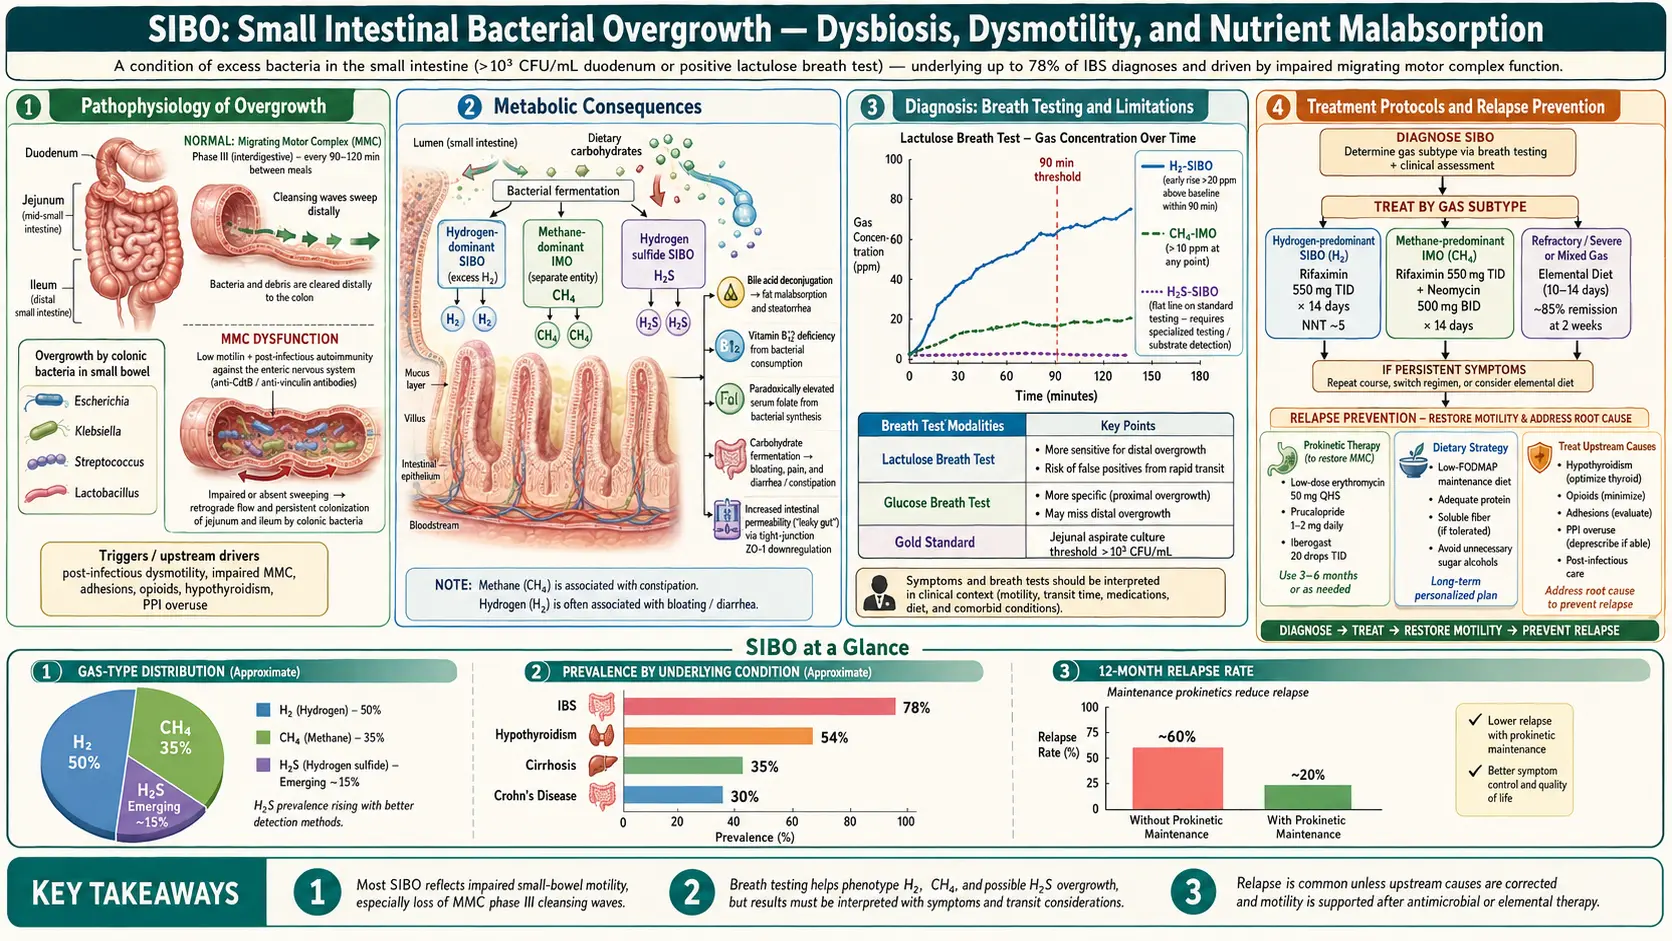
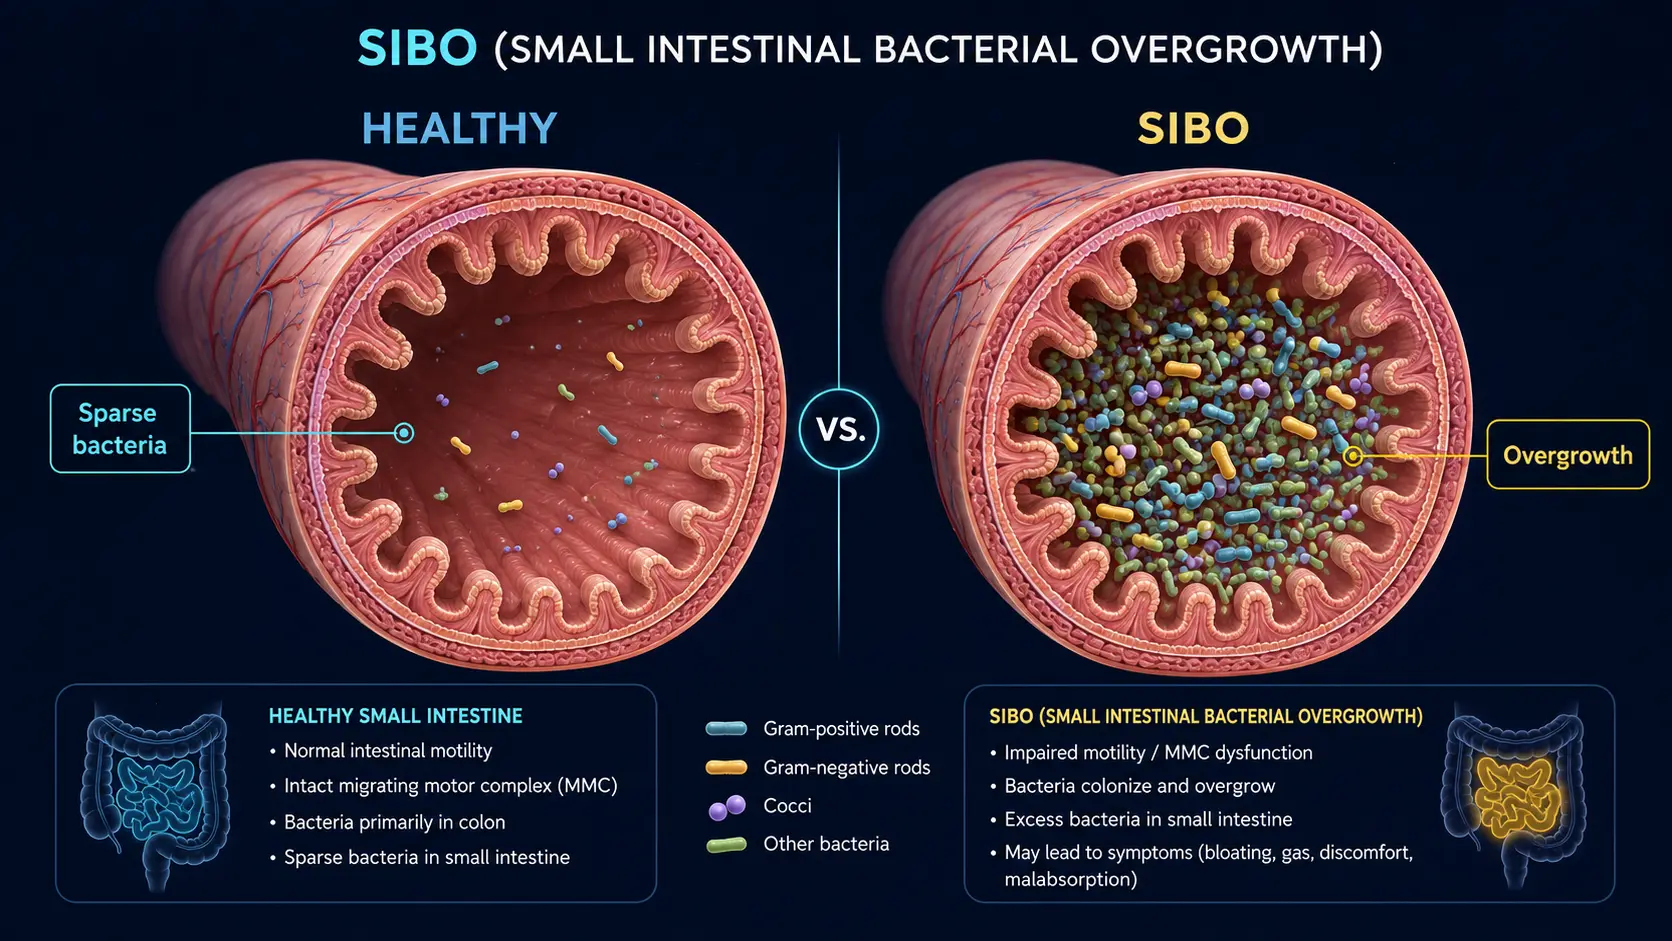
Small intestinal bacterial overgrowth (SIBO) is a clinical condition characterized by an abnormally excessive bacterial colonization of the small intestine, an area of the gastrointestinal tract that normally harbors relatively few microorganisms compared to the colon. Under normal physiological conditions, the small intestine contains fewer than 10^3 to 10^4 colony-forming units per milliliter (CFU/mL) of luminal fluid, primarily consisting of gram-positive aerobes and facultative anaerobes. SIBO is traditionally defined as the presence of ≥10^5 CFU/mL in a jejunal aspirate, though more recent consensus recommendations have proposed a lower threshold of ≥10^3 CFU/mL in the setting of colonic-type bacteria (anaerobes, gram-negative organisms) to improve diagnostic sensitivity.
The overgrowth of bacteria in the small intestine disrupts normal digestive and absorptive functions through multiple mechanisms, including deconjugation of bile salts (leading to fat malabsorption), competitive consumption of nutrients (particularly vitamin B12 and iron), damage to the intestinal epithelium (causing increased intestinal permeability, or "leaky gut"), and fermentation of undigested carbohydrates (producing hydrogen, methane, and hydrogen sulfide gases that cause bloating, distension, and altered bowel habits). SIBO has emerged as a significant clinical entity due to its strong association with irritable bowel syndrome (IBS), with studies suggesting that 30-78% of patients meeting Rome criteria for IBS have underlying SIBO.
SIBO is now recognized to exist in three distinct subtypes based on the predominant gas produced during fermentation: hydrogen-dominant SIBO (associated with diarrhea-predominant symptoms), methane-dominant SIBO (now termed intestinal methanogen overgrowth, or IMO, associated with constipation-predominant symptoms), and hydrogen sulfide-dominant SIBO (recently characterized, associated with diarrhea and sulfurous eructation). This subtyping has important therapeutic implications, as different gas-producing organisms respond to different antimicrobial strategies.
2. Epidemiology
The true prevalence of SIBO in the general population is difficult to determine due to variability in diagnostic methods and thresholds, but estimates range from 0.5-6% in healthy, asymptomatic individuals to much higher rates in specific populations. Among patients with irritable bowel syndrome (IBS), SIBO prevalence ranges from 30-78% depending on the diagnostic modality used, with breath testing consistently showing higher rates than jejunal aspirate culture. SIBO disproportionately affects the elderly, with prevalence increasing to 15-33% in individuals over age 60, attributed to age-related declines in gastric acid production, intestinal motility, and immune function.
Specific high-risk populations demonstrate markedly elevated SIBO prevalence: chronic pancreatitis (30-40%), liver cirrhosis (30-73%), celiac disease (9-55%), Crohn's disease (18-30%), diabetes mellitus (8-44%), systemic sclerosis/scleroderma (43-55%), chronic kidney disease (27-36%), hypothyroidism (54%), Parkinson's disease (25-55%), morbid obesity (17-41%), and patients on chronic proton pump inhibitor (PPI) therapy (50%). Post-surgical populations are also at high risk, particularly after Roux-en-Y gastric bypass (40-52%), ileocecal valve resection, and any surgery creating blind loops or altered intestinal anatomy.
Women are affected more frequently than men, with a female-to-male ratio of approximately 2-3:1, which parallels the sex distribution of IBS. The economic burden of SIBO is substantial, with patients utilizing significantly more healthcare resources, undergoing more diagnostic testing, and reporting lower quality-of-life scores than matched controls without the condition.
3. Pathophysiology
Normal Protective Mechanisms
The small intestine maintains its low bacterial count through several interconnected defense mechanisms. Disruption of any of these mechanisms predisposes to bacterial overgrowth:
- Gastric acid: Hydrochloric acid (pH 1-3) serves as the first barrier against ingested microorganisms. Conditions that reduce gastric acid (achlorhydria, PPI use, atrophic gastritis) remove this protective barrier.
- Migrating motor complex (MMC): The MMC is a cyclical pattern of gastrointestinal motor activity that occurs during fasting, approximately every 90-120 minutes. Phase III of the MMC produces high-amplitude propulsive contractions that sweep residual bacteria, debris, and undigested material from the small intestine into the colon. This "intestinal housekeeper" function is considered the most important defense mechanism against SIBO.
- Ileocecal valve: This anatomical sphincter prevents retrograde migration of the dense colonic microbiota into the distal ileum. Surgical removal, incompetence, or anatomical disruption of the ileocecal valve significantly increases SIBO risk.
- Intestinal secretory immunoglobulin A (sIgA): sIgA binds to bacteria and prevents adherence to the intestinal epithelium, promoting clearance.
- Bile acids and pancreatic enzymes: Conjugated bile acids have bacteriostatic properties. Pancreatic enzymes, particularly lipase and proteases, contribute to bacterial clearance.
Mechanism of Bacterial Overgrowth
When protective mechanisms fail, colonic-type bacteria (predominantly Escherichia coli, Klebsiella, Proteus, Enterococcus, and obligate anaerobes such as Bacteroides and Clostridium) colonize the small intestine in excessive numbers. The overgrowth bacteria generate pathology through several interconnected mechanisms:
- Carbohydrate fermentation: Bacteria ferment dietary carbohydrates and endogenous mucus glycoproteins, producing hydrogen (H2), carbon dioxide (CO2), and short-chain fatty acids. Hydrogen is subsequently utilized by methanogenic archaea (Methanobrevibacter smithii) to produce methane (CH4), or by sulfate-reducing bacteria (Desulfovibrio spp.) to produce hydrogen sulfide (H2S). These gases cause abdominal bloating, distension, flatulence, and altered motility.
- Bile salt deconjugation: Overgrowth bacteria possess bile salt hydrolase enzymes that deconjugate bile acids prematurely in the small intestine. Deconjugated bile acids are less effective at forming micelles, leading to fat malabsorption, steatorrhea, and malabsorption of fat-soluble vitamins (A, D, E, K). Free bile acids are also directly toxic to enterocytes, causing mucosal inflammation.
- Nutrient competition: Bacteria consume vitamin B12 (cobalamin) before it can be absorbed by the host in the terminal ileum, leading to vitamin B12 deficiency. Paradoxically, overgrowth bacteria produce folate, so folate levels may be normal or elevated. Bacterial consumption of dietary iron contributes to iron deficiency.
Intestinal Permeability and Systemic Effects
SIBO damages the intestinal epithelial barrier through bacterial metabolite-induced inflammation, disruption of tight junction proteins (occludin, claudins, ZO-1), and villous blunting. This increased intestinal permeability ("leaky gut") allows translocation of bacterial endotoxins (lipopolysaccharide, LPS) and food antigens into the systemic circulation, triggering low-grade systemic inflammation, immune activation, and potentially contributing to extraintestinal manifestations including rosacea, restless legs syndrome, fibromyalgia, interstitial cystitis, and non-alcoholic fatty liver disease (NAFLD).
Methane and Motility
Methane gas, produced by the archaeon Methanobrevibacter smithii, is not merely an inert byproduct of fermentation. In a 2006 study, infusing methane into the small intestine of dogs slowed transit by an average of 59%, methane augmented contractile activity in guinea-pig ileum, and methane-producing IBS patients had a higher small-bowel motility index than hydrogen producers (Pimentel 2006). Slow motility is thought to favour bacterial overgrowth, and methane production may slow motility further, which would perpetuate the condition. Methane on the breath test is associated with constipation-predominant IBS (IBS-C).
4. Etiology and Risk Factors
Impaired Motility (Most Common Predisposing Factor)
- Diabetic gastroparesis and enteropathy (autonomic neuropathy affecting MMC)
- Scleroderma/systemic sclerosis (smooth muscle fibrosis and atrophy)
- Hypothyroidism (reduced intestinal motility)
- Chronic opioid use (mu-receptor mediated motility suppression)
- Parkinson's disease (vagal nerve dysfunction and alpha-synuclein deposition in the enteric nervous system)
- Post-infectious gastroparesis (following viral or bacterial gastroenteritis)
- Ehlers-Danlos syndrome (connective tissue disorders affecting intestinal wall compliance)
- Chronic intestinal pseudo-obstruction
Anatomical Abnormalities
- Surgically created blind loops (Billroth II, Roux-en-Y reconstruction)
- Ileocecal valve resection or incompetence
- Small intestinal diverticulosis (stasis within diverticula)
- Strictures (Crohn's disease, radiation enteritis, surgical adhesions)
- Small intestinal obstruction (partial)
- Gastric bypass surgery (Roux-en-Y gastric bypass)
Reduced Gastric Acid
- Proton pump inhibitors (PPIs): Chronic PPI use increases SIBO risk by 2-8 fold by raising gastric pH above 4, eliminating the acid barrier to ingested bacteria
- Atrophic gastritis (including autoimmune/pernicious anemia)
- Vagotomy
- Advanced age (age-related hypochlorhydria)
Immune Deficiency
- IgA deficiency (selective or common variable immunodeficiency)
- HIV/AIDS
- Combined variable immunodeficiency (CVID)
- Chronic immunosuppressive therapy
Other Predisposing Conditions
- Celiac disease (reduced MMC activity even after gluten-free diet)
- Chronic pancreatitis (loss of bacteriostatic pancreatic secretions)
- Liver cirrhosis (portal hypertension, reduced bile acid secretion, impaired motility)
- End-stage renal disease
- Fibromyalgia
- Chronic fatigue syndrome
- Mast cell activation syndrome
5. Clinical Presentation
Gastrointestinal Symptoms
The clinical presentation of SIBO is highly variable and overlaps significantly with IBS and other functional gastrointestinal disorders:
- Bloating and abdominal distension: The most common and often most distressing symptom, typically worsening throughout the day and after meals, particularly those high in fermentable carbohydrates (FODMAPs). Present in 70-85% of SIBO patients.
- Flatulence and excessive gas: Due to bacterial fermentation of carbohydrates in the small intestine, producing hydrogen, methane, and carbon dioxide.
- Abdominal pain and cramping: Diffuse or periumbilical discomfort, often postprandial, caused by gas distension and visceral hypersensitivity.
- Diarrhea: Characteristic of hydrogen-dominant SIBO. Results from bile acid malabsorption, osmotic effects of unabsorbed nutrients, and bacterial enterotoxin-mediated secretion. May be watery, frequent, and foul-smelling.
- Constipation: Characteristic of methane-dominant SIBO (IMO). Methane gas directly inhibits intestinal peristalsis and transit.
- Nausea: Particularly common in severe cases or those with concurrent gastroparesis.
- Steatorrhea: Fatty, malodorous stools due to fat malabsorption from bile acid deconjugation.
- Belching: Particularly sulfurous belching in hydrogen sulfide-dominant SIBO.
Nutritional Deficiencies
- Vitamin B12 deficiency: Bacteria in the proximal small intestine consume vitamin B12 before it reaches its absorption site in the terminal ileum. Can lead to megaloblastic anemia, peripheral neuropathy, and cognitive impairment.
- Iron deficiency: Bacterial consumption and impaired absorption.
- Fat-soluble vitamin deficiencies (A, D, E, K): Due to bile acid deconjugation and fat malabsorption. Can cause night blindness (A), osteoporosis (D), neuropathy (E), and coagulopathy (K).
- Protein malabsorption: In severe cases, hypoalbuminemia from protein-losing enteropathy.
- Elevated folate: Paradoxically, bacterial production of folate may elevate serum levels, which combined with low B12 is a characteristic pattern suggestive of SIBO.
Extraintestinal Manifestations
- Fatigue and brain fog: Among the most common extraintestinal complaints, potentially related to systemic endotoxemia and D-lactic acidosis from bacterial fermentation.
- Rosacea: Strong epidemiological association; SIBO eradication has been shown to improve or resolve rosacea in clinical studies.
- Restless legs syndrome: Association with SIBO, possibly mediated through iron deficiency or systemic inflammation.
- Joint pain and arthralgia: Related to immune complex formation and systemic inflammation.
- Skin conditions: Acne, eczema, and urticaria have been associated with SIBO and intestinal permeability.
- Depression and anxiety: Gut-brain axis disruption through altered neurotransmitter production, vagal signaling, and systemic inflammation.
6. Diagnosis
Small Bowel Aspirate and Culture (Gold Standard)
Jejunal aspirate culture obtained during upper endoscopy (esophagogastroduodenoscopy, EGD) is considered the traditional gold standard for SIBO diagnosis. Fluid is aspirated from the proximal jejunum and cultured quantitatively. A bacterial count of ≥10^5 CFU/mL is the classic diagnostic threshold, though the 2017 North American Consensus suggests a threshold of >10^3 CFU/mL if culture is used. Limitations include its invasive nature, cost, risk of oropharyngeal contamination during scope passage, inability to sample the distal small intestine, and the fact that up to 30% of SIBO-causing organisms may not grow on standard culture media.
Hydrogen and Methane Breath Testing
Breath testing is the most widely used diagnostic modality due to its non-invasive nature, accessibility, and relatively low cost. The test measures exhaled hydrogen (H2) and methane (CH4) gases produced by bacterial fermentation of an ingested substrate:
- Lactulose breath test (LBT): The patient drinks 10 grams of lactulose (a non-absorbable synthetic disaccharide, the consensus dose), and breath samples are collected at intervals; the consensus states that testing for SIBO can be limited to two hours. The consensus criterion for a positive test is a rise in hydrogen of ≥20 ppm from baseline by 90 minutes. Across validation studies, sensitivity ranged from 31-68% and specificity from 44-100%.
- Glucose breath test (GBT): The consensus dose is 75 grams of glucose, with breath samples collected in the same way. Because glucose is absorbed in the proximal small intestine, an early rise in hydrogen points to bacterial fermentation in the proximal small bowel. The consensus criterion is the same as for lactulose: a rise of ≥20 ppm from baseline by 90 minutes. Across validation studies, sensitivity ranged from 20-93% and specificity from 30-86%. Glucose may not detect distal small bowel overgrowth.
- Methane measurement: The consensus suggests that a methane level of ≥10 ppm be considered positive; the ACG guideline uses the term intestinal methanogen overgrowth (IMO). Methane is produced mainly by Methanobrevibacter smithii and is associated with constipation.
Preparation: The 2017 consensus recommends avoiding antibiotics for 4 weeks before the test, and suggests stopping promotility drugs and laxatives at least 1 week before if tolerated, avoiding fermentable foods such as complex carbohydrates the day before, and fasting for 8-12 hours; it recommends no smoking on the test day and limited physical activity during the test, and suggests that stopping proton pump inhibitors is not necessary. Laboratories often add their own rules on specific foods, mouthwash and toothpaste, which the consensus statements do not address.
Three-Gas Breath Test
The three-gas breath test is a newer breath testing method that measures all three fermentation gases on the same samples: hydrogen, methane, and hydrogen sulfide. The 2017 consensus noted that a test with no methane and a low, flat hydrogen line had been suggested to reflect hydrogen sulfide-producing bacteria, which the devices of the time could not detect. There is no consensus cut-off for hydrogen sulfide; studies have used different thresholds, and higher breath hydrogen sulfide has been associated with diarrhea-predominant symptoms (Villanueva-Millan 2022).
Adjunctive Laboratory Testing
- Vitamin B12 level: Low in SIBO due to bacterial consumption (unlike in short bowel syndrome where folate is low)
- Folate level: Normal or elevated due to bacterial production
- Iron studies: Iron deficiency pattern from malabsorption
- Fat-soluble vitamins (A, D, E, K): May be reduced
- Complete blood count: Macrocytic anemia (B12 deficiency) or microcytic anemia (iron deficiency) or combined
- Fecal fat testing: Elevated in cases with significant bile acid deconjugation
- D-xylose absorption test: Abnormal in SIBO due to mucosal damage and bacterial metabolism of the substrate
- Anti-vinculin and anti-CdtB antibodies: Proposed biomarkers for post-infectious IBS/SIBO, measuring autoantibodies against the interstitial cells of Cajal and cytolethal distending toxin B
7. Treatment
Antibiotic Therapy
The 2020 ACG guideline suggests antibiotics for symptomatic SIBO, a conditional recommendation based on low-quality evidence, and describes the antibiotic data as “small clinical trials of poor to modest quality.” The regimens studied differ by breath-gas pattern:
- Rifaximin: The most studied antibiotic for SIBO. It is minimally absorbed — in the mass-balance study on the US prescribing information, 0.32% of a radiolabelled dose was recovered in the urine — and acts mainly in the gut lumen. SIBO is not among its approved US indications (travelers’ diarrhea, hepatic encephalopathy and IBS-D), so its use for SIBO is off-label. A 2017 meta-analysis of 32 studies (1,331 patients) found an overall eradication rate of 70.8% by intention to treat, with adverse events in 4.6%, while describing the quality of the studies as generally poor; doses varied between studies (Gatta 2017). In the TARGET 1 and 2 trials in IBS without constipation, which measured symptom relief rather than breath tests, 550 mg three times daily for 14 days gave adequate relief of global IBS symptoms in 40.7% against 31.7% with placebo; that regimen is the approved IBS-D dose.
- Rifaximin plus neomycin for methane-positive breath tests (IMO): In a 2010 retrospective chart review of methane-positive IBS patients, methane cleared in 87% with rifaximin plus neomycin, against 28% with rifaximin alone (400 mg three times daily) and 33% with neomycin alone (500 mg twice daily), each given for 10 days (Low 2010). Partially hydrolyzed guar gum (PHGG) has been tested as an add-on for SIBO in general: in a 2010 randomized trial, eradication was 85.0% with rifaximin 1,200 mg a day plus PHGG 5 g a day for 10 days, against 62.1% with rifaximin alone, by intention to treat (Furnari 2010).
- Other antibiotics: Regimens listed in the literature include metronidazole, ciprofloxacin, amoxicillin-clavulanate, doxycycline, neomycin and trimethoprim-sulfamethoxazole; the doses reported and the comparison data are set out on the rifaximin deep-dive. In a retrospective chart review, 69% of IBS patients treated with rifaximin had a clinical response, compared with 44% across non-rifaximin antibiotics (Yang 2008).
Herbal Antimicrobial Therapy
The study most often cited for herbal antimicrobials is a 2014 retrospective chart review by Chedid et al. (2014), published in Global Advances in Health and Medicine, in which patients chose their own 4-week treatment. The follow-up lactulose breath test was negative in 17 of 37 (46%) on commercial multi-ingredient herbal blends and 23 of 67 (34%) on rifaximin 1,200 mg a day (P = 0.24), a difference that was not statistically significant (adjusted odds ratio 1.85, 95% CI 0.77-4.41). The paper reports no non-inferiority margin, so it did not establish equivalence; the authors reported no conflicts of interest. Herbs described in practitioner regimens include:
- Allicin (from garlic): Used by practitioners for methane-positive SIBO; the evidence for an effect on methane-producing archaea comes from livestock research, not human trials, and allicin was not an ingredient of the Chedid blends.
- Berberine: An alkaloid from goldenseal, Oregon grape and barberry; berberine-containing extracts were among the Chedid blends’ ingredients. In healthy men, repeated doses decreased CYP2D6, CYP2C9 and CYP3A4 activity (Guo 2012), which raises a concern for people taking drugs cleared by those enzymes.
- Oregano oil: Contains carvacrol and thymol; it was one ingredient of one of the four commercial products in the Chedid review.
- Neem: A traditional Ayurvedic antimicrobial; it was not in the Chedid blends, and no human SIBO trial of neem is cited here.
- First pair of commercial blends: One of the two pairs of multi-ingredient blends, each pair from a different supplement company, taken by the Chedid herbal group at 2 capsules of each twice daily.
- Second pair of commercial blends: The other pair used in the Chedid review; across the four products, the ingredients included oregano oil, red thyme oil, sage, lemon balm, berberine-containing extracts, wormwood and olive leaf.
Elemental Diet
The elemental diet is a liquid formula containing pre-digested nutrients (amino acids, simple sugars, medium-chain triglycerides, and micronutrients) that are absorbed in the proximal jejunum, effectively starving bacteria in the mid and distal small intestine. In a 2004 study by Pimentel et al. of 93 IBS patients with an abnormal lactulose breath test, 80% had a normal test after 14 days of an exclusive elemental diet, and 85% after up to 21 days. Its limits include poor palatability, high cost, and difficulty with compliance. Semi-elemental diets with partially hydrolyzed proteins offer an alternative with improved palatability.
Prokinetic Therapy (Preventing Recurrence)
Impaired motility, particularly reduced MMC activity, is a common predisposing factor for SIBO, and prokinetic agents are used to try to delay relapse after antibiotic treatment. In a 2009 chart review, IBS symptoms returned after an average of 59.7 days with no prevention, 138.5 days with low-dose erythromycin (a difference that was not statistically significant, P = 0.08) and 241.6 days with tegaserod (Pimentel 2009). Agents described include:
- Low-dose erythromycin: Acts as a motilin receptor agonist at sub-antimicrobial doses, stimulating Phase III of the MMC; the 2009 chart review used 50 mg at bedtime.
- Low-dose naltrexone (LDN): An opioid receptor antagonist used at low doses by some clinicians; its evidence in SIBO is covered in the prokinetics deep-dive.
- Prucalopride: Selective 5-HT4 receptor agonist that stimulates high-amplitude propagating contractions.
- Nine-herb liquid preparation: A commercial herbal combination of nine botanical extracts, studied for effects on gastric and intestinal motility.
- Ginger (Zingiber officinale): Studied for effects on gastric emptying and intestinal motility; its use after SIBO treatment is covered in the prokinetics deep-dive.
Dietary Management
- Low-FODMAP diet: Restriction of fermentable oligosaccharides, disaccharides, monosaccharides, and polyols reduces substrate for bacterial fermentation and provides symptomatic relief, though it does not eradicate SIBO. It is used alongside antimicrobial treatment, during the treatment phase.
- Specific Carbohydrate Diet (SCD): Eliminates complex carbohydrates and disaccharides, allowing only monosaccharides. Some practitioners combine SCD principles with low-FODMAP restrictions.
- Bi-Phasic Diet (Dr. Nirala Jacobi): A two-phase dietary approach for SIBO described by its author as progressing from a restrictive to a more liberal phase over 8 weeks; no published trial of it is cited here.
- Meal spacing: Some practitioners describe leaving 4-5 hours between meals without snacking, on the reasoning that the MMC runs its Phase III “housekeeping” sweep in the fasting state and is interrupted by food intake. This has not been tested in a SIBO trial cited here.
8. Complications
- Severe malnutrition: Prolonged untreated SIBO can cause clinically significant malabsorption of macronutrients and micronutrients, leading to weight loss, muscle wasting, and sarcopenia.
- Vitamin B12 deficiency neuropathy: Chronic B12 depletion can cause subacute combined degeneration of the spinal cord, peripheral neuropathy, and irreversible neurological damage if untreated.
- Osteoporosis and osteomalacia: From vitamin D and calcium malabsorption.
- Coagulopathy: Vitamin K malabsorption can cause bleeding diathesis, particularly in patients on anticoagulants.
- D-lactic acidosis: In severe cases, particularly following bariatric surgery, bacterial production of D-lactic acid can cause episodic encephalopathy, ataxia, and metabolic acidosis.
- Intestinal permeability and systemic inflammation: Chronic SIBO increases intestinal permeability, facilitating bacterial translocation and endotoxemia, contributing to hepatic steatosis (NAFLD) and systemic inflammatory conditions.
- Autoimmune conditions: Increased intestinal permeability and molecular mimicry have been implicated in the development or exacerbation of autoimmune diseases including Hashimoto's thyroiditis and rheumatoid arthritis.
- High recurrence rate: In an Italian cohort, 43.7% of patients were breath-test positive again 9 months after successful rifaximin treatment; older age, a past appendectomy and long-term PPI use were associated with recurrence (Lauritano 2008).
9. Prognosis
The prognosis for SIBO depends heavily on the underlying cause and the ability to address predisposing factors. In patients with correctable underlying causes (such as discontinuing PPIs, treating hypothyroidism, or surgical correction of anatomical abnormalities), SIBO is described as more likely to resolve without recurring. However, in patients with irreversible predisposing conditions (such as systemic sclerosis, diabetic autonomic neuropathy, or surgical blind loops), SIBO tends to be a chronic, relapsing condition requiring long-term management strategies.
A 2017 meta-analysis put the initial eradication rate for rifaximin at 70.8% by intention to treat (Gatta 2017), and a 2004 study found 80% normalization after 14 days of an elemental diet. Recurrence is common: 43.7% at 9 months in an Italian cohort (Lauritano 2008). Prokinetic therapy is used to delay relapse; in a 2009 chart review, low-dose erythromycin (50 mg nightly) was followed by an average of 138.5 symptom-free days against 59.7 days with no prevention, a difference that was not statistically significant (P = 0.08), while tegaserod was followed by 241.6 days (Pimentel 2009).
For patients with IBS-SIBO overlap, a 2000 study found that 48% of IBS patients whose overgrowth was eradicated no longer met Rome criteria for IBS (Pimentel 2000), and the 2017 meta-analysis found improvement or resolution of symptoms in 67.7% of patients whose SIBO was eradicated (Gatta 2017). Long-term management described in the literature combines dietary measures (low-FODMAP, meal spacing), prokinetic therapy, repeat breath testing, and retreatment with antibiotics or herbal antimicrobials.
10. Prevention
- MMC function: The MMC sweeps the small intestine between meals and is described as a main defense against SIBO; it is interrupted by food intake. Meal spacing and prokinetic agents are used on that reasoning (see Treatment).
- PPI use: Long-term proton pump inhibitor use was associated with SIBO recurrence after rifaximin in an Italian cohort (odds ratio 3.52) (Lauritano 2008). PPIs also treat conditions such as GERD, Barrett’s esophagus and Zollinger-Ellison syndrome, so decisions about stopping or reducing one belong with the prescriber.
- Hypothyroidism: Hypothyroidism slows intestinal motility and is listed among the risk factors above.
- Diabetes: Diabetic autonomic neuropathy and gastroparesis impair motility and are listed among the risk factors above.
- Antibiotic courses: While antibiotics treat SIBO, repeated or prolonged courses can disrupt the protective commensal microbiome and select resistant organisms.
- After gastroenteritis: Acute gastroenteritis (particularly from Campylobacter jejuni, Salmonella, Shigella, and E. coli) is described as a trigger of post-infectious IBS; in a rat model, Campylobacter jejuni infection was linked to antibodies against vinculin and to lasting changes in gut function (Pimentel 2015).
- Opioids: Opioids inhibit intestinal motility and MMC function, and chronic opioid use is listed among the risk factors above.
- Physical activity: Moderate exercise is described as promoting intestinal motility; no study cited here tested exercise for preventing SIBO.
- Psychological stress: Chronic stress is described as impairing MMC function through sympathetic nervous system and cortisol effects; no study cited here tested stress reduction for preventing SIBO.
11. Recent Research and Advances
The understanding and management of SIBO has evolved rapidly in recent years. The reclassification of methane-dominant SIBO as intestinal methanogen overgrowth (IMO) by Pimentel et al. (2020) reflects the recognition that methanogens (Methanobrevibacter smithii) are archaea, not bacteria, and that methanogen overgrowth can occur throughout the intestine, not just the small bowel. This reclassification has important implications for treatment algorithms and ongoing research.
Three-gas breath testing adds hydrogen sulfide to hydrogen and methane. Research has linked breath hydrogen sulfide with hydrogen sulfide-producing bacteria (including Desulfovibrio and Fusobacterium species) and with diarrhea-predominant IBS (Villanueva-Millan 2022). Bismuth subsalicylate, which binds hydrogen sulfide, reduced fecal hydrogen sulfide release by more than 95% in 10 healthy volunteers (Suarez 1998); it has not been tested in a published trial in hydrogen sulfide-dominant SIBO cited here.
The anti-vinculin and anti-CdtB antibody tests have been proposed as biomarkers for post-infectious IBS/SIBO, to identify patients whose symptoms developed after acute gastroenteritis; the vinculin link comes from work including a rat model of Campylobacter jejuni infection (Pimentel 2015). This has opened new avenues for understanding the pathogenesis of post-infectious functional gastrointestinal disorders. Lovastatin lactone, a form of a statin, has been proposed as an anti-methanogen; a 2016 review describes inhibition of archaeal membrane synthesis through HMG-CoA reductase and a possible direct effect on methanogenesis enzymes, and reported a phase 2 trial in IBS with constipation as in progress (Gottlieb 2016). Research into the small intestinal microbiome using capsule-based sampling devices and metagenomic sequencing is adding detail on the composition and metabolic activity of the small intestinal microbial community in health and SIBO.
Key Research Papers
Historical Background
The concept of bacterial overgrowth in the small intestine was first described in the context of surgically created blind loops in the early 20th century, with Faber reporting macrocytic anemia associated with intestinal stasis in 1897. The "blind loop syndrome" was formally characterized in the 1960s and 1970s by researchers including Tabaqchali and Booth, who demonstrated that bacterial overgrowth in surgically created blind loops caused vitamin B12 malabsorption and steatorrhea. The modern understanding of SIBO as a widespread clinical entity beyond the surgical context was significantly advanced by the work of Mark Pimentel at Cedars-Sinai Medical Center beginning in the early 2000s, whose research established the connection between SIBO and IBS, developed lactulose breath testing protocols, and demonstrated the efficacy of rifaximin for treatment.
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. American Journal of Gastroenterology. 2020;115(2):165-178. — doi:10.14309/ajg.0000000000000501
- Rezaie A, et al. Hydrogen and methane-based breath testing in gastrointestinal disorders: the North American Consensus. American Journal of Gastroenterology. 2017;112(5):775-784. — doi:10.1038/ajg.2017.46
- Pimentel M, et al. Rifaximin therapy for patients with irritable bowel syndrome without constipation (TARGET 1 and TARGET 2). New England Journal of Medicine. 2011;364(1):22-32. — doi:10.1056/NEJMoa1004409
- Ghoshal UC, Shukla R, Ghoshal U. Small intestinal bacterial overgrowth and irritable bowel syndrome: a bridge between functional organic dichotomy. Gut and Liver. 2017;11(2):196-208. — doi:10.5009/gnl16126
- Chedid V, et al. Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine. 2014;3(3):16-24. — doi:10.7453/gahmj.2014.019
- Pimentel M, et al. A 14-day elemental diet is highly effective in normalizing the lactulose breath test. Digestive Diseases and Sciences. 2004;49(1):73-77. — doi:10.1023/b:ddas.0000011605.43979.e1
- Pimentel M, et al. A link between irritable bowel syndrome and fibromyalgia may be related to findings on lactulose breath testing. Annals of the Rheumatic Diseases. 2004;63(4):450-452. — doi:10.1136/ard.2003.011502
- Lin HC. Small intestinal bacterial overgrowth: a framework for understanding irritable bowel syndrome. JAMA. 2004;292(7):852-858. — doi:10.1001/jama.292.7.852
- Pimentel M, et al. Methane, a gas produced by enteric bacteria, slows intestinal transit and augments small intestinal contractile activity. American Journal of Physiology. 2006;290(6):G1089-G1095. — doi:10.1152/ajpgi.00574.2004
- Bures J, et al. Small intestinal bacterial overgrowth syndrome. World Journal of Gastroenterology. 2010;16(24):2978-2990. — doi:10.3748/wjg.v16.i24.2978
- Dukowicz AC, Lacy BE, Levine GM. Small intestinal bacterial overgrowth: a comprehensive review. Gastroenterology and Hepatology. 2007;3(2):112-122. — PubMed PMID: 21960820
- Pimentel M, et al. Autoimmunity links vinculin to the pathophysiology of chronic functional bowel changes following Campylobacter jejuni infection in a rat model. Digestive Diseases and Sciences. 2015;60(5):1195-1205. — doi:10.1007/s10620-014-3435-5
- Takakura W, Pimentel M. Small intestinal bacterial overgrowth and irritable bowel syndrome: an update. Frontiers in Psychiatry. 2020;11:664. — doi:10.3389/fpsyt.2020.00664
- Singer-Englar T, Rezaie A, Gupta K, et al. Competitive hydrogen gas utilization by methane- and hydrogen sulfide-producing microorganisms and associated symptoms: results of a novel 4-gas breath test machine. Gastroenterology. 2018;154(6 Suppl 1):S-47 (meeting abstract 182). — doi:10.1016/s0016-5085(18)30625-5 (Replaces an entry, “Singer-Englar T, et al. (2022), Validation of a hydrogen and methane and hydrogen sulfide breath test device, Clinical Gastroenterology and Hepatology 20(7):e1488–e1497,” that could not be found in PubMed; its DOI belonged to an unrelated paper on liver disease.)
- Gatta L, Scarpignato C. Systematic review with meta-analysis: rifaximin is effective and safe for the treatment of small intestine bacterial overgrowth. Alimentary Pharmacology and Therapeutics. 2017;45(5):604-616. — PubMed PMID: 28078798
- Low K, Hwang L, Hua J, et al. A combination of rifaximin and neomycin is most effective in treating irritable bowel syndrome patients with methane on lactulose breath test. Journal of Clinical Gastroenterology. 2010;44(8):547-550. — PubMed PMID: 19996983
- Furnari M, Parodi A, Gemignani L, et al. Clinical trial: the combination of rifaximin with partially hydrolysed guar gum is more effective than rifaximin alone in eradicating small intestinal bacterial overgrowth. Alimentary Pharmacology and Therapeutics. 2010;32(8):1000-1006. — PubMed PMID: 20937045
- Yang J, Lee HR, Low K, et al. Rifaximin versus other antibiotics in the primary treatment and retreatment of bacterial overgrowth in IBS. Digestive Diseases and Sciences. 2008;53(1):169-174. — PubMed PMID: 17520365
- Lauritano EC, Gabrielli M, Scarpellini E, et al. Small intestinal bacterial overgrowth recurrence after antibiotic therapy. American Journal of Gastroenterology. 2008;103(8):2031-2035. — PubMed PMID: 18802998
- Pimentel M, Morales W, Lezcano S, et al. Low-dose nocturnal tegaserod or erythromycin delays symptom recurrence after treatment of irritable bowel syndrome based on presumed bacterial overgrowth. Gastroenterology & Hepatology (N Y). 2009;5(6):435-442. — PubMed PMID: 20574504
- Pimentel M, Chow EJ, Lin HC. Eradication of small intestinal bacterial overgrowth reduces symptoms of irritable bowel syndrome. American Journal of Gastroenterology. 2000;95(12):3503-3506. — PubMed PMID: 11151884
- Guo Y, Chen Y, Tan ZR, Klaassen CD, Zhou HH. Repeated administration of berberine inhibits cytochromes P450 in humans. European Journal of Clinical Pharmacology. 2012;68(2):213-217. — PubMed PMID: 21870106
- Villanueva-Millan MJ, Leite G, Wang J, et al. Methanogens and hydrogen sulfide producing bacteria guide distinct gut microbe profiles and irritable bowel syndrome subtypes. American Journal of Gastroenterology. 2022;117(12):2055-2066. — PubMed PMID: 36114762
- Suarez FL, Furne JK, Springfield J, Levitt MD. Bismuth subsalicylate markedly decreases hydrogen sulfide release in the human colon. Gastroenterology. 1998;114(5):923-929. — PubMed PMID: 9558280
- Gottlieb K, Wacher V, Sliman J, Pimentel M. Review article: inhibition of methanogenic archaea by statins as a targeted management strategy for constipation and related disorders. Alimentary Pharmacology and Therapeutics. 2016;43(2):197-212. — PubMed PMID: 26559904
- US Food and Drug Administration. Rifaximin tablets: US prescribing information (FDA-approved label), DailyMed, version published January 2026. — DailyMed setid c5e8e2fd-7087-4b78-9181-cc259c0be2f1
PubMed Topic Searches
Curated PubMed topic searches of peer-reviewed literature on Small Intestinal Bacterial Overgrowth (SIBO). Each link opens a live PubMed query so you always see the most current studies.
- PubMed: SIBO diagnosis
- PubMed: Rifaximin for SIBO
- PubMed: Hydrogen breath testing
- PubMed: SIBO and IBS overlap
- PubMed: Methane/IMO
- PubMed: PPI and SIBO
- PubMed: Prokinetics and motility
- PubMed: Elemental diet for SIBO
- PubMed: Low-FODMAP diet and SIBO
- PubMed: SIBO recurrence
- PubMed: SIBO in scleroderma
- PubMed: Short bowel syndrome and SIBO
Herbs Traditionally Used for SIBO
The coloured half of every capsule shows how much human evidence supports that herb for this condition. None of these replace a diagnosis, and the marked cautions are there because the harm is documented.
Connections
- Gastroenterology
- Prebiotics — why prebiotic fibers can backfire in SIBO, and how to reintroduce
- The Gut Barrier & Your Microbiome — interactive animation
- IMO and Constipation
- Elemental Diet
- Herbal Antimicrobials
- Rifaximin for SIBO
- Root Causes
- Breath Test Guide
- Prokinetics and Relapse Prevention
- Low-FODMAP Diet
- Hydrogen vs Methane vs Hydrogen Sulfide
- Irritable Bowel Syndrome
- IBS and SIBO Overlap
- Celiac Disease
- Inflammatory Bowel Disease
- POTS
- MCAS
- Thyroid Disorders
- Berberine
- Elimination Diet
- High Resistant Starch Foods — food rankings by RS grams per serving, the cook-and-cool RS3 protocol, a daily ~20g meal plan, and butyrate/SCFA mechanism.
- Yeast Infections
- Herbs covered on this site that discuss this condition: Elecampane · Goldenseal (Hydrastis canadensis) · Oregano (Origanum vulgare) · Peppermint (Mentha × piperita) · Wormwood · Coriander Seeds (Coriandrum sativum)
- All Conditions — the complete index of diseases covered on this site.