Elemental Diet for Small Intestinal Bacterial Overgrowth (SIBO)
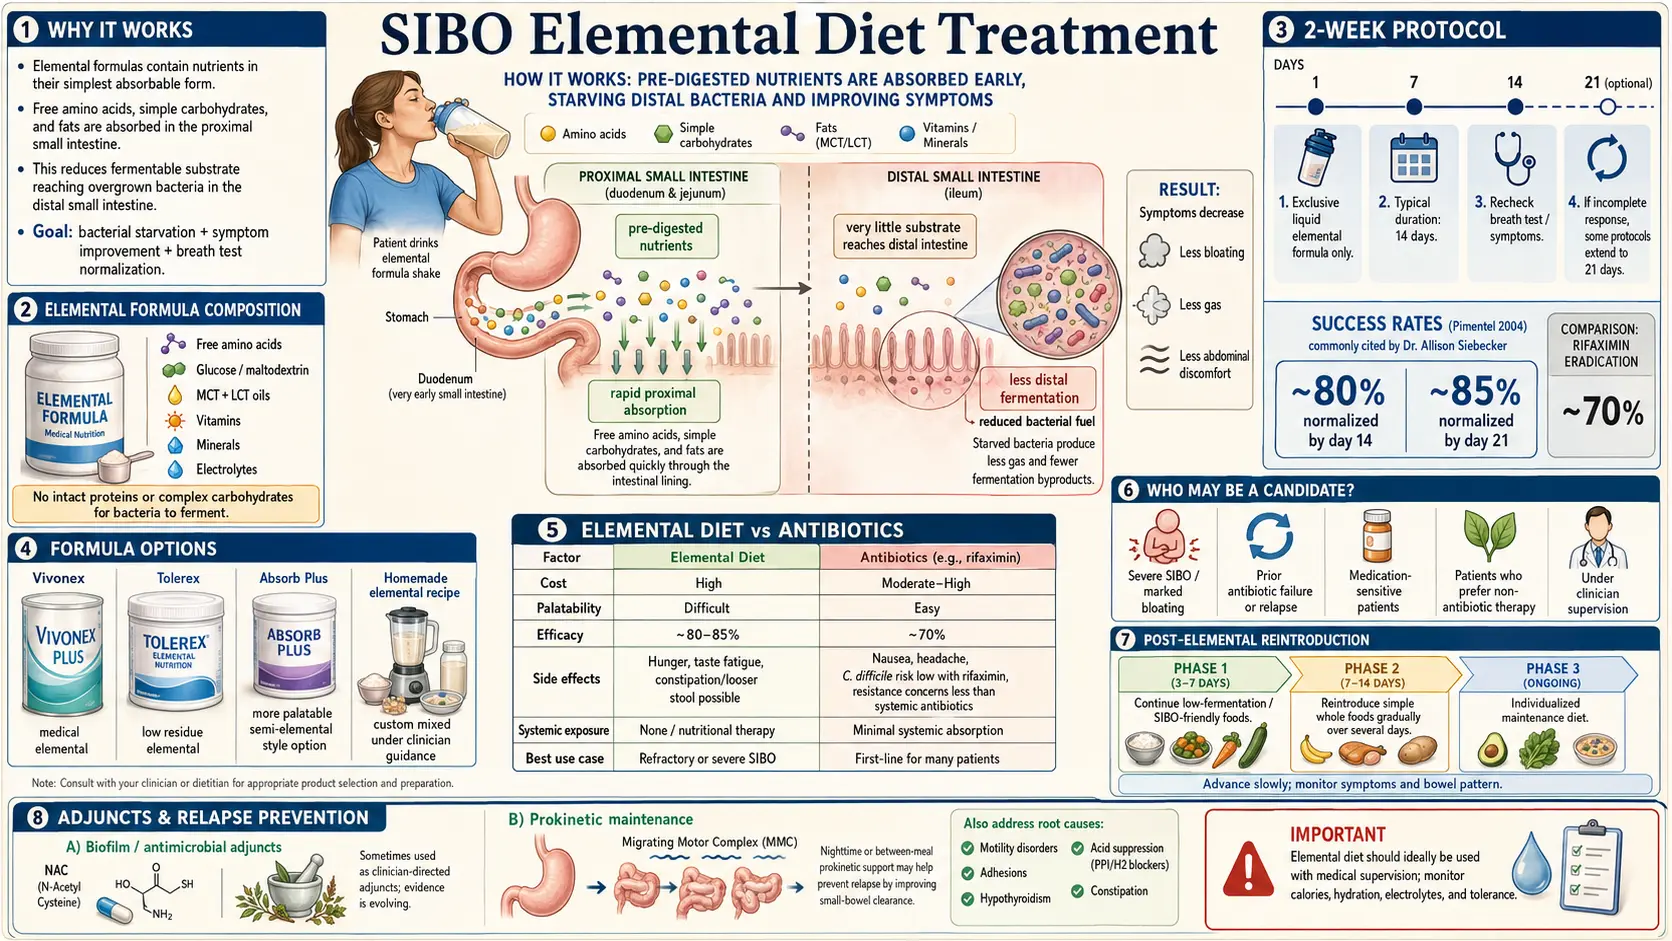
In an uncontrolled series of 93 patients, the elemental diet normalized the breath test for small intestinal bacterial overgrowth (SIBO) in 80% by day 15 — and it is also one of the hardest treatments to get through. Two weeks of a liquid-only medical formula, no food, no social meals, no coffee breaks with a pastry. This article covers how it works, who it is used for, what kinds of product exist, how to make it yourself, and what the two weeks actually feel like.
Interactive Visualization The Gut Barrier & Your Microbiome Watch fibre become butyrate and butyrate tighten the gut wall — then starve the microbes and see them eat your mucus layer instead. Launch →
Table of Contents
- How the Elemental Diet Works
- The Success Rate — What the Research Shows
- Who the Elemental Diet Is For
- Who It’s NOT For
- Commercial Products — What’s Available
- Homemade Elemental Diet Recipe
- What the Two Weeks Actually Look Like
- Palatability Hacks
- Breaking the Diet Safely (Refeeding)
- Partial and Semi-Elemental Approaches
- Why Relapse Happens After Elemental
- Key Research Papers
- Featured Videos
1. How the Elemental Diet Works
The elemental diet is a medical liquid formula of pre-digested nutrition. Instead of intact protein, it contains free amino acids. Instead of starches and complex carbohydrates, it contains monosaccharides — mostly dextrose (glucose) and maltodextrin. Instead of long-chain fats that require bile salts and pancreatic lipase to break down, it uses primarily medium-chain triglycerides (MCTs), with a small amount of long-chain fat to prevent essential fatty acid deficiency. A full spectrum of vitamins, minerals, and electrolytes rounds it out.
The key is where this mixture gets absorbed. Free amino acids and monosaccharides are absorbed in the proximal jejunum — roughly the first 20 inches of small intestine beyond the stomach. MCTs are absorbed even more proximally, often directly across the intestinal wall into the portal circulation without needing bile. By the time the formula has moved past the first foot or so of small intestine, there is essentially nothing left to feed bacteria. The overgrowth population downstream — in the distal jejunum, ileum, and especially any pockets of stasis — runs out of substrate.
Bacteria do not starve instantly. They consume residual mucus glycoproteins and shed epithelial cells for a few days. But with no dietary carbohydrate, protein, or fiber reaching them, populations collapse over the course of 10–14 days. This is also why the diet must be exclusive: a single piece of toast — a few grams of starch reaching the lower small bowel — resets the clock.
2. The Success Rate — What the Research Shows
The foundational data comes from Pimentel et al. (2004), published in Digestive Diseases and Sciences. In an uncontrolled series of 93 consecutive patients with irritable bowel syndrome (IBS) and a positive lactulose breath test (everyone received the diet; there was no comparison group), a 14-day exclusive elemental diet normalized the breath test in 80% of patients. Extending to 21 days pushed normalization to 85%. Symptom improvement tracked the breath-test response.
Because the series had no comparison arm, it does not show how the diet compares head-to-head with other treatments. In a separate 2014 study of 104 patients with follow-up breath tests, the breath test turned negative in 34% (23 of 67) after rifaximin 1,200 mg a day for 4 weeks and in 46% (17 of 37) after herbal therapy. For refractory cases — patients who have already failed two or more rounds of rifaximin or herbals — practitioners report that the elemental diet is often the intervention that finally clears the overgrowth.
The catch: the 80–85% figure is in patients who completed the protocol. Completion rates in real-world use are significantly lower, because the diet is genuinely hard to get through. Clinician estimates put real-world completion somewhere between 50% and 75%, depending on support, product chosen, and patient circumstances.
3. Who the Elemental Diet Is For
- Patients who have failed two or more rounds of rifaximin or herbal antimicrobials and still have a positive breath test.
- Methane-dominant overgrowth, called intestinal methanogen overgrowth (IMO), that will not respond to rifaximin+neomycin or allicin-based herbal protocols. Methanogens are notoriously stubborn, and substrate starvation often works where antimicrobials don’t.
- Severe cases with documented malabsorption and malnutrition — the formula simultaneously treats the overgrowth and restores nutritional status, because it’s absorbed before bacteria can compete for it.
- Patients who cannot tolerate antibiotics (prior C. difficile, severe drug allergies, significant drug interactions).
- Patients who have made an informed choice to avoid antibiotics for personal or medical reasons.
- Refractory cases being prepared for retesting and rescue protocols — a 2-week elemental reset before a fresh breath test can clarify whether the overgrowth is truly the problem.
4. Who It’s NOT For
- History of anorexia, bulimia, or any eating disorder. Two weeks of liquid-only caloric restriction, constant hunger, rapid weight loss, and obsessive measurement is psychologically dangerous and can trigger relapse of the eating disorder. Practitioners treat this as a hard contraindication, not a cautious footnote.
- Diabetes (type 1 or type 2). The formula is mostly monosaccharide carbohydrate — essentially glucose with some amino acids. Blood sugar excursions are severe, insulin dosing becomes extremely difficult, and hypoglycemia between feeds is a real risk. Where it has been attempted, practitioners describe close endocrinology supervision and continuous glucose monitoring.
- Pregnancy and lactation. Not studied; caloric and micronutrient margins are too thin for fetal development.
- Chronic kidney disease requiring protein restriction. Free amino acid loads are handled differently than whole protein and can stress a compromised kidney.
- Patients without social or home support. Patients describe doing this alone — cooking for the family while drinking a chalky beverage, watching everyone eat, handling a full work week at peak hunger on day 4 — as brutal, and practitioners report that people who try it solo are the ones most likely to quit around day 5.
- Children and adolescents outside a pediatric gastrointestinal (GI) program.
5. Commercial Products — What’s Available
Four kinds of product are in common use. They differ in cost, palatability, whether they are strictly “elemental” (free amino acids) or “semi-elemental” (partially hydrolyzed protein), and whether they were designed for small intestinal bacterial overgrowth or for something else.
| Product | Type | Cost (14 days) | Palatability | Notes |
|---|---|---|---|---|
| Prescription amino-acid-based elemental formula | True elemental (free amino acids) | ~$1,260 (~$15/packet × 6/day) | Patients often describe a strong amino acid taste that is hard to drink | The original medical elemental formula. Cheapest strictly-elemental option. Designed for short-bowel and critical care, repurposed for small intestinal bacterial overgrowth. |
| Over-the-counter elemental powder | True elemental | ~$660 (~$110 × 6 containers) | Described as somewhat easier to drink, still chalky | Formulated specifically for small intestinal bacterial overgrowth by functional gastrointestinal practitioners. Available dextrose-free version for candida concerns. |
| Semi-elemental hydrolysed whey formula | Semi-elemental (partially hydrolyzed whey) | ~$400–600 | Usually described as the easiest of these to drink | Not strictly elemental — the protein is hydrolyzed, not broken into free amino acids. Better compliance in practice, slightly lower theoretical efficacy. |
| Pediatric amino acid formulas | True elemental (pediatric) | Variable, often insurance-covered for pediatric gastrointestinal | Flavored, more tolerable | Pediatric formulas used off-label in adults. Lower calorie density means drinking more volume. |
Insurance coverage for adult small intestinal bacterial overgrowth is rare. Some functional medicine clinics buy wholesale and pass savings along. The prescription elemental formula and the pediatric amino acid formulas are occasionally covered under medical-food benefits with a prescription and diagnostic codes.
6. Homemade Elemental Diet Recipe
Homemade elemental diets cost a fraction of commercial formulas (~$100–200 for two weeks) but are less validated in trials. Strict interpretation requires free-form amino acid powder, not protein isolate — because even a pure whey isolate is still intact protein that needs enzymatic breakdown. That said, many practitioners use whey protein isolate successfully in practice, especially for the semi-elemental variant.
Typical Homemade Protocol Ingredients (per day, for a ~70 kg / 154 lb adult)
- Protein: 80–100 g free amino acid powder (or whey protein isolate, NOT concentrate) — split across 6 feeds
- Carbohydrate: 250–300 g dextrose (glucose) powder — this is the bulk of the calories
- Fat: 40–60 g MCT oil, plus a small amount of long-chain fat that supplies the essential fatty acids MCT oil lacks
- Multivitamin/mineral: a full-spectrum powdered multi (liquid or crushed-tablet form); gummies are left out because they contain sugar alcohols and gelatin
- Electrolytes: ~3–5 g sodium (sea salt), 2–3 g potassium (potassium chloride salt substitute), 300–400 mg magnesium glycinate
- Water: ~3 liters across all feeds plus between-meal hydration
Daily Macros Target
- Calories: ~1,800–2,200 kcal/day split across 6 feeds (~300–370 kcal each)
- Protein: ~80–100 g (roughly 1.2 g/kg body weight, on the low end to minimize nitrogen load)
- Carbohydrate: ~250–300 g (the dominant fuel source)
- Fat: ~55–75 g (mostly MCT)
Mixing
In these protocols each feed is blended in a shaker or blender with 10–14 oz cold water and drunk within 15–20 minutes, because amino acid solutions taste worse as they warm. Feeds are spaced every 2–3 hours with no snacks between them; water, plain tea, and clear broth are allowed.
Caveat. Homemade protocols have less trial data than commercial elemental formulas. Practitioners describe commercial products as more predictable for refractory small intestinal bacterial overgrowth, where a patient may get only one attempt at the two weeks, and homemade versions as more often used for repeat protocols, semi-elemental approaches, or by people with severe cost constraints.
7. What the Two Weeks Actually Look Like
Honest day-by-day, based on patient reports and clinical observation:
- Days 1–2: Novelty holds you. You feel fine. Hunger is manageable.
- Days 3–4: The worst stretch. Hunger peaks. You are not yet in ketosis, your stored glycogen is depleted, and your body is still expecting real food. Irritability, headaches, and obsessive food thoughts are common. Most people who quit, quit here.
- Day 5: Mild ketosis sets in (despite the carbohydrate load, because total calories are below baseline for most adults). Hunger blunts noticeably.
- Day 7: Energy often stabilizes. Bloating is noticeably down. Many people report their first day of flat abdomen in years.
- Days 8–10: Mental steadiness. Food cravings shift from “I need to eat” to a more detached awareness.
- Days 11–14: Physically easier but psychologically grinding. You want to chew something.
Constipation is common during the protocol — not because of slowed transit, but because with bacterial populations and fiber intake both collapsing, there is genuinely less stool to pass. One bowel movement every 3–4 days is normal. Protocols do not add fiber to “fix” this, because fiber would feed the bacteria the diet is starving.
Social isolation is the underrated cost. No meals with family. No coffee meetings. No work lunches. Patients describe planning for it: telling people in advance, choosing a low-social two weeks (not the holidays), and not scheduling anything food-adjacent. Broth, plain tea, plain coffee (if tolerated), and water are allowed between feeds. Patients report that a cup of warm water with a pinch of salt helps both hydration and the psychological need for “something warm.”
8. Palatability Hacks
- Cold. Patients chill the formula overnight in the fridge; cold mutes the amino acid bitterness.
- Fast. Patients report drinking each feed in 10–15 minutes rather than sipping it over 45.
- Straw. A straw bypasses most of the taste buds. Patients describe this single change as what makes the strongest-tasting formulas tolerable.
- Stevia + vanilla + cinnamon. Pure stevia extract (no erythritol or other sugar alcohols, which ferment), a few drops of vanilla extract, and a shake of cinnamon transform the flavor without adding fermentable substrate.
- Pinch of salt. Counterintuitive, but a small amount of salt blunts bitter amino acids the way it does in cooking.
- Water only. Protocols mix the formula with water, not milk, juice, or anything creamy, because any fermentable substrate defeats the protocol.
9. Breaking the Diet Safely (Refeeding)
Practitioners describe the first week back as being as important as the two weeks of the diet. After two weeks without whole food, bacterial populations are at their lowest point since the overgrowth began, and practitioners warn that a disordered small-bowel microbiome can re-seed within 48 hours of heavy, fermentable eating. A typical refeeding schedule they describe:
- Days 15–17: Bone broth, simple steamed proteins (white fish, poached chicken, eggs), plain white rice, well-cooked zucchini or carrots. Small portions, 4–5 meals spaced 4 hours apart. No raw vegetables, no beans, no dairy yet, no fermented foods, no alcohol.
- Days 18–21: Expand to cooked low-FODMAP vegetables (low in fermentable oligo-, di- and monosaccharides and polyols, the short-chain carbohydrates gut bacteria ferment), additional proteins, moderate fat. Still no fiber bombs, no FODMAP triggers, no alcohol.
- Week 2 post-diet: Begin structured low-FODMAP reintroduction to identify personal triggers.
- Week 3 onward: Gradually expand toward a normal, whole-food diet you can actually live on.
Practitioner protocols start a prokinetic (a medicine or herb that stimulates gut movement) by day 15. Practitioners consider this the single biggest determinant of whether the elemental diet holds, and describe low-dose naltrexone, prucalopride, low-dose erythromycin, or a structured ginger protocol being in place before the first real meal. For comparison, in a 2008 study of 80 patients whose overgrowth had cleared with rifaximin, the breath test was positive again in 12.6% at 3 months, 27.5% at 6 months and 43.7% at 9 months; that study did not include elemental-diet patients. See Prokinetics and Relapse Prevention.
10. Partial and Semi-Elemental Approaches
Not everyone needs — or can do — a full 14-day exclusive protocol. Several modified versions exist:
- Half-elemental. Elemental formula replaces 2 of 3 daily meals, with one real, low-FODMAP meal per day, for 2–4 weeks. Much more sustainable. Reported eradication rates are lower (roughly 50–60%) but still meaningful for moderate cases.
- Rotating protocols. 5 days elemental, 2 days simple real food, repeated for 3–4 weeks. Preserves social life and motivation at the cost of slower bacterial starvation.
- Mini-elemental weekend resets. Friday evening through Sunday evening on elemental formula, repeated once monthly, as a maintenance tool after a full protocol or antibiotic course.
- Semi-elemental (hydrolysed whey formulas). Partially hydrolyzed whey protein instead of free amino acids. More palatable, better compliance, slightly less efficacy on paper.
11. Why Relapse Happens After Elemental
The elemental diet clears the overgrowth. It does not fix why the overgrowth happened. If your migrating motor complex (MMC) is impaired — from post-infectious autoimmunity, hypothyroidism, diabetic autonomic neuropathy, chronic opioid use, or structural issues — bacteria will recolonize the small intestine within weeks to months, no matter how clean you got it.
Practitioners point to two interventions to reduce post-elemental relapse:
- Prokinetic therapy started on the first day of refeeding and continued for at least 3–6 months in practitioner protocols. See Prokinetics and Relapse Prevention.
- Treating the root cause. Proton pump inhibitors (PPIs) discontinued where possible, thyroid optimized, glucose controlled, opioids weaned, structural issues evaluated. See Root Causes.
An elemental diet without follow-through is a very expensive, very unpleasant temporary reset.
Key Research Papers
Peer-reviewed evidence supporting the elemental diet as a 14- to 21-day intervention for refractory small intestinal bacterial overgrowth, plus related work on enteral nutrition and bowel rest. Each citation ends with its DOI or PubMed link.
- Pimentel M, Constantino T, Kong Y, Bajwa M, Rezaei A, Park S. A 14-Day Elemental Diet Is Highly Effective in Normalizing the Lactulose Breath Test. Digestive Diseases and Sciences. 2004;49(1):73–77. — doi:10.1023/B:DDAS.0000011605.43979.e1
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. American Journal of Gastroenterology. 2020;115(2):165–178. — doi:10.14309/ajg.0000000000000501
- Rezaie A, Buresi M, Lembo A, et al. Hydrogen and Methane-Based Breath Testing in Gastrointestinal Disorders: The North American Consensus. American Journal of Gastroenterology. 2017;112(5):775–784. — doi:10.1038/ajg.2017.46
- Pimentel M, Chow EJ, Lin HC. Eradication of Small Intestinal Bacterial Overgrowth Reduces Symptoms of Irritable Bowel Syndrome. American Journal of Gastroenterology. 2000;95(12):3503–3506. — doi:10.1111/j.1572-0241.2000.03368.x
- Olendzki BC, Silverstein TD, Persuitte GM, Ma Y, Baldwin KR, Cave D. An Anti-Inflammatory Diet as Treatment for Inflammatory Bowel Disease: A Case Series Report. Nutrition Journal. 2014;13:5. — doi:10.1186/1475-2891-13-5
- O'Morain C, Segal AW, Levi AJ. Elemental Diet as Primary Treatment of Acute Crohn's Disease: A Controlled Trial. British Medical Journal. 1984;288(6434):1859–1862. — doi:10.1136/bmj.288.6434.1859
- Zoli G, Care M, Parazza M, et al. A Randomized Controlled Study Comparing Elemental Diet and Steroid Treatment in Crohn's Disease. Alimentary Pharmacology & Therapeutics. 1997;11(4):735–740. — doi:10.1046/j.1365-2036.1997.t01-1-00192.x
- Chedid V, Dhalla S, Clarke JO, et al. Herbal Therapy Is Equivalent to Rifaximin for the Treatment of Small Intestinal Bacterial Overgrowth. Global Advances in Health and Medicine. 2014;3(3):16–24. — doi:10.7453/gahmj.2014.019
- Pimentel M, Park S, Mirocha J, Kane SV, Kong Y. The Effect of a Nonabsorbed Oral Antibiotic (Rifaximin) on the Symptoms of the Irritable Bowel Syndrome: A Randomized Trial. Annals of Internal Medicine. 2006;145(8):557–563. — doi:10.7326/0003-4819-145-8-200610170-00004
- Bures J, Cyrany J, Kohoutova D, et al. Small Intestinal Bacterial Overgrowth Syndrome. World Journal of Gastroenterology. 2010;16(24):2978–2990. — doi:10.3748/wjg.v16.i24.2978
- Lauritano EC, Gabrielli M, Scarpellini E, et al. Small Intestinal Bacterial Overgrowth Recurrence after Antibiotic Therapy. American Journal of Gastroenterology. 2008;103(8):2031–2035. — PubMed PMID: 18802998
- Quigley EMM. The Spectrum of Small Intestinal Bacterial Overgrowth (SIBO). Current Gastroenterology Reports. 2019;21(1):3. — PubMed PMID: 30645678
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: elemental diet and SIBO
- PubMed: elemental diet and lactulose breath test
- PubMed: elemental nutrition and small bowel
- PubMed: amino acid formula and bacterial overgrowth
- PubMed: semi-elemental diet and bacterial overgrowth
- PubMed: elemental diet for methane / IMO
- PubMed: elemental diet refeeding
- PubMed: elemental diet and IBS
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Small Intestinal Bacterial Overgrowth Overview
- Prokinetics and Relapse Prevention
- Root Causes
- Herbal Antimicrobials
- Rifaximin Protocols
- Low-FODMAP Diet
- Hydrogen vs Methane vs Hydrogen Sulfide
- Breath Test Guide
- IMO and Constipation
- Irritable Bowel Syndrome
- Celiac Disease
- Elimination Diet
- Gut Healing
- Probiotics
- Crohn's Disease
- Bloating
- Bone Broth
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap