Low-FODMAP Diet for Small Intestinal Bacterial Overgrowth (SIBO)
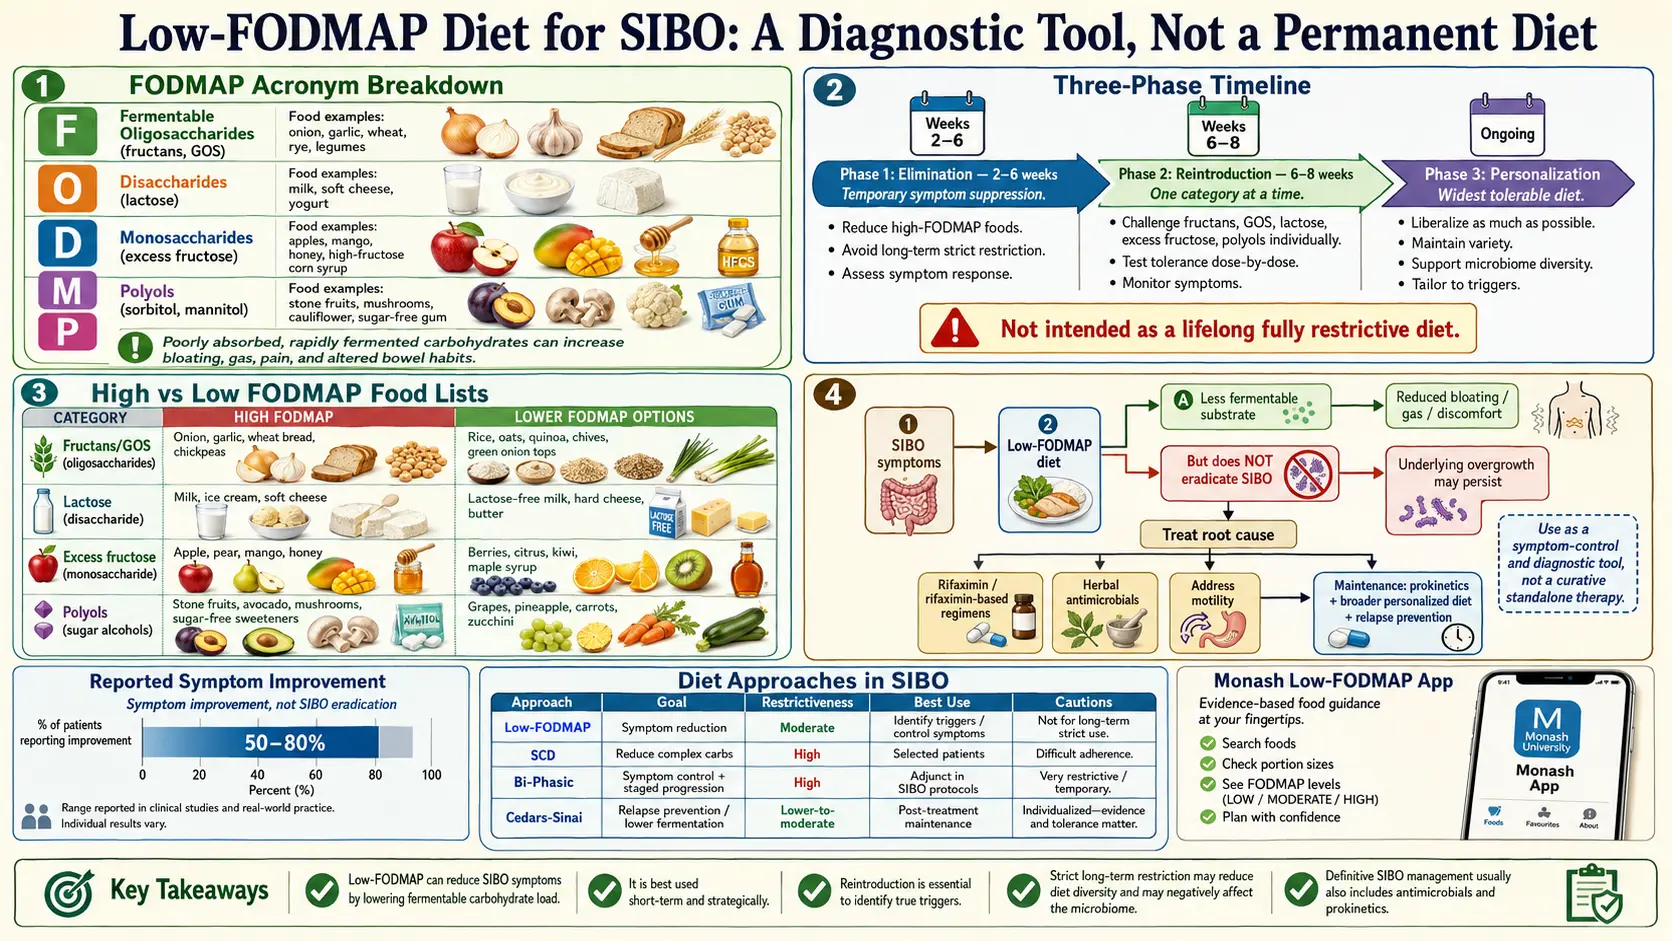
Many people are handed a one-page FODMAP list and little else. The low-FODMAP diet, as its developers describe it, is a diagnostic tool with three distinct phases, not a permanent way of eating, and the middle phase (the one almost everyone skips) is where the real answers live. Here is the whole map, written for tired people who are reading this in the cereal aisle.
Interactive Visualization The Gut Barrier & Your Microbiome Watch fibre become butyrate and butyrate tighten the gut wall — then starve the microbes and see them eat your mucus layer instead. Launch →Table of Contents
- What FODMAP Even Means
- The Three Phases (This Is Important)
- The FODMAP Categories, with Food Lists
- A Sample Low-FODMAP Day
- Why the Research Raises Concern About Staying Low-FODMAP Long-Term
- Low-FODMAP vs. SCD vs. Bi-Phasic Diet
- Why Diet Alone Doesn't Cure Small Intestinal Bacterial Overgrowth
- Apps and Resources
- Working with a Dietitian
- Key Research Papers
- Connections
- Featured Videos
1. What FODMAP Even Means
FODMAP is an acronym — not a food group, not a toxin, just a cluster of carbohydrate shapes that share one inconvenient property. It stands for Fermentable Oligosaccharides, Disaccharides, Monosaccharides And Polyols. These are short-chain carbohydrates that the human small intestine absorbs poorly (or not at all) but that bacteria absolutely love.
The concept was developed at Monash University in Melbourne, Australia, by gastroenterologist Peter Gibson and dietitian Sue Shepherd around 2005. Their 2005 paper proposed the "FODMAP hypothesis" for Crohn's disease: that too many poorly absorbed short-chain carbohydrates reaching the lower small intestine and the colon are rapidly fermented there. The diet was then developed for irritable bowel syndrome and later applied to small intestinal bacterial overgrowth (SIBO), on a simple rationale: if the small intestine harbors excess bacteria that ferment carbohydrates into hydrogen, methane, and hydrogen sulfide, then removing the substrate removes the gas, bloating, and pain.
Low-FODMAP is not about eating "healthier." It is about starving bacteria of their favorite fuel long enough to quiet symptoms and to find out which specific fuels a person's bacteria overreact to. A banana is a perfectly healthy food. In someone with small intestinal bacterial overgrowth, a ripe banana becomes a buffet.
2. The Three Phases (This Is Important)
This is the section most people never hear about. The low-FODMAP diet is a three-phase protocol. Most patients only ever do Phase 1, stay on it for months or years, and wonder why they feel worse. This is how the protocol is designed.
Phase 1: Elimination (2 to 6 weeks — not longer)
Phase 1 removes all high-FODMAP foods, every category, strictly, for 2 to 6 weeks. The goal is to reach a clear symptom baseline — a quieter gut, less bloating, more predictable bowel movements. If symptoms do not improve at all after 4 weeks of strict elimination, FODMAPs are probably not the main driver, and the protocol stops there for a rethink of the cause.
Phase 1 is not designed to last indefinitely. It is diagnostic. It is the equivalent of turning off every appliance in the house to see which one was tripping the breaker — useful for a day, not a way to live.
Phase 2: Reintroduction / Challenge (6 to 8 weeks)
This is the most-skipped and the most important phase. Once symptoms have stabilized, one FODMAP category at a time is reintroduced, over three days, while the body's response is recorded. A typical challenge looks like this:
- Day 1: small serving of the test food (for example, 1/4 avocado for polyols).
- Day 2: medium serving (1/2 avocado).
- Day 3: normal serving (whole avocado).
- Then 2 to 3 washout days of strict low-FODMAP before challenging the next category.
The challenge does not test whether a food is "good" or "bad." It measures a personal dose threshold for each category. Most people tolerate some FODMAPs fine and react strongly to only one or two.
Phase 3: Personalization
Phase 2 produces a map — for example, that a person tolerates lactose and polyols but reacts badly to fructans. Phase 3 is the long-term diet built from that map: normal eating, with only that person's trigger FODMAPs restricted, and tolerance re-tested every few months because tolerance changes as small intestinal bacterial overgrowth is treated.
The aim of the protocol is the widest diet a person can eat comfortably — not the narrowest.
3. The FODMAP Categories, with Food Lists
Each FODMAP subgroup has its own biology and its own food list. The lists below are representative, not exhaustive; Monash University publishes lab-tested ratings for specific foods and serving sizes in its food-rating app.
Fructans (Oligosaccharides)
Chains of fructose. Humans do not produce the enzyme to break them down, so everyone ferments fructans to some degree — the question is how much. Fructans are the single biggest symptom driver in most small intestinal bacterial overgrowth patients.
- High (removed in Phase 1): wheat, rye, barley, garlic, onion, leek, shallots, scallions (white part), artichokes, chicory root, inulin-fortified foods.
- Low (allowed): firm/green banana, carrot, bell pepper, cucumber, potato, rice, oats, quinoa, scallion greens, garlic-infused oil (the fructans are water-soluble, not oil-soluble).
GOS (Galacto-oligosaccharides)
Short chains of galactose found mainly in legumes. Like fructans, humans cannot digest them — which is why beans produce gas in basically everyone.
- High: lentils, chickpeas, kidney beans, black beans, soybeans, cashews, pistachios.
- Low: canned and well-drained lentils or chickpeas (draining removes much of the GOS), firm tofu, tempeh, peanuts, macadamia nuts, walnuts.
Lactose (Disaccharide)
Milk sugar. Roughly 65% of adults worldwide are lactase-deficient to some degree, so this one is often already familiar.
- High: cow's milk, goat's milk, soft cheese (ricotta, cottage, cream cheese), yogurt, ice cream, custard.
- Low: lactose-free milk, hard aged cheeses (cheddar, parmesan, Swiss — the aging process digests the lactose), butter, lactose-free yogurt, almond/coconut milk.
Fructose in Excess (Monosaccharide)
Fructose is only a FODMAP when it exists in excess of glucose in the same food. Glucose helps fructose absorb; an imbalance leaves fructose stranded in the gut to be fermented.
- High: honey, apples, pears, mango, watermelon, high-fructose corn syrup, agave, dried fruit, fruit juice concentrates.
- Low: strawberries, blueberries, raspberries, oranges, grapes, kiwi, pineapple, cantaloupe, table sugar (sucrose is balanced 1:1).
Polyols (Sorbitol and Mannitol)
Sugar alcohols. Poorly absorbed by design — which is why sugar-free gum gives most people diarrhea.
- High (sorbitol): apples, pears, stone fruits (peaches, plums, cherries, apricots, nectarines), blackberries, avocado (more than 1/8), sugar-free gum and mints (sorbitol, xylitol, maltitol, isomalt).
- High (mannitol): mushrooms, cauliflower, snow peas, celery, sweet potato (large servings).
- Low: grapes, kiwi, strawberries, zucchini, carrots, cucumber, spinach, lettuce, green beans.
4. A Sample Low-FODMAP Day
Phase 1 does not have to be grim. Here is what a normal day can look like:
- Breakfast: oatmeal cooked in lactose-free milk, topped with blueberries, a handful of walnuts, and a drizzle of maple syrup. Black coffee or green tea.
- Mid-morning snack: a firm banana and a small handful of peanuts, or a rice cake with peanut butter.
- Lunch: grilled chicken over rice with roasted carrots, zucchini, and bell peppers, dressed with olive oil, lemon, salt, and a splash of garlic-infused oil for flavor.
- Afternoon snack: carrot sticks with lactose-free Greek yogurt dip, or a square of dark chocolate (some brands add inulin).
- Dinner: pan-seared salmon, mashed potato with butter and chives (green part only), sauteed spinach with garlic-infused oil.
- Dessert: strawberries with a scoop of lactose-free vanilla ice cream.
- Drinks all day: water, black/green tea, peppermint tea, coffee (dairy adds lactose), still or sparkling water with lemon.
That is three meals, three snacks, and every major food group — no garlic, no onion, no wheat, no apples, no milk, and not a shred of deprivation.
5. Why the Research Raises Concern About Staying Low-FODMAP Long-Term
The foods removed in Phase 1 are many of the same foods that feed beneficial gut bacteria. FODMAPs are prebiotics. Removing them starves the overgrowth — but also Bifidobacterium, Faecalibacterium prausnitzii, and other commensals that keep the colon healthy.
Staudacher et al. (2012, Journal of Nutrition) randomised 41 people with irritable bowel syndrome and found that after 4 weeks of restricting fermentable carbohydrates, stool bifidobacteria were significantly lower, in both concentration and proportion, than in the group on their habitual diet. Bennet et al. (2018, Gut), another 4-week trial in 67 people with irritable bowel syndrome, found the low-FODMAP diet was associated with reduced Bifidobacterium and Actinobacteria, and that stool bacterial profiles predicted who responded to the diet. A 2022 meta-analysis of 9 randomized trials (So, Loughman and Staudacher, American Journal of Clinical Nutrition) found the diet consistently lowered Bifidobacteria but had no clear effect on overall microbiome diversity or on other specific bacteria.
Practitioners raise the concern that a narrower microbiome is a more fragile one: slower to recover from antibiotics, more prone to Clostridioides difficile, and possibly more food-sensitive over time as the gut's tolerance for variety shrinks.
The protocol's own sequence: Phase 1 for 2 to 6 weeks, Phase 2 done systematically, Phase 3 long-term. Not the other way around.
6. Low-FODMAP vs. SCD vs. Bi-Phasic Diet
Three different dietary frameworks are used for small intestinal bacterial overgrowth. They overlap but are not the same.
- Low-FODMAP (Monash): restricts fermentable carbohydrates by category. Best-studied. Designed originally for irritable bowel syndrome (IBS), later applied to small intestinal bacterial overgrowth. Structured three-phase protocol.
- Specific Carbohydrate Diet (SCD): developed by Sidney Haas and popularized by Elaine Gottschall's Breaking the Vicious Cycle. Eliminates all grains, most disaccharides, and starches — only monosaccharides are allowed. Stricter than low-FODMAP and not phase-structured. Often used for inflammatory bowel disease (IBD).
- Small intestinal bacterial overgrowth Bi-Phasic Diet (Dr. Nirala Jacobi): specifically designed for small intestinal bacterial overgrowth. Combines the low-FODMAP framework with the carbohydrate restrictions of SCD, structured into two phases over roughly 8 weeks with clear food lists for each phase. It is the most small intestinal bacterial overgrowth-specific of the three and practitioners describe it as easier to follow than merging low-FODMAP and SCD rules by hand.
In practice, low-FODMAP is the framework most small intestinal bacterial overgrowth patients try first, and practitioners commonly move to the Bi-Phasic Diet when low-FODMAP helps only partly.
7. Why Diet Alone Doesn't Cure Small Intestinal Bacterial Overgrowth
This is the hard truth. Low-FODMAP relieves symptoms by reducing the fuel bacteria use to produce gas. It does not reduce the number of bacteria in your small intestine. The overgrowth is still there; you have just put it on a diet.
When low-FODMAP is stopped without treating the underlying small intestinal bacterial overgrowth, symptoms return within days. This is why patients often conclude "I have to eat this way forever" — because the diet is the only thing holding symptoms down. It is a valid coping strategy, but it is not a cure, and it has a real microbiome cost.
Eradication, as practitioners describe it, means treating the overgrowth directly — covered on the pages on rifaximin protocols and herbal antimicrobials — and then preventing relapse by identifying why the overgrowth happened in the first place. See root causes. Diet is a supporting player, not the protagonist.
8. Apps and Resources
- Monash University FODMAP Diet app (paid phone app): Monash researchers developed the FODMAP framework and continue to test specific foods in their lab. The app rates foods with a traffic-light system (green/yellow/red per serving size) based on that lab testing.
- A commercial certification program (Australian): a second certification body that tests packaged foods and labels qualifying products, which shoppers use to check boxes in supermarkets.
- Other food-scanning apps: some free apps scan a grocery barcode and filter it against low-FODMAP (and other) dietary needs, for quick shopping checks.
- Monash blog and recipes: the Monash University department of gastroenterology publishes recipes and updates as foods are retested.
9. Working with a Dietitian
Phase 2 reintroduction is genuinely hard to do alone. The protocol requires careful food journaling, dose laddering, and washout periods. Most people — especially exhausted, overwhelmed small intestinal bacterial overgrowth patients — abandon it halfway and either spring back to their old diet or stay stuck in Phase 1 forever.
A registered dietitian (RD) with gastrointestinal (GI) and small intestinal bacterial overgrowth training can make the difference between success and a lost six months. Monash University keeps a directory of dietitians who have completed its FODMAP training. A dietitian experienced with small intestinal bacterial overgrowth structures the reintroduction schedule, interprets ambiguous reactions, and adapts the plan along the way.
If cost is a barrier, even one or two sessions — one to plan Phase 2, one to interpret results — is usually enough. Many insurance plans cover medical nutrition therapy (MNT) for irritable bowel syndrome, small intestinal bacterial overgrowth, or functional gastrointestinal disorders.
Key Research Papers
Peer-reviewed studies on the low-FODMAP diet for irritable bowel syndrome and small intestinal bacterial overgrowth — mechanisms, clinical efficacy, microbiome impact, and reintroduction strategy. Each citation links to the full text via DOI.
- Halmos EP, Power VA, Shepherd SJ, Gibson PR, Muir JG. A Diet Low in FODMAPs Reduces Symptoms of Irritable Bowel Syndrome. Gastroenterology. 2014;146(1):67–75. — doi:10.1053/j.gastro.2013.09.046
- Böhn L, Störsrud S, Liljebo T, et al. Diet Low in FODMAPs Reduces Symptoms of Irritable Bowel Syndrome as Well as Traditional Dietary Advice: A Randomized Controlled Trial. Gastroenterology. 2015;149(6):1399–1407. — doi:10.1053/j.gastro.2015.07.054
- Staudacher HM, Whelan K. The Low FODMAP Diet: Recent Advances in Understanding Its Mechanisms and Efficacy in IBS. Gut. 2017;66(8):1517–1527. — doi:10.1136/gutjnl-2017-313750
- Staudacher HM, Lomer MCE, Anderson JL, et al. Fermentable Carbohydrate Restriction Reduces Luminal Bifidobacteria and Gastrointestinal Symptoms in Patients with Irritable Bowel Syndrome. Journal of Nutrition. 2012;142(8):1510–1518. — doi:10.3945/jn.112.159285
- Marsh A, Eslick EM, Eslick GD. Does a Diet Low in FODMAPs Reduce Symptoms Associated with Functional Gastrointestinal Disorders? A Comprehensive Systematic Review and Meta-Analysis. European Journal of Nutrition. 2016;55(3):897–906. — doi:10.1007/s00394-015-0922-1
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. American Journal of Gastroenterology. 2020;115(2):165–178. — doi:10.14309/ajg.0000000000000501
- Bennet SMP, Böhn L, Störsrud S, et al. Multivariate Modelling of Faecal Bacterial Profiles of Patients with IBS Predicts Responsiveness to a Diet Low in FODMAPs. Gut. 2018;67(5):872–881. — doi:10.1136/gutjnl-2016-313128
- Eswaran SL, Chey WD, Han-Markey T, Ball S, Jackson K. A Randomized Controlled Trial Comparing the Low FODMAP Diet vs. Modified NICE Guidelines in US Adults with IBS-D. American Journal of Gastroenterology. 2016;111(12):1824–1832. — doi:10.1038/ajg.2016.434
- Tuck CJ, Muir JG, Barrett JS, Gibson PR. Fermentable Oligosaccharides, Disaccharides, Monosaccharides and Polyols: Role in Irritable Bowel Syndrome. Expert Review of Gastroenterology & Hepatology. 2014;8(7):819–834. — doi:10.1586/17474124.2014.917956
- Pimentel M, Chow EJ, Lin HC. Eradication of Small Intestinal Bacterial Overgrowth Reduces Symptoms of Irritable Bowel Syndrome. American Journal of Gastroenterology. 2000;95(12):3503–3506. — doi:10.1111/j.1572-0241.2000.03368.x
- Hill P, Muir JG, Gibson PR. Controversies and Recent Developments of the Low-FODMAP Diet. Gastroenterology & Hepatology. 2017;13(1):36–45. — PubMed PMID: 28420945
- Chedid V, Dhalla S, Clarke JO, et al. Herbal Therapy Is Equivalent to Rifaximin for the Treatment of Small Intestinal Bacterial Overgrowth. Global Advances in Health and Medicine. 2014;3(3):16–24. — doi:10.7453/gahmj.2014.019
- So D, Loughman A, Staudacher HM. Effects of a Low FODMAP Diet on the Colonic Microbiome in Irritable Bowel Syndrome: A Systematic Review with Meta-Analysis. American Journal of Clinical Nutrition. 2022;116(4):943–952. — PubMed PMID: 35728042
- Gibson PR, Shepherd SJ. Personal View: Food for Thought — Western Lifestyle and Susceptibility to Crohn's Disease. The FODMAP Hypothesis. Alimentary Pharmacology & Therapeutics. 2005;21(12):1399–1409. — PubMed PMID: 15948806
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Small Intestinal Bacterial Overgrowth Overview
- Root Causes
- Herbal Antimicrobials
- Rifaximin Protocols
- Elemental Diet
- Prokinetics and Relapse Prevention
- Hydrogen vs Methane vs Hydrogen Sulfide
- Breath Test Guide
- IMO and Constipation
- Irritable Bowel Syndrome
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Celiac Disease
- Elimination Diet
- Gut Healing
- Probiotics
- Bloating
- Peppermint
- Abdominal Pain