Sleep, Stress & Cortisol in Insulin Resistance
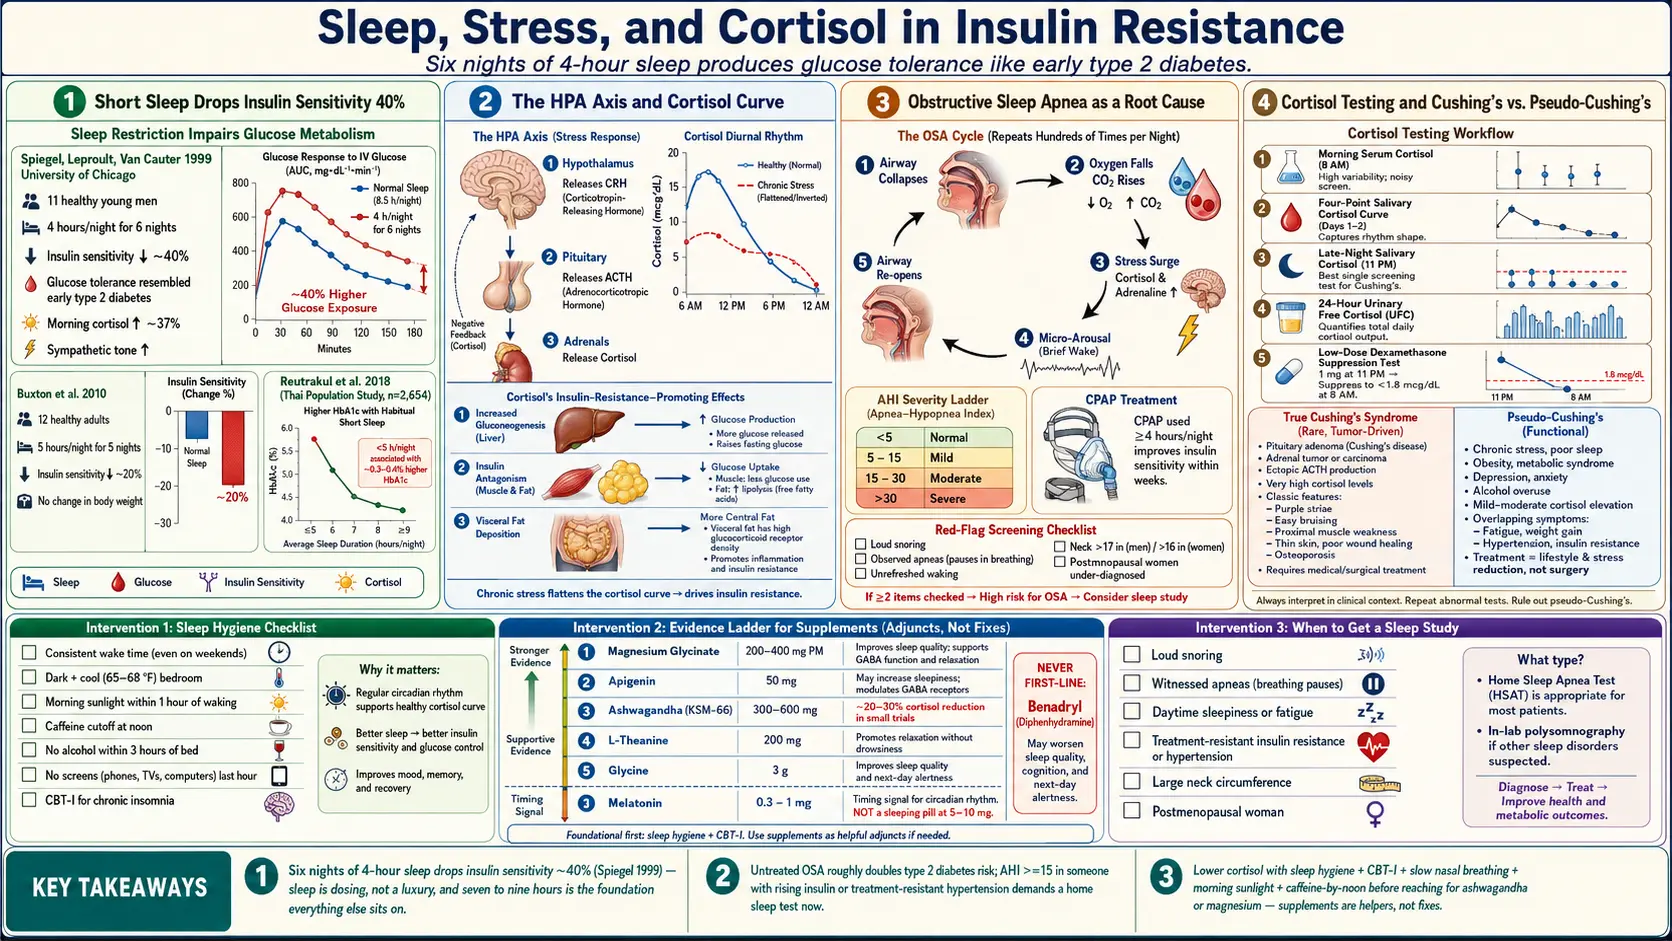
When fasting insulin climbs and the waistline widens with nothing in the diet to explain it, sleep and stress are two of the causes the research points to. The hormones that rise with tiredness and overwhelm are the same ones that drive glucose into the bloodstream and fat into the belly. A person can eat a carefully chosen diet and still be insulin resistant while sleeping six hours a night, grinding their teeth over work at 2 a.m., or quietly choking off their airway every thirty seconds because of undiagnosed sleep apnea.
This article walks through the science linking short sleep, circadian disruption, and chronic stress to insulin resistance — and the practical approaches that research and practitioners describe.
Interactive Visualization Blood Sugar & Insulin — eat a meal and watch glucose move Watch insulin escort glucose into cells and the liver bank glycogen, then switch on insulin resistance and see the curve change. Launch →Table of Contents
- One Week of Short Sleep Lowers Insulin Sensitivity
- Circadian Disruption and Shift Work
- Obstructive Sleep Apnea as a Root Cause
- Cortisol, Gluconeogenesis, and the Liver
- Chronic Stress and Visceral Belly Fat
- The Hypothalamic-Pituitary-Adrenal Axis in Plain English
- Testing Cortisol: Morning Levels, Saliva, Dexamethasone
- Cushing's Syndrome vs. "Pseudo-Cushing's"
- Lifestyle Interventions That Actually Move the Needle
- Supplements: Magnesium, Apigenin, Ashwagandha
- Signs That Lead to a Sleep Study
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
One Week of Short Sleep Lowers Insulin Sensitivity
In 1999, a small but now-famous study by Karine Spiegel, Rachel Leproult, and Eve Van Cauter at the University of Chicago cut the time in bed of 11 healthy young men to 4 hours a night for 6 nights, then compared them with the same men after 6 recovery nights of 12 hours in bed. In the sleep-debt week their glucose tolerance was lower, evening cortisol was raised, and sympathetic nervous system activity (fight-or-flight tone) was higher. The authors described these effects as similar to those seen in normal ageing.
After the recovery nights the measures were better than in the sleep-debt week. The body was not broken; it was responding to a stressor. The concern this raises is for people who live for years on 5–6 hours of sleep, who may carry a lasting, sleep-induced insulin resistance whatever they eat; the authors wrote that chronic sleep debt may increase the severity of age-related chronic disorders.
Follow-up work by Orfeu Buxton's group (2010) confirmed the effect in 20 healthy men kept in an inpatient research unit with diet and activity controlled: after 7 nights of 5 hours in bed, insulin sensitivity fell by about 20% on an intravenous glucose tolerance test and by about 11% on a euglycemic clamp (a second, more direct test). Salivary cortisol rose by about 51%, but the fall in insulin sensitivity did not track the cortisol change. Sirimon Reutrakul and colleagues have since linked habitual short sleep (less than 6 hours) with measurably higher hemoglobin A1c (HbA1c), higher fasting insulin, and greater long-term diabetes risk in population studies.
Taken together, these studies place sleep beside diet as the foundation of insulin sensitivity rather than an afterthought. Seven to nine hours a night is the adult range sleep researchers commonly cite.
Circadian Disruption and Shift Work
The pancreas, liver, and muscle cells all have internal clocks. They expect glucose to arrive during the day and to be quiet at night. A large meal at 11 p.m. or a rotating night shift feeds glucose into a system that has already clocked out — and the insulin response becomes sluggish and disordered.
A 2015 meta-analysis of 12 observational studies (226,652 people) found that ever working shifts was linked to about 9% higher odds of diabetes (odds ratio 1.09). The link was stronger in men (odds ratio 1.37, about 37% higher) than in women (1.09), and rotating shifts carried a higher risk than normal daytime schedules. Even short-term lab simulations of jet lag produce measurable drops in insulin sensitivity within days.
Where working hours cannot be regular, practitioners describe clustering meals instead. Time-restricted eating — finishing the last meal 3 hours before bed and compressing most calories into daylight — is described as letting the circadian machinery recover even when the sleep schedule is imperfect.
Obstructive Sleep Apnea as a Root Cause
In people who are overweight, snore, wake unrefreshed, or whose partner notices pauses in their breathing, untreated obstructive sleep apnea (OSA) may be the biggest single driver of insulin resistance.
Each time the airway collapses, oxygen falls, carbon dioxide rises, and the body releases a burst of cortisol and adrenaline that wakes the sleeper just enough to re-open the airway. The sleeper does not remember these micro-arousals, but they can happen hundreds of times a night. Each one is a small surge of stress hormones and a small spike of glucose. Multiplied across years, it hammers insulin sensitivity, raises blood pressure, and fattens the liver.
The key number is the Apnea-Hypopnea Index (AHI), measured during a sleep study:
- AHI < 5 — normal.
- AHI 5–15 — mild OSA.
- AHI 15–30 — moderate OSA.
- AHI > 30 — severe OSA.
Moderate-to-severe OSA roughly doubles the risk of developing type 2 diabetes. On the treatment side, CPAP therapy (continuous positive airway pressure), used for at least 4 hours a night, is reported to improve insulin sensitivity within weeks to months. A 2021 meta-analysis of 7 randomized trials (691 people with type 2 diabetes and sleep apnea) found that CPAP, compared with sham CPAP or no CPAP, lowered HbA1c, fasting glucose, the insulin-resistance score HOMA-IR (homeostatic model assessment of insulin resistance), and both systolic and diastolic blood pressure. Weight loss of 10% can halve the AHI. Side- or stomach-sleeping, no alcohol within 3 hours of bed, and treating nasal congestion are also described as helping.
A home sleep test is the usual first check when sleep apnea is suspected. These tests run $200–$500 out of pocket and are usually covered by insurance when there is clinical suspicion.
Cortisol, Gluconeogenesis, and the Liver
Cortisol is not the villain it is sometimes painted as. It is the hormone that gets people out of bed in the morning, powers a hard workout, and keeps the body alive in a real emergency. The problem is chronic, low-grade elevation — cortisol that never comes down.
One of cortisol's jobs is to make sure glucose is available when the body needs it. It does this by:
- Gluconeogenesis — telling the liver to manufacture new glucose from amino acids and glycerol, even without food.
- Antagonizing insulin — actively blunting insulin's signal at the muscle and fat cell.
- Promoting lipolysis centrally while encouraging visceral fat storage — fat around the organs, not under the skin.
So chronically high cortisol means more glucose in the blood and more resistance at the tissues that should absorb it. That is essentially the definition of insulin resistance — and it happens without a single donut.
Chronic Stress and Visceral Belly Fat
This is why the classic stressed-out executive grows a hard, round belly rather than soft subcutaneous fat on the hips and thighs. Visceral fat cells have a high density of cortisol receptors. They preferentially respond to high cortisol by taking up circulating fatty acids and storing them right next to the liver, pancreas, and intestines — exactly the worst real estate for metabolic health.
Visceral fat is not passive storage. It secretes inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, IL-6) that further impair insulin signaling in muscle and liver. The loop feeds itself: stress raises cortisol, cortisol grows visceral fat, visceral fat drives inflammation, inflammation worsens insulin resistance, insulin resistance raises glucose, and the brain interprets high glucose as another stressor.
Breaking the loop requires lowering cortisol and shrinking the visceral depot — and the interventions that do one almost always do the other.
The Hypothalamic-Pituitary-Adrenal Axis in Plain English
The Hypothalamic-Pituitary-Adrenal (HPA) axis is the stress hormone assembly line. It has three stations:
- Hypothalamus (deep in the brain) senses a stressor and releases CRH (corticotropin-releasing hormone).
- Pituitary gland (just below the hypothalamus) responds to CRH by releasing adrenocorticotropic hormone (ACTH) into the bloodstream.
- Adrenal glands (sitting on top of the kidneys) respond to adrenocorticotropic hormone by releasing cortisol.
Cortisol then feeds back to the hypothalamus and pituitary to shut off its own production — a negative feedback loop. In a healthy axis, cortisol surges in the morning, gently declines through the day, and bottoms out around midnight. In chronic stress, sleep loss, or shift work, the curve flattens — high at night, low in the morning, with the brakes on the feedback loop partially broken.
A flat or inverted cortisol curve is one of the most consistent findings in metabolic syndrome, burnout, and chronic insomnia.
Testing Cortisol: Morning Levels, Saliva, Dexamethasone
When cortisol excess is suspected of driving the metabolic picture, a few standard tests sort it out:
- Morning serum cortisol (8 a.m. blood draw). A useful screen but noisy — stress of the needle itself can raise it.
- Salivary cortisol curve (4 samples across the day at home). Captures the shape of the rhythm, not just one point. Very useful for identifying flat curves.
- Late-night salivary cortisol (11 p.m. sample). In a healthy axis it is near zero; elevation is one of the earliest signs of true cortisol excess.
- 24-hour urinary free cortisol. Measures total daily output, bypassing moment-to-moment noise.
- Low-dose dexamethasone suppression test. The person takes 1 mg of dexamethasone (a synthetic cortisol-like steroid) at 11 p.m. and measure cortisol at 8 a.m. In a healthy axis, the pituitary senses the dexamethasone and shuts off adrenocorticotropic hormone, so morning cortisol is suppressed below 1.8 μg/dL. Failure to suppress is a red flag for Cushing's.
Cushing's Syndrome vs. "Pseudo-Cushing's"
Two scenarios can produce a Cushing-like picture — central weight gain, insulin resistance, high blood pressure, easy bruising, mood changes — and the distinction matters enormously.
True Cushing's syndrome is caused by a tumor (pituitary adenoma, adrenal adenoma, or ectopic adrenocorticotropic hormone-producing tumor) pumping out excess cortisol. It is rare: a population-based study in Malta (2008–2020) counted about 4.5 new cases per million people per year. Diagnosis involves imaging and specialized testing, and treatment is usually surgery. Red flags include purple abdominal stretch marks more than 1 cm wide, proximal muscle weakness (trouble standing from a chair), unexplained bone fractures, and rapidly progressive features.
Pseudo-Cushing's looks similar on the surface but is driven by chronic stress, poor sleep, obesity, depression, or heavy alcohol use — functional overdrive of a normal hypothalamic-pituitary-adrenal axis rather than a tumor. It is vastly more common. The clinical features are milder, and the dexamethasone suppression test usually does suppress cortisol (though sometimes incompletely).
In someone with insulin resistance plus the Cushing-looking picture, endocrinologists run screening tests (late-night salivary cortisol, 24-hour urinary free cortisol, low-dose dexamethasone). Clearly abnormal results lead to imaging. When results are only mildly off, the diagnosis is almost always pseudo-Cushing's — and the approach is the lifestyle work described below, not surgery.
Lifestyle Interventions That Actually Move the Needle
The approaches below are low-risk, cheap, and drawn from sleep and stress research. Practitioners describe cortisol coming down within weeks when several are combined.
Sleep hygiene basics, as sleep-hygiene guidance lists them.
- Consistent wake time — same time every day including weekends. This is the single most powerful circadian anchor. Sleep-in drift is worse than slightly shorter sleep.
- Dark bedroom — blackout curtains or a sleep mask. Even low levels of ambient light (streetlamp, LED standby) measurably raise overnight heart rate and morning insulin resistance.
- Cool bedroom — 65–68°F (18–20°C). Core body temperature needs to drop for deep sleep to begin.
- Morning sunlight — 10 minutes of outdoor light within an hour of waking sets the cortisol rhythm for the day.
- A screen-free last hour — blue light suppresses melatonin. When screens are used, night-mode filters are described as helping, and glasses that block blue light as helping more.
- Caffeine cutoff by noon — caffeine's half-life is about 5–6 hours. An afternoon coffee still has 25% of the caffeine circulating at midnight.
- An alcohol-free last 3 hours before bed — alcohol brings on sleep but breaks up deep sleep and worsens apnea.
Cognitive behavioral therapy for insomnia (CBT-I). Described as the first-line evidence-based treatment for chronic insomnia — reported to work better than sleeping pills over the long term, without drug side effects. It is delivered by trained therapists or by digital programs that deliver cognitive behavioral therapy for insomnia (some are FDA-cleared). A 6–8 week program is the standard. The insomnia page covers the specifics.
Mindfulness and breathing. Ten minutes of slow nasal breathing (inhale 4 seconds, exhale 6 seconds) before bed is described by practitioners as activating the parasympathetic — "rest and digest" — nervous system and lowering cortisol. Meditation apps are one way people practise it; a timer and silence is another.
Exercise — but not too late. Regular exercise is one of the strongest long-term cortisol regulators, but intense evening training (within 3 hours of bed) raises core temperature and adrenaline and can wreck sleep. For that reason practitioners describe morning or early-afternoon training as the better timing for sleep. The exercise and muscle page covers the full dose-response picture.
Late evening food. Eating within 2–3 hours of bed raises overnight glucose and insulin, fragments sleep, and worsens reflux. A 12–14 hour overnight fast costs nothing and is described by practitioners as a metabolic intervention.
Supplements: Magnesium, Apigenin, Ashwagandha
Evidence for supplements in this space is modest — practitioners describe them as helpers, not fixes, alongside the lifestyle basics above.
- Magnesium glycinate, commonly taken at 200–400 mg in the evening. Magnesium is a cofactor for gamma-aminobutyric acid (GABA) activity and parasympathetic tone. Deficiency is common. The glycinate form is well-absorbed and easy on the gut. Citrate also works but is laxative at higher doses. More on the magnesium page.
- Apigenin, commonly taken at 50 mg before bed. A flavonoid found in chamomile and parsley that binds benzodiazepine receptors mildly and has modest anxiolytic and sleep-promoting effects in small trials.
- Ashwagandha, an adaptogenic herb commonly taken at 300–600 mg/day. In a randomized trial of 64 adults with chronic stress, a standardized ashwagandha root extract given at 300 mg twice a day for 60 days lowered morning serum cortisol by 27.9% from baseline, against 7.9% with placebo, and lowered scores on stress questionnaires. Concerns are raised for its use in pregnancy, in autoimmune thyroid disease, and alongside sedative medications. More on the ashwagandha page.
- L-theanine (commonly 200 mg) and glycine (commonly 3 g) are also used; both are described as mild and well tolerated.
What is not first-line: melatonin at high doses (it is a circadian timing signal, not a sleeping pill — 0.3–1 mg is physiologic; 5–10 mg pharmacologic and often counterproductive), diphenhydramine (an older sedating antihistamine — it does not produce real sleep architecture and worsens cognition), and alcohol (for the reasons above).
Signs That Lead to a Sleep Study
A sleep study is commonly ordered when any of the following apply:
- Loud snoring, or a partner has seen breathing stop during sleep.
- Waking unrefreshed despite adequate time in bed.
- Daytime sleepiness (Epworth Sleepiness Scale > 10) or falling asleep while driving.
- Insulin resistance, prediabetes, or type 2 diabetes that is not responding to lifestyle change.
- High blood pressure (hypertension) that is resistant to medication.
- A neck circumference > 17 inches (men) or > 16 inches (women).
- A large tongue, recessed jaw, or crowded airway on exam.
- Being postmenopausal (OSA in women is dramatically under-diagnosed).
Home sleep tests (Level III studies) are now the usual first step — small portable devices measuring airflow, oxygen saturation, heart rate, and chest movement. Accurate for moderate-to-severe OSA; may miss mild cases, in which a full in-lab polysomnography is the next step. Online (telemedicine) sleep services can also order home sleep tests directly, without a primary care visit, for roughly $200–$400.
Key Research Papers
- Spiegel K, Leproult R, Van Cauter E. Impact of sleep debt on metabolic and endocrine function. Lancet. 1999;354(9188):1435–1439. — doi:10.1016/S0140-6736(99)01376-8
- Buxton OM, et al. Sleep restriction for 1 week reduces insulin sensitivity in healthy men. Diabetes. 2010;59(9):2126–2133. — doi:10.2337/db09-0699
- Reutrakul S, Van Cauter E. Interactions between sleep, circadian function, and glucose metabolism: implications for risk and severity of diabetes. Ann N Y Acad Sci. 2014. — doi:10.1111/nyas.12355
- Buxton OM, et al. Adverse metabolic consequences in humans of prolonged sleep restriction combined with circadian disruption. Sci Transl Med. 2012. — doi:10.1126/scitranslmed.3003200
- Punjabi NM, Ahmed MM, Polotsky VY, Beamer BA, O'Donnell CP. Sleep-disordered breathing, glucose intolerance, and insulin resistance. Respir Physiol Neurobiol. 2003;136(2–3):167–178. — doi:10.1016/s1569-9048(03)00079-x
- Chandrasekhar K, Kapoor J, Anishetty S. A prospective, randomized double-blind, placebo-controlled study of safety and efficacy of a high-concentration full-spectrum extract of ashwagandha root in reducing stress and anxiety. Indian J Psychol Med. 2012. — doi:10.4103/0253-7176.106022
- Gan Y, Yang C, Tong X, et al. Shift work and diabetes mellitus: a meta-analysis of observational studies. Occup Environ Med. 2015;72(1):72–78. — PubMed PMID: 25030030
- Shang W, Zhang Y, Wang G, Han D. Benefits of continuous positive airway pressure on glycaemic control and insulin resistance in patients with type 2 diabetes and obstructive sleep apnoea: a meta-analysis. Diabetes Obes Metab. 2021;23(2):540–548. — PubMed PMID: 33146450
- Mangion J, Imbroll MG, Craus S, Vassallo J, Gruppetta M. Epidemiology and blood parameter changes in Cushing's syndrome – a population-based study. Hormones (Athens). 2022;21(3):467–476. — PubMed PMID: 35793065
PubMed Topic Searches
For further reading, the following PubMed searches return current peer-reviewed work:
- Sleep restriction and insulin sensitivity
- Shift work and type 2 diabetes risk
- Obstructive sleep apnea, insulin resistance, and CPAP
- Cortisol, gluconeogenesis, and insulin resistance
- Visceral adiposity, cortisol, and the HPA axis
- Dexamethasone suppression test and pseudo-Cushing's
- CBT-I, insomnia, and metabolic outcomes
- Ashwagandha and cortisol (randomized trials)
- Magnesium, sleep, and insulin sensitivity
- Time-restricted eating, circadian rhythm, and glucose
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Ashwagandha
- Insomnia
- Magnesium
- Exercise and Muscle Insulin Sensitivity
- Insulin Resistance
- Reversal Protocol: Diet and Fasting
- CGM for Non-Diabetics
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Metabolic Syndrome Cardiovascular Risk
- Non-Alcoholic Fatty Liver Disease & Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Insulin Resistance and Polycystic Ovary Syndrome
- Obstructive Sleep Apnea
- Cushing's Syndrome
- Visceral Fat
- Burnout
- Sleep Hygiene
- Insulin Resistance: Diet & Blood-Sugar Strategies — the dietary and blood-sugar side of the same problem, for after the sleep and cortisol work is underway.