Reversing Insulin Resistance: Diet and Fasting Protocols
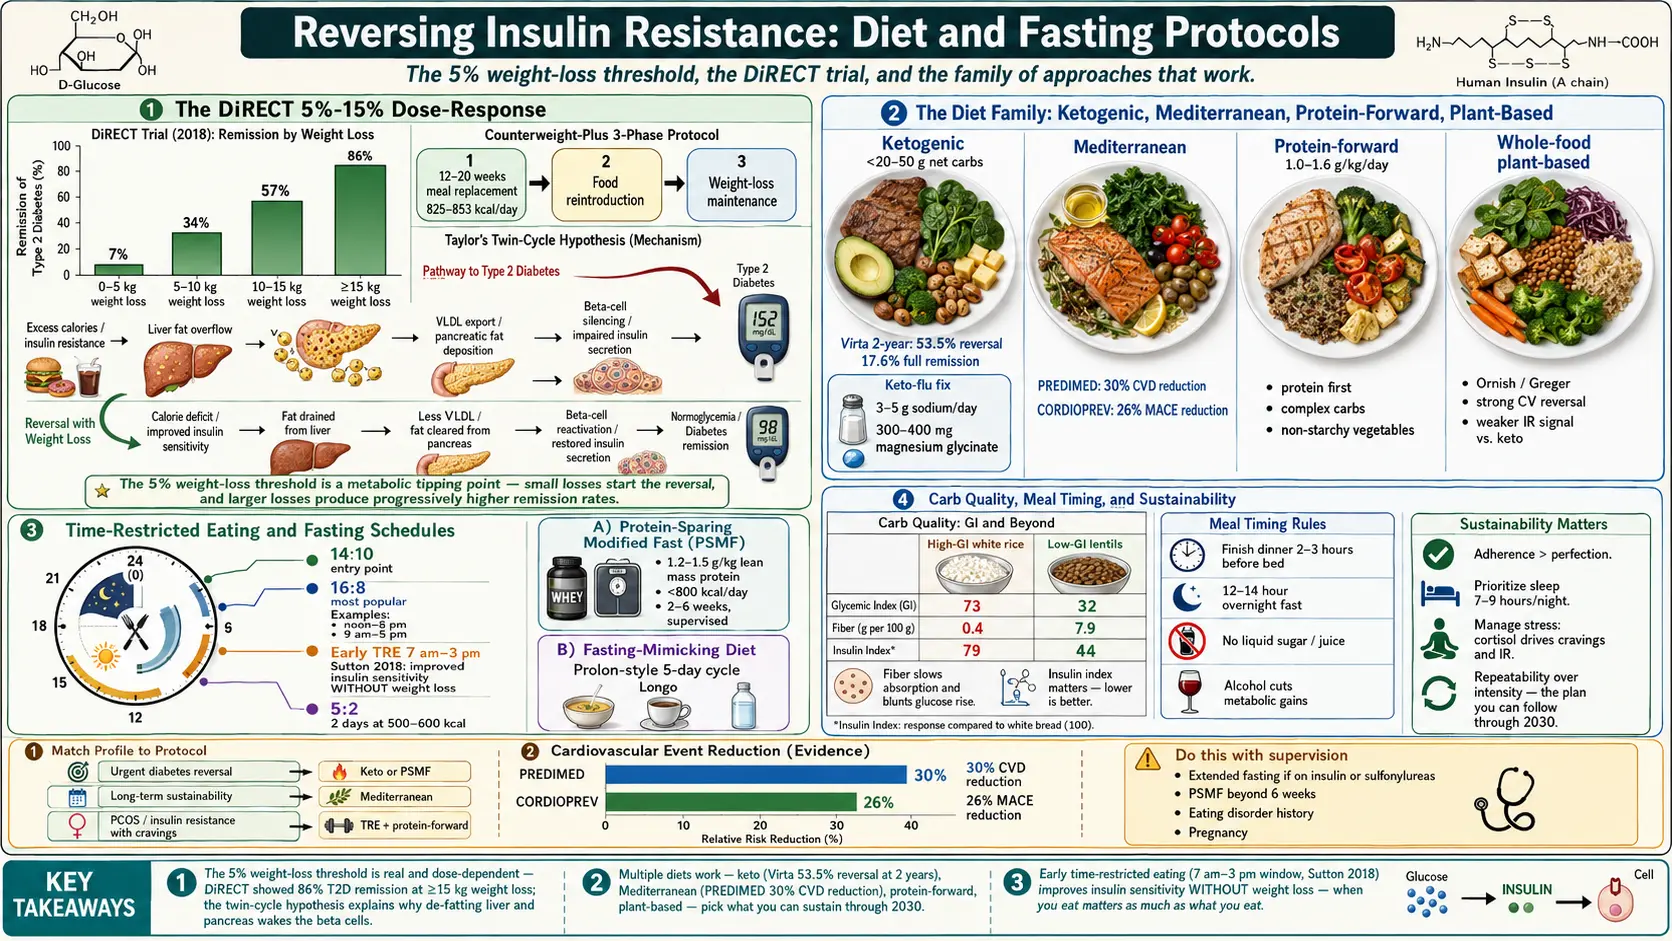
Table of Contents
- Why Food Comes First
- The 5% Weight-Loss Threshold — DiRECT and Newcastle
- Low-Carb and Ketogenic Diets
- The Mediterranean Diet
- Protein-Forward, Lower-Glycemic-Load Eating
- Low-Fat and Whole-Food Plant-Based
- Time-Restricted Eating and Intermittent Fasting
- The Protein-Sparing Modified Fast
- Extended Fasts and Fasting-Mimicking Diets
- Carbohydrate Quality Over Quantity
- Meal Timing, Sleep, and Alcohol
- How to Pick a Protocol You Will Actually Keep
- Cautions: Groups at Higher Risk
- Key Research Papers
- Connections
- Featured Videos
Why Food Comes First
Insulin resistance is, at its core, a problem of too much insulin circulating too often. Your muscles and liver stop responding to the hormone because they are flooded with it, day after day. The medications we have — metformin, berberine, glucagon-like peptide-1 (GLP-1) agonists like semaglutide — help. Diet researchers argue that nothing lowers insulin as powerfully, as cheaply, or as durably as changing what and when you eat.
The encouraging news, and the point of this article, is that insulin resistance is one of the most reversible metabolic conditions in medicine. Not just managed. Reversed. We have high-quality randomized trials showing that the majority of people with type 2 diabetes can come off insulin and hit normal hemoglobin A1c (HbA1c) — sometimes within weeks — using nothing but a structured eating plan. Prediabetes and the milder insulin resistance that shows up on a homeostatic model assessment of insulin resistance (HOMA-IR) score are even easier targets.
No single diet is "the" answer. Several have trial data. What they share is a consistent reduction in the metabolic load the pancreas has to handle, and the trials show that the version people can keep up over years matters most.
The 5% Weight-Loss Threshold — DiRECT and Newcastle
The number this page keeps coming back to is 5%. Researchers describe it as the weight-loss threshold at which insulin resistance and type 2 diabetes begin to reverse in a meaningful way for most people who carry extra visceral fat.
The evidence comes primarily from the DiRECT trial (Diabetes Remission Clinical Trial), run across UK primary care clinics by Roy Taylor at Newcastle University and Mike Lean at Glasgow, published in The Lancet in 2018. DiRECT randomized 306 adults with type 2 diabetes (diagnosed within the last six years, not on insulin) to either standard care or a structured primary-care total-diet-replacement program. The intervention had three phases:
- Total diet replacement. Four meal-replacement shakes and soups per day, totaling 825–853 kcal, for 12 to 20 weeks. All other diabetes and antihypertensive drugs were stopped on day one under physician supervision.
- Structured food reintroduction. Two to eight weeks of stepped reintroduction of ordinary food, starting at around 1,500 kcal per day.
- Long-term weight maintenance with monthly primary-care check-ins.
The results redefined what primary care can do:
- 46% of the intervention group achieved diabetes remission at 12 months (hemoglobin A1c under 6.5% with no diabetes medications), versus 4% of controls.
- Remission was strongly dose-dependent on weight loss. Participants losing 0–5 kg had a 7% remission rate. Those losing 5–10 kg hit 34%. Those losing 10–15 kg hit 57%. And those losing 15 kg or more reached 86%.
- In the two-year follow-up, of the participants who maintained at least 10 kg of weight loss at 24 months (45 of 272 with data), 29 (64%) were in remission.
- At the two-year follow-up, 36% of the original intervention group remained in remission, compared to 3% of controls.
Taylor's twin-cycle hypothesis explains the mechanism. Excess calories pile up as fat in the liver, which oozes that fat into the pancreas, which strangles the insulin-producing beta cells. Take the fat out of the liver and pancreas — which happens quickly on a calorie-deficit diet — and the beta cells wake up. The 5% threshold is roughly the point at which the organs begin to de-fat.
In the DiRECT data, the amount of weight lost tracked remission more closely than any detail of the program. The diets below are all delivery vehicles for the same underlying trick: sustained energy deficit plus lower insulin exposure.
Low-Carb and Ketogenic Diets
Because carbohydrates are the single biggest drivers of post-meal insulin spikes, cutting them hard and fast is the most mechanically direct way to lower insulin. A ketogenic diet restricts net carbohydrates to under 20–50 grams per day, keeps protein moderate, and fills the rest of the plate with fats. After four to seven days, the liver switches to making ketones from fat, and blood glucose stabilizes in a narrow range.
The strongest insulin-resistance evidence comes from a two-year open-label, non-randomized, controlled study of a commercial remote low-carbohydrate program (262 people in the intervention group and 87 in usual care), led by Sarah Hallberg and published by Athinarayanan and colleagues in 2019. The program used an individualized ketogenic intervention with continuous remote physician and coach support. At two years:
- 53.5% of the intervention group met criteria for type 2 diabetes reversal.
- 17.6% achieved full remission (normal hemoglobin A1c off all medications).
- Most participants came off sulfonylureas and reduced or eliminated insulin.
- Hemoglobin A1c dropped by about 0.9 points; homeostatic model assessment of insulin resistance dropped sharply in parallel.
How practitioners usually describe a keto approach:
- Carbs: Under 20 g net for strict keto, under 50 g for "low-carb." Many people track carbohydrates for the first month.
- Protein: 1.2–1.6 g per kg of ideal body weight. Protein does raise insulin modestly but far less than carbs, and it protects muscle during weight loss.
- Fat: Fills the rest. Olive oil, avocado, nuts, fatty fish, eggs, full-fat dairy if tolerated.
- Ketone monitoring: Optional. A blood ketone meter reading 0.5–3.0 mmol/L confirms nutritional ketosis. Urine strips work in week one but become unreliable thereafter.
Keto flu is the headache, fatigue, and brain fog many people hit in days 2–5. It reflects sodium, potassium, and magnesium loss. Keto practitioners commonly describe replacing them with 3–5 g of sodium per day (broth, salt on food, electrolyte powders), 300–400 mg of magnesium glycinate at night, and normal potassium intake from avocado, leafy greens, and salmon.
Two honest caveats. First, a minority of people — particularly lean, athletic hyper-responders — see their low-density lipoprotein (LDL) cholesterol rise steeply on keto. When low-density lipoprotein rises above 190 mg/dL or apolipoprotein B (apoB) above 120, practitioners commonly replace some saturated fat with olive oil and nuts. Second, keto is chemically effective but socially and culinarily narrow. Long-term adherence rates at five years are mediocre. Many practitioners use keto as a tool for a 3–12 month reversal phase, then move to a Mediterranean or protein-forward pattern for maintenance.
The Mediterranean Diet
If keto is a scalpel, the Mediterranean diet is a steady hand. It is the only eating pattern with decades of randomized-trial data on cardiovascular and metabolic endpoints, and it wins on long-term adherence almost every time it is tested.
The PREDIMED trial (Estruch et al., NEJM; the 2013 report was retracted over randomization problems and republished in corrected form in 2018) randomized 7,447 high-cardiovascular-risk Spanish adults to either a Mediterranean diet supplemented with extra-virgin olive oil, the same diet supplemented with mixed nuts, or a reduced-fat control diet. Over a median of 4.8 years, the two Mediterranean arms had about 30% fewer major cardiovascular events (hazard ratios 0.69 and 0.72). Subsequent substudies showed significant drops in fasting insulin, homeostatic model assessment of insulin resistance, and progression to type 2 diabetes.
The CORDIOPREV study (Delgado-Lista et al., 2022) compared the Mediterranean diet head-to-head with a low-fat diet in 1,002 coronary-heart-disease patients over seven years. Mediterranean produced a 26% reduction in major adverse cardiac events and better long-term insulin sensitivity.
What the Mediterranean plate typically looks like:
- Extra-virgin olive oil as the primary fat (4+ tablespoons per day).
- Vegetables at every meal, fruit daily (lower-glycemic — berries, apples, citrus — when insulin resistance is active).
- Legumes several times per week.
- Fish 3+ times per week, especially oily fish (sardines, salmon, anchovies).
- Poultry and eggs in moderation; red meat rarely.
- Nuts daily (a handful).
- Whole grains in portions matched to insulin status — smaller portions when homeostatic model assessment of insulin resistance is high.
- Red wine, in the traditional pattern, with meals and in modest amounts; it is not a required part of the diet.
Mediterranean does not produce the sharp drops in fasting insulin that keto delivers in eight weeks. It produces durable drops over years, with strong cardiovascular protection baked in. For mild to moderate insulin resistance with no urgent diabetes to reverse, it is the pattern with the strongest long-term record.
Protein-Forward, Lower-Glycemic-Load Eating
A middle path between strict carb counting and a standard Western diet. The pattern usually described:
- Protein first at every meal. Typically 1.0–1.6 g per kg of body weight per day, distributed across 3–4 meals, with 30–40 g at breakfast.
- Non-starchy vegetables. Half the plate, most meals.
- Complex carbohydrates — lentils, beans, intact whole grains, berries, root vegetables — as the carb portion, instead of bread, rice, and flour-based foods.
- Healthy fats — olive oil, nuts, avocado, fatty fish — to round out meals and drive satiety.
This approach leans on protein's two advantages for insulin resistance. First, protein is the most satiating macronutrient, which quietly cuts total calorie intake without conscious restriction. Second, adequate protein during any weight-loss phase protects skeletal muscle, and muscle is the largest glucose disposal organ in your body. Losing muscle along with weight works against insulin sensitivity; adequate protein helps keep muscle on.
Low-Fat and Whole-Food Plant-Based
The opposite end of the macronutrient map. Approaches like Dean Ornish's reversal program and the whole-food plant-based approach popularized by Michael Greger restrict fat to 10–15% of calories, eliminate animal products, and rely on legumes, whole grains, fruit, and vegetables.
The evidence is a mixed bag for insulin resistance specifically. Ornish's program has the best cardiovascular-reversal data (Lifestyle Heart Trial, 1990) of any diet ever tested, with documented regression of coronary plaques. On fasting insulin and homeostatic model assessment of insulin resistance, plant-based diets perform well, but the signal is weaker than for keto or DiRECT-style caloric restriction in head-to-head studies. Where whole-food plant-based shines is cardiovascular risk reduction, gut microbiome diversity, and sustainability for people who dislike meat.
Points the plant-based literature returns to:
- Protein adequacy — from legumes, tempeh and seitan, at about the same 1.0–1.4 g/kg.
- Vitamin B12 — a fully vegan diet supplies almost no B12, so vegan plans include a B12 supplement or fortified foods.
- Omega-3 from algae oil on plans without fish.
- Refined carbohydrate traps. "Plant-based" pasta, bread, and dessert are still high-glycemic. Plant-based reversal programs rely on whole foods, not just meatless foods.
Time-Restricted Eating and Intermittent Fasting
Time-restricted eating (TRE) narrows your daily food intake to a window — typically 8, 10, or 12 hours — and leaves the rest of the 24 as water, black coffee, or plain tea. No counting, no forbidden foods, just a clock.
The mechanistic breakthrough study is Sutton et al., Cell Metabolism 2018. Eight men with prediabetes were randomized to early time-restricted feeding (a 6-hour eating window, with dinner before 3 p.m.) or a 12-hour schedule for five weeks, then crossed over to the other schedule, with food intake matched. On early time-restricted feeding, the early-TRE arm had substantially improved insulin sensitivity, lower fasting insulin, lower blood pressure, and reduced oxidative stress — without any weight change. This trial is the cleanest demonstration that when you eat affects insulin signaling independent of how much.
Common time-restricted eating schedules:
- 14:10 — 10-hour eating window. The easiest entry point; many people reach it simply by dropping bedtime snacks.
- 16:8 — 8-hour window. The most popular format. Typical windows are noon to 8 p.m. or 9 a.m. to 5 p.m.
- Early vs late window. Finishing dinner by 6–7 p.m. outperforms a late window in head-to-head data. Circadian insulin sensitivity is higher in the morning.
- OMAD (one meal a day) — popular online but no evidence it beats 16:8 on insulin metrics, and harder to hit protein targets.
- 5:2 — five normal days, two days at 500–600 kcal. Works for some. Equivalent results to standard caloric restriction in most randomized comparisons.
Time-restricted eating pairs naturally with any of the food-quality approaches above and is one of the simplest behavioral changes to add.
The Protein-Sparing Modified Fast
The protein-sparing modified fast (PSMF) is an aggressive short-term tool, not a lifestyle. The format as usually described:
- Protein: 1.2–1.5 g per kg of lean body mass, from lean meat, fish, poultry, or egg whites.
- Fat: minimal (incidental to the protein source).
- Carbs: minimal, usually only from non-starchy vegetables.
- Total calories: typically under 800.
- Duration: two to six weeks, with multivitamin, sodium, potassium, and magnesium supplementation, and — for longer runs — physician supervision.
Lyle McDonald documented the protocol in book form in the 1990s; Benjamin Bikman and others have updated it for modern metabolic-health use. It is effectively a medically-supervised very-low-calorie diet that spares muscle via high protein. Practitioners describe 1–2 kg of fat loss per week and rapid drops in fasting insulin and liver fat.
The PSMF is intense and flavorless by design; the protocol limits it to about six weeks unless there is medical oversight. Practitioners use it to break through a plateau or start a reversal phase, followed by a sustainable pattern.
Extended Fasts and Fasting-Mimicking Diets
Beyond daily TRE lie extended water fasts — 24 to 72 hours of water, black coffee, tea, and electrolytes only. Done under medical supervision, they produce deep autophagy, rapid liver-fat clearance, and sharp insulin drops. Risks include refeeding syndrome (especially after 72+ hours), electrolyte disturbance, and hypoglycemia in people on sulfonylureas or insulin. The risks are highest for people who are underweight, pregnant, on diabetes medication, or have a history of disordered eating.
A gentler alternative is the fasting-mimicking diet (FMD), developed by Valter Longo at the University of Southern California and sold as a commercial fasting-mimicking meal kit. FMD is a five-day cycle of plant-based, low-protein, low-calorie meal kits (roughly 1,100 kcal on day 1 and 800 kcal on days 2–5) that produces most of the metabolic signatures of water fasting while still letting you eat. In a 2017 randomized trial in 100 generally healthy adults (Wei et al.), three monthly five-day cycles reduced body weight, body fat, blood pressure and insulin-like growth factor 1 (IGF-1); in a post hoc analysis, fasting glucose, IGF-1, triglycerides, cholesterol and C-reactive protein improved more in participants at risk for disease. Some practitioners describe using it as a periodic reset alongside a Mediterranean pattern.
Carbohydrate Quality Over Quantity
Not all carbs behave the same in your blood. Fifty grams of lentils and fifty grams of white-bread carbohydrate produce very different glucose and insulin curves, even though they are the same quantity. The quality dimensions that matter:
- Glycemic index (GI) — how fast 50 g of the carb raises blood glucose. White rice is 73; lentils are 32.
- Glycemic load (GL) — GI scaled to a realistic portion. A better real-world number.
- Insulin index — the insulin response specifically. Some foods (dairy, some protein-carb mixes) provoke more insulin than their glucose curve predicts.
- Fiber content. Soluble fiber slows carbohydrate absorption and feeds beneficial gut bacteria that produce butyrate, which improves insulin signaling.
The practical pattern: meals built around carbs that come packaged with fiber, water, and a little protein or fat. Berries instead of juice. Whole intact oats instead of instant. Lentils and beans instead of refined flour. Sweet potato instead of potato chips. Even if your net carb count stays the same, your insulin exposure drops.
Meal Timing, Sleep, and Alcohol
Earlier calories. Jakubowicz et al., Diabetes Care 2019, randomized 28 adults with type 2 diabetes (average body-mass index 32.4) to three meals a day with a carbohydrate-rich breakfast (3Mdiet) or six meals spread through the day (6Mdiet), with the same calories. After twelve weeks, only the three-meal group lost weight (5.4 kg), lowered glucose and hemoglobin A1c, and reduced their total daily insulin dose (by 26 units on average). The meta-message: human metabolism handles carbohydrates better in the morning than at night.
In practical terms, this research points toward an earlier dinner, before about 7 p.m., as the smallest meal of the day rather than the biggest, which also fits early-window time-restricted eating.
Sleep is sugar. In Karine Spiegel, Rachel Leproult and Eve Van Cauter's classic 1999 sleep-restriction study, 11 young healthy men spent 4 hours a night in bed for 6 nights; their glucose tolerance was lower in the sleep-debt condition, effects the authors compared to those of normal ageing. Chronic poor sleep can undo much of what a good diet achieves, and most reversal programs treat seven to nine hours of sleep as part of the protocol.
Alcohol. Ethanol is processed by the liver ahead of anything else. While alcohol is in the bloodstream, fat metabolism pauses and de-novo lipogenesis rises. Heavy or daily drinking drives fatty liver, which drives insulin resistance, which drives more fatty liver. Reversal programs for insulin resistance or non-alcoholic fatty liver disease (NAFLD) usually cut alcohol to a few drinks per week or remove it for the reversal phase.
How to Pick a Protocol You Will Actually Keep
The honest summary: the best diet for insulin resistance is the one a person is still following three years later. The trials are full of crossover and dropout. The winners, statistically, are the people who found a pattern they could live with.
How the evidence lines up by situation:
- Urgent diabetes with hemoglobin A1c over 8, on multiple drugs. The trial models are a DiRECT-style 12-week total diet replacement or a medically supervised ketogenic reset. In both trials medications were adjusted from day one, because the diet lowers blood sugar enough to cause hypoglycemia on full drug doses.
- Clear diagnosis of type 2 diabetes, motivated, food-focused. The remote-care ketogenic model ran 6–12 months and longer; practitioners often follow it with a Mediterranean or protein-forward pattern for maintenance.
- Prediabetes or homeostatic model assessment of insulin resistance of 2.5–4.5, no urgent emergency. Mediterranean or protein-forward eating plus 14:10 or 16:8 time-restricted eating, with retesting at 3 and 6 months, is the common pattern.
- Polycystic ovary syndrome (PCOS) with insulin resistance. Lower-carb Mediterranean, protein-forward, or moderate keto all have good data. See IR and polycystic ovary syndrome.
- Non-alcoholic fatty liver disease/metabolic dysfunction-associated steatotic liver disease (MASLD) as the driver. Any approach that produces 5–10% weight loss works; Mediterranean has the most liver-specific data. See the non-alcoholic fatty liver disease/metabolic dysfunction-associated steatotic liver disease article.
- Plateau or reset. Practitioners use a 2–4 week PSMF or a single cycle of a fasting-mimicking diet.
Measuring progress. Practitioners commonly measure fasting insulin and homeostatic model assessment of insulin resistance at baseline, 3 months, and 6 months. Hemoglobin A1c and fasting glucose are slower to move and can miss improvements. Triglycerides, high-density lipoprotein (HDL), and the triglyceride-to-HDL ratio are cheap surrogates that often track homeostatic model assessment of insulin resistance well. See the fasting insulin and homeostatic model assessment of insulin resistance testing guide.
Cautions: Groups at Higher Risk
Most of the tools on this page have been used safely by adults with standard insulin resistance or mild type 2 diabetes. The research and the trial protocols flag a few groups at higher risk:
- Type 1 diabetes. Keto, time-restricted eating, and fasting have been used in type 1 diabetes, but the insulin dose has to change with the diet; unadjusted sliding-scale insulin on a low-carb or fasting plan causes dangerous hypoglycemia.
- Type 2 diabetes on insulin or sulfonylureas. Cutting carbs or starting a fast lowers blood sugar from day one, so the trials adjusted these drugs on day one. Hypoglycemia from unadjusted glipizide is the most common preventable harm in this space.
- Pregnancy or breastfeeding. Extended fasting and strict ketogenic diets have no safety data in pregnancy; Mediterranean and lower-glycemic patterns are the ones used in gestational diabetes care.
- History of eating disorders. Rigid food rules, prolonged fasting, and intense counting are contraindicated, because they can trigger relapse. Eating-disorder specialists usually describe a gentle Mediterranean pattern as the safe floor.
- Elderly adults with sarcopenia. Aggressive caloric restriction can cost irreplaceable muscle. Protein-forward approaches with resistance training are the ones used at this age; PSMFs and extended fasts carry the most risk of muscle loss.
- Low body weight or underweight. Further weight loss is not a route to reversing insulin resistance in lean people and adds risk; the levers left are muscle-building resistance training, sleep, and less refined carbohydrate. See exercise and muscle insulin sensitivity.
- Chronic kidney disease stage 3 or beyond. The 1.6 g/kg protein level used in some plans above may be too high for damaged kidneys; renal dietitians set protein intake by kidney stage.
Dietary reversal lowers blood sugar and blood pressure enough to need the same dose changes as starting a new drug; on diabetes or blood-pressure medication, an unchanged dose can push blood sugar or blood pressure too low within days.
Key Research Papers
Foundational publications demonstrating that type 2 diabetes is reversible — from the DiRECT trial's primary-care weight-loss remission, to the remote-care ketogenic 2-year results, to the time-restricted-eating and meal-timing studies that work without calorie restriction. Each citation links to the full text via DOI.
- Lean MEJ, Leslie WS, Barnes AC, et al. Primary Care-Led Weight Management for Remission of Type 2 Diabetes (DiRECT): An Open-Label, Cluster-Randomised Trial. Lancet. 2018;391(10120):541–551. — doi:10.1016/S0140-6736(17)33102-1
- Lean MEJ, Leslie WS, Barnes AC, et al. Durability of a Primary Care-Led Weight-Management Intervention for Remission of Type 2 Diabetes: 2-Year Results of the DiRECT Open-Label, Cluster-Randomised Trial. Lancet Diabetes & Endocrinology. 2019;7(5):344–355. PubMed PMID: 30852132
- Hallberg SJ, McKenzie AL, Williams PT, et al. Effectiveness and Safety of a Novel Care Model for the Management of Type 2 Diabetes at 1 Year: An Open-Label, Non-Randomized, Controlled Study. Diabetes Therapy. 2018;9(2):583–612. — doi:10.1007/s13300-018-0373-9
- Athinarayanan SJ, Adams RN, Hallberg SJ, et al. Long-Term Effects of a Novel Continuous Remote Care Intervention Including Nutritional Ketosis for the Management of Type 2 Diabetes: A 2-Year Non-Randomized Clinical Trial. Frontiers in Endocrinology. 2019;10:348. — doi:10.3389/fendo.2019.00348
- Sutton EF, Beyl R, Early KS, Cefalu WT, Ravussin E, Peterson CM. Early Time-Restricted Feeding Improves Insulin Sensitivity, Blood Pressure, and Oxidative Stress Even Without Weight Loss in Men with Prediabetes. Cell Metabolism. 2018;27(6):1212–1221. — doi:10.1016/j.cmet.2018.04.010
- Jakubowicz D, Landau Z, Tsameret S, et al. Reduction in Glycated Hemoglobin and Daily Insulin Dose Alongside Circadian Clock Upregulation in Patients with Type 2 Diabetes Consuming a Three-Meal Diet: A Randomized Clinical Trial. Diabetes Care. 2019;42(12):2171–2180. PubMed PMID: 31548244
- de Cabo R, Mattson MP. Effects of Intermittent Fasting on Health, Aging, and Disease. New England Journal of Medicine. 2019;381(26):2541–2551. — doi:10.1056/NEJMra1905136
- Volek JS, Phinney SD, Forsythe CE, et al. Carbohydrate Restriction Has a More Favorable Impact on the Metabolic Syndrome Than a Low Fat Diet. Lipids. 2009;44(4):297–309. — doi:10.1007/s11745-008-3274-2
- Salas-Salvadó J, Bulló M, Estruch R, Ros E, Covas MI, et al. Prevention of Diabetes with Mediterranean Diets: A Subgroup Analysis of a Randomized Trial. Annals of Internal Medicine. 2014;160(1):1–10. PubMed PMID: 24573661
- Estruch R, Ros E, Salas-Salvadó J, Covas MI, Corella D, et al. Primary Prevention of Cardiovascular Disease with a Mediterranean Diet Supplemented with Extra-Virgin Olive Oil or Nuts. New England Journal of Medicine. 2018;378(25):e34. (Retracted 2013 report, corrected and republished.) PubMed PMID: 29897866
- Knowler WC, Barrett-Connor E, Fowler SE, et al. Reduction in the Incidence of Type 2 Diabetes with Lifestyle Intervention or Metformin (Diabetes Prevention Program). New England Journal of Medicine. 2002;346(6):393–403. — doi:10.1056/NEJMoa012512
- Reaven GM. Banting Lecture 1988. Role of Insulin Resistance in Human Disease. Diabetes. 1988;37(12):1595–1607. — doi:10.2337/diab.37.12.1595
- Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98(4):2133–2223. — doi:10.1152/physrev.00063.2017
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: DiRECT trial and remission
- PubMed: ketogenic diet and T2D
- PubMed: Mediterranean diet and HOMA-IR
- PubMed: time-restricted eating and IR
- PubMed: fasting-mimicking diet (Longo)
- PubMed: protein-sparing modified fast
- PubMed: glycemic load and IR
- PubMed: sleep deprivation and IR
- PubMed: PREDIMED and diabetes
- PubMed: remote-care ketogenic 2-year results
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Exercise and Muscle Insulin Sensitivity
- Non-Alcoholic Fatty Liver Disease & Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Insulin Resistance and Polycystic Ovary Syndrome
- Insulin Resistance
- Diabetes
- Obesity
- CGM for Non-Diabetics
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Metabolic Syndrome Cardiovascular Risk
- Elimination Diet
- Fasting
- Fasting Insulin
- Magnesium
- Olive Oil
- Lentils
- Metabolic Syndrome
- Visceral Fat
- Blood Sugar Deep Dive: Insulin Resistance — the Reaven Syndrome X framework, homeostatic model assessment of insulin resistance ranges, and the ectopic-lipid mechanism these diet and fasting protocols are working against.