Non-Alcoholic Fatty Liver Disease (NAFLD) / Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD): The Hepatic Arm of Insulin Resistance
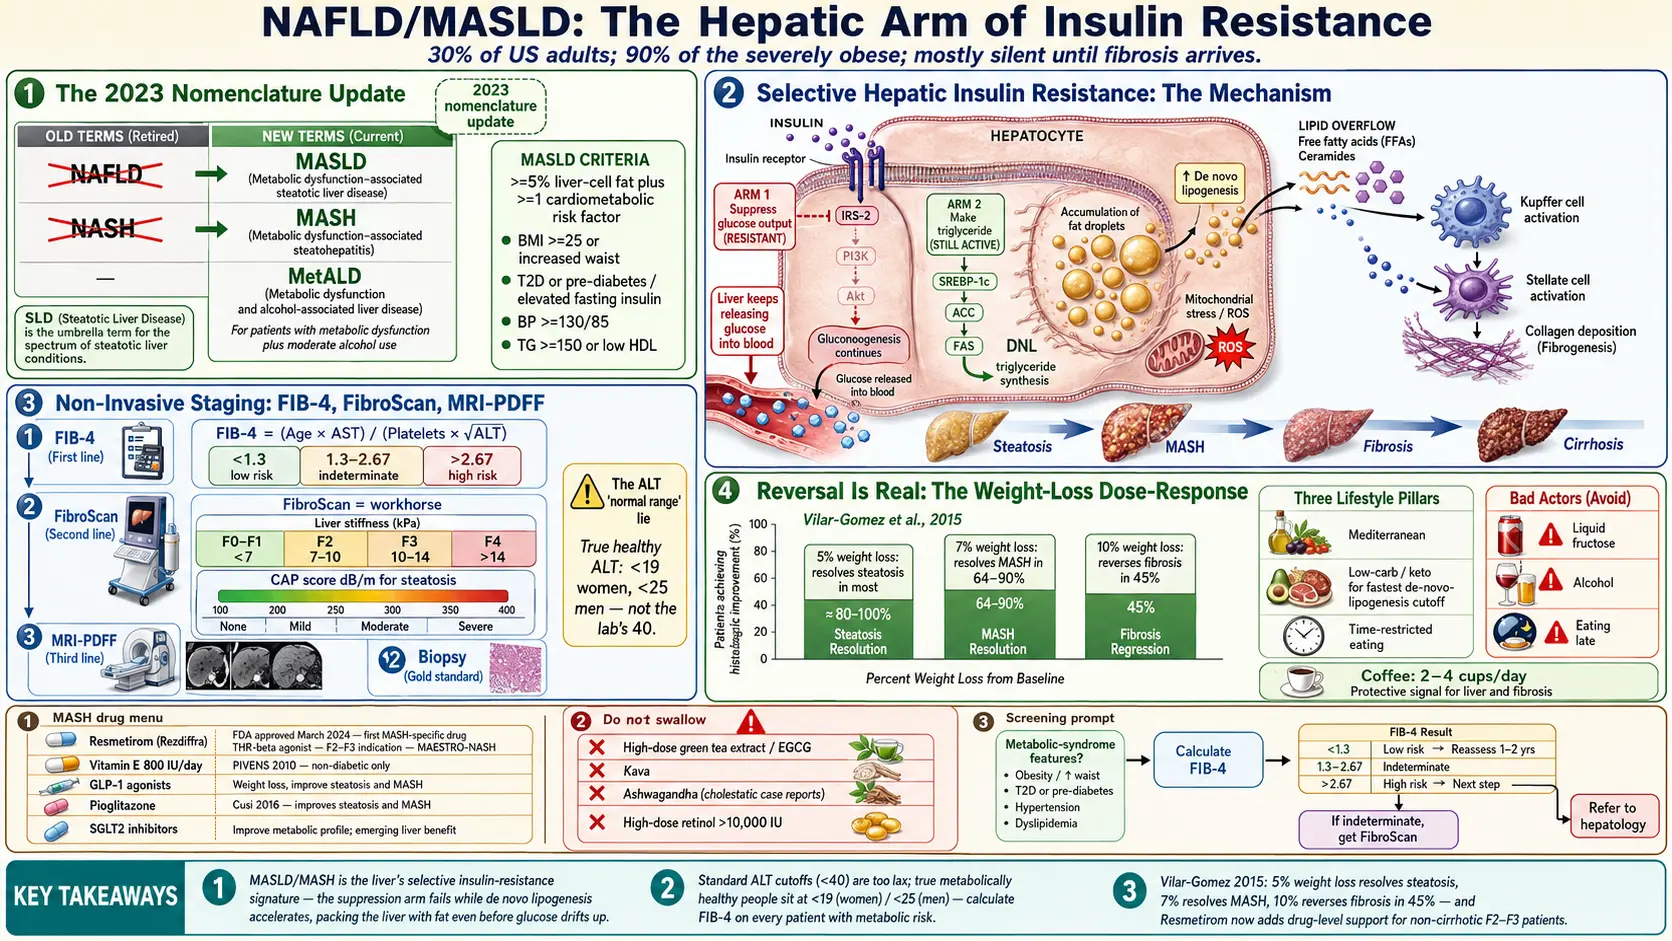
Table of Contents
- The 2023 Name Change: Non-Alcoholic Fatty Liver Disease Becomes Metabolic Dysfunction-Associated Steatotic Liver Disease
- Metabolic Dysfunction-Associated Steatotic Liver Disease Diagnostic Criteria
- How Common It Is — and Why It's Silent
- The Mechanism: Hepatic Insulin Resistance
- The Alanine Aminotransferase "Normal Range" Lie
- FIB-4, Non-Alcoholic Fatty Liver Disease Fibrosis Score, and ELF
- Transient Elastography: The Non-Invasive Workhorse
- MRI-PDFF and Liver Biopsy
- Staging: F0 to F4
- Reversal Is Real: The Weight-Loss Dose-Response
- Diet: Mediterranean, Low-Carb, TRE
- Fructose, Alcohol, and Coffee
- Drugs: Vitamin E, Resmetirom, Glucagon-Like Peptide-1 Receptor Agonists, Pioglitazone
- Supplements Linked to Liver Injury
- Who the 2023 AASLD Guidance Screens
- Key Research Papers
- Connections
- Featured Videos
The 2023 Name Change: Non-Alcoholic Fatty Liver Disease Becomes Metabolic Dysfunction-Associated Steatotic Liver Disease
In June 2023, a multinational consensus convened by three major liver societies (AASLD, EASL, ALEH) retired the term non-alcoholic fatty liver disease (NAFLD) after more than four decades of use. In its place came a new name: metabolic dysfunction-associated steatotic liver disease (MASLD). The accompanying inflammatory form, formerly non-alcoholic steatohepatitis (NASH), was renamed MASH (metabolic dysfunction-associated steatohepatitis).
The change was not cosmetic. Three problems drove it. First, the old term defined the disease by what it was not — "non-alcoholic" — which is clinically awkward and tells you nothing about the actual mechanism. Second, "fatty" carried stigma; patients heard it as a personal failing. Third, the old framework excluded patients who drank any alcohol, even though the underlying metabolic biology is identical whether or not a person enjoys wine on weekends. A new category, MetALD, now covers people who have metabolic-driven steatosis and drink moderate-to-heavy amounts — because in real life, the two problems are routinely stacked.
If you were diagnosed before 2023 and your chart says "non-alcoholic fatty liver disease" or "fatty liver," you have metabolic dysfunction-associated steatotic liver disease by the new criteria unless something unusual was going on (e.g., a genetic or drug-induced steatosis). The biology is the same. The testing is the same. The treatments are the same. Only the label has changed.
Metabolic Dysfunction-Associated Steatotic Liver Disease Diagnostic Criteria
Metabolic dysfunction-associated steatotic liver disease requires two things at once:
- Hepatic steatosis — fat in at least 5% of liver cells, shown on imaging (ultrasound, the CAP score from transient elastography, MRI-PDFF) or biopsy.
- At least one cardiometabolic risk factor:
- Overweight or obesity (body mass index (BMI) ≥ 25 in most populations, ≥ 23 in Asian populations), or increased waist circumference.
- Type 2 diabetes or prediabetes. The 2023 consensus deliberately left direct insulin tests (fasting insulin, HOMA-IR) out of the criteria because of their complexity, cost and lab-to-lab variation, while noting that testing for insulin resistance may help when liver fat appears without these risk factors.
- Hypertension (≥ 130/85 or on treatment).
- Elevated triglycerides (≥ 150 mg/dL) or low high-density lipoprotein (HDL) (< 40 in men, < 50 in women), or on lipid-lowering therapy.
Almost everyone with steatosis meets at least one cardiometabolic criterion, which is the whole point. Liver fat is not a random accident — it is a downstream marker of systemic insulin resistance. If you have fat in your liver and none of the metabolic triggers, the steatosis is probably being driven by something else (alcohol, a medication, a rare genetic disorder) and needs a different workup.
How Common It Is — and Why It's Silent
Metabolic dysfunction-associated steatotic liver disease is the single most common liver disease on the planet. Roughly 30% of US adults have it. Among people with type 2 diabetes, prevalence climbs to 55–70%. Among the severely obese, it exceeds 90%. About one in four people with metabolic dysfunction-associated steatotic liver disease progresses to MASH, where inflammation and fibrosis join the fat deposition, and a smaller subset progresses to cirrhosis or hepatocellular carcinoma.
Yet most people with metabolic dysfunction-associated steatotic liver disease have no idea they have it. The liver has no pain fibers in its parenchyma, so silent fibrosis can advance for years without a single symptom. By the time decompensated cirrhosis appears — ascites, variceal bleeding, hepatic encephalopathy, jaundice — the window for reversal has closed. The tragedy of metabolic dysfunction-associated steatotic liver disease is that it is both extremely common and extremely reversible in its early stages, but almost nobody catches it there.
Metabolic dysfunction-associated steatotic liver disease becomes more likely with any of the following: a waistline that has quietly expanded, a fasting glucose creeping above 100, a fasting triglyceride above 150, borderline blood pressure, polycystic ovary syndrome (PCOS), obstructive sleep apnea, or a family history of type 2 diabetes. This is not hypochondria — it is base rates.
The Mechanism: Hepatic Insulin Resistance
The liver is the central clearinghouse for incoming calories. When you eat carbohydrate, glucose floods the portal vein, and insulin tells the liver to do three things in sequence: take up glucose and store it as glycogen, turn off glucose production, and convert excess carbohydrate into triglyceride for storage (a process called de novo lipogenesis). When insulin signaling works, the system is elegant.
In insulin resistance, the liver's response becomes paradoxically selective. The suppression arm of insulin signaling — "stop making glucose" — weakens, so the liver keeps pouring glucose into the bloodstream even after meals. But the lipogenic arm — "make triglyceride" — remains fully on, and actually accelerates under chronically high insulin. This is called selective hepatic insulin resistance, and it is the reason insulin-resistant livers both raise blood sugar and simultaneously pack themselves with fat.
At the same time, fatty-acid oxidation — the liver's ability to burn stored fat — is impaired. Triglycerides accumulate in hepatocytes. Once the storage droplets exceed a threshold, they leak free fatty acids and ceramides that poison mitochondria, activate inflammatory Kupffer cells, and recruit stellate cells that lay down collagen. Steatosis turns into steatohepatitis; steatohepatitis turns into fibrosis; fibrosis, over years, turns into cirrhosis.
The driver at every step is insulin resistance. Metabolic dysfunction-associated steatotic liver disease is not a liver disease that happens to coexist with diabetes. Metabolic dysfunction-associated steatotic liver disease is the hepatic expression of the same systemic problem that causes type 2 diabetes, metabolic syndrome, and polycystic ovary syndrome.
The Alanine Aminotransferase "Normal Range" Lie
When your doctor looks at your liver enzymes, the single most important number is alanine aminotransferase (ALT). Most US labs report the upper limit of normal as 40 U/L for both sexes. This cutoff is misleading in a way that matters clinically.
The "normal" was set decades ago using reference populations that, by today's standards, were not healthy — they included plenty of unrecognized fatty liver. When researchers restricted the reference group to truly metabolically healthy people (lean, non-diabetic, no viral hepatitis, no steatosis on imaging), the true upper limit of normal dropped to roughly 19 U/L for women and 30 U/L for men (Prati and colleagues, 2002, a study of 6,835 first-time blood donors in Milan). An alanine aminotransferase of 35 may read as "within normal limits" on your report, but in a metabolically healthy person that number is distinctly high.
Practical translation: a "normal" flag on a lab report does not settle the question. The 2023 AASLD guidance calls for a FIB-4 calculation in everyone with liver fat or suspected fatty liver plus obesity and metabolic risk factors, whatever the alanine aminotransferase reads, with transient elastography as a possible next step. Conversely — and this is equally important — a normal alanine aminotransferase does not rule out metabolic dysfunction-associated steatotic liver disease or even MASH with advanced fibrosis. Up to half of patients with significant fibrosis have ALTs in the normal range. Alanine aminotransferase alone does not work as a screening test for liver disease.
FIB-4, Non-Alcoholic Fatty Liver Disease Fibrosis Score, and ELF
Because alanine aminotransferase is unreliable as a standalone test, several composite scores were developed to estimate fibrosis from routinely available blood work.
FIB-4 is the workhorse. The formula is:
FIB-4 = (Age × aspartate aminotransferase, AST) / (Platelet count × √alanine aminotransferase)
Free calculators are everywhere — search "FIB-4 calculator" and any major hepatology site will have one. You already have all four inputs on any recent complete blood count (CBC) plus comprehensive metabolic panel. Interpretation:
- < 1.3 — low probability of advanced fibrosis. The 2023 AASLD guidance repeats the test every 1–2 years in people with prediabetes, type 2 diabetes or two or more metabolic risk factors, and every 2–3 years in others.
- 1.3 to 2.67 — indeterminate. The usual next step is transient elastography or ELF.
- > 2.67 — high probability of advanced fibrosis; this usually leads to a hepatology referral.
FIB-4 loses specificity in people over 65, where age inflates the number; the 2023 AASLD guidance uses a cutoff above 2.0 in people older than 65. The same guidance notes that FIB-4 has low accuracy in people under 35.
The non-alcoholic fatty liver disease Fibrosis Score adds body mass index, diabetes status, and albumin to the inputs and performs slightly better in some populations. The ELF test (Enhanced Liver Fibrosis) is a direct serum panel of three fibrosis biomarkers (hyaluronic acid, PIIINP, TIMP-1). It is more expensive and not always covered by insurance, but it has excellent performance for ruling advanced fibrosis in or out.
Transient Elastography: The Non-Invasive Workhorse
The single most useful test many people have not heard of is transient elastography (often called by the trade name of the best-known machine). It is a bedside ultrasound-like probe that measures two things in about ten minutes, painlessly, without contrast or fasting:
- Liver stiffness in kilopascals (kPa) — a direct estimate of fibrosis. Roughly: < 7 kPa is F0–F1 (minimal), 7–10 kPa suggests F2 (moderate), 10–14 kPa suggests F3 (advanced), and > 14 kPa suggests F4 (cirrhosis). Interpretation adjusts for metabolic dysfunction-associated steatotic liver disease versus viral hepatitis.
- CAP score (controlled attenuation parameter, in dB/m) — a measure of steatosis (fat). Roughly: < 238 is normal, 238–260 is mild (S1), 260–290 is moderate (S2), and > 290 is severe (S3).
Transient elastography is available at most hospital-based hepatology clinics, many gastroenterology practices, and an increasing number of obesity/metabolic clinics. Cash-pay prices typically run $100 to $300 in the US; insurance covers it with a fibrosis workup indication. It is the most important piece of equipment for staging metabolic dysfunction-associated steatotic liver disease without a biopsy, and for tracking response to treatment over months and years. For people with metabolic dysfunction-associated steatotic liver disease risk factors plus an indeterminate FIB-4, transient elastography is the usual next step.
MRI-PDFF and Liver Biopsy
MRI-PDFF (proton-density fat fraction) is the research gold standard for quantifying liver fat, reported as a percentage. It is precise enough to detect changes of a few percentage points and is now the primary endpoint in most MASH drug trials. Availability is expanding but still concentrated at academic centers; expect $500–$1500 cash, variable insurance coverage. For routine care, transient elastography is usually sufficient. For enrollment in a trial or a question that transient elastography cannot answer, MRI-PDFF is the next step up.
Liver biopsy remains the ultimate arbiter of MASH versus simple steatosis, because only tissue can show the ballooning hepatocytes, inflammation, and fibrosis pattern that distinguishes MASH. Pathologists grade biopsies with the NAS (non-alcoholic fatty liver disease Activity Score), which sums steatosis, ballooning, and lobular inflammation, and stage fibrosis separately on a 0–4 scale. Biopsies are invasive, carry a small risk of bleeding, and sample only 1/50,000th of the liver — so sampling error is real. In 2026, biopsy is reserved for cases where non-invasive tests are equivocal, where diagnosis is contested, or where a trial protocol requires it.
Staging: F0 to F4
Fibrosis stage is the strongest predictor of long-term mortality in metabolic dysfunction-associated steatotic liver disease. Inflammation matters, but what ultimately kills the liver is scar tissue. The scale is universal:
- F0 — no fibrosis.
- F1 — perisinusoidal or periportal fibrosis. Easily reversible.
- F2 — both perisinusoidal and periportal. Still highly reversible with sustained weight loss and metabolic correction.
- F3 — bridging fibrosis. Reversible but harder; this is the stage where drug therapy (Resmetirom, glucagon-like peptide-1 (GLP-1) receptor agonists (GLP-1s)) most clearly adds value.
- F4 — cirrhosis. Architectural distortion. Partial reversal is possible; full reversal is not. Shifts the conversation to surveillance for hepatocellular carcinoma and portal hypertension.
The reason to know your stage is that it determines both your urgency and your expectations. F1 metabolic dysfunction-associated steatotic liver disease with a 10% weight loss over a year is essentially a cured problem. F2 and F3 are the stages for which the two approved MASH drugs, resmetirom and semaglutide, are licensed in the U.S.
Reversal Is Real: The Weight-Loss Dose-Response
The most encouraging data in all of metabolic dysfunction-associated steatotic liver disease come from a single landmark study. In 2015, Vilar-Gomez and colleagues followed 293 people with biopsy-proven non-alcoholic steatohepatitis in Havana, Cuba, who were encouraged to adopt recommended lifestyle changes for 52 weeks, and re-biopsied them at the end (paired biopsies were available for 261). After a year, 88 of the 293 (30%) had lost at least 5% of their body weight. The dose-response was clean:
- ≥ 5% body weight loss — NASH (MASH) resolved in 58% (51 of 88) and the activity score (NAS) fell by at least 2 points in 82% (72 of 88), both more often than in people who lost less.
- 7–10% weight loss — every patient in this range who had few risk factors had a lower activity score.
- ≥ 10% weight loss — every patient had a lower activity score, 90% had NASH (MASH) resolved, and fibrosis regressed in 45%.
Almost no other chronic disease has a reversal curve this steep. In this study the highest rates of activity-score reduction, MASH resolution and scar regression came with weight loss of 10% or more. The challenge is the sustained part. What the study does not show: it re-biopsied people once, at one year, so it did not test what happens to the liver when lost weight is regained.
This is why the broader insulin-resistance reversal protocol — diet change plus muscle-building exercise — matters so much. Losing the weight is half the problem. Not regaining it is the other half, and it is the harder half.
Diet: Mediterranean, Low-Carb, TRE
No single eating pattern dominates the evidence, but three approaches have held up well in metabolic dysfunction-associated steatotic liver disease trials:
Mediterranean diet. The best-studied pattern for metabolic dysfunction-associated steatotic liver disease. High in olive oil, nuts, vegetables, legumes, fish; low in red and processed meat, refined carbohydrate, and sugar. Multiple trials show liver-fat reduction independent of weight loss.
Low-carb or ketogenic diet. Removing the raw substrate for de novo lipogenesis (refined carbohydrate and added sugar) drops liver fat faster than any other dietary lever, often within two weeks. How far people go, up to fully ketogenic, varies with goals and tolerance; cutting added sugar and refined grain is the step most often described as the high-value first one.
Time-restricted eating (TRE). Compressing all eating into an 8- to 10-hour window gives the liver a long daily fasting interval to oxidize stored fat rather than laying down more. TRE works modestly well even without changing what you eat; combined with a Mediterranean or low-carb pattern, the effect compounds.
The eating pattern most often described as worst for a fatty liver is grazing all day on snacks, drink juice or sweetened beverages, and eat late into the evening. That pattern keeps insulin elevated for 14+ hours a day and drives de novo lipogenesis nonstop.
Fructose, Alcohol, and Coffee
Fructose is uniquely bad for the liver. Unlike glucose, which any cell can metabolize, fructose is processed almost exclusively in the liver, where it feeds directly into de novo lipogenesis without triggering the normal satiety or insulin response. Sucrose (table sugar) is half fructose; high-fructose corn syrup is 55% fructose. Fruit juice — even "freshly squeezed" — delivers fructose without the fiber and chewing that slow absorption from whole fruit. In metabolic dysfunction-associated steatotic liver disease, cutting liquid fructose (juice, soda, sweetened coffee drinks, sweet teas) is described as one of the single highest-yield changes. Whole fruit, which brings fibre and chewing, is a different exposure from juice.
Alcohol adds to the damage. Every drink adds hepatic fat-synthesis substrate on top of what carbohydrate is already doing. The old cutoff of "up to two drinks a day for men" was based on cardiovascular data, not liver data. In metabolic dysfunction-associated steatotic liver disease specifically, even "moderate" drinking accelerates fibrosis. The 2023 AASLD guidance describes alcohol as a cofactor for progression in everyone with the disease and calls for complete abstinence in people with significant scarring (F2 or higher). People with metabolic-driven steatosis who drink moderate-to-heavy amounts fall into the MetALD category, where the disease progresses faster than it would otherwise.
Coffee is protective. Two to four cups a day of coffee (caffeinated or decaf, black or with a splash of milk, but not loaded with syrup) is consistently associated with lower metabolic dysfunction-associated steatotic liver disease progression, lower fibrosis, and lower hepatocellular carcinoma risk. The mechanism probably involves chlorogenic acids and caffeine's effects on adenosine signaling in the liver. This is one of the few dietary exposures where the "more is better" signal extends to four cups a day for liver outcomes.
Drugs: Vitamin E, Resmetirom, Glucagon-Like Peptide-1 Receptor Agonists, Pioglitazone
Vitamin E 800 international units (IU) daily. In the 2010 PIVENS trial of 247 adults with MASH and without diabetes, vitamin E at 800 international units/day for 96 weeks improved liver biopsy features in 43% versus 19% on placebo; it lowered liver fat and inflammation but did not improve fibrosis scores. The 2023 AASLD guidance says it can be considered in selected people without diabetes. Two safety points come with it: in the large randomized SELECT trial of 35,533 healthy men, vitamin E at 400 international units/day raised prostate cancer risk (hazard ratio 1.17; 1.6 extra cases per 1,000 person-years), and the AASLD guidance notes a raised concern about bleeding and haemorrhagic stroke that still awaits prospective data.
Resmetirom. On March 14, 2024, the U.S. Food and Drug Administration (FDA) granted the first-ever approval for a MASH-specific drug: resmetirom, a thyroid hormone receptor-beta (THR-β) agonist that acts selectively in the liver to accelerate fat oxidation. The phase 3 MAESTRO-NASH trial (Harrison 2024) showed MASH resolution and fibrosis improvement in a meaningful minority of patients with F2–F3 fibrosis. According to the FDA’s announcement, at 12 months 24% to 36% of people on resmetirom (80 or 100 mg) had MASH resolved without worse scarring, against 9% to 13% on placebo, the range reflecting different pathologists’ readings. It is an accelerated approval for non-cirrhotic MASH with moderate to advanced fibrosis, taken orally once daily; the agency lists drug-induced liver toxicity, gallbladder side effects and interactions with statins among its warnings. This is a genuinely new option and has changed the conversation for F2–F3 patients who cannot reach their goals through lifestyle alone.
Glucagon-like peptide-1 receptor agonists. In the phase 3 ESSENCE trial (Sanyal 2025) of 1,197 people with MASH and stage 2 or 3 scarring, weekly semaglutide 2.4 mg cleared MASH without worse scarring in 62.9% versus 34.3% on placebo at week 72 (results for the first 800 patients), and reduced scarring in 36.8% versus 22.4%; body weight fell 10.5% versus 2.0%, and stomach and bowel side effects were more common on semaglutide. On August 15, 2025, the FDA gave semaglutide injection accelerated approval for MASH with moderate-to-advanced scarring, making it the second approved MASH medicine after resmetirom; the trial continues to 240 weeks to see whether the biopsy gains mean fewer deaths, transplants and liver events. Tirzepatide is still in trials for MASH. The FDA describes semaglutide as working through weight loss and possibly other mechanisms not fully understood. These drugs are discussed in more detail on the Metformin, Berberine, and glucagon-like peptide-1 receptor agonists page.
Pioglitazone. The 2016 Cusi trial of 101 people with MASH and prediabetes or type 2 diabetes found that pioglitazone 45 mg/day improved liver histology (58% reached the main goal; 51% had MASH resolved), with 2.5 kg more weight gain than placebo. In the 2010 PIVENS trial of adults without diabetes, pioglitazone’s improvement (34% versus 19% on placebo) missed that trial’s threshold for statistical significance. It carries side effects (weight gain, edema, fracture risk in women, heart-failure caution) that have limited its use; the 2023 AASLD guidance says it can be considered for MASH in people with type 2 diabetes.
Sodium-glucose cotransporter-2 (SGLT2) inhibitors. Empagliflozin, dapagliflozin, and canagliflozin lower liver fat modestly and are already first-line for type 2 diabetes with cardiovascular or kidney risk. For a person with both diabetes and metabolic dysfunction-associated steatotic liver disease, a sodium-glucose cotransporter-2 inhibitor therefore treats the diabetes while modestly lowering liver fat.
Supplements Linked to Liver Injury
The liver is the organ that metabolizes almost everything you swallow, and some popular supplements are directly hepatotoxic. These are the ones the concern centres on for people with metabolic dysfunction-associated steatotic liver disease or MASH:
- High-dose green tea extract (epigallocatechin gallate, EGCG). Standardized pill forms have caused acute liver failure at modest doses. Brewed green tea as a drink has not carried the same reports as concentrated extracts.
- Kava. Banned or restricted in several countries for hepatotoxicity.
- Ashwagandha. Case reports of cholestatic liver injury are accumulating.
- High-dose vitamin A / retinol. Above roughly 10,000 international units/day chronically, retinol is directly hepatotoxic. Beta-carotene is not the same problem.
- Anabolic steroids and "testosterone boosters" with undeclared ingredients — a common cause of drug-induced liver injury in younger patients.
- Unregulated herbal weight-loss products bought online, especially multi-ingredient powders. The literature on these is a rotating cast of liver-failure case reports.
When alanine aminotransferase rises in someone taking a supplement, the usual clinical practice is to stop the supplement and recheck labs after four to six weeks. The liver recovers quickly from drug-induced injury if the offending agent is removed early.
Who the 2023 AASLD Guidance Screens
The 2023 AASLD practice guidance calls for a first FIB-4 in everyone with liver fat or suspected fatty liver plus obesity and metabolic risk factors, and sets how often it is repeated:
- Every 1–2 years with prediabetes, type 2 diabetes, or two or more metabolic risk factors (central obesity, hypertension, dyslipidemia).
- Every 2–3 years without prediabetes or type 2 diabetes and with one or two metabolic risk factors.
- Over age 65 the guidance uses a cutoff above 2.0; under age 35 it notes that FIB-4 has low accuracy.
FIB-4 is free, non-invasive, and calculable from any recent complete blood count plus comprehensive metabolic panel (CMP). In the guidance, a FIB-4 of 1.3 or higher leads to a second test — transient elastography, magnetic resonance elastography or ELF. The reason this matters: by the time a patient presents with ascites or variceal bleeding from cirrhosis, the horse has left the barn. Catching fibrosis at F1 or F2 — while it is still reversible — requires active screening, not waiting for symptoms that will never come until it is too late.
Because all four inputs are on routine blood work, FIB-4 can be calculated by anyone from labs they already have; a result of 1.3 or above is the point at which the guidance moves to a second test such as transient elastography.
Key Research Papers
Foundational publications on the metabolic-hepatic axis — from the original non-alcoholic fatty liver disease/metabolic syndrome link, through global epidemiology, to the 2023 metabolic dysfunction-associated steatotic liver disease nomenclature shift and the first U.S. Food and Drug Administration-approved pharmacotherapy. Each citation links to the full text via DOI.
- Rinella ME, Lazarus JV, Ratziu V, et al. A Multisociety Delphi Consensus Statement on New Fatty Liver Disease Nomenclature. Hepatology. 2023;78(6):1966–1986. — doi:10.1097/HEP.0000000000000520
- Younossi ZM, Koenig AB, Abdelatif D, Fazel Y, Henry L, Wymer M. Global Epidemiology of Nonalcoholic Fatty Liver Disease — Meta-Analytic Assessment of Prevalence, Incidence, and Outcomes. Hepatology. 2016;64(1):73–84. — doi:10.1002/hep.28431
- Marchesini G, Bugianesi E, Forlani G, et al. Nonalcoholic Fatty Liver, Steatohepatitis, and the Metabolic Syndrome. Hepatology. 2003;37(4):917–923. — doi:10.1053/jhep.2003.50161
- Vilar-Gomez E, Martinez-Perez Y, Calzadilla-Bertot L, et al. Weight Loss Through Lifestyle Modification Significantly Reduces Features of Nonalcoholic Steatohepatitis. Gastroenterology. 2015;149(2):367–378. — doi:10.1053/j.gastro.2015.04.005
- Sanyal AJ, Chalasani N, Kowdley KV, et al. Pioglitazone, Vitamin E, or Placebo for Nonalcoholic Steatohepatitis (PIVENS). New England Journal of Medicine. 2010;362(18):1675–1685. — doi:10.1056/NEJMoa0907929
- Harrison SA, Bedossa P, Guy CD, et al. A Phase 3, Randomized, Controlled Trial of Resmetirom in NASH with Liver Fibrosis (MAESTRO-NASH). New England Journal of Medicine. 2024;390(6):497–509. — doi:10.1056/NEJMoa2309000
- Newsome PN, Sasso M, Deeks JJ, et al. FibroScan-AST (FAST) Score for the Non-Invasive Identification of Patients with Non-Alcoholic Steatohepatitis with Significant Activity and Fibrosis: A Prospective Derivation and Global Validation Study. Lancet Gastroenterology & Hepatology. 2020;5(4):362–373. — doi:10.1016/S2468-1253(19)30383-8
- Reaven GM. Banting Lecture 1988. Role of Insulin Resistance in Human Disease. Diabetes. 1988;37(12):1595–1607. — doi:10.2337/diab.37.12.1595
- Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98(4):2133–2223. — doi:10.1152/physrev.00063.2017
- Saltiel AR, Olefsky JM. Inflammatory Mechanisms Linking Obesity and Metabolic Disease. Journal of Clinical Investigation. 2017;127(1):1–4. — doi:10.1172/JCI92035
- Stanhope KL, Schwarz JM, Keim NL, et al. Consuming Fructose-Sweetened, Not Glucose-Sweetened, Beverages Increases Visceral Adiposity and Lipids and Decreases Insulin Sensitivity in Overweight/Obese Humans. Journal of Clinical Investigation. 2009;119(5):1322–1334. — doi:10.1172/JCI37385
- Newsome PN, Buchholtz K, Cusi K, et al. A Placebo-Controlled Trial of Subcutaneous Semaglutide in Nonalcoholic Steatohepatitis. New England Journal of Medicine. 2021;384(12):1113–1124. — doi:10.1056/NEJMoa2028395
- Sanyal AJ, Newsome PN, Kliers I, et al. Phase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis (ESSENCE). New England Journal of Medicine. 2025;392(21):2089–2099. — PubMed PMID: 40305708
- Rinella ME, Neuschwander-Tetri BA, Siddiqui MS, et al. AASLD Practice Guidance on the clinical assessment and management of nonalcoholic fatty liver disease. Hepatology. 2023;77(5):1797–1835. — PubMed PMID: 36727674
- Prati D, Taioli E, Zanella A, et al. Updated definitions of healthy ranges for serum alanine aminotransferase levels. Annals of Internal Medicine. 2002;137(1):1–10. — PubMed PMID: 12093239
- Cusi K, Orsak B, Bril F, et al. Long-Term Pioglitazone Treatment for Patients With Nonalcoholic Steatohepatitis and Prediabetes or Type 2 Diabetes Mellitus: A Randomized Trial. Annals of Internal Medicine. 2016;165(5):305–315. — PubMed PMID: 27322798
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. 2011;306(14):1549–1556. — PubMed PMID: 21990298
- U.S. Food and Drug Administration. FDA Approves First Treatment for Patients with Liver Scarring Due to Fatty Liver Disease (resmetirom). News release, March 14, 2024. — fda.gov
- U.S. Food and Drug Administration. FDA Approves Treatment for Serious Liver Disease Known as ‘MASH’ (semaglutide). August 15, 2025. — fda.gov
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: MASLD nomenclature and consensus
- PubMed: NAFLD and de novo lipogenesis
- PubMed: FIB-4 fibrosis screening
- PubMed: transient elastography in MASLD
- PubMed: MRI-PDFF and liver fat
- PubMed: resmetirom and MAESTRO-NASH
- PubMed: semaglutide in MASH/NASH
- PubMed: weight loss and fibrosis regression
- PubMed: fructose and hepatic steatosis
- PubMed: coffee and liver fibrosis
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Diabetes
- Metabolic Syndrome
- Reversal Protocol: Diet and Fasting
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Exercise and Muscle Insulin Sensitivity
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Polycystic Ovary Syndrome
- Insulin Resistance
- Non-Alcoholic Fatty Liver Disease
- Cirrhosis
- CGM for Non-Diabetics
- Insulin Resistance and Polycystic Ovary Syndrome
- Metabolic Syndrome Cardiovascular Risk
- Obesity
- Vitamin E
- Glucagon-Like Peptide-1 Receptor Agonists
- Fatty Liver Disease
- Fasting
- Gastroenterology