Continuous Glucose Monitors (CGM) for Non-Diabetics
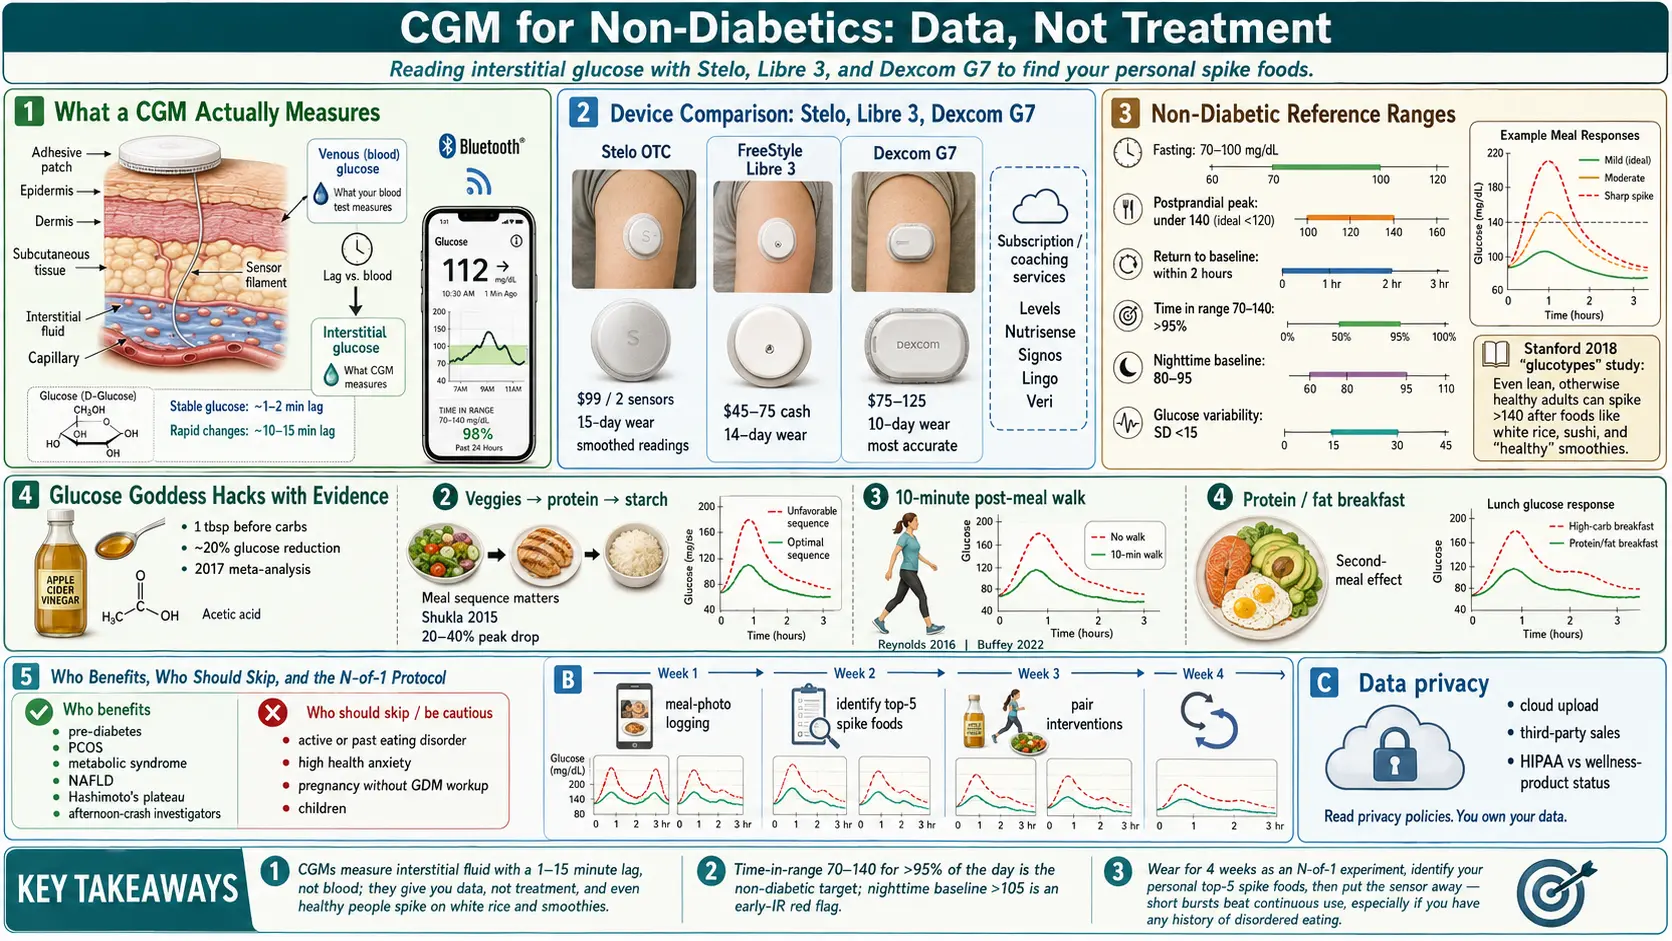
Table of Contents
- What a CGM Actually Measures
- Device Types — 10-Day, 14-Day, Pump-Paired and Over-the-Counter Sensors
- Subscription CGM Services for Non-Diabetics
- How People Without Diabetes Obtain a CGM
- Interpretation Basics — What the Numbers Mean
- Realistic Expectations — Data, Not Treatment
- The N-of-1 Protocol — How to Actually Learn Something
- Popular Glucose “Hacks” — What the Evidence Shows
- Who Benefits Most
- When a CGM Can Do More Harm Than Good
- Practical Troubleshooting — Skin, Sleep, Sensors
- Data Privacy Considerations
- Key Research Papers
- Connections
- Featured Videos
What a CGM Actually Measures
A continuous glucose monitor is a small disc that sticks to the back of your upper arm (or abdomen). A hair-thin filament sits in the fatty layer just under the skin and measures interstitial glucose — the sugar floating in the fluid between your cells — every one to five minutes. A Bluetooth chip sends the reading to your phone, where an app graphs it in near real time.
Here is the important technical detail most marketing glosses over: CGMs do not read blood sugar directly. They read interstitial fluid, which trails venous blood glucose by roughly one to two minutes when glucose is stable and up to ten to fifteen minutes when it is moving fast. That means if you check your CGM two minutes after chugging a soda, the spike you see on screen is already old news; the actual peak in your blood has already crested. And if you compare a CGM reading to a fingerstick meter taken at the same moment, they will almost never match exactly. A 10–15% discrepancy is normal, not a malfunction.
For someone without diabetes, this lag and accuracy range is fine. You are not dosing insulin. You are looking for patterns — does this meal spike me, does that walk flatten my curve — and patterns emerge clearly even with imperfect readings.
Device Types — 10-Day, 14-Day, Pump-Paired and Over-the-Counter Sensors
Four sensor types dominate the U.S. market, each with its own trade-offs.
10-day sensor. Wear time is 10 days. Cash price runs $75–$125 per sensor without insurance. Readings are sent every 5 minutes (FDA 510(k) summary K234070); no fingerstick calibration required. The app supports customizable alerts and integrates with smartwatches.
14-day sensor. 14-day wear per sensor, $45–$75 cash, the lower cost per day of the two. The newest generation is small (about the size of two stacked pennies), pushes readings to the phone every minute, and has improved accuracy over its earlier generations.
Pump-paired sensor. A clinical sensor made by an insulin-pump manufacturer, mostly used inside that manufacturer's pump systems, and rarely used by people without diabetes.
Over-the-counter CGM. In 2024 the U.S. Food and Drug Administration (FDA) cleared the first over-the-counter CGM for non-insulin-using adults, which went on sale that August. No prescription is required; it is sold directly by the manufacturer and through online retailers, roughly $99 for two sensors (about a month of wear) or a subscription near $89/month. It uses the same hardware as that maker's 10-day sensor, but the FDA 510(k) summary (K234070) describes a sensor worn for up to 15 days, an app that shows a new glucose reading and trend every 15 minutes (so the value on screen can be up to 15 minutes old), and no glucose or system alerts at all; it is cleared for adults 18 and older who do not use insulin. A second over-the-counter CGM, built on the 14-day sensor platform, followed later in 2024; its FDA 510(k) summary (K233655) likewise states that it has no alarms.
Subscription CGM Services for Non-Diabetics
A parallel industry has grown up around the CGM — companies that ship you the sensor, an app, and a coaching layer so you do not have to interpret the data alone. They typically route you through a tele-prescribing doctor who writes a cash-pay prescription (this was the only legal path before over-the-counter CGMs existed).
- Meal-score app services. One of the earliest services in the category; the app focuses on per-meal scores and a metabolic dashboard. Roughly $199 for the first month, then a subscription for sensors, running on 14-day or 10-day sensor hardware.
- Dietitian-paired services. The sensor is paired with a registered dietitian who reviews the logs weekly. $299–$399 for a four-week starter; ongoing plans drop to around $250/month.
- Weight-loss services. Aimed at weight loss and exercise, with an algorithm that suggests workouts when glucose is rising. $143–$199/month on an annual plan.
- Prediction-model services. Use only one or two weeks of CGM data, then predict the wearer's glucose response to foods not yet eaten. After the initial wear, the sensor comes off and the prediction model takes over.
- App-only services. At least one European-built app is described as popular with Hashimoto's and polycystic ovary syndrome (PCOS) users.
- Manufacturer direct-to-consumer programs. The second over-the-counter CGM (built on 14-day sensor hardware) is sold by its maker as a direct-to-consumer program, priced around $89/month, the same price point as the first.
What a subscription price covers: the hardware itself costs the company $30–$60, and the premium goes to the app, the coaching, and the tele-prescribing step that over-the-counter CGMs no longer require. An over-the-counter or cash-pay sensor without coaching costs about half as much.
How People Without Diabetes Obtain a CGM
There are three legal routes in the U.S.:
1. Over the counter. No prescription is required for an over-the-counter CGM, which is sold online and typically ships in 3–5 days.
2. A prescription from a primary care doctor. For people with pre-diabetes (hemoglobin A1c 5.7–6.4), elevated fasting insulin (see homeostatic model assessment of insulin resistance (HOMA-IR) testing), polycystic ovary syndrome, metabolic syndrome, or non-alcoholic fatty liver disease (NAFLD), many physicians write a cash-pay prescription for a 14-day or 10-day sensor. Insurance usually will not cover it without a Type 1 or Type 2 diagnosis, but HSA and FSA funds are eligible for CGM sensors with a prescription, which amounts to a 25–35% tax saving on the total cost.
3. A subscription service. These charge a premium for tele-prescribing plus an app, and are used by people whose own doctor declines to prescribe or who want the coaching layer.
Large pharmacy chains and many independent pharmacies stock prescription CGM sensors behind the counter, and the cash price with a prescription is often lower than the list price when insurance is not run.
Interpretation Basics — What the Numbers Mean
The non-diabetic reference ranges are the starting point for reading the data. These are different from the ranges diabetics target because a healthy metabolism is considerably tighter than most CGM apps' default “in range” bands.
- Fasting glucose (morning, before eating): 70–100 mg/dL is normal. 100–125 is pre-diabetic. Over 125 on two separate tests is diabetic.
- Postprandial peak (1–2 hours after a meal): under 140 mg/dL is the goal for a healthy non-diabetic. Under 120 is ideal.
- Return to baseline: in healthy non-diabetic adults glucose is back under 120 within two hours of eating, and within roughly 20 mg/dL of your fasting value by three hours.
- Time in range (70–140): a metabolically healthy adult spends more than 95% of the day inside this band.
- Nighttime baseline: most healthy adults cruise at 80–95 mg/dL overnight. A chronic overnight value over 105 is a red flag for early insulin resistance, even with a normal fasting morning number.
- Glucose variability (standard deviation): under 15 mg/dL over 24 hours indicates a smooth curve. Over 25 signals a roller-coaster pattern worth investigating.
Realistic Expectations — Data, Not Treatment
Here is the blunt version most influencers skip. A CGM gives you data. It does not give you treatment. If you have insulin resistance, the CGM cannot fix it; it can only show you which meals make it worse. And the difference between data and treatment is the difference between a bathroom scale and weight loss — one measures, the other requires work.
More importantly: healthy non-diabetic people spike, too. The 2018 Stanford “glucotypes” study by Michael Snyder's group put CGMs on 57 people with no prior diagnosis of diabetes (screening tests then found that 5 of them met the criteria for type 2 diabetes and 14 for prediabetes) and found that standardized meals produced wildly different responses. Even the participants whose standard tests were normal spent about 15% of the time in the prediabetic range, and a breakfast of cornflakes and milk pushed glucose above 140 mg/dL in 80% of the people tested. Examples of foods that commonly spike non-diabetics:
- White rice, white bread, any refined grain. Glycemic index over 70 hits the bloodstream fast.
- Grapes, bananas, dates, mango. Fructose plus glucose, little fiber, easy to over-eat.
- “Healthy” smoothies. A large smoothie-chain cup can contain 70–90 g of sugar in liquid form — more than a can of soda.
- Breakfast cereal, even “fiber” brands.
- Sushi. The rice is usually doctored with sugar.
- Wine or beer on an empty stomach (biphasic: initial bump, then a reactive low 3–4 hours later).
Seeing your glucose hit 150 after a bowl of jasmine rice is not evidence you are pre-diabetic. It is evidence that you ate jasmine rice. The pattern over days and weeks says more than any single reading.
The N-of-1 Protocol — How to Actually Learn Something
A framework commonly used by non-diabetic CGM wearers is an N-of-1 experiment: the wearer is the only subject, and the aim is to learn their own specific responses, not general truths. As usually described, it runs like this:
- Two sensors back to back (4 weeks total). One week is noise. Four weeks shows patterns across workdays, weekends, menstrual cycles, travel, and the stress curve of real life.
- Every meal logged with a photo and a time-stamp. Most apps do this in two taps. The walk after, the wine, the coffee and the stressful meeting go in the log too.
- Each meal photo paired with its 3-hour glucose curve. Three numbers matter: the peak, the time-to-peak, and the time-to-return-to-baseline. A tight curve peaking under 120 and back down by two hours counts as a “green” meal for that person.
- A personal top 5 spike foods. They often surprise people. For one person it is oats. For another it is grapes. For another it is a specific brand of protein bar sweetened with maltitol.
- Retest — the rematch round. In week three or four, each spike meal is repeated with one variable changed: added fat, added fiber, a 10-minute post-meal walk, eating it later in the day, pairing it with protein. The aim is the lowest-effort swap that flattens the curve.
- Taking it off. After a month most wearers have learned most of what the device can teach. The usual pattern is to put the sensor box away, apply the lessons, and re-wear for a week once or twice a year to recalibrate.
Popular Glucose “Hacks” — What the Evidence Shows
A best-selling glucose-focused diet book codified a set of tricks that CGM-wearers commonly report working. Most have at least modest trial evidence behind them:
- One tablespoon of vinegar in water before a carb-heavy meal. A 2017 meta-analysis of clinical trials found that vinegar taken with a meal lowered post-meal glucose, measured as the area under the glucose curve, compared with control (pooled standardized mean difference −0.60). The mechanism is slowed gastric emptying and inhibition of intestinal alpha-amylase.
- Veggies first, protein and fat second, starch and sugar last. Multiple small crossover trials show this sequence lowers the glucose peak by 20–40% compared with the same foods eaten in reverse.
- A 10-minute walk after eating. Even light walking activates muscle glucose uptake independent of insulin (GLUT4 translocation via contraction). In a 2016 crossover study of 41 adults with type 2 diabetes, walking for 10 minutes after each main meal left the post-meal glucose area 12% lower than one 30-minute walk a day, and 22% lower after the evening meal; people without diabetes were not studied.
- Protein and fat at breakfast instead of sweet carbs. Eggs or Greek yogurt set a flatter curve for the whole day, in part because of next-meal glucose priming (the “second-meal effect”).
- Strength training 2–3x/week. The single biggest lever. See Exercise and Muscle Insulin Sensitivity.
What the hacks will not do is compensate for chronic overeating or a diet built on ultra-processed food. They are polish, not foundation.
Who Benefits Most
CGM as a short-term diagnostic tool is especially useful in:
- Polycystic ovary syndrome. Glucose variability often drives the weight, acne, and cycle irregularity. See polycystic ovary syndrome.
- Pre-diabetes (hemoglobin A1c 5.7–6.4, homeostatic model assessment of insulin resistance > 2). A single month of CGM-guided eating often drops hemoglobin A1c by 0.3–0.5 points at the next lab draw.
- Metabolic syndrome. Three of the five criteria (waist, triglycerides, glucose, high-density lipoprotein (HDL), blood pressure) can shift within weeks of CGM-driven changes.
- Hashimoto's with a weight plateau. People on stable thyroid medication who cannot lose weight often uncover hidden carbohydrate intolerance via CGM.
- Unexplained fatigue or “afternoon crashes.” Many are reactive hypoglycemia following a high-glycemic meal — visible instantly on a CGM trace.
- Athletes dialing fueling strategy. Training zones, fasted work, and carbohydrate tolerance are all legible on a CGM.
When a CGM Can Do More Harm Than Good
This is the section most CGM marketing leaves out. A CGM is a powerful tool, and for some people it does more harm than good. The FDA clearance documents for the over-the-counter devices limit them to adults 18 and older who do not use insulin, and the FDA states that they are not for people with problematic low blood sugar (hypoglycemia), because the devices are not designed to alert the user to it.
- Active or recent eating disorder. Anorexia, bulimia, orthorexia, and avoidant/restrictive food intake disorder (ARFID). The FDA documents for the over-the-counter devices do not list eating disorders, but a CGM gives a restrictive mindset more to restrict.
- High baseline health anxiety. For someone who already catastrophizes lab numbers, watching glucose bounce around all day does not calm them down. It can create new fears about foods that were never a problem.
- Pregnancy (unless gestational diabetes is being worked up). Non-diabetic pregnant women generally do not benefit from CGM and may worsen food anxiety during an already stressful period.
- Children and adolescents without a medical indication. The over-the-counter devices are cleared only for adults 18 and older; in children, CGM is a medical tool, not a quantified-self toy.
- People who will not act on the data. For someone who reads the data, feels guilty and changes nothing, the device becomes an expensive source of shame.
Practical Troubleshooting — Skin, Sleep, Sensors
Skin reactions. About 10–20% of wearers develop itching or a rash at the adhesive site within a few wears. What wearers commonly try, in order of escalation:
- Rotating sites — alternating arms, or the upper abdomen with a prescription.
- Wiping the site with an alcohol swab and letting it dry fully before applying.
- A thin hydrocolloid layer or a skin-prep barrier wipe under the sensor (a liquid skin adhesive, a transparent film dressing, or a dedicated CGM overpatch).
- A rash that persists can be allergic contact dermatitis (a skin allergy to the device): a 2017 report in the journal Contact Dermatitis described 15 people with this allergy to an older generation of the 14-day sensor; all reacted to the sensor's adhesive part, and 12 were allergic to isobornyl acrylate (IBOA), a chemical found in the sensors.
Sleep-disturbing alerts. On prescription CGMs, default low-glucose alarms are calibrated for Type 1 diabetics and go off at 70 mg/dL — a number that is perfectly normal for a non-diabetic overnight. On the 14-day sensor that the second over-the-counter device is based on, the low and high glucose alarms are optional and an urgent-low alarm is mandatory (FDA 510(k) summary K233655). The over-the-counter CGMs give no glucose alerts at all: their FDA 510(k) summaries state that the apps provide no glucose or system alerts, and the FDA states that these devices are not for people with problematic low blood sugar because they are not designed to alert the user to it.
Sensor failures. By wearers' reports, roughly one in every 5–10 sensors fails early — signal loss, premature shutdown, bad adhesive. The major manufacturers replace failed sensors for free when reported to the support line within the warranty window (usually 14 days).
Compression lows. Sleeping on top of the sensor squeezes interstitial fluid out of the area and produces a fake low reading. Real number; artifact reading. If you see a low that appears only at night and resolves the moment you roll over, this is why.
Acetaminophen can briefly skew readings upward on older-generation sensors of the 10-day family; the current generation and its over-the-counter version are much less affected. High-dose vitamin C is labelled as an interfering substance on the 14-day sensor family: the FDA 510(k) summary K222447 records the label threshold as more than 500 mg of vitamin C a day on the earlier sensor, and more than 1,000 mg a day after a modified sensor tail designed to reduce vitamin C interference.
Data Privacy Considerations
Every CGM subscription service uploads your glucose data to the cloud, on the terms set out in its privacy policy. The questions that policy answers:
- Is the data de-identified and sold to third parties (food brands, pharma, insurers)?
- Can you export and delete your complete dataset on request?
- Is the data covered by HIPAA (usually yes if prescribed) or only by the company's privacy policy (usually the case for over-the-counter wellness CGMs)?
- If the company is acquired, where does the dataset go?
These are not paranoid questions. Glucose curves, paired with meal photos and timestamps, are among the most behaviorally revealing datasets that exist.
Key Research Papers
Foundational publications on continuous glucose monitoring in non-diabetic populations, glucose variability, and the behavioral interventions revealed by CGM data. Each citation links to the paper via its DOI or its PubMed record.
- Hall H, Perelman D, Breschi A, et al. Glucotypes Reveal New Patterns of Glucose Dysregulation. PLoS Biology. 2018;16(7):e2005143. — doi:10.1371/journal.pbio.2005143
- Shah VN, DuBose SN, Li Z, et al. Continuous Glucose Monitoring Profiles in Healthy Nondiabetic Participants: A Multicenter Prospective Study. Journal of Clinical Endocrinology & Metabolism. 2019;104(10):4356–4364. — doi:10.1210/jc.2018-02763
- Zeevi D, Korem T, Zmora N, et al. Personalized Nutrition by Prediction of Glycemic Responses. Cell. 2015;163(5):1079–1094. — doi:10.1016/j.cell.2015.11.001
- Klonoff DC, Nguyen KT, Xu NY, et al. Use of Continuous Glucose Monitors by People Without Diabetes: An Idea Whose Time Has Come? Journal of Diabetes Science and Technology. 2023;17(6):1686–1697. — PubMed PMID: 35856435
- Battelino T, Danne T, Bergenstal RM, et al. Clinical Targets for Continuous Glucose Monitoring Data Interpretation: Recommendations From the International Consensus on Time in Range. Diabetes Care. 2019;42(8):1593–1603. — doi:10.2337/dci19-0028
- Knowler WC, Barrett-Connor E, Fowler SE, et al. Reduction in the Incidence of Type 2 Diabetes with Lifestyle Intervention or Metformin (Diabetes Prevention Program). New England Journal of Medicine. 2002;346(6):393–403. — doi:10.1056/NEJMoa012512
- Matthews DR, Hosker JP, Rudenski AS, Naylor BA, Treacher DF, Turner RC. Homeostasis Model Assessment: Insulin Resistance and Beta-Cell Function from Fasting Plasma Glucose and Insulin Concentrations in Man (HOMA). Diabetologia. 1985;28(7):412–419. — doi:10.1007/BF00280883
- Reaven GM. Banting Lecture 1988. Role of Insulin Resistance in Human Disease. Diabetes. 1988;37(12):1595–1607. — doi:10.2337/diab.37.12.1595
- Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98(4):2133–2223. — doi:10.1152/physrev.00063.2017
- Saltiel AR, Olefsky JM. Inflammatory Mechanisms Linking Obesity and Metabolic Disease. Journal of Clinical Investigation. 2017;127(1):1–4. — doi:10.1172/JCI92035
- Reynolds AN, Mann JI, Williams S, Venn BJ. Advice to Walk After Meals Is More Effective for Lowering Postprandial Glycaemia in Type 2 Diabetes Mellitus Than Advice That Does Not Specify Timing. Diabetologia. 2016;59(12):2572–2578. — doi:10.1007/s00125-016-4085-2
- Shukla AP, Iliescu RG, Thomas CE, Aronne LJ. Food Order Has a Significant Impact on Postprandial Glucose and Insulin Levels. Diabetes Care. 2015;38(7):e98–e99. — doi:10.2337/dc15-0429
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Exercise and Muscle Insulin Sensitivity
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Polycystic Ovary Syndrome
- Diabetes
- Insulin Resistance
- Metabolic Syndrome
- Reversal Protocol: Diet and Fasting
- Insulin Resistance and Polycystic Ovary Syndrome
- Non-Alcoholic Fatty Liver Disease & Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Metabolic Syndrome Cardiovascular Risk
- CGM
- Fasting
- Blood Sugar
- Obesity
- Fasting Insulin
- Ultra-Processed Foods
- Sleep, Stress & Cortisol in Insulin Resistance
- Lab Tests