⚠ Evidence warning: Clinical trials or other evidence do not support the claim that nebulized glutathione reduces chronic-sinusitis symptoms, antibiotic use and biofilm burden. This page keeps it as a report of what people, websites or other media say.
Glutathione for Lung Disease (Cystic Fibrosis, COPD, ARDS)
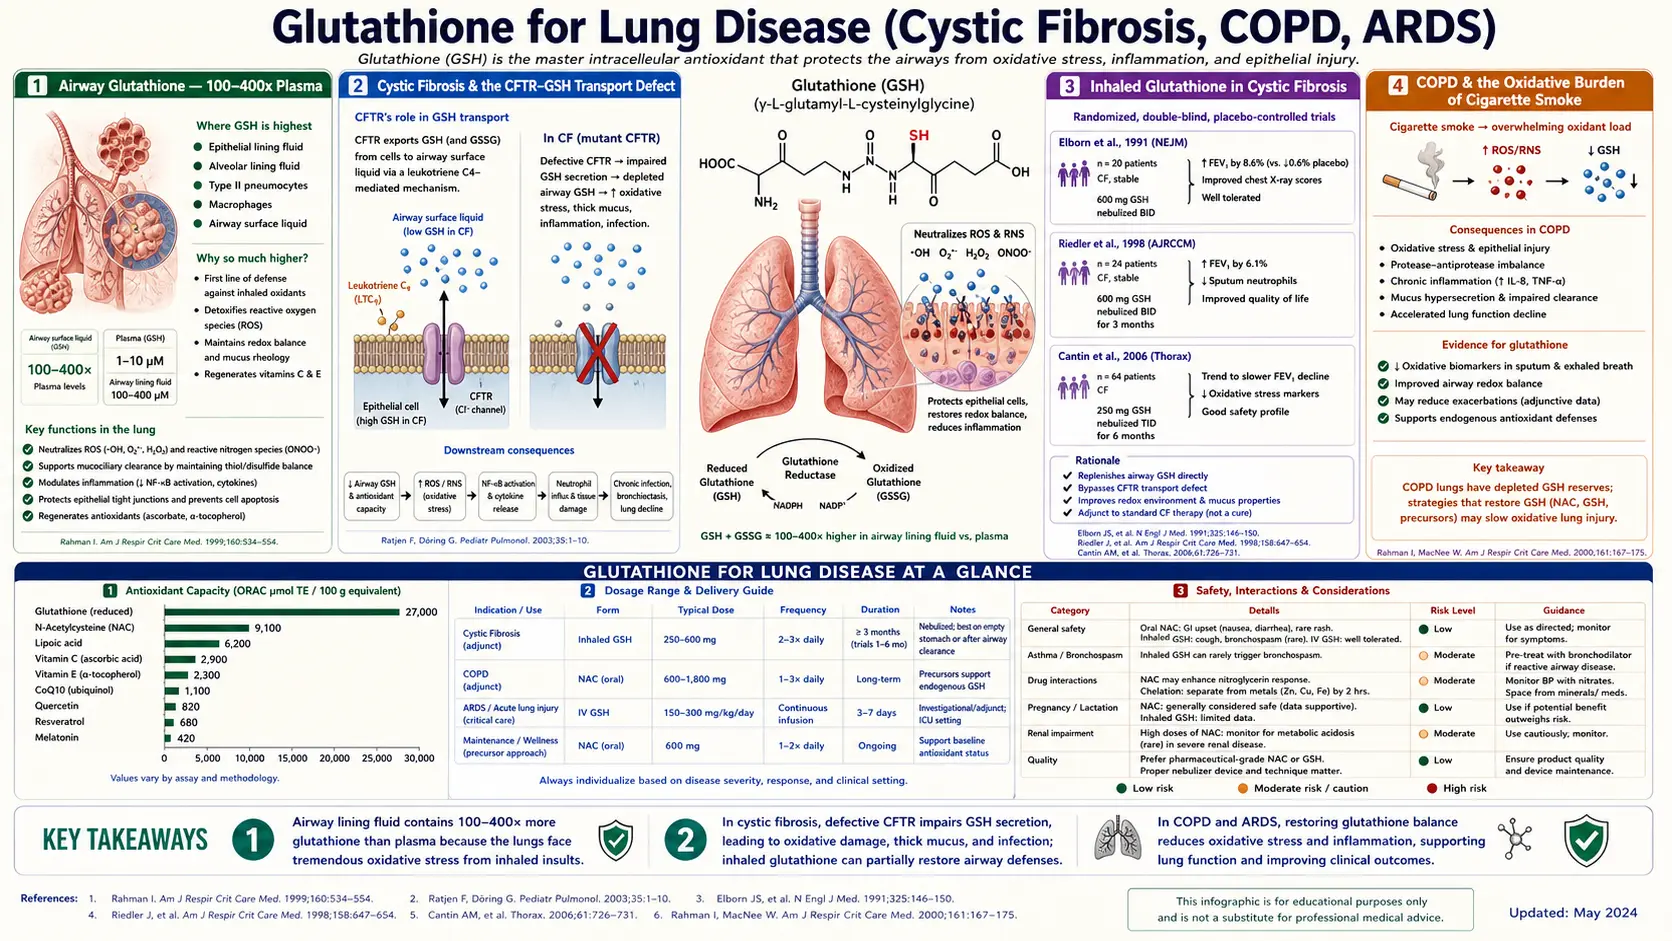
The lungs are uniquely exposed to oxidative stress — they are the only organ in continuous direct contact with 21% atmospheric oxygen, they receive the entire cardiac output, and they handle inhaled pollutants, allergens, infectious agents, and (in some patients) cigarette smoke. To cope with this constant oxidative burden, the airway maintains glutathione in alveolar lining fluid at concentrations about 140× higher than plasma — the highest extracellular reduced glutathione (GSH) concentration anywhere in the body. In cystic fibrosis, mutant CFTR cannot transport glutathione into the airway lumen, leaving CF patients with airway reduced glutathione levels under 10% of normal and accelerated neutrophil-mediated airway destruction. In chronic obstructive pulmonary disease (COPD), cigarette smoke oxidatively damages the airway epithelium; its effect on airway glutathione is not simple — a 1987 study found that the lung lining fluid of chronic smokers held 80% more total glutathione than that of non-smokers. The PANTHEON trial (Zheng 2014, Lancet Respiratory Medicine) showed N-acetylcysteine (NAC) 600 mg twice daily reduced chronic obstructive pulmonary disease exacerbations by 22% in moderate-to-severe disease. Inhaled glutathione for CF, oral N-acetylcysteine for chronic obstructive pulmonary disease, and adjunctive N-acetylcysteine/reduced glutathione in ARDS together form the major glutathione-targeted interventions in pulmonary medicine.
Interactive Visualization Free Radicals & Your Antioxidant Network Follow one superoxide radical down the whole relay — superoxide dismutase (SOD), catalase, glutathione, vitamin E, vitamin C, reduced nicotinamide adenine dinucleotide phosphate (NADPH) — then release free iron and watch a membrane tear itself apart. Launch →
Table of Contents
- Airway Glutathione — About 140× Plasma
- Cystic Fibrosis & the CFTR-GSH Transport Defect
- Inhaled Glutathione in Cystic Fibrosis
- Chronic Obstructive Pulmonary Disease & the Oxidative Burden of Cigarette Smoke
- The PANTHEON Trial & BRONCUS
- N-Acetylcysteine as Mucolytic — Disulfide Bond Disruption
- ARDS & Ventilator-Associated Lung Injury
- Idiopathic Pulmonary Fibrosis (IFIGENIA, PANTHER)
- Chronic Sinusitis & Nebulized Reduced Glutathione
- Asthma & the N-Acetylcysteine Paradox
- Doses Used in Trials and Practice, by Condition
- Cautions Specific to Pulmonary Patients
- Key Research Papers
- Connections
- Featured Videos
Airway Glutathione — About 140× Plasma
The respiratory epithelium maintains the most concentrated extracellular glutathione environment anywhere in the body. Alveolar lining fluid (the thin liquid film coating the alveolar surface) contains glutathione at concentrations of 100-400 micromolar, compared to plasma levels of 1-3 micromolar. The 1987 study that measured it in healthy volunteers (Cantin) found total glutathione in the lining fluid about 140-fold higher than in the same people's plasma, with 96% of it in the reduced form. The total airway glutathione pool (including the bronchial epithelial cell intracellular reduced glutathione and the airway surface fluid) represents one of the largest organ-system reduced glutathione stores in the body.
This concentration is maintained by active transport of intracellular glutathione (synthesized in alveolar type II cells and bronchial epithelial cells) into the airway lumen via the CFTR chloride channel and the MRP family of efflux transporters. The high airway reduced glutathione is the front-line chemical defense against:
- Inhaled oxidant pollutants — ozone, nitrogen dioxide, sulfur dioxide, particulate matter (PM2.5), and other air pollutants directly react with airway reduced glutathione, being neutralized before they can damage the underlying epithelium.
- Reactive oxygen species from immune cells — alveolar macrophages and recruited neutrophils generate large amounts of superoxide, hydrogen peroxide, and hypochlorous acid as part of their bactericidal respiratory burst. Airway reduced glutathione buffers this oxidative output, limiting collateral damage to the airway epithelium.
- Cigarette smoke oxidants — cigarette smoke contains approximately 1015 free radicals per puff in the gas phase alone, plus quinones, semiquinones, and aldehydes in the particulate phase. Airway reduced glutathione is depleted within minutes of smoking and takes hours to replenish.
- Inhaled microorganism virulence factors — many bacterial and fungal toxins generate reactive oxygen species (ROS) as part of their pathogenicity; airway reduced glutathione buffers this damage.
When airway reduced glutathione is depleted — whether through CFTR dysfunction, chronic cigarette smoke exposure, severe acute respiratory inflammation, or systemic reduced glutathione deficiency — the airway epithelium becomes vulnerable to oxidative damage from these same agents. Chronic depletion accelerates airway remodeling, mucus hypersecretion, fibrosis, and progressive airflow obstruction. This is the unifying mechanism underlying CF airway disease, COPD, ARDS, and progressive interstitial lung diseases.
Cystic Fibrosis & the CFTR-GSH Transport Defect
Cystic fibrosis is the genetic disease that most clearly illustrates the role of glutathione in lung biology. CF is caused by mutations in the CFTR gene encoding the cystic fibrosis transmembrane conductance regulator — an apical-membrane chloride channel expressed in airway, intestinal, biliary, pancreatic, and reproductive epithelia.
The dominant CF mutation (F508del, accounting for ~70% of CF alleles) and other major mutations produce dysfunctional CFTR that cannot transport chloride properly. The downstream consequences are well-known: thick, dehydrated airway mucus that impairs mucociliary clearance, leading to chronic bacterial colonization (Pseudomonas, Staphylococcus, Burkholderia), persistent neutrophilic inflammation, progressive bronchiectasis, and ultimately respiratory failure.
A less widely appreciated function of CFTR is that it also transports glutathione (in addition to chloride). When CFTR is non-functional, glutathione cannot be transported from airway epithelial cells into the airway lumen. The consequence is dramatic:
- CF airway surface fluid reduced glutathione is reduced to ~10% of normal in the airways of CF patients
- The remaining reduced glutathione is largely oxidized (GSSG), so functional reducing capacity is even more reduced
- Inflammatory neutrophils continue to generate oxidative mediators (myeloperoxidase, neutrophil elastase, reactive oxygen species) without the normal reduced glutathione-mediated buffer
- The result is amplified oxidative damage to airway epithelium, accelerated airway remodeling, and a vicious cycle of inflammation and damage
This reduced glutathione-transport defect is partly independent of the chloride-transport defect. Even with effective mucus clearance and bacterial control, the airway antioxidant deficiency persists and contributes to disease progression. This is the biological rationale for direct airway glutathione delivery in CF: bypass the broken transport mechanism by inhaling glutathione directly into the airway lumen.
For the broader picture of CF management, see our Cystic Fibrosis page.
Inhaled Glutathione in Cystic Fibrosis
Multiple clinical trials have studied inhaled (nebulized) glutathione as antioxidant therapy in CF. The intervention rationale is straightforward: nebulized reduced glutathione delivers reduced glutathione directly to the airway surface, bypassing the broken CFTR-mediated transport mechanism.
Bishop trial (2005)
An early pilot trial enrolled 19 CF patients aged 6 to 19 to inhaled buffered reduced glutathione (about 66 mg per kg of body weight per day in total, split across four inhalation sessions a day) or placebo for 8 weeks; 9 glutathione and 7 placebo patients made up the final analysis. The glutathione group showed:
- A rise in peak flow of 33.7 L/min, against a fall of 6.5 L/min on placebo (p = 0.04)
- Higher self-reported improvement (4.7 vs 2.8 on a 1-to-5 scale, p = 0.004)
- 11 of the 13 lung-function and symptom outcomes favoured glutathione
- Good tolerability with minimal adverse events
Griese trial (2013)
A larger German trial of 153 CF patients tested inhaled glutathione 646 mg every 12 hours for 6 months. The glutathione arm did not show a statistically significant FEV1 improvement over the 6 months (an exploratory analysis found a gain of 100 mL, or 2.2% of predicted, that was significant at 3 months but not later), and had neither fewer lung flare-ups (pulmonary exacerbations) nor better quality-of-life scores. Sputum glutathione rose, showing the drug reached the lungs, but markers of oxidative stress and inflammation did not change; the authors reported no clinically relevant improvements at this dose. Heterogeneity in baseline severity, antibiotic use, and CFTR genotype likely contributed to the diluted effect.
Calabrese trial (2015)
An Italian single-blind trial randomized 105 patients (54 adults, 51 children) to inhaled glutathione or placebo twice daily for 12 months. It did not reach its pre-set goal of a 15% improvement in FEV1%; only patients with moderate lung disease had a statistically significant FEV1 rise from baseline at 3, 6 and 9 months, and the 6-minute walking test improved in the children. Glutathione was well tolerated.
Cochrane review (Ciofu 2019 update)
The 2019 Cochrane systematic review of antioxidants in CF (20 studies, 924 children and adults) found that inhaled glutathione probably improves lung function (FEV1 % predicted) by about 3.5 percentage points at three months, but not significantly at six months (2.3 points). One study of 153 people found no difference in the time to the first lung flare-up (pulmonary exacerbation), and inhaled glutathione probably made little or no difference to quality of life; adverse events were similar to placebo. Oral N-acetylcysteine probably raised FEV1 % predicted by about 4.4 points at six months (two studies, 109 people). Only 1 of the 20 studies was judged free of bias. The authors called for further, better-designed studies before a firm conclusion can be drawn, and noted that the benefit of antioxidants in people taking the newer CFTR modulator drugs has not yet been studied.
Practical use
In current CF practice, inhaled glutathione is not standard of care but is used in some specialized centers as adjunctive therapy. Typical regimen: reduced glutathione 300-600 mg in 3-4 mL saline, nebulized twice daily, prepared by a compounding pharmacy (glutathione must be reduced form, not oxidized, and is air-sensitive). Many CF clinicians prefer oral N-acetylcysteine 600-1200 mg twice daily as a simpler systemic alternative that has shown similar though smaller benefits in some trials.
The arrival of CFTR modulator therapy (elexacaftor/tezacaftor/ivacaftor) has transformed the CF clinical landscape and reduced the relative importance of antioxidant adjuncts. With effective modulator therapy restoring partial CFTR function, airway reduced glutathione transport is partially restored. However, modulators are not curative, and antioxidant adjuncts may still have a role — particularly for the ~10% of CF patients with mutations not addressed by current modulators.
Chronic Obstructive Pulmonary Disease & the Oxidative Burden of Cigarette Smoke
Chronic obstructive pulmonary disease (COPD) is the third leading cause of death worldwide, responsible for over 3 million deaths annually. The disease encompasses chronic bronchitis (airway mucus hypersecretion and inflammation), emphysema (destruction of alveolar walls and loss of elastic recoil), and small airway disease — usually overlapping in any given patient.
The primary causal mechanism is cigarette smoke exposure. Each cigarette puff contains approximately 1015-1017 free radicals in the gas phase (semiquinones, peroxyl radicals, nitric oxide) plus quinones, semiquinones, aldehydes (acrolein, formaldehyde), and reactive aromatic compounds in the particulate phase. This oxidative burden:
- Depletes airway and intracellular glutathione within minutes; full replenishment takes 12-24 hours
- Recruits neutrophils that release additional reactive oxygen species, elastase, and matrix metalloproteinases
- Inactivates alpha-1-antitrypsin (the major elastase inhibitor) through oxidation of its critical methionine residue, permitting unchecked elastase damage to alveolar walls
- Damages alveolar type II cells, impairing surfactant production
- Activates NF-κB and the inflammatory cytokine cascade
- Promotes goblet cell hyperplasia and mucus hypersecretion
- Drives epigenetic and gene expression changes that persist long after smoking cessation
Even decades after smoking cessation, ex-smokers show persistent reductions in glutathione/cysteine status, ongoing oxidative airway damage markers, and progressive airflow obstruction. The "memory" of cigarette smoke exposure includes a sustained antioxidant deficiency that contributes to continued chronic obstructive pulmonary disease progression.
This is the conceptual basis for the long-running interest in antioxidant supplementation (particularly N-acetylcysteine) as adjunctive therapy in chronic obstructive pulmonary disease. The hypothesis: restore the cellular reduced glutathione pool that smoking has depleted, reduce ongoing oxidative damage, and slow the rate of FEV1 decline.
For the full picture of chronic obstructive pulmonary disease management, see our chronic obstructive pulmonary disease page.
The PANTHEON Trial & BRONCUS
BRONCUS (Decramer et al., 2005, The Lancet)
The Bronchitis Randomized On N-acetylcysteine Cost-Utility Study was a 3-year randomized double-blind placebo-controlled trial of N-acetylcysteine 600 mg daily vs placebo in 523 chronic obstructive pulmonary disease patients in Europe. The trial had mixed results:
- Failed primary endpoint: No significant difference in annual FEV1 decline rate (~50 mL/year in both arms)
- Failed co-primary endpoint: No significant difference in chronic obstructive pulmonary disease exacerbation rate overall (1.25 vs 1.29 per year)
- Subgroup signal: Patients not taking inhaled corticosteroids did show reduced exacerbations with N-acetylcysteine, suggesting the active treatment was being masked by inhaled steroid effects
BRONCUS was widely interpreted as a negative trial that dampened enthusiasm for N-acetylcysteine in chronic obstructive pulmonary disease throughout the late 2000s. However, the subgroup signal kept investigator interest alive, and a key insight emerged: the 600 mg/day N-acetylcysteine dose used in BRONCUS may have been too low to produce meaningful airway antioxidant effects.
PANTHEON (Zheng et al., 2014, Lancet Respiratory Medicine)
The Chinese PANTHEON trial (Prevention of Acute exacerbations of chronic bronchitis with N-acetylcysteine randomized HEterogeneity ON) tested N-acetylcysteine at twice the BRONCUS dose: 600 mg twice daily (1200 mg total/day) vs placebo for 1 year, in 1006 moderate-to-severe chronic obstructive pulmonary disease patients:
- Primary endpoint MET: 22% reduction in annual exacerbation rate (1.16 vs 1.49 exacerbations/year; risk ratio 0.78, p = 0.0011); the authors described the benefit as seen especially in disease of moderate severity
- Significant reduction in moderate and severe exacerbations specifically
- Reduced time to first exacerbation
- Similar safety profile between N-acetylcysteine and placebo
- Benefit was independent of inhaled corticosteroid use
PANTHEON established 600 mg twice daily as the standard N-acetylcysteine dose for chronic obstructive pulmonary disease and reversed the negative reading of BRONCUS. The mechanism is most likely a combination of:
- Restoration of bronchial epithelial intracellular glutathione
- Reduction of neutrophil-mediated oxidative damage
- Mucolytic effect (N-acetylcysteine cleaves mucin disulfide bonds, see next section)
- Modest anti-inflammatory effect through reduced glutathione-mediated NF-κB suppression
Following PANTHEON, the GOLD (Global Initiative for Chronic Obstructive Lung Disease) guidelines updated their recommendations to include N-acetylcysteine 600 mg twice daily as adjunctive therapy for patients with frequent exacerbations, particularly those not on inhaled corticosteroids or with phenotypes suggesting predominant oxidative stress mechanisms.
N-Acetylcysteine as Mucolytic — Disulfide Bond Disruption
Beyond its glutathione-precursor role, N-acetylcysteine has direct mucolytic activity that is mechanistically independent of the antioxidant pathway. Airway mucus contains mucin glycoproteins (predominantly MUC5AC and MUC5B in healthy airways; MUC5AC dominates in disease states like chronic bronchitis and asthma) cross-linked by disulfide bonds between cysteine residues. The cross-linking is what creates the viscoelastic gel structure of mucus.
The free sulfhydryl group on N-acetylcysteine can directly attack and cleave these mucin disulfide bonds, reducing mucus viscosity and improving the rheological properties. The effect is dose-dependent and dose-related: higher local concentrations produce more mucolysis. This is why nebulized N-acetylcysteine (10-20% solution) is used acutely in cystic fibrosis exacerbations, bronchiectasis with thick secretions, and intubated intensive care unit (ICU) patients with impaired airway clearance.
Oral N-acetylcysteine at the PANTHEON dose (600 mg BID) produces measurable but modest mucolytic effect — some patients report reduced sputum viscosity and easier expectoration. The clinical benefit in chronic obstructive pulmonary disease likely combines this mucolytic effect with the antioxidant effect, with the relative contributions varying by patient phenotype.
Other mucolytic strategies that complement N-acetylcysteine include:
- Hypertonic saline (3-7%) — osmotically draws water into the airway, hydrating mucus; standard adjunct in CF and bronchiectasis
- Dornase alfa — recombinant DNase that cleaves DNA from neutrophil debris in CF mucus; CF-specific therapy
- Carbocisteine — a cysteine derivative used in Europe for chronic bronchitis with claimed mucolytic and antioxidant effects
- Erdosteine and ambroxol — mucolytics used in some European countries
A 2019 Cochrane review of oral mucolytics (N-acetylcysteine, carbocisteine, erdosteine and ambroxol; 38 trials, 10,377 people with chronic bronchitis or COPD) found that people taking a mucolytic were more likely to stay free of flare-ups during the study period (Peto odds ratio 1.73, from 28 studies with 6,723 people): on average, 8 people had to take a mucolytic for about nine months for one extra person to stay flare-up-free. Mucolytics were linked to about 0.43 fewer days of disability per person per month and were not associated with more side effects than placebo. The reviewers noted that longer and more recent studies showed smaller benefits than the earlier ones, and found limited effect on lung function or quality of life.
For chronic bronchitis patients with productive cough and thick sputum, the combination of oral N-acetylcysteine 600 mg BID + adequate hydration + regular airway clearance maneuvers (huff coughing, oscillatory PEP, postural drainage) often substantially reduces sputum burden and improves quality of life.
ARDS & Ventilator-Associated Lung Injury
Acute respiratory distress syndrome (ARDS) is acute, severe, diffuse alveolar injury from sepsis, pneumonia, aspiration, trauma, or other systemic insults, resulting in non-cardiogenic pulmonary edema, severe hypoxemia, and reduced lung compliance. Intensive care unit mortality remains 30-40% even with optimal supportive care including low-tidal-volume ventilation and prone positioning.
The pathophysiology of ARDS involves massive oxidative damage to the alveolar-capillary barrier. Activated neutrophils release reactive oxygen species, proteases, and inflammatory mediators that disrupt endothelial and epithelial integrity, allowing protein-rich edema fluid to flood the alveolar space. Alveolar lining fluid reduced glutathione is depleted within hours of ARDS onset, removing the primary chemical defense against further oxidative damage.
Multiple small intensive care unit trials have tested intravenous (IV) N-acetylcysteine and intravenous glutathione as adjunctive ARDS therapy:
- Bernard 1997 trial — 46 ARDS patients randomized to intravenous N-acetylcysteine 70 mg/kg (14 patients), procysteine (17) or placebo (15) every 8 hours for 10 days. Both antioxidants restored red-blood-cell glutathione, shortened the number of days of acute lung injury and raised cardiac index (+14% vs −6% on placebo); mortality did not differ (placebo 40%, N-acetylcysteine 36%, procysteine 35%)
- Domenighetti 1997 trial — 42 patients with established ARDS of various causes (22 on intravenous N-acetylcysteine 190 mg/kg/day for 3 days, 20 on placebo); N-acetylcysteine neither improved oxygenation nor reduced the need for ventilator support, mortality did not differ significantly (32% vs 25% on placebo), and outcomes did not differ in the 19 patients whose ARDS followed sepsis
- Suter 1994 trial — 61 patients with mild-to-moderate acute lung injury (not established ARDS) given intravenous N-acetylcysteine 40 mg/kg/day or placebo for 3 days; oxygenation improved and fewer N-acetylcysteine patients still needed a ventilator at day 3 (17% vs 48%, p = 0.01), but development of ARDS and 1-month mortality (22% vs 35%) were not significantly reduced
- Meta-analysis (Adhikari 2004, Cochrane) — pooled N-acetylcysteine data (five trials, 239 patients) showed no effect on early mortality (relative risk 0.89, 95% CI 0.65 to 1.21); the reviewers found insufficient evidence to support any specific drug treatment for acute lung injury or ARDS
The clinical synthesis: intravenous N-acetylcysteine has biological plausibility and shows some signal of benefit in ARDS, but the effect size is modest and most studies are small. N-acetylcysteine is not standard of care for ARDS but is used in some intensive care units, particularly for sepsis-related ARDS where the additional anti-inflammatory effects may help. No standard ARDS dose exists; the trials above used 70 mg/kg every 8 hours (Bernard), 190 mg/kg/day (Domenighetti) and 40 mg/kg/day (Suter).
For ventilator-associated lung injury more broadly, the antioxidant rationale extends to all critically ill ventilated patients, but the evidence is even weaker than for ARDS specifically. N-acetylcysteine adjunctive use remains a clinician-by-clinician decision.
Idiopathic Pulmonary Fibrosis (IFIGENIA, PANTHER)
Idiopathic pulmonary fibrosis (IPF) is a progressive scarring lung disease of unknown cause, with median survival of 3-5 years from diagnosis. Oxidative stress is implicated in the pathobiology: lower airway reduced glutathione is depleted, oxidative damage markers are elevated, and aberrant epithelial-mesenchymal transition (driving fibroblast activation) is partly redox-mediated.
IFIGENIA (Demedts et al., 2005, NEJM)
The first major N-acetylcysteine trial in IPF. 182 patients were randomized to N-acetylcysteine 600 mg three times daily or placebo, each added to standard prednisone + azathioprine therapy, for 12 months; 155 of them formed the main analysis group. The N-acetylcysteine arm showed:
- Slower decline in vital capacity (a difference of 0.18 litre, or 9%, at 12 months; P = 0.02)
- Slower decline in DLCO (a 24% difference; P = 0.003)
- No significant difference in mortality (9% vs 11% on placebo)
- Fewer bone-marrow side effects (myelotoxic effects) than placebo (P = 0.03)
IFIGENIA produced enthusiasm for N-acetylcysteine as part of standard IPF therapy.
PANTHER-IPF (2012, NEJM)
The follow-up PANTHER trial randomized IPF patients to three arms: triple therapy (prednisone + azathioprine + N-acetylcysteine), N-acetylcysteine alone, or placebo. The triple therapy arm was stopped early due to increased mortality and hospitalization in the active treatment group — an unexpected and concerning finding that overturned the prior practice of triple therapy for IPF.
The N-acetylcysteine-monotherapy vs placebo arms continued. Final analysis (2014) showed:
- No significant difference in FVC decline between N-acetylcysteine and placebo
- No significant difference in mortality
- No significant difference in acute exacerbations
- N-acetylcysteine monotherapy was disappointingly negative
Subgroup analyses
Post-hoc analyses of PANTHER suggested that patients with the TT genotype of the TOLLIP rs3750920 polymorphism may benefit from N-acetylcysteine monotherapy while patients with other genotypes do not. In the 2015 re-analysis (Oldham), N-acetylcysteine was linked to a lower risk of the combined outcome of death, transplant, hospitalization or a fall of 10% or more in FVC in people with the TT genotype (hazard ratio 0.14; P = 0.03), while people with the CC genotype showed a non-significant increase in risk (hazard ratio 3.23; P = 0.10) — a trend toward harm; the pattern was repeated in a separate IPF group. The TT genotype is present in about 25% of people with IPF. This pharmacogenomic finding has not yet been prospectively validated but is being explored in ongoing IPF research: the PRECISIONS trial, whose design was published in 2022, is randomizing 200 people with IPF and the TT genotype to N-acetylcysteine 600 mg three times a day or placebo for 24 months (no results were listed in PubMed as of November 2026).
Current standard of care for IPF is now nintedanib or pirfenidone (anti-fibrotic agents) rather than N-acetylcysteine. N-acetylcysteine is not recommended as standard IPF therapy. Some integrative pulmonologists continue to use N-acetylcysteine adjunctively for patients with documented antioxidant deficiency or with the TOLLIP TT genotype, but this remains exploratory.
Chronic Sinusitis & Nebulized Reduced Glutathione
Chronic rhinosinusitis (CRS) is persistent inflammation of the paranasal sinus mucosa, often with biofilm formation, fungal colonization, and oxidative damage to the sinus epithelium. Standard treatment combines saline irrigation, intranasal corticosteroids, occasional courses of antibiotics, and (in refractory cases) functional endoscopic sinus surgery.
Nebulized glutathione has been used as adjunctive therapy in chronic sinusitis, typically delivered via specialized sinus nebulizers that produce particle sizes appropriate for sinus penetration rather than alveolar deposition. Practitioners report, from small case series and clinical experience:
- Reduced symptom burden (nasal congestion, post-nasal drip, headache)
- Reduced reliance on antibiotics for sinus exacerbations
- Improved tolerance of saline irrigation
- Possible reduction in biofilm burden through disulfide bond disruption (parallel to mucin-disrupting mechanism in airway mucus)
Typical regimen: reduced glutathione 100-200 mg in 3-5 mL saline, nebulized via sinus nebulizer once or twice daily. Often combined with topical lactoferrin or xylitol for synergistic antimicrobial effects. The intervention requires compounding pharmacy preparation of fresh reduced glutathione solution (oxidizes within days even refrigerated).
The evidence base is limited (mostly observational and small case series); practitioners describe the safety profile as excellent and their clinical experience as favorable, and use it as an add-on for people whose sinusitis has not responded to standard therapy or who want to reduce antibiotic exposure.
Asthma & the N-Acetylcysteine Paradox
Asthma shares pathophysiological features with chronic obstructive pulmonary disease — airway inflammation, oxidative stress, and mucus production — and might therefore seem like a natural target for N-acetylcysteine therapy. However, the asthma situation is more complex.
- Some asthmatic patients have reduced bronchial reduced glutathione and might theoretically benefit from precursor supplementation
- Small trials of oral N-acetylcysteine in asthma have shown modest reductions in symptom scores and inhaled bronchodilator use
- The paradoxical bronchospasm risk — nebulized N-acetylcysteine at high concentrations can trigger bronchospasm in some asthmatic patients, particularly those with sulfite sensitivity. The same risk exists at lower frequency with oral N-acetylcysteine.
- Sulfa allergy is not a true contraindication — N-acetylcysteine's sulfhydryl group is chemically distinct from sulfonamide-containing "sulfa drugs", but some patients with sulfa sensitivity tolerate N-acetylcysteine poorly
- Clinical practice: some clinicians use N-acetylcysteine in carefully selected asthmatic patients with refractory disease, giving the first dose under supervision to check tolerability
For most asthma patients, the standard of care remains inhaled corticosteroids, long-acting beta-agonists, leukotriene modifiers, and (for severe disease) biologic agents targeting immunoglobulin E (IgE) (omalizumab), IL-5 (mepolizumab, reslizumab), or IL-4/IL-13 (dupilumab). N-acetylcysteine is at most an adjunctive consideration.
Doses Used in Trials and Practice, by Condition
Chronic Obstructive Pulmonary Disease (moderate-to-severe, frequent exacerbations)
- N-acetylcysteine 600 mg twice daily — the PANTHEON dose, which reduced exacerbations over 1 year
- Duration — PANTHEON measured its benefit over 1 year of continuous use, BRONCUS over 3 years
- Glycine 3-5 g/day — used by some practitioners alongside N-acetylcysteine for broader reduced glutathione support (not tested in the COPD trials above)
- Selenium 100-200 mcg/day — included in some practitioners' regimens
- Standard care: inhaled bronchodilators and inhaled corticosteroids
- Stopping smoking — described in COPD care as the single most important intervention
- Pneumococcal and influenza vaccination
Cystic fibrosis
- CFTR modulator therapy (elexacaftor/tezacaftor/ivacaftor), prescribed by CF specialists — primary therapy for amenable mutations
- Oral N-acetylcysteine 600 mg twice daily — systemic reduced glutathione support
- Inhaled glutathione 300-600 mg twice daily via nebulizer (compounding pharmacy preparation) — used in some specialized centers
- Inhaled hypertonic saline 7% twice daily — standard mucus hydration
- Dornase alfa per CF protocol
- Airway clearance therapy daily
- Selenium 100-200 mcg/day
- Pancreatic enzyme replacement, vitamin ADEK supplementation per CF protocol
ARDS (ICU setting, by clinician decision)
- Standard ARDS care: lung-protective ventilation (low tidal volume, low plateau pressure), prone positioning for severe cases, conservative fluid management
- Intravenous N-acetylcysteine — trial doses were 70 mg/kg every 8 hours (Bernard), 190 mg/kg/day (Domenighetti) and 40 mg/kg/day (Suter); not standard of care, and pooled trials showed no effect on early mortality (Adhikari 2004)
- Identification and treatment of underlying cause (sepsis, pneumonia, aspiration)
Chronic sinusitis (refractory)
- Standard care: saline irrigation, intranasal corticosteroids, treatment of underlying allergies or biofilm
- Nebulized glutathione 100-200 mg once or twice daily via sinus nebulizer (compounding pharmacy preparation)
- Oral N-acetylcysteine 600 mg twice daily — used by some practitioners for systemic support
- Ear, nose and throat (ENT) specialist evaluation is the usual next step when medical management does not help
Asthma (selected patients)
- Standard of care: inhaled corticosteroid + long-acting beta-agonist, biologic agents for severe asthma
- Oral N-acetylcysteine 600 mg twice daily — used in some carefully selected patients with refractory symptoms, with the first dose given under supervision
- Nebulized N-acetylcysteine — bronchospasm has been reported in people with asthma
Idiopathic pulmonary fibrosis
- Standard of care: nintedanib or pirfenidone
- N-acetylcysteine not routinely recommended (PANTHER negative result)
- TOLLIP TT genotype — the subgroup in which a PANTHER re-analysis found a lower risk on N-acetylcysteine; the PRECISIONS trial is testing it
- Pulmonary rehabilitation, supplemental oxygen, lung transplant evaluation for advanced disease
Cautions Specific to Pulmonary Patients
- N-acetylcysteine paradoxical bronchospasm in asthmatics — the most important pulmonary-specific N-acetylcysteine caution. Some asthmatic patients develop bronchospasm with oral or particularly nebulized N-acetylcysteine. The cautious practice described for people with reactive airways is a supervised first dose with a bronchodilator at hand, and nebulized N-acetylcysteine in people with asthma is generally reserved for specific indications with monitoring.
- Inhaled glutathione preparation — must be reduced (not oxidized) glutathione; air-sensitive and oxidizes within days even refrigerated. Requires compounding pharmacy with experience preparing reduced glutathione for inhalation. Compounded solutions are typically used within 1-2 weeks of preparation.
- Sulfite sensitivity — some patients with sulfite-sensitive asthma have cross-reactivity with N-acetylcysteine and inhaled glutathione.
- Drug interactions in pulmonary patients — N-acetylcysteine may modestly enhance nitroglycerin effects (relevant for patients with coronary artery disease (CAD) comorbidity); no significant interactions with bronchodilators or inhaled corticosteroids.
- Acetylcysteine-tetracycline interaction — theoretical concern that N-acetylcysteine chelates tetracycline; the usual practice is to separate the two doses by 2 or more hours.
- Sulfurous breath odor — common with chronic N-acetylcysteine; can be socially limiting; lower doses and taking it with food are the usual ways it is managed.
- Gastrointestinal (GI) side effects — nausea, indigestion, occasional diarrhea, particularly with high doses; usually resolves with food.
- Renal function — N-acetylcysteine doses are commonly reduced in significant chronic kidney disease (CKD).
- Mucus over-clearance — rare paradoxical concern with high-dose mucolytic N-acetylcysteine: in patients with impaired cough or swallow function, very fluid mucus can pool in airways when airway clearance is poor.
- Pregnancy — chronic N-acetylcysteine use in pregnancy lacks safety data; its established use in pregnancy is the treatment of acetaminophen (paracetamol) overdose.
Key Research Papers
- Zheng JP, Wen FQ, Bai CX, Wan HY, Kang J, Chen P, Yao WZ, Ma LJ, Li X, Raiteri L, Sardina M, Gao Y, Wang BS, Zhong NS (2014). Twice daily N-acetylcysteine 600 mg for exacerbations of chronic obstructive pulmonary disease (PANTHEON): a randomised, double-blind placebo-controlled trial. Lancet Respiratory Medicine. — PubMed PMID: 24621680
- Decramer M, Rutten-van Mölken M, Dekhuijzen PNR, et al. (2005). Effects of N-acetylcysteine on outcomes in chronic obstructive pulmonary disease (BRONCUS): a randomised placebo-controlled trial. The Lancet. — PubMed PMID: 15866309
- Demedts M, Behr J, Buhl R, et al.; IFIGENIA Study Group (2005). High-dose acetylcysteine in idiopathic pulmonary fibrosis. New England Journal of Medicine. — PubMed PMID: 16306520
- Idiopathic Pulmonary Fibrosis Clinical Research Network; Raghu G, Anstrom KJ, King TE Jr, Lasky JA, Martinez FJ (2012). Prednisone, azathioprine, and N-acetylcysteine for pulmonary fibrosis. New England Journal of Medicine. — PubMed PMID: 22607134
- Idiopathic Pulmonary Fibrosis Clinical Research Network; Martinez FJ, de Andrade JA, Anstrom KJ, King TE Jr, Raghu G (2014). Randomized trial of acetylcysteine in idiopathic pulmonary fibrosis. New England Journal of Medicine. — PubMed PMID: 24836309
- Oldham JM, Ma SF, Martinez FJ, Anstrom KJ, Raghu G, Schwartz DA, Valenzi E, Witt L, Lee C, Vij R, Huang Y, Strek ME, Noth I; IPFnet Investigators (2015). TOLLIP, MUC5B, and the Response to N-Acetylcysteine among Individuals with Idiopathic Pulmonary Fibrosis. American Journal of Respiratory and Critical Care Medicine. — PubMed PMID: 26331942
- Podolanczuk AJ, Kim JS, Cooper CB, Lasky JA, Murray S, Oldham JM, Raghu G, Flaherty KR, Spino C, Noth I, Martinez FJ; PRECISIONS Study Team (2022). Design and rationale for the prospective treatment efficacy in IPF using genotype for NAC selection (PRECISIONS) clinical trial. BMC Pulmonary Medicine. — PubMed PMID: 36514019
- Bishop C, Hudson VM, Hilton SC, Wilde C (2005). A pilot study of the effect of inhaled buffered reduced glutathione on the clinical status of patients with cystic fibrosis. Chest. — PubMed PMID: 15653998
- Griese M, Kappler M, Eismann C, Ballmann M, Junge S, Rietschel E, van Koningsbruggen-Rietschel S, Staab D, Rolinck-Werninghaus C, Mellies U, Köhnlein T, Wagner T, König S, Teschler H, Heuer HE, Kopp M, Heyder S, Hammermann J, Küster P, Honer M, Mansmann U, Beck-Speier I, Hartl D, Fuchs C; Glutathione Study Group; Hector A (2013). Inhalation treatment with glutathione in patients with cystic fibrosis: a randomized clinical trial. American Journal of Respiratory and Critical Care Medicine. — PubMed PMID: 23631796
- Ciofu O, Smith S, Lykkesfeldt J (2019). Antioxidant supplementation for lung disease in cystic fibrosis. Cochrane Database of Systematic Reviews. — PubMed PMID: 31580490
- Calabrese C, Tosco A, Abete P, Carnovale V, Basile C, Magliocca A, Quattrucci S, De Sanctis S, Alatri F, Mazzarella G, De Pietro L, Turino C, Melillo E, Buonpensiero P, Di Pasqua A, Raia V (2015). Randomized, single blind, controlled trial of inhaled glutathione vs placebo in patients with cystic fibrosis. Journal of Cystic Fibrosis. — PubMed PMID: 25458463
- Bernard GR, Wheeler AP, Arons MM, et al. (1997). A trial of antioxidants N-acetylcysteine and procysteine in ARDS. Chest. — PubMed PMID: 9228372
- Domenighetti G, Suter PM, Schaller MD, Ritz R, Perret C (1997). Treatment with N-acetylcysteine during acute respiratory distress syndrome: a randomized, double-blind, placebo-controlled clinical study. Journal of Critical Care. — PubMed PMID: 9459113
- Suter PM, Domenighetti G, Schaller MD, Laverrière MC, Ritz R, Perret C (1994). N-acetylcysteine enhances recovery from acute lung injury in man. A randomized, double-blind, placebo-controlled clinical study. Chest. — PubMed PMID: 8275731
- Adhikari N, Burns KE, Meade MO (2004). Pharmacologic therapies for adults with acute lung injury and acute respiratory distress syndrome. Cochrane Database of Systematic Reviews. — PubMed PMID: 15495113
- Cantin AM, North SL, Hubbard RC, Crystal RG (1987). Normal alveolar epithelial lining fluid contains high levels of glutathione. Journal of Applied Physiology. — PubMed PMID: 3040659
- Gao L, Kim KJ, Yankaskas JR, Forman HJ (1999). Abnormal glutathione transport in cystic fibrosis airway epithelia. American Journal of Physiology — Lung Cellular and Molecular Physiology. — PubMed PMID: 10409237
- Rahman I, MacNee W (2000). Oxidative stress and regulation of glutathione in lung inflammation. European Respiratory Journal. — PubMed PMID: 11028671
- Poole P, Sathananthan K, Fortescue R (2019). Mucolytic agents versus placebo for chronic bronchitis or chronic obstructive pulmonary disease. Cochrane Database of Systematic Reviews. — PubMed PMID: 31107966
- Sadowska AM, Manuel-Y-Keenoy B, De Backer WA (2007). Antioxidant and anti-inflammatory efficacy of NAC in the treatment of COPD: discordant in vitro and in vivo dose-effects: a review. Pulmonary Pharmacology & Therapeutics. — PubMed PMID: 16458553
PubMed Topic Searches
Connections
- Free Radicals & Your Antioxidant Network — interactive animation
- Glutathione Overview
- Reduced Glutathione Benefits Hub
- Reduced Glutathione for Liver Detoxification
- Reduced Glutathione for Aging (GlyNAC)
- Reduced Glutathione for Parkinson's
- N-Acetylcysteine (Primary Precursor)
- Alpha Lipoic Acid
- Coenzyme Q10
- Cysteine
- Glycine
- Methionine
- Selenium
- Zinc
- Vitamin C
- Vitamin D
- Vitamin E
- Cystic Fibrosis
- Chronic Obstructive Pulmonary Disease
- Asthma
- Chronic Bronchitis
- Pulmonary Fibrosis
- Chronic Sinusitis
- Cigarette Smoke
- Air Pollution
- Oxidative Stress
- All Antioxidants
- History