Coenzyme Q10 (CoQ10) for Statin-Associated Muscle Symptoms (SAMS)
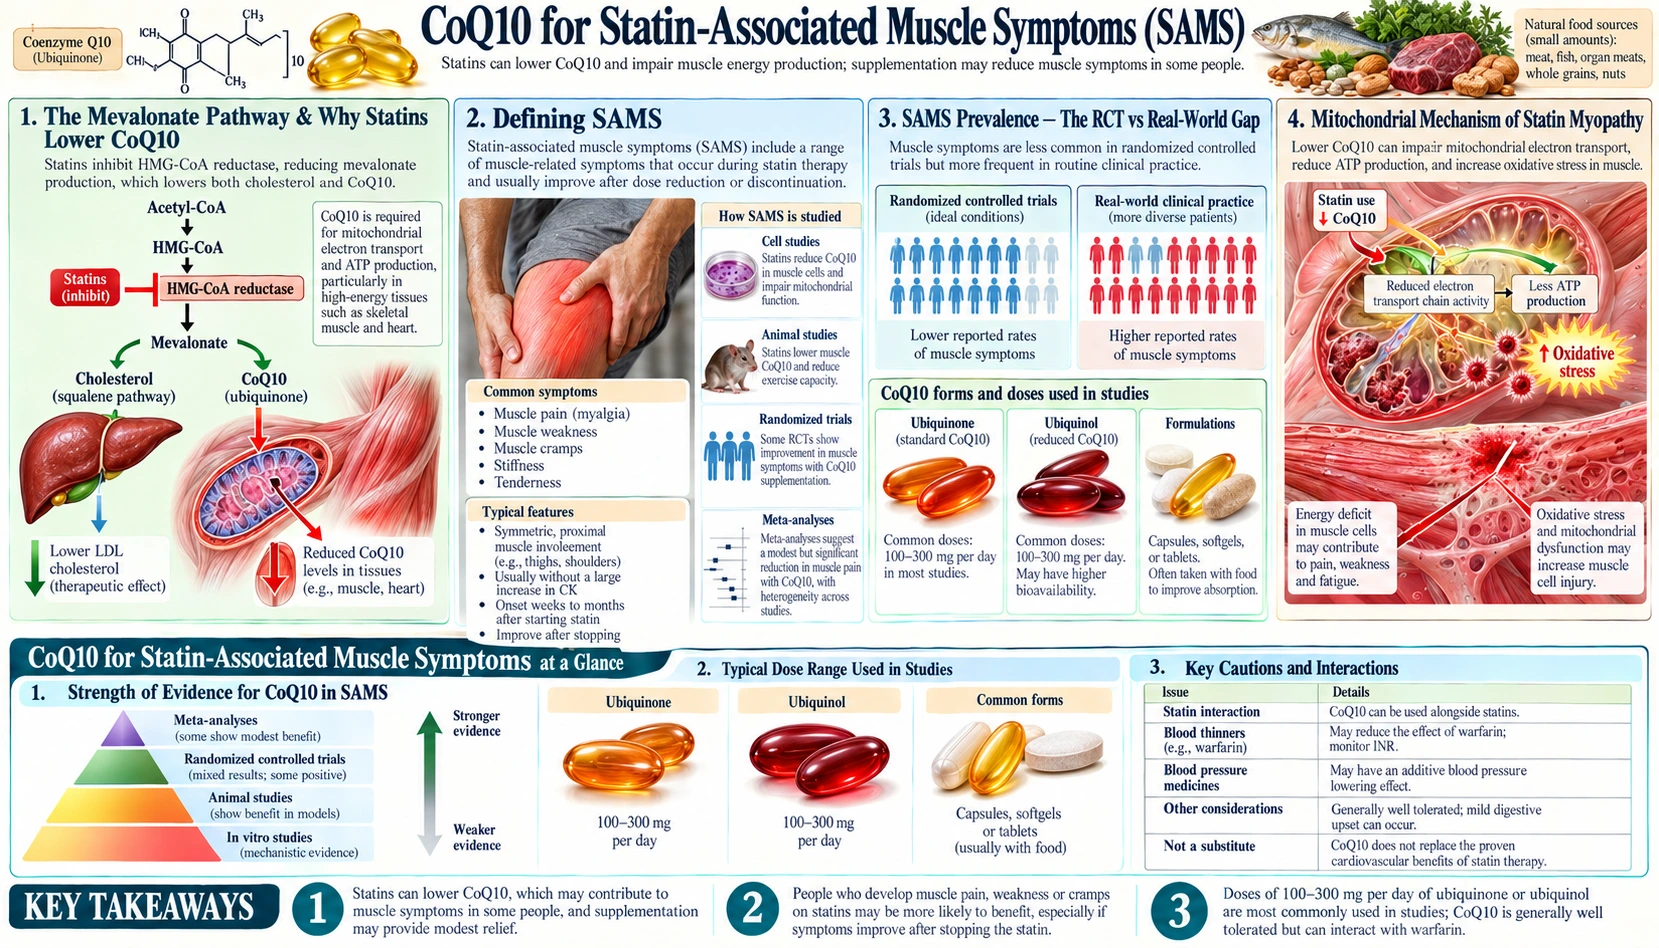
Statin drugs (atorvastatin, simvastatin, rosuvastatin, pravastatin, lovastatin, pitavastatin) lower low-density lipoprotein (LDL) cholesterol by inhibiting HMG-CoA reductase, the rate-limiting enzyme of the mevalonate pathway. Coenzyme Q10 (CoQ10) biosynthesis branches off the same pathway downstream of HMG-CoA reductase, and a 2015 meta-analysis of placebo-controlled trials found that statins lower plasma coenzyme Q10. In one study, atorvastatin 80 mg/day roughly halved blood coenzyme Q10 within 30 days; muscle-biopsy findings are less consistent. Statin-Associated Muscle Symptoms (SAMS) — pain, weakness, cramping, exercise intolerance — are reported by 7-29% of statin users in registries and observational studies. The coenzyme Q10 evidence is split: the Qu 2018 meta-analysis (12 trials, 575 patients) found less muscle pain, weakness, cramping and tiredness with coenzyme Q10, while the Banach 2015 (6 studies, 302 patients) and Kennedy 2020 (7 trials, 321 patients) meta-analyses found no significant benefit. This deep-dive walks through the mevalonate-pathway mechanism, the SAMS prevalence question, the doses used in the trials, and the statin-switching and non-statin options described in consensus documents.
Interactive Visualization Free Radicals & Your Antioxidant Network Follow one superoxide radical down the whole relay — superoxide dismutase (SOD), catalase, glutathione, vitamin E, vitamin C, reduced nicotinamide adenine dinucleotide phosphate (NADPH) — then release free iron and watch a membrane tear itself apart. Launch →
Table of Contents
- The Mevalonate Pathway & Why Statins Lower Coenzyme Q10
- Defining SAMS
- SAMS Prevalence — The Randomized Controlled Trial vs Real-World Gap
- Mitochondrial Mechanism of Statin Myopathy
- Serum Coenzyme Q10 vs Muscle Coenzyme Q10 Depletion
- The Banach 2015 Meta-Analysis
- The Skarlovnik 2014 Trial
- The Taylor 2015 Negative Trial
- The Qu 2018 Updated Meta-Analysis
- Prophylactic Use vs Treatment: What Was Studied
- Statin Switching and Non-Statin Options
- Trial Regimens at a Glance
- The Nocebo Question (SAMSON Trial)
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Mevalonate Pathway & Why Statins Lower Coenzyme Q10
The mevalonate pathway is one of the most important anabolic pathways in human biochemistry. Starting from acetyl-CoA, it produces a long list of essential isoprenoid molecules:
- Cholesterol — the membrane lipid and the precursor of all steroid hormones, bile acids, and vitamin D
- Coenzyme Q10 — the mitochondrial electron carrier
- Dolichol — required for N-glycosylation of membrane proteins
- Heme A — the heme variant required for Complex IV of the electron transport chain
- Geranylgeranyl-PP and farnesyl-PP — required for prenylation of small GTPases (Ras, Rho, Rac) that regulate cell signaling and cytoskeletal dynamics
- Selenoproteins — their synthesis depends on isopentenylation of the selenocysteine transfer RNA, which uses a mevalonate-pathway product; Moosmann and Behl (2004) proposed that impaired selenoprotein synthesis could explain some statin side effects, statin myopathy in particular
The rate-limiting enzyme of the pathway is HMG-CoA reductase, which converts HMG-CoA (3-hydroxy-3-methylglutaryl coenzyme A) to mevalonate. Statins are competitive inhibitors of HMG-CoA reductase. They reduce hepatic cholesterol synthesis, which in turn upregulates hepatic low-density lipoprotein receptor expression, increasing low-density lipoprotein clearance from the circulation. The result is the low-density lipoprotein-lowering effect that has made statins among the most widely prescribed drugs in the world.
But by blocking HMG-CoA reductase, statins also reduce synthesis of the downstream mevalonate-pathway products — including coenzyme Q10. The body's coenzyme Q10 supply comes from two sources: dietary intake (estimated at 3-5 mg/day in the average Danish diet, mostly from meat and poultry; the optimal intake is unknown) and endogenous synthesis through the mevalonate pathway. In a randomized trial of high-dose simvastatin (80 mg/day) and atorvastatin (40 mg/day), a plasma marker of the body's own cholesterol synthesis fell by 66% in both statin groups (Päivä 2005), and a meta-analysis of 8 placebo-controlled trial arms found a significant fall in plasma coenzyme Q10 with atorvastatin, simvastatin, rosuvastatin and pravastatin alike (Banach 2015, Pharmacological Research).
The mevalonate-pathway block also reduces synthesis of geranylgeranyl-PP and farnesyl-PP — the isoprenoid donors for protein prenylation. Reduced prenylation of small GTPases interferes with skeletal muscle membrane signaling and may contribute to statin myopathy through an entirely separate mechanism from coenzyme Q10 depletion. This "pleiotropic" effect is one proposed reason why coenzyme Q10 supplementation would not be expected to reverse every case of SAMS — it addresses one proposed mechanism but not the others.
Defining SAMS
Statin-Associated Muscle Symptoms (SAMS) is the umbrella term for the spectrum of muscle complaints that develop in patients on statin therapy. The National Lipid Association's 2014 Statin Muscle Safety Task Force update reviewed the definitions used for statin-associated muscle adverse events. The categories in common use are:
- Myalgia — muscle pain or aching without a significant enzyme elevation; the most common presentation. The 2015 European Atherosclerosis Society (EAS) consensus panel puts the prevalence of these symptoms, usually with normal or minimally elevated creatine kinase (CK), at 7-29% in registries and observational studies
- Myopathy — muscle symptoms with a significant creatine kinase elevation; the EAS panel estimates 1 per 1,000 to 1 per 10,000 people on standard statin doses
- Rhabdomyolysis — severe muscle breakdown with myoglobinuria and acute kidney injury risk; very rare — about 3.4 cases per 100,000 person-years in cohort studies of statins other than cerivastatin (Law & Rudnicka 2006)
- Statin-induced necrotizing autoimmune myopathy (IMNM) — an autoimmune phenotype with antibodies against HMG-CoA reductase (anti-HMGCR; Mammen 2011); rare, and it can persist after the statin is stopped
SAMS is typically described as appearing within weeks to months of starting a statin (or after dose escalation) as bilateral, symmetric, proximal muscle pain or weakness — thighs, hips, shoulders, and upper arms most commonly. The pain is often described as aching, cramping, soreness, or fatigue rather than sharp pain. Exercise tolerance falls, recovery from physical activity prolongs, and stair climbing or rising from chairs becomes notably more difficult.
The differential diagnosis is broad — hypothyroidism, vitamin D deficiency, polymyalgia rheumatica, fibromyalgia, polymyositis, and primary muscle disease can all mimic SAMS. The EAS consensus panel identifies SAMS by symptoms typical of statin myalgia (muscle pain or aching) and their temporal association with stopping the statin and with repeated re-challenge: symptoms that ease after the statin is stopped ("dechallenge") and return on a "rechallenge" with the same or a different statin support the diagnosis.
Patients with SAMS often progress through multiple statin trials before either tolerating one well or being switched to non-statin low-density lipoprotein-lowering therapy (ezetimibe, PCSK9 inhibitors, bempedoic acid).
SAMS Prevalence — The Randomized Controlled Trial vs Real-World Gap
A contested question in lipidology is how common SAMS actually is. Blinded randomized controlled trials (RCTs) find muscle symptoms almost as often on placebo as on a statin: in a 2022 individual-participant meta-analysis of 19 double-blind statin-versus-placebo trials (123,940 participants), 27.1% of those allocated a statin and 26.6% of those allocated placebo reported muscle pain or weakness during a weighted average median follow-up of 4.3 years (Cholesterol Treatment Trialists' Collaboration). Registries and observational studies report muscle symptoms in 7-29% of statin users (EAS 2015). The disagreement is striking and persistent.
Several explanations are advanced for the gap:
- Randomized controlled trial (RCT) inclusion criteria — many randomized controlled trials exclude patients with prior statin intolerance, baseline muscle symptoms, or active rheumatologic disease. The resulting trial population may not represent the broader patient pool actually prescribed statins.
- Randomized controlled trial run-in periods — some statin randomized controlled trials include a placebo or active-statin run-in period, and patients who experience adverse effects during run-in are not randomized. This removes some of the most statin-intolerant patients before the trial begins.
- Nocebo effect — in the SAMSON trial (2020-2021, see below), 90% of the symptom burden reported during statin months was also reported during placebo months, implicating expectation effects rather than pharmacologic causality
- Background musculoskeletal complaints — muscle pain is common in middle-aged and elderly populations (the typical statin candidates) for non-statin reasons; attribution can be miscategorized
Mechanistic studies report that statins can lower muscle coenzyme Q10 and impair mitochondrial respiration in muscle biopsy specimens (see below), which supports a biological basis for some symptoms. At the same time, the 2022 CTT analysis estimated that only about 1 in 15 first-year reports of muscle pain or weakness among people allocated a statin was actually due to the statin, and concluded that more than 90% of all muscle-symptom reports in the statin arms were not caused by the statin. Expectation-driven symptoms are real to the person who has them, even when they are not pharmacological.
For the coenzyme Q10 question, the relevant points are that some statin users have measurably lower muscle coenzyme Q10, that oral coenzyme Q10 raises blood levels without depending on the blocked synthesis pathway, and that whether this relieves muscle symptoms is what the trials below tested.
Mitochondrial Mechanism of Statin Myopathy
The mitochondrial-dysfunction hypothesis of statin myopathy draws on several lines of evidence, some of them mixed:
Muscle biopsy findings
Biopsy studies give mixed results. In 18 patients with statin-related myopathy and raised creatine kinase, average muscle coenzyme Q10 was not statistically different from controls, although it was more than 2 standard deviations below the normal mean in 3 patients and more than 1 SD below it in 7; muscle structure was essentially normal in 14, and there was no evidence of apoptosis (Lamperti 2005). In a randomized trial in people with high cholesterol, 8 weeks of simvastatin 80 mg/day lowered muscle ubiquinone from 39.7 to 26.4 nmol/g, while atorvastatin 40 mg/day and placebo did not, and respiratory-chain enzyme activities were lower in simvastatin patients with markedly reduced ubiquinone (Päivä 2005). In a cross-sectional study, 10 simvastatin users had lower muscle coenzyme Q10 and lower maximal oxidative phosphorylation (OXPHOS) capacity than 9 matched controls, with similar mitochondrial content (Larsen 2013).
Energy demand mismatch
Skeletal muscle has very high mitochondrial demand, particularly during exercise, when adenosine triphosphate (ATP) turnover rises many-fold above resting rates. The hypothesis is that reduced mitochondrial coenzyme Q10 limits peak adenosine triphosphate production: subclinical at rest, but during physical activity contributing to fatigue, weakness, and the post-exertion soreness that SAMS patients describe. Larsen 2013 found the OXPHOS deficit only when maximal (complex I + II) electron input was tested, not with either input alone — consistent with a limit that appears at high demand.
Oxidative damage to muscle membranes
Lower mitochondrial coenzyme Q10 would also mean less ubiquinol (the antioxidant-active form) in muscle cell membranes; the proposed consequences include more lipid peroxidation, weaker membrane integrity, and low-grade inflammation in affected muscles. The EAS panel notes that most SAMS occur with normal or only minimally raised creatine kinase, and frank rhabdomyolysis is rare.
Type II fiber predilection
In rat studies, statin-induced muscle necrosis follows fiber type: fast-twitch glycolytic type IIB fibers are the most sensitive and type I fibers the least, and in early lesions the only changes seen in some glycolytic fibers were mitochondrial (Westwood 2005). Because type I fibers are the most oxidative (mitochondria-rich) and type IIB the most glycolytic, the fibers most dependent on mitochondria were the least affected — a pattern that does not map simply onto a coenzyme Q10-demand explanation. These findings come from rats.
Genetic susceptibility — SLCO1B1 variants
Patients carrying the SLCO1B1 c.521T>C variant (rs4149056) have reduced hepatic statin uptake (the gene encodes OATP1B1, the transporter that regulates statin uptake into the liver), leading to higher plasma statin concentrations and higher myopathy risk — particularly with simvastatin. In a genome-wide study of people taking simvastatin 80 mg/day, the odds ratio for myopathy was 4.5 per copy of the C allele and 16.9 in CC compared with TT homozygotes, and more than 60% of the myopathy cases could be attributed to the variant (SEARCH Collaborative Group 2008). The SLCO1B1 genotype is testable and is increasingly used in pharmacogenomic-guided statin selection.
The coenzyme Q10 mechanism remains a hypothesis rather than an established cause: a 2007 systematic review concluded that statins reduce circulating coenzyme Q10, that their effect on muscle coenzyme Q10 is not clear, and that the evidence is insufficient to prove that coenzyme Q10 deficiency causes statin myopathy (Marcoff & Thompson 2007).
Serum Coenzyme Q10 vs Muscle Coenzyme Q10 Depletion
An important diagnostic subtlety: serum coenzyme Q10 measurements may not capture the muscle-level coenzyme Q10 that is proposed to matter for symptoms.
Serum coenzyme Q10 is bound largely to circulating lipoproteins (low-density lipoprotein, very-low-density lipoprotein (VLDL), high-density lipoprotein (HDL)) and reflects the systemic coenzyme Q10 pool. Because statins simultaneously lower coenzyme Q10 synthesis AND lower the lipoprotein concentrations that carry coenzyme Q10 in serum, the apparent serum decrease can underestimate the true biochemical impact — or, conversely, the coenzyme Q10:low-density lipoprotein ratio may be normal even when absolute coenzyme Q10 is reduced.
Muscle coenzyme Q10 is measured directly from biopsy specimens (not routinely done clinically) and reflects the cellular pool proposed to matter for symptoms. Serum and muscle levels do not always move together: statins consistently lower plasma coenzyme Q10, whereas the muscle-biopsy results are mixed (see above).
One implication is that a normal-range serum coenzyme Q10 in a statin user with muscle symptoms does not by itself exclude a lower muscle level. The reverse also holds: a rise in serum coenzyme Q10 does not show that muscle levels or symptoms change — in the Taylor 2015 trial, ubiquinol 600 mg/day raised serum coenzyme Q10 from 1.3 to 5.2 mcg/mL without reducing muscle pain.
The Banach 2015 Meta-Analysis
Maciej Banach and colleagues (the Lipid and Blood Pressure Meta-analysis Collaboration Group) published a meta-analysis of randomized controlled trials of coenzyme Q10 for statin-induced myopathy in 2015 (Mayo Clinic Proceedings). Its result was negative.
Methods
- Searched MEDLINE, the Cochrane Library, Scopus, and EMBASE (November 1987 to May 2014) for randomized controlled trials of coenzyme Q10 in patients receiving statins
- Included 6 studies with 302 patients: 5 studies (226 participants) in the analysis of plasma creatine kinase (CK) activity and 5 studies (253 participants) in the analysis of muscle pain
- Outcomes: muscle pain and plasma creatine kinase activity as two measures of statin-induced myalgia
Results
- Muscle pain: no significant effect, despite a trend toward a decrease (standardized mean difference −0.53, 95% confidence interval (CI) −1.33 to 0.28, p = 0.20)
- Plasma creatine kinase: a non-significant increase after coenzyme Q10 (mean difference 11.69 U/L, 95% confidence interval −14.25 to 37.63, p = 0.38)
- No dose-effect association between the coenzyme Q10 dose and changes in creatine kinase or in muscle pain
The authors concluded that the available randomized trials "do not suggest any significant benefit of coenzyme Q10 supplementation in improving statin-induced myopathy" and called for larger, well-designed trials. The figures of 12 trials and 575 patients belong to the later Qu 2018 meta-analysis (below), which reached the opposite conclusion.
The Skarlovnik 2014 Trial
Skarlovnik and colleagues at the University of Ljubljana Medical Centre published a 50-patient randomized trial in 2014 (Medical Science Monitor), testing coenzyme Q10 in a specific group of statin users with mild-to-moderate muscle symptoms.
Design
- 50 statin-treated patients reporting muscle pain, 25 per group
- Randomized to coenzyme Q10 50 mg twice daily (100 mg/day total) or placebo for 30 days
- Outcomes: the Brief Pain Inventory (BPI) — Pain Severity Score and Pain Interference Score — plus blood tests at inclusion and after 30 days
Results
- Pain severity in the coenzyme Q10 group fell from 3.9 to 2.9 (p < 0.001), and pain interference with daily activities fell from 4.0 to 2.6 (p < 0.001)
- In the placebo group, pain severity and pain interference did not change
- Relative to placebo, pain severity fell 33.1% and pain interference 40.3% (both p < 0.05); symptoms decreased in 75% of coenzyme Q10-treated patients
- No differences from baseline in liver or muscle enzymes or cholesterol values
The trial was small and short (30 days), enrolled a selected group with mild-to-moderate symptoms, and the placebo group showed no change in pain scores. Its positive result sits alongside the earlier Caso 2007 trial, which also reported less pain with coenzyme Q10 100 mg/day, and against several negative trials (Young 2007, Bookstaver 2012, Taylor 2015).
The Taylor 2015 Negative Trial
The Taylor 2015 trial (Beth Taylor and colleagues, Hartford Hospital, Atherosclerosis) tested coenzyme Q10 in patients whose statin myalgia had been confirmed under blinded conditions. The trial first screened 120 patients with prior statin muscle symptoms using an 8-week randomized, double-blind crossover of simvastatin 20 mg/day and placebo. The 41 who developed muscle pain on simvastatin but not on placebo were then randomized to simvastatin 20 mg/day plus coenzyme Q10 (600 mg/day as ubiquinol) or simvastatin plus placebo for 8 weeks.
Results: serum coenzyme Q10 rose from 1.3 to 5.2 mcg/mL with coenzyme Q10 but not with placebo. Pain severity and pain interference scores rose on simvastatin regardless of coenzyme Q10 assignment (p = 0.53 and 0.56), muscle strength and aerobic capacity (VO2max) did not change, and time to pain onset did not differ. Marginally more participants reported pain on coenzyme Q10 (14 of 20 vs 7 of 18, p = 0.05). The trial used a higher coenzyme Q10 dose (600 mg/day) than the positive trials, which makes the negative result striking. The screening crossover also showed that only 36% of patients who reported statin myalgia developed symptoms on the statin but not on placebo.
Points raised in comparing it with the positive trials:
- Inclusion criteria — Taylor enrolled only patients whose myalgia was confirmed under blinded conditions (pain on simvastatin, none on placebo), a stricter selection than in the positive trials, which enrolled statin users reporting muscle pain without a blinded confirmation step
- Statin reintroduction during trial — all randomized patients took simvastatin throughout, so the trial tested whether coenzyme Q10 prevents or blunts pain on statin re-exposure, rather than whether it relieves pain that is already present
- Trial size — 41 patients were randomized, a small trial; a similar lack of coenzyme Q10 effect was seen in 24 subjects who were then crossed over to the alternative treatment
- Plasma coenzyme Q10 measurement — serum coenzyme Q10 roughly quadrupled on ubiquinol, so the negative result was not due to absorption failure
The authors concluded that coenzyme Q10 supplementation does not reduce muscle pain in patients with statin myalgia. Together with the negative Young 2007 and Bookstaver 2012 trials, it is part of why the meta-analyses disagree (see below).
The Qu 2018 Updated Meta-Analysis
Qu and colleagues (China Academy of Chinese Medical Sciences) published an updated meta-analysis in 2018 (Journal of the American Heart Association). They included 12 randomized controlled trials with a total of 575 patients — 294 in the coenzyme Q10 groups and 281 in the placebo groups.
Results: compared with placebo, coenzyme Q10 reduced muscle pain (weighted mean difference −1.60, 95% confidence interval −1.75 to −1.44, p < 0.001), muscle weakness (−2.28, 95% confidence interval −2.79 to −1.77, p = 0.006), muscle cramp (−1.78, 95% confidence interval −2.31 to −1.24, p < 0.001), and muscle tiredness (−1.75, 95% confidence interval −2.31 to −1.19, p < 0.001). Plasma creatine kinase did not fall (0.09, 95% confidence interval −0.06 to 0.24, p = 0.23). The authors concluded that coenzyme Q10 supplementation ameliorated statin-associated muscle symptoms and "may be a complementary approach to manage statin-induced myopathy."
The evidence remains split. A 2020 meta-analysis limited to placebo-controlled trials in adults with statin-associated myalgia (Kennedy, Köller & Surkova, Atherosclerosis) pooled 7 trials with 321 patients and found no benefit for myalgia (weighted mean difference −0.42, 95% confidence interval −1.47 to 0.62) and no improvement in the proportion of patients remaining on a statin (relative risk (RR) 0.99, 95% confidence interval 0.81 to 1.20); only two of the eight trials it reviewed showed less muscle pain with coenzyme Q10. The three meta-analyses differ in which trials they included.
Two later meta-analyses kept the split. A 2022 review (Wei and colleagues, Irish Journal of Medical Science) covered 8 trials with 472 statin users and found no significant benefit: muscle pain was not clearly lower with coenzyme Q10 (standardized mean difference −0.59, 95% confidence interval −1.54 to 0.36, p = 0.22; 4 trials, 220 people), and creatine kinase did not change significantly (+3.29 U/L, p = 0.84). A 2025 review (Kovacic, Habicht & Eckert, Journal of Nutritional Science) pooled 7 randomized trials with 389 statin users who took coenzyme Q10 100–600 mg a day for 30 to 90 days. Four trials found less muscle pain and three found no change; pooled, pain intensity was slightly lower with coenzyme Q10 (weighted mean difference −0.96, 95% confidence interval −1.88 to −0.03), and the authors wrote that more research is needed.
In plain words: the five meta-analyses on this page (Banach 2015, Qu 2018, Kennedy 2020, Wei 2022, Kovacic 2025) disagree mostly because each one pools a different set of small trials — in the 2025 review, every trial had between 35 and 76 patients. No single large trial has settled the question.
Prophylactic Use vs Treatment: What Was Studied
Two distinct clinical questions:
Prophylactic use in statin users without symptoms
Functional and integrative medicine sources commonly describe prophylactic coenzyme Q10 (100-200 mg/day) for people on long-term statin therapy regardless of symptoms, on the rationale that statins lower coenzyme Q10 even when symptoms are absent. The argument is that the downstream consequences (subclinical reductions in muscle strength, exercise tolerance, perhaps long-term mitochondrial damage) may not produce immediate symptoms but could matter over decades of statin use.
Cardiology and lipidology guidance does not endorse prophylactic coenzyme Q10 for statin users without symptoms. The 2007 Marcoff & Thompson systematic review concluded that the routine use of coenzyme Q10 in statin-treated patients "cannot be recommended", while noting that there are no known risks to the supplement and some anecdotal and preliminary trial evidence of effectiveness, and that some patients may respond "if only via a placebo effect." The randomized trials described on this page enrolled people who already had muscle symptoms; none tested coenzyme Q10 as prevention in people without symptoms. The argument against prophylactic supplementation is that it adds cost and pill burden for a benefit that has not been demonstrated.
Doses used in trials of established SAMS
The randomized trials summarized on this page used doses from 100 to 600 mg/day for 30 days to 3 months. Among these five trials, the two positive ones (Caso 2007, Skarlovnik 2014) used 100 mg/day, and the three that used 120-600 mg/day (Bookstaver 2012, Young 2007, Taylor 2015) found no benefit over placebo. The Banach meta-analysis found no dose-effect association.
Integrative-medicine protocols describe raising the dose, switching between ubiquinone and ubiquinol, or adding vitamin D, magnesium, L-carnitine, or ribose when there is no response; these steps and combinations have not been tested in the randomized SAMS trials above.
Statin Switching and Non-Statin Options
Steps described in consensus documents and the clinical literature for people with SAMS:
- Confirming SAMS — other causes of muscle pain, such as hypothyroidism, vitamin D deficiency, and polymyalgia rheumatica, are part of the usual work-up; tests commonly include creatine kinase, thyroid-stimulating hormone (TSH), 25-OH vitamin D, and erythrocyte sedimentation rate (ESR)/C-reactive protein (CRP) as indicated.
- Coenzyme Q10 — tested in the trials above with mixed results. Marcoff & Thompson (2007) concluded that coenzyme Q10 "can be tested" in patients who require a statin, develop statin myalgia, and cannot be satisfactorily treated with other agents.
- Statin switch — the EAS 2015 consensus panel recommends a structured work-up, generally to at least three different statins, to identify clinically relevant SAMS. Hydrophilic statins (pravastatin, rosuvastatin) are often described as entering skeletal muscle less than lipophilic statins (simvastatin, atorvastatin); however, the 2022 CTT analysis found no clear evidence that the excess of muscle symptoms differed between statins, and the 2015 plasma-CoQ10 meta-analysis found no difference between lipophilic and hydrophilic statins in how much they lowered plasma coenzyme Q10.
- Dose reduction — for people with SAMS, the EAS panel recommends the maximally tolerated statin dose combined with non-statin lipid-lowering therapy to reach low-density lipoprotein cholesterol targets.
- Alternate-day dosing — rosuvastatin's long half-life has prompted every-other-day regimens; in a retrospective review of 51 statin-intolerant patients at two lipid clinics, 72.5% tolerated every-other-day rosuvastatin (mean dose 5.6 mg) and low-density lipoprotein cholesterol fell 34.5% in those who tolerated it, though the approach has not been shown to reduce cardiovascular events (Backes 2008)
- Switch to non-statin therapy — ezetimibe (10 mg/day) for modest low-density lipoprotein reduction; PCSK9 inhibitors (alirocumab, evolocumab) for substantial low-density lipoprotein reduction; bempedoic acid (an adenosine triphosphate-citrate lyase inhibitor that acts upstream of HMG-CoA reductase; it is a prodrug activated by the enzyme ACSVL1, which is absent from skeletal muscle — Pinkosky 2016); investigational gene-editing approaches targeting PCSK9 are being tested in clinical trials. In the CLEAR Outcomes trial, 13,970 people who were unable or unwilling to take statins because of side effects received bempedoic acid 180 mg a day or placebo for a median of 40.6 months; major cardiovascular events occurred in 11.7% vs 13.3% (hazard ratio 0.87), and heart attacks were fewer (3.7% vs 4.8%), but stroke, death from cardiovascular causes and death from any cause did not change significantly. Gout (3.1% vs 2.1%) and gallstones (2.2% vs 1.2%) were more common with bempedoic acid (Nissen 2023)
With these non-statin options, statin intolerance is no longer the clinical dead-end it once was: people with documented SAMS who cannot tolerate any statin can still reach substantial low-density lipoprotein reduction with ezetimibe, PCSK9 inhibitor, and bempedoic acid combinations.
Trial Regimens at a Glance
The randomized trials of coenzyme Q10 for statin muscle symptoms used these regimens. None tested a tiered protocol, or the combinations with other supplements that some integrative-medicine sources describe.
- Caso 2007 — 32 statin users with myopathic symptoms; coenzyme Q10 100 mg/day (n = 18) vs vitamin E 400 international units (IU)/day (n = 14) for 30 days; with coenzyme Q10, pain severity fell 40% and pain interference 38%, with no significant change on vitamin E
- Skarlovnik 2014 — 50 patients with mild-to-moderate symptoms; 50 mg twice daily vs placebo for 30 days; positive (see above)
- Bookstaver 2012 — 76 patients with new-onset myalgia within 60 days of starting or increasing a statin; 60 mg twice daily vs placebo for 3 months while continuing the statin; no difference in the 1-month pain score (3.9 vs 4.0 cm on a 10-cm visual analog scale, p = 0.97)
- Young 2007 — 44 patients with previous statin myalgia; 200 mg/day vs placebo for 12 weeks during simvastatin titration from 10 to 40 mg/day; no difference in myalgia score, in the number tolerating 40 mg/day (16 of 22 vs 13 of 22, p = 0.34), or in the number remaining on therapy
- Taylor 2015 — 41 patients with blinded-confirmed statin myalgia; ubiquinol 600 mg/day vs placebo for 8 weeks with simvastatin 20 mg/day; negative (see above)
Cofactor considerations
Vitamin D deficiency (more common at northern latitudes), low magnesium status, and subclinical hypothyroidism can each produce muscle symptoms independently of a statin, which is why they appear in the usual work-up. Identifying them reduces the risk of attributing non-statin muscle symptoms to the statin.
The Nocebo Question (SAMSON Trial)
The SAMSON (Self-Assessment Method for Statin Side-effects Or Nocebo) trial, first reported in the NEJM in 2020 (Wood et al.) and analyzed in full in JACC in 2021 (Howard et al.), used an n-of-1 crossover design to investigate the contribution of nocebo (expectation-driven negative experience) to symptoms reported on statins.
60 participants who had previously abandoned statins received 12 one-month medication bottles — 4 containing atorvastatin 20 mg, 4 placebo, and 4 empty — over 12 months, and recorded daily symptom intensity in an app (scale 1-100); 49 completed the 12-month protocol.
Results: the mean symptom score was 8.0 in no-tablet months, 16.3 in statin months, and 15.4 in placebo months, with no significant difference between statin and placebo (p = 0.388). The nocebo ratio was 0.90: 90% of the symptom burden induced by taking the statin was also induced by taking placebo. Six months after the trial, 30 of the 60 participants (50%) were back taking statins. The authors concluded that the majority of symptoms caused by statin tablets were nocebo.
The SAMSON finding does not rule out a pharmacological component in some people — it complicates interpretation by suggesting that a substantial fraction of patients labeled "statin intolerant" may actually be experiencing primarily expectation-driven symptoms. The implications discussed include:
- People who discontinue statins solely because of "anticipated" muscle problems, before any trial, forgo the cardiovascular protection statins provide
- Open-label rechallenge of patients with reported SAMS may show resolution simply through expectation management
- Any improvement on coenzyme Q10 outside a blinded trial may reflect expectation as well as pharmacology; only placebo-controlled trials separate the two, and those trials disagree (see the meta-analyses above)
The EAS 2015 consensus takes SAMS reports seriously while using repeated statin re-challenge to identify clinically relevant symptoms. Approaches discussed for primarily nocebo-driven symptoms include expectation management, a statin switch (which provides an expectation reset), and non-statin therapy. Howard and colleagues cautioned against reading symptom intensity or the timing of onset or relief as evidence of pharmacological causation, because the pattern was identical on placebo.
Cautions
- Stopping statin therapy — statins provide substantial cardiovascular mortality reduction in appropriate patients, and the 2022 CTT analysis concluded that the small risks of muscle symptoms are much lower than the known cardiovascular benefits. For people with SAMS, the EAS 2015 consensus describes statin switching and the maximally tolerated dose combined with non-statin therapy rather than discontinuing lipid-lowering treatment altogether. Decisions about medicines and supplements belong with a clinician.
- Warfarin interaction — coenzyme Q10 has a quinone structure similar to vitamin K, and case reports describe a reduced warfarin effect with coenzyme Q10 (Spigset 1994). A small randomized, double-blind, placebo-controlled crossover trial in 24 people on stable long-term warfarin found that the international normalized ratio (INR) stayed stable and the warfarin dose did not change with coenzyme Q10 100 mg/day for 4 weeks (Engelsen 2003). International normalized ratio checks after starting coenzyme Q10 are commonly described for people taking warfarin.
- Absorption with dietary fat — coenzyme Q10 is fat-soluble and is generally described as better absorbed when taken with a meal containing fat
- Persistent or progressive muscle symptoms warrant evaluation — in clinical guidance, severe myopathy with creatine kinase >10× ULN, or rhabdomyolysis with myoglobinuria, is a reason for discontinuing the statin and for clinical evaluation regardless of coenzyme Q10 status
- Statin-induced necrotizing autoimmune myopathy (IMNM) — presents as persistent severe weakness that does not resolve on statin discontinuation and is treated with immunosuppression. Coenzyme Q10 does not address IMNM — the diagnosis is considered in any SAMS patient whose symptoms do not improve on statin withdrawal.
- Creatine kinase testing during an initial statin trial — a baseline creatine kinase, repeated if symptoms emerge, is commonly described; routine creatine kinase monitoring of people without symptoms is not part of current guidance.
- Work-up for muscle symptoms — the usual work-up checks for hypothyroidism (thyroid-stimulating hormone), vitamin D deficiency (25-OH vitamin D), polymyalgia rheumatica (erythrocyte sedimentation rate/C-reactive protein), polymyositis (anti-Jo-1, and anti-HMGCR antibodies if symptoms persist after withdrawal), and primary muscle disease
Key Research Papers
- Banach M et al. (2015). Effects of coenzyme Q10 on statin-induced myopathy: a meta-analysis of randomized controlled trials. Mayo Clinic Proceedings 90(1):24-34. — PubMed PMID: 25440725
- Skarlovnik A et al. (2014). Coenzyme Q10 supplementation decreases statin-related mild-to-moderate muscle symptoms: a randomized clinical study. Medical Science Monitor 20:2183-2188. — PubMed PMID: 25375075
- Taylor BA et al. (2015). A randomized trial of coenzyme Q10 in patients with confirmed statin myopathy. Atherosclerosis 238(2):329-335. — PubMed PMID: 25545331
- Qu H et al. (2018). Effects of coenzyme Q10 on statin-induced myopathy: an updated meta-analysis of randomized controlled trials. Journal of the American Heart Association 7(19):e009835. — PubMed PMID: 30371340
- Marcoff L & Thompson PD (2007). The role of coenzyme Q10 in statin-associated myopathy: a systematic review. JACC 49(23):2231-2237. — PubMed PMID: 17560286
- Howard JP et al. (SAMSON Investigators, 2021). Side effect patterns in a crossover trial of statin, placebo, and no treatment. JACC 78(12):1210-1222. — PubMed PMID: 34531021
- Caso G et al. (2007). Effect of coenzyme Q10 on myopathic symptoms in patients treated with statins. American Journal of Cardiology 99(10):1409-1412. — PubMed PMID: 17493470
- Bookstaver DA et al. (2012). Effect of coenzyme Q10 supplementation on statin-induced myalgias. American Journal of Cardiology 110(4):526-529. — PubMed PMID: 22608359
- Stroes ES et al. (European Atherosclerosis Society Consensus Panel, 2015). Statin-associated muscle symptoms: impact on statin therapy — European Atherosclerosis Society Consensus Panel Statement on Assessment, Aetiology and Management. European Heart Journal 36(17):1012-1022. — PubMed PMID: 25694464
- Rosenson RS et al. (National Lipid Association Statin Muscle Safety Task Force, 2014). An assessment by the Statin Muscle Safety Task Force: 2014 update. Journal of Clinical Lipidology 8(3 Suppl):S58-S71. — PubMed PMID: 24793443
- Wood FA et al. (2020). N-of-1 trial of a statin, placebo, or no treatment to assess side effects. New England Journal of Medicine 383(22):2182-2184. — PubMed PMID: 33196154
- Kennedy C, Köller Y & Surkova E (2020). Effect of coenzyme Q10 on statin-associated myalgia and adherence to statin therapy: a systematic review and meta-analysis. Atherosclerosis 299:1-8. — PubMed PMID: 32179207
- Young JM et al. (2007). Effect of coenzyme Q10 supplementation on simvastatin-induced myalgia. American Journal of Cardiology 100(9):1400-1403. — PubMed PMID: 17950797
- Cholesterol Treatment Trialists' Collaboration (2022). Effect of statin therapy on muscle symptoms: an individual participant data meta-analysis of large-scale, randomised, double-blind trials. Lancet 400(10355):832-845. — PubMed PMID: 36049498
- Banach M et al. (2015). Statin therapy and plasma coenzyme Q10 concentrations: a systematic review and meta-analysis of placebo-controlled trials. Pharmacological Research 99:329-336. — PubMed PMID: 26192349
- Rundek T et al. (2004). Atorvastatin decreases the coenzyme Q10 level in the blood of patients at risk for cardiovascular disease and stroke. Archives of Neurology 61(6):889-892. — PubMed PMID: 15210526
- Lamperti C et al. (2005). Muscle coenzyme Q10 level in statin-related myopathy. Archives of Neurology 62(11):1709-1712. — PubMed PMID: 16286544
- Päivä H et al. (2005). High-dose statins and skeletal muscle metabolism in humans: a randomized, controlled trial. Clinical Pharmacology & Therapeutics 78(1):60-68. — PubMed PMID: 16003294
- Larsen S et al. (2013). Simvastatin effects on skeletal muscle: relation to decreased mitochondrial function and glucose intolerance. Journal of the American College of Cardiology 61(1):44-53. — PubMed PMID: 23287371
- SEARCH Collaborative Group; Link E et al. (2008). SLCO1B1 variants and statin-induced myopathy: a genomewide study. New England Journal of Medicine 359(8):789-799. — PubMed PMID: 18650507
- Westwood FR et al. (2005). Statin-induced muscle necrosis in the rat: distribution, development, and fibre selectivity. Toxicologic Pathology 33(2):246-257. — PubMed PMID: 15902968
- Law M & Rudnicka AR (2006). Statin safety: a systematic review. American Journal of Cardiology 97(8A):52C-60C. — PubMed PMID: 16581329
- Weber C et al. (1997). The coenzyme Q10 content of the average Danish diet. International Journal for Vitamin and Nutrition Research 67(2):123-129. — PubMed PMID: 9129255
- Moosmann B & Behl C (2004). Selenoprotein synthesis and side-effects of statins. Lancet 363(9412):892-894. — PubMed PMID: 15031036
- Mammen AL et al. (2011). Autoantibodies against 3-hydroxy-3-methylglutaryl-coenzyme A reductase in patients with statin-associated autoimmune myopathy. Arthritis & Rheumatism 63(3):713-721. — PubMed PMID: 21360500
- Pinkosky SL et al. (2016). Liver-specific ATP-citrate lyase inhibition by bempedoic acid decreases LDL-C and attenuates atherosclerosis. Nature Communications 7:13457. — PubMed PMID: 27892461
- Backes JM et al. (2008). Effectiveness and tolerability of every-other-day rosuvastatin dosing in patients with prior statin intolerance. Annals of Pharmacotherapy 42(3):341-346. — PubMed PMID: 18285559
- Spigset O (1994). Reduced effect of warfarin caused by ubidecarenone. Lancet 344(8933):1372-1373. — PubMed PMID: 7968059
- Wei H, Xin X, Zhang J, Xie Q, Naveed M, Kaiyan C, Xiao P (2022). Effects of coenzyme Q10 supplementation on statin-induced myopathy: a meta-analysis of randomized controlled trials. Irish Journal of Medical Science 191(2):719-725. — PubMed PMID: 33999383
- Kovacic S, Habicht SD, Eckert GP (2025). Effects of coenzyme Q10 supplementation on myopathy in statin-treated patients: a systematic review and meta-analysis. Journal of Nutritional Science 14:e72. — PubMed PMID: 41158831
- Nissen SE, Lincoff AM, Brennan D, et al. (CLEAR Outcomes Investigators, 2023). Bempedoic acid and cardiovascular outcomes in statin-intolerant patients. New England Journal of Medicine 388(15):1353-1364. — PubMed PMID: 36876740
- Engelsen J, Nielsen JD & Hansen KF (2003). Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in patients on long-term warfarin treatment: a randomized, double-blind, placebo-controlled cross-over trial (article in Danish). Ugeskrift for Laeger 165(18):1868-1871. — PubMed PMID: 12772396
PubMed Topic Searches
Connections
- Free Radicals & Your Antioxidant Network — interactive animation
- Coenzyme Q10 Overview
- Coenzyme Q10 Benefits Hub
- Coenzyme Q10 for Heart Failure
- Coenzyme Q10 for Migraine
- Coenzyme Q10 for Fertility
- Heart Failure
- Cardiovascular Disease
- Lipid Panel
- Apolipoprotein B
- Coronary Calcium Score
- Statins & Coronary Artery Calcium Threshold
- Alpha Lipoic Acid
- All Antioxidants
- Vitamin D
- Magnesium
- L-Carnitine
- Creatine
- Oxidative Stress
- History