Intravenous (IV) High-Dose Vitamin C & Cancer
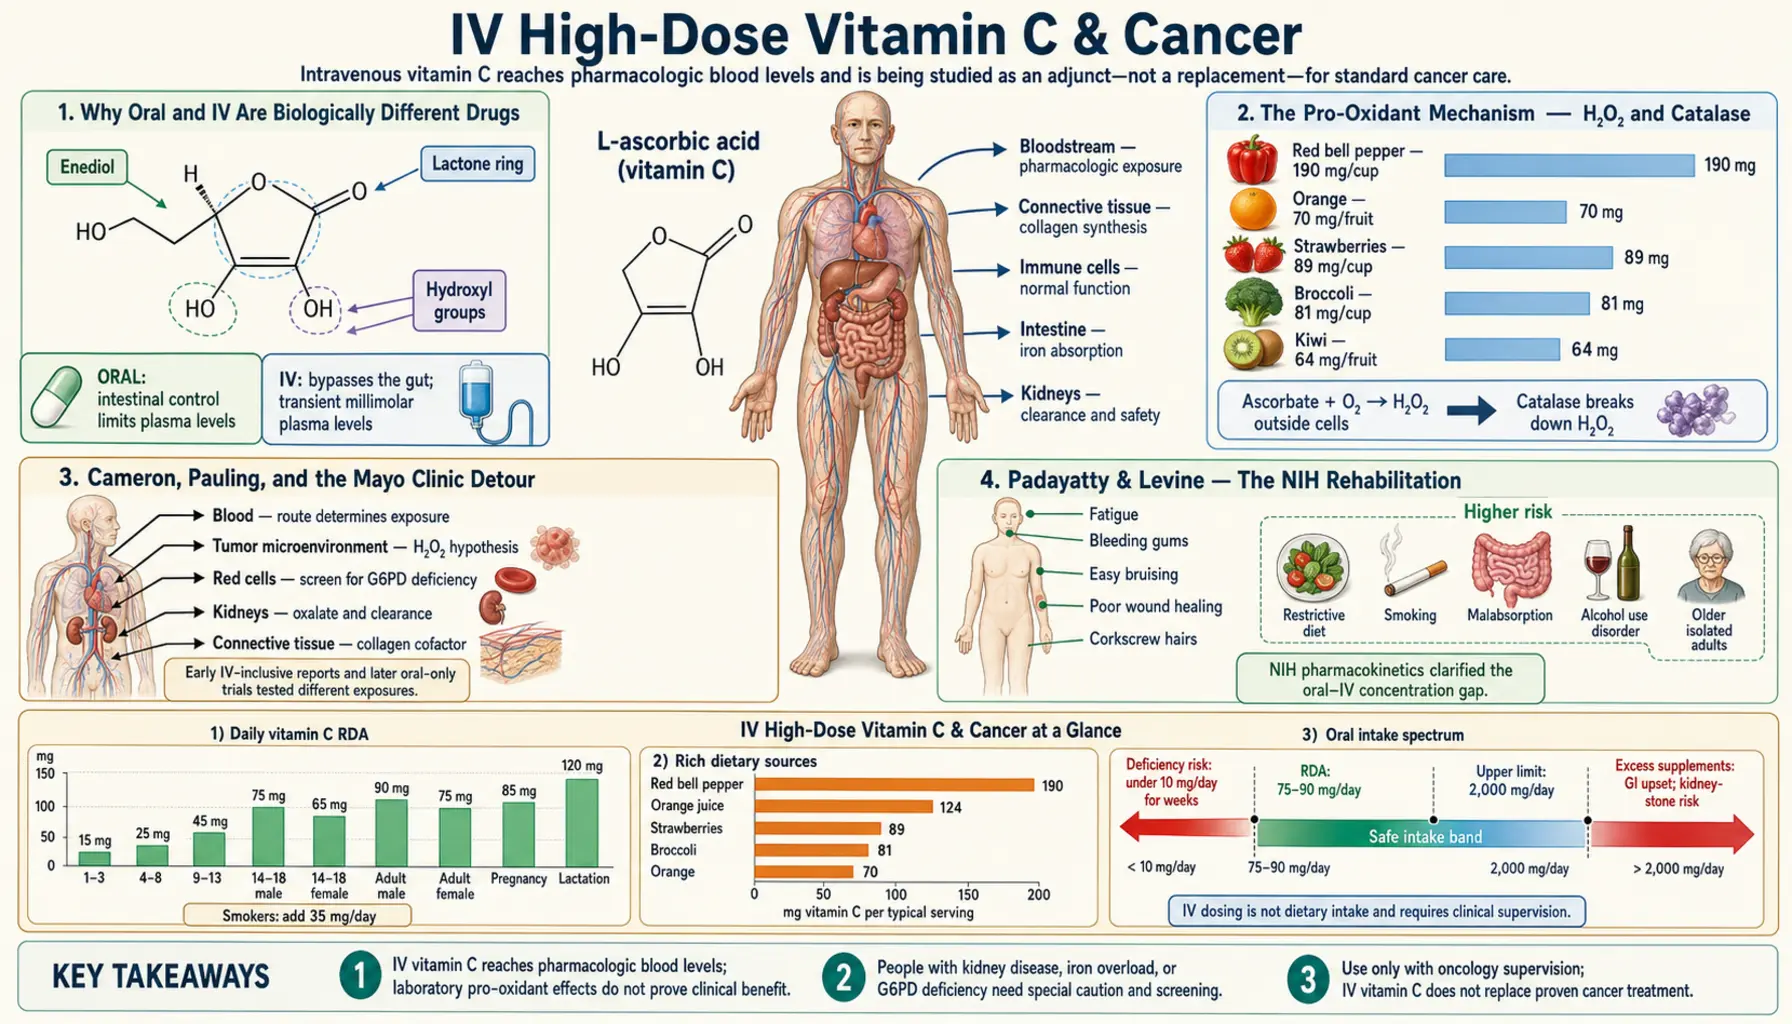
High-dose intravenous Vitamin C is, biochemically, a different drug from the same molecule taken orally. Oral dosing saturates plasma ascorbate around 100–200 µM; intravenous (IV) infusion at 50–100 g pushes plasma above 20,000 µM (over 20 mM) — a 100-fold concentration jump that activates a completely different mechanism: pro-oxidant generation of extracellular hydrogen peroxide selectively toxic to cancer cells that have lost normal catalase activity. This is the Riordan Clinic / Padayatty U.S. National Institutes of Health (NIH) / University of Kansas integrative-oncology protocol. This deep-dive walks through the historical arc from Cameron and Pauling through the Mayo Clinic rebuttals to the Levine pharmacokinetic rehabilitation, the mechanism work by Chen and Schoenfeld, the glucose-6-phosphate dehydrogenase (G6PD) screening requirement, and an honest accounting of what the evidence shows and what it doesn't.
Interactive Visualization Vitamin C, Collagen & Why Sailors Fell Apart Zip three protein chains into the strongest rope in biology — then take the vitamin C away and watch the helix unravel, and old healed scars split back open. Launch →
Table of Contents
- Why Oral and Intravenous Are Biologically Different Drugs
- The Pro-Oxidant Mechanism — H&sub2;O&sub2; and Catalase
- Cameron, Pauling, and the Mayo Clinic Detour
- Padayatty & Levine — The U.S. National Institutes of Health Rehabilitation
- Chen, Schoenfeld & the Mechanism Work
- The Riordan Clinic Protocol
- Modern Trials: University of Kansas, Cornell, Iowa
- What the Evidence Shows — And What It Doesn't
- Glucose-6-Phosphate Dehydrogenase Screening — The Essential Safety Step
- Integration With Conventional Oncology
- Cautions & Contraindications
- Patient FAQ
- Key Research Papers
- Connections
- Featured Videos
Why Oral and Intravenous Are Biologically Different Drugs
The single most important fact about intravenous Vitamin C is the pharmacokinetic one: oral dosing simply cannot achieve the plasma concentrations that make intravenous interesting for cancer. The Levine 1996 PNAS paper and the Padayatty 2004 Annals of Internal Medicine follow-up established the curve definitively.
Oral dosing saturates. As single-dose intake rises above 200 mg, fractional absorption drops sharply. Renal tubular reabsorption of filtered ascorbate also saturates — the excess spills into urine. The result: oral plasma steady-state caps at approximately 80–220 µM no matter how much you take. Even bowel-tolerance megadoses (10–30 g/day) plateau around 220 µM plasma. The body's homeostatic systems are tuned to keep plasma vitamin C in the low-micromolar range.
Intravenous infusion bypasses every absorption and renal homeostasis barrier. The Padayatty 2004 study measured levels in 17 healthy volunteers only up to 1.25 g; for larger doses it used pharmacokinetic modelling, which predicted a peak of about 13,400 µM for a 50 g intravenous dose, against about 220 µM for the maximum tolerated oral dose (3 g every 4 hours). The authors noted that patient data were not available to confirm the modelling at high doses. The 2006 Padayatty case report gives about 14,000 µM for 50–100 g given intravenously. Integrative-oncology sources quote figures of 13,000–20,000 µM (13–20 mM) after a 50 g infusion over 60–90 minutes and about 30,000 µM after 100 g. These concentrations are far higher than oral dosing can achieve, and they persist for several hours before renal clearance brings them back down.
At these pharmacological concentrations the chemistry of ascorbate in extracellular fluid changes. Ascorbate auto-oxidizes in the presence of trace metals (released from injured or dying tissue) generating hydrogen peroxide (H&sub2;O&sub2;) in the extracellular space at micromolar concentrations. The H&sub2;O&sub2; is the active agent, not the ascorbate itself. The Chen 2005 and Chen 2008 PNAS papers measured tumor extracellular H&sub2;O&sub2; concentrations during intravenous ascorbate infusion in mouse xenografts and confirmed the mechanism directly.
This is why every oral-dose clinical trial that fails to show anti-cancer benefit is irrelevant to the intravenous-dose question. They are different drugs. Treating them as the same drug is the conceptual error that delayed serious clinical investigation by about 30 years.
The Pro-Oxidant Mechanism — H&sub2;O&sub2; and Catalase
Why would extracellular H&sub2;O&sub2; selectively kill cancer cells? The answer is catalase deficiency.
Catalase is the enzyme that converts H&sub2;O&sub2; to water and oxygen, neutralizing it. Normal cells have high catalase activity in peroxisomes and adequate glutathione peroxidase backup in cytoplasm and mitochondria. When extracellular H&sub2;O&sub2; appears, normal cells absorb it and detoxify it quickly — net result, no damage.
Many cancer cells have low catalase activity. The reasons vary: metabolic reprogramming during oncogenic transformation downregulates peroxisomal enzymes; rapid proliferation outstrips antioxidant gene expression; some oncogenes (KRAS, BRAF, MYC) actively suppress catalase. Whatever the cause, low catalase means the cancer cell cannot detoxify the incoming H&sub2;O&sub2;. The H&sub2;O&sub2; reacts with intracellular iron (cancer cells often have elevated labile iron pools too) via Fenton chemistry to generate hydroxyl radical — the most damaging reactive oxygen species (ROS) in biology — which fragments DNA, peroxidizes lipids, and kills the cell.
The Schoenfeld 2017 Cancer Cell paper extended the picture: non-small-cell lung cancer (NSCLC) and glioblastoma (GBM) cells are particularly susceptible because they have both low catalase and elevated labile iron, making them doubly vulnerable to the H&sub2;O&sub2;-iron-hydroxyl-radical cascade. This work led directly to the ongoing trials of pharmacological ascorbate as a radiosensitizer in NSCLC and GBM at the University of Iowa.
The Yun 2015 Science paper added another wrinkle for KRAS- and BRAF-mutant colorectal cancers: dehydroascorbate (DHA, the oxidized form of vitamin C) is taken up by these cells through GLUT1 (which they overexpress because of their altered glucose metabolism), then reduced back to ascorbate inside the cell. The intracellular ascorbate then oxidizes again, depleting cellular reduced nicotinamide adenine dinucleotide phosphate (NADPH) and glutathione, and selectively killing the mutant cells.
So there is no single anti-cancer mechanism for high-dose ascorbate. There are at least three (extracellular H&sub2;O&sub2; / Fenton chemistry; intracellular DHA uptake via GLUT1 + redox depletion in KRAS/BRAF mutants; HIF-1α degradation via prolyl hydroxylase activity) and the relative importance varies by tumor type.
Cameron, Pauling, and the Mayo Clinic Detour
The modern story starts with Scottish surgeon Ewan Cameron and Linus Pauling. In a 1976 PNAS paper, they reported that 100 terminally ill cancer patients given 10 g/day of vitamin C (initially intravenous for 10 days, then oral indefinitely) had a mean survival more than 4.2 times as long (more than 210 days) as 1,000 similar patients who did not receive it (50 days). A 1978 follow-up paper in the same journal re-evaluated these survival times. Some patients experienced apparent remissions. The paper was electrifying.
The Mayo Clinic mounted what was supposed to be a definitive refutation, with two randomized double-blind trials comparing 10 g/day oral vitamin C to placebo. The first (Creagan and colleagues, with Charles Moertel as co-author, 1979 NEJM) enrolled 150 patients with advanced cancer of various primary sites, most of whom had previous chemotherapy; median survival was about seven weeks and the survival curves essentially overlapped. The second (Moertel and colleagues, 1985 NEJM) enrolled 100 patients with advanced colorectal cancer who had had no prior chemotherapy. Both trials found no benefit. The oncology establishment concluded the matter was settled and "vitamin C does not work for cancer" became the consensus.
The conceptual error: the Mayo trials used oral dosing. Cameron and Pauling had used intravenous dosing initially before transitioning to oral. The intravenous phase was producing the plasma concentrations that mattered; the subsequent oral was maintenance. By eliminating the intravenous induction, the Mayo design tested a different intervention — one that, in retrospect, could not possibly have worked because oral plasma levels cannot reach the pro-oxidant pharmacological range.
Levine and colleagues at U.S. National Institutes of Health spent years documenting the pharmacokinetic difference. By the late 1990s and early 2000s, the Padayatty 2004 paper made the case rigorously: the efficacy of vitamin C in cancer cannot be judged from trials that used only oral dosing, and the authors called for its role in cancer treatment to be re-evaluated. The Mayo trials had effectively tested whether a homeopathic dose of a chemotherapy drug worked — an unfair test. The path to serious intravenous trials reopened.
The 25 years between the Mayo trials (1979/1985) and the Padayatty rehabilitation (2004) is sometimes called "the lost generation" in integrative-oncology vitamin C research. The Riordan Clinic in Wichita, Kansas, kept the intravenous clinical practice alive throughout this period, treating thousands of patients and accumulating the case-series experience that later trials would build on.
Padayatty & Levine — The U.S. National Institutes of Health Rehabilitation
Sebastian Padayatty and Mark Levine at the U.S. National Institutes of Health's National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) did the conceptual rehabilitation in three landmark papers:
- Padayatty 2004 (Ann Intern Med) — established the oral vs intravenous pharmacokinetic difference quantitatively in 17 healthy volunteers. At 1.25 g, oral dosing gave a mean peak of 134.8 µM and intravenous dosing 885 µM — already about four times the 220 µM that modelling predicted for the maximum tolerated oral dose. For a 50 g intravenous dose, the model predicted about 13,400 µM (a prediction, not a measured level).
- Padayatty 2006 (CMAJ) — reported three well-documented case studies of patients with advanced cancers (renal, bladder, B-cell lymphoma) treated with intravenous ascorbate (15–65 g, 1–3×/week) who had apparent durable remissions. Case reports are not randomized controlled trial (RCT) evidence but they re-established the clinical plausibility that had been dismissed for decades.
- Padayatty 2010 (PLoS ONE) — surveyed complementary and alternative medicine (CAM) practitioners at conferences. In 2006, 172 practitioners gave intravenous vitamin C to 11,233 patients, at an average dose of 28 g every 4 days. Of 9,328 patients with data, 101 had side effects, mostly minor (tiredness in 59, change in mental status in 21, vein irritation in 6). Published reports documented serious adverse events, including 2 deaths in patients known to be at risk. The authors concluded that, other than the known complications in people with kidney impairment or glucose-6-phosphate dehydrogenase deficiency, high-dose intravenous vitamin C appears remarkably safe. This supported the case for formal clinical trials.
The combined effect was to make intravenous vitamin C respectable again in academic oncology. By 2010 the University of Kansas Medical Center, University of Iowa, Thomas Jefferson, and Weill Cornell had ongoing trials. The framing had shifted from "alternative medicine" to "investigational drug at pharmacological dose."
Chen, Schoenfeld & the Mechanism Work
The pre-clinical mechanism work that anchored the clinical revival came mostly from Mark Levine's U.S. National Institutes of Health lab and from Joseph Cullen and Garry Buettner at the University of Iowa.
Qi Chen's two PNAS papers (2005 and 2008) showed that pharmacological ascorbate generates extracellular H&sub2;O&sub2; in tumor tissue at concentrations capable of killing cancer cells but not normal cells. The 2008 paper used mouse xenograft models of ovarian, pancreatic, and glioblastoma tumors and demonstrated tumor growth reduction with intravenous ascorbate alone.
Welsh 2013 (Cancer Chemother Pharmacol) ran a phase I safety trial in 9 people with stage IV pancreatic cancer, giving twice-weekly intravenous ascorbate (15–125 g) with gemcitabine. Side effects from the combination were rare (diarrhea in 4, dry mouth in 6). The trial had no comparison group; mean survival of those completing at least two cycles (8 weeks) was 13 ± 2 months, and the authors wrote that the small sample suggested “some efficacy”. This led to the Polireddy 2017 follow-up and to the larger ongoing pancreatic trials.
Schoenfeld 2017 (Cancer Cell) elucidated why NSCLC and GBM are particularly sensitive: low catalase plus high labile iron creates the Fenton-chemistry vulnerability described above. This paper led to ongoing radiosensitization trials in those two cancer types — intravenous ascorbate during radiotherapy to selectively amplify radiation-induced reactive oxygen species damage in the tumor while sparing normal tissue (which has normal catalase).
Yun 2015 (Science) opened a separate mechanistic chapter for KRAS- and BRAF-mutant colorectal cancers: GLUT1-mediated dehydroascorbate uptake leading to intracellular redox collapse. This is being pursued in colorectal cancer specifically, where the KRAS-mutant subset has historically been the hardest to treat with targeted therapy.
The Cieslak and Cullen 2015 review consolidated the pancreatic cancer mechanism work; Polireddy 2017 demonstrated metastasis inhibition in pancreatic xenografts; multiple other groups have published parallel work in lymphoma, melanoma, and hepatocellular carcinoma.
The Riordan Clinic Protocol
The Riordan Clinic (founded by Hugh Riordan in 1975 in Wichita, Kansas) is the longest-running clinical center treating cancer with intravenous ascorbate. Hugh Riordan was a contemporary of Pauling and Cameron; the clinic continued under his son Mikael after his death and has published its intravenous vitamin C protocol.
The clinic's published 2005 paper (Riordan 2005) tested a different design: a pilot of continuous infusion in 24 terminal cancer patients given 150–710 mg/kg/day for up to eight weeks, reaching a mean plasma level of 1.1 mM. Most side effects were minor (nausea, swelling, dry mouth or skin). Two serious (grade 3) events were possibly related: a kidney stone in a patient with a history of kidney stones, and low blood potassium (hypokalemia). The authors concluded the therapy was relatively safe for patients without a history of kidney stones.
The Riordan Intravenous Vitamin C (RIVC) protocol below is the clinic's own practice protocol, refined over thousands of patient-treatment-sessions (a practitioner protocol, not the content of the 2005 paper):
- Initial test dose: 15 g intravenous ascorbate (as buffered sodium ascorbate) infused over 60–90 minutes — verifies tolerance and measures post-infusion plasma ascorbate
- Standard escalation: Increase to 25 g, then 50 g, then 75 g per infusion as tolerated, monitoring plasma ascorbate to confirm reaching pharmacological levels (typically >7,000 µM / 7 mM)
- Maintenance frequency: 2–3 infusions per week during active treatment phase
- Duration: Months, often years; continued indefinitely in patients with response
- Concurrent oral: 4–10 g/day oral ascorbate to maintain baseline tissue ascorbate between infusions
- Adjunctive nutrients: Magnesium (to support cardiovascular tolerance of infusion volume), B-complex, glutathione, alpha lipoic acid as indicated; protocols vary by clinic
- Pre-treatment requirements: glucose-6-phosphate dehydrogenase enzyme assay (rule out deficiency); complete blood count (CBC) and comprehensive metabolic panel (CMP) (rule out renal failure or marked hypovolemia); review of all current chemotherapy / radiation timing
Practitioners describe a similar approach at many North American integrative oncology intravenous vitamin C clinics. Specific dosing and frequency vary, but the basic architecture — pharmacological dosing aimed at >5–20 mM plasma, 2–3 weekly, indefinite duration, glucose-6-phosphate dehydrogenase-screened patients — is consistent across practitioners.
Cost in the US in 2026: typically $150–$400 per infusion at private integrative oncology clinics. Most insurance does not cover it. A treatment year is often $20,000–$50,000 out of pocket. The financial burden is a real constraint and is one reason oral high-dose remains the more accessible option even though it is biochemically inferior for the cancer indication.
Modern Trials: University of Kansas, Cornell, Iowa
The University of Kansas Medical Center integrative oncology program (Jeanne Drisko and colleagues) has been a major academic center for intravenous vitamin C trials. Their published ovarian cancer work (Ma 2014, Science Translational Medicine) found that intravenous ascorbate combined with carboplatin and paclitaxel inhibited ovarian cancer synergistically in mouse models, and reduced chemotherapy-associated toxicity in patients with ovarian cancer. The pancreatic cancer trials at Kansas, Iowa, and Cornell have explored ascorbate as chemosensitizer or radiosensitizer rather than monotherapy.
The University of Iowa Free Radical Cancer Biology program (Garry Buettner, Joseph Cullen, Bryan Allen) has focused on intravenous ascorbate as a radiosensitizer. Their NSCLC and GBM phase I/II trials have shown the combination is well-tolerated and have suggested radiosensitization benefit, with phase III trials ongoing.
Iowa has also tested intravenous ascorbate with chemotherapy in lung cancer. In a phase II trial (Furqan 2022), 38 people with advanced NSCLC who had not had chemotherapy received 75 g intravenous ascorbate twice a week with carboplatin and paclitaxel. Tumors shrank (confirmed partial response) in 34.2%, against a historical comparison figure of 20% (P = 0.03); median progression-free survival (time before the cancer grew) was 5.7 months and overall survival 12.8 months. Treatment-related side effects included one death (from fever with very low white blood cells, called neutropenic fever) and five grade 4 drops in blood counts. The trial had no randomized comparison group.
Memorial Sloan Kettering, MD Anderson, and other major National Cancer Institute (NCI)-designated cancer centers have run smaller pilot trials, with mixed but generally encouraging results. The current research direction is increasingly toward intravenous ascorbate as combination therapy (sensitizer for chemo or radiation; toxicity-reducer for chemo) rather than as monotherapy.
Pancreatic cancer is the most-studied tumor type. Lung cancer (especially NSCLC) is the most-studied with radiation combinations. Glioblastoma is studied at Iowa specifically. Ovarian cancer has the Kansas data. Blood cancers, including lymphomas and leukemias, are an emerging area. For leukemia with a faulty TET2 gene, Cimmino 2017 found in mice and in human leukemia cells (including human leukemia grown in mice) that vitamin C mimicked restoring TET2 function and slowed leukemia progression; it was not a study in patients.
What the Evidence Shows — And What It Doesn't
An honest accounting in 2026:
The randomized trials so far
- Colorectal cancer, phase III (VITALITY, Wang 2022): the largest randomized trial so far. 442 people with untreated metastatic colorectal cancer and normal glucose-6-phosphate dehydrogenase status received FOLFOX chemotherapy (folinic acid, fluorouracil and oxaliplatin, with or without bevacizumab), with or without intravenous vitamin C 1.5 g/kg/day on days 1–3. Overall, vitamin C did not lengthen progression-free survival (median 8.6 vs 8.3 months; HR 0.86; P = 0.1) or overall survival (20.7 vs 19.7 months). In a prespecified subgroup with RAS mutations, progression-free survival was longer with vitamin C (9.2 vs 7.8 months; HR 0.67; P = 0.01). Serious (grade 3 or higher) treatment-related side effects occurred in 33.5% with vitamin C and 30.3% without.
- Pancreatic cancer, randomized phase II (Bodeker 2024, University of Iowa): 36 people with stage IV pancreatic cancer were randomized to gemcitabine plus nab-paclitaxel, with or without intravenous vitamin C 75 g three times a week. Median overall survival was 16 months with vitamin C vs 8.3 months without (HR 0.46; P = 0.030), and progression-free survival 6.2 vs 3.9 months. Adding vitamin C did not worsen quality of life or increase side effects. It is a small trial.
What the evidence DOES show
- Intravenous ascorbate at 50–100 g per infusion reliably achieves plasma concentrations (5–20 mM) that activate the pro-oxidant H&sub2;O&sub2; mechanism in pre-clinical models
- The procedure is safe in glucose-6-phosphate dehydrogenase-screened, properly hydrated, normal-renal-function patients — serious adverse events are uncommon
- Multiple cancer cell lines and xenograft models show meaningful in-vivo growth inhibition from pharmacological ascorbate alone
- Intravenous ascorbate appears to reduce chemotherapy toxicity (especially fatigue and nausea) when added to standard chemotherapy regimens, improving quality of life
- The radiosensitization signal in NSCLC and GBM is mechanistically coherent and supported by phase I/II data
- Subset analyses suggest particular benefit in some groups: in the VITALITY phase III trial, people with RAS-mutant colorectal cancer had longer progression-free survival (9.2 vs 7.8 months), and in pancreatic cancer the small Bodeker 2024 randomized trial reported longer overall survival (16 vs 8.3 months)
- Case series of durable remissions in advanced cancers (especially lymphomas) are real and credibly documented, though uncontrolled
What the evidence DOES NOT yet show
- No phase III randomized controlled trial has demonstrated improved overall survival from intravenous ascorbate monotherapy or combination therapy in any cancer type. The one published phase III trial (VITALITY, colorectal cancer) was negative overall, with a positive result only in the RAS-mutant subgroup. The pancreatic and lung cancer results come from small phase II trials (36 and 38 people) that have not yet been confirmed in a phase III trial. The trials underway may change this in the next 3–5 years.
- The optimal dose, infusion frequency, and treatment duration are not standardized — clinical practice varies widely and may be sub-optimal in either direction
- Which cancers respond and which do not is not fully characterized — current selection is partly based on mechanism (KRAS/BRAF mutants; low-catalase tumors) and partly on tradition (Riordan-era pancreatic and ovarian emphasis)
- Whether intravenous ascorbate combined with specific newer targeted therapies (immune checkpoint inhibitors, chimeric antigen receptor T-cell (CAR-T) therapy, cyclin-dependent kinase 4/6 (CDK4/6) inhibitors) helps, hurts, or is neutral is largely unknown
- Cost-effectiveness has not been formally analyzed in any health-system context
Where the Evidence Leaves Patients
Intravenous vitamin C is one of the most-studied integrative oncology interventions and has the strongest mechanistic case of any "complementary" cancer treatment. It has not been shown to cure cancer, and marketing it as a cure goes beyond the evidence. The studies above give the most support to its use as an add-on to standard cancer care, especially for reducing chemotherapy side effects and supporting quality of life; whether it kills cancer in people is still uncertain and appears to depend on tumor type. Every trial described here tested it alongside standard treatment, not in place of it. Cost and time (2–3 infusions a week) are real burdens.
Glucose-6-Phosphate Dehydrogenase Screening — The Essential Safety Step
Glucose-6-phosphate dehydrogenase (G6PD) deficiency is an X-linked enzyme deficiency affecting roughly 400 million people worldwide, with highest prevalence in people of African, Mediterranean, Middle Eastern, and Southeast Asian descent. Glucose-6-phosphate dehydrogenase is the rate-limiting enzyme in the pentose phosphate pathway that generates reduced nicotinamide adenine dinucleotide phosphate, which keeps glutathione reduced. Glucose-6-phosphate dehydrogenase-deficient red blood cells cannot regenerate glutathione fast enough to detoxify acute oxidative stress.
High-dose intravenous ascorbate generates extracellular H&sub2;O&sub2;. In glucose-6-phosphate dehydrogenase-deficient patients, this H&sub2;O&sub2; can overwhelm red cell glutathione defenses and cause acute hemolysis — a potentially life-threatening medical emergency. Several cases of fatal hemolysis from intravenous vitamin C in unrecognized glucose-6-phosphate dehydrogenase deficiency have been published.
The screening test is a simple quantitative glucose-6-phosphate dehydrogenase enzyme assay on a blood sample. It costs around $30–100 and is widely available. The Riordan protocol lists the glucose-6-phosphate dehydrogenase test as a pre-treatment requirement, and the VITALITY phase III trial enrolled only people with normal glucose-6-phosphate dehydrogenase status. Infusing without the test exposes a deficient person to the hemolysis risk described above.
In glucose-6-phosphate dehydrogenase-deficient patients, intravenous ascorbate is contraindicated. Oral high-dose vitamin C is generally considered safe even in glucose-6-phosphate dehydrogenase deficiency (oral plasma concentrations stay too low to generate problematic H&sub2;O&sub2; loads), though some practitioners advise caution at bowel-tolerance levels.
Integration With Conventional Oncology
Older concerns that vitamin C would "interfere with chemotherapy by blocking the oxidative damage chemo depends on" have largely been resolved in the negative direction. The Welsh 2013 pancreatic cancer phase I work and subsequent combination studies have shown that intravenous ascorbate generally either does not interfere or actively sensitizes chemotherapy. Some specific drug combinations are favorable:
- Gemcitabine (pancreatic, NSCLC) — multiple positive combination signals
- Carboplatin + paclitaxel (ovarian) — Kansas work (Ma 2014) reported reduced chemotherapy-associated toxicity in patients
- Radiation therapy (NSCLC, GBM) — mechanistically rational radiosensitization
- Fluorouracil (5-FU) / FOLFIRINOX — emerging combinations in colorectal and pancreatic
Combinations that may warrant more caution:
- Bortezomib in multiple myeloma — some in-vitro data suggests high vitamin C might reduce bortezomib efficacy by direct chemical reduction of the boronic acid. Most clinicians separate intravenous ascorbate from bortezomib dosing by at least 24 hours.
- Methotrexate — vitamin C may slightly enhance methotrexate clearance; some protocols separate the timing of the two.
For timing relative to chemotherapy infusions: most protocols give intravenous ascorbate either on chemo-free days or 2–4 hours after the chemotherapy infusion completes. This avoids any theoretical direct chemical interaction in the bloodstream during infusion.
For radiation therapy combinations, intravenous ascorbate is typically given within hours before each radiation session to amplify the radiation-induced reactive oxygen species damage in the tumor.
A parallel intravenous protocol that the oncology team does not know about can lead to conflict over care and to misinterpretation of imaging and lab changes.
Cautions & Contraindications
- Glucose-6-phosphate dehydrogenase deficiency — absolute contraindication for intravenous high-dose (see above). The protocols and trials above test for it before the first infusion.
- Renal failure — ascorbate is cleared renally; impaired clearance allows prolonged elevation and risks oxalate-stone formation. Kidney clearance is lowest in chronic kidney disease (CKD) stage 4–5, and Padayatty 2010 names kidney impairment as one of the two known settings for complications of intravenous vitamin C.
- Hemochromatosis or iron overload — ascorbate mobilizes iron and could worsen iron-mediated tissue damage.
- Active oxalate kidney stones — high-dose vitamin C increases urinary oxalate; relative contraindication. In the Riordan 2005 pilot, a patient with a history of kidney stones developed a stone after 13 days of treatment. Practitioners use generous hydration when it is given.
- Severe heart failure — the infusion volume (typically 250–500 mL of fluid per infusion) can precipitate fluid overload in compromised cardiac status. Practitioners reduce the volume or skip infusions in this case.
- Pregnancy — intravenous high-dose vitamin C in pregnancy is not well-studied, and practitioners generally do not use it in pregnancy.
- Concurrent bortezomib — practitioners separate the two by more than 24 hours (see above).
- Glucose-meter interference — many glucometers (the ones using glucose dehydrogenase chemistry strips) read falsely elevated glucose when plasma ascorbate is very high. For people with diabetes on insulin, a falsely "high" reading in the hours after an infusion can lead to an insulin dose that is not needed, which can push blood sugar too low.
Patient FAQ
Q: How much does intravenous vitamin C cost?
$150–$400 per infusion at most US integrative oncology clinics; typically 2–3 infusions per week. Annual cost $15,000–$60,000 out of pocket in most cases. Insurance rarely covers it.
Q: Can this replace chemotherapy?
No. The strongest evidence supports intravenous vitamin C as an adjunct to standard oncologic care, not a replacement. Patients who use it as a substitute for evidence-based treatment have worse outcomes.
Q: Will my oncologist support this?
Increasingly, yes — especially at academic centers with integrative oncology programs. Patients whose oncologist is not supportive sometimes seek a referral to an integrative oncologist or to one of the academic centers running trials (Kansas, Iowa, Memorial Sloan Kettering).
Q: How quickly will it work?
For quality-of-life and chemotherapy toxicity reduction: often within 1–3 weeks. For tumor response: this is highly variable and depends on tumor type, stage, and what else is being done. Some patients show measurable tumor markers improvement within 2–3 months; some show no measurable benefit; some show stabilization without shrinkage.
Q: Is there an oral alternative?
For the pharmacological pro-oxidant cancer mechanism, no — oral cannot reach the required plasma concentrations. For general supportive care during cancer treatment (immune support, fatigue, antioxidant defense), practitioners use high-dose oral vitamin C (4–10 g/day in divided doses, or to bowel tolerance) as a lower-cost option for the non-pharmacological effects.
Q: What about liposomal vitamin C?
Liposomal oral vitamin C does achieve higher plasma levels than conventional oral (Davis 2016) but still does not reach the multi-millimolar pharmacological range. It sits between conventional oral and intravenous but does not replace intravenous for cancer indications.
Key Research Papers
- Cameron E, Pauling L (1976). Supplemental ascorbate in the supportive treatment of cancer: Prolongation of survival times in terminal human cancer. PNAS. — PubMed PMID: 1068480
- Cameron E, Pauling L (1978). Supplemental ascorbate in the supportive treatment of cancer: reevaluation of prolongation of survival times in terminal human cancer. PNAS. — PubMed PMID: 279931
- Creagan ET et al. (1979). Failure of high-dose vitamin C (ascorbic acid) therapy to benefit patients with advanced cancer. A controlled trial. NEJM. — PubMed PMID: 384241
- Moertel CG et al. (1985). High-dose vitamin C versus placebo in the treatment of patients with advanced cancer who have had no prior chemotherapy. NEJM. — PubMed PMID: 3880867
- Padayatty SJ et al. (2004). Vitamin C pharmacokinetics: implications for oral and intravenous use. Ann Intern Med. — PubMed PMID: 15068981
- Padayatty SJ et al. (2006). Intravenously administered vitamin C as cancer therapy: three cases. CMAJ. — PubMed PMID: 16567755
- Chen Q et al. (2005). Pharmacologic ascorbic acid concentrations selectively kill cancer cells. PNAS. — PubMed PMID: 16157892
- Chen Q et al. (2008). Pharmacologic doses of ascorbate act as a prooxidant in tumor xenografts. PNAS. — PubMed PMID: 18678913
- Schoenfeld JD et al. (2017). O&sub2;&sup-; and H&sub2;O&sub2;-mediated disruption of Fe metabolism causes the differential susceptibility of NSCLC and GBM cancer cells to pharmacological ascorbate. Cancer Cell. — PubMed PMID: 28366679
- Yun J et al. (2015). Vitamin C selectively kills KRAS and BRAF mutant colorectal cancer cells. Science. — PubMed PMID: 26541605
- Welsh JL et al. (2013). Pharmacological ascorbate with gemcitabine for the control of metastatic and node-positive pancreatic cancer. Cancer Chemother Pharmacol. — PubMed PMID: 23381814
- Riordan HD et al. (2005). A pilot clinical study of continuous intravenous ascorbate in terminal cancer patients. PR Health Sci J. — PubMed PMID: 16570523
- Hoffer LJ et al. (2008). Phase I clinical trial of i.v. ascorbic acid in advanced malignancy. Ann Oncol. — PubMed PMID: 18544557
- Padayatty SJ et al. (2010). Vitamin C: intravenous use by complementary and alternative medicine practitioners and adverse effects. PLoS ONE. — PubMed PMID: 20628650
- Cimmino L et al. (2017). Restoration of TET2 function blocks aberrant self-renewal and leukemia progression by ascorbate. Cell. — PubMed PMID: 28823558
- Ma Y et al. (2014). High-dose parenteral ascorbate enhanced chemosensitivity of ovarian cancer and reduced toxicity of chemotherapy. Sci Transl Med. — PubMed PMID: 24500406
- Wang F et al. (2022). A Randomized, Open-Label, Multicenter, Phase 3 Study of High-Dose Vitamin C Plus FOLFOX ± Bevacizumab versus FOLFOX ± Bevacizumab in Unresectable Untreated Metastatic Colorectal Cancer (VITALITY Study). Clin Cancer Res. — PubMed PMID: 35929990
- Furqan M et al. (2022). Pharmacological ascorbate improves the response to platinum-based chemotherapy in advanced stage non-small cell lung cancer. Redox Biol. — PubMed PMID: 35525024
- Bodeker KL et al. (2024). A randomized trial of pharmacological ascorbate, gemcitabine, and nab-paclitaxel for metastatic pancreatic cancer. Redox Biol. — PubMed PMID: 39369582
- Polireddy K et al. (2017). High-dose parenteral ascorbate inhibited pancreatic cancer growth and metastasis. Sci Rep. — PubMed PMID: 29215048
PubMed Topic Searches
Connections
- All Vitamins
- Dr. Abram Hoffer — the psychiatrist-biochemist whose niacin and vitamin C program founded orthomolecular medicine
- Linus Pauling & the Cameron Collaboration — the story behind the 1976 survival claims this page evaluates
- Vitamin C, Collagen & Why Sailors Fell Apart — interactive animation
- Vitamin C Overview
- Vitamin C Benefits Hub
- Vitamin C for Immune Function
- Vitamin C for Collagen Synthesis
- Vitamin C for Iron Absorption
- Cancer
- Alpha Lipoic Acid Benefits Hub
- Glutathione
- N-Acetylcysteine
- Gerson Therapy
- Fenbendazole
- Oxidative Stress
- Magnesium
- Iron
- Glucose-6-phosphate dehydrogenase Enzyme Assay
- Ferritin
- All Antioxidants
- Covered in depth on its own page: Catalase
- Deficiency
- Toxicity
- History
- Sources