Folate for Depression & Mental Health
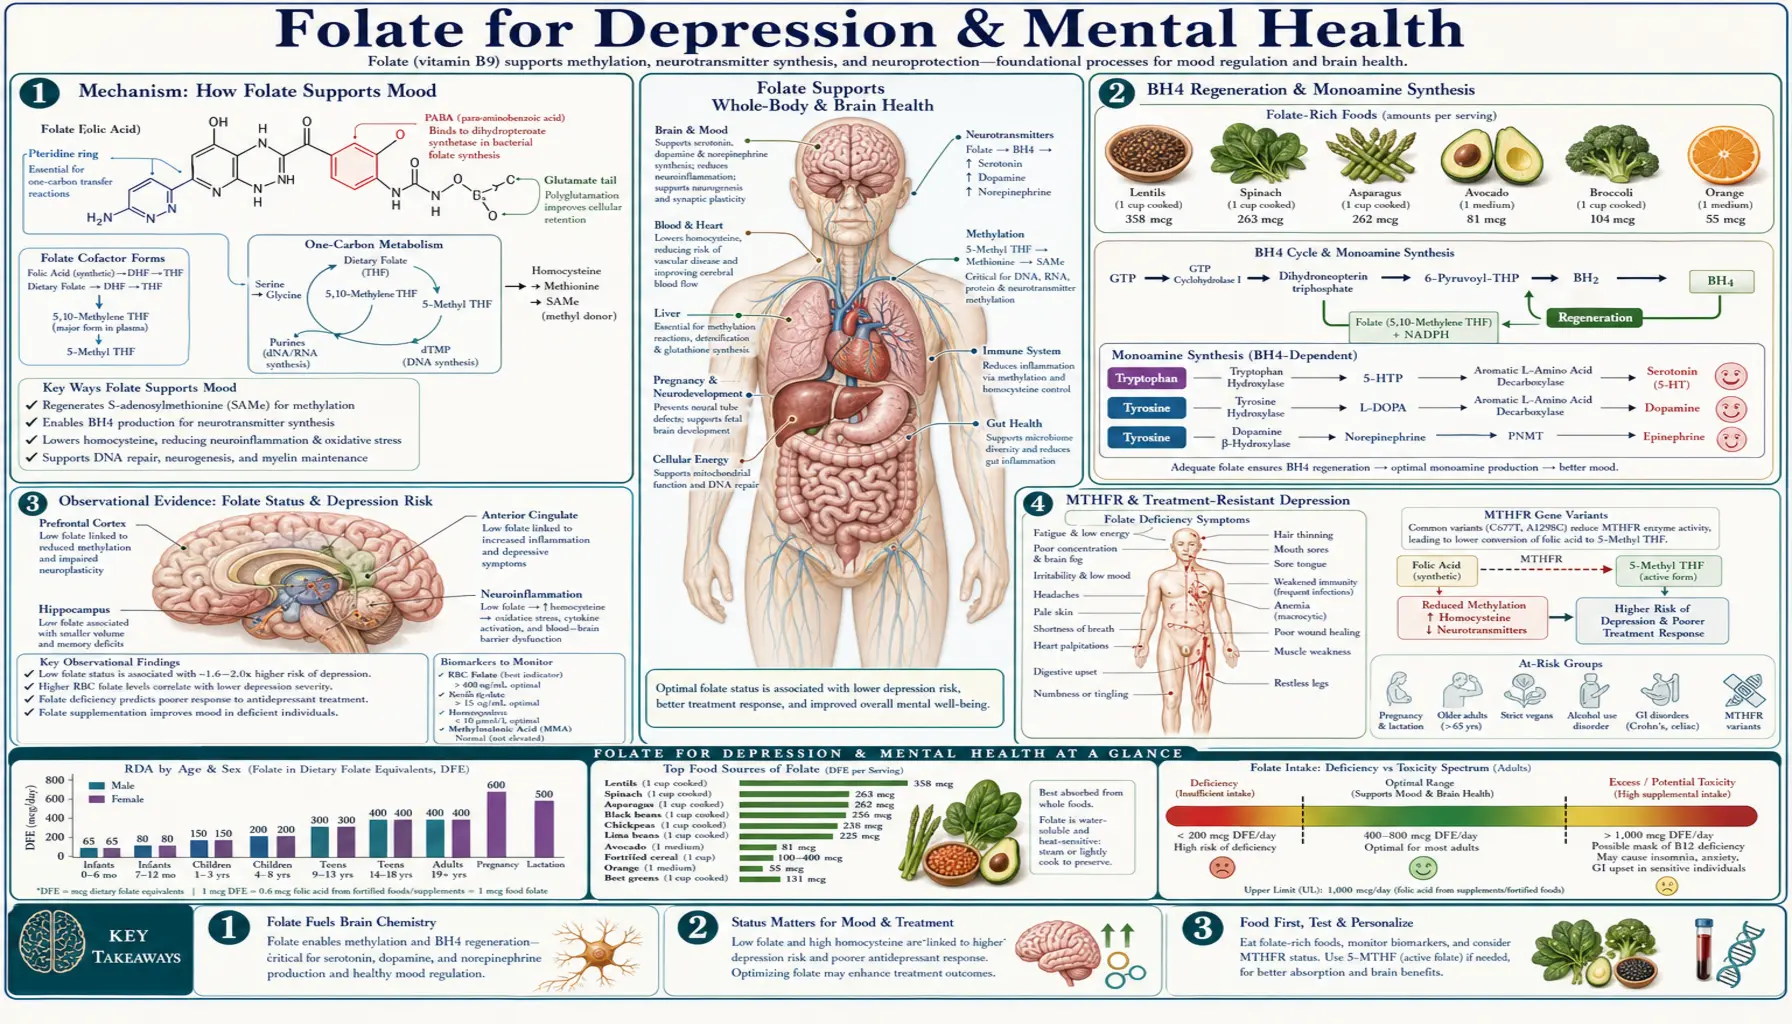
Low folate status is associated with depression in observational studies, and several trials have added a folate form to antidepressant treatment. In a 2000 trial, 500 mcg of folic acid added to fluoxetine gave greater improvement overall, an effect confined to women (Coppen 2000). In two 2012 trials of L-methylfolate added to an SSRI in people who had not responded to it, the first found no significant difference from placebo and the second found 15 mg a day more effective than placebo, with a number needed to treat of about six (Papakostas 2012). A 2022 meta-analysis described the effect of adjunctive L-methylfolate as small and its efficacy as possibly modest (Maruf 2022), and a large 2014 trial of 5 mg of folic acid added to antidepressants found no benefit (Bedson 2014). This page covers those trials, the MTHFR–depression association, what the FDA's medical-food framework says, postpartum depression, schizophrenia, bipolar disorder, cognitive decline and the safety findings.
Table of Contents
- Proposed Mechanisms: Folate and Mood
- BH4 & Monoamine Synthesis
- Observational Evidence: Folate Status & Depression
- MTHFR Variants & Depression
- Coppen & Bailey (2000) Folic Acid + Fluoxetine
- Papakostas (2012) L-Methylfolate + SSRI
- L-Methylfolate and the FDA Medical-Food Framework
- Folic Acid and L-Methylfolate: What the Trials Show
- Pregnancy and Postpartum Depression
- Schizophrenia, Bipolar Disorder & Autism
- Cognitive Decline & Dementia
- Doses Used in the Trials
- Safety Findings & Interactions
- Key Research Papers
- Connections
- Featured Videos
Proposed Mechanisms: Folate and Mood
The pathways most often proposed to link folate with mood, as described in the reviews cited here:
- SAMe (S-adenosylmethionine) and methylation — folate and vitamin B12 are required both to turn homocysteine back into methionine and to make SAMe, which takes part in methylation reactions involving proteins, phospholipids, DNA and neurotransmitter metabolism. A current theory holds that a defect in methylation is central to the neuropsychiatric effects of folate and B12 deficiency (Bottiglieri 1996).
- Monoamine synthesis — folate is needed in the brain for the synthesis of norepinephrine, serotonin and dopamine (Fava & Mischoulon 2009), and folate deficiency may specifically affect central monoamine metabolism and aggravate depressive disorders (Bottiglieri 1996).
- Homocysteine — homocysteine is a sensitive marker of folate and B12 deficiency; whether it is only a marker or plays a more direct role in mood disorders is not completely understood (Bottiglieri 2005). Possible neurotoxic effects of homocysteine have also been proposed (Bottiglieri 1996).
SAMe itself has been tested as an antidepressant. A 2016 Cochrane review of eight trials (934 adults) found no strong evidence of a difference from placebo as monotherapy (very low quality evidence), similar results to imipramine (low quality evidence), and low quality evidence of benefit over placebo as an add-on to an SSRI in one trial of 73 people. The authors concluded that, given the absence of high quality evidence, SAMe for depression needs further investigation (Galizia 2016).
BH4 & Monoamine Synthesis
Tetrahydrobiopterin (BH4) is an essential cofactor for phenylalanine hydroxylase, tyrosine hydroxylase and the two tryptophan hydroxylases, as well as for the nitric oxide synthases. In inherited BH4 deficiency, defective tyrosine and tryptophan hydroxylase activity explains the neurological deterioration, and patients with one of these disorders (dihydropteridine reductase deficiency) also need folinic acid, since that enzyme may help keep folate in its tetrahydro form (Longo 2009).
Stahl's 2008 commentary states that synthesis of serotonin, dopamine and norepinephrine is regulated by L-methylfolate (Stahl 2008). The sources reviewed for this page do not describe a measured effect of L-methylfolate on BH4 in the brains of people with depression.
Observational Evidence: Folate Status & Depression
- Gilbody 2007 meta-analysis — 11 observational studies (15,315 participants: three case-control studies, seven population surveys and one cohort study). Low folate was associated with depression (pooled unadjusted odds ratio 1.55, 95% CI 1.26–1.91; adjusted 1.42, 1.10–1.83), and folate levels were lower in depression. The authors note that much of the evidence comes from case-control and cross-sectional studies, and that cohort studies and definitive randomized trials are required to confirm or refute a causal relationship (Gilbody 2007, J Epidemiol Community Health).
- Hordaland Homocysteine Study (Norway, 5,948 people aged 46–49 and 70–74) — high homocysteine (≥15 µmol/L; odds ratio 1.90) and the MTHFR TT genotype (odds ratio 1.69), but not low plasma folate or low B12, were related to depression without anxiety. Plasma folate was inversely associated with depression only in middle-aged women, and none of the factors studied was related to anxiety (Bjelland 2003).
- Reviews — Coppen and Bolander-Gouaille describe low plasma and especially red-cell folate in major depression, low B12 status in depressive patients, and a link between low folate and poor response to antidepressants (Coppen & Bolander-Gouaille 2005). Bottiglieri's 2005 review states that numerous studies have confirmed the association between folate deficiency and depression (Bottiglieri 2005).
Observational studies face confounding, reverse causality and measurement error, which is why genetic studies of the MTHFR variant have been used to ask whether the link is causal (Lewis 2006). A 2010 review concluded there is not enough data to justify prescribing folic acid as an aid in severe or chronic depression, and suggested examining folic acid levels in people at increased risk of deficiency or who do not respond to medication (Lazarou & Kapsou 2010).
MTHFR Variants & Depression
The MTHFR C677T variant has been studied as a natural test of whether folate metabolism affects depression risk. The associations are modest:
- Lewis 2006 — in 3,478 women in the British Women's Heart and Health Study, TT individuals had higher odds of ever being diagnosed with depression than CC individuals (odds ratio 1.35, 95% CI 1.01–1.80); a meta-analysis with eight other studies gave a summary odds ratio of 1.36 (1.11–1.67) (Lewis 2006).
- Gilbody 2007 HuGE review — for unipolar depression, TT versus CC odds ratio 1.36 (1.11–1.67), based on 1,280 cases and 10,429 controls (Gilbody 2007, Am J Epidemiol).
- Wu 2013 updated meta-analysis — 26 studies (4,992 cases, 17,082 controls): TT versus CC odds ratio 1.42 (1.16–1.75) overall; the association was clearer in Asian populations (TT vs CC 1.88), marginal in White populations (TT vs CT+CC 1.15, 1.01–1.31), and not observed in the elderly (Wu 2013).
CDC's MTHFR Gene Variant and Folic Acid Facts page states that “people with an MTHFR gene variant can process all types of folate, including folic acid,” and that more people in the United States have one or two copies of the C677T variant than do not. In a large folic acid trial in Chinese women, the TT genotype was associated with lower folate and higher homocysteine at every dose, and the genotype did not significantly interact with folic acid dose (Crider 2011).
A post hoc analysis of the second 2012 trial reported greater improvement with L-methylfolate than placebo among patients with certain genetic markers related to folate metabolism; its authors state that confirmatory studies are needed (Papakostas 2014). No trial found for this page compared L-methylfolate with folic acid in MTHFR carriers with depression.
Coppen & Bailey (2000) Folic Acid + Fluoxetine
Coppen and Bailey randomized 127 patients with major depression (Hamilton score of 20 or more) to 500 mcg of folic acid or an identical-looking placebo, in addition to 20 mg of fluoxetine daily, with plasma folate and homocysteine measured at baseline and at 10 weeks (Coppen 2000).
- Plasma folate rose with folic acid, less in men than in women. Homocysteine fell by 20.6% in women, with no significant change in men.
- Overall there was significantly greater improvement in the folic acid group. This was confined to women: mean Hamilton score at the end was 6.8 with folic acid and 11.7 with placebo (P<0.001), and 93.9% of women on folic acid had a good response (more than 50% reduction in score) compared with 61.1% on placebo.
- Side effects possibly or probably related to medication were reported by 12.9% in the folic acid group and 29.7% in the placebo group.
- The authors wrote that men need a higher folic acid dose than women to lower homocysteine and that more work is required to find the optimum dose.
A later and larger trial did not replicate a benefit of folic acid. In FolATED, 475 adults with moderate to severe depression who were taking or starting an antidepressant (and were not folate or B12 deficient) added 5 mg of folic acid or placebo daily for 12 weeks. Folic acid did not significantly improve any of the outcome measures and reduced SF-12 mental health scores by 3.0%; the authors suggested future trials of methylfolate (Bedson 2014).
Papakostas (2012) L-Methylfolate + SSRI
Papakostas and colleagues ran two multicenter trials using a sequential parallel comparison design in outpatients with major depressive disorder who had partial or no response to an SSRI. SSRI doses were kept constant (Papakostas 2012).
Trial 1
- 148 outpatients; 60 days in two 30-day periods
- Randomized 2:3:3 to L-methylfolate for 60 days (7.5 mg/day for 30 days, then 15 mg/day for 30 days), placebo for 30 days then L-methylfolate 7.5 mg/day, or placebo for 60 days
- Result: no significant difference in outcomes between the treatment groups
Trial 2
- 75 patients; the same design, with L-methylfolate at 15 mg/day in both 30-day periods
- Result: L-methylfolate 15 mg/day was significantly more effective than SSRI plus placebo on both primary outcomes (response rate and degree of change in depression score) and two secondary measures of symptom severity
- The number needed to treat for response was approximately six
- Adverse event rates did not differ from placebo
The authors concluded that adjunctive L-methylfolate at 15 mg/day may be an effective, safe and relatively well-tolerated strategy for patients who respond partly or not at all to SSRIs (Papakostas 2012).
Post hoc analyses of trial 2. Greater improvement with L-methylfolate than placebo was reported among patients with a body mass index of 30 or more, elevated high-sensitivity C-reactive protein or 4-hydroxy-2-nonenal, a low SAMe/SAH ratio, and certain genetic markers (Papakostas 2014). A separate exploratory analysis found a significant overall treatment effect on the 17-item Hamilton scale (−2.74 points) and a larger one in patients with BMI of 30 or more, but not in those below 30 (Shelton 2015). Both groups of authors state that further studies are needed to confirm these findings.
Meta-analysis. Maruf and colleagues reviewed nine articles (6,707 patients). In a meta-analysis of three studies (483 patients), adjunctive L-methylfolate was associated with a small effect on Hamilton response versus antidepressant monotherapy (relative risk 1.25, 95% CI 1.08–1.46); four studies (507 patients) using a continuous measure gave a standardized mean difference of −0.38. They note that L-methylfolate augmentation is rarely included in major clinical practice guidelines, and concluded that it may have modest efficacy in antidepressant-treated adults with major depression (Maruf 2022).
L-Methylfolate and the FDA Medical-Food Framework
In the United States, L-methylfolate for depression is available as L-methylfolate (medical-food product); the trials above used L-methylfolate calcium at 7.5 mg and 15 mg a day (Papakostas 2012; Shelton 2015).
What the FDA's Frequently Asked Questions About Medical Foods guidance (third edition, 2023) states:
- A medical food, as defined in the Orphan Drug Act, is “a food which is formulated to be consumed or administered enterally under the supervision of a physician and which is intended for the specific dietary management of a disease or condition for which distinctive nutritional requirements, based on recognized scientific principles, are established by medical evaluation.” The FDA considers this definition to narrowly constrain the products that fit the category.
- Medical foods are not drugs and are not subject to the regulatory requirements that specifically apply to drugs.
- There is no federal requirement that medical foods be dispensed by prescription, and their labeling may not bear the symbol “Rx only”; labeling may state that the product must be used under the supervision of a physician.
- “Under the supervision of a physician” is interpreted as active and ongoing medical supervision by a physician who has determined that the medical food is necessary to the patient's overall medical care.
The guidance describes the category; it does not name L-methylfolate or state that the FDA has evaluated it for depression.
Folic Acid and L-Methylfolate: What the Trials Show
No head-to-head trial of folic acid versus L-methylfolate in depression was found for this page. The evidence is indirect:
- Folic acid — a benefit confined to women at 500 mcg with fluoxetine (Coppen 2000); no benefit at 5 mg added to antidepressants in FolATED (Bedson 2014). The FolATED authors described their negative result as consistent with the view that methylfolate is a better candidate, and called for trials of it (Bedson 2014).
- L-methylfolate — no difference in the first 2012 trial and a benefit at 15 mg/day in the second (Papakostas 2012); a small effect in meta-analysis (Maruf 2022).
- Reviews — Fava and Mischoulon write that some forms may be more bioavailable than others in people with a genetic polymorphism or who take particular medications or use alcohol; that folic acid augmentation may reduce residual symptoms; that 5-MTHF may be less likely to incur some of the risks raised about folate; and that more information is needed about dosage and the populations most suited to folate therapy (Fava & Mischoulon 2009).
CDC states that people with an MTHFR variant can process all types of folate, including folic acid (see the MTHFR section above). The Methylation & Homocysteine page covers the studies that compared the blood markers of folic acid and 5-MTHF.
Pregnancy and Postpartum Depression
In a prospective cohort of 6,809 pregnant women in the UK, Lewis and colleagues found no strong evidence that folic acid supplementation during pregnancy reduced the risk of depression during pregnancy or up to 8 months after it. They did find evidence that supplements taken during pregnancy were associated with protection against depression 21 months after birth, more marked in women with the MTHFR TT genotype. They concluded that low folate is unlikely to be an important risk factor for depression in pregnancy and for postpartum depression, but may be a risk factor outside pregnancy (Lewis 2012).
No trial of L-methylfolate for postpartum depression was found for this page. Folic acid in pregnancy is covered on the Pregnancy & Neural Tube page.
Schizophrenia, Bipolar Disorder & Autism
Schizophrenia
- In the Gilbody 2007 HuGE meta-analysis, the MTHFR C677T TT versus CC odds ratio for schizophrenia was 1.44 (95% CI 1.21–1.70; 2,762 cases, 3,363 controls) (Gilbody 2007, Am J Epidemiol).
- Roffman and colleagues (JAMA Psychiatry 2013) randomized 140 outpatients with chronic schizophrenia and persistent symptoms on antipsychotics to 2 mg of folic acid plus 400 mcg of vitamin B12 daily, or placebo, for 16 weeks. The trial used folic acid, not L-methylfolate. Negative symptoms improved significantly with the vitamins when genotype was taken into account, but not when it was excluded; only patients homozygous for the 484T allele of the FOLH1 gene showed a significantly greater benefit. Positive and total symptoms did not differ between groups (Roffman 2013).
Bipolar disorder
- In the Gilbody 2007 HuGE meta-analysis, the TT versus CC odds ratio for bipolar disorder was 1.82 (95% CI 1.22–2.70; 550 cases, 1,098 controls).
- CEQUEL (2016) — 202 people with bipolar depression on quetiapine were randomized to lamotrigine or placebo and to folic acid or placebo. Folic acid was not superior to placebo, and there was a significant interaction in which folic acid reduced the effectiveness of lamotrigine at 12 weeks; the authors wrote that folic acid “seems to nullify the effect of lamotrigine” (Geddes 2016).
- Mania — in 88 patients with acute mania in bipolar I disorder, folic acid added to sodium valproate gave lower mania scores than placebo after 3 weeks (Behzadi 2009).
- L-methylfolate — an open-label registry of 10 patients with bipolar I depression given 15 mg/day for 6 weeks alongside usual treatment reported improvement in depression scores; the authors note it was small and uncontrolled, that regression to the mean cannot be ruled out, and that a controlled trial is warranted (Nierenberg 2017).
Autism spectrum disorder
- Cerebral folate deficiency, with blocking folate-receptor autoantibodies, is covered on the Methylation & Homocysteine page.
- Frye and colleagues randomized 48 children with autism and language impairment to high-dose folinic acid (2 mg/kg per day, maximum 50 mg per day) or placebo for 12 weeks. Verbal communication improved more with folinic acid (an effect of 5.7 standardized points), especially in children positive for folate receptor-α autoantibodies, with no significant difference in adverse effects. The authors describe it as a small trial (Frye 2018).
Cognitive Decline & Dementia
- VITACOG — 271 people over 70 with mild cognitive impairment took folic acid (0.8 mg/day), vitamin B12 (0.5 mg/day) and vitamin B6 (20 mg/day), or placebo, for 24 months. Among the 168 who completed the MRI part, brain atrophy was 0.76% a year with the vitamins and 1.08% a year with placebo (P=0.001). In participants with homocysteine above 13 µmol/L, the atrophy rate was 53% lower with treatment. The authors called for trials of whether the same treatment delays Alzheimer's disease (Smith 2010). The trial used folic acid, not methylfolate; it is covered in more detail on the Methylation chapter.
- Omega-3 status — a retrospective analysis of the same trial found that B vitamins slowed atrophy by 40.0% in people with high baseline omega-3 fatty acids (>590 µmol/L) and had no significant effect in those with low levels (<390 µmol/L) (Jernéren 2015).
Doses Used in the Trials
This section lists what the trials on this page used. It is a record of the research, not dosing guidance; decisions about medicines and supplements belong with a clinician.
- Major depression, added to an SSRI — L-methylfolate 7.5 mg/day then 15 mg/day (trial 1, no significant difference) and 15 mg/day (trial 2, benefit), each in 30-day periods over 60 days (Papakostas 2012).
- Major depression, added to fluoxetine 20 mg — folic acid 500 mcg/day for 10 weeks (Coppen 2000).
- Depression, added to antidepressants — folic acid 5 mg/day for 12 weeks, no benefit (Bedson 2014).
- Schizophrenia, added to antipsychotics — folic acid 2 mg plus vitamin B12 400 mcg daily for 16 weeks (Roffman 2013).
- Bipolar I depression, open-label — L-methylfolate 15 mg/day for 6 weeks in 10 patients (Nierenberg 2017).
- Mild cognitive impairment — folic acid 0.8 mg, B12 0.5 mg and B6 20 mg daily for 24 months (Smith 2010).
- Autism with language impairment — folinic acid 2 mg/kg per day (maximum 50 mg) for 12 weeks (Frye 2018).
- Reviews — Coppen and Bolander-Gouaille suggested trying folic acid (800 mcg daily) and vitamin B12 (1 mg daily) to improve treatment outcome in depression (Coppen & Bolander-Gouaille 2005); this was the review's suggestion, made before the FolATED trial.
Safety Findings & Interactions
- Vitamin B12 deficiency — Fava and Mischoulon list masking of B12 deficiency among the concerns historically raised about folate, together with cancer risk and worsening depressive symptoms, and write that 5-MTHF may be less likely to incur some of these risks (Fava & Mischoulon 2009). The Methylation & Homocysteine page covers the B12 masking findings and guidelines in detail.
- Lamotrigine — in the CEQUEL trial, folic acid reduced the effectiveness of lamotrigine in bipolar depression at 12 weeks, and the authors wrote that concurrent folic acid might reduce its effectiveness (Geddes 2016).
- Mania — the 2016 Cochrane review of SAMe recorded two reports of mania or hypomania among 441 participants given SAMe, and named induction of mania as of particular interest for future trials (Galizia 2016). In the open-label L-methylfolate registry in bipolar depression, mania scores did not rise (3.2 before, 2.7 after) (Nierenberg 2017).
- Tolerability in the trials — adverse event rates with L-methylfolate did not differ from placebo in the 2012 trials (Papakostas 2012); side effects were less common with folic acid than placebo in the fluoxetine trial (Coppen 2000); and the folinic acid trial in autism found no significant difference in adverse effects (Frye 2018).
- Antidepressants — the depression trials on this page added a folate form to an antidepressant whose dose was kept constant (Papakostas 2012) or to ongoing antidepressant treatment (Coppen 2000; Bedson 2014); none tested a folate form as a replacement for the antidepressant.
The homocysteine-lowering trials in heart disease, including NORVIT, are covered on the Methylation & Homocysteine page.
Key Research Papers
- Papakostas GI et al. (2012). L-methylfolate as adjunctive therapy for SSRI-resistant major depression: results of two randomized, double-blind, parallel-sequential trials. Am J Psychiatry 169:1267-74. — PubMed PMID: 23212058
- Coppen A, Bailey J (2000). Enhancement of the antidepressant action of fluoxetine by folic acid: a randomised, placebo controlled trial. J Affect Disord 60:121-30. — PubMed PMID: 10967371
- Fava M, Mischoulon D (2009). Folate in depression: efficacy, safety, differences in formulations, and clinical issues. J Clin Psychiatry 70 Suppl 5:12-7. — PubMed PMID: 19909688
- Coppen A, Bolander-Gouaille C (2005). Treatment of depression: time to consider folic acid and vitamin B12. J Psychopharmacol 19:59-65. — PubMed PMID: 15671130
- Bottiglieri T (2005). Homocysteine and folate metabolism in depression. Prog Neuropsychopharmacol Biol Psychiatry 29:1103-12. — PubMed PMID: 16109454
- Gilbody S, Lewis S, Lightfoot T (2007). Methylenetetrahydrofolate reductase (MTHFR) genetic polymorphisms and psychiatric disorders: a HuGE review. Am J Epidemiol 165:1-13. — PubMed PMID: 17074966
- Roffman JL et al. (2013). Randomized multicenter investigation of folate plus vitamin B12 supplementation in schizophrenia. JAMA Psychiatry 70:481-9. — PubMed PMID: 23467813
- Frye RE et al. (2018; online 2016). Folinic acid improves verbal communication in children with autism and language impairment: a randomized double-blind placebo-controlled trial. Mol Psychiatry 23:247-256. — PubMed PMID: 27752075
- Bottiglieri T (1996). Folate, vitamin B12, and neuropsychiatric disorders. Nutr Rev 54:382-90. — PubMed PMID: 9155210
- Stahl SM (2008). L-methylfolate: a vitamin for your monoamines. J Clin Psychiatry 69:1352-3. — PubMed PMID: 19193337
- Lewis SJ et al. (2006). The thermolabile variant of MTHFR is associated with depression in the British Women's Heart and Health Study and a meta-analysis. Mol Psychiatry 11:352-60. — PubMed PMID: 16402130
- Lazarou C, Kapsou M (2010). The role of folic acid in prevention and treatment of depression: an overview of existing evidence and implications for practice. Complement Ther Clin Pract 16:161-166. — PubMed PMID: 20621278
- Lewis SJ et al. (2012). Folic acid supplementation during pregnancy may protect against depression 21 months after pregnancy, an effect modified by MTHFR C677T genotype. Eur J Clin Nutr 66:97-103. — PubMed PMID: 21772318 (Editorial note: this entry previously listed a 2012 Mol Psychiatry paper carrying the title of the 2006 paper above; no such paper is in PubMed. This is the 2012 Lewis paper on folate and depression.)
- Gilbody S, Lightfoot T, Sheldon T (2007). Is low folate a risk factor for depression? A meta-analysis and exploration of heterogeneity. J Epidemiol Community Health 61:631-7. — PubMed PMID: 17568057
- Maruf AA, Poweleit EA, Brown LC, Strawn JR, Bousman CA (2022). Systematic review and meta-analysis of L-methylfolate augmentation in depressive disorders. Pharmacopsychiatry 55:139-147. — PubMed PMID: 34794190
- Bedson E et al. (2014). Folate Augmentation of Treatment – Evaluation for Depression (FolATED): randomised trial and economic evaluation. Health Technol Assess 18(48):1-159. — PubMed PMID: 25052890
- Papakostas GI et al. (2014). Effect of adjunctive L-methylfolate 15 mg among inadequate responders to SSRIs in depressed patients who were stratified by biomarker levels and genotype: results from a randomized clinical trial. J Clin Psychiatry 75:855-63. — PubMed PMID: 24813065
- Shelton RC et al. (2015). Association of obesity and inflammatory marker levels on treatment outcome: results from a double-blind, randomized study of adjunctive L-methylfolate calcium in patients with MDD who are inadequate responders to SSRIs. J Clin Psychiatry 76:1635-41. — PubMed PMID: 26613389
- Bjelland I, Tell GS, Vollset SE, Refsum H, Ueland PM (2003). Folate, vitamin B12, homocysteine, and the MTHFR 677C→T polymorphism in anxiety and depression: the Hordaland Homocysteine Study. Arch Gen Psychiatry 60:618-26. — PubMed PMID: 12796225
- Wu YL et al. (2013). Association between MTHFR C677T polymorphism and depression: an updated meta-analysis of 26 studies. Prog Neuropsychopharmacol Biol Psychiatry 46:78-85. — PubMed PMID: 23831680
- Crider KS et al. (2011). MTHFR 677C→T genotype is associated with folate and homocysteine concentrations in a large, population-based, double-blind trial of folic acid supplementation. Am J Clin Nutr 93:1365-72. — PubMed PMID: 21508090
- Galizia I et al. (2016). S-adenosyl methionine (SAMe) for depression in adults. Cochrane Database Syst Rev 10:CD011286. — PubMed PMID: 27727432
- Geddes JR et al. (2016). Comparative evaluation of quetiapine plus lamotrigine combination versus quetiapine monotherapy (and folic acid versus placebo) in bipolar depression (CEQUEL): a 2 × 2 factorial randomised trial. Lancet Psychiatry 3:31-39. — PubMed PMID: 26687300
- Behzadi AH et al. (2009). Folic acid efficacy as an alternative drug added to sodium valproate in the treatment of acute phase of mania in bipolar disorder: a double-blind randomized controlled trial. Acta Psychiatr Scand 120:441-5. — PubMed PMID: 19392814
- Nierenberg AA et al. (2017). L-Methylfolate for bipolar I depressive episodes: an open trial proof-of-concept registry. J Affect Disord 207:429-433. — PubMed PMID: 27794238
- Smith AD et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PLoS One 5:e12244. — PubMed PMID: 20838622
- Jernéren F et al. (2015). Brain atrophy in cognitively impaired elderly: the importance of long-chain ω-3 fatty acids and B vitamin status in a randomized controlled trial. Am J Clin Nutr 102:215-21. — PubMed PMID: 25877495
- Longo N (2009). Disorders of biopterin metabolism. J Inherit Metab Dis 32:333-42. — PubMed PMID: 19234759
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B9 Overview
- B9 Benefits Hub
- B9 Pregnancy & Neural Tube
- B9 Methylation & Homocysteine
- B9 Cardiovascular & Stroke
- Folate and Mental Health
- Vitamin B12 (Methylcobalamin)
- Vitamin B6 (P5P)
- Vitamin B2 (Riboflavin)
- Vitamin D
- Methionine
- Tryptophan
- Tyrosine
- Homocysteine
- Depression
- Anxiety
- Alzheimer's Disease
- Dementia
- Deficiency
- Toxicity
- History
- Sources