Kidney Disease
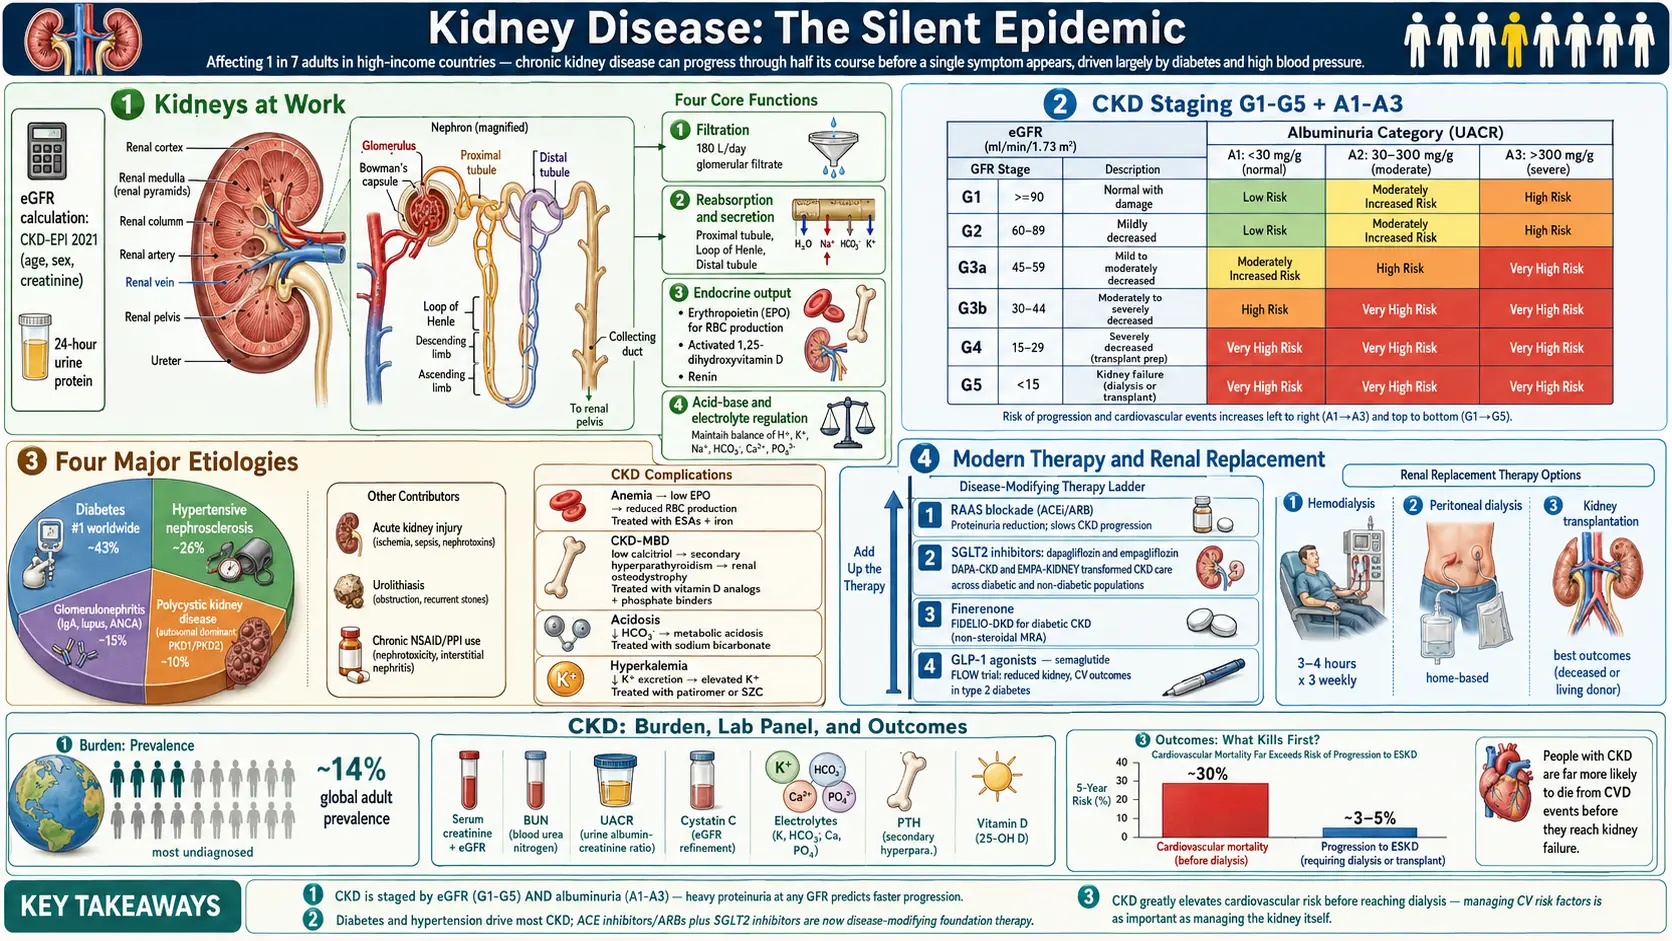
The kidneys are the body's silent chemists — two fist-sized organs that filter roughly 180 liters of blood per day, regulate blood pressure, balance electrolytes, activate vitamin D, produce erythropoietin for red blood cell formation, and quietly remove the metabolic waste generated by every cell in the body. When they start to fail, they fail quietly. Chronic kidney disease (CKD) can progress through half of its course before a single symptom appears, which is why it is sometimes called the silent epidemic: an estimated 1 in 7 adults in high-income countries have some degree of chronic kidney disease, and most of them do not know it. The good news is that chronic kidney disease is largely a disease of two other conditions — diabetes and high blood pressure — and is therefore substantially preventable and, especially in its earlier stages, slowable with the right medical, nutritional, and lifestyle strategies.
Deep-Dive Articles
Kidney disease is a big topic, and most people arrive with one specific worry — a lab result, a new diagnosis, a diet question, or a decision about what comes next. The five guides below each go deep on one part of the journey. Start wherever you are.
Understanding Your Estimated Glomerular Filtration Rate & Chronic Kidney Disease Stage
What your estimated glomerular filtration rate (eGFR) number really means, how the G1–G5 stages and the albuminuria (UACR) axis combine in the KDIGO risk map, when creatinine misleads, and when to ask for a nephrologist.
Read the deep dive →The Kidney-Friendly Diet
Sodium, potassium, phosphorus, and protein in plain language — with real food lists, label-reading tricks, the potassium double-edge, and why the rules flip on dialysis.
Read the deep dive →Slowing Chronic Kidney Disease Progression
The modern toolkit that changed the outlook: sodium-glucose cotransporter-2 (SGLT2) inhibitors, finerenone, glucagon-like peptide-1 receptor agonists (GLP-1s), ACE/angiotensin receptor blockers (ARBs), and blood-pressure targets — plus nephrotoxins to avoid and a what-to-ask-your-doctor checklist.
Read the deep dive →Diabetic Kidney Disease
The number-one cause of kidney failure: why diabetes harms the kidneys, the microalbuminuria early-warning test, and the four pillars of protection that can now slow it dramatically.
Read the deep dive →Dialysis & Transplant
Preparing for kidney failure without panic: hemodialysis vs peritoneal dialysis vs transplant vs conservative care, how access works, and why planning early matters.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- What is Kidney Disease?
- Types of Kidney Disease
- Stages of Chronic Kidney Disease
- Common Symptoms
- Causes and Risk Factors
- Diagnosis
- Lab Tests to Monitor
- Treatment Options
- Natural & Nutritional Support
- Prevention and Management Strategies
- Complications of Kidney Disease
- Key Research Papers
- Featured Videos
What is Kidney Disease?
Kidney disease refers to any condition that affects the kidneys' ability to filter waste and excess fluids from the blood to produce urine. When kidneys are damaged, waste can build up in the body, leading to a range of health problems. Kidney disease can be acute (sudden) or chronic (long-term), with chronic kidney disease (CKD) being more common and potentially leading to kidney failure if not managed properly.
Types of Kidney Disease
1. Chronic Kidney Disease (CKD)
- Long-term condition characterized by a gradual loss of kidney function over time.
- Common causes: Diabetes, high blood pressure, and glomerulonephritis.
2. Acute Kidney Injury (AKI)
- Sudden decrease in kidney function, often due to severe illness, injury, or certain medications.
- Can be reversible with prompt treatment.
3. Polycystic Kidney Disease (PKD)
- Genetic disorder that causes cysts to form in the kidneys, impairing their function.
- Can lead to chronic kidney disease and kidney failure over time.
4. Glomerulonephritis
- Inflammation of the glomeruli, the tiny filtering units in the kidneys.
- Can be acute or chronic and may result from infections, autoimmune diseases, or other conditions.
Stages of Chronic Kidney Disease
Chronic kidney disease is classified into five stages based on the estimated glomerular filtration rate (eGFR), a measure of how much blood the kidneys filter each minute, normalized to body surface area. Staging guides both monitoring frequency and treatment intensity. The KDIGO 2024 guideline defines chronic kidney disease as abnormalities of kidney structure or function present for at least three months, with implications for health: an estimated glomerular filtration rate below 60 mL/min/1.73 m², or a urine albumin-to-creatinine ratio of 30 mg/g or more, or other markers of kidney damage. That is why stages 1 and 2 below count as chronic kidney disease even though filtration is 60 or higher.
| Stage | Estimated glomerular filtration rate (mL/min/1.73 m²) | Description | Typical Management |
|---|---|---|---|
| Stage 1 | ≥ 90 | Normal filtration with evidence of kidney damage (e.g., protein in urine, imaging changes) | Treat underlying cause; control blood pressure and blood sugar |
| Stage 2 | 60–89 | Mildly reduced filtration with kidney damage | Aggressive risk-factor control; annual monitoring |
| Stage 3a | 45–59 | Mild to moderate loss of function | Every 6–12 months monitoring; angiotensin-converting enzyme inhibitor or angiotensin receptor blocker (ARB); sodium-glucose cotransporter-2 (SGLT2) inhibitor — KDIGO 2024 recommends one for people with type 2 diabetes, and for people without diabetes when urine albumin is high (albumin-to-creatinine ratio 200 mg/g or more) or heart failure is present |
| Stage 3b | 30–44 | Moderate to severe loss of function | Nephrology referral; manage anemia, bone disease, acidosis |
| Stage 4 | 15–29 | Severe loss of function | Planning for kidney replacement therapy or comprehensive conservative care; protein at 0.8 g/kg body weight per day (KDIGO 2024 suggestion for stages 3–5) |
| Stage 5 | < 15 | Kidney failure | Dialysis or kidney transplant, or comprehensive conservative care — KDIGO 2024 lists all three as options |
A separate albuminuria axis (A1, A2, A3) modifies the stage based on urine protein loss. A patient with stage 3a estimated glomerular filtration rate but heavy proteinuria (A3) has a substantially worse prognosis than stage 3a with minimal proteinuria (A1), which is why modern chronic kidney disease guidelines describe patients by both dimensions.
Common Symptoms of Kidney Disease
Symptoms may not appear until the disease is advanced. Common signs include:
- Fatigue and weakness
- Swelling (edema) in the legs, ankles, or feet
- Frequent urination, especially at night
- Blood in the urine
- Foamy urine due to excess protein
- High blood pressure
- Loss of appetite
- Nausea and vomiting
Causes and Risk Factors
- Diabetes: High blood sugar can damage blood vessels in the kidneys.
- High blood pressure: Can damage the kidneys over time.
- Genetic disorders: Such as polycystic kidney disease.
- Infections and autoimmune diseases: Such as lupus and glomerulonephritis.
- Prolonged use of certain medications: Such as nonsteroidal anti-inflammatory drugs (NSAIDs) and some antibiotics.
- Age: Risk increases with age, particularly after 60.
Diagnosis
- Blood tests: To measure levels of creatinine and calculate the estimated glomerular filtration rate (eGFR).
- Urine tests: To check for protein or blood in the urine.
- Imaging tests: Ultrasound or computed tomography (CT) scans to examine the structure of the kidneys.
- Kidney biopsy: To take a small tissue sample for examination.
Lab Tests to Monitor
Routine kidney-function monitoring relies on a small, focused panel of tests. Most of these are components of the Comprehensive Metabolic Panel ordered at a typical annual physical, plus a dedicated urine test.
- Serum creatinine: A waste product of muscle metabolism that the kidneys filter. Rising levels indicate declining function, though values vary with muscle mass.
- Estimated glomerular filtration rate (eGFR): Calculated from creatinine, age, and sex using the 2021 CKD-EPI equation. The single most important number for staging chronic kidney disease.
- Blood urea nitrogen (BUN): Another nitrogen-containing waste product. Elevated levels can reflect reduced filtration, dehydration, or high protein intake.
- Urine albumin-to-creatinine ratio (UACR): Detects small amounts of albumin leaking into the urine — often the earliest sign of kidney damage, years before estimated glomerular filtration rate drops.
- Cystatin C: An alternative marker independent of muscle mass, useful in elderly, very lean, or very muscular patients where creatinine is misleading.
- Serum electrolytes: Potassium, sodium, bicarbonate, calcium, and phosphorus all shift as kidney function declines and are monitored regularly.
- Parathyroid hormone (PTH) and vitamin D: chronic kidney disease-mineral and bone disorder (CKD-MBD) develops as kidneys lose the ability to activate vitamin D, driving secondary hyperparathyroidism.
Treatment Options
- Medications:
- Blood pressure drugs: Such as angiotensin-converting enzyme inhibitors (ACE inhibitors) or angiotensin receptor blockers to manage blood pressure and slow kidney damage.
- Diuretics: To reduce swelling.
- Medications for diabetes: To control blood sugar levels.
- Dietary changes:
- Less sodium, to control blood pressure and reduce fluid retention; the KDIGO 2024 guideline suggests less than 2 g of sodium a day.
- Protein: the KDIGO 2024 guideline suggests 0.8 g of protein per kg of body weight per day for adults in stages 3–5. It says low- and very-low-protein diets are not prescribed for people who are metabolically unstable, and that protein is not restricted in children because of the risk to growth.
- Hydration and a balanced diet.
- Dialysis:
- Hemodialysis: Filters blood outside the body using a machine.
- Peritoneal dialysis: Uses the lining of the abdomen to filter blood inside the body.
- Kidney transplant: For end-stage kidney disease, a healthy kidney from a donor is transplanted to replace the damaged kidneys.
Natural & Nutritional Support
Medical therapy slows chronic kidney disease; nutrition and targeted micronutrients protect the downstream systems that fail alongside the kidneys. These are adjuncts to conventional care, not substitutes, and every one of them interacts with kidney clearance, especially at stages 3b and beyond. The KDIGO 2024 guideline asks clinicians to review and limit over-the-counter medicines and dietary or herbal remedies that may be harmful for people with chronic kidney disease (Practice Point 4.1.3).
- Vitamin D3: Healthy kidneys convert 25(OH)D to the active hormone 1,25(OH)₂D. In chronic kidney disease this conversion falters, contributing to secondary hyperparathyroidism, bone loss, and immune dysfunction. Supplementation is routinely used in chronic kidney disease under clinician guidance.
- Magnesium: Often low in early chronic kidney disease and important for blood pressure control, vascular calcification resistance, and glucose handling. In advanced chronic kidney disease, however, magnesium can accumulate, and a blood magnesium test is how a build-up is detected.
- Potassium: A double-edged sword. A potassium-rich plant-forward diet lowers blood pressure and protects early-stage kidneys, but in stages 3b–5 the kidneys lose the ability to excrete potassium, and high blood potassium (hyperkalemia) becomes life-threatening. Which side of the double edge applies depends on the stage.
- Turmeric (curcumin): Anti-inflammatory and antifibrotic in animal models of diabetic nephropathy and obstructive uropathy. Early human trials are promising but small; high doses raise a concern of extra bleeding in people taking blood thinners.
- Dietary protein: The KDIGO 2024 guideline suggests 0.8 g/kg/day in adults with stages 3–5, notes that low- or very-low-protein diets are not for metabolically unstable people, and does not restrict protein in children because of the risk to growth. Plant-based protein sources appear gentler on the kidneys than red meat.
- Sodium restriction: The KDIGO 2024 guideline suggests less than 2 g (2,000 mg) of sodium a day — about 5 g of salt (sodium chloride) — for people with chronic kidney disease, and notes that restriction is usually not appropriate for people whose kidneys waste salt (sodium-wasting nephropathy). This single change can lower blood pressure as effectively as adding a second antihypertensive medication.
- Omega-3 fatty acids: Associated with reduced proteinuria and slower progression in immunoglobulin A (IgA) nephropathy trials. Oily fish is the food source.
Prevention and Management Strategies
- Blood pressure and diabetes control to prevent kidney damage.
- Diet: the KDIGO 2024 guideline suggests less than 2 g of sodium a day and, for adults in stages 3–5, 0.8 g of protein per kg of body weight a day (protein is not restricted in children).
- Hydration: staying hydrated and preventing dehydration.
- Nonsteroidal anti-inflammatory drugs (NSAIDs): the KDIGO 2024 guideline lists them among medicines with documented kidney toxicity — they lower kidney filtration by reducing the prostaglandin-dependent blood flow to the kidneys, and can cause allergic kidney inflammation (allergic interstitial nephritis) and nephrotic syndrome — and names acetaminophen (paracetamol) as the alternative pain reliever. It reports that 18–20% of people with stage 3–5 chronic kidney disease receive at least one potentially inappropriate kidney-toxic medicine a year, mainly NSAIDs.
- Not smoking and keeping alcohol moderate.
- Regular check-ups: kidney-function tests for people at risk of kidney disease.
Complications of Kidney Disease
- Fluid retention: Can lead to swelling, high blood pressure, and pulmonary edema.
- Heart disease: Increased risk due to high blood pressure and fluid buildup.
- Anemia: Reduced production of erythropoietin, leading to fewer red blood cells.
- Bone health issues: Imbalances in calcium and phosphorus can lead to bone weakening.
- Electrolyte imbalances: Affecting heart and muscle function.
- Kidney failure: Treated with dialysis or a kidney transplant; the KDIGO 2024 guideline also lists comprehensive conservative care — planned care focused on symptoms and quality of life — as an option for people who choose not to have dialysis or a transplant.
Key Research Papers
- Levey AS, Coresh J. Chronic kidney disease. The Lancet. 2012;379(9811):165-180. — doi:10.1016/S0140-6736(11)60178-5
- Levey AS, Stevens LA, Schmid CH, et al. A new equation to estimate glomerular filtration rate. Annals of Internal Medicine. 2009;150(9):604-612. — doi:10.7326/0003-4819-150-9-200905050-00006
- Jha V, Garcia-Garcia G, Iseki K, et al. Chronic kidney disease: global dimension and perspectives. The Lancet. 2013;382(9888):260-272. — doi:10.1016/s0140-6736(13)60687-x
- Brenner BM, Cooper ME, de Zeeuw D, et al. Effects of losartan on renal and cardiovascular outcomes in patients with type 2 diabetes and nephropathy (RENAAL trial). New England Journal of Medicine. 2001;345(12):861-869. — doi:10.1056/NEJMoa011161
- Lewis EJ, Hunsicker LG, Clarke WR, et al. Renoprotective effect of the angiotensin-receptor antagonist irbesartan in patients with nephropathy due to type 2 diabetes (IDNT trial). New England Journal of Medicine. 2001;345(12):851-860. — doi:10.1056/NEJMoa011303
- Perkovic V, Jardine MJ, Neal B, et al. Canagliflozin and renal outcomes in type 2 diabetes and nephropathy (CREDENCE trial). New England Journal of Medicine. 2019;380(24):2295-2306. — doi:10.1056/NEJMoa1811744
- Heerspink HJL, Stefansson BV, Correa-Rotter R, et al. Dapagliflozin in patients with chronic kidney disease (DAPA-CKD trial). New England Journal of Medicine. 2020;383(15):1436-1446. — doi:10.1056/NEJMoa2024816
- National Kidney Foundation. K/DOQI clinical practice guidelines for chronic kidney disease: evaluation, classification, and stratification. American Journal of Kidney Diseases. 2002;39(2 Suppl 1):S1-266. — Search PubMed
- KDIGO CKD Work Group. KDIGO 2024 clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney International. 2024;105(4S):S117-S314. — doi:10.1016/j.kint.2023.10.018
- GBD Chronic Kidney Disease Collaboration. Global, regional, and national burden of chronic kidney disease, 1990-2017. The Lancet. 2020;395(10225):709-733. Find on PubMed
- Bakris GL, Agarwal R, Anker SD, et al. Effect of finerenone on chronic kidney disease outcomes in type 2 diabetes (FIDELIO-DKD trial). New England Journal of Medicine. 2020;383(23):2219-2229. — doi:10.1056/NEJMoa2025845
- Go AS, Chertow GM, Fan D, et al. Chronic kidney disease and the risks of death, cardiovascular events, and hospitalization. New England Journal of Medicine. 2004;351(13):1296-1305. — doi:10.1056/NEJMoa041031
Historical Background
Richard Bright, a physician at Guy's Hospital in London, first described the connection between kidney disease and protein in the urine in 1827, and chronic kidney disease was long known as "Bright's disease." The development of hemodialysis by Willem Kolff in 1943 in the Netherlands and the first successful kidney transplant by Joseph Murray in 1954 (for which he received the 1990 Nobel Prize) were transformative milestones in nephrology.
PubMed Topic Searches
Explore current literature on chronic kidney disease via PubMed topic searches. These links open live PubMed searches for the listed keywords — results update as new studies are indexed.
- Clinical trials on chronic kidney disease — PubMed search
- Clinical trials on diabetic nephropathy — PubMed search
- Clinical trials on SGLT2 inhibitors kidney — PubMed search
- Clinical trials on CKD progression — PubMed search
- Clinical trials on end-stage renal disease dialysis — PubMed search
- Clinical trials on kidney transplantation — PubMed search
- Clinical trials on KDIGO CKD guidelines — PubMed search
Connections
- Nephrology & Hepatology
- How Your Body Makes Red Blood Cells (EPO) — interactive animation
- Sodium-Glucose Cotransporter-2: Why Diabetes Drugs Make You Pee Sugar — interactive animation
- Blood pH: The Acid–Base Balancing Act — interactive animation
- How Your Body Controls Blood Pressure — interactive animation
- Kidney Nephron — interactive animation
- Pyelonephritis (Kidney Infection)
- Deep Dives: Estimated Glomerular Filtration Rate & Staging · Kidney-Friendly Diet · Slowing Progression · Diabetic Kidney Disease · Dialysis & Transplant · History & Discovery
- Beans for Kidney Health
- Glomerulonephritis
- Acute Kidney Injury
- Nephrotic Syndrome
- Diabetes
- Hypertension
- Potassium
- Magnesium
- Vitamin D3
- Comprehensive Metabolic Panel
- Estimated Glomerular Filtration Rate
- Creatinine
- Kidney Function Tests
- Anemia
- Osteoporosis
- Turmeric
- Lupus
- Edema
- Lead
- Kidney Cancer
- Diabetic Retinopathy
- Polycystic Kidney Disease
- Herbs covered on this site that discuss this condition: Cat’s Whiskers / Java Tea (Orthosiphon aristatus) · Sorrel · Uva Ursi · Astragalus (Astragalus membranaceus) · Houttuynia cordata (Fish Mint) · Noni (Morinda citrifolia)
- Cystatin C
- Kidney Stones