BNP and NT-proBNP: Cardiac Biomarker Guide
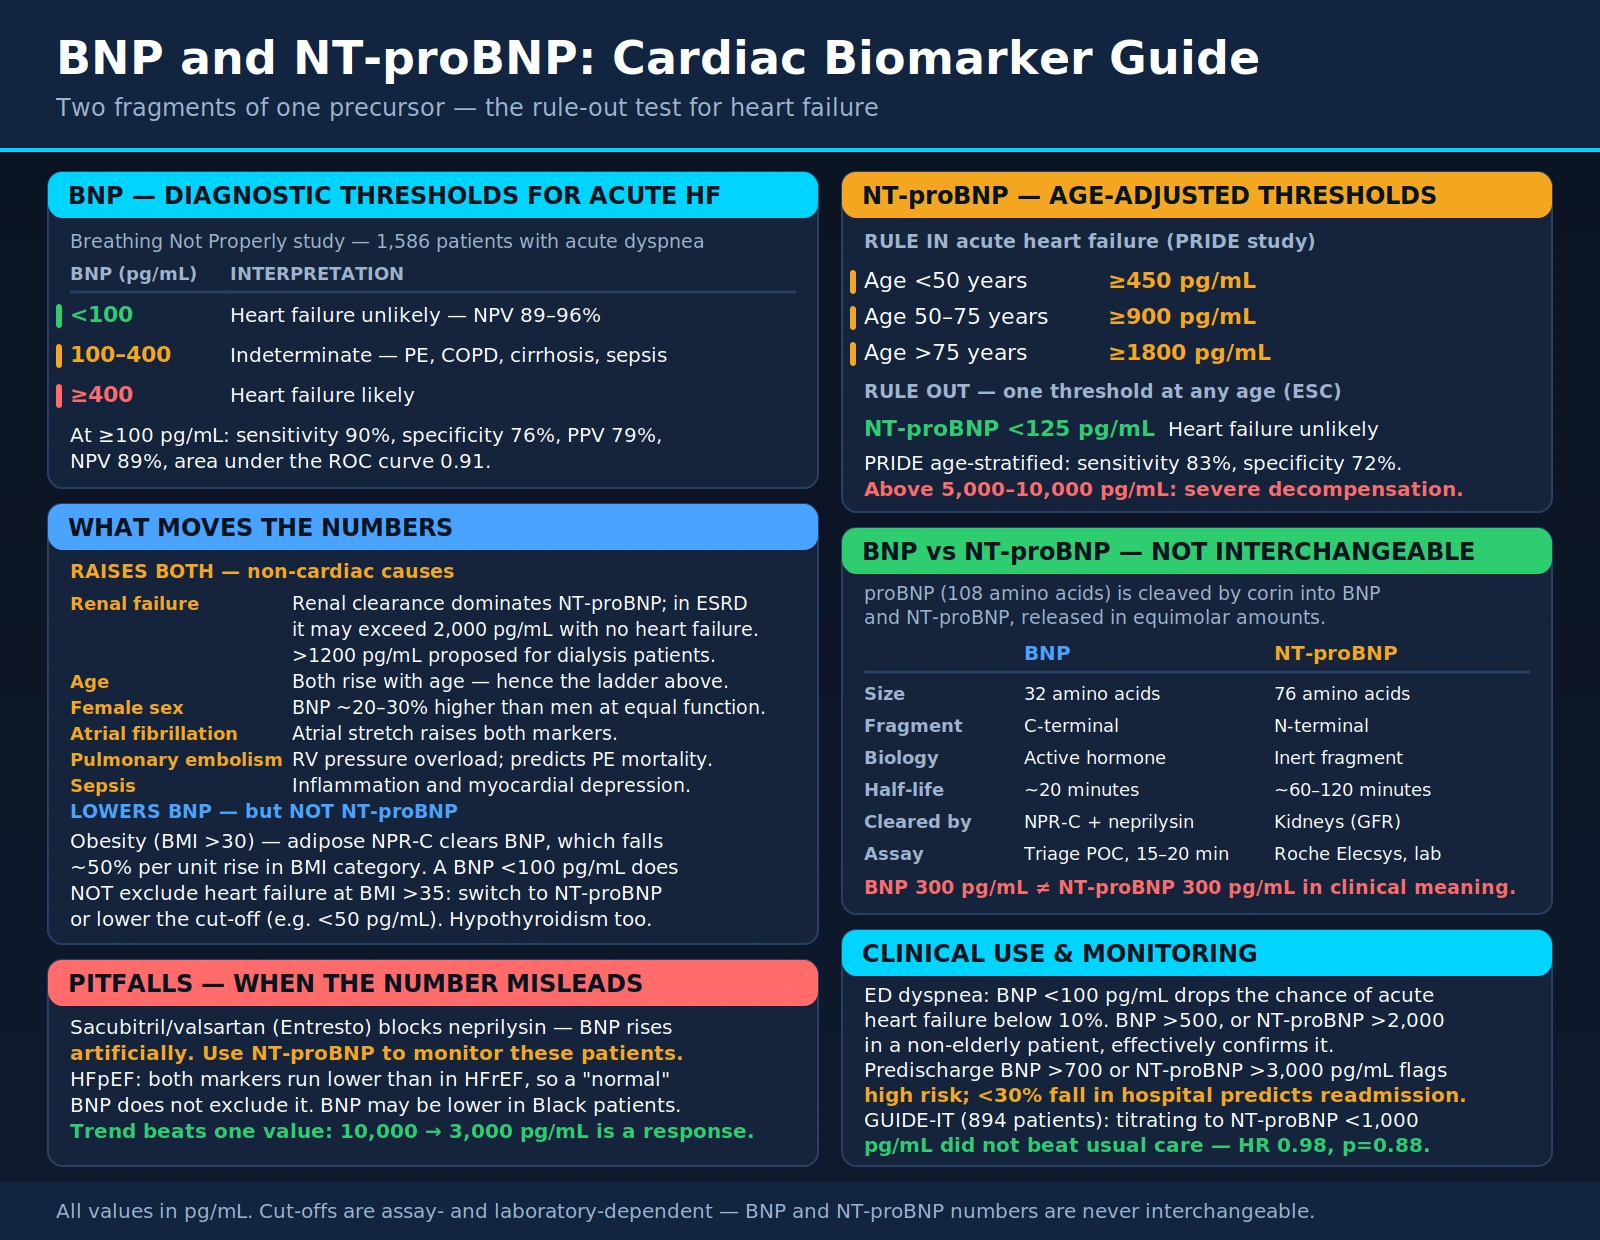
BNP (B-type natriuretic peptide) and NT-proBNP are cardiac biomarkers secreted by the heart in response to increased ventricular wall stress and volume overload. They are widely used blood tests in the evaluation of suspected acute heart failure in the emergency department, in estimating prognosis, and in the long-term follow-up of people with established heart failure. In the Breathing Not Properly study, a BNP below 100 pg/mL made heart failure an unlikely cause of breathlessness, and higher levels made it progressively more likely. The two tests differ in half-life, in how they respond to some drugs, and in their diagnostic cut-points, and two well-documented sources of misleading results are kidney disease (higher levels) and obesity (lower levels). Reference ranges and cut-points depend on the assay and the laboratory; the figures on this page are the ones the cited studies and guidelines report.
Interactive Visualization The Heart & Circulation — watch a blood cell make the loop Trace a blood cell through all four chambers and both circuits, with a live ECG, chamber pressures, and an exercise mode. Launch →Table of Contents
- What are BNP and NT-proBNP?
- Biology: How and Why They Are Released
- BNP Diagnostic Thresholds
- NT-proBNP Age-Adjusted Thresholds
- BNP vs NT-proBNP: Key Differences
- Diagnosing Acute Heart Failure in the Emergency Department
- Factors That Affect Levels
- When BNP Is Falsely Low
- Clinical Uses: Diagnosis and Monitoring
- Prognostic Value and Serial Monitoring
- Biomarker-Guided Therapy and the GUIDE-IT Trial
- Interpreting Results in Kidney Disease
- Interpretation Pitfalls
- Key Research Papers
- Connections
- Featured Videos
What are BNP and NT-proBNP?
BNP (B-type natriuretic peptide) and NT-proBNP (N-terminal pro-B-type natriuretic peptide) are cardiac biomarkers released by the heart when it is under mechanical stress — specifically when the ventricles experience elevated wall tension due to pressure or volume overload. Both are derived from the same precursor molecule (proBNP), and both are measured from a routine blood draw. Guidelines and expert guidance list them among the core tests in the evaluation of suspected heart failure, particularly in the emergency setting when a patient presents with acute dyspnea.
BNP was first isolated from porcine brain tissue in 1988 (Sudoh and colleagues, as a 26-amino-acid peptide) — which is where the original name "brain natriuretic peptide" came from. The name is a historical misnomer: in humans the dominant source is the ventricular cardiomyocyte, not the brain. The designation was later revised to "B-type" to distinguish it from ANP (A-type natriuretic peptide), which is secreted mainly by the atria. When ventricular walls are stretched by increased pressure or volume — as happens in heart failure, cardiomyopathy, severe valve disease, or pulmonary hypertension — ventricular cells step up transcription of the BNP gene.
Functionally, BNP is the heart's own distress signal: it relaxes blood vessels, promotes sodium and water excretion, suppresses the renin-angiotensin-aldosterone system, and damps down sympathetic activation. In other words, BNP is the heart trying to reduce its own workload. Measured levels track cardiac wall stress, including in people whose physical signs, such as edema or a third heart sound, are absent or equivocal.
First characterized in the 1980s and 1990s and adopted into routine practice in the early 2000s, natriuretic peptides transformed the evaluation of shortness of breath. Before their adoption, distinguishing cardiac from pulmonary causes of dyspnea relied on clinical judgment, chest X-ray, and echocardiography. In the Breathing Not Properly study, adding BNP to emergency physicians' clinical judgment raised diagnostic accuracy from 74% to 81%.
Biology: How and Why They Are Released
The natriuretic peptide system is a counter-regulatory mechanism against volume and pressure overload:
- Stimulus: Increased wall stress (from elevated filling pressures, volume overload, or myocardial injury) triggers ventricular myocytes — primarily in the left ventricle, with smaller contributions from the right ventricle and atria — to transcribe the NPPB gene (chromosome 1p36). The initial product, preproBNP-134, is processed to proBNP (108 amino acids).
- Cleavage: The proprotein convertases furin and corin (laboratory work identifies both as candidate enzymes, each yielding slightly different BNP forms) cleave proBNP into two fragments: the biologically active BNP-32 (32 amino acids; C-terminal) and the biologically inactive NT-proBNP (76 amino acids; N-terminal). Both fragments are released into the circulation in equimolar amounts, and some uncleaved proBNP also circulates.
- Biological effects of BNP: BNP-32 binds natriuretic peptide receptor A (NPR-A) on vascular smooth muscle and renal tubular cells, producing natriuresis (sodium and water excretion), vasodilation (reduced preload and afterload), suppression of the renin-angiotensin-aldosterone system (RAAS), and inhibition of sympathetic nervous system activation. These effects partially counteract the maladaptive neurohormonal activation of heart failure.
- Clearance: BNP is cleared by natriuretic peptide clearance receptor C (NPR-C), which internalizes and degrades it, and by enzymatic cleavage by neprilysin (neutral endopeptidase). NT-proBNP has no known clearance receptor and is not a neprilysin substrate. Both peptides are partly cleared by the kidneys: in a study that sampled renal arteries and veins in 165 hypertensive people, the kidneys extracted BNP and NT-proBNP to a similar degree, which the authors described as contrary to widespread belief that NT-proBNP depends more on renal clearance.
The clearance differences matter in two ways: both peptides rise as kidney function falls (the cut-points studied in kidney disease are covered below), and because BNP is a neprilysin substrate, its levels rise when neprilysin is inhibited by sacubitril, while NT-proBNP's do not.
Stimulus-Response Kinetics
BNP production responds to changes in wall stress, and levels fall when the hemodynamic burden is relieved, for example after diuresis, which is why serial measurements are studied as a way to track treatment response. A draw taken very early in a sudden-onset event may precede the full rise. NT-proBNP, with its longer half-life, changes more slowly than BNP.
BNP Diagnostic Thresholds
BNP thresholds for acute heart failure (AHF) diagnosis come mainly from the Breathing Not Properly Multinational Study (Maisel et al., 2002), which enrolled 1,586 emergency patients with acute dyspnea at seven centers and used a 100 pg/mL cut-point. The 100–400 pg/mL "gray zone" and the 400 pg/mL rule-in level shown below come from later expert consensus documents rather than from that single study.
The Three-Zone BNP Interpretation Scheme
| BNP Level | Interpretation | What It Reflects |
|---|---|---|
| <100 pg/mL | Heart failure unlikely | A non-cardiac cause of dyspnea is more likely |
| 100–400 pg/mL | Gray zone — indeterminate | Heart failure possible; other cardiac conditions, pulmonary embolism and kidney disease also raise BNP into this range |
| >400 pg/mL | Heart failure likely | Heart failure the more likely cause; echocardiography is used to characterize it |
- BNP <100 pg/mL: Heart failure unlikely. In Breathing Not Properly, the 96% negative predictive value applied to levels below 50 pg/mL (see the note below).
- BNP 100–400 pg/mL: Indeterminate zone — heart failure possible, and other causes also raise BNP into this range (acute cor pulmonale from pulmonary embolism, COPD exacerbation with right heart strain, cirrhosis, sepsis).
- BNP ≥400 pg/mL: Heart failure likely.
- BNP ≥100 pg/mL (primary threshold): Overall diagnostic accuracy 83.4% in the main report. A companion analysis of 1,538 participants reported 90% sensitivity and 73% specificity at this cut-point, compared with 49% sensitivity and 96% specificity for the emergency physician's judgment at 80% certainty.
A note on the widely quoted "96% negative predictive value": in the Breathing Not Properly paper that figure belongs to BNP levels below 50 pg/mL, not below 100 pg/mL. At the 100 pg/mL cut-point the abstract reports an overall diagnostic accuracy of 83.4%. The figures describe different operating points, and quoting 96% for the 100 pg/mL threshold overstates how safely that value excludes heart failure.
For ruling out heart failure in acute breathlessness, BNP <100 pg/mL is the cut-point the 2021 European Society of Cardiology (ESC) heart failure guideline lists, because of its high sensitivity. Higher thresholds trade sensitivity for specificity when the question is ruling in.
NT-proBNP Age-Adjusted Thresholds
NT-proBNP thresholds are more complex because NT-proBNP levels increase with age even in healthy individuals (due to declining GFR and increased ventricular stiffness). The PRIDE study established the first two age tiers in a single-center cohort of 600 dyspneic patients, and the International Collaborative of NT-proBNP (ICON) pooled analysis of 1,256 patients from four sites on three continents identified the three age-specific cut-points below, adding a tier for people over 75.
Age-Stratified Cut-Points for Acute Heart Failure
| Age Group | Rule-In Threshold (HF Likely) | Rule-Out Threshold (HF Unlikely) |
|---|---|---|
| Under 50 years | 450 pg/mL | <300 pg/mL |
| 50–75 years | 900 pg/mL | <300 pg/mL |
| Over 75 years | 1,800 pg/mL | <300 pg/mL |
Used together, the three rule-in cut-points yielded 90% sensitivity and 84% specificity for acute heart failure in the ICON analysis. The rule-in values climb with age because NT-proBNP is higher in older people even without heart failure; declining kidney function and age-related cardiac changes are the usual explanations offered.
Rule-Out Thresholds
- Acute setting — NT-proBNP <300 pg/mL: A single age-independent threshold. In ICON it carried a 98% negative predictive value for excluding acute heart failure; in PRIDE the negative predictive value was 99%. The ICON authors described it as age-independent.
- Non-acute / outpatient setting — NT-proBNP <125 pg/mL (BNP <35 pg/mL): The 2021 ESC guideline lists these lower values when heart failure is suspected in a stable ambulatory patient rather than an acutely breathless one; the 2019 Heart Failure Association guidance explains that chronic heart failure with exertional symptoms involves smaller rises in filling pressure than acute heart failure.
These two numbers are not in conflict — they answer different questions. The 300 pg/mL value was studied in acutely breathless emergency patients; the 125 pg/mL value is the guideline cut-point for stable outpatients being evaluated for chronic heart failure.
In ICON, NT-proBNP levels correlated with heart failure symptom severity, and among patients with acute heart failure a presenting NT-proBNP above 5,180 pg/mL was strongly predictive of death by 76 days (odds ratio 5.2).
Obesity Adjustment
Both BNP and NT-proBNP run lower in obese patients with heart failure (shown for both markers in a PRIDE substudy of 204 patients with acute heart failure), so standard cut-points lose sensitivity. The 2019 Heart Failure Association guidance describes cut-offs about 50% lower in obese patients. The Breathing Not Properly obesity analysis (Daniels et al., 2006) recalculated the BNP cut-point needed to preserve 90% sensitivity across body-mass strata:
- Lean patients: 170 pg/mL (a higher cut-point can be used here to gain specificity).
- Overweight and obese patients: 110 pg/mL.
- Severely or morbidly obese patients: 54 pg/mL.
These findings mean a "normal" BNP in a severely obese, breathless patient carries less reassurance than the same value in a lean patient. Mean BNP among patients with confirmed acute heart failure fell from 643 pg/mL in lean patients to 462 in the overweight/obese group and 247 in the severely/morbidly obese group in that same analysis.
BNP vs NT-proBNP: Key Differences
Comparison of Key Properties
| Property | BNP | NT-proBNP |
|---|---|---|
| Biological activity | Active hormone (vasodilatory, natriuretic) | Inactive fragment |
| Plasma half-life | ~20 minutes (commonly cited) | ~60–120 minutes (commonly cited) |
| Clearance route | NPR-C receptor, neprilysin, and the kidneys | Mainly passive routes including the kidneys; not neprilysin |
| Effect of sacubitril/valsartan | Rises, often modestly, early in treatment (neprilysin inhibited) | Not a neprilysin substrate; falls on treatment in PARADIGM-HF |
| Effect of CKD/ESRD | Elevated; studied cut-points rise as eGFR falls | Elevated; a higher cut-point (1,200 pg/mL) was studied below eGFR 60 |
| Effect of obesity | Lower; a 54 pg/mL cut-point kept 90% sensitivity in severe obesity | Also lower |
| Rule-out cut-off | 100 pg/mL acute; 35 pg/mL non-acute | 300 pg/mL acute; 125 pg/mL non-acute |
| Rule-in cut-off | 400 pg/mL | Age-stratified (450 / 900 / 1,800 pg/mL) |
| Stability in sample | Generally described as less stable | Generally described as more stable |
Biological Activity
- BNP: Biologically active hormone; exerts natriuretic, vasodilatory, and neurohumoral effects.
- NT-proBNP: Biologically inert fragment released alongside BNP.
Half-Life
- BNP: commonly cited as about 20 minutes, so levels change comparatively quickly with hemodynamic changes or treatment.
- NT-proBNP: commonly cited as about 60–120 minutes, so levels change more slowly. Its longer survival in the circulation is the usual explanation for its higher absolute concentrations than BNP in the same patient.
Effect of Neprilysin Inhibition (Sacubitril/Valsartan)
Sacubitril/valsartan, an angiotensin receptor–neprilysin inhibitor (ARNI) used in heart failure with reduced ejection fraction (HFrEF), inhibits neprilysin, one of the clearance pathways for BNP. In a PARADIGM-HF analysis, median BNP rose from 202 to 235 pg/mL after 8 to 10 weeks of treatment; BNP doubled in 18% of patients, while comparable rises in NT-proBNP were extremely rare. In the main PARADIGM-HF trial, NT-proBNP fell early and stayed lower with sacubitril/valsartan than with enalapril.
The PARADIGM-HF authors concluded that NT-proBNP, which is not a neprilysin substrate, may cause less confusion when measured within 8 to 10 weeks of starting the drug, and that during treatment both BNP and NT-proBNP still predicted major adverse outcomes, with similar accuracy.
Assay Availability
- BNP: Measured by laboratory immunoassays and by point-of-care devices; the Breathing Not Properly study used a bedside assay.
- NT-proBNP: Measured by laboratory immunoassays. Results and reference ranges differ between manufacturers' assays, which is one reason cut-points are laboratory-dependent.
Choosing Between the Tests: What the Evidence Shows
The 2019 Heart Failure Association guidance describes BNP, NT-proBNP and MR-proANP as having comparable diagnostic and prognostic accuracy. The two tests are not interchangeable numerically — a BNP of 300 pg/mL and an NT-proBNP of 300 pg/mL mean very different things — so a trend is only interpretable when the same test is used throughout. Early after starting sacubitril/valsartan, BNP can rise because of the drug itself (see above). In advanced kidney disease both tests are elevated.
Diagnosing Acute Heart Failure in the Emergency Department
The landmark application of natriuretic peptide testing was the emergency evaluation of acute breathlessness. In the Breathing Not Properly Multinational Study, BNP measurement was more accurate on its own than any single item of history, physical examination, or routine laboratory testing for identifying heart failure as the cause of dyspnea, and it added significant independent predictive power to other clinical variables.
Differential Diagnosis of Dyspnea: Where BNP Fits
Acute dyspnea has a broad differential: acute decompensated heart failure (ADHF), COPD exacerbation, asthma, pneumonia, pulmonary embolism, anemia, and anxiety. In the studies above, the natriuretic peptide result shifted the probability toward or away from a cardiac cause:
- BNP <100 pg/mL: Heart failure is unlikely as the cause; pulmonary, thromboembolic, hematologic, or other causes become more likely.
- BNP 100–400 pg/mL: Indeterminate. Could reflect mild or treated heart failure, heart failure with preserved ejection fraction, right heart strain from pulmonary embolism, cor pulmonale, or a non-cardiac cause of elevation. Echocardiography is the imaging test used to sort these out.
- BNP >400 pg/mL: ADHF is the more likely diagnosis. The 2019 Heart Failure Association guidance notes that natriuretic peptides cannot identify the underlying cause of heart failure, so an elevated value is interpreted together with cardiac imaging.
Heart Failure with Preserved Ejection Fraction (HFpEF)
HFpEF (heart failure with an ejection fraction of 50% or more) is diagnostically awkward because the ejection fraction is normal on echocardiogram. In a PRIDE analysis of 153 patients with acute heart failure, median levels were lower with preserved than with reduced ejection fraction (NT-proBNP 2,849 vs 6,196 pg/mL; BNP 259 vs 592 pg/mL). With optimal cut-points, BNP was falsely negative in 20% of the preserved-ejection-fraction patients versus 9% for NT-proBNP, and the authors concluded that NT-proBNP appeared superior to BNP in this group.
Acute Flash Pulmonary Edema — A Special Case
In acute severe mitral regurgitation — ruptured chordae tendineae, or papillary muscle rupture complicating a myocardial infarction — flash pulmonary edema can develop within minutes. Reviews describe natriuretic peptide levels as possibly lower than expected very early in such sudden-onset presentations, before peptide production has caught up with the rise in wall stress; precise timing data for this situation are limited.
Factors That Affect Levels
An elevated natriuretic peptide is not synonymous with heart failure. Many conditions raise BNP and NT-proBNP through ventricular wall stress, impaired clearance, or inflammatory cytokine-driven upregulation of the BNP gene — and several non-disease factors shift the baseline.
Cardiac Conditions Other Than Heart Failure
- Atrial fibrillation: Atrial stretch and rapid ventricular rate elevate both markers even without structural heart disease. The 2019 Heart Failure Association guidance notes that natriuretic peptides also carry prognostic information in atrial fibrillation.
- Acute myocardial infarction: Myocardial injury and the resulting wall-motion abnormalities raise BNP, and levels after infarction carry prognostic information for death and heart failure hospitalization (2019 Heart Failure Association guidance).
- Myocarditis: Inflammatory injury to cardiomyocytes produces an acute rise that mirrors the degree of ventricular dysfunction.
- Hypertrophic cardiomyopathy: Chronically elevated filling pressures and outflow tract obstruction raise BNP.
- Constrictive pericarditis (often lower than expected): In a small study of 11 patients with similar intracardiac pressures, mean BNP was 128 pg/mL in constrictive pericarditis versus 826 pg/mL in restrictive cardiomyopathy, so constriction tends to produce lower values than its pressures would suggest.
Pulmonary and Vascular Conditions
- Pulmonary embolism: Acute right ventricular strain from PE elevates BNP. In a study of 73 consecutive patients with acute PE, median BNP was 194 pg/mL in those with an adverse in-hospital course (death, resuscitation, ventilation, pressors, thrombolysis or clot removal) versus 39 pg/mL in those without; a BNP below 90 pg/mL had a 93% negative predictive value for an adverse course, though three patients with adverse outcomes had low values. PE is one of the non-heart-failure causes of a raised result in the emergency dyspnea workup.
- Pulmonary arterial hypertension: Chronic right heart pressure overload produces persistent elevation.
- ARDS: Severe acute lung injury with hypoxia causes right ventricular stress and cytokine-mediated release.
- High-altitude exposure: Hypoxic pulmonary vasoconstriction raises right ventricular afterload, elevating BNP at high altitude.
Systemic and Renal Conditions
- Renal failure (CKD/ESRD): Both NT-proBNP and BNP rise as GFR falls; in the renal-clearance study described above, the two peptides were equally dependent on kidney function for their clearance. In PRIDE, a higher NT-proBNP cut-point of 1,200 pg/mL was studied for patients with eGFR below 60 mL/min/1.73 m², and in Breathing Not Properly the optimal BNP cut-point also rose as eGFR fell (details in the kidney section below).
- Sepsis and critical illness: Septic cardiomyopathy and the inflammatory cytokine surge of critical illness raise natriuretic peptides; the 2019 Heart Failure Association guidance notes that in shock the result cannot distinguish cardiogenic from septic causes, although it remains prognostic.
- Thyrotoxicosis: Excess thyroid hormone raises cardiac output and heart rate, loading the ventricles and elevating BNP. Hypothyroidism can push levels the other way.
- Liver cirrhosis with ascites: Portal hypertension with splanchnic vasodilation increases effective cardiac output and wall stress.
Demographic Factors
- Age: Both biomarkers increase with age; the age-adjusted NT-proBNP thresholds above exist precisely to handle this.
- Female sex: Women have higher natriuretic peptide levels than men. In 4,056 adults from the Framingham Third-Generation cohort, NT-proBNP was lower with higher free testosterone in both sexes, and women taking hormonal contraceptives had higher NT-proBNP than women not taking hormone therapy; the authors concluded that lower androgen levels and exogenous female hormones contribute to the sex difference.
- Race and ethnicity: In the Dallas Heart Study (3,148 people free of cardiovascular disease), Black participants had NT-proBNP levels 39% lower than White participants after adjustment for clinical factors and MRI measures of cardiac structure and function; Hispanic and White participants did not differ. The mechanism is incompletely understood.
In the general population, natriuretic peptides are related to subclinical heart disease, but only loosely: the Framingham Heart Study analysis by Vasan and colleagues (3,177 participants) found that BNP and NT-ANP performed suboptimally at detecting left ventricular hypertrophy or systolic dysfunction (areas under the ROC curve at or below 0.75), and the authors concluded the peptides had limited usefulness as mass screening tools.
When BNP Is Falsely Low
Recognizing false positives matters, but the more dangerous error is a falsely reassuring result — a value below the diagnostic threshold in a patient who genuinely has heart failure.
Obesity — the Most Important Pitfall
Obesity is a well-documented cause of a falsely low BNP. Mehra and colleagues studied 318 patients with heart failure and found mean BNP of 205 pg/mL in obese patients versus 335 pg/mL in non-obese patients despite similar heart failure severity, with body-mass index an independent negative correlate of BNP. Proposed mechanisms include clearance of BNP by NPR-C receptors in fat tissue and reduced secretion; the PRIDE substudy found NT-proBNP (which does not use NPR-C) was lower too, which its authors read as a body-mass-related defect in secretion. In that substudy, BNP at 100 pg/mL was falsely negative in 20% of overweight and obese patients with heart failure, while NT-proBNP at 900 pg/mL was falsely negative in up to 10% of overweight and 15% of obese patients. The body-mass-adjusted BNP cut-points studied are listed above.
Early or Compensated Heart Failure
Patients with mild, stable, well-compensated chronic heart failure on treatment — particularly RAAS inhibitors and beta-blockers — may sit below 100 pg/mL while hemodynamically stable. This is not really a false negative. BNP reports real-time wall stress; when therapy is working, wall stress is low and BNP falls toward normal even though the underlying structural disease persists. It does mean a single normal value cannot be used to say a patient never had heart failure.
Flash Pulmonary Edema from Acute Valvular Catastrophe
As above: in sudden severe mitral or aortic regurgitation, a very early measurement may be lower than the severity of the event would suggest.
Patients on Sacubitril/Valsartan
Sacubitril inhibits neprilysin and therefore raises BNP early in treatment, a rise driven by the drug rather than by worsening heart failure. NT-proBNP, which neprilysin does not degrade, fell on sacubitril/valsartan in PARADIGM-HF. This is not a false low in the strict sense, but it is the same problem in reverse: early in ARNI treatment a BNP value can be higher than the patient's wall stress alone would produce. In the PARADIGM-HF analysis, rises in either BNP or NT-proBNP over 8 to 10 weeks were still associated with worse outcomes.
Clinical Uses: Diagnosis and Monitoring
1. Acute Dyspnea — Emergency Department Diagnosis
The main studied use. In emergency patients with shortness of breath, BNP or NT-proBNP shifts the probability of acute heart failure: low values (BNP <100 pg/mL, NT-proBNP <300 pg/mL) make it unlikely, and the 2019 Heart Failure Association guidance states that the higher the level, the higher the likelihood that dyspnea is caused by heart failure. The same guidance stresses that natriuretic peptides are interpreted together with all other clinical information.
2. Prognostication in Established Heart Failure
Persistently elevated or rising natriuretic peptides predict adverse outcomes (hospitalization, death). In one French study, a predischarge BNP above 700 pg/mL identified patients at much higher risk of death or readmission within six months (details below).
3. Guiding GDMT Titration
Guideline-directed medical therapy (GDMT) for HFrEF lowers natriuretic peptides over weeks to months; in the single-group PROVE-HF study of 794 patients starting sacubitril/valsartan, median NT-proBNP fell from 816 to 455 pg/mL over 12 months, and the fall correlated weakly with improvements in heart size and function. Trials that titrated therapy to a target used NT-proBNP ≤1,000 pg/mL (PROTECT) or <1,000 pg/mL (GUIDE-IT); their mixed results are described in the next sections.
4. Screening for Asymptomatic LV Dysfunction
The 2019 Heart Failure Association guidance describes natriuretic peptide screening of people with cardiovascular risk factors as a way that may identify those at increased risk. In the STOP-HF trial (1,374 people with cardiovascular risk factors in Irish primary care, mean follow-up 4.2 years), participants with a BNP of 50 pg/mL or higher received echocardiography and collaborative cardiology care. The primary endpoint, left ventricular dysfunction with or without heart failure, occurred in 5.3% of the screened group versus 8.7% of usual care (odds ratio 0.55); heart failure alone occurred in 1.0% versus 2.1%, a difference that was not statistically significant (P = .12), and emergency hospitalizations for major cardiovascular events were lower with screening. In the PONTIAC trial, 300 people with type 2 diabetes, no cardiac disease and NT-proBNP above 125 pg/mL were randomized; intensified up-titration of RAS antagonists and beta-blockers at a cardiac clinic reduced hospitalization or death from cardiac disease at 2 years (hazard ratio 0.35). For unselected community screening, the Framingham analysis by Vasan and colleagues found natriuretic peptides performed suboptimally at detecting left ventricular hypertrophy or systolic dysfunction.
Prognostic Value and Serial Monitoring
BNP and NT-proBNP carry strong prognostic information. The 2019 Heart Failure Association guidance describes high prognostic accuracy for death and heart failure hospitalization, and higher levels at admission for acute decompensated heart failure have been associated with outcomes such as:
- Higher short-term mortality (death by 76 days in ICON; 60-day mortality in PRIDE)
- Higher risk of heart failure re-hospitalization
- A more severe course overall
Predischarge BNP and Readmission Risk
Logeart and colleagues followed two consecutive cohorts of patients admitted for decompensated heart failure (105 and 97 survivors) for six months. Predischarge BNP had the best discriminative power for death or readmission (area under the ROC curve 0.80 and 0.83) and was the only significant variable in multivariate analysis; clinical variables and left ventricular ejection fraction were poorly predictive. Compared with a predischarge BNP below 350 pg/mL, adjusted hazard ratios were 5.1 for 350–700 pg/mL and 15.2 for above 700 pg/mL.
Trend Beats Absolute Value
Studies of serial measurement point the same way: the direction of change carries information that a single value does not. In a GUIDE-IT analysis, patients whose NT-proBNP fell to 1,000 pg/mL or less by 90 days had better outcomes regardless of how high their starting level was, and in the PARADIGM-HF analysis rising levels over 8 to 10 weeks were associated with worse outcomes.
Biomarker-Guided Therapy and the GUIDE-IT Trial
A natural question follows from the prognostic data: if a high natriuretic peptide predicts bad outcomes, does treating to a target level improve them? Several trials have tested titrating heart failure therapy against an NT-proBNP goal versus usual clinically guided care, with mixed results.
The Earlier Guided-Therapy Trials
- Troughton et al., 2000 (Christchurch pilot): An early proof-of-concept trial in 69 patients with impaired systolic function. Titrating therapy against plasma N-BNP concentrations reduced total cardiovascular events compared with intensive clinically guided treatment (19 vs 54 events, p=0.02). Small and single-center.
- PRIMA (Eurlings et al., 2010): Managed chronic heart failure against each patient's own individually-set NT-proBNP target. In 345 patients, the primary endpoint — days alive outside hospital — did not differ significantly from clinically guided care (685 vs 664 days, p=0.49).
- SIGNAL-HF (Persson et al., 2010): Tested NT-proBNP-guided management in 252 patients in Swedish primary care. Doses of beta-blockers and RAAS blockers were pushed toward target in both arms, and the composite primary endpoint showed no significant difference (p=0.28). The authors concluded that NT-proBNP guidance did not add important improvements beyond what education and structured guideline-based treatment achieved.
- PROTECT (Januzzi et al., 2011): A single-center trial of 151 patients with heart failure from LV systolic dysfunction, randomized to standard care versus standard care plus a goal of reducing NT-proBNP to ≤1,000 pg/mL. Total cardiovascular events were significantly lower in the NT-proBNP arm — 58 versus 100 events (p=0.009; logistic odds for events 0.44) — with better quality of life and more favorable left ventricular remodeling.
GUIDE-IT — The Largest Trial
The GUIDE-IT trial (Guiding Evidence-Based Therapy Using Biomarker Intensified Treatment in Heart Failure) was the large multicenter test of the strategy. It planned to randomize 1,100 patients with HFrEF (EF ≤40%), recent elevated natriuretic peptides, and a prior heart failure event across 45 sites in the United States and Canada, to:
- NT-proBNP-guided therapy: Titration of GDMT targeting NT-proBNP <1,000 pg/mL.
- Usual care: Guideline-based management with emphasis on titrating proven neurohormonal therapies, without specific biomarker targets.
Primary finding: The data and safety monitoring board stopped the trial for futility after 894 patients had been enrolled and followed for a median of 15 months. The primary composite endpoint of time-to-first heart failure hospitalization or cardiovascular death occurred in 164 patients (37%) in each arm (adjusted HR 0.98, 95% CI 0.79–1.22; p=0.88). No secondary endpoint differed, and the reduction in NT-proBNP over time was similar in both groups.
Interpretation: Biomarker-guided titration did not outperform usual care when both arms received GDMT intensification. The trial does not negate the prognostic value of NT-proBNP: in a later GUIDE-IT analysis of 638 participants, 31% reached NT-proBNP ≤1,000 pg/mL by 90 days, equally often in both arms, and they had a lower adjusted hazard of heart failure hospitalization or cardiovascular death (hazard ratio 0.26) and of all-cause death (0.34). The authors suggested this helps explain the main result: the NT-proBNP fall tracked response to therapy in both arms.
Where the Guidelines Landed
The 2022 AHA/ACC/HFSA heart failure guideline recommends natriuretic peptide measurement to support the diagnosis or exclusion of heart failure and to establish prognosis, and the 2021 ESC guideline lists the rule-out cut-points given on this page. After GUIDE-IT, titrating therapy to a natriuretic peptide target is not established as a way to reduce hospitalization or death: the test is well established for diagnosis and risk stratification, and less so as a treatment target.
Interpreting Results in Kidney Disease
Kidney disease is a common reason for a natriuretic peptide to be elevated in a patient who is not in heart failure, and it is a frequent source of misinterpretation.
The Breathing Not Properly renal sub-analysis (McCullough et al., 2003) stratified 1,452 dyspneic patients by estimated GFR and showed that the optimal BNP cut-point climbs as kidney function falls — approximately 70 pg/mL at eGFR ≥90, 104 pg/mL at eGFR 60–89, 201 pg/mL at eGFR 30–59, and 225 pg/mL at eGFR <30 mL/min/1.73 m². Discrimination remained good throughout (area under the ROC curve 0.81–0.91), which is the important point: BNP does not stop working in CKD, it simply needs a higher bar. The correlation between BNP and eGFR is real but weak, so renal impairment alone does not account for a markedly elevated value.
For NT-proBNP, the PRIDE renal analysis (Anwaruddin et al., 2006) found that the standard age-based cut-points of 450 and 900 pg/mL performed well (85% sensitivity, 88% specificity) in patients with eGFR ≥60, but that a substantially higher cut-point of 1,200 pg/mL was needed once eGFR fell below 60 mL/min/1.73 m² (89% sensitivity, 72% specificity). Even so, NT-proBNP remained the strongest independent predictor of 60-day mortality in that cohort, including among the patients with reduced GFR, and the authors concluded the test was valuable irrespective of renal function. Neither study included dialysis patients (Breathing Not Properly excluded eGFR below 15 and dialysis; PRIDE's lowest GFR was 15), so these cut-points do not describe dialysis-dependent patients. A renal-vein sampling study found that the kidneys clear BNP and NT-proBNP to a similar degree.
Interpretation Pitfalls
- Obesity and low BNP: BNP <100 pg/mL excludes heart failure less reliably in obesity; in Breathing Not Properly, a cut-point of 54 pg/mL was needed to keep 90% sensitivity in severe obesity, and NT-proBNP is lowered too.
- Sacubitril/valsartan and BNP: BNP can rise early in treatment because of the drug itself; NT-proBNP is not affected this way. Both still predicted outcomes during treatment in PARADIGM-HF.
- Kidney disease: Both BNP and NT-proBNP rise as eGFR falls. The studied cut-points rise too (NT-proBNP 1,200 pg/mL below eGFR 60 in PRIDE; BNP about 200 pg/mL below eGFR 60 in Breathing Not Properly).
- Race/ethnicity: NT-proBNP levels were lower in Black than White participants in the Dallas Heart Study; the mechanism is incompletely understood.
- Preserved vs reduced EF: Both BNP and NT-proBNP were lower in HFpEF than HFrEF in PRIDE, and BNP was falsely negative in 20% of the HFpEF patients — so a BNP within the "normal" range excludes HFpEF less reliably.
- Very early presentation: In flash pulmonary edema from an acute valvular catastrophe, a very early value may be lower than expected.
- Mixing assays: A BNP value and an NT-proBNP value are on different scales, so a trend built from both tests, or from different manufacturers' assays, is not interpretable.
- Single values versus trends: Studies of serial measurement (GUIDE-IT, PARADIGM-HF) found that the direction of change carries prognostic information beyond a single value, and expert guidance stresses reading any value with the clinical context.
Key Research Papers
The peer-reviewed studies below established the diagnostic, prognostic, and treatment-guiding roles of BNP and NT-proBNP. Every PMID has been checked against PubMed (2026-10-13).
- Maisel AS, Krishnaswamy P, Nowak RM, et al. Rapid measurement of B-type natriuretic peptide in the emergency diagnosis of heart failure. N Engl J Med. 2002;347(3):161–167. — PubMed PMID: 12124404
- Januzzi JL Jr, Camargo CA, Anwaruddin S, et al. The N-terminal Pro-BNP investigation of dyspnea in the emergency department (PRIDE) study. Am J Cardiol. 2005;95(8):948–954. — PubMed PMID: 15820160
- Januzzi JL, van Kimmenade R, Lainchbury J, et al. NT-proBNP testing for diagnosis and short-term prognosis in acute destabilized heart failure: an international pooled analysis of 1256 patients (ICON). Eur Heart J. 2006;27(3):330–337. — PubMed PMID: 16293638
- Daniels LB, Clopton P, Bhalla V, et al. How obesity affects the cut-points for B-type natriuretic peptide in the diagnosis of acute heart failure. Results from the Breathing Not Properly Multinational Study. Am Heart J. 2006;151(5):999–1005. — PubMed PMID: 16644321
- Mehra MR, Uber PA, Park MH, et al. Obesity and suppressed B-type natriuretic peptide levels in heart failure. J Am Coll Cardiol. 2004;43(9):1590–1595. — PubMed PMID: 15120816
- Krauser DG, Lloyd-Jones DM, Chae CU, et al. Effect of body mass index on natriuretic peptide levels in patients with acute congestive heart failure: a ProBNP Investigation of Dyspnea in the Emergency Department (PRIDE) substudy. Am Heart J. 2005;149(4):744–750. — PubMed PMID: 15990762
- McCullough PA, Duc P, Omland T, et al. B-type natriuretic peptide and renal function in the diagnosis of heart failure: an analysis from the Breathing Not Properly Multinational Study. Am J Kidney Dis. 2003;41(3):571–579. — PubMed PMID: 12612980
- Anwaruddin S, Lloyd-Jones DM, Baggish A, et al. Renal function, congestive heart failure, and amino-terminal pro-brain natriuretic peptide measurement: results from the PRIDE Study. J Am Coll Cardiol. 2006;47(1):91–97. — PubMed PMID: 16386670
- Logeart D, Thabut G, Jourdain P, et al. Predischarge B-type natriuretic peptide assay for identifying patients at high risk of re-admission after decompensated heart failure. J Am Coll Cardiol. 2004;43(4):635–641. — PubMed PMID: 14975475
- Troughton RW, Frampton CM, Yandle TG, et al. Treatment of heart failure guided by plasma aminoterminal brain natriuretic peptide (N-BNP) concentrations. Lancet. 2000;355(9210):1126–1130. — PubMed PMID: 10791374
- Eurlings LW, van Pol PE, Kok WE, et al. Management of chronic heart failure guided by individual N-terminal pro-B-type natriuretic peptide targets: results of the PRIMA study. J Am Coll Cardiol. 2010;56(25):2090–2100. — PubMed PMID: 21144969
- Persson H, Erntell H, Eriksson B, et al. Improved pharmacological therapy of chronic heart failure in primary care: a randomized Study of NT-proBNP Guided Management of Heart Failure (SIGNAL-HF). Eur J Heart Fail. 2010;12(12):1300–1308. — PubMed PMID: 20876734
- Januzzi JL Jr, Rehman SU, Mohammed AA, et al. Use of amino-terminal pro-B-type natriuretic peptide to guide outpatient therapy of patients with chronic left ventricular systolic dysfunction (PROTECT). J Am Coll Cardiol. 2011;58(18):1881–1889. — PubMed PMID: 22018299
- Felker GM, Anstrom KJ, Adams KF, et al. Effect of natriuretic peptide-guided therapy on hospitalization or cardiovascular mortality in high-risk patients with heart failure and reduced ejection fraction: a randomized clinical trial (GUIDE-IT). JAMA. 2017;318(8):713–720. — PubMed PMID: 28829876
- Vasan RS, Benjamin EJ, Larson MG, et al. Plasma natriuretic peptides for community screening for left ventricular hypertrophy and systolic dysfunction: the Framingham Heart Study. JAMA. 2002;288(10):1252–1259. — PubMed PMID: 12215132
- Ledwidge M, Gallagher J, Conlon C, et al. Natriuretic peptide-based screening and collaborative care for heart failure: the STOP-HF randomized trial. JAMA. 2013;310(1):66–74. — PubMed PMID: 23821090
- Lam CS, Cheng S, Choong K, et al. Influence of sex and hormone status on circulating natriuretic peptides. J Am Coll Cardiol. 2011;58(6):618–626. — PubMed PMID: 21798425
- McKie PM, Burnett JC Jr. B-type natriuretic peptide as a biomarker beyond heart failure: speculations and opportunities. Mayo Clin Proc. 2005;80(8):1029–1036. — PubMed PMID: 16092582
- Sudoh T, Kangawa K, Minamino N, et al. A new natriuretic peptide in porcine brain. Nature. 1988;332(6159):78–81. — PubMed PMID: 2964562
- Semenov AG, Tamm NN, Seferian KR, et al. Processing of pro-B-type natriuretic peptide: furin and corin as candidate convertases. Clin Chem. 2010;56(7):1166–1176. — PubMed PMID: 20489134
- van Kimmenade RR, Januzzi JL Jr, Bakker JA, et al. Renal clearance of B-type natriuretic peptide and amino terminal pro-B-type natriuretic peptide: a mechanistic study in hypertensive subjects. J Am Coll Cardiol. 2009;53(10):884–890. — PubMed PMID: 19264247
- McCullough PA, Nowak RM, McCord J, et al. B-type natriuretic peptide and clinical judgment in emergency diagnosis of heart failure: analysis from Breathing Not Properly (BNP) Multinational Study. Circulation. 2002;106(4):416–422. — PubMed PMID: 12135939
- O'Donoghue M, Chen A, Baggish AL, et al. The effects of ejection fraction on N-terminal ProBNP and BNP levels in patients with acute CHF: analysis from the ProBNP Investigation of Dyspnea in the Emergency Department (PRIDE) study. J Card Fail. 2005;11(5 Suppl):S9–S14. — PubMed PMID: 15948094
- Packer M, McMurray JJ, Desai AS, et al. Angiotensin receptor neprilysin inhibition compared with enalapril on the risk of clinical progression in surviving patients with heart failure. Circulation. 2015;131(1):54–61. — PubMed PMID: 25403646
- Myhre PL, Vaduganathan M, Claggett B, et al. B-type natriuretic peptide during treatment with sacubitril/valsartan: the PARADIGM-HF trial. J Am Coll Cardiol. 2019;73(11):1264–1272. — PubMed PMID: 30846338
- Januzzi JL Jr, Prescott MF, Butler J, et al. Association of change in N-terminal pro-B-type natriuretic peptide following initiation of sacubitril-valsartan treatment with cardiac structure and function in patients with heart failure with reduced ejection fraction (PROVE-HF). JAMA. 2019;322(11):1085–1095. — PubMed PMID: 31475295
- Januzzi JL Jr, Ahmad T, Mulder H, et al. Natriuretic peptide response and outcomes in chronic heart failure with reduced ejection fraction. J Am Coll Cardiol. 2019;74(9):1205–1217. — PubMed PMID: 31466618
- Kucher N, Printzen G, Goldhaber SZ. Prognostic role of brain natriuretic peptide in acute pulmonary embolism. Circulation. 2003;107(20):2545–2547. — PubMed PMID: 12742987
- Leya FS, Arab D, Joyal D, et al. The efficacy of brain natriuretic peptide levels in differentiating constrictive pericarditis from restrictive cardiomyopathy. J Am Coll Cardiol. 2005;45(11):1900–1902. — PubMed PMID: 15936624
- Gupta DK, de Lemos JA, Ayers CR, et al. Racial differences in natriuretic peptide levels: the Dallas Heart Study. JACC Heart Fail. 2015;3(7):513–519. — PubMed PMID: 26071618
- Huelsmann M, Neuhold S, Resl M, et al. PONTIAC (NT-proBNP selected prevention of cardiac events in a population of diabetic patients without a history of cardiac disease): a prospective randomized controlled trial. J Am Coll Cardiol. 2013;62(15):1365–1372. — PubMed PMID: 23810874
- Mueller C, McDonald K, de Boer RA, et al. Heart Failure Association of the European Society of Cardiology practical guidance on the use of natriuretic peptide concentrations. Eur J Heart Fail. 2019;21(6):715–731. — PubMed PMID: 31222929
- McDonagh TA, Metra M, Adamo M, et al. 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur Heart J. 2021;42(36):3599–3726. — PubMed PMID: 34447992
- Heidenreich PA, Bozkurt B, Aguilar D, et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2022;145(18):e895–e1032. — PubMed PMID: 35363499
PubMed Topic Searches
The following links run current searches on PubMed and return literature published since this page was written.
- PubMed: Breathing Not Properly study
- PubMed: Obesity and BNP suppression
- PubMed: GUIDE-IT and guided therapy
- PubMed: ACC/AHA heart failure guidelines
- PubMed: ESC heart failure guidelines
- PubMed: NT-proBNP and neprilysin inhibition
- PubMed: NT-proBNP age-stratified thresholds
- PubMed: STOP-HF screening trial
- PubMed: BNP and incident heart failure risk
- PubMed: BNP thresholds in renal failure
- PubMed: Natriuretic peptides in HFpEF
- PubMed: BNP in pulmonary embolism
Connections
- All Lab Tests
- Echocardiogram — the ultrasound window into your heart
- The Heart & Circulation — interactive animation
- Cardiac Troponin (Troponin I & T)
- Kidney Function Tests
- Complete Blood Count
- Comprehensive Metabolic Panel
- Inflammatory Markers
- High-Sensitivity CRP
- Coagulation Panel
- Cortisol Test
- Coronary Calcium Score
- Cardiology Diseases
- Heart Failure
- Atrial Fibrillation
- Cardiomyopathy
- Cardiovascular Disease
- Pulmonary Hypertension
- Pulmonary Embolism
- Kidney Disease
- Hypertension
- Coronary Artery Disease
- Shortness of Breath
- Aortic Stenosis
- Hypothyroidism