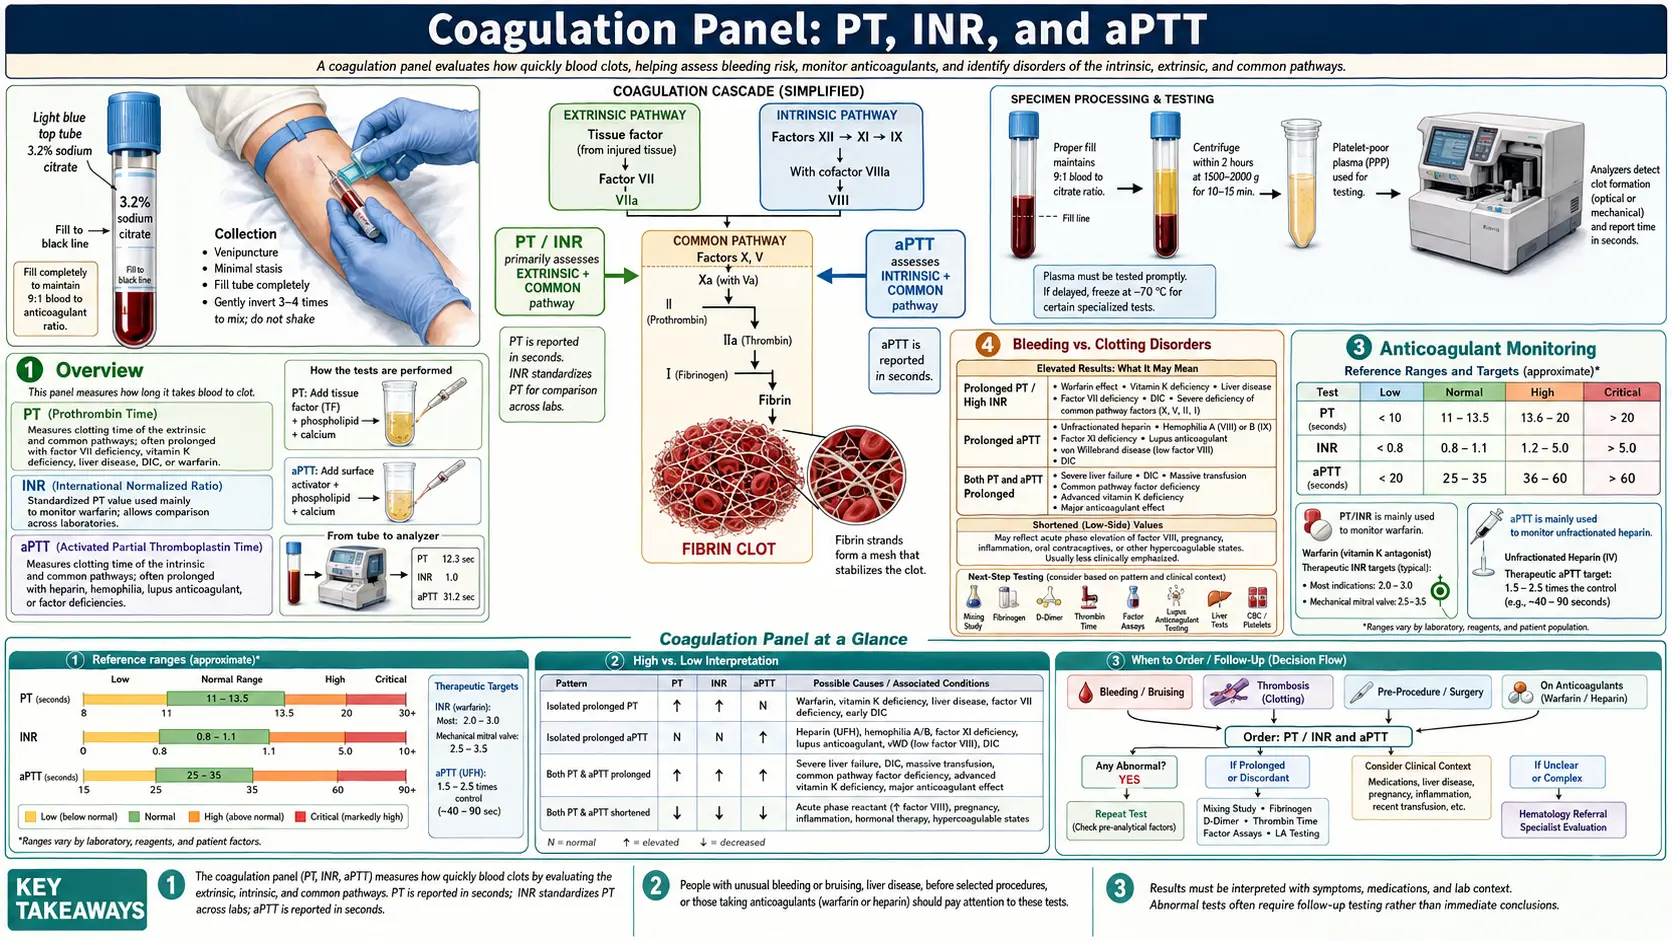
Coagulation Panel: PT, INR, and aPTT
Coagulation tests measure the integrity and speed of the blood clotting cascade. They are used in pre-operative screening, in the diagnosis of bleeding and clotting disorders, and in monitoring anticoagulant therapy. The coagulation panel typically includes the prothrombin time (PT), international normalized ratio (INR), activated partial thromboplastin time (aPTT), fibrinogen, and D-dimer.
Interactive Visualization How Blood Clots — and how thinners stop it Build a platelet plug, weave a fibrin mesh, then watch aspirin, warfarin and a DOAC each break a different step — with a live INR. Launch →Table of Contents
Overview
Hemostasis — the process of stopping bleeding — involves a tightly regulated cascade of clotting factors. This cascade is divided into three pathways:
- Extrinsic pathway (measured by PT/INR): Initiated by tissue factor (Factor III) released from damaged cells. Involves Factors VII, X, V, II (prothrombin), and I (fibrinogen).
- Intrinsic pathway (measured by aPTT): Initiated by contact activation (Factor XII) and involves Factors XI, IX, VIII, X, V, II, and I.
- Common pathway: The point where both pathways converge at Factor X activation, leading to thrombin generation and fibrin clot formation.
Which pathway is abnormal narrows the list of likely causes. For example, an isolated prolonged PT with a normal aPTT points to Factor VII deficiency or early warfarin effect, while an isolated prolonged aPTT points to deficiencies in Factors VIII, IX, XI, or XII, or the presence of a lupus anticoagulant.
Coagulation studies are performed on citrated plasma (blue-top tube). Citrate chelates calcium to prevent clotting during transport; calcium is then re-added in the laboratory to initiate the reaction. The tube is filled to a set volume; an underfilled tube holds too much citrate for the amount of blood and can falsely prolong clotting times.
When Ordered
A coagulation panel is ordered in many clinical situations:
- Pre-operative screening — assessing bleeding risk before surgery or invasive procedures
- Anticoagulant monitoring — INR for warfarin therapy; aPTT for unfractionated heparin infusions
- Unexplained bleeding — easy bruising, prolonged bleeding from minor cuts, spontaneous nosebleeds, heavy menstrual periods
- Suspected coagulopathy — hemophilia A or B, von Willebrand disease, Factor deficiencies
- Liver disease evaluation — the liver synthesizes most clotting factors; a prolonged PT/INR reflects hepatic synthetic dysfunction
- Suspected DIC — disseminated intravascular coagulation presents with low fibrinogen, elevated D-dimer, and prolonged PT/aPTT
- Venous thromboembolism (VTE) — elevated D-dimer as a screening tool for deep vein thrombosis (DVT) or pulmonary embolism (PE)
- Vitamin K deficiency — malnutrition, malabsorption syndromes, or prolonged antibiotic use
- Lupus anticoagulant evaluation — patients with recurrent pregnancy loss or unexplained thrombosis
Individual Tests and Reference Ranges
Prothrombin Time (PT)
The PT measures how long it takes plasma to clot after the addition of tissue factor and calcium. It reflects the function of the extrinsic and common pathways (Factors I, II, V, VII, X). It is the primary test for monitoring warfarin therapy and assessing liver synthetic function.
Prothrombin Time (PT) (seconds)
The normal range shown is the one MedlinePlus gives for people not taking blood thinners (PT 11 to 13.5 seconds); each laboratory sets its own range, which depends on its reagent and method (MedlinePlus: Prothrombin time).
Clinical notes: PT values vary between laboratories depending on the thromboplastin reagent used, which is why the INR was developed to standardize warfarin monitoring across institutions. A prolonged PT with normal aPTT suggests isolated Factor VII deficiency, early warfarin effect, or mild vitamin K deficiency. The INR is one of the variables in the MELD score used to grade the severity of end-stage liver disease (Kamath 2001), and prothrombin time is also part of the Child-Pugh score.
International Normalized Ratio (INR)
The INR is a standardized calculation derived from the PT that corrects for variability in laboratory thromboplastin reagents. It is the standard measure for monitoring warfarin anticoagulation and is also used to assess liver function. The INR is calculated as: INR = (Patient PT ÷ Mean Normal PT)ISI, where ISI is the International Sensitivity Index of the reagent used.
INR — Baseline (ratio)
MedlinePlus gives an INR of 0.8 to 1.1 for people not taking blood thinners and describes a usual warfarin target of 2.0 to 3.0; laboratory ranges vary.
INR — Therapeutic (warfarin, most indications) (ratio)
Clinical notes: The 2012 American College of Chest Physicians (ACCP) guideline makes a strong recommendation for a target INR of 2.0–3.0 for people on vitamin K antagonist therapy such as warfarin (Holbrook 2012). For mechanical heart valves, the ACCP valve guideline lists a target INR of 2.5 (range 2.0–3.0) for mechanical aortic valves and 3.0 (range 2.5–3.5) for mechanical mitral or double valves (Whitlock 2012). In a 1994 case-control study of 121 warfarin-treated outpatients hospitalized with intracranial hemorrhage, the risk of intracerebral hemorrhage roughly doubled with each 0.5 rise in the prothrombin-time ratio, and the risk of subdural hemorrhage rose sharply above a ratio of 2.0 (approximately INR 4.0) (Hylek 1994). Outside anticoagulation, an INR above 1.5 together with encephalopathy is part of the usual definition of acute liver failure (De Gasperi 2009).
Activated Partial Thromboplastin Time (aPTT)
The aPTT measures the intrinsic and common pathway clotting factors (XII, XI, IX, VIII, X, V, II, I). It is the primary test for monitoring unfractionated heparin infusions and for detecting deficiencies in intrinsic pathway factors.
aPTT (seconds)
MedlinePlus gives a general aPTT range of 25 to 35 seconds and notes that normal ranges vary among laboratories (MedlinePlus: Partial thromboplastin time).
Clinical notes: A therapeutic aPTT range of 1.5–2.5 times control for unfractionated heparin gained wide acceptance from a retrospective study in the 1970s, in which that ratio corresponded to an anti-Xa heparin level of 0.3–0.7 units/mL. The 2012 ACCP review notes that this range has not been confirmed in randomized trials, that aPTT reagents and instruments differ in their response to heparin, and that each institution's therapeutic aPTT range is meant to be adapted to its own reagent (Garcia 2012). Some hospitals monitor heparin with anti-Xa levels instead. An isolated prolonged aPTT with normal PT occurs in hemophilia A (Factor VIII), hemophilia B (Factor IX), Factor XI deficiency, or the presence of lupus anticoagulant. A prolonged aPTT that normalizes on mixing with normal plasma (mixing study) points to a factor deficiency; failure to correct points to an inhibitor (e.g., lupus anticoagulant, Factor VIII inhibitor).
Fibrinogen
Fibrinogen (Factor I) is the final substrate of the coagulation cascade, converted to fibrin by thrombin to form the clot scaffold. It is an acute-phase reactant and is elevated in inflammatory states. Critically low levels occur in DIC, severe liver disease, or congenital afibrinogenemia.
Fibrinogen (mg/dL)
MedlinePlus gives a normal range of 200 to 400 mg/dL (2.0 to 4.0 g/L) and notes that ranges vary among laboratories (MedlinePlus: Fibrinogen blood test).
Clinical notes: In DIC, fibrinogen is consumed as clotting runs unchecked, producing low levels alongside elevated D-dimer and prolonged PT/aPTT. In an individual-participant meta-analysis of 154,211 adults in 31 prospective studies, higher usual fibrinogen was associated with higher risk of coronary heart disease and stroke (hazard ratios of about 1.8 per 1 g/L after adjustment for established risk factors); the authors wrote that whether elevated fibrinogen causes disease requires further research (Fibrinogen Studies Collaboration 2005). Fibrinogen normally rises during pregnancy. In a study of 128 women with postpartum hemorrhage, a fibrinogen of 2 g/L or less at enrollment had a positive predictive value of 100% for severe hemorrhage, and the risk of severe hemorrhage was 2.63-fold higher for each 1 g/L decrease (Charbit 2007).
D-Dimer
D-dimer is a fibrin degradation product released when plasmin breaks down cross-linked fibrin clots. It is a highly sensitive but non-specific marker of active clot formation and fibrinolysis. An elevated D-dimer indicates that coagulation and fibrinolysis are occurring somewhere in the body, but does not specify where.
D-Dimer (µg/L)
The 500 µg/L figure is the conventional fixed cutoff used in the ADJUST-PE study (Righini 2014). D-dimer units and cutoffs depend on the assay, and MedlinePlus describes the result simply as normal or higher than normal (MedlinePlus: D-Dimer Test).
Clinical notes: In a randomized trial of outpatients with suspected DVT (530 assigned to ultrasound alone, 566 to D-dimer testing first), ultrasound was safely omitted in patients judged clinically unlikely to have DVT who had a negative D-dimer; 0.4% of patients in the D-dimer group in whom DVT had been ruled out had a confirmed venous thromboembolic event over 3 months (Wells 2003). D-dimer is also elevated in many non-thrombotic conditions: pregnancy, recent surgery, infection, inflammation, cancer, liver disease, and advanced age. In the ADJUST-PE study of 3,346 outpatients with suspected pulmonary embolism, an age-adjusted cutoff of age × 10 µg/L for patients 50 years or older was used together with clinical probability assessment; among patients 75 or older with a non-high clinical probability, the share in whom PE could be excluded by D-dimer rose from 6.4% with the 500 µg/L cutoff to 29.7%, without additional false-negative findings (Righini 2014). The ISTH scoring system for overt DIC includes a fibrin-related marker such as D-dimer (Taylor 2001).
Interpretation of Results
The coagulation panel is read by looking at which tests are abnormal together:
- Prolonged PT only (normal aPTT): Isolated Factor VII deficiency, early warfarin effect, early vitamin K deficiency, mild liver disease.
- Prolonged aPTT only (normal PT): Hemophilia A (Factor VIII deficiency), Hemophilia B (Factor IX deficiency), Factor XI deficiency, lupus anticoagulant (paradoxically associated with thrombosis), heparin therapy.
- Both PT and aPTT prolonged: Common pathway deficiency (Factors X, V, II, I), severe vitamin K deficiency, warfarin overdose, severe liver disease, DIC. Direct oral anticoagulants can prolong one or both tests, but the effect varies by drug and reagent and the tests may be normal at trough drug levels (Cuker 2014).
- Low fibrinogen + elevated D-dimer + prolonged PT and aPTT: the pattern of DIC, which is driven by an underlying trigger (sepsis, trauma, malignancy, obstetric emergency).
- Elevated D-dimer alone: can reflect DVT/PE or one of the non-thrombotic causes listed above; on its own it does not show where clotting is taking place.
Anticoagulant Monitoring
Different anticoagulant drugs are monitored in different ways:
- Warfarin (vitamin K antagonist): Monitored with INR. The 2012 ACCP guidelines give a target of 2.0–3.0 for most indications (Holbrook 2012) and 2.5–3.5 (target 3.0) for mechanical mitral valves (Whitlock 2012). For patients whose INRs are consistently stable, the 2012 ACCP guideline suggests INR testing up to every 12 weeks rather than every 4 weeks (Holbrook 2012). Warfarin works by blocking the recycling of vitamin K, so changes in vitamin K intake shift the INR; in a double-blind trial in 70 warfarin patients with unstable control, 150 µg/day of oral vitamin K for 6 months reduced INR variability and increased time in the target range compared with placebo (Sconce 2007).
- Unfractionated heparin (UFH): Monitored with the aPTT (a ratio of 1.5–2.5 times control, adapted to each laboratory's reagent) or with anti-Xa levels (0.3–0.7 units/mL) (Garcia 2012).
- Low molecular weight heparin (LMWH — enoxaparin, dalteparin): Given without routine coagulation monitoring. Anti-Xa levels are used in special populations: pregnancy, obesity, renal impairment, or extreme body weight. For VTE treatment, the 2012 ACCP review gives a peak anti-Xa level (measured 4 hours after the dose) of 0.6–1.0 units/mL for twice-daily enoxaparin or nadroparin (Garcia 2012).
- Direct oral anticoagulants (DOACs): Dabigatran, rivaroxaban, apixaban, edoxaban. They do not require routine laboratory monitoring (Douxfils 2018). Their effect on the PT and aPTT varies: for dabigatran, a normal thrombin time excludes clinically relevant drug levels, while the aPTT and PT are less sensitive and may be normal at trough levels; for rivaroxaban and apixaban, the PT is less sensitive (especially for apixaban), a normal PT may not exclude clinically relevant levels, and the aPTT is not suitable for measuring the drug (Cuker 2014). Drug-calibrated anti-Xa or anti-IIa assays are the preferred methods when quantitative information is useful, such as in bleeding, emergencies or before surgery (Douxfils 2018).
- Fondaparinux: Given once daily by subcutaneous injection in fixed doses without coagulation monitoring; when a level is measured, the 2012 ACCP review notes it has to be done with an anti-Xa assay calibrated with fondaparinux itself (Garcia 2012).
Bleeding vs. Clotting Disorders
The coagulation panel helps distinguish primary bleeding disorders from thrombotic disorders:
Bleeding Disorders
- Hemophilia A: X-linked Factor VIII deficiency. Isolated prolonged aPTT. The ISTH definitions grade severity by factor activity: severe (<1% of normal), moderate (1–5%), mild (>5% to <40%) (White 2001).
- Hemophilia B: X-linked Factor IX deficiency. Isolated prolonged aPTT. Clinically similar to Hemophilia A and less common; severity is graded on the same factor-activity scale.
- Von Willebrand disease (vWD): The most common inherited bleeding disorder known in humans, according to the 2021 ASH/ISTH/NHF/WFH diagnosis guideline (James 2021). vWF is required for platelet adhesion and Factor VIII stabilization. May prolong aPTT in severe forms. Diagnosis requires specific vWF antigen and activity assays.
- Vitamin K deficiency: Affects Factors II, VII, IX, X, Protein C, and Protein S. Prolongs the PT first; the aPTT is also prolonged when deficiency is severe. Causes include malnutrition, malabsorption (Crohn's disease, celiac disease), prolonged antibiotic use, and cholestatic liver disease.
- Liver disease: The liver makes most clotting factors. Advanced liver disease prolongs PT/INR and aPTT, can reduce fibrinogen, and may cause thrombocytopenia from hypersplenism. Because pro- and anti-clotting systems fall together, reviews describe a “rebalanced” hemostasis with narrower margins that can tip toward either bleeding or thrombosis (van der Werf 2009).
- DIC: Consumptive coagulopathy triggered by sepsis, trauma, malignancy, or obstetric emergencies. Characterized by simultaneous widespread clotting and bleeding.
Clotting (Thrombotic) Disorders
- Factor V Leiden: An inherited mutation in Factor V that gives a poor anticoagulant response to activated Protein C and raises the risk of venous thromboembolism (Bertina 1994; Kujovich 2011). PT and aPTT are typically normal; diagnosis uses the activated Protein C resistance assay or DNA analysis of the F5 gene (Kujovich 2011).
- Prothrombin gene mutation (G20210A): In the 1996 population-based case-control study that described it, the 20210 A allele was associated with elevated prothrombin levels and an almost threefold higher risk of venous thrombosis (odds ratio 2.8) (Poort 1996). Standard coagulation tests are normal; it is diagnosed by genetic testing.
- Antiphospholipid syndrome (APS): Autoimmune condition with lupus anticoagulant, anticardiolipin antibodies, or anti-beta-2 glycoprotein I antibodies. Paradoxically prolongs aPTT in vitro but causes thrombosis in vivo. Associated with recurrent miscarriage (classification criteria: Miyakis 2006).
- Protein C and Protein S deficiency: Natural anticoagulants that inactivate Factors Va and VIIIa. Deficiency increases VTE risk. Standard coagulation tests are normal.
- Antithrombin deficiency: Antithrombin inhibits thrombin and Factor Xa. Hereditary deficiency increases VTE risk. Also causes heparin resistance.
Key Research Papers
- Holbrook A, Schulman S, Witt DM, et al. (2012). Evidence-based management of anticoagulant therapy: Antithrombotic Therapy and Prevention of Thrombosis, 9th ed: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines. Chest 141(2 Suppl):e152S-e184S — PubMed PMID: 22315259
- Whitlock RP, Sun JC, Fremes SE, et al. (2012). Antithrombotic and thrombolytic therapy for valvular disease: Antithrombotic Therapy and Prevention of Thrombosis, 9th ed: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines. Chest 141(2 Suppl):e576S-e600S — PubMed PMID: 22315272
- Garcia DA, Baglin TP, Weitz JI, Samama MM (2012). Parenteral anticoagulants: Antithrombotic Therapy and Prevention of Thrombosis, 9th ed: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines. Chest 141(2 Suppl):e24S-e43S — PubMed PMID: 22315264
- Hylek EM, Singer DE (1994). Risk factors for intracranial hemorrhage in outpatients taking warfarin. Annals of Internal Medicine 120(11):897-902 — PubMed PMID: 8172435
- Sconce E, Avery P, Wynne H, Kamali F (2007). Vitamin K supplementation can improve stability of anticoagulation for patients with unexplained variability in response to warfarin. Blood 109(6):2419-23 — PubMed PMID: 17110451
- Cuker A, Siegal DM, Crowther MA, Garcia DA (2014). Laboratory measurement of the anticoagulant activity of the non-vitamin K oral anticoagulants. Journal of the American College of Cardiology 64(11):1128-39 — PubMed PMID: 25212648
- Douxfils J, Ageno W, Samama CM, et al. (2018). Laboratory testing in patients treated with direct oral anticoagulants: a practical guide for clinicians. Journal of Thrombosis and Haemostasis 16(2):209-219 — PubMed PMID: 29193737
- Righini M, Van Es J, Den Exter PL, et al. (2014). Age-adjusted D-dimer cutoff levels to rule out pulmonary embolism: the ADJUST-PE study. JAMA 311(11):1117-24 — PubMed PMID: 24643601
- Wells PS, Anderson DR, Rodger M, et al. (2003). Evaluation of D-dimer in the diagnosis of suspected deep-vein thrombosis. New England Journal of Medicine 349(13):1227-35 — PubMed PMID: 14507948
- Taylor FB Jr, Toh CH, Hoots WK, et al. (2001). Towards definition, clinical and laboratory criteria, and a scoring system for disseminated intravascular coagulation. Thrombosis and Haemostasis 86(5):1327-30 — PubMed PMID: 11816725
- Fibrinogen Studies Collaboration; Danesh J, Lewington S, Thompson SG, et al. (2005). Plasma fibrinogen level and the risk of major cardiovascular diseases and nonvascular mortality: an individual participant meta-analysis. JAMA 294(14):1799-809 — PubMed PMID: 16219884
- Charbit B, Mandelbrot L, Samain E, et al. (2007). The decrease of fibrinogen is an early predictor of the severity of postpartum hemorrhage. Journal of Thrombosis and Haemostasis 5(2):266-73 — PubMed PMID: 17087729
- Kamath PS, Wiesner RH, Malinchoc M, et al. (2001). A model to predict survival in patients with end-stage liver disease. Hepatology 33(2):464-70 — PubMed PMID: 11172350
- De Gasperi A, Corti A, Mazza E, et al. (2009). Acute liver failure: managing coagulopathy and the bleeding diathesis. Transplantation Proceedings 41(4):1256-9 — PubMed PMID: 19460532
- van der Werf J, Porte RJ, Lisman T (2009). Hemostasis in patients with liver disease. Acta Gastro-Enterologica Belgica 72(4):433-40 — PubMed PMID: 20163038
- White GC 2nd, Rosendaal F, Aledort LM, et al. (2001). Definitions in hemophilia. Recommendation of the scientific subcommittee on factor VIII and factor IX of the scientific and standardization committee of the International Society on Thrombosis and Haemostasis. Thrombosis and Haemostasis 85(3):560 — PubMed PMID: 11307831
- James PD, Connell NT, Ameer B, et al. (2021). ASH ISTH NHF WFH 2021 guidelines on the diagnosis of von Willebrand disease. Blood Advances 5(1):280-300 — PubMed PMID: 33570651
- Bertina RM, Koeleman BP, Koster T, et al. (1994). Mutation in blood coagulation factor V associated with resistance to activated protein C. Nature 369(6475):64-7 — PubMed PMID: 8164741
- Kujovich JL (2011). Factor V Leiden thrombophilia. Genetics in Medicine 13(1):1-16 — PubMed PMID: 21116184
- Poort SR, Rosendaal FR, Reitsma PH, Bertina RM (1996). A common genetic variation in the 3'-untranslated region of the prothrombin gene is associated with elevated plasma prothrombin levels and an increase in venous thrombosis. Blood 88(10):3698-703 — PubMed PMID: 8916933
- Miyakis S, Lockshin MD, Atsumi T, et al. (2006). International consensus statement on an update of the classification criteria for definite antiphospholipid syndrome (APS). Journal of Thrombosis and Haemostasis 4(2):295-306 — PubMed PMID: 16420554
PubMed Topic Searches
- PT INR warfarin monitoring — PubMed literature search
- Activated partial thromboplastin time — PubMed literature search
- D-dimer venous thromboembolism — PubMed literature search
- Fibrinogen cardiovascular — PubMed literature search
- Disseminated intravascular coagulation — PubMed literature search
- Hemophilia diagnosis — PubMed literature search
- Antiphospholipid syndrome lab — PubMed literature search
- Direct oral anticoagulants monitoring — PubMed literature search
- Thrombophilia workup — PubMed literature search
- Von Willebrand disease testing — PubMed literature search
External Authoritative Resources
Connections
- All Lab Tests
- How Blood Clots — interactive animation
- Deep Vein Thrombosis
- Pulmonary Embolism
- Complete Blood Count
- Hemophilia
- Liver Disease
- Lupus
- Vitamin K
- Von Willebrand Disease
- Disseminated Intravascular Coagulation
- Atrial Fibrillation
- Sepsis
- Thrombocytopenia
- Calcium
- Crohn's Disease
- Lipid Panel
- Nattokinase
- Inflammatory Markers
- Cardiovascular Disease
Featured Videos