⚠ Evidence warning: Clinical trials or other evidence do not support the claim that astragalus reduces re-hospitalization for decompensated congestive heart failure. This page keeps it as a report of what people, websites or other media say.
Astragalus for Cardiovascular Health
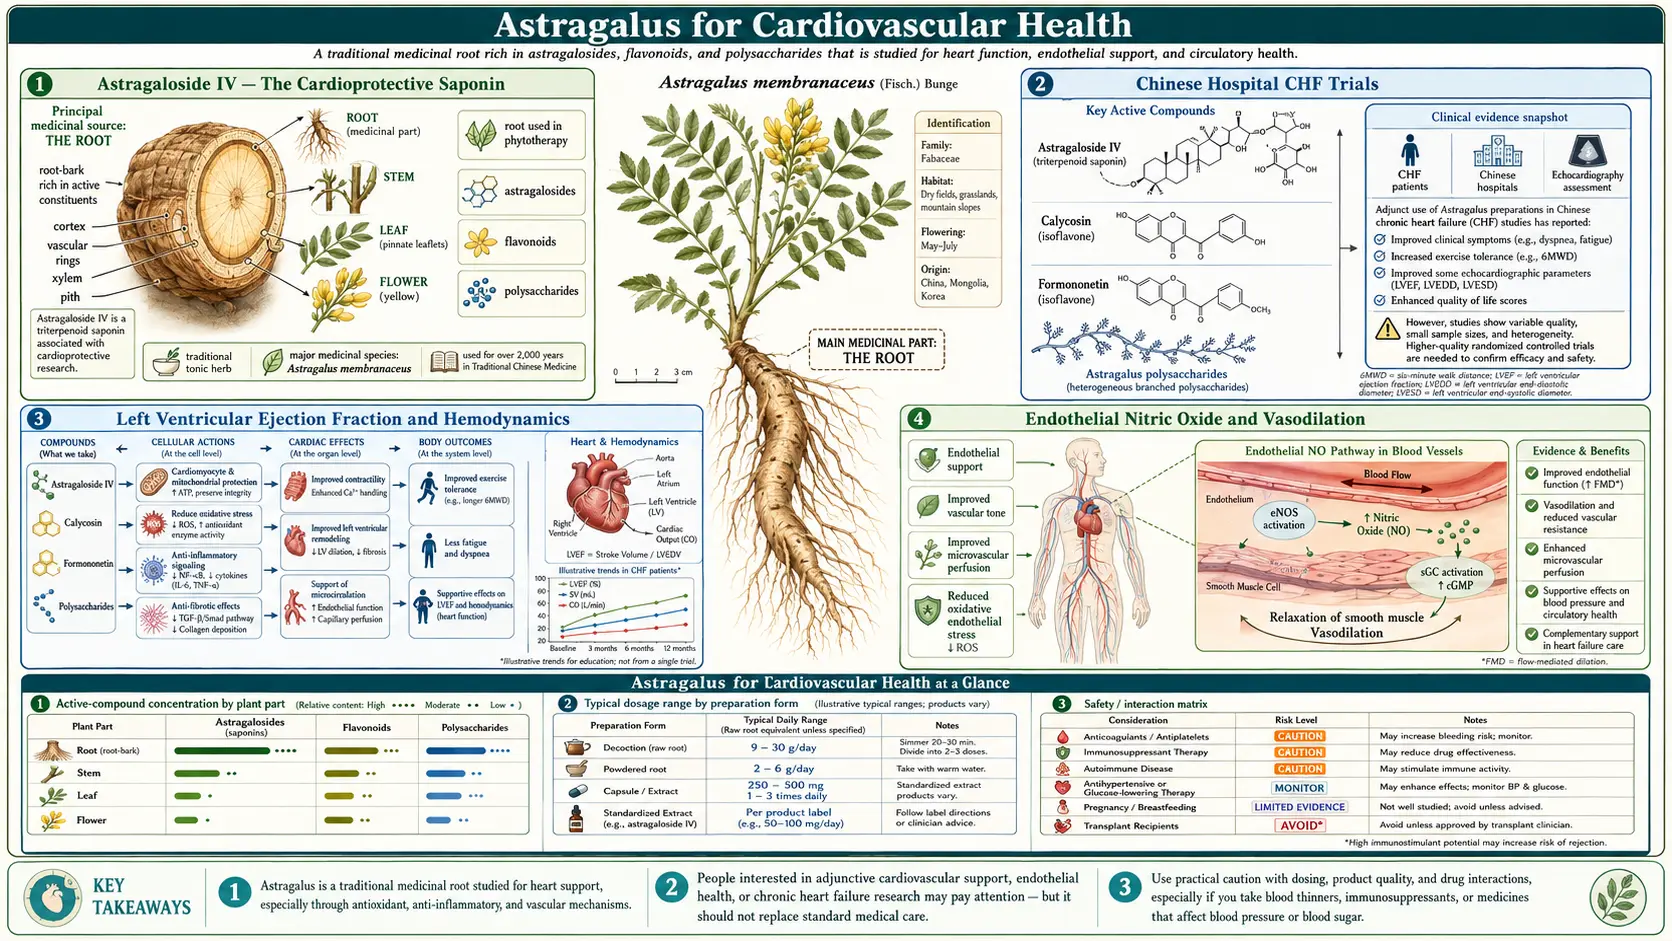
Astragaloside IV, the most thoroughly characterized triterpenoid saponin in Astragalus membranaceus, has produced one of the most coherent cardioprotective data packages of any single botanical compound. Chinese hospital trials report that intravenous astragalus injection added to standard congestive heart failure therapy improves left ventricular ejection fraction and exercise tolerance, although a 2011 systematic review judged those trials too low in quality to draw a conclusion; laboratory and animal studies report that oral preparations and astragaloside IV support endothelial nitric oxide production, reduce cardiac fibrosis after myocardial infarction, modulate cAMP signaling for a gentle positive inotropic effect, and protect vascular endothelium from oxidative damage. The pattern is consistent with the classical Chinese characterization of huang qi as a qi-tonifying herb for chronic deficiency — gradual restoration of cardiac function over weeks rather than acute hemodynamic intervention. This deep-dive traces the mechanism through endothelial biology, cardiomyocyte calcium handling, post-MI remodeling biology, and the integrative cardiology rationale for combining astragalus with optimal medical therapy in heart failure and ischemic heart disease.
Table of Contents
- Astragaloside IV — The Cardioprotective Saponin
- Chinese Hospital CHF Trials
- Left Ventricular Ejection Fraction and Hemodynamics
- Endothelial Nitric Oxide and Vasodilation
- cAMP Signaling and Positive Inotropic Effect
- Post-Myocardial Infarction Remodeling
- Ischemia-Reperfusion Injury Protection
- Low-Density Lipoprotein Oxidation and Atherosclerosis
- Antiplatelet Activity and Thrombosis Prevention
- Anthracycline Cardiotoxicity Mitigation
- Integrative Cardiology — Adding Astragalus to Standard Therapy
- Dosing for Cardiovascular Indications
- Cautions (Anticoagulants, Hypotension, Surgery)
- Key Research Papers
- Connections
- Featured Videos
Astragaloside IV — The Cardioprotective Saponin
Astragaloside IV (AS-IV) is the most abundant and most thoroughly studied of the triterpenoid saponins in Astragalus membranaceus root. Chemically it is a cycloartane-type tetracyclic triterpene glycoside — an aglycone (cycloastragenol) attached to two sugar units (xylose and glucose). Standardized astragalus extracts for cardiovascular indications are commonly assayed for AS-IV content, typically 0.3 to 1.0% by weight of the dried root extract.
AS-IV is sufficiently lipid-soluble to cross cell membranes (the aglycone portion enters the lipid bilayer) and engage intracellular signaling targets. The pharmacological profile spans:
- Inhibition of TGF-beta-driven fibroblast-to-myofibroblast transition (the cellular basis of cardiac fibrosis)
- Modulation of PI3K/Akt and AMP-activated protein kinase (AMPK) signaling, both relevant to cardiomyocyte survival under stress
- Upregulation of endothelial nitric oxide synthase (eNOS) and increased nitric oxide bioavailability
- Reduction of mitochondrial dysfunction and apoptosis under ischemia-reperfusion conditions
- Mild positive inotropic effect via cAMP-dependent calcium handling enhancement
- Direct antioxidant activity and upregulation of endogenous antioxidant enzyme expression (superoxide dismutase (SOD), catalase, glutathione peroxidase)
The same molecular mechanisms that make AS-IV cardioprotective also drive its renoprotective effects, discussed in the Kidney and Diabetic Nephropathy deep-dive — TGF-beta inhibition reduces fibrosis equally in cardiac and renal tissue, eNOS upregulation improves microcirculation in both vascular beds, and the antioxidant effects translate across organ systems. This is one of the reasons supporters propose astragalus for people with combined cardiorenal disease, where the two organ systems are simultaneously failing.
Chinese Hospital CHF Trials
The clinical evidence base for astragalus in congestive heart failure (CHF) is largely Chinese in origin. Multiple randomized controlled trials have been conducted in Chinese university hospital cardiology departments, generally adding astragalus — most often as an injectable preparation (huang qi zhu she ye) administered intravenously alongside standard therapy — to a control arm receiving standard therapy alone.
The standard therapy in these trials is the usual heart-failure regimen: an angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB), a beta-blocker, a diuretic, and digoxin where indicated. Individual Chinese trials report improvements in left ventricular ejection fraction (LVEF), in N-terminal pro-B-type natriuretic peptide (NT-proBNP) levels, in New York Heart Association (NYHA) symptom class, in walking distance and in quality of life when the injection is added, along with a reduction in re-hospitalization rates for decompensated CHF.
The best-known review of these trials, a 2011 systematic review by Fu and colleagues, screened 1,205 articles and found 62 randomized and quasi-randomized trials of Huangqi (astragalus) injection for chronic heart failure, all conducted in China and published in Chinese journals. The reviewers judged the methodological quality of the trials low: in most trials the rules for who could and could not take part were not stated, and only one trial measured the drug's effect after an adequate length of time. For these reasons, and because the patients in different trials started from different baselines, the reviewers did not pool the results into a meta-analysis. They concluded that the available studies were not adequate to draw a conclusion on either the efficacy or the safety of Huangqi injection.
Two later network meta-analyses (studies that compare several treatments at once across many trials) looked at astragalus again. A 2025 analysis of 20 randomized trials with 2,077 heart-failure patients, comparing several plant extracts, ranked astragalus extract highest for improving the 6-minute walk test and for lowering tumor necrosis factor-alpha (TNF-alpha), an inflammation marker; red ginseng extract ranked highest for LVEF. Its authors note heterogeneity and method problems in the included studies and call for larger, high-quality randomized trials. A 2026 analysis of 18 randomized trials with 1,584 patients, covering 16 oral Chinese medicines that contain astragalus, found that adding them to Western heart-failure drugs improved the overall clinical response rate, with astragalus granules ranking best on that measure; its authors write that the limited number and quality of the trials mean the result still needs confirmation in well-designed double-blind trials.
The methodological quality of individual trials varies substantially — many trials are single-center, open-label or single-blind, with relatively short follow-up — and the reliance on injectable astragalus rather than oral preparations limits direct translation to outpatient Western practice. Major Western cardiology guidelines do not incorporate astragalus, and the review authors above all call for rigorous, larger trials. Supporters point to the consistent direction of the reported effects and to the laboratory mechanisms; the reviewers' point is that low-quality trials cannot show whether that direction is real.
Left Ventricular Ejection Fraction and Hemodynamics
Left ventricular ejection fraction (LVEF) is the fraction of blood pumped from the left ventricle with each contraction. Normal LVEF is 55-70%; reduced LVEF (typically defined as <40%) is the diagnostic threshold for "heart failure with reduced ejection fraction" (HFrEF), the systolic heart failure pattern that benefits from neurohormonal blockade with angiotensin-converting enzyme inhibitors (ACE inhibitors), beta-blockers, mineralocorticoid receptor antagonists, and sodium-glucose cotransporter-2 (SGLT2) inhibitors.
The astragalus effect on LVEF appears to operate through three mechanisms:
- Direct positive inotropic effect — astragaloside IV mildly enhances cardiomyocyte calcium handling and contractility through cAMP-dependent and calcium-channel modulating mechanisms (discussed below)
- Afterload reduction via endothelial nitric oxide enhancement — improved peripheral vasodilation reduces the resistance the failing left ventricle must pump against, increasing ejection fraction at the same level of myocardial contractility
- Reverse remodeling effect — chronic astragalus use reduces TGF-beta-driven cardiac fibrosis and may allow gradual recovery of viable but stunned or hibernating myocardium
The combination of inotropic support, afterload reduction, and reverse remodeling closely parallels the effect profile of the optimal medical therapy regimen for HFrEF — which is why astragalus produces an additive rather than overlapping effect when added to standard therapy. Supporters therefore describe astragalus as a complement to, not a replacement for, evidence-based guideline-directed medical therapy.
Endothelial Nitric Oxide and Vasodilation
The vascular endothelium — the single layer of cells lining all blood vessels — produces nitric oxide (NO) via the enzyme endothelial nitric oxide synthase (eNOS). Endothelium-derived NO diffuses to adjacent vascular smooth muscle, triggering relaxation, vasodilation, and reduced peripheral vascular resistance. Endothelial dysfunction — impaired NO production due to age, hypertension, diabetes, dyslipidemia, smoking, or chronic inflammation — is among the earliest detectable abnormalities in cardiovascular disease and a major contributor to hypertension, ischemic disease, and heart failure with preserved ejection fraction.
Astragaloside IV restores endothelial function through several pathways:
- Direct upregulation of eNOS gene expression and protein abundance in endothelial cells
- Increased eNOS enzymatic activity through PI3K/Akt-mediated phosphorylation of the eNOS Ser1177 activation site
- Reduction of inducible NOS (iNOS) overactivity in chronic inflammation (which produces pathological NO levels that scavenge oxygen)
- Antioxidant effects that preserve NO bioavailability by reducing the reaction of NO with superoxide to form peroxynitrite
- Reduced endothelial cell apoptosis under oxidative stress
The clinical effects described for this are improved flow-mediated dilation (a standard non-invasive measure of endothelial function), reduced peripheral vascular resistance, modest blood pressure lowering in people with mildly raised blood pressure, and improved exercise tolerance in patients with both stable angina and heart failure. The blood-pressure-lowering effect is described as too mild to substitute for first-line blood pressure medicines but additive when combined with them.
cAMP Signaling and Positive Inotropic Effect
The classical positive inotropic pharmacology (drugs that enhance cardiac contractility) operates primarily through one of two mechanisms: beta-adrenergic agonism (epinephrine, dobutamine) that activates G-protein coupled receptors and increases intracellular cAMP, or phosphodiesterase-3 inhibition (milrinone, inamrinone) that prevents cAMP degradation. Either way, the downstream effect is increased cAMP, which activates protein kinase A, which phosphorylates and enhances the activity of voltage-gated calcium channels and the sarcoplasmic reticulum calcium handling machinery.
Astragaloside IV exerts a mild positive inotropic effect through a similar cAMP-related mechanism, though with a more modest magnitude and a much more favorable safety profile than dobutamine or milrinone. The conventional pharmaceutical inotropes increase cardiac contractility powerfully but at the cost of increased oxygen consumption, arrhythmogenicity, and worse outcomes. In the PROMISE trial (1991), 1,088 people with severe chronic heart failure took 40 mg of oral milrinone daily or placebo on top of standard therapy; milrinone was linked to a 28 percent increase in deaths from all causes and a 53 percent increase in the sickest group (NYHA class IV), along with more hospital stays, low blood pressure and fainting. In the OPTIME-CHF trial (2002), 951 people admitted with worsening heart failure received a 48-hour intravenous milrinone drip or saline; the drip did not shorten hospital stays or change deaths at 60 days (10.3% vs 8.9%), and it caused more sustained low blood pressure needing treatment (10.7% vs 3.2%) and more new atrial rhythm problems (4.6% vs 1.5%). Astragalus appears to provide modest inotropic support without these adverse long-term consequences — though the evidence base for very long-term outcomes is less mature than the evidence base for established Western inotropes.
The complementary effect to inotropy is the reverse-remodeling effect described above: while the cAMP-mediated boost provides modest immediate contractility enhancement, the TGF-beta antifibrotic effect and the eNOS-mediated afterload reduction produce slower, more durable structural improvement that persists after each individual dose. The net long-term clinical pattern is gradual improvement in cardiac function over weeks to months of consistent use, rather than the immediate but short-lived hemodynamic boost of acute inotropic infusion.
Post-Myocardial Infarction Remodeling
After acute myocardial infarction, the injured myocardium undergoes a process called "ventricular remodeling" the chamber dilates, the wall thins, scar tissue replaces dead cardiomyocytes, and the remaining viable myocardium hypertrophies to compensate. Adverse remodeling progresses over months to years and is a major mechanism of post-MI heart failure. Pharmacologic reverse-remodeling (with angiotensin-converting enzyme inhibitors, angiotensin receptor blockers (ARBs), mineralocorticoid receptor antagonists, and beta-blockers) is the central goal of standard post-MI care.
Astragaloside IV has been studied in animal myocardial infarction (MI) models, and astragalus has been described in Chinese clinical reports as an adjunct to standard post-MI care:
- In rat coronary ligation models, AS-IV reduces infarct expansion, improves post-MI LVEF, and reduces fibrosis in remote (non-infarcted) myocardium
- The TGF-beta inhibition mechanism is particularly relevant — TGF-beta-driven myofibroblast transformation is the primary cellular driver of post-MI fibrosis
- Animal studies show reduced matrix metalloproteinase activity, suggesting reduced infarct-zone expansion
- Chinese clinical reports describe modest improvements in LVEF and reductions in NT-proBNP when astragalus is added to standard post-MI therapy
On this basis, supporters describe a possible adjunctive role for astragalus in the post-MI recovery period — alongside, not instead of, the guideline-directed combination of ACE-inhibitor/angiotensin receptor blocker, beta-blocker, statin, and antiplatelet therapy. For more on the broader cardiovascular context, see our Cardiovascular Disease page.
Ischemia-Reperfusion Injury Protection
Ischemia-reperfusion (I-R) injury is the paradoxical cellular damage that occurs when blood flow is restored to ischemic tissue. The reperfusion itself — through generation of reactive oxygen species, intracellular calcium overload, mitochondrial dysfunction, and inflammatory cell infiltration — can produce a substantial fraction of the final tissue damage. In clinical practice this matters for primary percutaneous coronary intervention (PCI, opening the blocked artery with a balloon or stent) after acute myocardial infarction, for cardiac surgery requiring cardiopulmonary bypass, and for stroke management with thrombolysis or thrombectomy.
Astragaloside IV has been one of the more thoroughly studied botanical cardioprotectants against I-R injury. In rodent and isolated-heart models:
- Pretreatment with AS-IV before coronary occlusion reduces infarct size
- Treatment given at the time of reperfusion (clinically more relevant) also reduces infarct size, suggesting protection against the reperfusion phase specifically
- Mitochondrial integrity is preserved — reduced opening of the mitochondrial permeability transition pore, the proximate trigger of cardiomyocyte death
- Endogenous antioxidant defenses (superoxide dismutase, catalase, glutathione) are upregulated
- Apoptosis markers (caspase-3 activation, Bax/Bcl-2 ratio) are favorably shifted
A 2018 systematic review and meta-analysis by Zheng and colleagues pooled 22 animal studies with 484 animals in which a coronary artery was blocked and then reopened. Astragaloside IV significantly reduced the size of the infarct (the area of dead heart muscle) compared with untreated animals. The quality scores of the studies ranged from only 3 to 6 points on a 10-item checklist, and no human trial was included; the authors describe astragaloside IV as a candidate for future clinical trials in heart attack.
The translation to humans is preliminary — Chinese clinical reports describe giving oral or intravenous astragalus to patients undergoing elective PCI or cardiac surgery, with reduced post-procedure troponin elevation, suggesting reduced myocardial injury. The evidence does not reach the level used for routine peri-procedural protocols, and this remains an area of research interest.
Low-Density Lipoprotein Oxidation and Atherosclerosis
Atherosclerosis — the inflammatory accumulation of cholesterol-rich plaque in arterial walls — is initiated and propagated in large part by oxidized low-density lipoprotein (LDL) particles. Native low-density lipoprotein is poorly atherogenic; oxidized low-density lipoprotein is highly atherogenic, taken up by macrophage scavenger receptors to form lipid-laden foam cells, the cellular foundation of atherosclerotic plaque. Reducing low-density lipoprotein oxidation is one of the mechanisms by which antioxidant interventions theoretically slow atherogenesis.
Astragalus has been studied in animal atherosclerosis models (particularly the apolipoprotein-E knockout mouse and the cholesterol-fed rabbit) with consistent findings of:
- Reduced oxidized low-density lipoprotein formation in plasma
- Reduced atherosclerotic plaque area in aortic specimens
- Reduced macrophage infiltration in plaque lesions
- Reduced inflammatory cytokine expression in plaque (tumor necrosis factor-alpha, interleukin-6 (IL-6), monocyte chemoattractant protein-1)
- Modest improvements in lipid profile (small reductions in total cholesterol and low-density lipoprotein, small increases in high-density lipoprotein (HDL))
The lipid effects are too small to substitute for statin therapy or other proven lipid-lowering interventions, but the antioxidant and anti-inflammatory effects on the vascular wall may complement statin therapy by addressing components of atherogenesis that lipid lowering alone does not fully control. The relationship is similar to the role of Vitamin E and other dietary antioxidants in cardiovascular prevention — supplementary, not primary.
Antiplatelet Activity and Thrombosis Prevention
Astragalus exerts mild antiplatelet activity, inhibiting both ADP-induced and collagen-induced platelet aggregation in laboratory assays. The mechanism appears to involve modulation of cyclooxygenase pathways, calcium signaling within platelets, and increased endothelial prostacyclin production that counters platelet activation.
The clinical significance of this antiplatelet effect cuts both ways:
- Potential benefit — modest reduction in pathologic thrombosis risk, complementary to the platelet effects of omega-3 fatty acids, garlic, ginkgo, and other dietary antiplatelet interventions
- Potential risk — additive bleeding risk when combined with antiplatelet medications (aspirin, clopidogrel, ticagrelor) or anticoagulants (warfarin, rivaroxaban, apixaban, dabigatran)
- Surgical context — herbal-safety guidance commonly lists stopping astragalus at least 2 weeks before scheduled surgery because of the peri-operative bleeding risk
For patients on combined antiplatelet and anticoagulant therapy (dual antiplatelet therapy for recent stent placement, anticoagulant plus aspirin for atrial fibrillation plus coronary disease), the bleeding risks of the medicines already add together, and the antiplatelet effect of astragalus would add to them. The mild magnitude of astragalus's antiplatelet effect means the absolute bleeding risk increase is small, but in people who already carry a high bleeding risk even a small addition matters.
Anthracycline Cardiotoxicity Mitigation
Anthracycline chemotherapy (doxorubicin, epirubicin, daunorubicin, idarubicin) is one of the most effective classes of cancer chemotherapy — central to the management of breast cancer, lymphoma, leukemia, and sarcoma — but it is dose-limited by cumulative cardiotoxicity. The dose-response is essentially linear with cumulative dose, with approximately 5% of patients developing clinical heart failure at 400 mg/m² doxorubicin equivalent and approximately 26% at 550 mg/m². The mechanism is thought to involve oxidative stress from iron-anthracycline complexes, mitochondrial dysfunction, and direct DNA damage in cardiomyocytes.
Astragaloside IV has been studied as a cardioprotectant during anthracycline chemotherapy, with animal studies showing:
- Reduced doxorubicin-induced cardiomyocyte apoptosis
- Preserved cardiac function on echocardiogram after equivalent cumulative doxorubicin doses
- Reduced cardiac troponin elevation during treatment cycles
- Preserved mitochondrial function in cardiac tissue
- Reduced lipid peroxidation in cardiac tissue
Small Chinese clinical reports in patients receiving anthracycline-containing regimens for breast cancer and lymphoma describe reduced subclinical cardiac injury markers (NT-proBNP, troponin) and preserved LVEF on serial echocardiography. The evidence does not reach the level of dexrazoxane (the U.S. Food and Drug Administration-approved pharmaceutical cardioprotectant); supporters cite the mechanistic case and the favorable safety profile reported so far. The cardiotoxicity risk is highest in people with pre-existing reduced LVEF, a very high planned cumulative dose, or prior chest radiation.
Integrative Cardiology — Adding Astragalus to Standard Therapy
The integrative cardiology rationale for adding astragalus to a standard cardiology regimen rests on several considerations:
- Mechanistic complementarity — the effects of astragalus (endothelial NO enhancement, mild inotropy, antifibrotic, antioxidant) complement rather than overlap with the effects of standard pharmaceuticals (renin-angiotensin-aldosterone system (RAAS) inhibition, beta-blockade, mineralocorticoid receptor antagonism, sodium-glucose cotransporter-2 inhibition)
- Safety profile — reported as favorable, with no major end-organ toxicity at usual doses; the drug interactions listed on this page are mostly theoretical rather than measured
- Patient-experienced benefits — many patients report improved exercise tolerance and energy on astragalus, which may improve adherence to the broader cardiac-rehabilitation regimen
- Cardiorenal patients — proposed for people with combined heart failure and chronic kidney disease, on the reasoning that the same molecular mechanism acts in both organs
The caveats are equally important. In the trials and reviews described on this page, astragalus was always given as an add-on to standard heart-failure therapy, never as a substitute for it, so none of this evidence covers replacing standard cardiac medicines with astragalus or any other herbal therapy. Standard heart-failure care tracks NT-proBNP, LVEF on serial echocardiograms, and functional status, and those are the measures by which any added effect would show. The antiplatelet interaction discussed above is the main reason the herb matters to anyone prescribing blood thinners.
Dosing for Cardiovascular Indications
- Standardized capsule extract (cardiovascular indication) — the amount commonly described is 250-500 mg of an extract standardized to 0.3-1.0% astragaloside IV, two to three times daily with meals. Extracts described for cardiovascular use are usually standardized to astragaloside IV rather than to astragalus polysaccharides (APS).
- Sliced root decoction — the traditional preparation is 15-30 g of dried root simmered in water for 20-30 minutes daily
- Tincture (1:3) — 3-5 mL three times daily is the range commonly listed
- Astragalus injection (huang qi zhu she ye) — the form used in Chinese hospital CHF trials, given intravenously by physicians trained in traditional Chinese medicine (TCM); it is not available in the United States outside research settings
- Course duration — cardiovascular effects are described as building slowly over 8-12 weeks, and herbal references usually allow at least 12 weeks before response is judged
- Monitoring — the measures used to judge response in heart-failure care are LVEF, NT-proBNP, functional class and 6-minute walk distance, compared with their starting values; blood pressure and heart rate are checked at routine cardiology visits; the international normalized ratio (INR) blood test tracks warfarin's effect
Cautions (Anticoagulants, Hypotension, Surgery)
- Anticoagulant interaction — the antiplatelet activity discussed above can add to the bleeding risk of warfarin, direct oral anticoagulants (DOACs: rivaroxaban, apixaban, edoxaban, dabigatran), aspirin, clopidogrel, ticagrelor, prasugrel. With warfarin, a change in effect shows up in the international normalized ratio (INR) blood test.
- Hypotension — the endothelial NO-mediated vasodilation can produce additive hypotension in patients on multiple antihypertensives. Dizziness on standing (orthostasis) is the typical sign, particularly in elderly patients and those on alpha-blockers, angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, or calcium-channel blockers.
- Pre-surgical period — herbal-safety guidance commonly lists stopping astragalus at least 2 weeks before scheduled surgery (cardiac or otherwise) because of the bleeding risk and unclear interactions with anesthesia.
- Severe aortic stenosis — theoretical concern about vasodilation in a patient with fixed cardiac output, where a drop in blood pressure is poorly tolerated.
- Lithium therapy — astragalus has mild diuretic effects and could affect lithium clearance, and a change in clearance changes the blood lithium level, which lithium blood tests measure.
- Pregnancy and breastfeeding — safety data in pregnancy and breastfeeding are insufficient.
- Heart transplant recipients — the research raises a theoretical concern: astragalus is described as immune-stimulating, which could work against the immunosuppressant drugs that prevent rejection; no study measuring such an interaction is cited here. Astragalus is contraindicated due to immunosuppression interaction risk and potential rejection.
- Combined with checkpoint-inhibitor immunotherapy — if astragalus is used for cardiac protection during anthracycline therapy in a cancer patient also receiving checkpoint inhibitors, the concern is a theoretical immune-stimulation interaction with the immunotherapy.
Key Research Papers
- Ren S et al. (2013). Pharmacological effects of astragaloside IV: a literature review. Journal of Traditional Chinese Medicine. — PubMed PMID: 24024343
- Zhang WD et al. (2006). Astragaloside IV from Astragalus membranaceus shows cardioprotection during myocardial ischemia in vivo and in vitro. Planta Medica. — PubMed PMID: 16450288
- Fu S, Zhang J, Menniti-Ippolito F, et al. (2011). Huangqi injection (a traditional Chinese patent medicine) for chronic heart failure: a systematic review. PLoS One 6(5):e19604. — PubMed PMID: 21573109
- Dong Z, Zhao P, Xu M, et al. (2017). Astragaloside IV alleviates heart failure via activating PPAR-alpha to switch glycolysis to fatty acid beta-oxidation. Scientific Reports 7(1):2691 (mouse and cell study). — PubMed PMID: 28578382
- Zheng Q, Zhu JZ, Bao XY, et al. (2018). A preclinical systematic review and meta-analysis of astragaloside IV for myocardial ischemia/reperfusion injury. Frontiers in Physiology 9:795 (22 animal studies). — PubMed PMID: 30018562
- Zhang J, Wu C, Gao L, Du G, Qin X (2020). Astragaloside IV derived from Astragalus membranaceus: a research review on the pharmacological effects. Advances in Pharmacology 87:89-112. — PubMed PMID: 32089240
- Packer M, Carver JR, Rodeheffer RJ, et al.; PROMISE Study Research Group (1991). Effect of oral milrinone on mortality in severe chronic heart failure. New England Journal of Medicine 325(21):1468-75. — PubMed PMID: 1944425
- Cuffe MS, Califf RM, Adams KF Jr, et al.; OPTIME-CHF Investigators (2002). Short-term intravenous milrinone for acute exacerbation of chronic heart failure: a randomized controlled trial. JAMA 287(12):1541-7. — PubMed PMID: 11911756
- Deng J, Huang Y, Fu D, Deng Y, Yu K, Lan C (2025). Effects of plant extracts on patients with heart failure: a network meta-analysis of randomized controlled trials. Frontiers in Pharmacology 16:1648811. — PubMed PMID: 41268442
- Rui F, Di Y, Li C, Liu T, Wu Y (2026). The clinical efficacy of Astragalus-containing Chinese patent medicines in the effective treatment of heart failure: a systematic review and network meta-analysis. Medicine (Baltimore) 105(22):e49013. — PubMed PMID: 42216323
PubMed Topic Searches
Connections
- All Herbs
- Astragalus Overview
- Astragalus Benefits Hub
- Astragalus for Immune Function
- Astragalus for Anti-Aging
- Astragalus for Kidney Disease
- Cardiovascular Disease
- Hawthorn
- Garlic
- Turmeric
- Omega-3 Fatty Acids
- Magnesium
- Potassium
- Vitamin K2
- Vitamin E
- Oxidative Stress
- Lipid Panel
- Blood Pressure
- Cancer (Anthracycline Context)
- Heart Failure — the condition the Chinese astragalus-injection trials were built around.
- History