Astragalus for Kidney and Diabetic Nephropathy
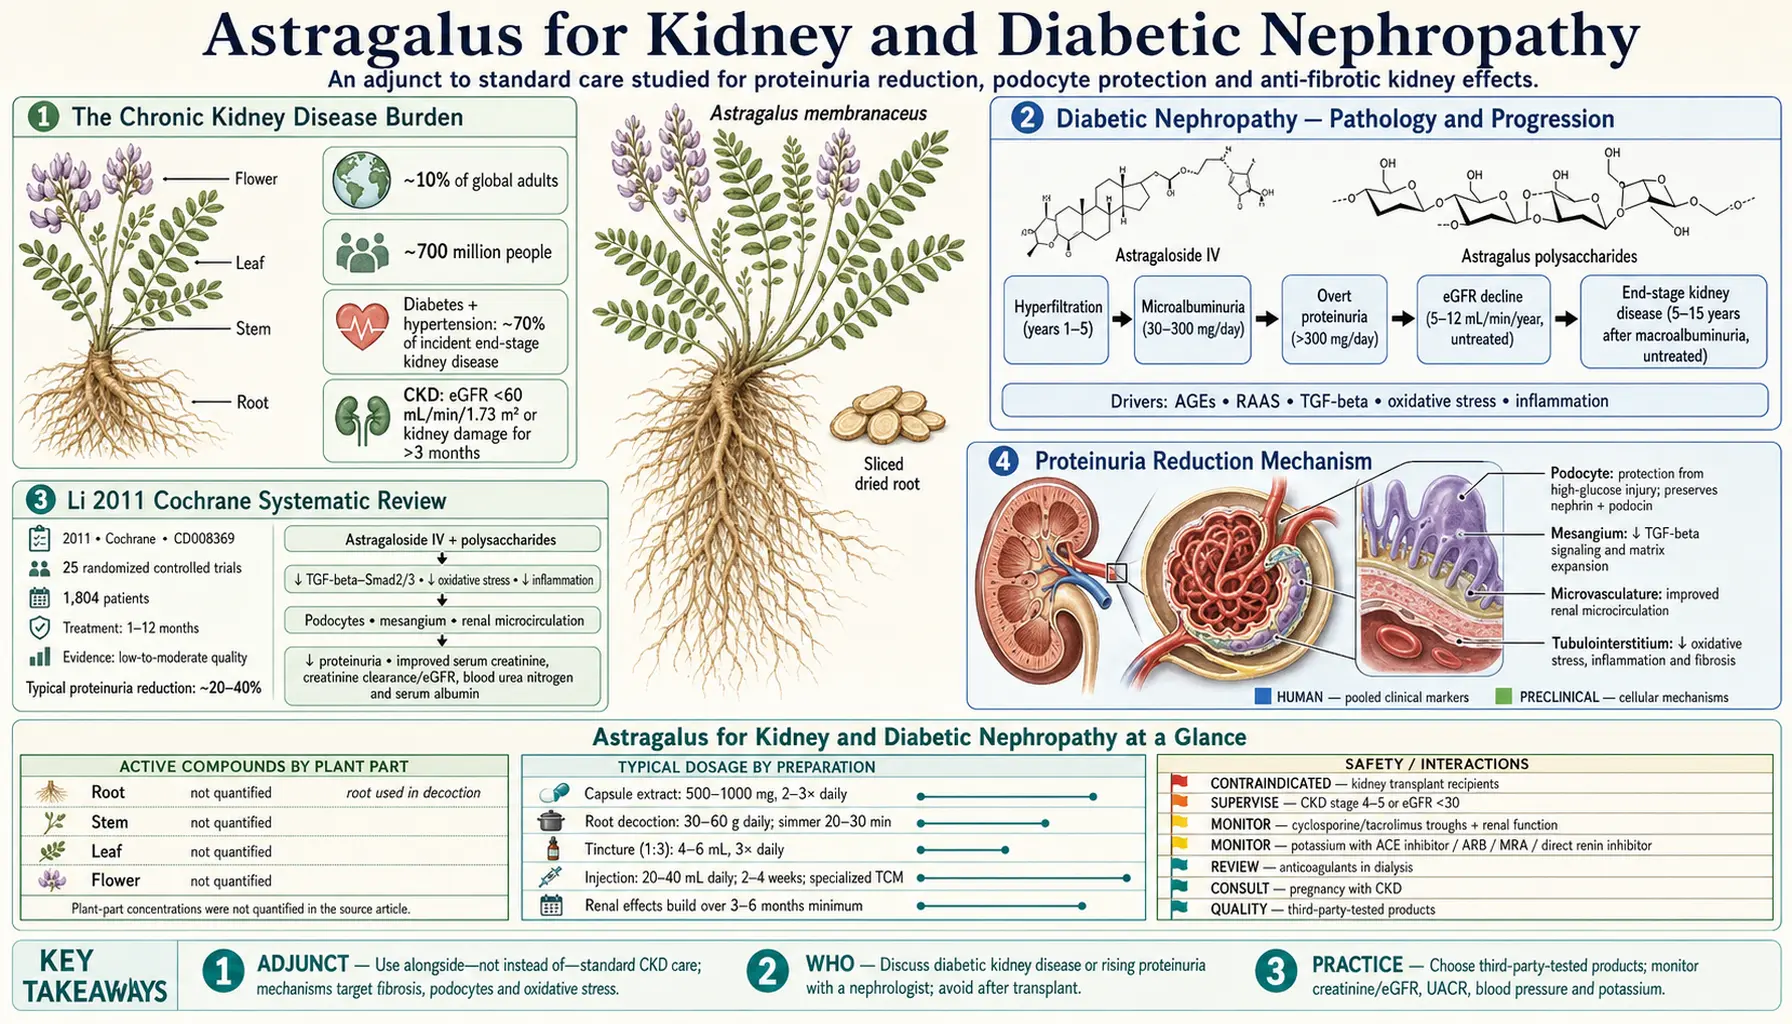
Among the modern uses of Astragalus membranaceus tested in people is chronic kidney disease — and diabetic nephropathy in particular. A 2011 meta-analysis by Li and colleagues in the Journal of Ethnopharmacology pooled 25 studies (21 randomized and 4 semi-randomized controlled trials, 1,804 patients) of astragalus for diabetic kidney disease and reported better kidney lab markers — blood urea nitrogen, serum creatinine, creatinine clearance and urine protein (proteinuria) — and higher serum albumin than in the comparison groups. A separate 2014 Cochrane review of astragalus in chronic kidney disease found lower urine protein and higher hemoglobin and albumin, but rated study quality low overall. These studies measured lab markers only: none reported whether anyone avoided dialysis or lived longer. In cell and animal studies, the proposed mechanism centers on astragaloside IV's inhibition of TGF-beta-driven renal fibrosis, podocyte protection against injury, modulation of inflammatory cytokine production in kidney tissue, improvement in renal microcirculation, and reduction of oxidative stress in kidney parenchyma. The herb is also studied in immunoglobulin A (IgA) nephropathy, nephrotic syndrome, lupus nephritis, and chronic kidney disease of other etiologies. This deep-dive walks through the review evidence, the mechanism, the doses used in studies and in traditional practice, and the cautions for using astragalus alongside angiotensin-converting enzyme inhibitors (ACE inhibitors) and sodium-glucose cotransporter-2 (SGLT2) inhibitors in modern kidney disease care.
Table of Contents
- The Chronic Kidney Disease Burden
- Diabetic Nephropathy — Pathology and Progression
- The Li 2011 Meta-Analysis and the 2014 Cochrane Review
- Proteinuria Reduction Mechanism
- TGF-beta Inhibition and Renal Fibrosis
- Podocyte Protection — The Filtration Barrier
- Broader Renoprotection Mechanisms
- Immunoglobulin A Nephropathy
- Nephrotic Syndrome
- Renal Ischemia-Reperfusion Injury
- Combination with ACE Inhibitors, Angiotensin Receptor Blockers, and Sodium-Glucose Cotransporter-2 Inhibitors
- Dosing for Renal Indications
- Cautions (Advanced Chronic Kidney Disease, Drug Interactions, Hyperkalemia)
- Key Research Papers
- Connections
- Featured Videos
The Chronic Kidney Disease Burden
Chronic kidney disease (CKD) affects approximately 10% of the global adult population — an estimated 700 million people worldwide. Chronic kidney disease is defined by either reduced glomerular filtration rate (estimated glomerular filtration rate (eGFR) less than 60 mL/min/1.73 m² for more than 3 months) or evidence of kidney damage (proteinuria, abnormal urine sediment, structural abnormalities, or biopsy findings) persisting for more than 3 months.
The two leading causes of chronic kidney disease in the developed world are type 2 diabetes and hypertension, together accounting for approximately 70% of incident end-stage kidney disease cases requiring dialysis or transplantation. Other important causes include glomerulonephritis (including immunoglobulin A nephropathy), polycystic kidney disease, lupus nephritis, and chronic interstitial nephritis from medication exposure.
The natural history of chronic kidney disease is one of gradual estimated glomerular filtration rate decline (typically 1-5 mL/min/year in stable patients on optimal therapy, faster in poorly controlled diabetes or untreated hypertension) culminating in either death from cardiovascular disease (the most common outcome) or transition to renal replacement therapy — dialysis or kidney transplantation. The economic and human burden is enormous, and any intervention that meaningfully slows chronic kidney disease progression can have substantial public health impact.
Standard chronic kidney disease care emphasizes:
- Blood pressure control to target (typically less than 130/80 mmHg)
- Renin-angiotensin-aldosterone-system (RAAS) blockade with angiotensin-converting enzyme inhibitors or angiotensin receptor blockers (ARBs) for any patient with proteinuria
- Sodium-glucose cotransporter-2 inhibitors (canagliflozin, dapagliflozin, empagliflozin) for diabetic and non-diabetic chronic kidney disease — one of the most important recent additions to kidney disease therapeutics
- Glycemic control in diabetic patients
- Avoidance of nephrotoxic medications when possible (nonsteroidal anti-inflammatory drugs (NSAIDs), intravenous contrast, certain antibiotics)
- Management of chronic kidney disease-associated complications (anemia, bone-mineral disease, acidosis, hyperkalemia)
- Cardiovascular risk reduction (statin therapy, smoking cessation)
In the trials reviewed below, astragalus was given as an add-on to standard care, not in place of it. For more context on kidney disease, see our Kidney Disease page and the Kidney Function lab tests.
Diabetic Nephropathy — Pathology and Progression
Diabetic nephropathy — technically diabetic kidney disease — develops in approximately 30-40% of patients with type 1 or long-standing type 2 diabetes. The pathology involves a characteristic sequence of changes:
- Glomerular hyperfiltration (years 1-5 after diabetes diagnosis) — paradoxical increase in estimated glomerular filtration rate driven by efferent arteriolar constriction
- Microalbuminuria (urinary albumin 30-300 mg/day) — the earliest clinically detectable sign of glomerular injury
- Macroalbuminuria / overt proteinuria (urinary albumin >300 mg/day) — established diabetic nephropathy
- Progressive estimated glomerular filtration rate decline — typically 5-12 mL/min/year in untreated overt diabetic nephropathy
- End-stage kidney disease — requiring dialysis or transplant, typically 5-15 years after onset of macroalbuminuria in untreated patients
The underlying pathology involves glomerular basement membrane thickening, mesangial matrix expansion, podocyte injury and loss, nodular glomerulosclerosis (the pathognomonic Kimmelstiel-Wilson lesion), and progressive tubulointerstitial fibrosis. The molecular drivers include hyperglycemia-induced advanced glycation end-products (AGEs), renal RAAS activation, glomerular hypertension, increased TGF-beta signaling driving fibrosis, oxidative stress, and chronic low-grade inflammation in kidney tissue.
Modern therapy has substantially slowed the natural history. The classical IDNT (Lewis 2001) and RENAAL (Brenner 2001) trials of angiotensin receptor blocker (ARB) therapy in type 2 diabetic nephropathy showed approximately 20% reduction in the composite endpoint of doubling of serum creatinine or end-stage kidney disease. The more recent trials of sodium-glucose cotransporter-2 inhibitors reported further reductions in composite kidney-failure-or-death endpoints: 30% with canagliflozin in CREDENCE (Perkovic 2019; hazard ratio 0.70) and 39% with dapagliflozin in DAPA-CKD (Heerspink 2020; hazard ratio 0.61). Astragalus has been studied as a third additive therapy on top of optimized ACE-inhibitor/angiotensin receptor blocker and increasingly with sodium-glucose cotransporter-2-inhibitor backbones.
The Li 2011 Meta-Analysis and the 2014 Cochrane Review
Two different reviews are described here. The first is a 2011 meta-analysis by Li M, Wang W, Xue J, Gu Y and Lin S, "Meta-analysis of the clinical value of Astragalus membranaceus in diabetic nephropathy," published in the Journal of Ethnopharmacology (it is not a Cochrane review). It pooled 25 studies — 21 randomized controlled trials and 4 semi-randomized controlled trials — with 1,804 patients with diabetic nephropathy (945 in the astragalus groups and 859 in the control groups).
Key findings:
- Reduction in urinary protein in the astragalus groups compared with control
- Improvement in serum creatinine in the astragalus arm
- Improvement in creatinine clearance
- Reduction in blood urea nitrogen
- Improvement in serum albumin (consistent with reduced protein loss)
- Most trials used the injectable form of astragalus (huang qi zhu she ye); some used oral astragalus or astragalus-containing Chinese herbal formulations
- Treatment duration in pooled trials ranged from 1 month to 12 months
The methodological limitations were significant — many included trials were small, open-label, conducted in Chinese hospital settings with non-standardized astragalus preparations, and had variable outcome definitions. The Li 2011 abstract gives no quality grade for the evidence.
The second is the Cochrane systematic review by Zhang and colleagues (published October 2014), which looked at astragalus for chronic kidney disease of any cause. It included 22 small studies with 1,323 people, 241 of them on dialysis. In plain numbers: urine protein over 24 hours fell by about half a gram a day on average (mean difference −0.53 g per 24 hours; 10 studies, 640 people, with results that varied widely between studies), serum albumin rose by 3.55 g/L (9 studies, 522 people) and hemoglobin rose by 9.51 g/L (4 studies, 222 people). Results on kidney function were inconsistent. What is not known: none of the 22 studies reported the outcomes the reviewers had set as most important — how long until someone needed dialysis, and how many people died. The reviewers rated study quality low overall and concluded that "definitive conclusions could not be made based on available evidence." Six of the studies reported that no side effects were seen; the other 16 did not report on side effects.
A 2024 meta-analysis in Renal Failure pooled 32 randomized trials with 2,462 people with stage III diabetic kidney disease (1,244 on the combination, 1,218 on the drugs alone). Adding astragalus to the standard blood-pressure kidney drugs — angiotensin-converting enzyme inhibitors or angiotensin receptor blockers — lowered urine protein excretion, serum creatinine, blood urea nitrogen and HbA1c (a three-month blood-sugar average) more than the drugs alone. The authors found signs of possible publication bias (missing unfavourable studies) for serum creatinine, 24-hour urine protein and overall response rate, and wrote that rigorous large, multi-center, double-blind trials are still needed.
Subsequent network meta-analyses comparing different traditional Chinese medicine interventions for diabetic nephropathy have consistently identified astragalus-based formulations as among the most effective.
In short, these studies measured lab markers only (urine protein, creatinine, albumin); none measured whether astragalus delays dialysis or prolongs life. Major Western nephrology guidelines have not incorporated astragalus; integrative practitioners describe using it as an add-on to standard therapy.
Proteinuria Reduction Mechanism
Proteinuria — the leakage of plasma proteins (most importantly albumin) into the urine — is the single most important prognostic biomarker in chronic kidney disease. Higher proteinuria predicts faster estimated glomerular filtration rate decline, higher cardiovascular mortality, and greater risk of progression to end-stage kidney disease. Reduction in proteinuria with therapy is associated with better long-term kidney outcomes — the rationale behind the standard practice of titrating angiotensin-converting enzyme inhibitors and angiotensin receptor blockers to maximum tolerated dose to achieve maximum proteinuria reduction.
The astragalus effect on proteinuria operates through multiple complementary mechanisms:
- Podocyte protection — podocytes are the specialized cells that form the glomerular filtration barrier. Astragaloside IV protects podocytes against high-glucose-induced injury and apoptosis (discussed further below).
- Reduced TGF-beta-driven mesangial expansion — mesangial matrix expansion increases intraglomerular pressure, which in turn drives more proteinuria. Astragaloside IV reduces TGF-beta signaling and mesangial expansion.
- Improved renal microcirculation — better afferent and efferent arteriolar function reduces glomerular hypertension, a key driver of progressive proteinuria.
- Antioxidant effects — reduced oxidative damage to the glomerular basement membrane preserves filtration barrier integrity.
- Possible direct effect on slit-diaphragm proteins — some preclinical studies suggest astragaloside IV preserves nephrin and podocin expression, the key proteins forming the slit diaphragm between podocyte foot processes.
In the 2014 Cochrane review, 24-hour urine protein was on average about half a gram a day lower with astragalus (−0.53 g/24 h). In the 2024 Renal Failure meta-analysis, astragalus added to angiotensin-converting enzyme inhibitors or angiotensin receptor blockers lowered urine protein more than the drugs alone, which suggests that astragalus may act on pathways the RAAS-blocker drugs do not fully control.
TGF-beta Inhibition and Renal Fibrosis
Transforming growth factor beta (TGF-beta) is the master cytokine driving chronic kidney fibrosis. TGF-beta is upregulated in diabetic kidneys, in chronically hypertensive kidneys, and in kidneys with chronic immune-mediated injury. The downstream effects include:
- Activation of resident fibroblasts and their differentiation into matrix-producing myofibroblasts
- Increased collagen and extracellular matrix protein deposition in the renal interstitium
- Epithelial-to-mesenchymal transition of tubular epithelial cells, contributing to the fibroblast pool
- Mesangial matrix expansion within glomeruli
- Progressive replacement of functional kidney tissue with non-functional scar tissue
TGF-beta is one of the most validated drug targets in nephrology, but direct TGF-beta inhibitors have so far failed in clinical trials (the FG-3019 anti-CTGF antibody and pirfenidone trials showed limited renal benefit, though pirfenidone is approved for pulmonary fibrosis). The challenge is selectively blocking TGF-beta's pathologic fibrosis-driving effects without disrupting its many other physiologic roles (immune regulation, wound healing, embryonic development).
In cell and animal studies, astragaloside IV has been reported to reduce TGF-beta signaling in kidney tissue through several mechanisms:
- Reduced TGF-beta receptor expression on renal cells
- Inhibition of TGF-beta-induced Smad2/Smad3 phosphorylation (the downstream signaling cascade)
- Reduced expression of connective tissue growth factor (CTGF), a downstream TGF-beta effector
- Reduced expression of matrix-producing genes (collagen type I, fibronectin, tissue inhibitors of metalloproteinase)
- Inhibition of epithelial-to-mesenchymal transition in tubular cells
The net effect in animal kidney disease models is reduced interstitial fibrosis, reduced glomerular sclerosis, and slower progression of structural kidney damage. In people, the Li 2011 meta-analysis and the later reviews report changes in lab markers (urine protein, creatinine) only; whether the anti-scarring effect seen in animals also happens in human kidneys was not measured.
Podocyte Protection — The Filtration Barrier
Podocytes are highly specialized epithelial cells that wrap around the glomerular capillaries and form the final layer of the glomerular filtration barrier. Their interdigitating foot processes are connected by "slit diaphragms" specialized intercellular junctions composed of nephrin, podocin, CD2-associated protein, and other proteins — that form the molecular size-selective filter that prevents albumin and larger proteins from entering the urine.
Podocyte injury is central to the pathology of multiple kidney diseases including diabetic nephropathy, focal segmental glomerulosclerosis, membranous nephropathy, and minimal change disease. Once injured, podocytes can detach from the glomerular basement membrane and are lost in the urine — and because mature podocytes have very limited proliferative capacity, podocyte loss is largely irreversible. Below a critical threshold of podocyte density, progressive glomerulosclerosis becomes inevitable.
Multiple preclinical studies have documented podocyte-protective effects of astragalus and astragaloside IV:
- Reduced high-glucose-induced podocyte apoptosis in cultured podocyte cell lines — a 2012 study by Gui and colleagues found this in cultured podocytes and in diabetic rats, where 14 weeks of astragaloside IV also reduced albumin in the urine and podocyte foot process effacement
- Preserved nephrin and podocin expression in diabetic animal kidney specimens
- Reduced podocyte foot process effacement on electron microscopy
- Maintained autophagy function in podocytes (autophagy is a key mechanism of podocyte stress tolerance)
- Reduced podocyte detachment as measured by urinary podocyte count
The clinical correlate is the proteinuria reduction discussed above. Patients with active podocyte injury (manifest as new or increasing proteinuria) may be the subgroup most likely to benefit from astragalus addition to their regimen.
Broader Renoprotection Mechanisms
Beyond the podocyte-protection and TGF-beta-inhibition pathways, cell and animal studies report several other kidney-protective effects of astragalus:
- Antioxidant action in kidney tissue — reduced lipid peroxidation, increased renal superoxide dismutase (SOD) and catalase activity, increased glutathione content. Oxidative stress is a major driver of progressive kidney damage in diabetes and hypertension.
- Anti-inflammatory effect — reduced tumor necrosis factor-alpha, interleukin-1-beta, interleukin-6 (IL-6), and monocyte chemoattractant protein-1 expression in kidney tissue. Chronic low-grade inflammation drives progressive nephron loss.
- Improved renal microcirculation — endothelial nitric oxide synthase upregulation in the renal vasculature improves intrarenal blood flow and reduces local ischemic injury.
- Mesangial cell protection — reduced mesangial matrix expansion (the cellular basis of diabetic glomerulosclerosis).
- Modulation of advanced glycation end-product (AGE) formation — reduced AGE accumulation in kidney tissue and reduced expression of the AGE receptor RAGE.
- Improved renal autophagy — preserved autophagy in tubular epithelial cells, important for clearance of damaged organelles and stress tolerance.
The collective effect is a multi-pathway kidney-protective profile that complements (rather than overlaps with) the mechanisms of standard pharmaceutical therapy. RAAS blockers reduce intraglomerular pressure; sodium-glucose cotransporter-2 inhibitors reduce hyperfiltration and provide metabolic benefits; astragalus addresses fibrosis, podocyte injury, microcirculation, and oxidative stress. This proposed complementarity is the rationale practitioners give for combining them.
Immunoglobulin A Nephropathy
Immunoglobulin A nephropathy (Berger's disease) is the most common primary glomerulonephritis worldwide and one of the leading causes of end-stage kidney disease in young adults. The pathology involves mesangial deposition of IgA1-containing immune complexes, mesangial proliferation, complement activation, and progressive glomerular and tubulointerstitial injury. Standard therapy includes RAAS blockade for proteinuria reduction, fish oil for its anti-inflammatory effect (modest evidence base), and immunosuppression (corticosteroids, mycophenolate, or cyclophosphamide) in patients with severe or progressive disease.
Astragalus has been studied in immunoglobulin A nephropathy in several Chinese trials, with findings suggesting:
- Reduced proteinuria comparable to the effect seen in diabetic nephropathy
- Reduced hematuria (microscopic blood in urine, a hallmark of immunoglobulin A nephropathy activity)
- Slowed estimated glomerular filtration rate decline in long-term follow-up
- Possible reduction in serum immunoglobulin A levels (though the clinical relevance of this is uncertain)
The mechanism appears to overlap with the diabetic-nephropathy mechanism (podocyte protection, anti-fibrotic, antioxidant) plus possible direct effects on the immune-complex deposition process. The evidence base is smaller than for diabetic nephropathy — immunoglobulin A nephropathy is less common, and most of the published trials are small and from single Chinese centers — and practitioners who use astragalus here describe it as an add-on to standard therapy.
Nephrotic Syndrome
Nephrotic syndrome is the clinical pattern of heavy proteinuria (more than 3.5 g/day), hypoalbuminemia, edema, and hyperlipidemia, caused by any condition that produces severe glomerular injury — including minimal change disease, focal segmental glomerulosclerosis (FSGS), membranous nephropathy, diabetic nephropathy in advanced stage, and amyloidosis. Standard therapy depends on the underlying etiology and typically includes RAAS blockade, immunosuppression (corticosteroids in minimal change and many secondary causes; cyclosporine, tacrolimus, rituximab, or mycophenolate for refractory cases), and supportive care for edema and hyperlipidemia.
Astragalus has been studied as adjunctive therapy in nephrotic syndrome, particularly in cases that are poorly responsive to or relapsing on standard immunosuppression. The available evidence suggests:
- Reduction in proteinuria when added to standard therapy
- Possible steroid-sparing effect (reduced corticosteroid dose required to maintain remission)
- Improvement in serum albumin
- Reduced edema severity
The mechanism includes the podocyte-protective effect (particularly relevant in minimal change and FSGS where podocyte injury is central), plus the immune-modulating effects of astragalus polysaccharides that may help control the underlying immune dysregulation in idiopathic nephrotic syndromes. In the studies described, astragalus was used alongside standard immunosuppression, not in place of it.
Renal Ischemia-Reperfusion Injury
Acute kidney injury (AKI) from renal ischemia-reperfusion is a common clinical problem — it occurs after cardiac surgery with cardiopulmonary bypass, after kidney transplantation (the donor kidney experiences ischemia during procurement and storage and then reperfusion in the recipient), during shock states, and after intravenous contrast exposure in vulnerable patients. Acute kidney injury doubles short-term mortality risk and substantially accelerates progression to chronic kidney disease.
Astragaloside IV has been studied extensively in animal renal ischemia-reperfusion models with consistent findings of:
- Reduced post-ischemia serum creatinine elevation
- Reduced tubular necrosis on histology
- Preserved mitochondrial function in renal tubular cells
- Reduced apoptosis markers in injured kidney tissue
- Reduced inflammatory cell infiltration
- Reduced expression of injury markers (KIM-1, NGAL)
Clinical translation to humans is preliminary — small trials of perioperative astragalus during cardiac surgery have suggested reduced post-operative acute kidney injury incidence, but the evidence is not yet sufficient for routine clinical adoption. In kidney transplantation, astragalus is sometimes used in Chinese practice as part of perioperative regimens to support graft function recovery, though Western transplant programs generally do not incorporate herbal therapy due to the complex immunosuppression and rejection management issues.
Combination with ACE Inhibitors, Angiotensin Receptor Blockers, and Sodium-Glucose Cotransporter-2 Inhibitors
Modern diabetic kidney disease care is built on a foundation of angiotensin-converting enzyme inhibitors or angiotensin receptor blockers for proteinuria reduction, plus sodium-glucose cotransporter-2 inhibitors for additional kidney protection and cardiovascular risk reduction. Astragalus has been studied in combination with these agents in multiple trials.
The combination ACE-inhibitor plus astragalus has consistently shown additive benefit in proteinuria reduction compared to ACE-inhibitor alone in diabetic nephropathy trials. The mechanism is mechanistically complementary: angiotensin-converting enzyme inhibitors reduce intraglomerular pressure through efferent arteriolar dilation, while astragalus addresses the fibrosis, podocyte injury, and oxidative stress mechanisms not directly affected by RAAS blockade. The combination is generally well-tolerated, with no documented adverse interactions.
The combination with sodium-glucose cotransporter-2 inhibitors has been less extensively studied because sodium-glucose cotransporter-2 inhibitors are a newer addition to kidney disease therapy (CREDENCE published in 2019, DAPA-CKD in 2020). On mechanistic grounds the combination is expected to be additive — sodium-glucose cotransporter-2 inhibitors reduce hyperfiltration through tubuloglomerular feedback and provide metabolic benefits, while astragalus addresses parallel fibrosis and inflammatory pathways. Initial small trials of the combination have supported additive benefit.
Standard monitoring for these combinations covers the expected effects of each agent: blood pressure with the angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker, glucose and ketones with the sodium-glucose cotransporter-2 inhibitor, kidney function and potassium with both, and proteinuria as the integrated efficacy biomarker. Astragalus does not change the laboratory monitoring requirements but adds an additional therapeutic agent to the regimen.
Dosing for Renal Indications
- Standardized capsule extract (renal indication) — 500-1000 mg of an extract standardized to either polysaccharide content (40%) or astragaloside IV content (0.3-1.0%), two to three times daily with meals. Both fractions appear to contribute to renal benefit.
- Sliced root decoction — 30-60 g of dried root daily, simmered in water for 20-30 minutes. The higher end of this range is used in classical Chinese renal-tonic prescriptions.
- Tincture (1:3) — 4-6 mL three times daily
- Astragalus injection (huang qi zhu she ye) — the form used in the majority of Chinese diabetic nephropathy trials. Not generally available outside specialized TCM clinical settings. Intravenous doses in trials have ranged from 20-40 mL daily for 2-4 weeks at a time, often repeated as cycles.
- Course duration — practitioners report that renal effects build over 3-6 months minimum, and integrative practitioners describe long-term continuous use given the chronic progressive nature of chronic kidney disease.
- Monitoring — standard kidney disease care checks serum creatinine and estimated glomerular filtration rate every 3-6 months, urinary albumin-to-creatinine ratio (UACR) every 3-6 months, blood pressure at all clinic visits, potassium and bicarbonate every 6-12 months. Astragalus does not change the standard kidney disease monitoring schedule.
Cautions (Advanced Chronic Kidney Disease, Drug Interactions, Hyperkalemia)
- Advanced chronic kidney disease (stage 4-5) — for people with estimated glomerular filtration rate less than 30 mL/min, the concerns raised are theoretical but serious: herbal product purity (potential kidney-toxic contaminants), build-up of the herb's compounds because failing kidneys clear them more slowly, and unclear effects on potassium balance.
- Kidney transplant recipients — astragalus is contraindicated in solid-organ transplant patients due to immunosuppression interaction risk and potential rejection.
- Cyclosporine and tacrolimus interactions — both calcineurin-inhibitor immunosuppressants are nephrotoxic at high blood levels and metabolized by cytochrome P450 3A4 (CYP3A4). Astragalus may modulate cytochrome P450 3A4 activity (in vitro evidence is mixed); with combined use, the drugs' trough blood levels and kidney function are the measures that show a problem.
- Combined hyperkalemia risk — angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, mineralocorticoid receptor antagonists (spironolactone, eplerenone), and direct renin inhibitors all increase serum potassium. Astragalus itself does not strongly affect potassium; potassium rises with these drugs whether or not astragalus is added.
- Anticoagulants in dialysis patients — dialysis patients often receive heparin during sessions and may be on warfarin or direct oral anticoagulants for atrial fibrillation. The concern raised is an antiplatelet interaction: astragalus may add to the bleeding effect of these drugs.
- Pregnancy with kidney disease — safety data for astragalus in pregnancy are lacking, and pregnancy with chronic kidney disease is already a high-risk pregnancy.
- Herbal product quality — chronic kidney disease patients are vulnerable to nephrotoxic contaminants in poorly regulated herbal products. Third-party tested single-herb products carry less of this risk than imported herbal mixtures of uncertain composition.
- Aristolochic acid contamination — the cautionary tale here is the historical aristolochic acid nephropathy outbreak from contaminated Chinese herbal weight-loss products in the 1990s. Pure single-herb astragalus has not been associated with aristolochic acid contamination; the risk lies in mislabelled or mixed products.
- Acute kidney injury or rapidly progressive glomerulonephritis — these are urgent kidney conditions that hospitals treat as emergencies. Astragalus has not been tested as the main treatment for sudden kidney conditions.
Key Research Papers
- Li M, Wang W, Xue J, Gu Y, Lin S (2011). Meta-analysis of the clinical value of Astragalus membranaceus in diabetic nephropathy. Journal of Ethnopharmacology, 133(2), 412-419. — PubMed PMID: 20951192
- Zhang HW et al. (2014). Astragalus (a traditional Chinese medicine) for treating chronic kidney disease. Cochrane Database of Systematic Reviews. — PubMed PMID: 25335553
- Lin YQ, Yu F, Chen HJ, Deng YR, Lin J, Xu Y, Zheng X, Zhang JW, Liu JF (2024). Efficacy of astragalus combined with renin-angiotensin-aldosterone system blockers in the treatment of stage III diabetic nephropathy: a systematic review and meta-analysis. Renal Failure, 46(2), 2359033. — PubMed PMID: 38836372
- Gui D, Guo Y, Wang F, Liu W, Chen J, Chen Y, Huang J, Wang N (2012). Astragaloside IV, a novel antioxidant, prevents glucose-induced podocyte apoptosis in vitro and in vivo. PLoS One, 7(6), e39824. — PubMed PMID: 22745830
- Brenner BM et al. (2001). Effects of losartan on renal and cardiovascular outcomes in patients with type 2 diabetes and nephropathy (RENAAL). NEJM. — PubMed PMID: 11565518
- Perkovic V et al. (2019). Canagliflozin and renal outcomes in type 2 diabetes and nephropathy (CREDENCE). NEJM. — PubMed PMID: 30990260
- Heerspink HJL et al. (2020). Dapagliflozin in patients with chronic kidney disease (DAPA-CKD). NEJM, 383(15), 1436-1446. — PubMed PMID: 32970396
PubMed Topic Searches
Connections
- All Herbs
- Astragalus Overview
- Astragalus Benefits Hub
- Astragalus for Immune Function
- Astragalus for Cardiovascular Health
- Astragalus for Anti-Aging
- Kidney Disease
- Kidney Function Tests
- Type 2 Diabetes
- Hemoglobin A1c
- Berberine
- Stinging Nettle
- Turmeric
- Omega-3 Fatty Acids
- Vitamin D3
- Magnesium
- Potassium
- Oxidative Stress
- Cardiovascular Disease
- Diabetic Nephropathy — the disease this page's review evidence and astragaloside IV mechanisms concern.
- History