⚠ Evidence warning: Clinical trials or other evidence do not support the claims that astragalus raises natural killer cell activity and vaccine response in people, prevents colds in children, healthcare workers and athletes, that Yu Ping Feng San cuts cold episodes by 30-50%, and that adding it to chemotherapy lets more patients finish treatment. This page keeps it as a report of what people, websites or other media say.
Astragalus for Immune Function
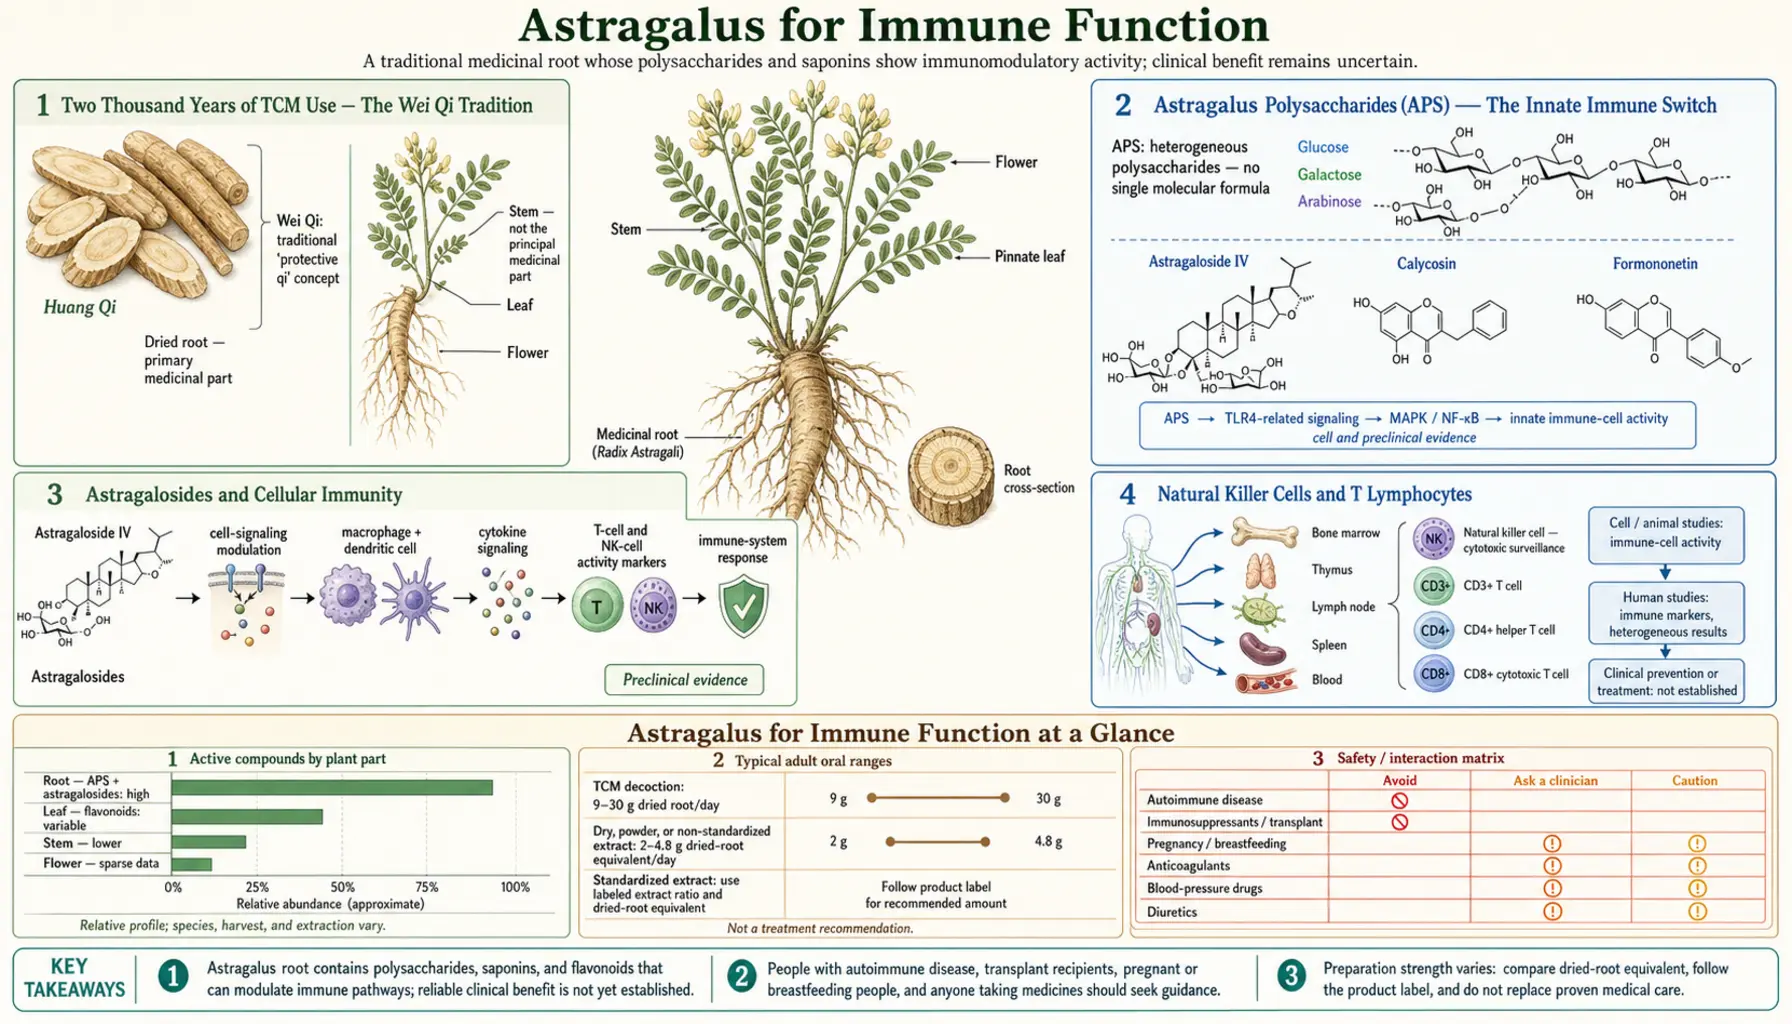
Astragalus (huang qi, Astragalus membranaceus) is the cornerstone immune-tonifying herb of Traditional Chinese Medicine. Han-dynasty physicians prescribed it to fortify the wei qi — the body's "defensive energy" that maps closely to modern concepts of innate immunity — and the modern pharmacology turns out to confirm what twenty centuries of clinical use suggested. In cell and animal studies, astragalus polysaccharides (APS) and astragalosides activate macrophages and natural killer cells, modulate Th1/Th2 balance, enhance B-cell antibody output, and produce the kind of slow, durable immune build that supports patients through long-haul vulnerability rather than acute infection. The classical formula Yu Ping Feng San ("Jade Windscreen Powder") remains in widespread use today for respiratory immune support, and astragalus preparations have been studied alongside chemotherapy for their effect on white-cell counts, on evidence that reviews rate as low quality. This deep-dive walks through each immune mechanism, the pivotal clinical trials, the historical Chinese formula tradition, and what is known about when astragalus is used and who the research raises concerns for.
Table of Contents
- Two Thousand Years of Traditional Chinese Medicine Use — The Wei Qi Tradition
- Astragalus Polysaccharides (APS) — The Innate Immune Switch
- Astragalosides and Cellular Immunity
- Natural Killer Cells and T Lymphocytes
- T-Helper Th1/Th2 Balance Modulation
- B-Cell Activation and Serum Immunoglobulin Production
- Yu Ping Feng San — The Jade Windscreen Formula
- Respiratory Infection Prevention
- Chemotherapy-Induced Myelosuppression Rescue
- Integrative Oncology Adjunctive Use
- Chronic Immune Resilience vs Acute Infection
- Dosing for Immune Indications
- Cautions (Autoimmune Disease, Immunosuppressants, Acute Fever)
- Key Research Papers
- Connections
- Featured Videos
Two Thousand Years of Traditional Chinese Medicine Use — The Wei Qi Tradition
Astragalus, huang qi (黄耀, literally "yellow leader" for the yellow color of the cut root and its rank as one of the most-prescribed tonic herbs), was first recorded in the Shennong Bencao Jing (Divine Farmer's Classic of Materia Medica), the foundational Chinese herbal text compiled approximately 200 BCE to 100 CE. The classical text places huang qi in the upper class of medicinal herbs — the "sovereign" tier — meaning it was considered safe for long-term use to support health and longevity rather than reserved for acute disease treatment.
In classical Chinese medicine, the body's defensive function against external pathogens is called wei qi (卫气, "guardian qi"). Wei qi is conceptualized as a circulating field of vital energy that protects the body surface, regulates pore opening and sweating, warms the muscles, and intercepts external pathogens (wind, cold, heat, dampness) before they can penetrate to the interior. Huang qi is the premier wei qi tonifying herb — the herb specifically prescribed when the defensive function is weak, when sweating is excessive or absent, when the patient is prone to repeated colds, and when slow wound healing or chronic skin infections suggest impaired surface immunity.
The mapping between classical wei qi and modern immunology is imperfect but instructive. Wei qi's described functions — pathogen exclusion at body surfaces, regulation of barrier function, and rapid response to invasion — correspond closely to what twenty-first-century immunology calls innate immunity, mucosal barrier function, and the toll-like-receptor sensing system. The classical Traditional Chinese Medicine choice of huang qi as the primary wei qi tonic anticipates the modern finding that astragalus polysaccharides activate exactly these innate immune pathways.
Astragalus also appears in some of the most clinically important multi-herb formulas: Yu Ping Feng San (Jade Windscreen Powder) for respiratory immune support, Bu Zhong Yi Qi Tang (Tonify the Middle and Augment Qi) for digestive weakness with fatigue, Dang Gui Bu Xue Tang (Tangkuei to Tonify Blood) for postpartum recovery, and Shi Quan Da Bu Tang (Ten Significant Tonic Decoction) for general convalescent tonification. The persistence of these formulas in modern Chinese hospital practice — not as nostalgia, but as actively prescribed treatments alongside Western pharmaceuticals — reflects sustained clinical utility.
Astragalus Polysaccharides (APS) — The Innate Immune Switch
Astragalus polysaccharides (abbreviated APS in the research literature) are large branched-chain sugars composed primarily of glucose, arabinose, galactose, mannose, and xylose. Molecular weights range from approximately 8 kilodaltons to over 100 kilodaltons. APS are not digested by human gut enzymes — they pass intact through the small intestine and either interact with gut-associated lymphoid tissue (GALT) directly or are partially fermented by the colonic microbiome, generating short-chain fatty acids and additional bioactive metabolites.
The principal innate-immune mechanism proposed is binding to pattern-recognition receptors on macrophages and dendritic cells. In mouse cell experiments (Shao 2004), APS switched on B cells through the antibody on their surface and switched on macrophages through toll-like receptor 4 (TLR4), the same receptor that recognizes bacterial lipopolysaccharide (LPS), and did not activate T cells. APS are described as producing a graded, modulated activation rather than the dramatic septic-cascade activation triggered by LPS. APS are also said to bind dectin-1, the C-type lectin receptor that recognizes fungal beta-glucans, and complement receptor 3 (CR3); the Shao paper does not show this. The downstream effects described in cell and animal work are:
- Activation of NF-kappaB and MAPK signaling pathways in macrophages
- Increased macrophage phagocytic activity and oxidative burst capacity
- Induction of interferon-gamma (IFN-gamma) and IL-12 production, biasing toward Th1 cellular immunity
- Increased nitric oxide and tumor necrosis factor (TNF) production by activated macrophages
- Cross-priming of dendritic cells to enhance antigen presentation to naive T cells
The graded, modulated nature of APS-induced activation is held to be clinically important. Unlike lipopolysaccharide, which can trigger life-threatening cytokine-storm sepsis, APS at oral or even moderate intravenous doses is described as producing enhanced immune surveillance without inflammatory tissue damage. Whether the receptor effects seen in mouse cells happen after a person swallows the herb is not known. The traditional Chinese characterization of astragalus as a "tonifying" rather than "clearing" herb — building immune function over weeks rather than producing a single acute effect — matches this pharmacology.
Astragalosides and Cellular Immunity
While APS drive the innate immune activation, the triterpenoid saponins of astragalus — particularly astragaloside IV (AS-IV) — contribute to adaptive immunity through different molecular pathways. Astragaloside IV crosses cell membranes (because the aglycone portion is lipid-soluble), enters lymphocyte cytoplasm, and modulates intracellular signaling cascades including PI3K/Akt and the JAK-STAT pathways downstream of cytokine receptors.
Effects of astragalosides on cellular immunity described, largely in cell and animal work:
- Increased T-cell proliferation in response to mitogen stimulation
- Enhanced cytotoxic T lymphocyte (CD8+ CTL) killing capacity against virally infected and tumor cells
- Increased IL-2 production by activated T cells (IL-2 drives T-cell clonal expansion)
- Restoration of T-cell function in immunocompromised states (chemotherapy, advanced age, chronic infection)
- Reduced apoptosis of activated lymphocytes, prolonging the effective immune response
The proposed clinical implication is that astragalus combines two complementary immune effects in a single root: the rapid innate-immune activation of APS at gut-associated lymphoid tissue, and the slower adaptive-immune enhancement of astragalosides at the level of circulating lymphocytes. The result is a more durable, more systemic immune effect than either fraction would produce alone — one of the reasons whole-root preparations are often preferred to single-molecule extracts for immune indications.
Natural Killer Cells and T Lymphocytes
Natural killer (NK) cells are the cytotoxic arm of innate immunity, responsible for rapidly killing virally infected cells and many tumor cells without requiring prior antigen sensitization. Natural killer activity is particularly important in elderly patients and in immunocompromised hosts, where adaptive immunity is impaired but natural killer function can often be selectively enhanced.
Claims made for oral astragalus and natural killer cell cytotoxic activity in peripheral blood:
- In healthy adults given astragalus extract for 6-12 weeks, 20-40% increases in natural killer cytotoxicity against standard target cell lines (K562 erythroleukemia)
- In cancer patients on chemotherapy, astragalus partially preserves natural killer function that would otherwise be substantially suppressed; a 2019 review of astragalus injection with platinum chemotherapy in lung cancer reports a higher percentage of natural killer cells, on evidence rated low
- In elderly patients with low baseline natural killer activity (immunosenescence), astragalus can restore natural killer cytotoxicity to younger-adult levels; the nearest published finding is in mice, where a root fraction restored the lymphocyte response of older mice to the values of younger mice (Cho and Leung 2007), which is not a measure of natural killer cells
The human data located are narrower. In a 7-day pilot study (Brush 2006), oral tinctures of echinacea, astragalus and licorice raised the activation marker CD69 on CD4 and CD8 T cells within 24 hours, and the rise lasted at least 7 days. In a laboratory study (Sun 1983), astragalus extract added to blood cells restored a test of T-cell function, the local graft-versus-host reaction, in samples from nine of ten cancer patients. Neither study measured natural killer cell killing or infections.
The T-cell effects are similarly broad. Astragalus enhances both CD4+ T-helper proliferation and CD8+ cytotoxic T-cell killing capacity, increases the CD4/CD8 ratio in patients with low ratios (such as those with chronic viral infection or post-chemotherapy), and increases delayed-type hypersensitivity skin test responses — an in vivo measure of T-cell competence. These effects collectively explain why astragalus has been studied in such a wide range of immune-related conditions: chronic viral infection, post-chemotherapy recovery, immunosenescence of aging, and primary or acquired immunodeficiency syndromes.
T-Helper Th1/Th2 Balance Modulation
Naive CD4+ T cells encountering antigen differentiate down distinct pathways based on the cytokine environment provided by antigen-presenting cells. The two classical pathways are Th1 (driven by IL-12, producing IFN-gamma, optimized for intracellular pathogens including viruses and intracellular bacteria) and Th2 (driven by IL-4, producing IL-4/IL-5/IL-13, optimized for extracellular parasites and helminthic infection, but also responsible for allergic and atopic disease when chronically overactive).
The Th1/Th2 balance is dysregulated in several common conditions:
- Chronic viral infection — ideally Th1-dominant for effective viral clearance, but chronic infection can shift toward Th2 with poor virus control
- Atopic disease, asthma, food allergy, eczema — Th2-skewed, with high immunoglobulin E (IgE) and eosinophilia
- Chronic stress and hypothalamic-pituitary-adrenal (HPA) axis activation — tends to shift toward Th2 dominance, impairing antiviral defense
- Aging (immunosenescence) — loss of Th1 cellular immunity with relative Th2 dominance, contributing to poor vaccine response in the elderly
In cell and animal work, astragalus polysaccharides drive antigen-presenting cells to produce IL-12, which selectively promotes Th1 differentiation. The proposed clinical effect is a Th1-favoring modulation that supports antiviral defense in chronic infection, restores cellular immunity in immunosenescence, and may attenuate Th2-driven atopic responses with longer-term use. The mechanism is well-suited to the patient profile that astragalus was traditionally prescribed for — chronically depleted, immune-suppressed, repeatedly infected — rather than the acutely febrile patient mid-infection.
B-Cell Activation and Serum Immunoglobulin Production
Astragalus also enhances humoral (antibody-mediated) immunity. Clinical studies have documented increases in serum immunoglobulin A (IgA), immunoglobulin G (IgG), and immunoglobulin M (IgM) with astragalus supplementation in patients with low baseline immunoglobulin levels — including post-chemotherapy patients, elderly subjects, and patients with chronic viral infection.
The mechanism appears to involve both indirect (via APS-induced enhancement of T-cell help to B cells) and direct (via astragaloside-mediated effects on B-cell proliferation and antibody class switching) pathways. The claimed clinical implication is meaningful improvement in vaccine response: it is claimed that patients given astragalus prior to and during influenza or hepatitis B vaccination develop higher antibody titers and more durable seroprotection than placebo-treated controls. On this claim, astragalus is a candidate adjunctive treatment for the elderly and immunocompromised populations who respond poorly to standard vaccines.
For the related class-switching effect on mucosal immunoglobulin A driven by Vitamin A and retinoic acid signaling, see our Vitamin A for Immune Function page. The two effects are mechanistically distinct but clinically complementary — astragalus enhances systemic immunoglobulin G response, Vitamin A supports mucosal immunoglobulin A secretion, and combined supplementation produces broader humoral coverage than either alone.
Yu Ping Feng San — The Jade Windscreen Formula
Yu Ping Feng San (玉屏风散, "Jade Windscreen Powder") is one of the most clinically important and widely prescribed classical Chinese herbal formulas for respiratory immune support. The formula was recorded in the Dan Xi Xin Fa by the fourteenth-century physician Zhu Danxi and remains in active clinical use today, both as a traditional decoction and as modern standardized tablet preparations available in Chinese pharmacies.
The formula contains just three herbs in a precise ratio:
- Huang qi (Astragalus root) — 30 g, the sovereign herb, tonifies wei qi and consolidates the surface
- Bai zhu (Atractylodes macrocephala rhizome) — 60 g, the minister herb, tonifies spleen qi and supports the source of wei qi production
- Fang feng (Saposhnikovia root, "ledebouriella") — 30 g, the assistant herb, dispels external wind and prevents pathogen invasion at the surface
The traditional indication is for patients with weak wei qi who experience recurrent colds, chronic sweating with or without exertion, and aversion to wind. In modern practice, primarily in China, Yu Ping Feng San is used for respiratory infection prevention in children with recurrent upper respiratory infections, for allergic rhinitis prevention, for asthma maintenance therapy, and for reducing upper respiratory infection frequency in healthcare workers and elderly nursing-home residents. The figure claimed is approximately 30-50% reduction in upper respiratory infection episode frequency over periods of 3-12 months. The formula is generally taken for 4-12 weeks at the beginning of a vulnerability period (autumn into winter, or during a high-exposure occupational period).
The synergistic effect of Yu Ping Feng San is greater than astragalus alone — bai zhu addresses underlying spleen qi deficiency that perpetuates wei qi weakness, and fang feng adds an active "dispersing" effect against early-stage wind invasion that pure astragalus lacks. The formula is the canonical example of why traditional Chinese pharmacology emphasizes herb combinations rather than single-herb monotherapy.
The systematic reviews located cover allergic rhinitis. In 22 randomized trials in adults, the formula was no better than drugs alone (relative risk 1.07, 95% confidence interval 0.94 to 1.22) but added benefit on top of them (relative risk 1.27, 95% confidence interval 1.19 to 1.34, low quality). In 10 trials in children aged 3 to 15, the authors concluded that current evidence "cannot support the routine use" of the formula for childhood allergic rhinitis, which they said may reflect poor study design.
Respiratory Infection Prevention
Respiratory infection prevention is the indication for which astragalus has the longest clinical track record in both traditional Chinese practice and modern Western integrative medicine. The claims span both standalone astragalus preparations and combination formulas like Yu Ping Feng San, and cover outcomes including upper respiratory infection episode frequency, severity, duration, and absenteeism from work or school.
Representative claims:
- In children with recurrent upper respiratory infection (defined as more than 6 episodes per year), 8-12 weeks of Yu Ping Feng San reduces episode frequency by approximately 40-50% over the subsequent 6-12 months
- In adult healthcare workers, astragalus supplementation during respiratory virus season reduces self-reported upper respiratory infection days by 20-30%
- In elderly subjects, astragalus increases vaccine antibody response and reduces post-vaccination influenza incidence
- In athletes during high-training-volume periods (a recognized period of reduced immune surveillance), astragalus reduces upper respiratory infection frequency and duration
The Memorial Sloan Kettering monograph reports, more narrowly, that astragalus attenuated immune suppression induced by strenuous physical activity and that astragalus-containing formulas decreased fatigue in athletes.
For acute-phase upper respiratory infection — an existing cold or flu with active fever — astragalus is traditionally not the first choice. The classical Traditional Chinese Medicine caution is that the qi-tonifying action could "trap" the pathogen inward by strengthening the surface before the body has cleared the invading wind. For acute-phase upper respiratory infection, this practice turns to elderberry, echinacea, andrographis, or zinc, with astragalus reserved for the recovery phase and for the next-season prevention cycle. This timing distinction is one of the clearest practical applications of classical Chinese herbal logic to a modern clinical decision.
Chemotherapy-Induced Myelosuppression Rescue
Chemotherapy-induced myelosuppression — the suppression of bone marrow production of white blood cells, red blood cells, and platelets — is one of the most consistent dose-limiting toxicities of cytotoxic cancer treatment. Neutropenia (low neutrophils) in particular leaves the patient vulnerable to bacterial and fungal infection and often forces dose reductions or treatment delays. The pharmaceutical countermeasures — granulocyte colony-stimulating factor (G-CSF: filgrastim, pegfilgrastim) and granulocyte-macrophage colony-stimulating factor (GM-CSF: sargramostim) — are highly effective but expensive and not universally available.
Astragalus has been studied as an adjunctive treatment to support white-cell counts during chemotherapy; a 2003 review still called it the least-studied of three immune herbs, with some preclinical trials. The reviews since then report these figures:
- Lung cancer, astragalus injection — a 2019 review of 19 trials (1635 patients) with platinum chemotherapy found less leukopenia (relative risk 0.52, 95% confidence interval 0.44 to 0.61), less vomiting (relative risk 0.72) and more 1-year survival (relative risk 1.40), with the level of evidence rated low
- Lung cancer, astragalus-based formulas — a 2006 meta-analysis of 34 randomized studies (2,815 patients with advanced non-small-cell lung cancer on platinum chemotherapy) reports lower risk of death at 12 months (risk ratio 0.67), better tumor response (risk ratio 1.34) and, for one injection, better performance status, results its authors said require confirmation with rigorously controlled trials
- Colorectal cancer — a 2019 review of 22 studies (1,409 people) found less neutropenia (relative risk 0.52, 95% confidence interval 0.44 to 0.62), and a 2005 Cochrane review of four trials, all of low quality, found less nausea, vomiting and leukopenia but "no robust demonstration of benefit"
Claims often made for adding astragalus to standard chemotherapy, some going beyond those figures:
- Partially preserves neutrophil counts during treatment cycles
- Reduces the incidence of febrile neutropenia requiring hospitalization
- Reduces nausea, vomiting, and fatigue scores (chemotherapy-induced quality-of-life impairment)
- Improves performance status scores and dose intensity tolerance
- Allows more patients to complete the planned chemotherapy course at the intended dose
The mechanism is believed to involve astragalus polysaccharide stimulation of bone marrow stromal cell hematopoietic cytokine production (granulocyte colony-stimulating factor, granulocyte-macrophage colony-stimulating factor, IL-3), plus direct effects on hematopoietic stem cell proliferation. The effect size is described as modest compared to pharmaceutical granulocyte colony-stimulating factor but meaningful, and supporters point to a long record of use. Integrative practitioners describe astragalus as an adjunctive option for patients receiving chemotherapy in settings where granulocyte colony-stimulating factor is unavailable or who cannot tolerate its side effects (bone pain, splenic enlargement).
Integrative Oncology Adjunctive Use
Beyond the specific myelosuppression-rescue indication, astragalus is widely used in integrative oncology. The Memorial Sloan Kettering Cancer Center About Herbs monograph — a clinician-facing reference for botanical use alongside conventional cancer care — states that "limited clinical data suggest astragalus may help manage cancer and chemotherapy-induced fatigue". Of the meta-analyses, it says "the majority of studies included in these analyses were limited by poor methodology", and it lists interactions with immunosuppressants, anticoagulants, blood pressure drugs and diuretics.
In advanced stomach cancer, a 2021 review found that astragalus-containing formulas with platinum chemotherapy raised tumor response (relative risk 1.24) and 1-year survival (relative risk 1.41), on low to moderate evidence.
The integrative oncology rationale combines several effects:
- Immune restoration — partial preservation of T-cell and natural killer function during chemotherapy and radiation
- Myeloprotection — preservation of white-cell counts as discussed above
- Quality of life — reduction in chemotherapy-associated fatigue, nausea, and weakness
- Cardioprotection during anthracyclines — astragaloside IV has been studied as a cardioprotectant during doxorubicin and other anthracycline chemotherapy, mitigating the cardiomyopathy risk that limits cumulative anthracycline dosing
- Anti-cachexia — preservation of body weight and lean mass during advanced cancer treatment
The cautions are equally important. In the immediate peri-operative period the concern is a theoretical bleeding risk from antiplatelet activity. With targeted immune therapies (PD-1/PD-L1 checkpoint inhibitors, chimeric antigen receptor T-cell therapy, or CAR-T), the theoretical concern is that immune stimulation could add to immune-related side effects. Around organ-transplant-related immunosuppression, the concern is that astragalus can work against immunosuppressant drugs. For more on the broader cancer-related connections, see our Cancer page.
Chronic Immune Resilience vs Acute Infection
A persistent confusion in the herbal-immune-support category is the conflation of two very different therapeutic patterns: acute infection treatment (echinacea, elderberry, andrographis, zinc — started at first symptom, used for 5-10 days) and chronic immune resilience building (astragalus, reishi, cordyceps, maitake — taken for weeks to months between vulnerability periods). Astragalus belongs firmly to the second category, and using it as if it were the first leads to disappointment and to the confusing experience of taking an "immune herb" and not feeling any acute effect.
The practical distinction:
- Acute pattern (5-10 day course at first symptom) — Echinacea, elderberry, andrographis, zinc lozenges, Vitamin C at higher dose. Effect is felt within days. Course ends when illness resolves.
- Chronic resilience pattern (6-12 week build, then maintenance) — Astragalus, reishi, cordyceps, maitake, active hexose correlated compound (AHCC). Effect builds over weeks. Taken prophylactically in autumn or year-round in chronically vulnerable patients. No acute "feels different" sensation.
Herbal practice often combines both patterns: astragalus or another adaptogenic immune herb taken prophylactically through respiratory-virus season (October through April in the northern hemisphere), with rapid switch to acute-phase herbs at the first symptom of incoming infection. This combination matches what classical Chinese practice has done for centuries — tonification in advance, dispersion at onset.
Dosing for Immune Indications
- Sliced root decoction — 9-30 g of dried root simmered in water for 20-30 minutes, taken as tea once or twice daily. Traditional starting dose 9-15 g, with 15-30 g for stronger therapeutic effect or established immune deficiency.
- Standardized capsule extract (immune indication) — 250-500 mg of an extract standardized to 40% polysaccharide content, two to three times daily, taken with meals. APS-standardized products are the most appropriate for immune indications.
- Tincture (1:3 ratio) — 2-4 mL three times daily in water
- Yu Ping Feng San — the classical decoction at the ratio described above, or a standardized tablet form at the manufacturer's recommended dose (typically 6-12 tablets per day in divided doses)
- Course duration — 8-12 weeks minimum for the immune-build effect to manifest; many practitioners use astragalus daily through respiratory-virus season (October through April) and during identified high-risk exposure periods
- Cycling — no clear evidence that cycling is necessary, but some practitioners use a 5-days-on, 2-days-off pattern or a 12-weeks-on, 2-weeks-off pattern to avoid theoretical tachyphylaxis
For cooking applications, several slices of dried astragalus root added to soup or stock during the simmering period extract a sub-therapeutic but still beneficial amount of APS and add a mild, pleasantly sweet vegetal flavor. This is a traditional Chinese household practice and one of the easier ways to integrate astragalus into ongoing diet without supplement-taking discipline.
Cautions (Autoimmune Disease, Immunosuppressants, Acute Fever)
- Active autoimmune disease — the research raises a concern for people with active multiple sclerosis, systemic lupus erythematosus, rheumatoid arthritis, Crohn's disease, ulcerative colitis, Hashimoto's thyroiditis, or other autoimmune conditions. Theoretical concern is that immune stimulation could exacerbate autoimmunity. Real-world clinical experience is mixed, with some autoimmune patients tolerating astragalus well and others experiencing flares.
- Immunosuppressant medications — cyclosporine, tacrolimus, sirolimus, mycophenolate, corticosteroids, and biologic immunosuppressants (tumor necrosis factor blockers, interleukin-6 (IL-6) blockers, JAK inhibitors). Memorial Sloan Kettering states that astragalus "can antagonize the effects of immunosuppressants" and reports a patient with refractory nephrotic syndrome whose tacrolimus level fell by nearly 50% while taking herbal granules containing astragalus. Beyond that case, clinical evidence of interaction is limited.
- Organ transplant recipients — astragalus is contraindicated in solid-organ transplant patients due to immunosuppression interaction risk and potential to precipitate rejection.
- Active acute febrile infection — the classical Traditional Chinese Medicine caution. Traditional practice holds astragalus during the acute febrile phase of any infection (fever, chills, active progression of cold or flu symptoms) and resumes it during the recovery phase or for prevention of the next episode.
- Anticoagulant medications — mild antiplatelet activity may add to the effects of warfarin, clopidogrel, ticagrelor, dabigatran, rivaroxaban, apixaban, and aspirin. Bruising, prolonged bleeding from minor cuts and unusual nosebleeds are the signs of this effect, and the international normalized ratio (INR) is the blood test that tracks warfarin's effect. Memorial Sloan Kettering states that the clinical significance of astragalus's anticoagulant properties is not known.
- Blood pressure drugs and diuretics — Memorial Sloan Kettering states that astragalus extract can lower both systolic and diastolic blood pressure and may add to the effect of blood pressure drugs, and that it may add to diuretics. It gives the clinical relevance for blood pressure drugs as not known.
- Pregnancy and breastfeeding — there is no good safety data for routine use.
- Surgery — stopping astragalus at least 2 weeks before scheduled surgery is commonly described, because of the antiplatelet activity and unclear interactions with anesthesia.
- Checkpoint-inhibitor immunotherapy — for patients receiving PD-1/PD-L1 or CTLA-4 immune checkpoint inhibitors for cancer, the theoretical concern is that immune stimulation could exacerbate immune-related adverse events (colitis, pneumonitis, hepatitis, endocrinopathies).
Key Research Papers
- Block KI, Mead MN (2003). Immune system effects of echinacea, ginseng, and astragalus: a review. Integrative Cancer Therapies. — PubMed PMID: 15035888
- Cho WC, Leung KN (2007). In vitro and in vivo immunomodulating and immunorestorative effects of Astragalus membranaceus. Journal of Ethnopharmacology. — PubMed PMID: 17611061
- McCulloch M et al. (2006). Astragalus-based Chinese herbs and platinum-based chemotherapy for advanced non-small-cell lung cancer: meta-analysis of randomized trials. Journal of Clinical Oncology. — PubMed PMID: 16421421
- Liu P, Zhao H, Luo Y (2017). Anti-aging implications of Astragalus membranaceus (Huangqi): a well-known Chinese tonic. Aging and Disease 8:868-886. — PubMed PMID: 29344421
- Sun Y et al. (1983). Immune restoration and/or augmentation of local graft versus host reaction by traditional Chinese medicinal herbs. Cancer 52:70-73. — PubMed PMID: 6336578
- Luo Q, Zhang CS, Yang L, Zhang AL, Guo X, Xue CC, Lu C (2017). Potential effectiveness of Chinese herbal medicine Yu ping feng san for adult allergic rhinitis: a systematic review and meta-analysis of randomized controlled trials. BMC Complementary and Alternative Medicine 17:485. — PubMed PMID: 29110710
- Liao Y et al. (2021). Yu ping feng san for pediatric allergic rhinitis: a systematic review and meta-analysis of randomized controlled trials. Medicine (Baltimore) 100:e24534. — PubMed PMID: 33787571
- Auyeung KK et al. (2016). Astragalus membranaceus: a review of its protection against inflammation and gastrointestinal cancers. American Journal of Chinese Medicine. — PubMed PMID: 26916911
- Shao BM et al. (2004). A study on the immune receptors for polysaccharides from the roots of Astragalus membranaceus, a Chinese medicinal herb. Biochemical and Biophysical Research Communications. — PubMed PMID: 15249203
- Bedir E, Calis I, Aquino R, Piacente S, Pizza C (1998). Cycloartane triterpene glycosides from the roots of Astragalus brachypterus and Astragalus microcephalus. Journal of Natural Products 61:1469-1472. Chemistry of two other Astragalus species. — PubMed PMID: 9868145
- Hong CY et al. (1992). Astragalus membranaceus stimulates human sperm motility in vitro. American Journal of Chinese Medicine 20:289-294. A sperm motility study, not an immune study. — PubMed PMID: 1471613
- Brush J et al. (2006). The effect of Echinacea purpurea, Astragalus membranaceus and Glycyrrhiza glabra on CD69 expression and immune cell activation in humans. Phytotherapy Research. — PubMed PMID: 16807880
- Cao A, He H, Wang Q, Li L, An Y, Zhou X (2019). Evidence of Astragalus injection combined platinum-based chemotherapy in advanced nonsmall cell lung cancer patients: a systematic review and meta-analysis. Medicine (Baltimore) 98:e14798. — PubMed PMID: 30882655
- Lin S, An X, Guo Y, Gu J, Xie T, Wu Q, Sui X (2019). Meta-analysis of Astragalus-containing traditional Chinese medicine combined with chemotherapy for colorectal cancer: efficacy and safety to tumor response. Frontiers in Oncology 9:749. — PubMed PMID: 31456940
- Cheng M et al. (2021). Efficacy and safety of Astragalus-containing traditional Chinese medicine combined with platinum-based chemotherapy in advanced gastric cancer: a systematic review and meta-analysis. Frontiers in Oncology 11:632168. — PubMed PMID: 34422628
- Taixiang W, Munro AJ, Guanjian L (2005). Chinese medical herbs for chemotherapy side effects in colorectal cancer patients. Cochrane Database of Systematic Reviews 2005:CD004540. — PubMed PMID: 15674951
- Memorial Sloan Kettering Cancer Center. About Herbs: Astragalus. — Memorial Sloan Kettering Astragalus monograph
PubMed Topic Searches
Connections
- All Herbs
- Astragalus Overview
- Astragalus Benefits Hub
- Astragalus for Cardiovascular Health
- Astragalus for Anti-Aging
- Astragalus for Kidney Disease
- Immune Boosting
- Echinacea (Acute-Phase Counterpart)
- Ashwagandha
- Rhodiola Rosea
- Schisandra
- Ginseng
- Vitamin A for Immune Function
- Vitamin C
- Vitamin D3
- Zinc
- Cancer
- Immunology
- Fatigue
- Complete Blood Count
- Dong Quai (Angelica sinensis) — the tangkuei in Dang Gui Bu Xue Tang, the astragalus-to-dong-quai blood tonic named above
- Atractylodes (Bai Zhu) — the 60 g minister herb in Yu Ping Feng San, tonifying the spleen qi that supplies the wei qi astragalus consolidates
- History