Milk Thistle for Liver Protection and Detox
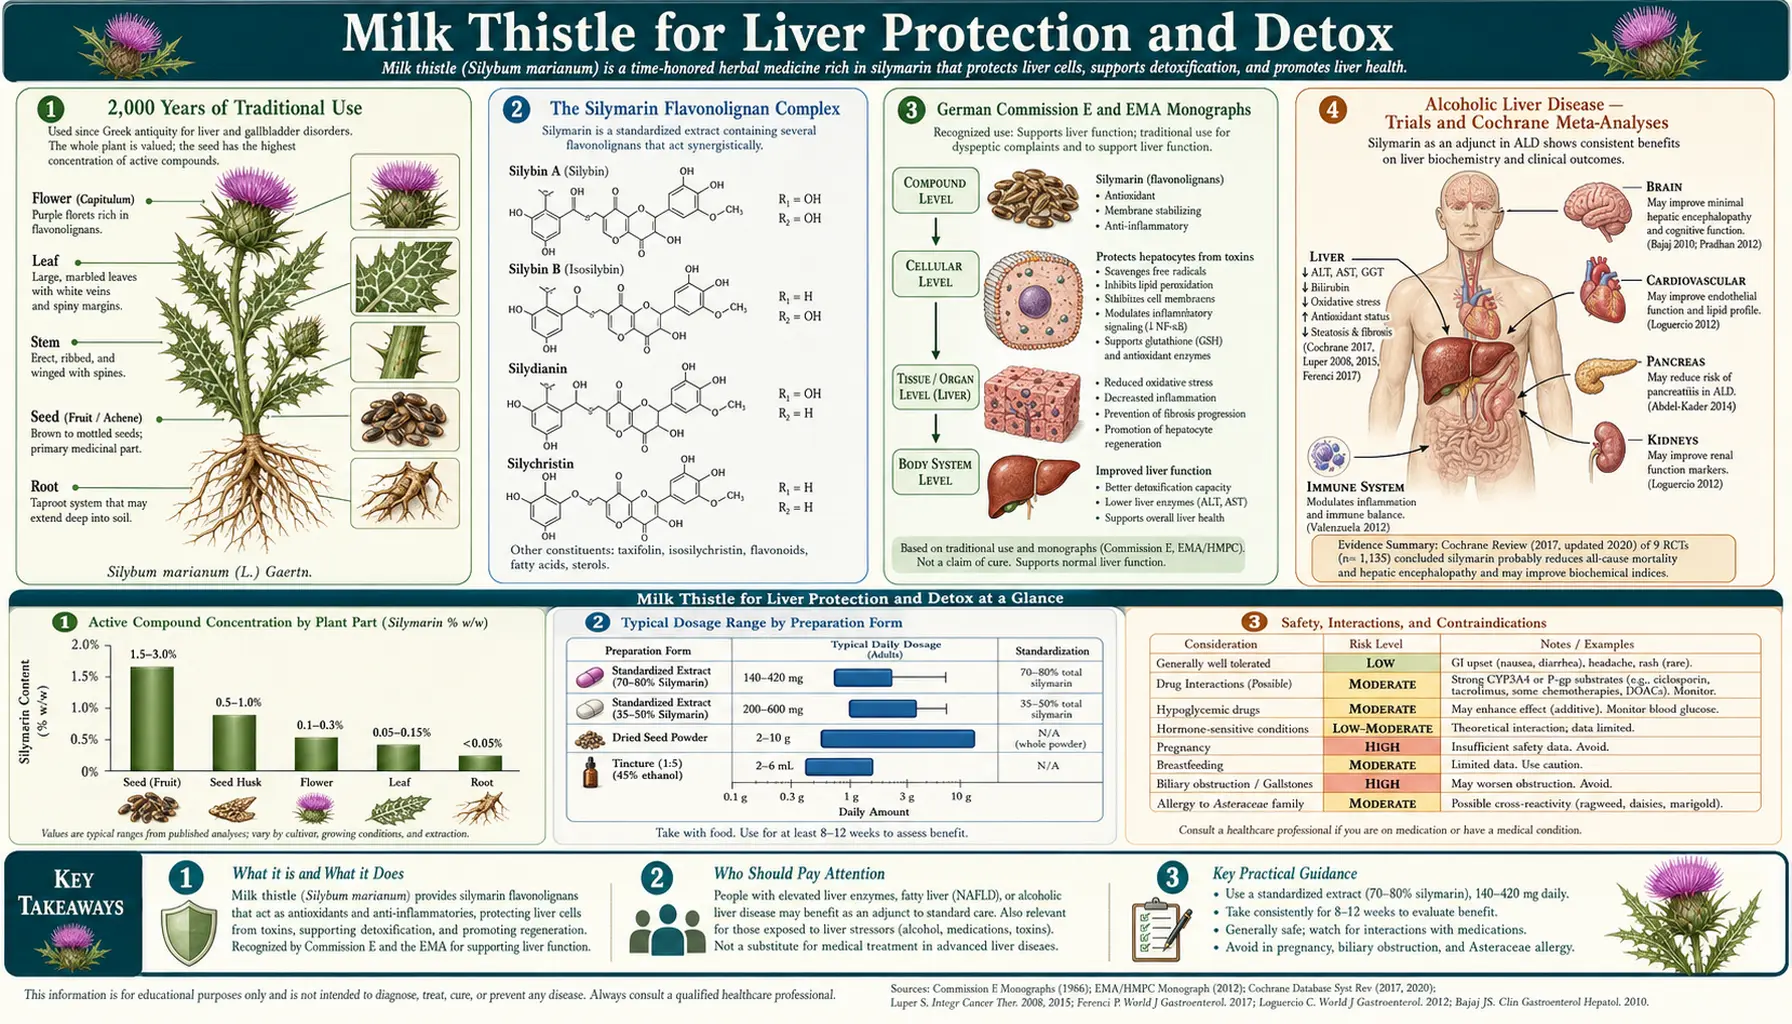
Milk thistle's reputation as the premier herbal liver protectant rests on three pillars of evidence: a 2,000-year traditional-use record stretching back to Dioscorides (1st century CE) and Pliny the Elder; modern regulatory recognition by the German Commission E (1986), the European Medicines Agency HMPC monograph (2018), and the WHO traditional-medicine monograph; and a uniquely dramatic clinical application as the standard-of-care intravenous antidote for Amanita phalloides (death cap mushroom) poisoning across Europe (as silibinin), where a review of observational reports gives mortality under 10% in treated patients, against more than 20% with penicillin-based treatment. The active extract, silymarin, is a flavonolignan complex composed principally of silybin A and silybin B (collectively called "silibinin") together with isosilybin, silychristin, and silydianin — with silybin alone accounting for 60-70% of standardized silymarin and serving as the principal active compound. This page walks through the historical record, the regulatory monographs, the Cochrane meta-analyses of alcoholic liver disease and cirrhosis, the mushroom-poisoning antidote story, and the hepatocyte membrane-stabilization plus protein-synthesis-stimulation mechanism that drives both damage prevention and active regeneration.
Table of Contents
- 2,000 Years of Traditional Use
- The Silymarin Flavonolignan Complex
- German Commission E and European Medicines Agency Monographs
- Alcoholic Liver Disease — Trials and Cochrane Meta-Analyses
- Cirrhosis Trials (Ferenci, Pares, Lucena)
- Non-Alcoholic Fatty Liver Disease (NAFLD/Non-Alcoholic Steatohepatitis)
- The Amanita phalloides Antidote — Intravenous Silibinin
- Hepatic Regeneration Mechanism (RNA Polymerase I)
- Hepatocyte Membrane Stabilization (OATP1B3 Block)
- Dosing Protocols, Forms, and Bioavailability
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
2,000 Years of Traditional Use
Milk thistle (Silybum marianum; Asteraceae family) is native to the Mediterranean basin and parts of Asia. The plant's common name derives from the white veining on its leaves, which medieval Christian tradition attributed to drops of the Virgin Mary's milk — the species epithet marianum shares the same etymology.
The earliest documented medicinal use comes from Dioscorides, the 1st-century-CE Greek physician whose De Materia Medica remained the dominant Western pharmacopeia for over fifteen centuries. Dioscorides recommended the plant for "carrying off bile." Pliny the Elder, writing in the same era, recorded its use specifically for liver complaints and as a "blood purifier."
The herb appears continuously throughout the European medieval and Renaissance herbal tradition. Nicholas Culpeper, the 17th-century English herbalist, wrote that milk thistle was "as good as any in the world for dropsy, opening obstructions of the liver and spleen." German physicians made it the central liver herb in the 18th and 19th centuries, and Eclectic medicine in 19th-century America (King's American Dispensatory) listed it as a specific for hepatic congestion and "passive congestion of the abdominal viscera."
The modern phytochemistry began in 1968 when Wagner and colleagues at the University of Munich isolated and characterized the silymarin complex. The first standardized pharmaceutical silymarin preparation was introduced in Germany in 1969 and has remained the reference standard against which other preparations are compared. Its standardization to 70-80% silymarin (with defined silybin content) is the basis on which essentially all rigorous clinical trials have been conducted.
The Silymarin Flavonolignan Complex
"Silymarin" refers not to a single molecule but to a defined mixture of flavonolignans extracted from the seed (more precisely, the achene, the dry indehiscent fruit) of Silybum marianum. Standardized silymarin contains:
- Silybin A and silybin B — the two diastereoisomers of the principal active compound, together called "silibinin." Silybin accounts for approximately 60-70% of total silymarin. Silybin A and B are present in roughly equimolar amounts and share the same flavonolignan skeleton (3-O,4-O-bond between taxifolin and coniferyl alcohol) but differ in stereochemistry at two chiral centers. Both isomers are pharmacologically active, with silybin B slightly more potent on most assays.
- Isosilybin A and B — structural isomers of silybin (regiochemistry of the flavonolignan bond differs), accounting for approximately 5-10% of silymarin. Isosilybin is the most potent inhibitor of prostate cancer cell proliferation in vitro and is being investigated as a possible cancer chemopreventive.
- Silychristin — approximately 10-20% of silymarin, with strong direct antioxidant activity and a distinct mechanism affecting thyroid hormone transport via MCT8.
- Silydianin — approximately 5% of silymarin, less studied than the others but contributes to the overall antioxidant capacity.
- Taxifolin (dihydroquercetin) — the flavonoid precursor of all the flavonolignans, present in small amounts and contributing flavonoid antioxidant activity.
The pharmacologic implication of this complex composition is that preparation matters enormously. Generic supermarket capsules labeled "milk thistle" with no silymarin assay may contain anywhere from 30% to 80% silymarin and may have wildly different silybin fractions. Clinical trials use standardized preparations — usually a standardized pharmaceutical silymarin extract, a silybin–phosphatidylcholine complex, or pharmacopoeial-grade silymarin meeting the European Pharmacopoeia monograph — and results from those trials do not automatically carry over to unstandardized commercial products.
German Commission E and European Medicines Agency Monographs
Milk thistle has monographs from both the German Commission E (1986) and the European Medicines Agency HMPC (Committee on Herbal Medicinal Products, finalized 2018). The Commission E approved it for liver indications; the European Medicines Agency monograph rests on traditional use only.
The German Commission E Monograph (1986) lists milk thistle fruit and standardized silymarin extract as approved for:
- Dyspeptic complaints
- Toxic liver damage
- Supportive treatment in chronic inflammatory liver disease and hepatic cirrhosis
Recommended daily dose per Commission E: 12-15 g of crushed seeds, or pharmaceutical preparations equivalent to 200-400 mg silymarin (calculated as silybin) daily. No serious adverse effects are recognized; the only contraindication listed is rare allergic reaction in patients sensitive to other Asteraceae family plants (ragweed, daisies, marigolds).
The EMA HMPC monograph (Committee on Herbal Medicinal Products, European Union herbal monograph on Silybum marianum (L.) Gaertn., fructus, published 2018) lists milk thistle fruit preparations as a traditional herbal medicinal product for the relief of digestive disorders, a sensation of fullness and indigestion, and to support liver function, after serious conditions have been ruled out — based exclusively on long-standing use. It has no "Well-Established Use" liver indication: the European Medicines Agency (EMA) states that clinical studies in patients with liver disorders suggested positive effects, but firm conclusions could not be drawn because of poor study design, small numbers of patients and differences in dose levels and treatment length. Its doses are given per preparation (for example, 3-5 g of the crushed fruit as a tea, two to three times a day before meals), and it lists use under 18 years of age as not recommended.
The WHO Monograph on Selected Medicinal Plants Volume 2 (2002) provides the global traditional-medicine reference, listing the same liver indications and the dosing range of 200-400 mg silymarin per day in divided doses.
These three monographs together are the main regulatory and traditional-medicine references for milk thistle.
Alcoholic Liver Disease — Trials and Cochrane Meta-Analyses
The largest body of human clinical-trial evidence on milk thistle is in alcoholic liver disease (ALD). The clinical question is whether silymarin slows progression from alcoholic hepatitis or steatohepatitis to cirrhosis, and whether it improves survival in cirrhotic patients who continue to drink.
The pivotal early trials were European, conducted from the 1970s through the 1990s. The most-cited is the Ferenci trial (Vienna, 1989): 170 patients with histologically-confirmed cirrhosis (predominantly alcoholic) were randomized to 420 mg/day silymarin or placebo for an average of 41 months. The trial reported a 4-year survival of 58% in the silymarin group versus 39% in placebo. The benefit was strongest in the Child-Pugh A (compensated cirrhosis) subgroup and in the alcohol-etiology subgroup. Mean follow-up was 41 months.
The subsequent Pares trial (Barcelona, 1998) was larger (200 patients), restricted to alcoholic cirrhosis, and ran for two years. It did not replicate the Ferenci survival benefit. This discrepancy — positive results in earlier smaller trials and null results in later larger trials — runs through the entire milk thistle literature and is the principal reason the herb remains controversial in conventional hepatology despite its strong regulatory monographs.
The Cochrane Review on milk thistle for alcoholic and/or hepatitis B or C liver disease (Rambaldi, Jacobs, Gluud, 2007, updating their 2005 review) pooled 18 randomized trials with a total of 1,088 patients. The conclusions:
- For mortality: silymarin did not significantly reduce all-cause mortality (relative risk 0.78, 95% confidence interval (CI) 0.53-1.15); liver-related mortality was significantly reduced across all trials (relative risk (RR) 0.50, 95% confidence interval 0.29-0.88) but not in the high-quality trials (RR 0.57, 95% confidence interval 0.28-1.19)
- For liver-related complications: no significant effect
- For aminotransferases (alanine aminotransferase (ALT)/aspartate aminotransferase (AST)): silymarin produced modest reductions (statistically significant but of uncertain clinical importance)
- Quality assessment: methodological quality was low (only 28.6% of the trials reported high-quality characteristics); the authors concluded that their results "question the beneficial effects of milk thistle" for these liver diseases and that adequately conducted randomized trials are needed
The honest summary: silymarin produces modest improvements in biochemical markers of liver damage (transaminases, bilirubin) and may produce small subgroup benefits in compensated alcoholic cirrhosis, but the highest-quality trials have not shown a survival benefit. The German Commission E approved the liver indications; the European Medicines Agency accepts milk thistle fruit for liver support only on the basis of traditional use; the U.S. Food and Drug Administration (FDA) has not approved it for any liver disease.
For patients with active alcoholic liver disease, milk thistle is best understood as an adjunct that may reduce inflammation while patients pursue the only definitively effective intervention — alcohol abstinence. See our Liver Disease page and Cirrhosis page for the broader clinical context.
Cirrhosis Trials (Ferenci, Pares, Lucena)
The cirrhosis trial set deserves separate attention because cirrhosis is the highest-stakes liver disease for which milk thistle has been tested, and because the discordance between trials is so instructive.
The Ferenci trial (1989), as described above, was the landmark survival trial — 170 patients, 41 months mean follow-up, significant survival benefit in compensated cirrhosis and alcohol-etiology subgroups.
The Pares trial (1998) attempted to replicate Ferenci with 200 alcoholic cirrhosis patients. Two-year follow-up. No significant survival benefit. Critics noted that the Pares cohort had more advanced disease at baseline (more Child-Pugh B and C), shorter follow-up than Ferenci, and continued drinking by a substantial fraction of both arms — possibly diluting any benefit.
The Lucena trial (2002) in chronic alcoholic liver disease showed silymarin reduced lipid peroxidation markers (MDA) and improved glutathione status but did not move clinical endpoints.
Most modern hepatology guidelines do not recommend silymarin as a standard-of-care intervention in cirrhosis. The herb is widely used in Germany, Austria, and Italy as an adjunct in chronic liver disease management.
Non-Alcoholic Fatty Liver Disease (NAFLD/Non-Alcoholic Steatohepatitis)
Non-alcoholic fatty liver disease (NAFLD) and its progressive form non-alcoholic steatohepatitis (NASH) are now the leading cause of chronic liver disease in the United States and most developed countries, affecting an estimated 25-30% of adults. Approved drugs were long lacking: the U.S. Food and Drug Administration approved the first one, resmetirom, in March 2024 for adults with non-alcoholic steatohepatitis without cirrhosis who have moderate to advanced liver scarring (fibrosis), and in 2025 approved semaglutide for the same condition, now also called metabolic-associated steatohepatitis (MASH). The long lack of approved drugs has driven interest in milk thistle as a possible non-alcoholic fatty liver disease adjunct.
The trial base is encouraging but small. The Solhi trial (2014) randomized 64 patients with non-alcoholic steatohepatitis to silymarin (210 mg a day) or placebo for 8 weeks. The silymarin group showed significant reductions in alanine aminotransferase and aspartate aminotransferase.
The 2017 Kheong trial (Malaysia) was the largest properly-designed silymarin non-alcoholic fatty liver disease trial: 99 patients with biopsy-proven non-alcoholic steatohepatitis, randomized to high-dose silymarin (700 mg three times daily) versus placebo for 48 weeks. The main goal — a fall of 30% or more in the disease-activity score on biopsy — was not met (32.7% versus 26.0% of patients). Fibrosis did fall: 22.4% of the silymarin group improved by at least one fibrosis stage on biopsy versus 6.0% on placebo, and liver stiffness fell by 30% or more in 24.2% versus 2.3%. The authors wrote that the fibrosis finding remains to be confirmed in a larger trial.
For people with non-alcoholic fatty liver disease, practitioners describe milk thistle at 420-700 mg/day for 6-12 months as an adjunct alongside weight loss, dietary change (Mediterranean diet), and management of metabolic syndrome components. See our non-alcoholic fatty liver disease page for the full clinical approach.
The Amanita phalloides Antidote — Intravenous Silibinin
The most dramatic clinical application of milk thistle in modern medicine is the use of intravenous silibinin (a water-soluble silibinin succinate infusion) as the standard-of-care antidote for Amanita phalloides (death cap) mushroom poisoning across Europe. This indication is unique in herbal medicine — nowhere else does a botanical extract serve as a registered emergency-medicine intravenous antidote.
Amanita phalloides ingestion is uncommon (estimated 50-100 cases annually in Europe, 5-10 in the United States) but devastating: untreated mortality is approximately 20-25%, driven by hepatic necrosis from the cyclopeptide toxins alpha-amanitin and phalloidin. Death typically occurs 6-16 days post-ingestion from fulminant hepatic failure, often requiring emergency liver transplantation.
The toxin uptake mechanism is the key. Alpha-amanitin enters hepatocytes via the OATP1B3 sodium-independent organic-anion transporter on the sinusoidal (basolateral) membrane of hepatocytes. Once inside, it irreversibly inhibits RNA polymerase II, halting messenger RNA transcription and killing the cell. Silybin competitively blocks OATP1B3, preventing alpha-amanitin uptake.
The intravenous (IV) protocol: intravenous silibinin is given as a 5 mg/kg loading dose over 1 hour, followed by 20 mg/kg/day as continuous infusion for 48-96 hours. Treatment is started as soon as possible after ingestion — ideally within 48 hours, before significant hepatocellular necrosis has occurred. Patients identified earlier (still in the asymptomatic latency phase 6-24 hours post-ingestion) have the best outcomes.
A 2012 review by Mengs and colleagues (Current Pharmaceutical Biotechnology), written mainly by staff of the drug's manufacturer, pooled published and unpublished reports: of 1,491 documented death-cap-poisoned patients treated with intravenous silibinin, 1,384 survived, a survival rate of 93%. In one cohort it describes, the combined rate of death or liver transplant was 5.1% with silibinin alone and 8.8% with silibinin plus penicillin. The review compares overall mortality of less than 10% with silibinin against more than 20% with penicillin or penicillin plus silibinin, and notes that mortality from these poisonings had already fallen to 10-20% mainly because of better supportive and intensive care. Randomized controlled trials are not considered possible because the poisoning is rare and life-threatening, so the evidence rests on these observational reports.
Intravenous silibinin is not U.S. Food and Drug Administration-approved in the United States, but the U.S. Food and Drug Administration grants emergency-use access through Investigational New Drug applications — U.S. poison centers can obtain it within 24 hours through the U.S. Food and Drug Administration expanded-access program. North American poison control protocols increasingly call for it as first-line antidote in confirmed or strongly suspected Amanita ingestion.
Hepatic Regeneration Mechanism (RNA Polymerase I)
The mechanism that distinguishes milk thistle from most other hepatoprotectants is that it does not merely prevent liver damage — it actively stimulates regeneration of damaged hepatocytes. The mechanism is silybin's stimulation of nucleolar RNA polymerase I.
RNA polymerase I is the enzyme responsible for transcribing ribosomal RNA (rRNA) genes. Because ribosomal RNA assembles into ribosomes that in turn manufacture all cellular proteins, RNA polymerase I activity is the rate-limiting step in protein synthesis. In rapidly-regenerating tissue (the regenerating liver after partial hepatectomy or toxic injury), RNA polymerase I activity surges, supporting the protein synthesis needed for cell growth and division.
Silybin binds to a specific site on the nucleolar polymerase complex and increases its transcriptional activity. The result is enhanced rRNA production, increased ribosome assembly, and accelerated protein synthesis — precisely what damaged liver cells need to recover. In experimental models of liver injury (partial hepatectomy, CCl4 toxicity, ischemia-reperfusion), silybin pretreatment accelerates the restoration of liver mass and the recovery of hepatic synthetic function.
This regenerative mechanism is distinct from (and complementary to) the membrane-stabilization and OATP1B3-blocking effects described in the next section. Together they explain why milk thistle works as both a prophylactic (taken before known toxin exposure, e.g., chemotherapy) and a rescue agent (started after acute hepatic injury). The Amanita protocol exploits both: silybin blocks further toxin uptake while simultaneously stimulating regeneration of cells that have already been damaged but not yet died.
Hepatocyte Membrane Stabilization (OATP1B3 Block)
The second mechanism on which essentially all milk thistle clinical effects depend is hepatocyte membrane stabilization. Silybin physically intercalates into the phospholipid bilayer of the hepatocyte plasma membrane, altering membrane fluidity and structurally protecting the membrane against toxin-induced permeabilization.
The membrane effect has two components. The first is the OATP1B3 transporter block already discussed for amanita. OATP1B3 (organic anion-transporting polypeptide 1B3) is one of the principal hepatocyte uptake transporters for amphipathic anionic compounds, including bilirubin, bile acids, several drugs (atorvastatin, fexofenadine), and toxic anions such as phalloidin and amanitin. Silybin's competitive inhibition of OATP1B3 reduces hepatocellular uptake of toxic substrates — a generalizable mechanism that protects against multiple chemical insults, not just amanita.
The second component is the membrane fluidity effect. By intercalating into the lipid bilayer, silybin modestly stiffens the membrane and reduces its permeability to small toxic molecules that would otherwise diffuse passively into the cell. In animal models, this effect protects against carbon tetrachloride (CCl4), thioacetamide, galactosamine, acetaminophen overdose, halothane hepatotoxicity, and chronic ethanol-induced injury.
The clinical translation extends beyond exotic poisonings. In oncology, silymarin is being studied as a chemoprotectant against the hepatotoxicity of methotrexate, cisplatin, doxorubicin, and tamoxifen. The trial base remains preliminary — most data are from animal models and small clinical pilot studies — but the mechanistic rationale is strong and consistent with the broader hepatocyte-protection picture.
Dosing Protocols, Forms, and Bioavailability
Standardized silymarin (pharmaceutical-grade extract): 420 mg/day in three divided doses (140 mg three times daily) is the canonical European hepatology dose, derived from Commission E and used in the Ferenci cirrhosis trial. Lower amounts that practitioners describe for general liver support are 200-280 mg/day. Higher-dose protocols (700 mg three times daily, 2,100 mg/day) have been used in non-alcoholic steatohepatitis and hepatitis C virus (HCV) trials.
Silybin–phosphatidylcholine complex: The bioavailability problem with oral milk thistle is real — free silybin has 20-50% oral bioavailability with extensive first-pass conjugation. A silybin–phosphatidylcholine complex binds silybin to phosphatidylcholine to improve lipid-membrane partitioning. The result is approximately 4.6-fold higher silybin plasma concentrations from an equivalent silybin dose. Amounts used for the complex are typically 120-360 mg/day, described as equivalent to roughly 540-1,620 mg of standard silymarin.
Whole-seed and tincture forms: The crushed seed (12-15 g/day per Commission E) and alcoholic tincture have a long traditional-use record but are not standardized and are not used in modern clinical trials. They are traditionally used for general digestive and gentle liver support, and have not been tested in serious liver disease.
Intravenous silibinin: 5 mg/kg loading then 20 mg/kg/day continuous infusion for amanita poisoning (hospital-only).
Bioavailability optimization: Practitioners describe taking it with a meal containing some fat to enhance absorption, and apart from high-fiber meals (fiber is said to bind silymarin in the gut); some place one of the three daily doses at bedtime to provide overnight liver exposure.
Duration: Liver-disease trials typically run 6-12 months. For prophylactic use during known hepatotoxic exposure (e.g., a course of acetaminophen, tuberculosis therapy with isoniazid, methotrexate), the pattern practitioners describe is to start 1-2 weeks before and continue throughout the exposure. Indefinite long-term use is generally regarded as safe.
Cautions and Drug Interactions
- Asteraceae allergy — allergic reactions to milk thistle are reported in people allergic to ragweed, daisies, chrysanthemums, marigolds, or other Asteraceae plants. Cross-reactivity is uncommon but documented.
- Mild gastrointestinal (GI) side effects — bloating, mild diarrhea, and abdominal discomfort are reported in approximately 2-10% of users at standard doses and tend to resolve with dose reduction or splitting doses with food.
- Estrogenic activity — silymarin has weak estrogen-receptor binding in vitro. The clinical relevance is uncertain; the concern applies to people with estrogen-sensitive conditions (hormone-receptor-positive breast cancer, endometriosis), and conservative practitioners leave high-dose milk thistle out for these groups.
- CYP450 drug interactions — silymarin weakly inhibits CYP3A4, CYP2C9, and CYP2D6 in vitro. Clinically significant interactions are uncommon at standard doses but theoretically possible with narrow-therapeutic-index drugs (warfarin, certain anticonvulsants, immunosuppressants). These are medicines where a small change in the blood level can tip the drug into too weak or too strong an effect, which is why they are the ones watched for interactions.
- Pregnancy and lactation — not specifically contraindicated, with a long traditional-use record in pregnant women. However, modern controlled safety data are limited, and conservative practice is not to start it new during pregnancy. Intravenous silibinin is given in life-threatening mushroom poisoning regardless of pregnancy status.
- Hemochromatosis and iron overload — one paradoxical concern: silymarin chelates iron in vitro and may reduce iron absorption from a meal. In iron-deficient patients this could matter; in iron-overloaded patients (hereditary hemochromatosis) it is actually beneficial.
- Hypoglycemic potentiation — silymarin modestly improves insulin sensitivity in diabetics. For people on insulin or sulfonylureas this could add to the drugs' glucose-lowering effect, and blood sugar is checked more closely after starting milk thistle as a precaution.
- Not a substitute for definitive treatment — for active alcoholic liver disease, alcohol abstinence remains the only definitively effective intervention. For chronic hepatitis B virus (HBV) infection, the World Health Organization lists oral medicines such as tenofovir or entecavir; for hepatitis C virus, it recommends pan-genotypic direct-acting antivirals, which cure the infection within 8–12 weeks in nearly all patients. Milk thistle is adjunctive, not curative.
Key Research Papers
- Ferenci P et al. (1989). Randomized controlled trial of silymarin treatment in patients with cirrhosis of the liver. J Hepatol 9(1):105-13. — PubMed
- Pares A et al. (1998). Effects of silymarin in alcoholic patients with cirrhosis of the liver: results of a controlled, double-blind, randomized and multicenter trial. J Hepatol 28(4):615-21. — PubMed PMID: 9566830
- Rambaldi A, Jacobs BP, Gluud C (2007). Milk thistle for alcoholic and/or hepatitis B or C virus liver diseases. Cochrane Database Syst Rev 2007(4):CD003620. — PubMed PMID: 17943794
- Mengs U, Pohl RT, Mitchell T (2012). Legalon SIL: the antidote of choice in patients with acute hepatotoxicity from amatoxin poisoning. Curr Pharm Biotechnol 13(10):1964-70. — PubMed PMID: 22352731
- Saller R, Meier R, Brignoli R (2001). The use of silymarin in the treatment of liver diseases. Drugs 61(14):2035-63. — PubMed PMID: 11735632
- Loguercio C, Festi D (2011). Silybin and the liver: from basic research to clinical practice. World J Gastroenterol 17(18):2288-301. — PubMed PMID: 21633595
- Kheong CW et al. (2017). A randomized trial of silymarin for the treatment of nonalcoholic steatohepatitis. Clin Gastroenterol Hepatol 15(12):1940-1949. — PubMed
- Letteron P et al. (1990). Mechanism for the protective effects of silymarin against carbon tetrachloride-induced lipid peroxidation and hepatotoxicity in mice. Biochem Pharmacol 39(12):2027-34. — PubMed PMID: 2353942
- Sonnenbichler J, Goldberg M, Hane L, Madubunyi I, Vogl S, Zetl I (1986). Stimulatory effect of silibinin on the DNA synthesis in partially hepatectomized rat livers. Biochem Pharmacol 35(3):538-41. — PubMed
- Floersheim GL, Eberhard M, Tschumi P, Duckert F (1978). Effects of penicillin and silymarin on liver enzymes and blood clotting factors in dogs given a boiled preparation of Amanita phalloides. Toxicol Appl Pharmacol 46(2):455-62. — PubMed PMID: 569913
- Magdalan J et al. (2010). Influence of commonly used clinical antidotes on antioxidant systems in human hepatocyte culture intoxicated with alpha-amanitin. Hum Exp Toxicol 30(1):38-43. — PubMed PMID: 20378659
PubMed Topic Searches
Connections
- All Herbs
- Milk Thistle Overview
- Milk Thistle Benefits Hub
- Antioxidant & Glutathione
- Hepatitis Adjunctive
- Skin Health
- Liver Disease
- Cirrhosis
- Non-Alcoholic Fatty Liver Disease
- Hepatitis
- Hepatitis C
- Hemochromatosis (Iron Overload)
- Liver Cleansing
- Detox Protocols
- Turmeric
- Dandelion
- Chanca Piedra
- Chanca Piedra: Liver Protection and Hepatitis B — hepatitis B virus-specific antiviral mechanism, niranthin vs nucleoside analogs, trial evidence on HBsAg/HBV-DNA, and adjunctive use with entecavir/tenofovir.
- N-Acetylcysteine
- Glutathione
- Comprehensive Metabolic Panel
- Gamma-Glutamyl Transferase
- History