⚠ Evidence warning: Clinical trials or other evidence do not support the claims that niranthin inhibits the hepatitis B virus polymerase at concentrations that matter in the body and escapes drug resistance, and that Phyllanthus lowers HBV-DNA in a meaningful minority, improves HBeAg seroconversion and clears HBsAg in 3-8% of people in modern trials. This page keeps it as a report of what people, websites or other media say.
Chanca Piedra for Hepatitis B: Niranthin Polymerase Inhibition, Clinical Trial Evidence, and Combination with Entecavir/Tenofovir
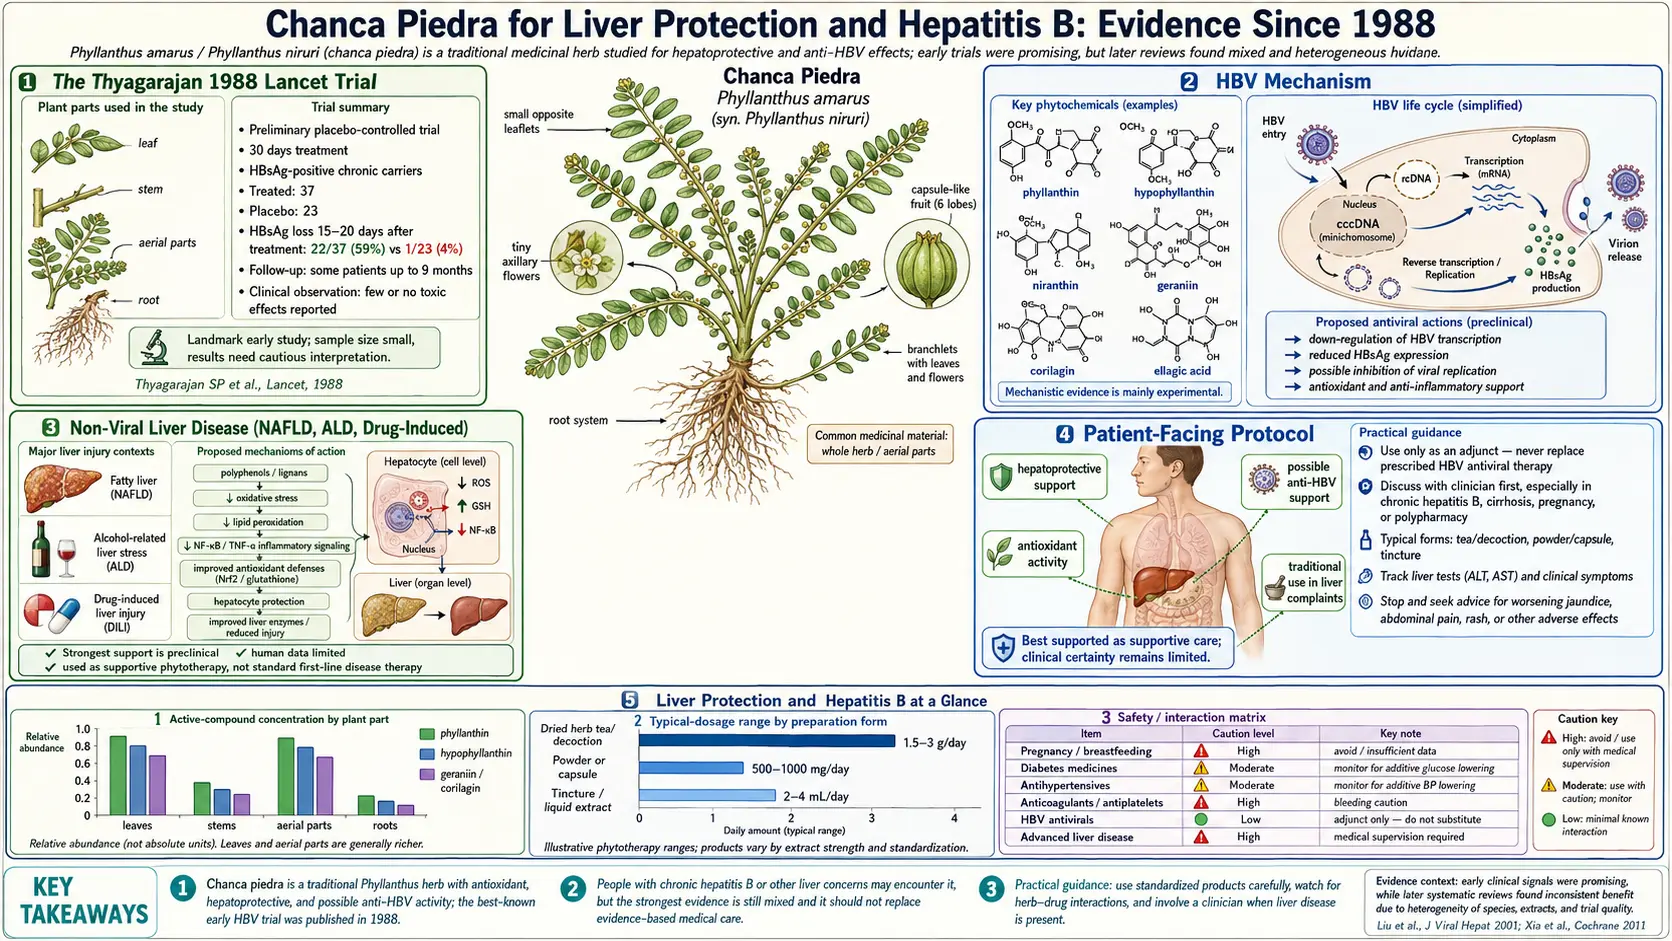
The companion Liver Protection page covers general hepatoprotection — the 1988 Thyagarajan Lancet headline, non-alcoholic fatty liver disease (NAFLD) signals, anti-tuberculosis hepatoprotection, drug interaction warnings. This page goes deeper on the one indication that drove Chanca Piedra into mainstream phytotherapy journals in the first place: chronic hepatitis B infection. We focus on the virology, the specific lignan that does the antiviral heavy lifting (niranthin), the surrogate-endpoint data from Phase II-style trials (HBsAg, HBeAg, HBV-DNA), how the herb's mechanism compares to nucleoside analogs like entecavir and tenofovir, and the honest answer to the question every hepatitis B virus (HBV) carrier eventually asks: "can I take this with my antiviral?"
Table of Contents
- Hepatitis B Virus Virology in 60 Seconds: Why HBsAg Loss Matters
- Niranthin: What the Cell and Duck Studies Measured
- Niranthin vs Nucleoside Analogs (Entecavir, Tenofovir, Lamivudine)
- HBsAg, HBeAg, and HBV-DNA Trial Data
- Dosing Used in the Trials
- Hepatitis C Virus and Other Chronic Hepatitides
- Alongside-Conventional-Therapy Strategy
- Monitoring Labs and What to Watch
- Limitations of the Evidence Base
- Situations Discussed and Who the Research Raises Concerns For
- Key Research Papers
- Connections
- Featured Videos
Hepatitis B Virus Virology in 60 Seconds: Why HBsAg Loss Matters
Chronic hepatitis B virus (HBV) is a partially double-stranded DNA virus with a quirky replication cycle. After infecting a hepatocyte, the relaxed circular DNA (rcDNA) is converted in the nucleus into a stable, episomal covalently closed circular DNA (cccDNA) — the viral "minichromosome." cccDNA is the durable reservoir that makes hepatitis B virus a lifelong infection in most adults who acquire it.
From cccDNA, the virus transcribes a 3.5-kb pregenomic RNA (pgRNA), which is packaged into nucleocapsids along with the viral polymerase. The polymerase is a multifunctional enzyme: it acts as an RNA-dependent DNA polymerase (a reverse transcriptase) to copy pgRNA back into the partially double-stranded DNA genome, plus it has DNA-dependent DNA polymerase and RNase H activity. This reverse-transcriptase step is the Achilles' heel that all approved oral hepatitis B virus drugs target.
Serologic markers carry the clinical meaning:
- HBV-DNA — quantitative polymerase chain reaction (PCR); reflects ongoing replication; modern antivirals routinely drive this below the limit of detection (LoD).
- HBeAg — e antigen; secreted protein from the precore region; presence correlates with high replication and infectivity. HBeAg seroconversion (loss of HBeAg + appearance of anti-HBe) is a meaningful clinical milestone.
- HBsAg — surface antigen; reflects ongoing viral protein production from cccDNA or from integrated HBV DNA in the host genome. HBsAg loss ("functional cure") is the holy grail — achieved in <1% per year of nucleoside-analog therapy and only marginally better with pegylated interferon.
- Anti-HBs — protective antibody; ideally follows HBsAg loss, locking in seroconversion.
This is why the original Thyagarajan paper made such a splash. It reported that 22 of 37 patients (59%) given a 30-day course had lost HBsAg when tested 15-20 days after treatment ended, against 1 of 23 (4%) on placebo. Modern entecavir and tenofovir, given for years, do not approach that. The Thyagarajan magnitude has never been independently reproduced — in the later carrier trials of Doshi 1994 and Wang 1995, and in a 2018 placebo-controlled trial, no patient lost HBsAg (details below). The biological plausibility of even the modest signal is what keeps the research going.
Niranthin: What the Cell and Duck Studies Measured
Of the four major aryltetralin lignans in P. amarus (phyllanthin, hypophyllanthin, niranthin, nirtetralin), niranthin is the standout antiviral. Mechanistic work over the past two decades has converged on several specific actions:
- Hepatitis B virus polymerase / reverse-transcriptase inhibition — niranthin (and nirtetralin) binds the catalytic pocket of hepatitis B virus polymerase and reduces RNA-templated DNA synthesis in cell-free enzyme assays and in stably-transfected HepG2.2.15 cells. The half-maximal inhibitory concentrations (IC50s) in cell culture sit in the low-micromolar range — substantially weaker than entecavir on a per-molar basis, but biologically meaningful given the achievable plasma concentrations.
- Lower antigen output from liver cells — in a 2014 study (Liu S and colleagues), niranthin purified from P. niruri was added for 144 hours to human liver-cancer cells that carry hepatitis B virus genes (HepG2.2.15 cells). The cells released significantly less HBsAg and HBeAg. The concentration that halved the output (IC50) was 15.6 µM for HBsAg and 25.1 µM for HBeAg, so the surface antigen was suppressed at a lower concentration than the e antigen. These are cell results, not human ones. The study measured antigen release; its abstract reports no test of niranthin on the viral polymerase enzyme itself.
- Ducks infected with duck hepatitis B virus — in the same study, ducklings given niranthin into the stomach once a day for 14 days (25, 50 or 100 mg/kg a day) had significantly lower blood levels of viral DNA, HBsAg, HBeAg and the liver enzymes alanine aminotransferase (ALT) and aspartate aminotransferase (AST), and their liver tissue showed less damage. These are animal results; no human trial of purified niranthin has been published.
- cccDNA-independent activity — the inhibition is downstream of the cccDNA pool. Niranthin does not appear to deplete cccDNA itself (no current antiviral does), which is why even effective suppression doesn't equal cure.
- Synergy with the ellagitannins — geraniin and corilagin contribute independent polymerase-binding activity in cell-free assays, and the urolithin metabolites produced by gut microbiota from geraniin add anti-inflammatory cover during long courses. Whole-herb extracts outperform isolated niranthin in most head-to-head assays for this reason.
- Immunomodulation — in animal models, Phyllanthus extracts shift Th1/Th2 cytokine balance toward Th1, boost natural killer (NK) cell activity, and modestly upregulate type I interferon signaling. Whether these effects translate to humans is uncertain, but they're the second plausible mechanism by which Phyllanthus could push HBeAg seroconversion rates.
For the broader lignan/tannin profile see the Active Compounds page.
Niranthin vs Nucleoside Analogs (Entecavir, Tenofovir, Lamivudine)
It's worth being precise about how niranthin's mechanism differs from the approved drugs:
- Nucleoside / nucleotide analogs (NAs) — entecavir (a deoxyguanosine analog), tenofovir disoproxil fumarate (TDF) and tenofovir alafenamide (TAF) (deoxyadenosine analogs), lamivudine and emtricitabine (cytidine analogs). These are chain terminators: phosphorylated to the active triphosphate, they get incorporated into the growing HBV DNA strand by the polymerase, then halt further nucleotide addition because they lack the 3'-OH group needed for the next bond.
- Niranthin — a non-nucleoside polymerase inhibitor. It binds the enzyme allosterically (not at the nucleotide-binding site), more analogous in concept to the non-nucleoside reverse transcriptase inhibitors (NNRTIs) used in human immunodeficiency virus (HIV). There is no need for intracellular phosphorylation, no chain termination, and no cross-resistance with NA mutations (rtM204V/I, rtL180M, etc.).
- Niranthin — a plant lignan, not a nucleoside, so it is not a chain terminator. The published niranthin study measured lower antigen and viral-DNA levels in cells and ducks; where in the viral life cycle niranthin acts, and whether it acts on the polymerase at all, has not been shown.
Because niranthin is not a nucleoside, some writers suggest it might still act on hepatitis B virus strains that resist nucleoside analogs (mutations such as rtM204V/I and rtL180M). This is a hypothesis: no study has tested niranthin against resistant strains, and there are no controlled trials of it. The idea that the two work differently is the basis for the combination logic discussed below.
The other side of the comparison — potency — is starkly in favor of the drugs. Entecavir has a cell-culture EC50 around 4 nM. Niranthin's half-maximal concentrations in the 2014 cell study were 15.6 µM and 25.1 µM — micromolar rather than nanomolar — although that study measured antigen release rather than the same endpoint. Niranthin is not going to replace entecavir for any patient who needs viral suppression. It might still contribute, which is the whole reason for the adjunctive-use literature.
HBsAg, HBeAg, and HBV-DNA Trial Data
The clinical literature on Phyllanthus in hepatitis B virus is uneven but not empty. The most-cited findings:
- Thyagarajan 1988 (Lancet) — 200 mg P. amarus powder TID × 30 days, a preliminary study against placebo-treated controls, 37 treated carriers. HBsAg loss: 22/37 (59%) when tested 15-20 days after the end of treatment vs 1/23 (4%) on placebo. Some patients were followed for up to 9 months, and in none had the surface antigen returned. The number that started everything.
- Doshi 1994 (Indian Journal of Gastroenterology) — a two-stage trial in Bombay in 30 symptom-free HBsAg carriers, given P. amarus 250-500 mg three times daily for 4-8 weeks. None of the 30 cleared HBsAg. The herb was well tolerated, with no side effects and no changes in the safety blood tests. The authors concluded that P. amarus "is not effective in clearing HBsAg" in symptom-free carriers.
- Wang 1995 (Journal of Laboratory and Clinical Medicine) — 123 patients with chronic hepatitis B in China, testing three preparations from different places: P. amarus from Madras, India (11 patients), P. niruri from Hainan (42) and P. urinaria from Henan (35), with 35 untreated controls. Patients given P. urinaria were more likely to lose HBeAg and to develop anti-HBe than those given either of the other two preparations. No patient changed HBsAg status.
- Berk 1991 (Journal of Hepatology) — one of the first negative replication attempts, a short report titled "Beneficial effects of Phyllanthus amarus for chronic hepatitis B, not confirmed."
- Xia 2011 Cochrane review — 16 randomized controlled trials (RCTs), 1,326 patients. Only one trial (42 people) compared Phyllanthus with placebo, and it found no significant difference in HBeAg seroconversion. The other 15 trials compared Phyllanthus plus an antiviral (interferon alpha, lamivudine, adefovir dipivoxil, thymosin, vidarabine or conventional treatment) with the same antiviral alone; the combination did better on blood HBV DNA, HBeAg and HBeAg seroconversion, but results varied a great deal between trials, and the HBV-DNA result did not hold up in trial sequential analysis (a check against chance findings). No serious side effects were reported. The authors concluded: "There is no convincing evidence that phyllanthus compared with placebo benefits patients with chronic HBV infection."
- Liu 2001 (Journal of Viral Hepatitis) — earlier systematic review of 22 randomized trials (1,947 patients) of various Phyllanthus species. Phyllanthus cleared HBsAg more often than placebo or no treatment (relative risk 5.64), showed no significant difference from interferon for HBsAg, HBeAg or HBV DNA, and Phyllanthus plus interferon cleared HBeAg and HBV DNA more often than interferon alone. The authors rated only the five double-blind trials as high quality and wrote that "the evidence is not strong due to the general low methodological quality and the variations of the herb."
- Baiguera 2018 (Complementary Medicine Research) — a double-blind trial in Italy that gave P. niruri or a placebo for 12 months to people with chronic hepatitis B (50 enrolled, 47 completed). Viral load did not differ between the groups and nobody lost HBsAg. Kidney tests did not change and no serious side effects occurred. The trial was stopped at the end of its second year because there was no apparent benefit; the authors wrote that it "does not support the use of Phyllanthus niruri for the treatment of chronic hepatitis B."
- Xia 2013 Cochrane review (Phyllanthus versus antiviral drugs) — five randomized trials, 290 patients, all judged at high risk of bias, comparing compound Phyllanthus (3-12 months) with lamivudine, interferon alpha, thymosin or thymosin alpha 1. Phyllanthus looked better for HBeAg clearance at the end of treatment in a standard meta-analysis (RR 0.76), but not after trial sequential analysis, and showed no difference for HBsAg or HBV DNA. No trial reported side-effect data. The reviewers found "insufficient evidence to support or refute the use of phyllanthus."
The pattern across the literature: the pooled reviews find more HBsAg, HBeAg and HBV-DNA clearance with Phyllanthus than with no treatment (Liu 2001) and with Phyllanthus added to an antiviral than with the antiviral alone (Xia 2011), but from mostly low-quality trials. The trials that tested carriers directly for HBsAg loss after Thyagarajan — Doshi 1994, Wang 1995 and the placebo-controlled Baiguera 2018 — found none. For comparison, HBsAg loss occurs in about 1% per year on entecavir/tenofovir. HBV-DNA does drop in a meaningful minority (typically 1-2 log10 reduction). HBeAg seroconversion is modestly improved (10-30% vs spontaneous rates of 5-15%). HBsAg loss is the headline endpoint that rarely reproduces at Thyagarajan magnitudes — usually 3-8% in modern trials, compared to ~1% per year on entecavir/tenofovir.
Dosing Used in the Trials
Dosing varies widely across the literature, which is one reason the meta-analyses are shaky. Representative protocols:
- Thyagarajan 1988 — 200 mg dried P. amarus powder, three times daily (600 mg/day total) × 30 days. (The abstract describes it only as "a preparation of the plant.")
- Doshi 1994 — 250 to 500 mg P. amarus three times daily for 4 to 8 weeks.
- Wang 1995 — three different extracts (P. amarus, P. niruri, P. urinaria); the abstract gives no dose or duration.
- Baiguera 2018 — P. niruri for 12 months; the abstract gives no dose.
- Various Indian trials — 500-1000 mg/day standardized extract, typically for 3-6 months. The longer durations seem to produce more HBeAg seroconversions.
- "Long-cure" Amazonian tea — 1 tablespoon of dried herb simmered in 1 liter water, sipped over the day, for 2-4 weeks. Lower extractive efficiency than alcoholic extracts, but the traditional dosing pattern.
See Forms, Dosing & Standardization for the broader dosing matrix.
Hepatitis C Virus and Other Chronic Hepatitides
The hepatitis C virus (HCV) evidence base for Phyllanthus is much thinner than the hepatitis B virus record, and modern direct-acting antivirals (DAAs — sofosbuvir, glecaprevir, velpatasvir, etc.) cure hepatitis C virus in >95% of patients in 8-12 weeks. Phyllanthus has no comparable record of curing hepatitis C virus.
What the cell-culture and small-study literature suggests:
- HCV NS3/4A protease inhibition — corilagin and geraniin show weak in-vitro inhibition; biologically interesting, clinically irrelevant given DAA availability.
- Adjunctive alanine aminotransferase support — in patients with persistent alanine aminotransferase elevation after DAA cure (so-called "post-SVR" liver disease, often driven by non-alcoholic fatty liver disease or alcohol), Phyllanthus may contribute to alanine aminotransferase normalization as part of a broader hepatoprotective stack.
- Hepatitis D virus (HDV) — no meaningful evidence. HDV is a satellite virus dependent on hepatitis B virus. Phyllanthus has not been studied here. A 2020 review of 282 studies (Stockdale) estimated that 4.5% of people with hepatitis B worldwide carry hepatitis D antibodies (16.4% of those seen in liver clinics), about 12 million people, and that hepatitis D accounts for an estimated 18% of cirrhosis and 20% of liver cancer among people with hepatitis B. The drug bulevirtide is approved for chronic hepatitis D in several countries and regions, including the United States, the European Economic Area and the United Kingdom. In the phase III MYR301 trial (150 patients), 73-92% had a virologic response (virus undetectable or down at least 100-fold) at the end of 144 weeks of treatment; two years after stopping, that had fallen to 30-33%.
- Hepatitis E (HEV) — no clinical evidence; some weak in-vitro signals from related ellagitannins, not enough to act on.
In short: the hepatitis C virus cure rates above come from DAAs. The Phyllanthus research on hepatitis C concerns liver protection after the cure, not antiviral action. For hepatitis B virus (where there is no cure, only suppression), the add-on antiviral question is the one most studied.
Alongside-Conventional-Therapy Strategy
For a chronic hepatitis B virus patient already on entecavir or tenofovir, what is the case for adding Chanca Piedra? The honest answer:
- Plausible — niranthin is not a chain-terminating nucleoside (where it acts is not established), potential synergy on HBV-DNA suppression, plausible additional pressure on HBeAg seroconversion, real antioxidant cover for hepatocytes.
- Not proven — no large head-to-head trial of NA monotherapy vs NA + Phyllanthus in hepatitis B virus has been done at modern methodologic standards. The 2011 Cochrane review's own conclusion: "Phyllanthus plus an antiviral drug may be better than the same antiviral drug alone. However, heterogeneity, systematic errors, and random errors question the validity of the results."
- Drug-interaction caveats matter — entecavir and tenofovir are not cytochrome P450 3A4 (CYP3A4) substrates (they're renally cleared), so the major Chanca Piedra cytochrome P450 3A4 inhibition concern doesn't apply to the NA itself. But many hepatitis B virus patients are on co-medications (statins, antihypertensives, immunosuppressants for transplant recipients) that are cytochrome P450 3A4 substrates. The drug-interaction risk lives there.
- Stopping the antiviral is the main danger — Chanca Piedra has not been shown to replace entecavir or tenofovir. NA cessation in chronic hepatitis B virus can produce severe alanine aminotransferase flares and acute liver failure. Patients who stop their antiviral to "try the herbal" are taking a real, occasionally lethal risk.
- Pegylated interferon combinations — the older literature with interferon-alpha + Phyllanthus combinations showed encouraging signals, but pegylated interferon use has declined as NAs improved. This regimen is now mostly reserved for younger HBeAg-positive patients with high alanine aminotransferase and low HBV-DNA who want a finite-duration treatment course.
Monitoring Labs and What to Watch
Hepatitis B virus care already includes routine monitoring. The herb doesn't change what gets checked — it changes which changes matter.
Baseline (before starting):
- HBV-DNA quantitative polymerase chain reaction
- HBsAg, anti-HBs (quantitative if available; the qHBsAg is increasingly used as a treatment-response marker)
- HBeAg, anti-HBe
- Alanine aminotransferase, aspartate aminotransferase, gamma-glutamyl transferase (GGT), alkaline phosphatase, total/direct bilirubin, albumin, international normalized ratio (INR), platelets (the basic synthetic-function panel)
- Alpha-fetoprotein (baseline for liver-cancer, or hepatocellular carcinoma (HCC), surveillance)
- Transient elastography (a liver-stiffness scan), or the APRI (aspartate aminotransferase-to-platelet ratio index) and FIB-4 (fibrosis-4) scores calculated from baseline labs
- Renal function (creatinine, estimated glomerular filtration rate (eGFR)) — especially if on tenofovir, given TDF nephrotoxicity risk
3-month and 6-month reassessment:
- Repeat HBV-DNA — the primary efficacy endpoint while on NAs; expected to remain suppressed
- HBeAg / anti-HBe seroconversion check
- HBsAg quantitative if available
- Repeat alanine aminotransferase/aspartate aminotransferase/gamma-glutamyl transferase — expected to be stable or improving
- Repeat synthetic function
Yearly:
- HCC surveillance: liver ultrasound +/- alpha-fetoprotein every 6 months for cirrhotics, every 12 months otherwise (per the American Association for the Study of Liver Diseases, AASLD)
- Repeat elastography or FIB-4
Warning signs of liver injury or viral rebound: the changes below can come from a herb-related flare or from the virus returning. Jaundice, bleeding and falling liver function are signs of liver injury that hospitals treat as urgent.
- Alanine aminotransferase rises >2× baseline or >5× upper limit of normal (could be a herb-induced flare or, more concerning, a viral rebound)
- Total bilirubin rises >2× baseline
- Any new jaundice, dark urine, pale stools
- New bruising, bleeding, or marked fatigue (potential synthetic-function decline)
- Rising international normalized ratio or falling albumin
Limitations of the Evidence Base
It's important to state the weaknesses of the Phyllanthus-HBV literature honestly:
- Heterogeneity — species (P. amarus vs niruri vs urinaria), preparation (powdered herb vs aqueous extract vs alcoholic extract vs standardized capsule), dose (200 mg to 1500 mg/day), duration (30 days to 6 months). Meta-analyses pool incomparable interventions.
- Small sample sizes — most trials have 30-100 patients per arm. Even the Cochrane pool of 1,326 patients is small compared to the registration trials for entecavir (~900 patients per study) and tenofovir.
- Open-label or single-blind design — most pre-2010 trials lacked rigorous blinding. Subjective endpoints (symptom scores) are particularly vulnerable; objective endpoints (HBV-DNA, HBsAg) less so.
- Publication bias toward positive results — Eastern journal publishing patterns, especially in the 1990s, skewed toward positive trials. The Berk 1991 negative replication in the Journal of Hepatology is a notable exception.
- Few modern trials — the recent double-blind placebo-controlled trial (Baiguera 2018) enrolled only 50 people, found no effect on viral load and no HBsAg loss, and was stopped early. No large trial matches modern hepatology methodology (sample size, blinding, intention-to-treat analysis, validated patient-reported outcome measures, central HBV-DNA assays). There is no economic incentive: Phyllanthus is unpatentable.
- The reviewers' own verdicts on quality — Liu 2001 rated only 5 of its 22 trials (the double-blind ones) as high quality and wrote that "the evidence is not strong due to the general low methodological quality and the variations of the herb." Xia 2011 found that none of its 16 trials reported deaths, hepatitis B complications, quality of life or liver tissue (histology), and that "heterogeneity, systematic errors, and random errors question the validity of the results." Xia 2013 judged all five of its trials at high risk of bias.
- Surrogate endpoints, not patient-relevant outcomes — HBV-DNA suppression and HBeAg seroconversion are surrogates. The patient-relevant outcomes — HCC incidence, cirrhosis progression, liver-related mortality — have never been measured in a Phyllanthus trial.
Taken together, the Cochrane reviewers found "no convincing evidence that phyllanthus compared with placebo benefits patients with chronic HBV infection" (Xia 2011) and "insufficient evidence to support or refute the use of phyllanthus" against antiviral drugs (Xia 2013); the possible benefit they describe is as an add-on to an antiviral, with the quality problems above.
Situations Discussed and Who the Research Raises Concerns For
Situations in which Chanca Piedra is discussed as an add-on:
- Chronic inactive hepatitis B virus carrier status (HBeAg-negative, normal alanine aminotransferase, low HBV-DNA) — not on antivirals because criteria for therapy aren't met, and looking for additional immunologic pressure to push toward HBsAg loss
- Chronic hepatitis B virus on entecavir or tenofovir, with HBV-DNA already suppressed, looking for adjunctive support; not on other cytochrome P450 3A4-substrate medications
- Persistent low-level hepatitis B virus reactivation after stopping NAs (with hepatology oversight)
- Hepatitis B virus with concurrent non-alcoholic fatty liver disease or alcoholic liver disease where the broader hepatoprotective profile is attractive
- Post-DAA hepatitis C virus with residual alanine aminotransferase elevation, as part of a broader hepatoprotective stack
Situations in which the research raises concerns:
- Pregnancy or breastfeeding
- Upcoming surgery — the cytochrome P450 3A4 and platelet effects matter in the 2 weeks before an operation
- Use of warfarin, tacrolimus, cyclosporine, human immunodeficiency virus protease inhibitors, certain statins (especially simvastatin, atorvastatin), or other narrow-therapeutic-window cytochrome P450 3A4 substrates — cytochrome P450 3A4 inhibition can change their blood levels
- Decompensated cirrhosis (Child-Pugh B or C) — the herb's safety profile in advanced cirrhosis is not established and the consequences of any drug-induced liver injury are severe
- Active hepatitis B virus flare with rising alanine aminotransferase — a rising ALT can mean viral rebound or liver injury, and a herb adds a second possible cause that makes the two harder to tell apart
- Post-liver-transplant on calcineurin inhibitors — the strongest concern; tacrolimus levels can fluctuate dramatically with cytochrome P450 3A4 inhibitors
For any person with chronic hepatitis B virus, the largest danger is stopping the prescribed antiviral to switch to Chanca Piedra: NA discontinuation flares can be severe, up to acute liver failure. The AASLD and European Association for the Study of the Liver (EASL) guidelines set the criteria for when antivirals can be stopped.
Key Research Papers
- Thyagarajan SP, Subramanian S, Thirunalasundari T, Venkateswaran PS, Blumberg BS. Effect of Phyllanthus amarus on chronic carriers of hepatitis B virus. Lancet 1988;2(8614):764-6. — PubMed PMID: 2901611 · doi:10.1016/S0140-6736(88)92416-6
- Venkateswaran PS, Millman I, Blumberg BS. Effects of an extract from Phyllanthus niruri on hepatitis B and woodchuck hepatitis viruses: in vitro and in vivo studies. Proc Natl Acad Sci USA 1987;84(1):274-8. — PubMed PMID: 3467354 · doi:10.1073/pnas.84.1.274
- Xia Y, Luo H, Liu JP, Gluud C. Phyllanthus species for chronic hepatitis B virus infection. Cochrane Database Syst Rev 2011;(4):CD008960. — PubMed PMID: 21491412 · doi:10.1002/14651858.CD008960.pub2
- Liu J, Lin H, McIntosh H. Genus Phyllanthus for chronic hepatitis B virus infection: a systematic review. J Viral Hepat 2001;8(5):358-66. — PubMed PMID: 11555193 · doi:10.1046/j.1365-2893.2001.00307.x
- Shead A, Vickery K, Pajkos A, Medhurst R, Freiman J, Cossart Y. Effects of Phyllanthus plant extracts on duck hepatitis B virus in vitro and in vivo. Antiviral Res 1992;18(2):127-38. — Search PubMed · Search PubMed · doi:10.1016/0166-3542(92)90033-2
- Berk L, de Man RA, Schalm SW, Labadie RP, Heijtink RA. Beneficial effects of Phyllanthus amarus for chronic hepatitis B, not confirmed. J Hepatol 1991;12(3):405-6. — PubMed PMID: 1940272 · doi:10.1016/0168-8278(91)90850-b
- Liu J, McIntosh H, Lin H. Chinese medicinal herbs for chronic hepatitis B: a systematic review. Liver 2001;21(4):280-6. — Search PubMed · Search PubMed · doi:10.1034/j.1600-0676.2001.021004280.x
- Patel JR, Tripathi P, Sharma V, Chauhan NS, Dixit VK. Phyllanthus amarus: ethnomedicinal uses, phytochemistry and pharmacology: a review. J Ethnopharmacol 2011;138(2):286-313. — PubMed PMID: 21982793 · doi:10.1016/j.jep.2011.09.040
- Calixto JB, Santos AR, Cechinel Filho V, Yunes RA. A review of the plants of the genus Phyllanthus: their chemistry, pharmacology, and therapeutic potential. Med Res Rev 1998;18(4):225-58. — PubMed PMID: 9664291 · doi:10.1002/(sici)1098-1128(199807)18:4<225::aid-med2>3.0.co;2-x<225::aid-med2>3.0.co;2-x
- Wei W, Li X, Wang K, Zheng Z, Zhou M. Lignans with anti-hepatitis B virus activities from Phyllanthus niruri L. Phytother Res 2012;26(7):964-8. — Search PubMed · Search PubMed · doi:10.1002/ptr.3663
- Notka F, Meier GR, Wagner R. Inhibition of wild-type human immunodeficiency virus and reverse transcriptase inhibitor-resistant variants by Phyllanthus amarus. Antiviral Res 2003;58(2):175-86. — Search PubMed · doi:10.1016/S0166-3542(02)00213-9
- Lam WY, Leung KT, Law PT, et al. Antiviral effect of Phyllanthus nanus ethanolic extract against hepatitis B virus (HBV) by expression microarray analysis. J Cell Biochem 2006;97(4):795-812. — Search PubMed · Search PubMed · doi:10.1002/jcb.20611
- Doshi JC, Vaidya AB, Antarkar DS, Deolalikar R, Antani DH. A two-stage clinical trial of Phyllanthus amarus in hepatitis B carriers: failure to eradicate the surface antigen. Indian J Gastroenterol 1994;13(1):7-8. — PubMed PMID: 8119752
- Wang M, Cheng H, Li Y, Meng L, Zhao G, Mai K. Herbs of the genus Phyllanthus in the treatment of chronic hepatitis B: observations with three preparations from different geographic sites. J Lab Clin Med 1995;126(4):350-2. — PubMed PMID: 7561442
- Liu S, Wei W, Shi K, Cao X, Zhou M, Liu Z. In vitro and in vivo anti-hepatitis B virus activities of the lignan niranthin isolated from Phyllanthus niruri L. J Ethnopharmacol 2014;155(2):1061-7. — PubMed PMID: 25009077 · doi:10.1016/j.jep.2014.05.064
- Baiguera C, Boschetti A, Raffetti E, Zanini B, Puoti M, Donato F. Phyllanthus niruri versus placebo for chronic hepatitis B virus infection: a randomized controlled trial. Complement Med Res 2018;25(6):376-382. — PubMed PMID: 30372693 · doi:10.1159/000484927
- Xia Y, Luo H, Liu JP, Gluud C. Phyllanthus species versus antiviral drugs for chronic hepatitis B virus infection. Cochrane Database Syst Rev 2013;(4):CD009004. — PubMed PMID: 23633363 · doi:10.1002/14651858.CD009004.pub2
- Stockdale AJ, Kreuels B, Henrion MYR, Giorgi E, Kyomuhangi I, de Martel C, Hutin Y, Geretti AM. The global prevalence of hepatitis D virus infection: systematic review and meta-analysis. J Hepatol 2020;73(3):523-532. — PubMed PMID: 32335166 · doi:10.1016/j.jhep.2020.04.008
- Wedemeyer H, Aleman S, Blank A, et al. 144 weeks of bulevirtide monotherapy for chronic hepatitis D: final and post-treatment results from a phase III randomized trial. J Hepatol 2026;85(3):493-503. — PubMed PMID: 41966308 · doi:10.1016/j.jhep.2026.03.046
PubMed Topic Searches
Connections
- All Herbs
- Chanca Piedra Overview
- Liver Protection (General)
- Active Compounds (Niranthin Detail)
- Forms, Dosing and Standardization
- Safety and Drug Interactions
- Phyllanthus Species Comparison
- Kidney Stones
- Hepatitis B
- Hepatitis
- Liver Disease
- Cirrhosis
- Non-Alcoholic Fatty Liver Disease
- Milk Thistle
- N-Acetylcysteine
- Gamma-Glutamyl Transferase
- Comprehensive Metabolic Panel
- Liver Cleansing