⚠ Evidence warning: Clinical trials or other evidence do not support the claims that silymarin may reduce chemotherapy mucositis, improves oxidative stress markers in type 2 diabetes and is an adjunct there, that intravenous silibinin is standard of care in Europe, and that a physician's death-cap protocol with alpha-lipoic acid, N-acetylcysteine and penicillin G is effective. This page keeps it as a report of what people, websites or other media say.
Milk Thistle for Antioxidant and Glutathione Support
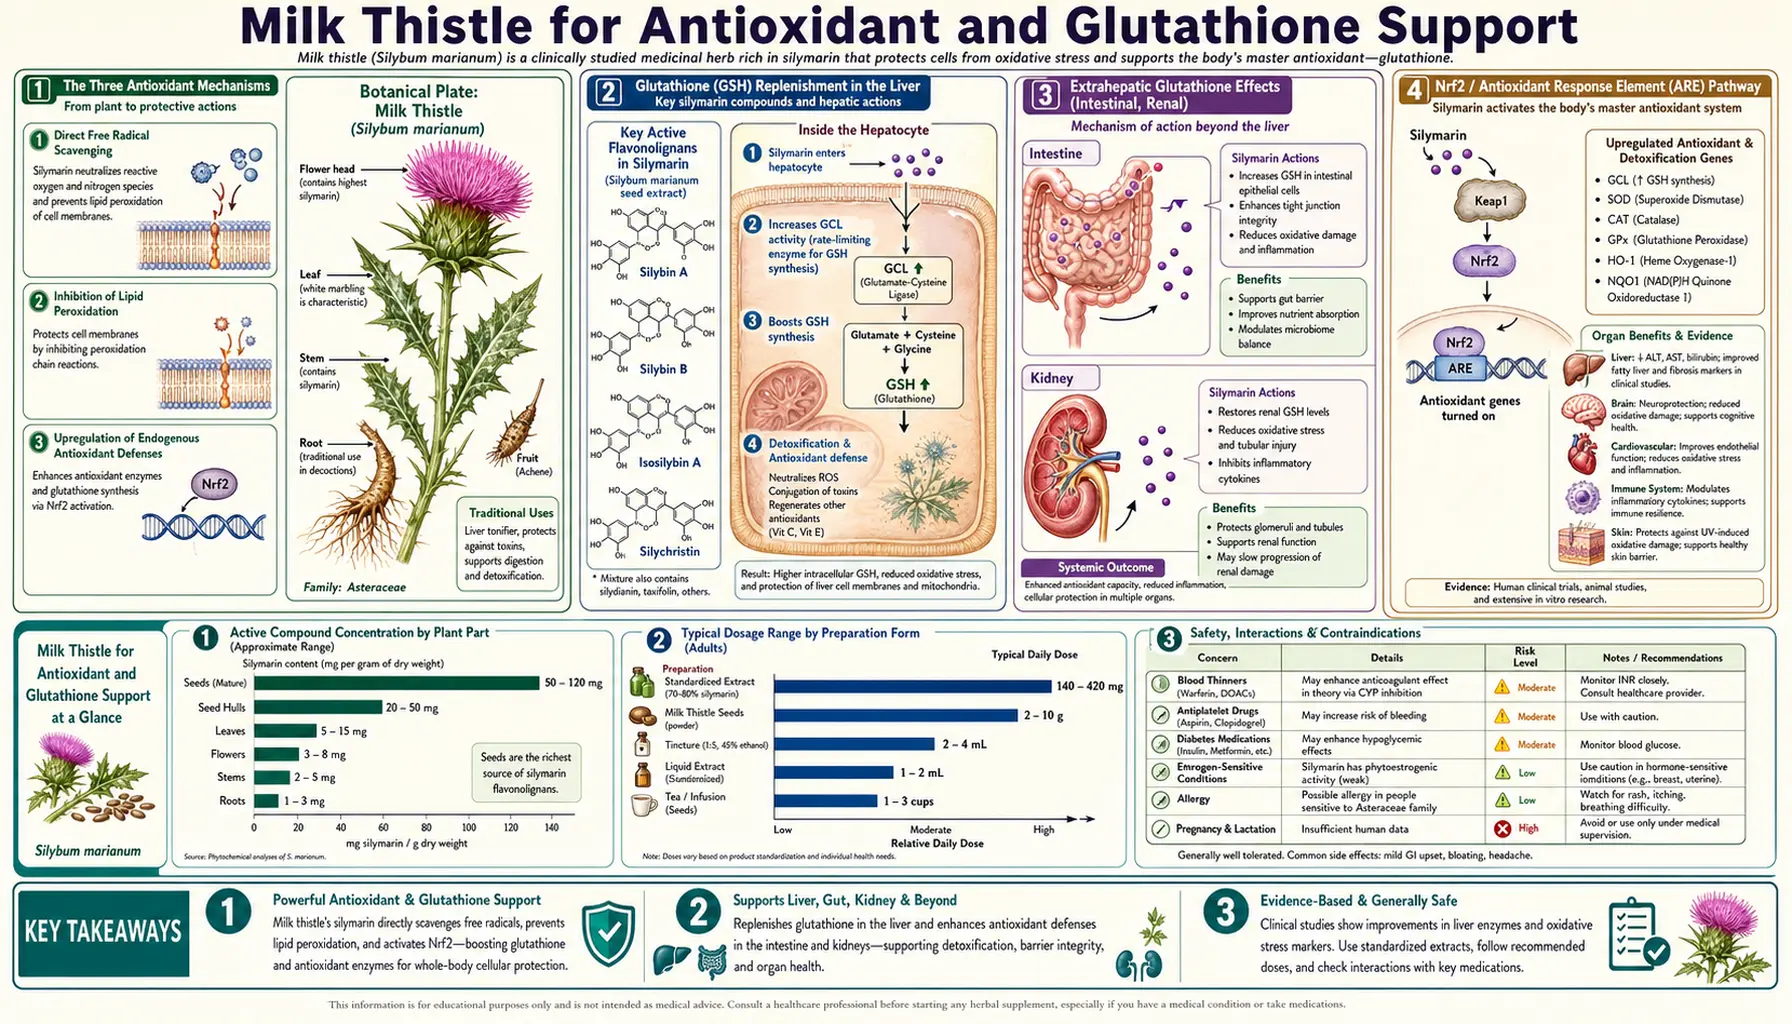
Most herbal "antioxidants" provide modest direct free-radical scavenging and stop there. Silymarin is unusual because it operates through three distinct antioxidant mechanisms that together produce an effect far larger than direct scavenging chemistry can explain. First, silymarin replenishes glutathione (reduced glutathione, GSH) — the body's principal water-soluble intracellular antioxidant — raising it in the liver and intestine of rats, and producing a small rise in red-blood-cell glutathione in a trial in people with alcoholic cirrhosis. Second, it activates the Nrf2 / antioxidant response element (ARE) master regulatory pathway, upregulating dozens of phase II detoxification and cytoprotective genes simultaneously. Third, it scavenges reactive oxygen species directly through its flavonolignan chemistry. The combined effect produces a clinically distinguishable hepatic-antioxidant footprint, and the reduced glutathione-replenishment mechanism in particular is why practitioners pair silymarin with N-acetylcysteine (NAC), alpha-lipoic acid, and selenium in liver-support protocols. This page details each mechanism, the comparison with N-acetylcysteine, the described combinations, the trials in fatty liver disease, and the clinical settings where silymarin has been studied.
Table of Contents
- The Three Antioxidant Mechanisms
- Glutathione (Reduced Glutathione) Replenishment in the Liver
- Extrahepatic Glutathione Effects (Intestinal, Renal)
- Nrf2 / Antioxidant Response Element (ARE) Pathway
- Phase II Detoxification Enzymes Upregulated
- Direct Free-Radical Scavenging Chemistry
- Silymarin vs N-Acetylcysteine Comparison
- Alpha-Lipoic Acid Synergy
- Selenium and Vitamin E Synergy
- Silymarin Trials in Fatty Liver Disease and the First Approved Medicine
- Clinical Applications — Oxidative Stress Conditions
- Dosing and Cautions
- Key Research Papers
- Connections
- Featured Videos
The Three Antioxidant Mechanisms
The antioxidant effect of silymarin is the most well-characterized of its biological activities and explains a substantial fraction of its clinical hepatoprotective benefit. Three distinct mechanisms operate in parallel:
- Glutathione replenishment — silymarin increases liver, intestinal and stomach glutathione (reduced glutathione) in rats (Valenzuela 1989) and produced a small rise in red-blood-cell glutathione in people with alcoholic cirrhosis (Lucena 2002), restoring the cell's principal endogenous water-soluble antioxidant. The mechanism is upregulation of glutamate-cysteine ligase (the rate-limiting enzyme in reduced glutathione synthesis) plus reduced glutathione consumption from less oxidative stress.
- Nrf2 / ARE pathway activation — silymarin disrupts the Keap1-Nrf2 cytoplasmic complex, freeing Nrf2 to translocate to the nucleus and activate transcription of hundreds of cytoprotective genes through ARE binding sites in their promoters. This is the master regulatory mechanism that ties together many of the discrete antioxidant effects.
- Direct scavenging — silymarin flavonolignans donate hydrogen atoms or electrons to reactive oxygen species (ROS), neutralizing them. The chemistry is conventional flavonoid antioxidant chemistry — the same kind that explains the antioxidant activity of green tea catechins, quercetin, and resveratrol — but is the smallest of the three contributions to overall effect.
The clinical consequence of this multi-mechanism architecture is that silymarin produces a larger antioxidant footprint than its direct scavenging activity alone would predict. Conversely, in vitro radical-trapping assays (DPPH, ORAC, etc.) systematically underestimate silymarin's clinical antioxidant effect, because they capture only mechanism 3 and miss mechanisms 1 and 2.
Glutathione (Reduced Glutathione) Replenishment in the Liver
Glutathione is a tripeptide (glutamate-cysteine-glycine) that serves as the cell's principal intracellular water-soluble antioxidant and is also the universal cofactor for the phase II glutathione S-transferase (GST) conjugation reactions that detoxify xenobiotic compounds before urinary excretion. Hepatic reduced glutathione concentrations are normally 5-10 mM — among the highest of any cell type in the body — reflecting the liver's role as the principal site of phase II xenobiotic detoxification.
In conditions of acute or chronic hepatic insult (alcohol exposure, acetaminophen overdose, toxic mushroom poisoning, viral hepatitis, non-alcoholic fatty liver disease (NAFLD)), hepatic reduced glutathione is rapidly depleted — sometimes to 20-40% of normal within hours. Reduced glutathione depletion is a key step in the cascade leading to hepatocellular necrosis: without reduced glutathione, the reactive metabolite N-acetyl-p-benzoquinoneimine (NAPQI) from acetaminophen overdose cannot be conjugated and instead covalently binds cellular proteins, killing the cell.
Silymarin restores hepatic reduced glutathione through two distinct mechanisms. First, it upregulates glutamate-cysteine ligase (GCLC), the rate-limiting enzyme in reduced glutathione biosynthesis from glutamate, cysteine, and glycine. This is the slow, sustained mechanism that produces durable reduced glutathione elevation with chronic dosing. Second, it reduces reduced glutathione consumption by lowering oxidative stress upstream of reduced glutathione demand — if the cell faces fewer reactive oxygen species to neutralize, less reduced glutathione is consumed per unit time.
The evidence comes from animal studies and one human trial. In rats, silymarin raised glutathione in the liver, intestine and stomach (Valenzuela 1989). In a 6-month randomized trial in 60 people with alcoholic cirrhosis (Lucena 2002), silymarin 150 mg three times a day (450 mg/day) raised red-blood-cell glutathione from 4.5 to 5.8 µmol per gram of hemoglobin, while it stayed about the same on placebo, and lowered a lipid-peroxidation marker in platelets (malondialdehyde, MDA) by 33%. The authors called the glutathione change “a small increase”, and routine liver blood tests did not change. Liver glutathione itself was not measured in that trial. The two strategies differ in mechanism — N-acetylcysteine (the standard pharmaceutical reduced glutathione-precursor strategy) delivers cysteine (the rate-limiting amino acid in reduced glutathione synthesis), while silymarin is reported to upregulate the enzyme that uses cysteine.
See our Glutathione page for the broader role of reduced glutathione in detoxification, immunity, and antioxidant defense.
Extrahepatic Glutathione Effects (Intestinal, Renal)
While the liver is the dominant site of silymarin's reduced glutathione effect, two extrahepatic effects are clinically important.
Intestinal reduced glutathione: Because oral silymarin has poor systemic absorption (20-50%) but is fully exposed to the intestinal epithelium during transit, intestinal cells receive higher silymarin concentrations than hepatocytes. Silymarin elevates intestinal reduced glutathione in animal studies of intestinal injury (chemotherapy-induced enteritis, radiation enteritis, nonsteroidal anti-inflammatory drug (NSAID)-induced enteropathy). This extrahepatic effect is being investigated as a possible adjunct to chemotherapy regimens to reduce mucositis. Milk thistle has also been tested in children on chemotherapy, for liver rather than gut toxicity: in a 2010 pilot trial (Ladas 2010), 50 children with acute lymphoblastic leukemia and chemotherapy-related liver toxicity took milk thistle or placebo by mouth for 28 days. Liver tests did not differ at day 28; at day 56 the milk thistle group had a lower AST liver enzyme and a trend toward lower ALT. Side effects and infections did not differ, and in laboratory tests milk thistle did not block the leukemia drugs vincristine or L-asparaginase.
Renal reduced glutathione: Kidney tubule cells are second only to hepatocytes in baseline reduced glutathione concentration and in vulnerability to oxidant-driven injury (radiocontrast nephropathy, aminoglycoside nephrotoxicity, cisplatin nephrotoxicity). In the rat study that found higher glutathione in the liver, intestine and stomach, silymarin did not change glutathione levels in the kidney, lung or spleen (Valenzuela 1989). In mice given an acetaminophen overdose, silymarin given afterwards for 7 days normalized kidney blood markers (urea and creatinine) and kidney tissue damage (Bektur 2016). Pilot trials in radiocontrast prophylaxis (where N-acetylcysteine has been the conventional intervention with mixed results) have included silymarin arms with suggestive but inconclusive benefit.
The skeptic's position: most of the strong reduced glutathione-elevation data is from hepatic tissue in animals at doses substantially above standard human dosing. Extrapolation to clinical effect on extrahepatic tissues at typical oral doses requires caution.
Nrf2 / Antioxidant Response Element (ARE) Pathway
Nrf2 (nuclear factor erythroid 2-related factor 2) is the master transcription factor regulating cellular antioxidant and cytoprotective gene expression. The Nrf2 pathway is now recognized as one of the central regulatory mechanisms of cellular antioxidant defense and has been the target of intensive drug discovery for the past two decades.
In the resting state, Nrf2 is sequestered in the cytoplasm bound to its inhibitor Keap1 (Kelch-like ECH-associated protein 1), which targets Nrf2 for proteasomal degradation. Oxidative stress, electrophilic stress, or specific phytochemical activators (sulforaphane from broccoli, curcumin from turmeric, silymarin from milk thistle) modify reactive cysteine residues on Keap1, disrupting the Keap1-Nrf2 complex. Freed Nrf2 then translocates to the nucleus, heterodimerizes with small Maf proteins, and binds antioxidant response elements (AREs) in the promoter regions of cytoprotective genes.
The downstream effect is broad. Several dozen genes are activated, including:
- NQO1 (nicotinamide adenine dinucleotide (NAD)(P)H quinone oxidoreductase 1) — reduces quinones to less-reactive hydroquinones
- HO-1 (heme oxygenase 1) — degrades heme, producing the antioxidant bilirubin
- GCLC and GCLM (glutamate-cysteine ligase catalytic and modifier subunits) — rate-limiting enzymes in reduced glutathione biosynthesis
- GST (glutathione S-transferases) — phase II conjugation
- SOD1 (superoxide dismutase 1) — superoxide neutralization
- UGT (UDP-glucuronosyltransferases) — phase II glucuronidation
- SLC7A11 (cystine-glutamate antiporter) — cysteine uptake supporting reduced glutathione synthesis
Silymarin is a well-documented Nrf2 activator at concentrations achievable with oral dosing. The downstream upregulation of NQO1, HO-1, GCLC, and GST has been confirmed in hepatocyte cell lines, animal models, and human peripheral blood mononuclear cell ex vivo studies. This is the mechanism that ties together silymarin's reduced glutathione-elevation effect, its phase-II detoxification enhancement, and much of its broader cytoprotection.
The Nrf2 mechanism is shared with curcumin, sulforaphane, and (to a lesser extent) green tea catechins, which is the rationale for combining these phytochemicals in liver-support and antioxidant protocols. Empirical evidence for additive or synergistic effect from combinations is preliminary but consistent.
Phase II Detoxification Enzymes Upregulated
"Phase II" detoxification refers to the conjugation reactions in the liver that take phase-I-oxidized intermediates and attach water-soluble groups (glutathione, glucuronic acid, sulfate, glycine, taurine, acetyl, methyl), rendering the compound water-soluble enough for urinary or biliary excretion. The phase II reactions are catalyzed by several distinct enzyme families, most of which are Nrf2-regulated and upregulated by silymarin.
The clinically most important phase II reactions and their silymarin response:
- Glutathione S-transferase (GST) conjugation — GST conjugates glutathione to electrophilic phase-I intermediates. Several GST isoforms (alpha, mu, pi, theta) are upregulated by Nrf2 activation. Silymarin produces modest GST induction in human and animal studies.
- UDP-glucuronosyltransferase (UGT) glucuronidation — UGT attaches glucuronic acid to hydroxyl, carboxyl, and amine groups. UGT1A1 (handling bilirubin), UGT1A6 (handling acetaminophen), and UGT2B7 (handling morphine, nonsteroidal anti-inflammatory drugs (NSAIDs)) are all upregulated by Nrf2. Silymarin shows modest UGT induction.
- Sulfotransferase (SULT) sulfation — SULT attaches sulfate. The Nrf2 effect on sulfation is smaller than on glutathione conjugation and glucuronidation.
- Nicotinamide adenine dinucleotide(P)H quinone oxidoreductase 1 (NQO1) — reduces toxic quinones to less-reactive hydroquinones. Strongly Nrf2-regulated and strongly silymarin-inducible.
The clinical translation: in patients with high xenobiotic burden (medication-heavy elderly, environmental-toxin-exposed workers, smokers, alcohol drinkers), enhanced phase II capacity is proposed to improve detoxification of xenobiotics, drugs, and endogenous oxidized metabolites. This is part of the rationale for milk thistle in general "liver support" protocols.
Direct Free-Radical Scavenging Chemistry
The third antioxidant mechanism — direct free-radical scavenging — is the most chemically straightforward but produces the smallest contribution to overall clinical effect. Silymarin flavonolignans have multiple hydroxyl groups (on the chroman and phenolic rings of silybin) that can donate hydrogen atoms to neutralize reactive oxygen species.
In standard in vitro radical-trapping assays:
- DPPH (1,1-diphenyl-2-picrylhydrazyl) radical scavenging — silybin shows IC50 approximately 8-15 µM, comparable to quercetin and somewhat less potent than vitamin E or epigallocatechin gallate (EGCG)
- ABTS (azinobis-3-ethylbenzothiazoline) radical scavenging — similar potency profile
- Hydroxyl radical scavenging — silybin is moderately effective
- Singlet oxygen quenching — modest activity
- Lipid peroxidation chain termination — effective at micromolar concentrations
The clinical limitation of direct-scavenging chemistry is that the achievable serum concentrations of silybin are typically in the low micromolar range (1-5 µM peak with standard oral dosing, somewhat higher with a silybin-phosphatidylcholine complex), which is below the IC50 for many of the direct scavenging assays. The clinical antioxidant effect is therefore not primarily driven by direct scavenging but by reduced glutathione elevation and Nrf2 induction, which produce sustained protective gene expression at lower silymarin concentrations.
The exception is the gastrointestinal lumen, where silymarin concentrations during absorption are much higher than circulating levels. Direct scavenging in the gut lumen may contribute to the intestinal-mucosal protective effect documented in chemotherapy-mucositis and nonsteroidal anti-inflammatory drug-enteropathy models.
Silymarin vs N-Acetylcysteine Comparison
N-Acetylcysteine is the conventional pharmaceutical agent for raising hepatic glutathione — it is the U.S. Food and Drug Administration-approved antidote for acetaminophen overdose and is widely used as a mucolytic and as a general glutathione precursor in integrative medicine. Comparing silymarin with N-acetylcysteine shows how the two differ.
| Property | N-acetylcysteine | Silymarin |
|---|---|---|
| Mechanism | Cysteine precursor (rate-limiting amino acid for reduced glutathione synthesis) | Upregulates GCLC enzyme; Nrf2 activation |
| Onset of reduced glutathione elevation | Hours (rapid) | Days to weeks (slower) |
| Magnitude of reduced glutathione elevation | Large with intravenous (IV) or high-dose oral | Small rise in red-blood-cell glutathione in one human trial (450 mg/day for 6 months) |
| Oral bioavailability | Modest (4-10%) | Modest (20-50%) |
| Acetaminophen antidote | U.S. Food and Drug Administration-approved, definitive (within 8-10 hours) | Not standard; supportive |
| Amanita antidote | Adjunctive; lower-tier | Intravenous silibinin: used in Europe as standard of care; no controlled trials |
| Chronic liver support | 600-1,200 mg/day described in practice | 420-450 mg/day in most trials; up to 2,100 mg/day in one fatty-liver trial |
| Cost | Inexpensive | Inexpensive to moderate |
| Tolerability | Sulfur odor; some gastrointestinal upset | Generally excellent |
| Pulmonary use | Mucolytic (nebulized or oral) | No respiratory indication |
For acute hepatic insult (acetaminophen overdose, the first 6-12 hours of amanita exposure), N-acetylcysteine is faster-acting and has more robust acute-care evidence. For chronic liver-support and oxidative-stress settings (chronic alcohol exposure, non-alcoholic fatty liver disease, environmental toxin exposure, recovery from past hepatic injury), practitioners favour silymarin on mechanistic grounds, because it is reported to upregulate reduced glutathione-synthesizing capacity rather than only providing precursor.
Practitioners describe using the two together — the mechanisms are complementary, not redundant — and integrative liver-support protocols commonly combine N-acetylcysteine 600 mg twice daily with silymarin 420 mg/day. There is no documented antagonism, and the cysteine-precursor + enzyme-induction combination is described as providing both rapid and sustained reduced glutathione elevation. See our N-acetylcysteine page for the broader N-acetylcysteine story.
Alpha-Lipoic Acid Synergy
Alpha-lipoic acid (ALA) is a sulfur-containing fatty acid that is both water- and lipid-soluble, allowing it to function as an antioxidant in both aqueous and membrane compartments. Its principal antioxidant role is recycling oxidized vitamin C and vitamin E back to their reduced active forms, indirectly extending the antioxidant lifetime of those vitamins. Alpha-lipoic acid also chelates transition metals, enhances insulin sensitivity, and supports mitochondrial bioenergetics.
The alpha-lipoic acid-silymarin combination has been described mainly in chronic hepatitis C. Milk thistle's best-known emergency use is different: poisoning by the death cap mushroom (Amanita phalloides) and related species. A 2012 review (Mengs 2012) states that amatoxin-containing mushrooms cause more than 90% of fatal mushroom poisonings worldwide; the first symptoms — abdominal cramps, vomiting and severe watery diarrhea — generally begin at least 6-8 hours after eating, and kidney and liver failure can follow. The protocol the review describes adds intravenous silibinin to aggressive intravenous fluids; alpha-lipoic acid is not part of it. Silibinin is reported to block specific liver transport proteins that take the toxin back up into liver cells, interrupting its circulation between the gut and the liver. There are no controlled trials, for ethical reasons. Pooled uncontrolled trials and case reports covering nearly 1,500 documented cases give an overall death rate under 10% with intravenous silibinin, compared with more than 20% with penicillin or penicillin plus silibinin. The review was written by research staff of the company that makes the intravenous silibinin product, together with a U.S. physician who treats these poisonings. A U.S. physician has also described a different protocol, combining intravenous silibinin with high-dose alpha-lipoic acid, N-acetylcysteine, penicillin G and supportive care; the review's death rates are for its own silibinin protocol, not for this combination.
Outside acute poisoning, practitioners describe the alpha-lipoic acid + silymarin combination in chronic liver disease. The mechanism rationale is multi-layered: alpha-lipoic acid recycles vitamin C and E, alpha-lipoic acid chelates iron in iron-overloaded livers (relevant in hemochromatosis and chronic hepatitis C virus-associated iron accumulation), silymarin elevates reduced glutathione and activates Nrf2, and the two together are proposed to give broader oxidative-stress coverage than either alone.
Amounts described in practitioner chronic liver-support protocols: silymarin 420 mg/day plus alpha-lipoic acid 300-600 mg/day in divided doses.
See our Antioxidants section for the broader antioxidant landscape and how individual agents complement each other.
Selenium and Vitamin E Synergy
Selenium is the central atom in selenoenzymes including glutathione peroxidase (GPx), the enzyme that uses reduced glutathione to reduce hydrogen peroxide to water. Without adequate selenium, GPx activity drops and oxidative stress increases regardless of reduced glutathione availability. Selenium deficiency is common in regions with selenium-poor soils (much of Europe, parts of China, parts of New Zealand).
The clinical logic for combining selenium with silymarin: silymarin elevates reduced glutathione, and selenium ensures that the reduced glutathione is being efficiently utilized by glutathione peroxidase. Selenium supplementation alone in low-selenium populations has been associated with reduced liver cancer incidence in observational studies. The combination is part of many integrative protocols for chronic hepatitis C virus (HCV) and chronic hepatitis B virus (HBV) infection described by practitioners, typically at selenium 100-200 µg/day (selenomethionine or yeast-bound forms).
Vitamin E (alpha-tocopherol) is the principal lipid-phase antioxidant, terminating lipid peroxidation chain reactions in cell membranes. Vitamin E is consumed (oxidized to the alpha-tocopheroxyl radical) when it performs this function and must be recycled back to its reduced form, traditionally via vitamin C and alpha-lipoic acid. In non-alcoholic fatty liver disease/non-alcoholic steatohepatitis (NASH), the 2010 PIVENS trial gave 247 adults without diabetes vitamin E 800 international units (IU)/day, pioglitazone or placebo for 96 weeks: liver biopsies improved in 43% on vitamin E versus 19% on placebo, but liver scarring (fibrosis) did not improve. Vitamin E has no U.S. Food and Drug Administration (FDA) approval for non-alcoholic steatohepatitis; the first medicine the FDA approved for it was resmetirom, in March 2024 (see the next section). Practitioners combine vitamin E with silymarin in non-alcoholic steatohepatitis on mechanistic grounds (membrane-phase antioxidant + reduced glutathione/Nrf2 enhancement), and it is a common integrative protocol.
Non-alcoholic steatohepatitis combination described in integrative practice: silymarin 420 mg/day + vitamin E 400-800 international units/day + selenium 100-200 µg/day.
Silymarin Trials in Fatty Liver Disease and the First Approved Medicine
Two newer sources measure silymarin directly in fatty liver disease:
- A 48-week biopsy trial (Wah Kheong 2017) — 99 adults in Malaysia with biopsy-proven non-alcoholic steatohepatitis took silymarin 700 mg three times a day (2,100 mg/day) or placebo, and had a second liver biopsy at 48 weeks. The main goal — a 30% or greater drop in the liver disease activity score — was reached by 32.7% on silymarin and 26.0% on placebo, a difference that was not significant. More people on silymarin had less scarring on biopsy (22.4% versus 6.0%) and a 30% or greater drop in liver stiffness (24.2% versus 2.3%). Side effects were no more common than on placebo. The authors write that the possible effect on scarring still needs to be confirmed in a larger trial.
- A 2024 meta-analysis of 26 randomized trials (Li 2024) — pooling 2,375 people with non-alcoholic fatty liver disease, it found that silymarin lowered the liver enzymes ALT and AST, total cholesterol, LDL cholesterol, triglycerides and fasting insulin, raised HDL cholesterol, and improved fat in the liver on biopsy. The authors state that these effects need to be confirmed by further research.
On 14 March 2024 the U.S. Food and Drug Administration approved resmetirom, a partial activator of a thyroid hormone receptor in the liver, for adults with non-cirrhotic non-alcoholic steatohepatitis and moderate to advanced liver scarring, to be used along with diet and exercise. The FDA described it as the first medication for these patients. It was approved on the accelerated pathway, based on liver biopsies at 12 months in a 54-month trial of 888 people that is still running to confirm its clinical benefit.
Clinical Applications — Oxidative Stress Conditions
Beyond classic liver disease, silymarin has been studied or used in several broader conditions characterized by significant oxidative stress:
- Type 2 diabetes — chronic hyperglycemia drives mitochondrial reactive oxygen species production and the formation of advanced glycation end products (AGEs). Silymarin trials in type 2 diabetes show modest reductions in fasting glucose and hemoglobin A1c (HbA1c), plus improvements in lipid panel and oxidative stress markers (MDA, GSH). The effect is small and would not replace metformin; silymarin is described as an adjunct, particularly in people with type 2 diabetes and concurrent non-alcoholic fatty liver disease. In a 4-month randomized trial in 51 people with type 2 diabetes (Huseini 2006), silymarin 200 mg three times a day added to their usual treatment lowered hemoglobin A1c (HbA1c), fasting blood glucose, total cholesterol, LDL cholesterol, triglycerides and two liver enzymes compared with placebo; that trial did not measure oxidative-stress markers. Silymarin was given alongside usual diabetes treatment, not instead of it. In people with fatty liver disease, the 2024 meta-analysis above also found lower fasting insulin with silymarin.
- Beta-thalassemia and iron overload — iron-overloaded patients have severe chronic oxidative stress as iron catalyzes Fenton-reaction generation of hydroxyl radicals. In a 3-month trial in 59 people with beta-thalassemia major on desferrioxamine (Gharagozloo 2009), silymarin 140 mg three times a day improved alkaline phosphatase (a liver enzyme) and red-blood-cell glutathione, but serum ferritin did not differ from placebo. In a 6-month trial in 40 children with beta-thalassemia major on deferasirox (Hagag 2013), serum ferritin fell more with silymarin than with placebo. In both trials silymarin was given together with iron chelation therapy, not instead of it.
- Drug-induced hepatotoxicity prophylaxis — pretreatment with silymarin before known hepatotoxic drug courses (anti-tuberculosis regimens with isoniazid + rifampin + pyrazinamide, chemotherapy with methotrexate or cisplatin, statins) is supported by animal data and small pilot trials. Practitioners describe 420 mg/day starting 1-2 weeks before such a course.
- Environmental toxin exposure — chronic occupational or environmental exposure to solvents, pesticides, heavy metals, or mycotoxins increases oxidative stress and depletes reduced glutathione. Silymarin is widely used in occupational-medicine integrative protocols for this population.
- Recovery from prolonged alcohol consumption — once a patient has achieved alcohol abstinence, silymarin during the first 6-12 months of recovery may accelerate hepatic regeneration and reduce residual oxidative stress markers.
- Mold/mycotoxin illness (chronic inflammatory response syndrome (CIRS), ochratoxin, aflatoxin exposure) — the Toxins section covers mycotoxin chemistry; silymarin is one of several agents used in detoxification-phase protocols. See Mold and Mycotoxins for the broader picture.
Dosing and Cautions
Doses used in trials: 420 mg/day of standardized silymarin in three divided doses (140 mg three times daily) is the long-used European hepatology dose (the 2009 thalassemia trial used it). Other trials on this page used 450 mg/day (Lucena 2002, alcoholic cirrhosis), 600 mg/day (Huseini 2006, type 2 diabetes) and 2,100 mg/day (Wah Kheong 2017, non-alcoholic steatohepatitis).
Combination protocols described by practitioners:
• Silymarin 420 mg/day + N-acetylcysteine 600 mg twice daily (basic protocol)
• Silymarin 420 mg/day + N-acetylcysteine 600 mg twice daily + alpha-lipoic acid 300-600 mg/day (intermediate)
• Silymarin 420 mg/day + N-acetylcysteine 600 mg twice daily + alpha-lipoic acid 300-600 mg/day + Selenium 200 µg/day + Vitamin E 400 international units/day (full non-alcoholic steatohepatitis or chronic-hepatitis adjunct)
With meals: practitioners describe taking it with a meal containing fat to improve oral absorption, and apart from high-fiber meals.
Duration: practitioner-described courses run 3-12 months; the trials on this page lasted from 28 days to 48 weeks, and in the 48-week trial side effects were no more common than on placebo. Long-term use is generally described as safe.
Cautions specific to the antioxidant role:
• Pro-oxidant paradox at very high doses — like many flavonoids, silymarin can switch from antioxidant to pro-oxidant behavior at supraphysiologic concentrations in vitro. The clinical relevance at oral doses is uncertain, but no additional benefit has been documented for doses above 2,100 mg/day of standard silymarin.
• Chemotherapy interaction caution — some chemotherapy agents work by inducing oxidative stress in tumor cells (doxorubicin, cisplatin, bleomycin). Concurrent high-dose antioxidant supplementation theoretically could reduce chemotherapy efficacy. The clinical data are mixed; oncology guidance is divided. Some practitioners leave out high-dose antioxidants on chemotherapy days and use silymarin on off-days or for hepatoprotection between cycles. In the 2010 childhood leukemia trial, milk thistle did not block vincristine or L-asparaginase in laboratory tests.
• Iron interaction — silymarin chelates iron and may reduce dietary iron absorption. For people low in iron (menstruating women, vegetarians, after bariatric surgery), practitioners describe spacing it 2-4 hours from iron-rich meals or iron supplements.
• Pregnancy/lactation — there is little safety data in pregnancy or breastfeeding.
Key Research Papers
- Valenzuela A, Aspillaga M, Vial S, Guerra R (1989). Selectivity of silymarin on the increase of the glutathione content in different tissues of the rat. Planta Med 55(5):420-2. — PubMed PMID: 2813578
- Kim S, Choi JH, Lim HI, Lee SK, Kim WW, Kim JS et al. (2009). Silibinin prevents TPA-induced MMP-9 expression and VEGF secretion by inactivation of the Raf/MEK/ERK pathway in MCF-7 human breast cancer cells. Phytomedicine 16(6-7):573-80. — PubMed PMID: 19181503
- Mereish KA, Bunner DL, Ragland DR, Creasia DA (1991). Protection against microcystin-LR-induced hepatotoxicity by silymarin: biochemistry, histopathology, and lethality. Pharm Res 8(2):273-7. — PubMed PMID: 1902564
- Surai PF (2015). Silymarin as a Natural Antioxidant: An Overview of the Current Evidence and Perspectives. Antioxidants (Basel) 4(1):204-47. — PubMed PMID: 26785346
- Huseini HF et al. (2006). The efficacy of Silybum marianum (L.) Gaertn. (silymarin) in the treatment of type II diabetes: a randomized, double-blind, placebo-controlled, clinical trial. Phytother Res 20(12):1036-9. — PubMed PMID: 17072885
- Gharagozloo M, Moayedi B, Zakerinia M, Hamidi M, Karimi M, Maracy M, Amirghofran Z (2009). Combined therapy of silymarin and desferrioxamine in patients with beta-thalassemia major: a randomized double-blind clinical trial. Fundam Clin Pharmacol 23(3):359-65. — PubMed PMID: 19453758
- Hagag AA, Elfrargy MS, Gazar RA, El-Lateef AE (2013). Therapeutic value of combined therapy with deferasirox and silymarin on iron overload in children with Beta thalassemia. Mediterr J Hematol Infect Dis 5(1):e2013065. — PubMed PMID: 24363880
- Bektur NE, Sahin E, Baycu C, Unver G (2016). Protective effects of silymarin against acetaminophen-induced hepatotoxicity and nephrotoxicity in mice. Toxicol Ind Health 32(4):589-600. — PubMed PMID: 24193058
- Kren V, Walterová D (2005). Silybin and silymarin — new effects and applications. Biomed Pap Med Fac Univ Palacky Olomouc Czech Repub 149(1):29-41. — PubMed PMID: 16170386
- Comelli MC et al. (2007). Toward the definition of the mechanism of action of silymarin: activities related to cellular protection from toxic damage. Integr Cancer Ther 6(2):120-9. — PubMed PMID: 17548791
- Lieber CS et al. (2003). Silymarin retards the progression of alcohol-induced hepatic fibrosis in baboons. J Clin Gastroenterol. — PubMed PMID: 14506392
- Polyak SJ, Ferenci P, Pawlotsky JM (2013). Hepatoprotective and antiviral functions of silymarin components in hepatitis C virus infection. Hepatology. — PubMed PMID: 23213025
- Lucena MI, Andrade RJ, de la Cruz JP, Rodriguez-Mendizabal M, Blanco E, Sánchez de la Cuesta F (2002). Effects of silymarin MZ-80 on oxidative stress in patients with alcoholic cirrhosis. Results of a randomized, double-blind, placebo-controlled clinical study. Int J Clin Pharmacol Ther 40(1):2-8. — PubMed PMID: 11841050
- Ladas EJ, Kroll DJ, Oberlies NH, Cheng B, Ndao DH, Rheingold SR, Kelly KM (2010). A randomized, controlled, double-blind, pilot study of milk thistle for the treatment of hepatotoxicity in childhood acute lymphoblastic leukemia (ALL). Cancer 116(2):506-13. — PubMed PMID: 20014183
- Mengs U, Pohl RT, Mitchell T (2012). Legalon® SIL: the antidote of choice in patients with acute hepatotoxicity from amatoxin poisoning. Curr Pharm Biotechnol 13(10):1964-70. — PubMed PMID: 22352731
- Sanyal AJ, Chalasani N, Kowdley KV, McCullough A, Diehl AM, Bass NM et al. (2010). Pioglitazone, vitamin E, or placebo for nonalcoholic steatohepatitis. N Engl J Med 362(18):1675-85. — PubMed PMID: 20427778
- Wah Kheong C, Nik Mustapha NR, Mahadeva S (2017). A Randomized Trial of Silymarin for the Treatment of Nonalcoholic Steatohepatitis. Clin Gastroenterol Hepatol 15(12):1940-1949.e8. — PubMed PMID: 28419855
- Li S, Duan F, Li S, Lu B (2024). Administration of silymarin in NAFLD/NASH: A systematic review and meta-analysis. Ann Hepatol 29(2):101174. — PubMed PMID: 38579127
- U.S. Food and Drug Administration (2024). FDA Approves First Treatment for Patients with Liver Scarring Due to Fatty Liver Disease. Press release, 14 March 2024. — FDA press release
PubMed Topic Searches
Connections
- All Herbs
- Milk Thistle Overview
- Milk Thistle Benefits Hub
- Liver Protection & Detox
- Hepatitis Adjunctive
- Skin Health
- N-Acetylcysteine
- Glutathione
- Oxidative Stress
- Liver Cleansing
- Detox Protocols
- Turmeric (Curcumin)
- Dandelion
- Liver Disease
- Non-Alcoholic Fatty Liver Disease/Non-Alcoholic Steatohepatitis
- Type 2 Diabetes
- Hemochromatosis
- Mold & Mycotoxins
- Vitamin C
- Selenium
- Comprehensive Metabolic Panel
- History