⚠ Evidence warning: Clinical trials or other evidence do not support the claim that thyme tea, culinary thyme or thyme-oil capsules relieve indigestion, bloating, irritable bowel syndrome or small intestinal bacterial overgrowth (no human trial of thyme alone for these complaints was found, and the nine-herb STW 5 trials test a product without thyme). This page keeps it as a report of what people, websites or other media say.
Thyme as a Digestive Aid
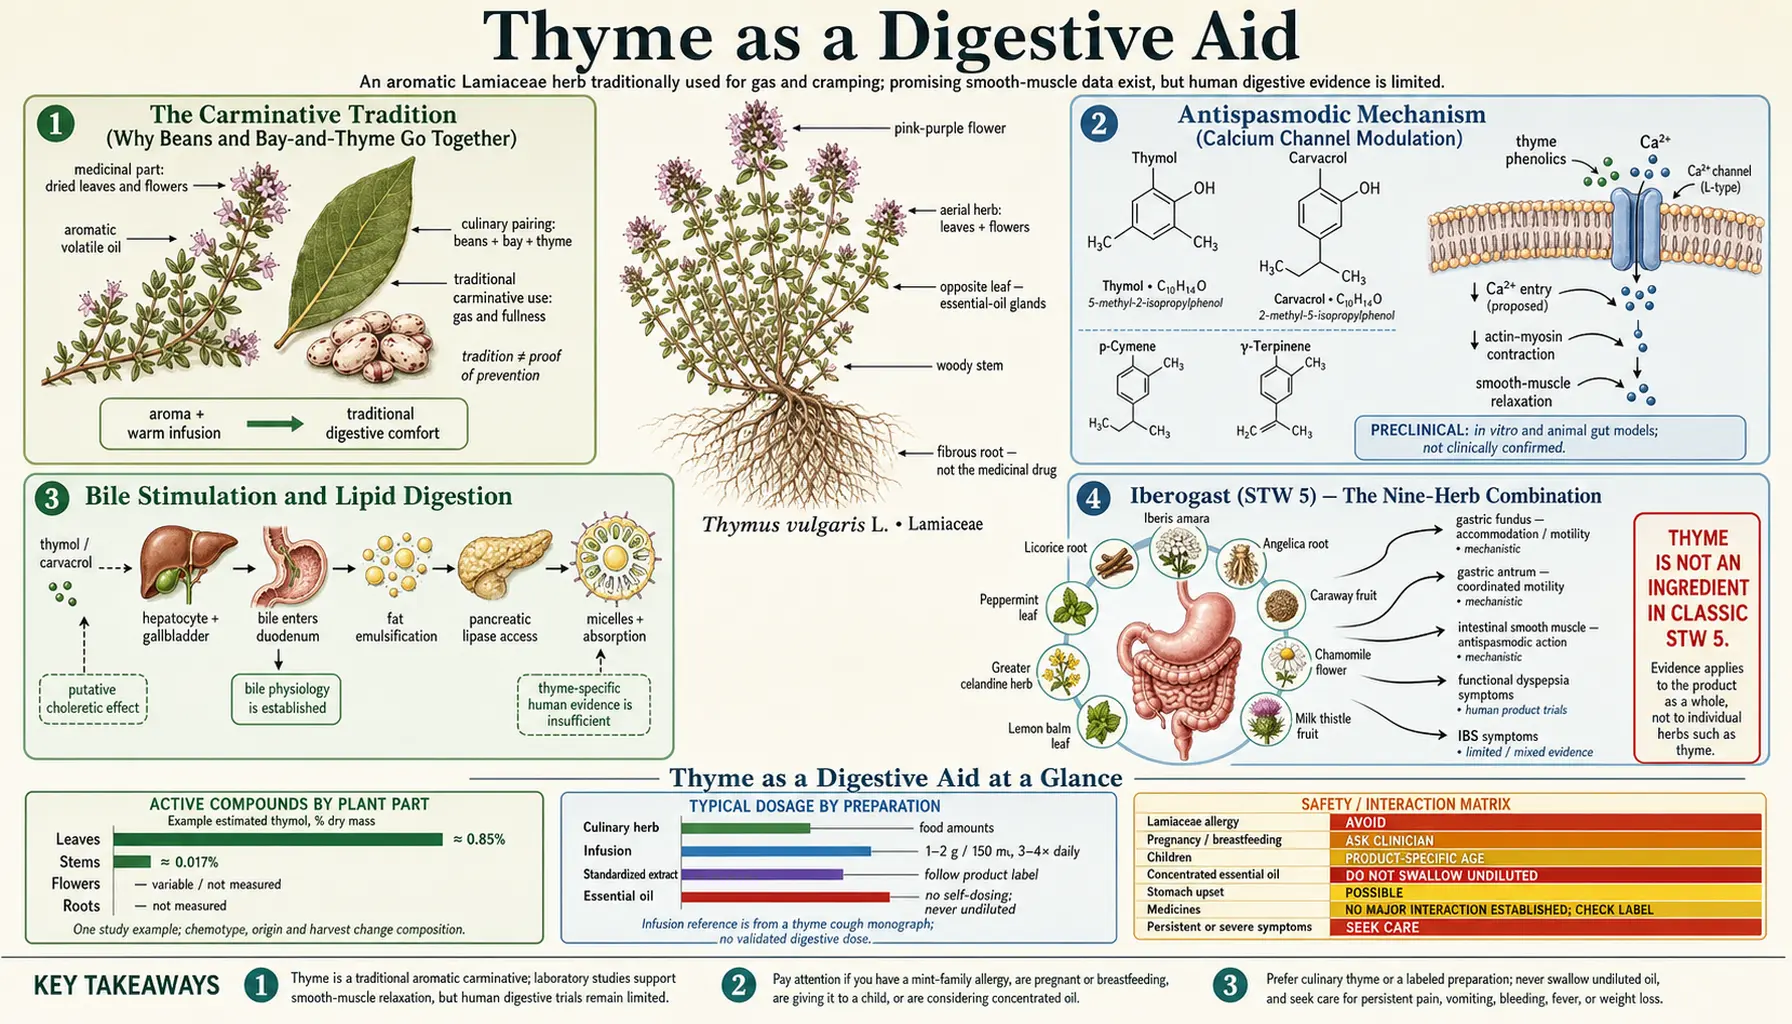
Thyme's long history as a culinary herb in southern European cooking is not just a flavor matter — thyme is traditionally added to bean dishes, fatty meats, and slow-stewed legumes because cooks credit it with relieving the bloating, flatulence, and post-prandial discomfort those foods otherwise produce. The proposed pharmacological basis is the same antispasmodic action studied in the respiratory indication: in animal-tissue experiments, thyme oil and thyme extracts relaxed gut muscle. A nine-herb German digestive preparation (research code STW 5) with European regulatory approval has a randomized-trial evidence base for functional dyspepsia and irritable bowel syndrome, but thyme is not one of its nine herbs (the published ingredient lists name peppermint), so those trials are context about multi-herb preparations, not evidence for thyme. The antimicrobial activity discussed in the parallel deep-dive also contributes to digestive use — thymol's suppression of pathogenic gut bacteria and overgrowth species can complement the muscle-relaxant action in mixed-etiology dyspepsia. This deep-dive walks through the antispasmodic mechanism, the carminative tradition, the STW 5 evidence (and why it is not thyme evidence), and the traditional use of thyme for indigestion, bloating, and irritable bowel syndrome (IBS).
Table of Contents
- The Carminative Tradition (Why Beans and Bay-and-Thyme Go Together)
- Antispasmodic Mechanism (What Laboratory Studies Show)
- Bile Stimulation and Lipid Digestion
- STW 5 — A Nine-Herb Combination That Does Not Contain Thyme
- Functional Dyspepsia (Indigestion)
- Irritable Bowel Syndrome (IBS)
- Antimicrobial Contribution to Digestive Use (Small Intestinal Bacterial Overgrowth, Dysbiosis)
- Preparation and Use for Digestive Complaints
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Carminative Tradition (Why Beans and Bay-and-Thyme Go Together)
A carminative is a substance that relieves gas and bloating by promoting expulsion of intestinal gas, reducing the cramping and discomfort of trapped gas, and often by reducing the production of gas through effects on intestinal motility and microbial fermentation. The traditional European carminative herbs include thyme, fennel, anise, caraway, peppermint, ginger, and chamomile — all of which contain aromatic essential oils with antispasmodic activity on intestinal smooth muscle.
Thyme's carminative reputation is preserved in the standard kitchen practice of adding bay leaves, thyme, savory, and other herbs to bean and lentil dishes. The combination known as a "bouquet garni" in French cooking (bay leaf, thyme, parsley, and often a leek leaf) is the canonical seasoning for slow-stewed meats, soups, and bean dishes — the flavor contribution is real, and tradition credits the herbs with a digestive contribution as well. Household tradition holds that a pot of beans cooked with bay and thyme produces less post-prandial bloating than the same pot cooked plain, a belief carried by centuries of household experience rather than by a study.
The Mediterranean / southern European cuisine that uses thyme most heavily is also the cuisine richest in legumes, slow-stewed fatty meats, and other high-fiber, hard-to-digest foods. The pairing is not accidental — the herbs and the foods co-evolved in regional cuisine because the herbs make the foods tolerable. The same pattern shows up in Indian cuisine (asafoetida, cumin, fennel, ginger added to dal and bean curry), Middle Eastern cuisine (cumin and coriander in falafel and chickpea dishes), and Latin American cuisine (epazote leaf added to black bean dishes). The carminative herb plus high-fiber food combination is a near-universal cultural pattern.
Antispasmodic Mechanism (What Laboratory Studies Show)
Gastrointestinal smooth muscle contracts in response to calcium influx through L-type voltage-gated calcium channels in the smooth muscle cell membrane. Excessive or uncoordinated contraction produces the painful cramping and altered motility patterns associated with functional dyspepsia, irritable bowel syndrome, and post-prandial bloating. Pharmaceutical antispasmodics for these conditions (hyoscyamine, dicyclomine, mebeverine) work by blocking either muscarinic acetylcholine receptors or directly inhibiting calcium channels on smooth muscle.
Laboratory studies on animal tissue show thyme relaxing gut muscle:
- Guinea-pig gut strips (1985). Reiter and Brandt compared the volatile oils of 22 plants. Sixteen of them calmed the rhythmic contractions of guinea-pig small-intestine (ileum) muscle, and thyme oil was among the five most potent, together with elecampane root, clove, balm leaves and angelica root oils.
- Rat gut and airway tissue (2010). Begrow and colleagues found that thymol and carvacrol relaxed rat airway muscle in a concentration-dependent way, and that a thyme extract with a normal thymol content relaxed rat ileum more than an extract almost free of thymol. The thymol-poor extracts still worked in every test except acetylcholine-induced ileum contraction, so the authors concluded that other, unidentified parts of thyme matter as well as thymol.
Explanations proposed for this relaxation include effects on calcium channels in the muscle cell and inhibition of phosphodiesterase (an enzyme whose blocking raises the muscle cell's cyclic AMP, a relaxing signal); the two studies above did not test these mechanisms. Both are animal-tissue results; whether the same relaxation happens in the human gut at tea or culinary doses was not measured in them.
The thyme flavonoid fraction (luteolin, apigenin, eriocitrin) is proposed to contribute additional antispasmodic activity, partly through calcium-channel effects and partly through modulation of neurotransmitter release at enteric neurons. The net effect of the combined essential oil + flavonoid fraction is described as a gentle, dose-dependent relaxation of gastrointestinal smooth muscle that reduces cramping and normalizes motility without significantly slowing transit. This is the proposed pharmacological basis for the traditional carminative use.
Notably, the antispasmodic effect is described as concentrated in the upper and middle gastrointestinal tract (esophagus, stomach, small intestine), with weaker effects on the colon. This is consistent with the clinical indication profile — thyme is better-established for upper-GI symptoms (indigestion, post-prandial bloating, epigastric cramping) than for lower-GI symptoms (colonic spasm of diarrhea-predominant irritable bowel syndrome (IBS-D), constipation of constipation-predominant irritable bowel syndrome (IBS-C)). For colonic-dominant irritable bowel syndrome symptoms, peppermint oil enteric-coated capsules (also a monoterpene mechanism, with menthol as the main active) have stronger evidence and target the lower bowel more effectively.
Bile Stimulation and Lipid Digestion
Beyond the antispasmodic effect, thyme has mild choleretic activity — it stimulates bile flow from the liver, which improves the digestion of dietary fats. The choleretic effect is shared with several other Lamiaceae herbs (rosemary, oregano, peppermint) and is mediated by aromatic essential oil constituents that signal cholecystokinin release from the duodenal endocrine cells. Cholecystokinin in turn stimulates gallbladder contraction and pancreatic enzyme secretion.
The clinical relevance is most apparent in patients with mild functional gallbladder dysmotility, post-cholecystectomy steatorrhea (fat intolerance after gallbladder removal), and the general fat-intolerance dyspepsia of older adults with declining bile production. Herbal tradition describes a cup of thyme tea taken 15-20 minutes before a fatty meal as reducing post-prandial fullness and right-upper-quadrant discomfort in these patients; the effect is described as modest, and it is not described as resolving symptoms in serious cholestatic disease.
For more on bile-related digestion and lipid absorption, see our pages on Gastroenterology and the related Rosemary page (rosemary has stronger documented choleretic activity than thyme but a similar mechanistic profile).
STW 5 — A Nine-Herb Combination That Does Not Contain Thyme
STW 5 (its research code) is a nine-herb German digestive preparation: a fluid combination of nine herbal extracts used in Europe for functional gastrointestinal disorders for over 60 years. A 2020 laboratory study of the preparation (Thumann 2020) and a 2001 trial report (Madisch 2001) list the nine herbs below. Thyme is not one of them — the ninth herb is peppermint — so the STW 5 trials described on this page say nothing directly about thyme. The nine herbs in the combination:
- Bitter candytuft (Iberis amara) — gives the product its name; bitter principle that increases gastric motility and tone
- Angelica root (Angelica archangelica) — carminative, mild antispasmodic
- Chamomile flower (Matricaria chamomilla) — antispasmodic, anti-inflammatory
- Caraway fruit (Carum carvi) — classic carminative
- Milk thistle fruit (Silybum marianum) — hepatoprotective, antioxidant
- Lemon balm (Melissa officinalis) — antispasmodic, mild sedative
- Greater celandine (Chelidonium majus) — antispasmodic on biliary tract (note: linked to occasional liver injury, the reason the product carries a liver warning)
- Licorice root (Glycyrrhiza glabra) — mucosal protective, mild anti-inflammatory
- Peppermint leaves (Mentha × piperita) — antispasmodic, carminative
The fluid extract is taken as drops in a small amount of water before meals; the trials gave 20 drops three times daily. The preparation has German Drug Authority registration for symptoms of functional dyspepsia (epigastric pain, post-prandial fullness, early satiety, nausea) and irritable bowel syndrome (cramping, bloating, alternating bowel habits). It is widely available over-the-counter in Germany and across Europe; in the United States it is sold as a dietary supplement.
The combination is pharmacologically rational because it pairs prokinetic activity (the bitter candytuft) with antispasmodic activity (peppermint, chamomile, lemon balm, caraway), mucosal protection (licorice, milk thistle), and bile-flow stimulation (angelica, celandine). The aggregate effect is a normalization of gastrointestinal motility — speeding up sluggish gastric emptying while relaxing spastic small-intestinal contractions, the two dysmotility patterns most commonly responsible for the symptoms of functional dyspepsia.
Functional Dyspepsia (Indigestion)
Functional dyspepsia is one of the most common gastrointestinal complaints in primary care — up to 20% of adults report at least monthly symptoms of post-prandial fullness, epigastric pain, early satiety, or nausea without identifiable structural disease on endoscopy. Conventional management is limited: proton pump inhibitors help a subset of acid-mediated cases, prokinetics (metoclopramide, domperidone) help motility-mediated cases but have significant side effects, and tricyclic antidepressants help visceral-hypersensitivity-mediated cases at the cost of considerable side-effect burden. The condition is therefore a major target for phytotherapy.
The evidence for the nine-herb preparation STW 5 in functional dyspepsia comes from trials of the whole mixture, which contains no thyme:
- von Arnim et al. (2007). Placebo-controlled trial in 315 treated patients with functional dyspepsia (308 in the intention-to-treat analysis), 20 drops three times daily for 8 weeks. The Gastrointestinal Symptom Score improved by 6.9 points on STW 5 and by 5.9 points on placebo (p < 0.05); tolerability and safety were similar in both groups.
- Madisch et al. (2004). 120 patients with functional dyspepsia received STW 5-II, a six-herb research version (bitter candytuft, chamomile, peppermint, caraway, licorice and lemon balm), or placebo. After 8 weeks, 43.3% on the herbal preparation and 3.3% on placebo reported complete relief of symptoms (p < 0.001).
- Rösch et al. (2002). 186 patients with the dysmotility type of functional dyspepsia were randomly assigned to STW 5, the research version STW 5-II, or cisapride (a prokinetic since withdrawn for cardiac arrhythmia risk) for four weeks. In the 137 patients of the main analysis, both herbal preparations were shown to be not inferior to cisapride, and there were no statistically significant differences in the secondary endpoints, which included tolerability.
- Melzer et al. (2004), meta-analysis. Pooled data from three placebo-controlled trials showed STW 5 (138 patients) to be more effective than placebo (135 patients) on the severity of the most bothersome gastrointestinal symptom (odds ratio 0.22, p = 0.001); adverse events were similar with STW 5 and placebo, and a fourth trial showed no significant difference between STW 5 and cisapride.
Herbal tradition uses simple thyme tea (1-2 teaspoons dried thyme in 250 mL boiling water, steeped 10 minutes, strained, sipped 15-30 minutes before meals 2-3 times daily) for indigestion at near-zero cost; because STW 5 contains no thyme, its trials do not measure this use. Herbalists also describe pairing thyme tea with a brief walk after meals for mild post-prandial dyspepsia.
Irritable Bowel Syndrome (IBS)
Irritable bowel syndrome affects approximately 10-15% of adults globally and is characterized by abdominal pain associated with altered bowel habits (constipation, diarrhea, or both alternating) in the absence of identifiable structural disease. The conventional pharmacotherapy is limited and the side-effect burden of several effective drugs (rifaximin, eluxadoline, lubiprostone, linaclotide) makes phytotherapy an attractive complementary or alternative approach.
Thyme's direct evidence base for irritable bowel syndrome is modest; it comes up in three main contexts:
- In discussions of STW 5, a nine-herb preparation that does not contain thyme. Its irritable bowel syndrome trial (Madisch 2004) randomly assigned 208 patients to STW 5 (51 patients), the six-herb research version STW 5-II (52), bitter candytuft alone (53) or placebo (52). After 4 weeks, STW 5 and STW 5-II reduced the abdominal pain score and the irritable bowel syndrome symptom score more than placebo, while bitter candytuft alone did not differ from placebo. Because thyme is not in the mixture, this trial says nothing directly about thyme.
- As a standalone for mild bloating-predominant irritable bowel syndrome. Herbalists describe thyme tea or thyme + fennel tea taken 2-3 times daily, especially before and after meals, as reducing the post-prandial bloating that is the most-frequent specific complaint in irritable bowel syndrome subtypes.
- As an adjunct in small intestinal bacterial overgrowth-associated irritable bowel syndrome. A subset of irritable bowel syndrome is now understood to be driven by small intestinal bacterial overgrowth (SIBO) — the same antimicrobial properties of thyme essential oil discussed in the parallel deep-dive translate to a role in herbal small intestinal bacterial overgrowth eradication protocols. For more on this, see the small intestinal bacterial overgrowth deep-dive hub and its sub-articles.
For comparison: enteric-coated peppermint oil (commonly 180-225 mg capsules, 1-2 capsules three times daily before meals) has the strongest evidence base of any single botanical for irritable bowel syndrome. A 2011 Cochrane review found that antispasmodic medicines as a group helped irritable bowel syndrome (number needed to treat 3 for the symptom score and 5 for the global assessment), with peppermint oil one of the subgroups that showed a significant benefit. A 2022 meta-analysis of 10 trials in 1,030 people found that for every 4 people treated with peppermint oil, 1 more had improved global symptoms than on placebo, and for every 7 treated, 1 more had less abdominal pain; side effects were more common on peppermint oil, and the authors rated the quality of the evidence as very low. Thyme is mechanistically similar but has less randomized controlled trial-level evidence in irritable bowel syndrome specifically.
Antimicrobial Contribution to Digestive Use (Small Intestinal Bacterial Overgrowth, Dysbiosis)
The broad-spectrum antimicrobial activity of thymol and carvacrol discussed in the parallel Antimicrobial Spectrum deep-dive has a specific application in gut dysbiosis and small intestinal bacterial overgrowth (SIBO). In small intestinal bacterial overgrowth, bacteria normally restricted to the colon proliferate in the small intestine, producing excessive hydrogen, methane, and (rarely) hydrogen sulfide gas through fermentation of small-bowel carbohydrates. The symptom profile — post-prandial bloating, abdominal pain, altered bowel habits — overlaps extensively with irritable bowel syndrome and functional dyspepsia.
Practitioners' herbal small intestinal bacterial overgrowth eradication protocols (popularized by the Chedid 2014 study comparing herbal antimicrobials to rifaximin) typically include a phenolic-monoterpene component — either oregano oil capsules, thyme oil capsules, or both, often combined with berberine-containing herbs (Oregon grape, goldenseal, barberry), neem, or wormwood. The phenolic monoterpene targets gram-negative coliforms and gram-positive overgrowth species in the small bowel through the membrane-disruption mechanism. The thyme essential oil dose practitioners describe in such a protocol is 1-2 enteric-coated 100-200 mg capsules twice daily for 4-6 weeks, with the enteric coating intended to ensure the oil reaches the small bowel rather than dissolving in the stomach.
The Chedid 2014 study is the main published comparison, but it was not a randomized trial: it was a review of patient records from a tertiary-care gastroenterology practice. 104 patients with newly diagnosed small intestinal bacterial overgrowth on a lactulose breath test, who had a repeat test after treatment, had chosen either rifaximin 1,200 mg daily (the conventional standard) or herbal therapy for 4 weeks. The herbal therapy was one of two pairs of commercial herbal antimicrobial formulas, one of which contained red thyme oil. The repeat breath test was negative in 17 of 37 patients on the herbs (46%) and in 23 of 67 on rifaximin (34%), a difference that was not statistically significant (P = .24). Side effects reported on rifaximin included 1 case of anaphylaxis, 2 of hives, 2 of diarrhea and 1 of Clostridium difficile infection, against 1 case of diarrhea on the herbs, a difference that was not statistically significant (P = .22). The authors put the cost of the herbal therapy at no more than $120 for a 30-day supply.
Taken together: thyme essential oil appears in herbal small intestinal bacterial overgrowth eradication protocols, and the one published comparison, a non-randomized record review, found the herbal formulas at least as effective as prescription rifaximin on the repeat breath test. Practitioners describe the combination of antispasmodic + antimicrobial activity in thyme as well matched to the small intestinal bacterial overgrowth clinical phenotype.
Preparation and Use for Digestive Complaints
Traditional and practitioner preparations differ by use:
- Mild post-prandial bloating / functional dyspepsia. The traditional preparation is thyme tea (1-2 teaspoons dried thyme in 250 mL boiling water, steeped 10 minutes covered, strained) sipped 15-30 minutes before meals and again 30-60 minutes after meals. Herbalists sometimes add fennel seed (1 teaspoon crushed fennel in the same infusion) for an additive carminative effect.
- STW 5 (the nine-herb preparation, which contains no thyme) for functional dyspepsia or irritable bowel syndrome. 20 drops in a small amount of water three times daily before meals is the usual use; the trials ran 4-8 weeks. Users report improvement in the first 1-2 weeks.
- Bouquet garni / culinary thyme for high-fiber meals. Cooks add 2-3 sprigs of fresh thyme (or 1 teaspoon dried thyme) to bean dishes, lentil soups, slow-stewed meats, and other carminative-needing meals, and remove the sprigs before serving. This is the lowest-dose form of thyme and is ordinary daily, long-term food use.
- Thyme tincture. Herbalists describe 2-4 mL in a small amount of warm water, 15-30 minutes before meals; it is convenient for travel.
- Enteric-coated thyme essential oil capsules for small intestinal bacterial overgrowth / dysbiosis. Practitioner protocols describe 100-200 mg capsules, 1-2 capsules twice daily, 4-6 weeks, often as part of a commercial herbal antimicrobial formula. Practitioners describe small intestinal bacterial overgrowth management as more complex than a single antimicrobial course.
- Thyme + ginger tea for nausea. The traditional recipe combines 1 teaspoon dried thyme + 1 teaspoon grated fresh ginger + 250 mL boiling water, steeped 10 minutes, strained and sipped slowly. Ginger is credited with direct anti-nausea activity (5-HT3 receptor antagonism) and thyme with antispasmodic relief.
Herbalists describe onset within 30-60 minutes for the antispasmodic effect, sustained 3-4 hours, dose-dependent. For chronic functional dyspepsia or irritable bowel syndrome, the STW 5 trials ran 4-8 weeks, the same timeframe herbalists describe for judging whether a remedy is working.
Cautions and Drug Interactions
- STW 5 and liver safety. The nine-herb preparation carries a hepatotoxicity warning due to rare idiosyncratic liver injury attributed primarily to its greater celandine component (thyme is not an ingredient). The German regulator updated the product warning in 2018 after an estimated 50 cases of significant liver injury over decades of use. A 2022 case report describes a 32-year-old woman with no earlier illness who came to an emergency department with abdominal pain, jaundice and itching; blood tests showed acute severe hepatitis, doctors attributed it to the preparation after ruling out other causes, and her symptoms resolved about 5 weeks after she stopped taking it. Jaundice, dark urine, or right-upper-quadrant pain are signs of liver injury that hospitals treat as urgent; liver function tests are the blood tests that measure it. A reformulated version of the product removed greater celandine to address this issue.
- Pregnancy. Culinary thyme is ordinary food in pregnancy, and medicinal-dose thyme tea is traditionally regarded as acceptable. Thyme essential oil capsules (the small intestinal bacterial overgrowth protocol dose) carry a high phenolic monoterpene exposure, and there is no good safety data for them in pregnancy. The nine-herb preparation STW 5 is generally not used in pregnancy.
- Active gastric ulcer. Thyme essential oil at high dose may irritate ulcerated mucosa. Mild thyme tea is generally tolerated and may even be slightly protective; the concern applies to high-dose capsules during active ulcer treatment.
- Concurrent calcium channel blockers. Theoretical additive hypotensive effect, but practically negligible at culinary or moderate medicinal doses. High-dose thyme essential oil capsules in a patient on multiple antihypertensives could theoretically lower blood pressure further.
- Anticoagulants. Theoretical antiplatelet additive effect; clinically minimal at culinary or tea doses. The theoretical concern is greatest for high-dose essential oil capsules in people taking warfarin.
- Selective serotonin reuptake inhibitors (SSRIs) and serotonergic drugs. No clinically reported interaction. A theoretical concern exists if combined with serotonergic irritable bowel syndrome drugs (alosetron, eluxadoline) due to possible additive 5-HT-modulating activity, but no published reports of adverse interaction.
- Allergy. Lamiaceae cross-reactivity (mint, oregano, sage, rosemary, basil). A rash or swelling inside the mouth after thyme are signs of an allergic reaction.
- Inflammatory bowel disease. Mild thyme tea is generally tolerated. The concern with high-dose thyme essential oil capsules during an active inflammatory bowel disease (IBD) flare is that the membrane-active mechanism could exacerbate mucosal inflammation.
Key Research Papers
- Madisch A et al. (2004). Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial. Digestion. — PubMed PMID: 14755152
- von Arnim U et al. (2007). STW 5, a phytopharmacon for patients with functional dyspepsia: results of a multicenter, placebo-controlled double-blind study. American Journal of Gastroenterology. — PubMed PMID: 17531013
- Madisch A et al. (2004). Treatment of irritable bowel syndrome with herbal preparations: results of a double-blind, randomized, placebo-controlled, multi-centre trial. Alimentary Pharmacology & Therapeutics. — PubMed PMID: 14984373
- Melzer J et al. (2004). Meta-analysis: phytotherapy of functional dyspepsia with the herbal drug preparation STW 5 (Iberogast). Alimentary Pharmacology & Therapeutics. — PubMed PMID: 15606389
- Thumann TA et al. (2020). Application of an in vitro digestion model to study the metabolic profile changes of an herbal extract combination by UHPLC-HRMS. Phytomedicine. (lists the nine herbs of STW 5) — PubMed PMID: 32447246
- Madisch A et al. (2001). A plant extract and its modified preparation in functional dyspepsia. Results of a double-blind placebo controlled comparative study. Zeitschrift fur Gastroenterologie. (in German) — PubMed PMID: 11505331
- Rösch W et al. (2002). A randomised clinical trial comparing the efficacy of a herbal preparation STW 5 with the prokinetic drug cisapride in patients with dysmotility type of functional dyspepsia. Zeitschrift fur Gastroenterologie. — PubMed PMID: 12055663
- Chedid V et al. (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine. — PubMed PMID: 24891990
- Begrow F et al. (2010). Impact of thymol in thyme extracts on their antispasmodic action and ciliary clearance. Planta Medica. — PubMed PMID: 19809973
- Engelbertz J et al. (2008). Thyme extract, but not thymol, inhibits endothelin-induced contractions of isolated rat trachea. Planta Medica. — PubMed PMID: 18729040
- Reiter M, Brandt W (1985). Relaxant effects on tracheal and ileal smooth muscles of the guinea pig. Arzneimittelforschung. (early mechanistic study) — PubMed PMID: 4039178
- Salehi B et al. (2018). Thymol, thyme, and other plant sources: Health and potential uses. Phytotherapy Research. — PubMed PMID: 29785774
- Pittler MH, Ernst E (1998). Peppermint oil for irritable bowel syndrome: a critical review and metaanalysis. American Journal of Gastroenterology. (related monoterpene context) — PubMed PMID: 9672344
- Ruepert L et al. (2011). Bulking agents, antispasmodics and antidepressants for the treatment of irritable bowel syndrome. Cochrane Database of Systematic Reviews. — PubMed PMID: 21833945
- Ingrosso MR et al. (2022). Systematic review and meta-analysis: efficacy of peppermint oil in irritable bowel syndrome. Alimentary Pharmacology & Therapeutics. — PubMed PMID: 35942669
- Leroy A et al. (2022). Iberogast®-Induced Acute Liver Injury-A Case Report. Gastro Hep Advances. — PubMed PMID: 39132058
PubMed Topic Searches
Connections
- All Herbs
- Thyme Overview
- Thyme Benefits Hub
- Thyme for Respiratory Health
- Thyme Antimicrobial Spectrum
- Thyme Antioxidant & Acne
- Oregano (Carvacrol Cousin)
- Rosemary
- Sage
- Lemon Balm
- Small Intestinal Bacterial Overgrowth
- Gastroenterology
- Escherichia Coli
- Honey
- Gut Healing
- Immune Boosting
- Functional Dyspepsia — the condition most studied with STW 5, a nine-herb preparation that does not contain thyme.
- History