⚠ Evidence warning: Clinical trials or other evidence do not support the claim that diluted thyme essential oil treats bacterial and fungal skin infections, nail fungus, wound infection and head lice, or that short internal courses of thyme essential oil work as an antimicrobial treatment. This page keeps it as a report of what people, websites or other media say.
Thyme Antimicrobial Spectrum
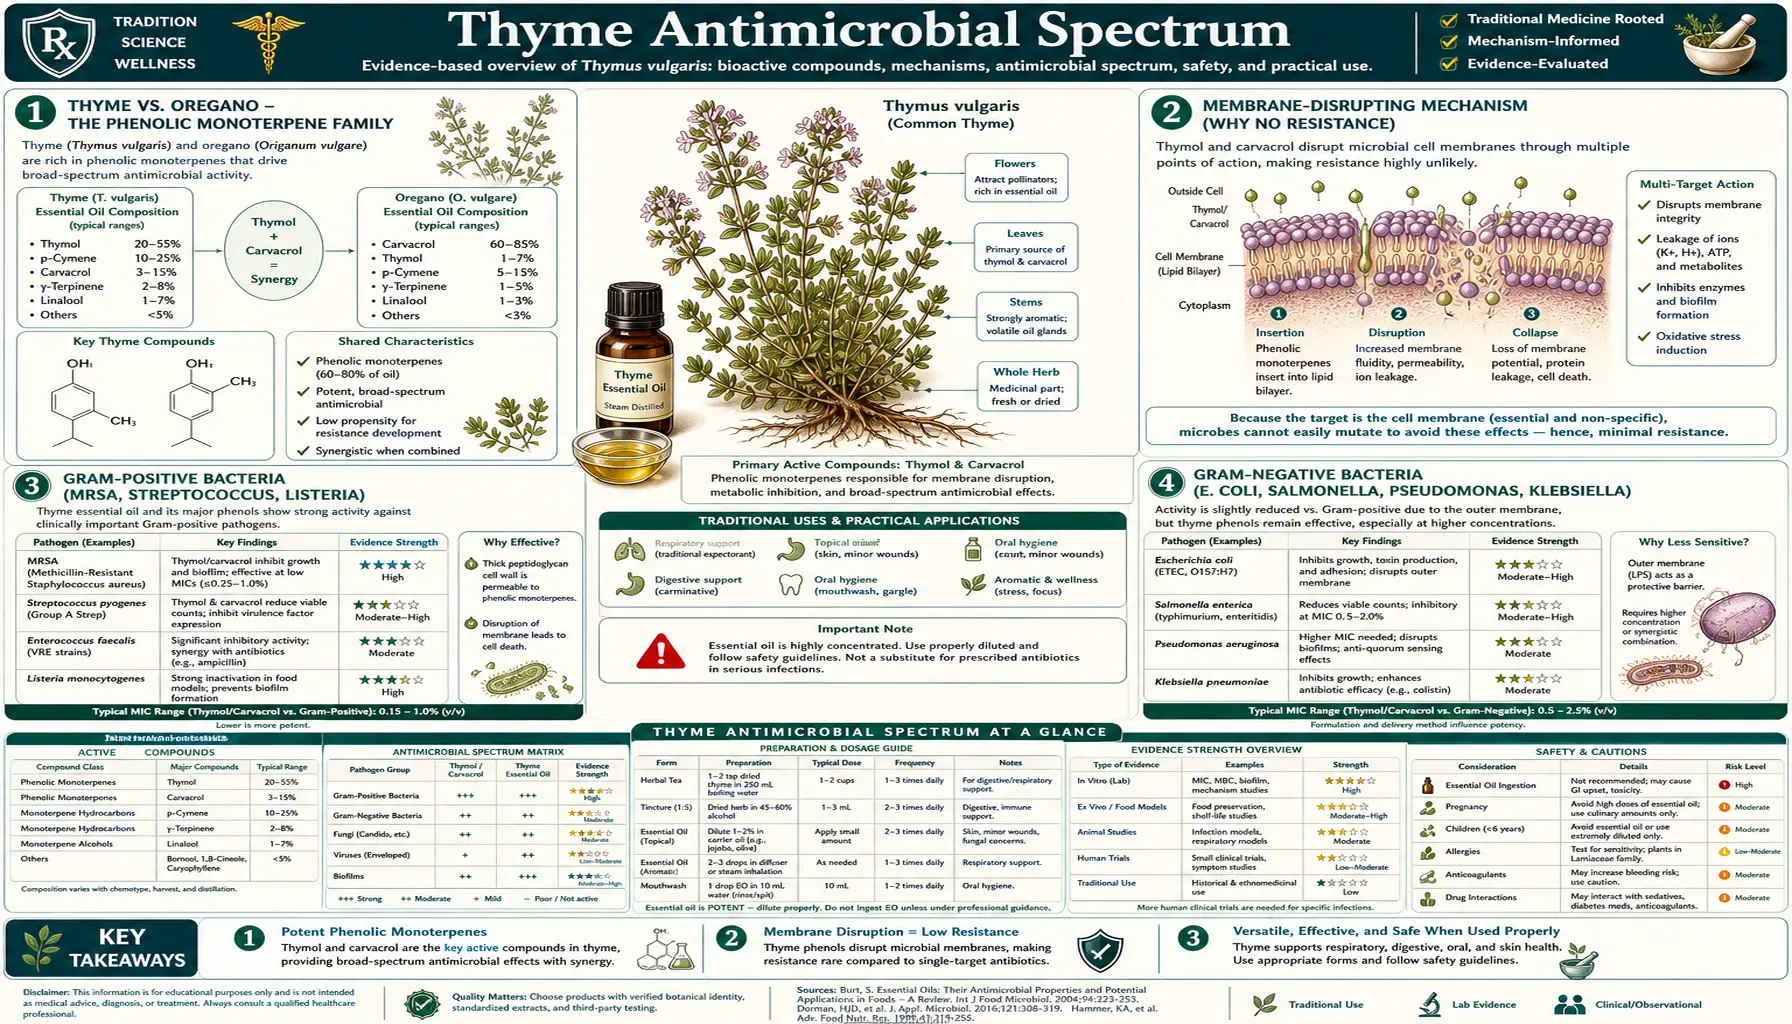
Thyme essential oil ranks alongside oregano oil as one of the two most broad-spectrum and most potent antimicrobial essential oils in the herbal pharmacy — the two herbs share the dominant active phenolic monoterpenes thymol and carvacrol but in different proportions. Published minimum inhibitory concentration (MIC) data document activity against a wide range of clinically important pathogens: methicillin-resistant Staphylococcus aureus (MRSA), Candida albicans (including fluconazole-resistant isolates), Escherichia coli, Salmonella enterica, Pseudomonas aeruginosa, Listeria monocytogenes, Klebsiella pneumoniae, and the dermatophytes Trichophyton and Microsporum. The applied uses fall into three categories: oral / dental antimicrobials (thymol is a principal active in an essential-oil mouthrinse (thymol, eucalyptol, menthol and methyl salicylate), in concentrations that have been clinically validated for plaque and gingivitis reduction), food preservation (thyme essential oil is on the U.S. Food and Drug Administration (FDA) generally recognized as safe (GRAS) list as a food additive and is increasingly used in antimicrobial food packaging and natural-preservative formulations), and topical therapeutic preparations (skin, nail, wound). This deep-dive walks through the minimum inhibitory concentration data by pathogen class, the membrane-disrupting mechanism that distinguishes phenolic-monoterpene antimicrobials from beta-lactam antibiotics, the clinical mouthwash and dental literature, and the chemotype variability that determines what a given thyme essential oil contains.
Table of Contents
- Thyme vs. Oregano — The Phenolic Monoterpene Family
- Membrane-Disrupting Mechanism and Bacterial Adaptation
- Gram-Positive Bacteria (Methicillin-Resistant Staphylococcus Aureus, Streptococcus, Listeria)
- Gram-Negative Bacteria (E. coli, Salmonella, Pseudomonas, Klebsiella)
- Antifungal Activity (Candida, Dermatophytes, Aspergillus)
- Oral and Dental Applications (Essential-Oil Mouthwash and Thymol)
- Food Preservation and Antimicrobial Packaging
- Topical Skin and Nail Applications
- Chemotype Variability (Thymol vs. Carvacrol vs. Linalool)
- Cautions for Internal Antimicrobial Use
- Key Research Papers
- Connections
- Featured Videos
Thyme vs. Oregano — The Phenolic Monoterpene Family
Thyme and oregano are closely related Lamiaceae (mint family) herbs that share the same dominant active chemistry — the phenolic monoterpene isomers thymol and carvacrol — in different proportions. The structural difference between the two molecules is a single methyl-group position on the aromatic ring; functionally they are nearly interchangeable, with carvacrol being slightly more potent than thymol against most tested pathogens.
- Common thyme (Thymus vulgaris, thymol chemotype) — typically 40-60% thymol, 5-15% carvacrol, 15-25% p-cymene, 5-10% gamma-terpinene, with thymol clearly dominant
- Oregano (Origanum vulgare, Mediterranean type) — typically 50-80% carvacrol, 5-15% thymol, 5-15% p-cymene, with carvacrol clearly dominant
- Spanish thyme (Thymus zygis) — intermediate, often used interchangeably with T. vulgaris in the European pharmacopeia
- Wild thyme (Thymus serpyllum) — lower in phenolic monoterpenes overall (15-30%), with higher linalool and geraniol — milder and less directly antimicrobial
The practical implication: when minimum inhibitory concentration tables in the antimicrobial literature compare "thyme essential oil" and "oregano essential oil" side-by-side against a panel of pathogens, the two are usually within a 2-fold range of each other — with oregano slightly more potent against most tested species because carvacrol is slightly more potent than thymol. The two herbs are interchangeable for most antimicrobial purposes, with the choice depending on flavor, tolerability (thyme is milder), and whatever happens to be in the pantry. The respiratory indication (for example, a thyme and ivy combination syrup) is more firmly attached to thyme because of the traditional cough-syrup history; the antimicrobial gut-cleansing folk indication is more firmly attached to oregano (the oil-of-oregano dietary supplement category). For the related Oregano deep dive, see the dedicated page.
Membrane-Disrupting Mechanism and Bacterial Adaptation
Thymol and carvacrol kill bacteria, fungi, and yeasts by disrupting the integrity of the cell membrane — a fundamentally different mechanism from the conventional pharmaceutical antibiotics that target specific enzymes, ribosomes, or cell-wall synthesis machinery. The membrane-disruption mechanism has several practical consequences that distinguish phenolic-monoterpene antimicrobials from conventional antibiotics:
- Broad spectrum. Every bacterial, fungal, and yeast cell has a lipid bilayer membrane. The membrane-active mechanism therefore works against essentially all of them — gram-positive, gram-negative, aerobic, anaerobic, intracellular, biofilm-embedded. Conventional antibiotics with narrower mechanisms have narrower spectra by design.
- Resistance. Bacteria can mutate their ribosomes (against macrolides), their cell-wall enzymes (against beta-lactams), or their efflux pumps (against many drug classes) to acquire resistance to conventional antibiotics. Bacteria can also adapt to a membrane-disrupting agent: laboratory studies show Salmonella changing the fats in its membrane in response to thymol and carvacrol (see the paragraph below the mechanism). To date, methicillin-resistant Staphylococcus aureus, fluconazole-resistant Candida, and other multi-drug-resistant pathogens remain fully susceptible to thymol and carvacrol in vitro.
- Synergy with conventional antibiotics. By compromising membrane integrity, thymol increases the intracellular concentration of co-administered conventional antibiotics — reversing the efflux-pump mechanism that causes much clinical antibiotic resistance. Combinations of thymol + ciprofloxacin, thymol + erythromycin, and thymol + tetracycline have all been shown to be synergistic against resistant clinical isolates in laboratory studies.
- Less selective. The flip side of the broad mechanism is that thymol can also disrupt human cell membranes at high enough concentrations. In vivo, the human gut and respiratory mucosa contain protective mucus, antioxidant enzymes, and rapid turnover that buffer against this; in vitro cytotoxicity studies show thymol cytotoxic to mammalian cells at concentrations roughly 10-50x higher than the bacterial minimum inhibitory concentration, providing a workable therapeutic index for topical and oral mucosal applications, narrower for systemic exposure.
The detailed biophysics: thymol's lipophilic phenol structure allows it to partition into the lipid bilayer of the target membrane. Once embedded, it disrupts the orderly packing of the phospholipid acyl chains, increasing membrane fluidity and permeability. At higher concentrations, it depolarizes the proton-motive force (the trans-membrane proton gradient that bacteria use to generate adenosine triphosphate (ATP)), causes leakage of intracellular potassium and adenosine triphosphate, and ultimately causes cell lysis. Carvacrol works by the same mechanism with slightly higher potency, attributed to its slightly more hydrophobic side-chain geometry.
Bacteria can adapt. In a 2011 laboratory study, Salmonella enterica serovar Typhimurium grown with sublethal (below killing) amounts of thymol, carvacrol, citral or eugenol changed the fatty-acid make-up of its membrane (the membrane fats became more saturated and fewer were converted to cyclopropane fatty acids) and became more resistant to two disinfectants, peracetic acid and didecyl dimethyl ammonium bromide. In a 2024 laboratory study, a carvacrol-resistant Salmonella Typhimurium variant bred by adaptive laboratory evolution carried mutations in four genes (sseG, flhA, wbaV, lon), tolerated heat significantly better in laboratory media and food models, grew better at refrigeration temperatures and kept its virulence in a roundworm model (Caenorhabditis elegans).
Gram-Positive Bacteria (Methicillin-Resistant Staphylococcus Aureus, Streptococcus, Listeria)
Gram-positive bacteria are characterized by a thick peptidoglycan cell wall outside a single cell membrane. The cell wall itself is permeable to small lipophilic molecules like thymol, so thymol gets ready access to the underlying membrane. Published minimum inhibitory concentration values for thyme essential oil against gram-positive clinical pathogens:
- Methicillin-sensitive Staphylococcus aureus (MSSA) — thyme essential oil minimum inhibitory concentration typically 0.05-0.5% v/v (500-5,000 mcg/mL)
- Methicillin-resistant Staphylococcus aureus (MRSA) — thyme essential oil minimum inhibitory concentration essentially identical to MSSA, often 0.05-0.5% v/v. Methicillin resistance does not protect against thymol because the resistance mechanism (altered penicillin-binding protein 2a) is irrelevant to membrane disruption.
- Streptococcus pyogenes (group A strep) — thyme minimum inhibitory concentration 0.1-0.5% v/v
- Streptococcus mutans (cariogenic oral strep) — thyme / thymol minimum inhibitory concentration 0.04-0.2% v/v; the basis for thymol mouthwash plaque-control efficacy
- Enterococcus faecalis (including vancomycin-resistant enterococci (VRE)) — thyme minimum inhibitory concentration 0.1-1% v/v
- Listeria monocytogenes — thyme minimum inhibitory concentration 0.05-0.25% v/v; the basis for thyme oil incorporation into ready-to-eat food packaging
- Bacillus subtilis, Bacillus cereus — thyme minimum inhibitory concentration 0.05-0.5% v/v
The methicillin-resistant Staphylococcus aureus finding is the clinically most striking. Methicillin-resistant Staphylococcus aureus causes a substantial fraction of healthcare-associated infections and is increasingly community-acquired; treatment options are limited and expensive (vancomycin, linezolid, daptomycin). The in-vitro evidence that thymol retains potent activity against methicillin-resistant Staphylococcus aureus has prompted interest in thymol-impregnated wound dressings, thymol-containing topical preparations for staphylococcal skin infections, and thymol nasal swab applications for methicillin-resistant Staphylococcus aureus decolonization. Clinical trials in these applications are still small and mostly proof-of-concept, but the in-vitro data is consistent and the mechanism is robust. For the related Staphylococcus aureus page, see the bacteria deep dive.
Gram-Negative Bacteria (E. coli, Salmonella, Pseudomonas, Klebsiella)
Gram-negative bacteria have an additional outer lipopolysaccharide (LPS) membrane outside the peptidoglycan cell wall, which acts as a permeability barrier that excludes many otherwise-active antimicrobials (one reason many natural antimicrobials are weaker against gram-negative than gram-positive species). Thymol can cross the lipopolysaccharide outer membrane reasonably well because of its small, lipophilic structure, but typical minimum inhibitory concentration values against gram-negative species are 2-4x higher than the corresponding gram-positive minimum inhibitory concentration. Still, the activity is clinically relevant:
- Escherichia coli (including extended-spectrum beta-lactamase (ESBL)-producing and multidrug-resistant clinical isolates) — thyme minimum inhibitory concentration typically 0.1-1% v/v. Activity confirmed against the diarrheagenic enterotoxigenic E. coli (ETEC) and the enterohemorrhagic E. coli O157:H7. For more on Escherichia coli see the bacteria deep dive.
- Salmonella enterica (Typhimurium, Enteritidis) — thyme minimum inhibitory concentration 0.1-0.5% v/v. The basis for thyme essential oil incorporation into poultry-feed and ready-to-eat food packaging applications.
- Pseudomonas aeruginosa — the most resistant of the gram-negative pathogens; thyme minimum inhibitory concentration typically 1-2.5% v/v. Notably, thyme oil disrupts Pseudomonas biofilms, which is clinically important because biofilm formation is the principal mechanism of Pseudomonas persistence in cystic fibrosis lung infection, chronic wound infection, and indwelling-catheter infection. For more on Pseudomonas aeruginosa, see the bacteria deep dive.
- Klebsiella pneumoniae (including carbapenem-resistant Klebsiella pneumoniae) — thyme minimum inhibitory concentration 0.1-1% v/v
- Helicobacter pylori — the gastric pathogen responsible for peptic ulcer disease and a major risk factor for gastric cancer. Thyme essential oil shows activity at minimum inhibitory concentration 0.05-0.25% v/v in vitro; clinical adjunctive use of thyme in H. pylori eradication regimens has been explored in small trials with mixed results.
- Campylobacter jejuni (foodborne diarrhea pathogen) — thyme minimum inhibitory concentration 0.05-0.25% v/v
- Vibrio cholerae — thyme minimum inhibitory concentration 0.05-0.5% v/v
The Pseudomonas biofilm activity is particularly notable because biofilm-embedded bacteria are notoriously refractory to conventional antibiotics — the biofilm matrix excludes drugs and creates anaerobic microenvironments where many antibiotics are ineffective. Phenolic monoterpenes like thymol penetrate the biofilm matrix and disrupt the embedded organisms' membranes. This has prompted research into thymol-containing topical preparations for chronic wound infection, where Pseudomonas biofilm is a major obstacle to healing.
Antifungal Activity (Candida, Dermatophytes, Aspergillus)
Fungal cell membranes have a different sterol composition from bacterial membranes — ergosterol rather than cholesterol, with different acyl-chain composition. The standard antifungal drug class (azoles like fluconazole, ketoconazole) targets ergosterol biosynthesis. Thymol and carvacrol act on the membrane downstream of the biosynthetic pathway, which means they retain activity against azole-resistant fungal isolates and offer a complementary mechanism for combination therapy.
- Candida albicans (the most common human fungal pathogen, oral and vaginal candidiasis) — thyme essential oil minimum inhibitory concentration typically 0.05-0.25% v/v. Activity is preserved against fluconazole-resistant isolates.
- Non-albicans Candida (C. glabrata, C. krusei, C. parapsilosis) — thyme minimum inhibitory concentration similar to C. albicans, an important advantage given the rising prevalence of non-albicans Candida species that are intrinsically less susceptible to fluconazole
- Dermatophytes (Trichophyton rubrum, T. mentagrophytes, Microsporum canis, Epidermophyton floccosum) — the causative organisms of tinea pedis (athlete's foot), tinea cruris (jock itch), tinea corporis (ringworm), and tinea capitis. Thyme oil minimum inhibitory concentration typically 0.05-0.25% v/v. Traditional Mediterranean topical use of thyme for fungal skin infections has good in-vitro backing.
- Aspergillus species (A. niger, A. fumigatus, A. flavus) — thyme minimum inhibitory concentration 0.1-1% v/v. The food-preservation application against Aspergillus mold spoilage of stored grain is the dominant agricultural use.
- Malassezia furfur (causative of tinea versicolor and seborrheic dermatitis) — thyme minimum inhibitory concentration 0.05-0.25% v/v
The Candida activity has clinical traction for oral candidiasis (thrush) management with thyme-containing mouthwashes and rinses, particularly in patients on inhaled corticosteroids for asthma (a common cause of oropharyngeal thrush). It also figures in the natural-medicine literature on intestinal candidiasis and "candida overgrowth" syndromes — though that broader naturopathic application is not as evidence-supported as the localized oral and topical uses.
Oral and Dental Applications (Essential-Oil Mouthwash and Thymol)
The most successful and widespread therapeutic application of thymol is as a principal active in an essential-oil mouthrinse (thymol, eucalyptol, menthol and methyl salicylate). The formula dates to 1879, when it was made as a surgical antiseptic; it combines four phenolic essential-oil constituents: thymol, eucalyptol, methyl salicylate, and menthol, dissolved in 21-26% ethanol. The thymol provides the broadest-spectrum antimicrobial activity in the formula. This essential-oil mouthrinse is the most-studied antiseptic mouthwash in the dental literature, with dozens of randomized trials documenting plaque reduction, gingivitis reduction, and modest periodontitis prevention.
Key clinical findings on thymol-containing mouthwash:
- Plaque reduction. A 2015 pooled analysis of 29 six-month randomized controlled trials (RCTs) found a 27.7% reduction in whole-mouth plaque when the essential-oil mouthrinse was added to toothbrushing and interdental cleaning, compared with toothbrushing and interdental cleaning alone. A 2011 systematic review of 19 studies found chlorhexidine mouthwash controlled plaque significantly better than the essential-oil mouthwash in studies lasting 4 weeks or longer.
- Gingivitis reduction. The same 2015 pooled analysis found a 16.0% reduction in whole-mouth gingivitis at 6 months; a single 6-month trial of 107 adults (1989) found 34% inhibition of both plaque and gingivitis compared with a hydroalcohol control rinse. The 2011 systematic review found no significant difference between the essential-oil mouthwash and chlorhexidine mouthwash for gum inflammation.
- Caries reduction. Less consistent but suggestive evidence for reduced incidence of dental caries with daily thymol mouthwash use, attributed to suppression of Streptococcus mutans.
- Halitosis (bad breath). Thymol's broad antimicrobial activity in the oral cavity reduces the volatile sulfur compounds produced by anaerobic oral bacteria that cause halitosis. Effect duration is typically 4-6 hours per use.
- Post-extraction infection prevention. Used as a pre-procedure rinse in dental surgery to reduce bacterial load in the surgical field.
What the pooled trials counted. The 2015 pooled analysis also counted people rather than averages: at 6 months, 36.9% of rinse users versus 5.5% of people using toothbrushing and interdental cleaning alone had at least half of their tooth sites free of plaque, and 44.8% versus 14.4% had at least half of their gum sites healthy. These trials tested the four-ingredient essential-oil mouthrinse rather than thyme on its own.
A thyme-only mouthwash. One small 2023 study of 60 gingivitis patients, measured one week after initial gum treatment (periodontal treatment), reported lower levels of bad-breath sulfur gases (volatile sulfur compounds) with a thyme mouthwash than with oral-hygiene instructions alone; gum-inflammation scores were lowest in the chlorhexidine group. The paper calls itself both a randomized trial and a retrospective study, and it ran for one week only.
A separate set of applications uses thymol in dental composite materials, root-canal medicaments (the venerable Camphorated Monochlorophenol or CMCP formulation includes a thymol-related compound), and as a temporary cavity sealant ingredient. The dental profession's use of thymol predates the modern antimicrobial literature by decades and is a quietly successful example of natural-product chemistry retained in mainstream medicine.
A traditional home gargle for sore throat or mouth ulcers (aphthous ulcers) is thyme tea (1 teaspoon dried thyme per cup of just-off-the-boil water, steeped 10 minutes, strained, cooled to warm), used 3-4 times daily alongside standard care.
Food Preservation and Antimicrobial Packaging
Thyme essential oil is on the U.S. Food and Drug Administration Generally Recognized As Safe (GRAS) list as a food additive and is one of the most commercially used natural food preservatives. The use cases:
- Meat and poultry preservation. Thyme essential oil at 0.05-0.5% in marinades, surface coatings, or spray applications inhibits the growth of Salmonella, Campylobacter, Listeria, and aerobic spoilage bacteria. The technology is approved for ready-to-eat meat products in the EU and has been adopted in the deli and packaged-meat industries.
- Antimicrobial food packaging. An active area of food-science research is incorporation of thyme essential oil (and oregano, clove, and other phenolic-monoterpene-rich essential oils) into edible coatings (chitosan, gelatin films) or into the inner layer of food packaging films. The packaging slowly releases volatile thymol into the food headspace, extending shelf life of meat, fish, fresh produce, and bakery products by 2-5x.
- Grain and stored-food protection. Thyme essential oil suppresses mold growth on stored grain (Aspergillus, Penicillium, Fusarium) and is used in some organic grain storage applications as a fumigant alternative.
- Beverage preservation. Low concentrations of thyme essential oil have been studied as preservatives for fruit juices and ciders.
- Probiotic-friendly preservation. An attractive feature of phenolic-monoterpene preservatives is that at sub-lethal concentrations they inhibit pathogenic and spoilage organisms while sparing the beneficial lactic-acid bacteria used in fermented foods — the mechanism is partly differential membrane sensitivity, partly the natural co-evolution of fermentation organisms with herbs.
The food-preservation literature is mostly a parallel scientific track from the medicinal literature, but the cross-referenced minimum inhibitory concentration data and mechanistic studies inform each other. Many of the clearest published minimum inhibitory concentration values for thyme essential oil against gram-negative foodborne pathogens come from food-science journals.
Topical Skin and Nail Applications
Topical applications of dilute thyme essential oil are a folk-traditional and increasingly evidence-supported approach to several skin conditions; the preparations below are those practitioners and aromatherapy texts describe:
- Bacterial skin infection (impetigo, folliculitis, infected eczema). Practitioners describe 1-3% thyme essential oil in a carrier oil (sweet almond, jojoba, coconut), applied 2-3 times daily, citing mechanistic and small-trial support. They describe it as an add-on for mild surface infection in people seeking to limit antibiotic exposure, not as a replacement for prescription antibiotics in cellulitis or severe infection.
- Fungal skin infection (athlete's foot, ringworm, jock itch). Practitioners describe 2-5% thyme essential oil in carrier oil, applied twice daily; laboratory (in-vitro) tests show good activity against the relevant dermatophytes. Tea tree oil is the more famous topical antifungal essential oil; practitioners describe thyme as a second option with broader bacterial activity when a lesion is mixed.
- Onychomycosis (nail fungus). Practitioners describe 5-10% thyme essential oil in carrier oil, applied to the affected nail twice daily. Nail fungus is notoriously slow to treat (6-12 months for full nail growout) and topical penetration is poor through nail keratin; practitioners describe thyme oil for mild surface cases or as an add-on, not as a substitute for prescription oral terbinafine when full nail clearance is the goal.
- Wound infection prevention. Practitioners describe 0.5-1% thyme essential oil in carrier oil or hydrogel base, applied to minor cuts and abrasions after standard cleansing. The described use is limited to minor wounds; deep, contaminated and animal-bite wounds fall outside it.
- Acne. The most-cited modern dermatologic application; covered in detail in the companion Antioxidant and Acne deep-dive.
- Lice and scabies. Some folk-medicine and small-trial support for thyme essential oil as part of an essential-oil treatment for head lice; activity is real but the more concentrated tea tree oil and the prescription permethrin are more effective.
For all topical essential-oil applications, the hazard is the same: undiluted essential oil on skin causes irritation and chemical burn because of its high phenolic concentration. Aromatherapy texts describe diluting to no more than 5% in a carrier oil for routine use, lower for facial application, and a patch test on the inner forearm before broader use.
Chemotype Variability (Thymol vs. Carvacrol vs. Linalool)
One of the most important and underappreciated aspects of thyme essential oil used medicinally is the chemotype variability. The same Latin binomial — Thymus vulgaris — covers at least six genetically distinct essential-oil chemotypes that produce dramatically different essential oils with different therapeutic indications. The standard chemotypes:
- Thymol chemotype — the canonical "thyme essential oil" of the European pharmacopeia. 40-60% thymol, the strongest antimicrobial chemotype, the standard for respiratory and antimicrobial use. This is what the medicinal literature generally describes.
- Carvacrol chemotype — less common in commercial thyme oil but available. 50-80% carvacrol, slightly more potent antimicrobially than thymol chemotype but functionally similar; closer to oregano essential oil in composition.
- Linalool chemotype — the gentlest chemotype, dominant in linalool (70-80%), with floral aroma similar to lavender. Mild antimicrobial activity but well-tolerated on sensitive skin; the chemotype aromatherapy texts describe for children's topical use and for facial applications.
- Geraniol chemotype — sweet, rose-like aroma. Modest antimicrobial activity. Mostly perfumery use.
- Alpha-terpineol chemotype — lilac-like aroma. Mostly perfumery.
- Trans-sabinene hydrate chemotype — rare, mild aromatic profile.
The chemotype is determined by the plant's genetics (set at seed) and is not changeable by growing conditions. The same field can contain individual plants of multiple chemotypes; commercial producers usually clone-propagate from a single mother plant to ensure chemotype consistency. A supplier's certificate of analysis (COA) typically specifies the chemotype (often written as "Thymus vulgaris ct. thymol" or "ct. linalool") and gives a gas chromatography (GC) report showing the actual percentage of major constituents. An oil sold without a published COA cannot be checked — unspecified "thyme oil" may be any of the six chemotypes, possibly adulterated with synthetic thymol, and may not deliver the medicinal effect described in this article.
Aromatherapy texts match chemotype to use: the thymol chemotype (40% or more thymol on the GC report) for antimicrobial use; the linalool chemotype for children and sensitive skin; and the thymol chemotype, 5-6 drops in a large bowl of hot water, for steam inhalation in healthy adults.
Cautions for Internal Antimicrobial Use
- Short courses. Internal antimicrobial use of thyme essential oil as practitioners describe it (1-2 drops on a sugar cube or in honey, 2-3 times daily) is a high-dose phenolic monoterpene exposure, and those practitioners limit it to 7-10 days at a time. Longer courses can produce gastric irritation, oral mucosal burning, and disruption of the normal commensal gut microbiome.
- Children. Internal essential oil dosing is contraindicated in children under 12 due to risk of mucosal burning and potential for seizure at accidental high doses. Thyme tea, syrup, and steam inhalation are the forms traditionally used for children.
- Pregnancy. Internal essential oil dosing is described as contraindicated in pregnancy; the caution is not applied to thyme tea at culinary-medicinal doses.
- Inflammatory bowel disease. Internal essential oil dosing raises a concern in active inflammatory bowel disease (IBD) — the membrane-active mechanism can exacerbate mucosal inflammation in already-inflamed gut. The concern is described for the concentrated oil, not for thyme tea.
- Anticoagulant interaction. Thymol has weak antiplatelet activity, which raises a bleeding concern for high-dose internal essential oil use by people on warfarin, clopidogrel, or high-dose aspirin.
- Allergic contact dermatitis. 1-2% of patch-tested individuals show sensitization to thymol or thyme essential oil. Aromatherapy texts describe a patch test before any extended topical use.
- Photosensitivity. Not a significant issue for thyme (unlike some other essential oils such as bergamot), but high-concentration topical use plus intense sun exposure could theoretically produce localized photoirritation.
- Drug-microbiome interactions. Like any antimicrobial, internal thyme essential oil at therapeutic doses will alter the gut commensal microbiome. Some practitioners pair the course with a probiotic, taken during it and for 2 weeks after.
Key Research Papers
- Burt S (2004). Essential oils: their antibacterial properties and potential applications in foods — a review. International Journal of Food Microbiology. — PubMed PMID: 15246235
- Nazzaro F et al. (2013). Effect of essential oils on pathogenic bacteria. Pharmaceuticals. — PubMed
- Sienkiewicz M et al. (2011). Antibacterial activity of thyme and lavender essential oils. Medicinal Chemistry. — PubMed PMID: 22313307
- Lambert RJ et al. (2001). A study of the minimum inhibitory concentration and mode of action of oregano essential oil, thymol and carvacrol. Journal of Applied Microbiology. — PubMed PMID: 11556910
- Memar MY et al. (2017). Carvacrol and thymol: strong antimicrobial agents against resistant isolates. Reviews in Medical Microbiology. — doi:10.1097/MRM.0000000000000100
- Ultee A et al. (2002). The phenolic hydroxyl group of carvacrol is essential for action against the food-borne pathogen Bacillus cereus. Applied and Environmental Microbiology. — PubMed PMID: 11916669
- DePaola LG et al. (1989). Chemotherapeutic inhibition of supragingival dental plaque and gingivitis development. Journal of Clinical Periodontology. — PubMed PMID: 2723103
- Stoeken JE et al. (2007). The long-term effect of a mouthrinse containing essential oils on dental plaque and gingivitis: a systematic review. Journal of Periodontology. — PubMed PMID: 17608576
- Pina-Vaz C et al. (2004). Antifungal activity of Thymus oils and their major compounds. Journal of the European Academy of Dermatology and Venereology. — PubMed
- Soliman KM, Badeaa RI (2002). Effect of oil extracted from some medicinal plants on different mycotoxigenic fungi. Food and Chemical Toxicology. — PubMed PMID: 12176092
- Lopez-Romero JC et al. (2015). Antibacterial effects and mode of action of selected essential oils components against Escherichia coli and Staphylococcus aureus. Evidence-Based Complementary and Alternative Medicine. — PubMed
- Trombetta D et al. (2005). Mechanisms of antibacterial action of three monoterpenes. Antimicrobial Agents and Chemotherapy. — PubMed
- Araujo MWB et al. (2015). Meta-analysis of the effect of an essential oil-containing mouthrinse on gingivitis and plaque. Journal of the American Dental Association. — PubMed PMID: 26227646
- Van Leeuwen MP et al. (2011). Essential oils compared to chlorhexidine with respect to plaque and parameters of gingival inflammation: a systematic review. Journal of Periodontology. — PubMed PMID: 21043801
- Altındal D et al. (2023). Effects of thyme on halitosis in gingivitis patients: Can thyme mouthwash prevent halitosis-A randomized trial. International Journal of Dental Hygiene. — PubMed PMID: 36760146
- Dubois-Brissonnet F et al. (2011). Induction of fatty acid composition modifications and tolerance to biocides in Salmonella enterica serovar Typhimurium by plant-derived terpenes. Applied and Environmental Microbiology. — PubMed PMID: 21131520
- Pagán E et al. (2024). Growth fitness, virulence, and heat tolerance of Salmonella Typhimurium variants resistant to food preservation methods. International Journal of Food Microbiology. — PubMed PMID: 38945050
PubMed Topic Searches
Connections
- All Herbs
- Thyme Overview
- Thyme Benefits Hub
- Thyme for Respiratory Health
- Thyme Digestive Aid
- Thyme Antioxidant & Acne
- Oregano (Carvacrol Cousin)
- Garlic
- Tea Tree
- Clove
- Cinnamon
- Staphylococcus Aureus / Methicillin-Resistant Staphylococcus Aureus
- Escherichia Coli
- Pseudomonas Aeruginosa
- Immune Boosting
- Honey
- History