Olive Leaf for Blood Sugar and Insulin Sensitivity
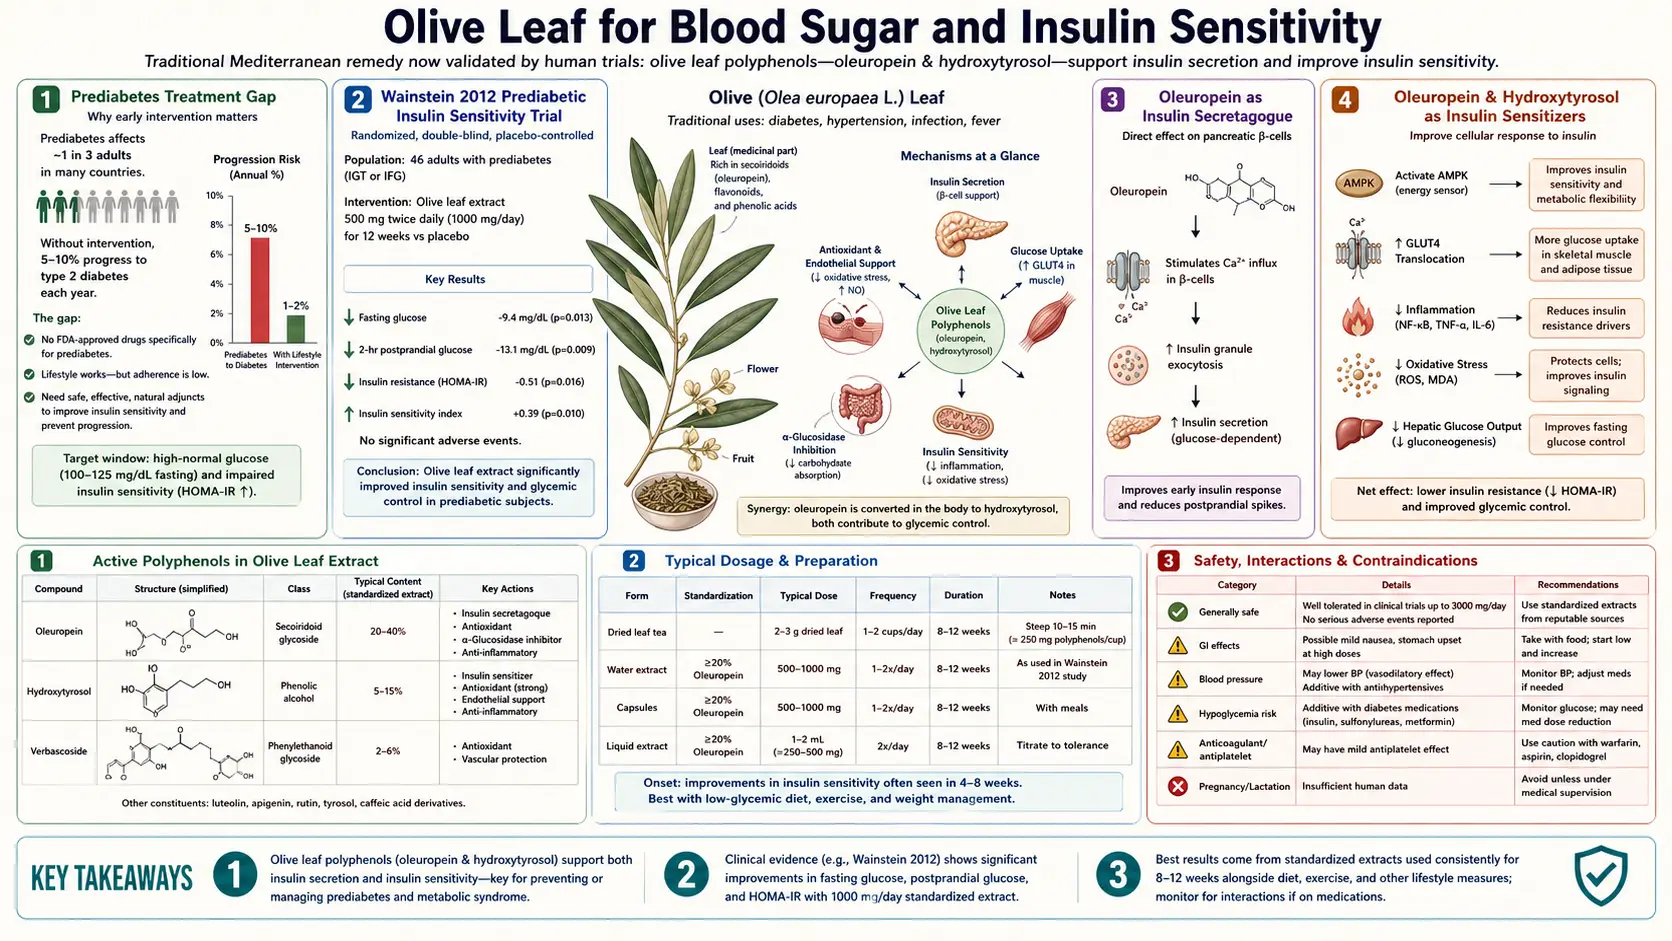
The Wainstein 2012 trial published in Journal of Medicinal Food randomized 79 adults with type 2 diabetes to olive leaf extract (OLE 500 mg once daily) or matching placebo for 14 weeks, measuring hemoglobin A1c (HbA1c) and plasma insulin. The OLE group had significantly lower HbA1c and fasting insulin, while insulin after meals did not differ between the groups. A separate 12-week crossover trial in 46 overweight middle-aged men (de Bock 2013) found 15% better insulin sensitivity and 28% better pancreatic beta-cell responsiveness than placebo. Two 2026 meta-analyses of all the trials, however, found no significant effect on blood-sugar markers overall (see below). Mechanistically, cell and animal studies show oleuropein acting as both an insulin secretagogue (potentiating glucose-stimulated insulin release from pancreatic beta cells, a mechanism similar to but milder than sulfonylureas) and as an insulin sensitizer in peripheral tissues (skeletal muscle, adipose, liver). The dual mechanism is uncommon among herbal therapeutics and is the basis for interest in OLE in prediabetes and as an adjunct to lifestyle intervention in early type 2 diabetes. This deep-dive walks through the Wainstein trial, the insulin secretagogue and sensitization mechanisms, the glucagon-like peptide-1 (GLP-1) and gut microbiome contributions, the combination with metformin and lifestyle, and the doses used in trials and described for adults with prediabetes or metabolic syndrome.
Table of Contents
- The Prediabetes Treatment Gap
- Wainstein 2012 — The Type 2 Diabetes Trial
- Oleuropein as Insulin Secretagogue
- Oleuropein and Hydroxytyrosol as Insulin Sensitizers
- Glucagon-Like Peptide-1 and the Gut Microbiome Contribution
- Postprandial Glucose Modulation
- Hemoglobin A1c, Fasting Glucose, and Long-Term Markers
- Stacking with Metformin and Lifestyle Intervention
- Doses Used and Monitoring Described
- Cautions (Hypoglycemia, Drug Interactions)
- Key Research Papers
- Connections
- Featured Videos
The Prediabetes Treatment Gap
Prediabetes — hemoglobin A1c 5.7-6.4% or fasting glucose 100-125 mg/dL or impaired glucose tolerance on an oral glucose tolerance test (OGTT) — affects 115.2 million U.S. adults aged 18 and older, according to the CDC's National Diabetes Statistics page (updated September 16, 2026), and a much larger fraction of overweight middle-aged adults globally. In the Diabetes Prevention Program trial (3,234 people, average follow-up 2.8 years), new diabetes occurred at 11.0 cases per 100 person-years on placebo, 7.8 on metformin and 4.8 with lifestyle change; the lifestyle program (goals of at least 7% weight loss and at least 150 minutes of physical activity a week) reduced the incidence by 58%, and metformin by 31%.
The clinical gap is large. Lifestyle intervention works but is hard to sustain at the population level. Metformin is well-tolerated and effective but underprescribed in prediabetes outside of high-risk populations. Many patients sit in a "watching and waiting" zone where they know they have prediabetes but receive no specific pharmacotherapy and inconsistent lifestyle counseling. This is the group in which herbal options like OLE are most often discussed: OLE needs no prescription, and its proposed mechanisms complement dietary and lifestyle approaches.
OLE has not been tested as a replacement for lifestyle change or metformin. The human evidence on blood sugar consists of the Wainstein 2012 trial in type 2 diabetes, the de Bock 2013 trial in overweight men, and the meta-analyses summarized below.
Wainstein 2012 — The Type 2 Diabetes Trial
Wainstein J, Ganz T, Boaz M et al. (2012), published in Journal of Medicinal Food, combined a human trial with animal tests. Design: a 14-week controlled clinical trial in which 79 adults with type 2 diabetes were randomized to:
- OLE arm — a 500 mg olive leaf extract tablet taken by mouth once daily
- Placebo arm — a matching placebo
Measures of blood-sugar control, including hemoglobin A1c (HbA1c) and plasma insulin, were compared between the groups.
Results at 14 weeks:
- Hemoglobin A1c: significantly lower in the OLE group
- Fasting plasma insulin: significantly lower in the OLE group
- Insulin after meals (postprandial): no significant difference between the groups
- Animal tests: in intestine from normal and streptozotocin-diabetic rats, olive leaf extract significantly reduced starch digestion and absorption; in sand rats the reduction did not reach statistical significance
The authors concluded that olive leaf extract is associated with improved blood-sugar control (glucose homeostasis) in humans, that the animal tests suggest this may work partly through reduced starch digestion and absorption, and that it may represent an effective adjunct therapy in diabetes.
A separate trial, often mixed up with this one, measured insulin sensitivity directly. In a double-blind, placebo-controlled crossover trial in New Zealand (de Bock 2013), 46 overweight middle-aged men took olive leaf extract capsules (51.1 mg oleuropein and 9.7 mg hydroxytyrosol a day) or placebo for 12 weeks each. Insulin sensitivity (Matsuda method) improved by 15% and pancreatic beta-cell responsiveness by 28% compared with placebo. There was no effect on blood fats (lipid profile), 24-hour blood pressure, body composition, carotid artery wall thickness or liver function.
Oleuropein as Insulin Secretagogue
Pancreatic beta cells release insulin in response to glucose via a well-characterized mechanism: glucose enters the beta cell via GLUT2, is phosphorylated by glucokinase, enters glycolysis and the TCA cycle, raises intracellular ATP/ADP ratio, closes the adenosine triphosphate-sensitive potassium channel (KATP), depolarizes the beta cell membrane, opens voltage-gated calcium channels, and the calcium influx triggers insulin granule exocytosis.
Sulfonylureas (glipizide, glyburide, glimepiride) are insulin secretagogues that work by directly closing the KATP channel via the sulfonylurea receptor (SUR1) subunit, bypassing the need for glucose-driven adenosine triphosphate (ATP). This produces strong glucose-lowering but also hypoglycemia risk because the secretagogue effect is not glucose-dependent.
Oleuropein and its hydrolysis products show insulin-secretagogue activity in isolated pancreatic islet preparations and in beta-cell line studies (INS-1, MIN6). The mechanism appears more nuanced than sulfonylureas:
- Oleuropein enhances glucose-stimulated insulin release without producing major insulin release at baseline (i.e., the effect is largely glucose-dependent, not the sulfonylurea-style indiscriminate release). This is why OLE has not produced symptomatic hypoglycemia in trials — the secretagogue effect amplifies the appropriate physiologic response rather than overriding it.
- Oleuropein supports beta-cell mitochondrial function and reduces glucotoxicity-induced beta-cell apoptosis, preserving long-term beta-cell mass
- Oleuropein may modestly inhibit dipeptidyl peptidase-4 (DPP-4), the enzyme that degrades glucagon-like peptide-1, indirectly raising glucagon-like peptide-1 levels and supporting glucose-dependent insulin secretion
The clinical implication is that OLE's effect on insulin secretion is gentler and safer than pharmaceutical sulfonylureas, but mechanistically similar in direction. For prediabetes and early type 2 diabetes where some beta-cell function is preserved, this is a useful effect.
Oleuropein and Hydroxytyrosol as Insulin Sensitizers
Beyond the secretagogue effect at the beta cell, OLE improves insulin signaling in peripheral target tissues: skeletal muscle, adipose tissue, and liver. The mechanisms include:
- Insulin receptor substrate (IRS) phosphorylation — hydroxytyrosol enhances tyrosine phosphorylation of IRS-1 and IRS-2 in response to insulin binding, preserving the downstream PI3K/Akt signaling that translocates GLUT4 glucose transporters to the cell membrane
- Reduced serine phosphorylation of IRS — inflammatory signaling (JNK, IKK-beta) drives inhibitory serine phosphorylation of IRS proteins, blocking the insulin signal. Hydroxytyrosol's anti-inflammatory effects reduce this inhibitory signal.
- AMP-activated protein kinase (AMPK) activation — oleuropein and hydroxytyrosol both activate AMP-activated protein kinase (AMPK), the cellular energy sensor, in skeletal muscle and hepatocytes. AMP-activated protein kinase activation increases GLUT4 translocation independently of insulin, increases fatty acid oxidation, and inhibits hepatic gluconeogenesis. This is essentially the same mechanism as metformin.
- Improved mitochondrial function and reduced lipotoxicity — the mitochondrial protection discussed in the Antioxidant deep-dive reduces intramyocellular lipid accumulation, which is a key driver of muscle insulin resistance
- Reduced hepatic lipogenesis — oleuropein modulates SREBP-1c, reducing de novo lipogenesis and hepatic triglyceride accumulation. Reduced hepatic fat is associated with restored hepatic insulin sensitivity.
The combination of beta-cell support plus peripheral sensitization is mechanistically attractive for prediabetes specifically, because both pathologies (relative beta-cell insufficiency and peripheral insulin resistance) are present in the prediabetic state and worsen as the patient progresses to overt diabetes.
Glucagon-Like Peptide-1 and the Gut Microbiome Contribution
A more recent line of research suggests that OLE's metabolic benefits are partly mediated through the gut. Two mechanisms:
- glucagon-like peptide-1 elevation — glucagon-like peptide-1 is an incretin hormone secreted by intestinal L cells in response to nutrient intake. It potentiates glucose-stimulated insulin secretion, suppresses glucagon, slows gastric emptying, and increases satiety. The glucagon-like peptide-1 axis is the target of glucagon-like peptide-1 receptor agonists like semaglutide and liraglutide, currently the most clinically transformative new drug class for type 2 diabetes and obesity. Olive polyphenols including oleuropein appear to stimulate L-cell glucagon-like peptide-1 secretion modestly, and to inhibit glucagon-like peptide-1 breakdown by dipeptidyl peptidase-4 (the same enzyme inhibited by sitagliptin and the other "gliptin" class drugs).
- Gut microbiome modulation — OLE produces favorable shifts in gut microbiome composition in both animal and limited human studies, including increases in Akkermansia muciniphila (a bacterium associated with metabolic health), Lactobacillus species, and short-chain-fatty-acid-producing Firmicutes. The metabolic implications of these microbiome changes include improved gut barrier integrity (less metabolic endotoxemia), increased butyrate production (with downstream effects on hepatic insulin sensitivity), and indirect modulation of glucagon-like peptide-1 secretion via bile acid signaling through TGR5 and FXR receptors.
The glucagon-like peptide-1 and microbiome mechanisms are mechanistically interesting and partially explain why OLE's effects extend beyond a simple "polyphenol antioxidant" framework. The magnitude of the glucagon-like peptide-1 elevation from OLE is much smaller than from pharmaceutical glucagon-like peptide-1 agonists, and OLE is not expected to produce semaglutide-like weight loss, but the directional alignment with one of the most clinically successful diabetes drug classes is encouraging.
Postprandial Glucose Modulation
OLE taken before a meal is reported to modestly reduce the rise in blood sugar after the meal (the postprandial glucose excursion), as seen on a continuous glucose monitor (CGM). The proposed mechanism combines three effects:
- Mild inhibition of intestinal alpha-amylase and alpha-glucosidase activity, slowing carbohydrate digestion (a milder version of the acarbose mechanism; reduced starch digestion and absorption was seen in rat intestine tests in Wainstein 2012)
- Enhanced first-phase insulin response to the meal
- Slowed gastric emptying via the glucagon-like peptide-1 mechanism
People who use a CGM describe taking OLE 500 mg about 30 minutes before a carbohydrate-containing meal and seeing a lower peak and a flatter curve. The effect is described as milder than that of pharmaceutical alpha-glucosidase inhibitors and is combined with other meal strategies (vinegar before meals, exercise after meals, fiber-first meal sequencing). See our CGM page for the broader CGM-based optimization framework.
Hemoglobin A1c, Fasting Glucose, and Long-Term Markers
What the trials found on the longer-term markers:
- Hemoglobin A1c — in the Wainstein 2012 trial in type 2 diabetes, HbA1c was significantly lower after 14 weeks of OLE 500 mg once daily than on placebo. For comparison, metformin produces approximately 1.0-1.5% hemoglobin A1c reduction.
- Fasting glucose — a 2024 meta-analysis (Álvares, 12 randomized trials, 703 people, follow-up 2 days to 12 weeks) found that in trials using a low dose of OLE, fasting blood sugar showed a significant result favoring the control group
- Insulin sensitivity — 15% better (Matsuda method) after 12 weeks in the de Bock 2013 trial in overweight men
- Fasting insulin — significantly lower in the Wainstein 2012 trial
Three meta-analyses now cover olive leaf and blood sugar. The largest (Mansouri 2026: 30 randomized trials, 1,726 people) found no significant effect on blood-sugar markers, while blood pressure and blood fats did improve. Another (Câmara Rocha Menezes 2026: 11 randomized trials) found that short-term crossover studies gave mixed results on blood sugar after meals, and that in longer, continuous-intake parallel trials there was no statistically or clinically significant effect on blood sugar or blood fats.
OLE has not been tested as a substitute for guideline-recommended medicines in type 2 diabetes (hemoglobin A1c >6.5%). In prediabetes and metabolic syndrome, where medicines are often deferred or not used, OLE is discussed as an add-on to lifestyle change.
Stacking with Metformin and Lifestyle Intervention
OLE's mechanism overlaps with metformin in some respects (both activate AMP-activated protein kinase; both improve insulin sensitivity) and complements it in others (OLE has a beta-cell secretagogue effect that metformin lacks; OLE provides additional cardiovascular and antioxidant benefits). For people already on metformin:
- No adverse drug interaction between OLE and metformin has been documented
- The glucose-lowering effects can add together, mainly in the first 2-4 weeks; a need to change the metformin dose is described as rare but possible
- The combination may produce additional cardiovascular benefit (blood pressure (BP) reduction, lipid improvement) that metformin alone does not provide
In lifestyle programs like the Diabetes Prevention Program, OLE is discussed as an add-on that may improve insulin sensitivity beyond what diet and exercise achieve alone. The Mediterranean dietary pattern itself, which delivers olive polyphenols through food, lowered the rate of new diabetes in the PREDIMED trial: in a 2014 subgroup analysis of 3,541 people aged 55 to 80 at high cardiovascular risk (median follow-up 4.1 years), a Mediterranean diet with extra-virgin olive oil and no calorie restriction had 16.0 new diabetes cases per 1,000 person-years against 23.6 on the control diet (hazard ratio 0.60); the Mediterranean diet with mixed nuts (18.7 per 1,000 person-years, hazard ratio 0.82) did not reach statistical significance. OLE supplementation may add to that effect for people who do not eat much olive oil.
The combined approach usually described includes:
- Weight loss of 5-10% of body weight through eating fewer calories and physical activity
- Mediterranean dietary pattern with liberal extra-virgin olive oil
- Regular aerobic exercise (150 min/week moderate or 75 min/week vigorous)
- Resistance training 2-3× per week (preserves muscle mass and insulin sensitivity)
- OLE at the doses used in trials (500 mg once daily in the Wainstein 2012 diabetes trial; 500 mg twice daily in the Susalit 2011 blood-pressure trial)
- Metformin for people with body mass index (BMI) >35 or other high-risk features when lifestyle alone is not enough
- Continuous glucose monitor (if available) to provide direct feedback on glucose response to meals and lifestyle
Doses Used and Monitoring Described
- Doses in trials and in common use: the Wainstein 2012 diabetes trial used 500 mg once daily; the dose commonly described for prediabetes and metabolic syndrome is 500 mg twice daily of OLE standardized to 18-20% oleuropein
- Pre-meal dosing for postprandial glucose: described as 500 mg 30 minutes before the largest carbohydrate meal of the day, sometimes in addition to twice-daily dosing
- Monitoring schedule described: fasting glucose, insulin, hemoglobin A1c, and lipid panel before starting, repeated at 3 months and, if improving, at 6 and 12 months. Practitioners describe that if there is no measurable improvement at 6 months alongside good lifestyle habits, OLE is unlikely to add value.
- CGM integration: for people using a CGM, any after-meal effect of OLE is directly visible, and the readings show how meal timing and dosing change the glucose curve.
- Time to effect: insulin sensitivity changes are measurable at 8-12 weeks; hemoglobin A1c changes lag and are not interpretable until 3 months minimum.
Cautions (Hypoglycemia, Drug Interactions)
- Hypoglycemia risk with insulin or sulfonylureas — in people on insulin (any type) or sulfonylureas (glipizide, glyburide, glimepiride), OLE's combined insulin-sensitizing and secretagogue effects can add to the drug's effect and cause symptomatic hypoglycemia (low blood sugar), so the insulin or sulfonylurea dose may need lowering.
- Dipeptidyl peptidase-4 inhibitors (sitagliptin, linagliptin) — theoretical additive effect on glucagon-like peptide-1, though documented interactions have not been reported.
- Glucagon-like peptide-1 receptor agonists (semaglutide, liraglutide, tirzepatide) — OLE's additional effects are minor relative to these drugs; no significant interaction expected.
- Metformin — well-tolerated combination; no documented interaction. Both activate AMP-activated protein kinase; the combined effect on glucose is typically additive but rarely causes hypoglycemia because both have weak intrinsic hypoglycemic effects.
- Surgery and fasting — practitioners describe stopping OLE 1-2 weeks before elective surgery or before extended fasting (more than 24 hours) to lower the risk of low blood sugar.
- Pregnancy and lactation — not studied in gestational diabetes management, and its safety in pregnancy has not been established.
- Cardiovascular drug interactions — see the Cardiovascular deep-dive for OLE's effects on blood pressure and the additive risk with antihypertensives.
Key Research Papers
- Wainstein J et al. (2012). Olive leaf extract as a hypoglycemic agent in both human diabetic subjects and in rats. Journal of Medicinal Food 15(7):605-610. — PubMed PMID: 22512698
- de Bock M et al. (2013). Olive (Olea europaea L.) leaf polyphenols improve insulin sensitivity in middle-aged overweight men: a randomized, placebo-controlled, crossover trial. PLOS ONE. — PubMed PMID: 23516412
- Al-Azzawie HF, Alhamdani MS (2006). Hypoglycemic and antioxidant effect of oleuropein in alloxan-diabetic rabbits. Life Sciences. — PubMed PMID: 16236331
- Jemai H, Fki I, Bouaziz M, Bouallagui Z, El Feki A, Isoda H, Sayadi S (2008). Lipid-lowering and antioxidant effects of hydroxytyrosol and its triacetylated derivative recovered from olive tree leaves in cholesterol-fed rats. Journal of Agricultural and Food Chemistry 56(8):2630-2636. — PubMed PMID: 18380465
- Sangi SM, Sulaiman MI, El-Wahab MF, Ahmedani EI, Ali SS (2015). Antihyperglycemic effect of thymoquinone and oleuropein, on streptozotocin-induced diabetes mellitus in experimental animals. Pharmacognosy Magazine 11(Suppl 2):S251-S257. — PubMed PMID: 26664013
- Hassen I, Casabianca H, Hosni K (2015). Biological activities of the natural antioxidant oleuropein: exceeding the expectation – a mini-review. Journal of Functional Foods 18:926-940. — doi:10.1016/j.jff.2014.09.001
- Salas-Salvadó J et al. (2014). Prevention of diabetes with Mediterranean diets: a subgroup analysis of a randomized trial (PREDIMED). Annals of Internal Medicine 160(1):1-10. — PubMed PMID: 24573661
- Knowler WC, Barrett-Connor E, Fowler SE, Hamman RF, Lachin JM, Walker EA, Nathan DM; Diabetes Prevention Program Research Group (2002). Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. New England Journal of Medicine 346(6):393-403. — PubMed PMID: 11832527
- Álvares AA, Garcêz A, Silva LT, Averbuch N, Garavaglia J (2024). Olive leaf extract effect on cardiometabolic risk factors: a systematic review and meta-analysis of randomized clinical trials. Nutrition Reviews 82(12):1710-1725. — PubMed PMID: 38287654
- Mansouri F, Mardani M, Rucci C, Bordoni L, Gabbianelli R (2026). A GRADE-assessed systematic review and meta-analysis of randomized controlled trials evaluating the effects of olive leaf or olive pomace supplementation on cardiometabolic and anthropometric health markers. Nutrition, Metabolism and Cardiovascular Diseases 36(10):104821. — PubMed PMID: 42303499
- Câmara Rocha Menezes R, Peres KK, da Mata IR, Morelo Dal Bosco S, Garavaglia J, Dallegrave E (2026). Metabolic and inflammatory effects of oleuropein and olive leaf extract: a systematic review and meta-analysis. Food & Function 17(7):3077-3090. — PubMed PMID: 41848522
PubMed Topic Searches
Connections
- All Herbs
- Olive Leaf Benefits Hub
- Olive Leaf Overview
- OLE Cardiovascular
- OLE Antimicrobial
- OLE Antioxidant
- Type 2 Diabetes
- Coffee for Type 2 Diabetes
- Continuous Glucose Monitor
- Olive Oil
- Cinnamon
- Berberine
- Magnesium
- Chromium
- Endocrinology
- Metformin — the first-line pharmaceutical this extract is compared against and stacked with.
- History