⚠ Evidence warning: Clinical trials or other evidence do not support the claim that olive leaf extract taken by mouth prevents recurrent urinary tract infections and herpes flare-ups, treats influenza and candidiasis, and improves Helicobacter pylori eradication. This page keeps it as a report of what people, websites or other media say.
Olive Leaf for Antimicrobial and Antiviral Use
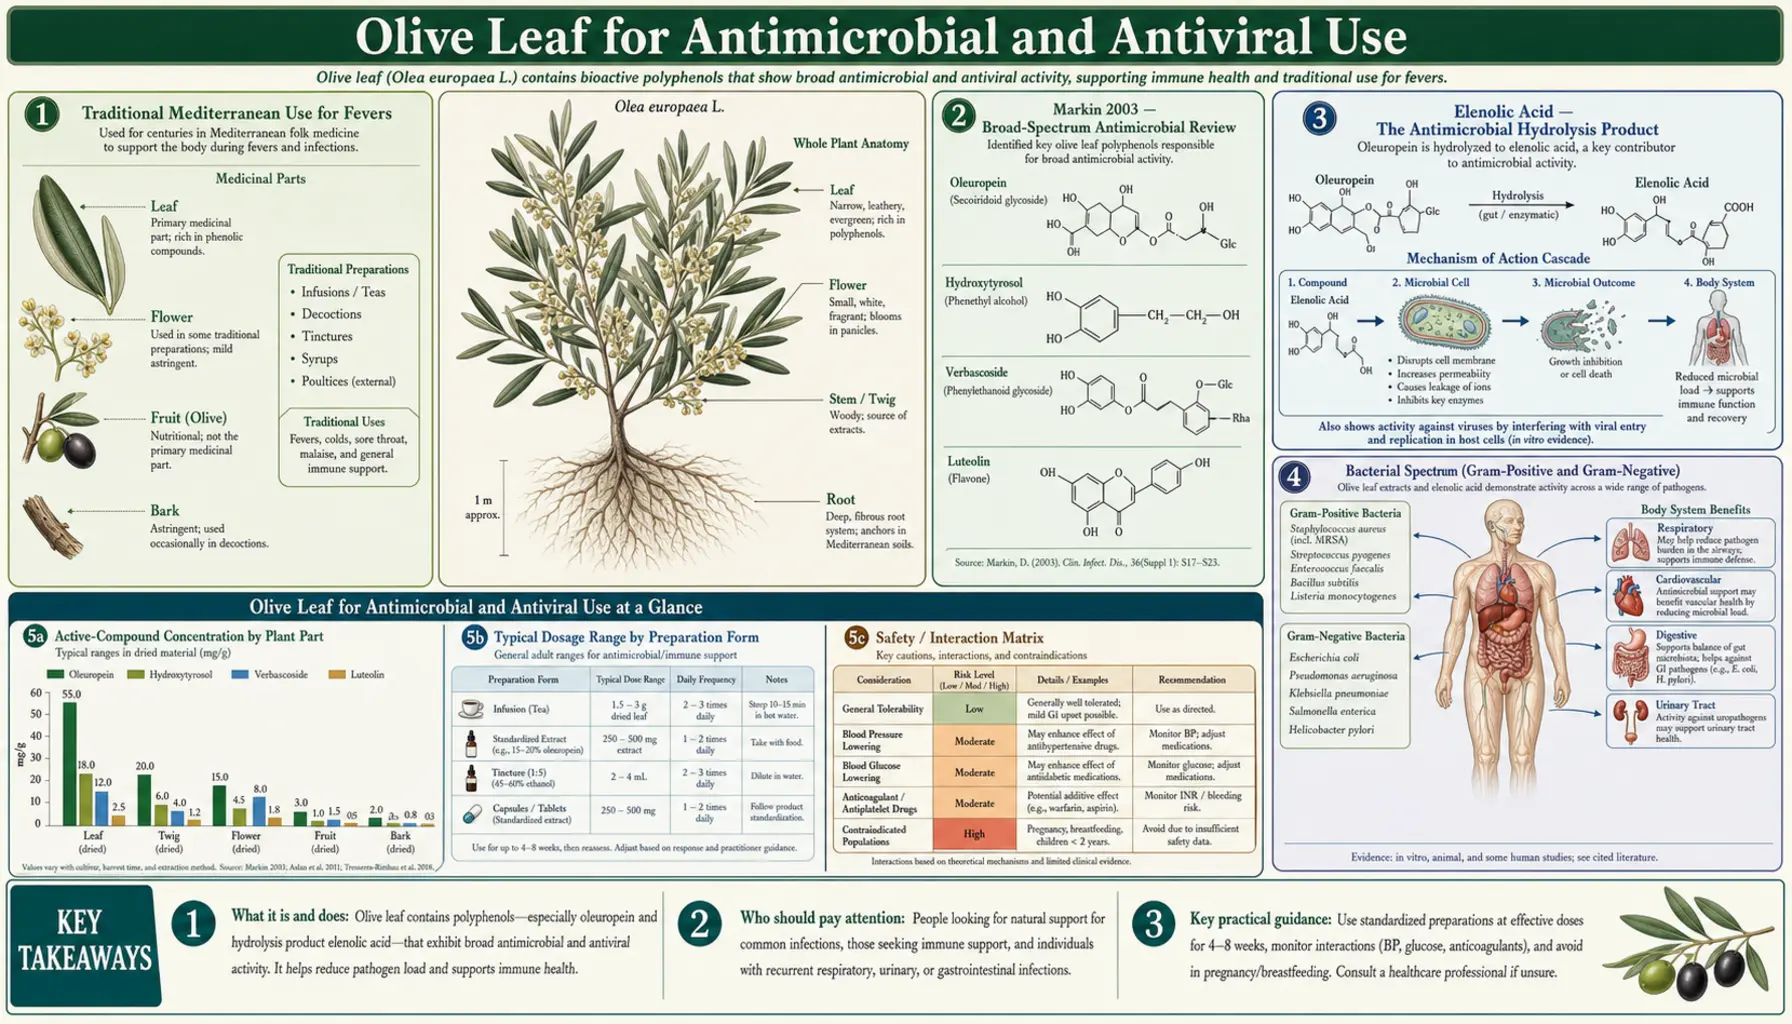
The Mediterranean traditional use of olive leaf for "fevers" predates the germ theory of disease by millennia — physicians from Galen to Avicenna to traditional Calabrian and Greek practitioners routinely prescribed olive leaf decoctions for malarial fevers, wound infections, and what we would today call upper respiratory and urinary tract infections. The modern mechanistic understanding centers on the phenolic constituent oleuropein and its breakdown (hydrolysis) products hydroxytyrosol and elenolic acid, which show antibacterial, antiviral and antifungal activity in vitro (in laboratory tests). That activity is narrower than often described: a 2009 test of a commercial olive leaf extract against 122 microorganisms concluded it "was not broad-spectrum in action", with appreciable activity only against Helicobacter pylori, Campylobacter jejuni and Staphylococcus aureus, including methicillin-resistant S. aureus (MRSA). The 2003 Markin paper in Mycoses is a laboratory study of an olive leaf water extract against bacteria and fungi; the antiviral findings come from other laboratory papers on calcium elenolate (Renis 1969 and 1975, Heinze 1975) and on human immunodeficiency virus (HIV) (Lee-Huang 2003 and 2007). This deep-dive walks through the historical context, the specific in vitro data, the elenolic acid mechanism, and the practical scope and limitations of olive leaf extract (OLE) as an adjunct in mild respiratory and viral illness.
Table of Contents
- Traditional Mediterranean Use for Fevers
- Markin 2003 — Laboratory Study Against Bacteria and Fungi
- Elenolic Acid — The Antimicrobial Hydrolysis Product
- Bacterial Spectrum (Gram-Positive and Gram-Negative)
- Herpes Simplex Virus (HSV-1 and HSV-2) In Vitro Data
- Other Viruses (Influenza, Hepatitis, Human Immunodeficiency Virus)
- Antifungal and Antiprotozoal Activity
- Urinary Tract and Respiratory Indications
- Dosing for Acute vs Prophylactic Use
- Cautions and What OLE Cannot Replace
- Key Research Papers
- Connections
- Featured Videos
Traditional Mediterranean Use for Fevers
The medicinal use of olive leaf is one of the oldest documented plant therapies in the Mediterranean basin. Egyptian papyri describe olive leaf preparations for mummification and for treating skin and wound infections. Galen of Pergamon, the second-century Greek physician whose writings shaped European medicine for 1,500 years, described olive leaf decoctions as a remedy for fever, particularly for what he called "intermittent fevers" — almost certainly malaria, given the prevalence of Plasmodium falciparum and P. vivax in coastal Mediterranean regions at the time.
The Arab golden age of medicine, particularly the works of Avicenna (Ibn Sina, 10th-11th century), formalized olive leaf as a treatment for fever, skin infections, and "weakness," with detailed instructions for preparation: fresh young leaves macerated in honey or boiled in water and the strained decoction administered in graduated doses. Maimonides (12th century) included olive leaf in his materia medica for similar indications.
In the 19th century, British colonial physicians in Mediterranean territories documented olive leaf use by local populations for malaria management, and several Western pharmacological investigations of olive leaf extract were initiated. The 1854 paper by Daniel Hanbury in the Pharmaceutical Journal noted that olive leaf decoctions were "esteemed by the inhabitants of the Mediterranean shores as a febrifuge of considerable efficacy." Subsequent investigations isolated oleuropein in the early 20th century, and elenolic acid was characterized by researchers at a pharmaceutical company in the late 1960s as the primary antimicrobial moiety.
The traditional use persists. In modern Calabria, Sicily, Crete, and rural Greece, olive leaf tea is still a common home remedy for incipient cold and flu symptoms, and many olive-growing families maintain a year-round supply of dried leaves for this purpose.
Markin 2003 — Laboratory Study Against Bacteria and Fungi
Markin D, Duek L, Berdicevsky I (2003), published in Mycoses, is a laboratory study, not a review. The authors placed bacteria and fungi in different strengths of an olive leaf water extract. A 0.6% (w/v) extract killed almost all the bacteria tested within 3 hours; dermatophytes (skin fungi) were inhibited by a 1.25% (w/v) extract after 3 days; and Candida albicans was killed only by a 15% (w/v) extract after 24 hours. The active fractions of the extract were small molecules (under 1,000 molecular weight). The paper did not test viruses or protozoa.
Organisms reported as inhibited in vitro across the olive leaf literature (not all of them in the Markin paper; minimum inhibitory concentrations, MICs, where reported):
- Bacteria: Staphylococcus aureus (including MRSA strains), Streptococcus pyogenes, Escherichia coli, Pseudomonas aeruginosa, Klebsiella pneumoniae, Salmonella species, Helicobacter pylori, Campylobacter jejuni, Listeria monocytogenes
- Fungi: Candida albicans, Candida glabrata, Candida parapsilosis, several dermatophyte species (Trichophyton mentagrophytes, Microsporum canis), Aspergillus niger
- Viruses (from the calcium elenolate papers, Renis 1969 and 1975 and Heinze 1975, and the HIV papers, Lee-Huang 2003 and 2007; not tested by Markin): Herpes simplex virus types 1 and 2, HIV-1 (reverse transcriptase inhibition and cell entry inhibition), respiratory syncytial virus, parainfluenza type 3, influenza A and B
- Protozoa (not tested by Markin): Plasmodium falciparum (in red blood cell cultures), Trypanosoma cruzi, Leishmania species
The extract strengths that worked in the Markin study were 0.6% (w/v) for bacteria, 1.25% (w/v) for dermatophytes and 15% (w/v) for Candida albicans, so the fungi needed far stronger extract than the bacteria. These concentrations are achievable in tissue compartments in vivo for some indications (skin, mucosal surfaces, urinary tract) and less easily achievable for systemic infections, which informs the scope of clinical use described below.
The Markin paper concludes only that "these findings suggest an antimicrobial potential for olive leaves." It did not test a mechanism or a clinical use. The mechanism described on this page (elenolic acid's direct disruption of microbial protein synthesis and membrane integrity) and the uses described below (mild upper respiratory infection, mucosal candidiasis, and a topical agent for skin and wound infection) come from other sources, and none of them is a replacement for antibiotic therapy in serious bacterial infection.
Elenolic Acid — The Antimicrobial Hydrolysis Product
Oleuropein itself has modest direct antimicrobial activity. When oleuropein is broken down (hydrolyzed) by host or microbial enzymes (esterase, beta-glucosidase), it releases two smaller compounds: hydroxytyrosol and elenolic acid, a monoterpene secoiridoid. In a 1999 laboratory study (Bisignano), hydroxytyrosol stopped the growth of bacteria that cause gut and chest infections at 0.24-7.85 µg/mL for standard laboratory strains and 0.97-31.25 µg/mL for strains taken from patients. Whole oleuropein needed far more, 62.5-500 µg/mL for the standard strains, and had no effect on Haemophilus influenzae or Moraxella catarrhalis. Elenolic acid was not tested in that study; the emphasis on elenolic acid rests on the 1969-1975 laboratory work on its calcium salt, calcium elenolate. The structural breakdown:
Oleuropein = elenolic acid + hydroxytyrosol + glucose (linked as a secoiridoid glycoside ester)
When ingested, oleuropein is partially hydrolyzed in the stomach (acidic environment) and small intestine (microbial beta-glucosidase), releasing the elenolic acid moiety which then has access to the systemic circulation and can reach mucosal surfaces. Calcium-elenolate (the calcium salt of elenolic acid, characterized by researchers at a pharmaceutical company in the 1960s) was found to have particularly potent broad-spectrum antimicrobial activity and was patented as a candidate antimicrobial agent, though it was never commercialized.
The proposed antimicrobial mechanism of elenolic acid involves three actions:
- Direct membrane disruption — elenolic acid intercalates into the lipid bilayer of bacterial and viral envelopes, increasing membrane permeability and causing leakage of intracellular contents
- Protein synthesis inhibition — binding to bacterial ribosomes and interfering with peptide bond formation
- Viral entry inhibition — for enveloped viruses, binding to the viral envelope glycoproteins can prevent docking with host cell surface receptors. In the HIV-1 laboratory study that tested this (Lee-Huang 2007), it was oleuropein and hydroxytyrosol, not elenolic acid, that bound the virus's gp41 fusion protein and blocked the fusion step (EC50, the concentration giving half the maximum effect, 66-58 nM). This is the basis for the "antiviral" rather than purely antibacterial categorization.
The dual mechanism (membrane disruption plus protein synthesis inhibition) explains why microbial resistance to elenolic acid is rare in vitro — a single point mutation can confer resistance to a single-target antibiotic, but resistance to a membrane-active agent is much harder to evolve.
Bacterial Spectrum (Gram-Positive and Gram-Negative)
OLE shows in vitro inhibition against both gram-positive cocci and gram-negative rods, although the gram-positive activity is generally stronger. The largest single test (Sudjana 2009) checked a commercial olive leaf extract against 122 microorganisms. It was clearly active only against Campylobacter jejuni, Helicobacter pylori and Staphylococcus aureus including MRSA, with MICs as low as 0.31-0.78% (v/v). Against the other 79 organisms tested it showed little activity, with MICs mostly 6.25-50% (v/v), and the authors concluded that the extract "was not broad-spectrum in action." Clinically relevant organisms with reported in vitro susceptibility include:
Gram-positive cocci:
- Staphylococcus aureus including methicillin-resistant strains (MRSA); MICs as low as 0.31-0.78% (v/v) of a commercial extract (Sudjana 2009)
- Streptococcus pyogenes (Group A strep, the cause of strep throat); susceptible at similar concentrations
- Streptococcus pneumoniae (the common cause of community-acquired pneumonia); intermediate susceptibility
- Enterococcus faecalis and E. faecium (including some vancomycin-resistant strains); intermediate susceptibility
Gram-negative rods:
- Escherichia coli (the dominant cause of uncomplicated urinary tract infections, UTIs); cells exposed to a 0.6% (w/v) water extract were completely destroyed in the Markin study
- Klebsiella pneumoniae; intermediate susceptibility
- Salmonella enterica serovars (including Typhimurium); susceptible
- Pseudomonas aeruginosa; relatively resistant compared to other gram-negatives, requires higher concentrations
- Helicobacter pylori (cause of peptic ulcer disease and gastric cancer risk); susceptible, with synergy reported in combination with proton pump inhibitors and conventional antibiotics
- Campylobacter jejuni (a major cause of bacterial gastroenteritis); susceptible
The clinical translation: in vitro susceptibility in a microbiology lab does not automatically translate to clinical efficacy at oral doses that produce safe tissue concentrations. The most likely clinically meaningful applications are mucosal and superficial — oropharyngeal, urinary, and skin/wound — where high local concentrations are achievable. Systemic invasive infection (sepsis, endocarditis, deep abscess) absolutely requires conventional antibiotic therapy, and OLE is not a substitute for it.
Herpes Simplex Virus (HSV-1 and HSV-2) In Vitro Data
One of the most consistent in vitro findings for OLE is activity against herpes simplex virus types 1 and 2. The mechanism is at the level of viral entry — elenolic acid binds the glycoprotein gB and gC on the HSV envelope and prevents the virus from docking and fusing with the host cell membrane. Once docking is blocked, the virus cannot deliver its DNA payload into the host cell and replication does not occur.
Published in vitro data (Renis 1969):
- HSV-1 infectivity reduced by >90% at OLE concentrations of 0.1-0.5 mg/mL in Vero cell culture
- HSV-2 infectivity similarly reduced; in fact, HSV-2 may be slightly more susceptible than HSV-1
- Pre-treatment of virus with elenolic acid before exposure to cells is more effective than treatment after viral attachment, consistent with the entry-inhibition mechanism
The clinical translation to recurrent oral or genital herpes is plausible but not rigorously established. The human trials published so far used olive leaf extract as a cream or gel on cold sores (herpes labialis, usually caused by HSV-1), compared with acyclovir cream:
- 2% cream, 66 people (Toulabi, published 2021-2022) — in a randomised double-blind trial, a 2% olive leaf extract cream was compared with 5% acyclovir cream, each applied 5 times a day for 6 days. Symptoms improved in both groups. The olive leaf group had less bleeding (P = 0.038), itching (P = 0.002) and pain (P = 0.001) on day 3, and its treatment course was shorter (P = 0.001).
- Emulgel, 40 people (Al-Hallak, 2024) — in a triple-blinded randomised trial in recurrent cold sores, an olive leaf extract emulgel was compared with 5% acyclovir cream, each applied 5 times a day for 5 days. Pain and the day the pain healed did not differ between the groups; the scab fell off sooner with olive leaf extract (P = 0.040).
- Systematic review (Anheyer, 2025) — a review of herbal treatments for cold sores included 7 randomised trials with 1,250 patients in all (lemon balm, olive leaf extract, propolis and a sage-rhubarb cream). It reported that olive leaf extract gave faster symptom improvement and shorter healing time than acyclovir. Only 2 of the 7 trials were judged at low risk of bias, and the authors noted that the total sample size was small.
These trials tested olive leaf extract applied to the skin; they did not test capsules taken by mouth. Many integrative practitioners use OLE 500 mg twice daily as a long-term prophylactic in patients with frequent HSV reactivation, often in combination with L-lysine 1-3 g/day for additive effect.
Other Viruses (Influenza, Hepatitis, Human Immunodeficiency Virus)
OLE has documented in vitro activity against a wider range of enveloped viruses beyond HSV. The published data:
- Influenza A and B — OLE inhibits viral hemagglutinin-mediated attachment to sialic acid receptors on host cells, and additionally inhibits influenza neuraminidase activity (the same enzyme targeted by oseltamivir). In vitro IC50 values (IC50, the 50% inhibitory concentration) are in the low microgram per mL range. In a 1975 laboratory study, calcium elenolate "inactivates all myxoviruses so far tested" (myxoviruses are the virus group that includes influenza), and the virus's ability to infect cells was more sensitive to it than either its neuraminidase or its hemagglutinin activity (Renis 1975). These are laboratory results; this page cites no trial of olive leaf extract for influenza in people. Clinical translation has been limited to traditional use for the prodromal "coming down with something" sensation, where many practitioners prescribe OLE 1,000-3,000 mg in the first 48 hours.
- Respiratory syncytial virus (RSV) and parainfluenza — in vitro inhibition is reported. Clinical use is largely traditional/empirical in pediatric integrative practice.
- Hepatitis B — in a 2009 laboratory study, oleuropein taken from jasmine flowers (Jasminum officinale var. grandiflorum), not from olive leaf, reduced the release of hepatitis B surface antigen (HBsAg) from liver cells grown in the laboratory that produce the virus (HepG2 2.2.15 cells), in a dose-dependent way (IC50 23.2 µg/mL). Oleuropein injected into the abdomen (80 mg/kg twice daily) also reduced virus levels in the blood of infected ducks (Zhao 2009). No modern translation to clinical hepatitis B therapy has been made; the standard antiviral drugs for hepatitis B are entecavir and tenofovir.
- Human immunodeficiency virus — in laboratory studies, olive leaf extract blocked HIV-1 infection and its spread between cells (EC50 around 0.2 µg/mL; Lee-Huang 2003), its compounds oleuropein and hydroxytyrosol blocked the virus's gp41 fusion step (Lee-Huang 2007), and calcium elenolate inhibits reverse transcriptases (Heinze 1975). The required concentrations are not achievable safely in vivo, and OLE has no clinical role in human immunodeficiency virus management. The data is mechanistically interesting but not therapeutically actionable.
The conservative interpretation: OLE has plausible in vitro antiviral activity against a range of enveloped viruses, with the strongest clinical evidence (such as it is) for HSV. For acute upper respiratory viral illness (the common cold, mild influenza-like illness in adults), practitioners describe early high-dose OLE as an addition to supportive care, pointing to its favorable safety profile. For confirmed influenza in high-risk patients (elderly, pregnant, immunocompromised), the standard treatment is the antiviral drug oseltamivir, whose study results are summarised under Cautions below.
Antifungal and Antiprotozoal Activity
OLE's antifungal activity is well documented against the major clinically relevant yeasts and dermatophytes. Markin's 2003 paper reported in vitro inhibition of Candida albicans, C. glabrata, C. parapsilosis, and several dermatophyte species including Trichophyton mentagrophytes (athlete's foot) and Microsporum canis (ringworm). In that study the dermatophytes were inhibited by a 1.25% (w/v) extract, while Candida albicans was killed only by a much stronger 15% (w/v) extract. Practitioners describe empirical use for mild oral or genital candidiasis (OLE 500 mg twice daily, often in combination with topical antifungals or probiotics) and topical application of OLE-containing creams for dermatophyte infections of the skin.
The antiprotozoal activity has historical relevance for the original "fever" indication. Plasmodium falciparum in red blood cell culture is inhibited by olive leaf extract at concentrations in the low microgram per mL range, consistent with the traditional malarial fever use. No modern OLE is used for malaria prophylaxis or treatment — artemisinin combinations are vastly more effective — but the in vitro activity helps explain why traditional Mediterranean physicians could observe genuine benefit from olive leaf for what we now call intermittent malarial fevers.
Trypanosoma and Leishmania species are also inhibited in vitro, with no clinical translation but mechanistic interest for kinetoplastid parasitology research.
Urinary Tract and Respiratory Indications
The adult uses of OLE for infections that practitioners and users describe most often are:
- Recurrent uncomplicated urinary tract infection (UTI) prophylaxis — women with two or more uncomplicated urinary tract infections per year often try OLE 500 mg twice daily as a long-term prophylactic strategy, frequently combined with cranberry concentrate, D-mannose, and adequate hydration. The proposed mechanism is the in vitro activity against E. coli plus achievable urinary tract concentrations. This is described as an adjunct strategy — acute symptomatic urinary tract infections are treated with an antibiotic course, and users report that the prophylactic regimen may reduce how often infections return.
- Upper respiratory viral illness at first symptoms — practitioners describe OLE 1,000-3,000 mg in the first 24-48 hours of symptoms (sore throat, runny nose, low-grade fever) as an empirical strategy, often combined with zinc lozenges, vitamin C, and rest. The evidence for this use is anecdotal and traditional; supporters point to the safety profile.
- Recurrent oral herpes (HSV-1) prophylaxis — practitioners describe OLE 500-1,000 mg twice daily taken long term to reduce how often flare-ups occur, particularly for people who do not want to take daily acyclovir or valacyclovir.
- Topical for mild skin and wound infections — OLE-containing creams or solutions are used for superficial cuts, scrapes, and minor skin infections. Not a substitute for proper wound care or medical evaluation of significant injuries.
- Adjunct in Helicobacter pylori regimens — some integrative gastroenterologists add OLE 500 mg twice daily to conventional triple- or quadruple-therapy regimens for H. pylori, with the hypothesis that the additional antimicrobial activity improves eradication rates. Evidence is preliminary but mechanistically plausible.
Dosing for Acute vs Prophylactic Use
The regimens below are those practitioners describe; this page cites no trial that tested them.
- Acute upper respiratory illness: 1,000 mg three times daily of OLE standardized to 18-20% oleuropein for the first 48-72 hours of symptoms, then tapered to 500 mg twice daily for 5-7 more days
- HSV flare-up prophylaxis (long-term): 500-1,000 mg twice daily continuously, often indefinitely, with flare frequency reviewed every 3-6 months
- Urinary tract infection recurrence prophylaxis (long-term): 500 mg twice daily continuously, often combined with the other modalities mentioned above, and reviewed at 6 months
- Acute urinary tract infection symptoms while awaiting culture/treatment: 1,000 mg three times daily, combined with copious water intake and unsweetened cranberry juice or D-mannose. This is described as bridge therapy only — a urinary tract infection confirmed by culture is treated with antibiotics.
- Helicobacter pylori adjunct: 500 mg twice daily during the 10-14 day pharmaceutical eradication regimen
"Herxheimer" or die-off reactions (mild flu-like symptoms, fatigue, headache) are sometimes reported in the first few days of high-dose OLE, particularly in patients with significant chronic infection or candidal overgrowth. These are reported to resolve in 2-4 days; when they persist or are severe, practitioners describe halving the dose and increasing it more slowly.
Cautions and What OLE Cannot Replace
- OLE is not a substitute for antibiotics in serious bacterial infection — bacterial pneumonia, pyelonephritis, sepsis, endocarditis, bacterial meningitis, deep abscesses, and serious skin/soft tissue infection (cellulitis with systemic symptoms, necrotizing fasciitis) all require conventional antibiotic therapy administered promptly. Delay can be fatal. In these infections OLE is at most an addition to antibiotics, never a replacement.
- Symptomatic urinary tract infection in a pregnant woman, a diabetic, an elderly patient, or anyone with kidney disease — is treated with antibiotics even when symptoms are mild, not with OLE alone, because in these groups the infection can spread up to the kidneys (ascending infection).
- Fever in a child, particularly an infant — hospitals treat fever in a young infant as urgent, because a serious bacterial infection has to be ruled out. The "fever" indication in adult traditional use does not extend to febrile infants.
- Immunocompromised patients — in oncology patients on chemotherapy, transplant patients on immunosuppression, acquired immunodeficiency syndrome (AIDS) patients with low CD4 counts, and patients on biologics for autoimmune disease, infections can become serious quickly, which is why hospitals treat fever in these groups as urgent.
- Influenza in high-risk patients — for pregnant women, the elderly, the morbidly obese, and patients with chronic lung/heart disease with documented influenza, the standard treatment is the antiviral drug oseltamivir started promptly. In a 2014 analysis of 29,234 patients of all ages admitted to hospital with pandemic H1N1 influenza (an observational study), neuraminidase-inhibitor treatment started within 2 days of symptoms was associated with lower risk of death than no treatment (adjusted odds ratio 0.50); the link was weaker and not significant in children. A 2014 Cochrane review of randomised trials found that oseltamivir shortened the time to first symptom relief in adults from 7 to 6.3 days and had no significant effect on hospital admissions.
- Drug interactions — OLE's blood-pressure-lowering effect (see Cardiovascular deep-dive) means caution with antihypertensives; its blood-glucose effect (see Blood Sugar deep-dive) means caution with insulin and sulfonylureas. Stopping OLE 1-2 weeks before surgery is a common precaution for herbs with these blood-pressure and blood-sugar effects.
The honest framing for patients: OLE has documented in vitro antimicrobial activity, strongest against a few organisms such as H. pylori, C. jejuni and S. aureus, and a strong traditional-use record for mild infections, but the clinical evidence base is far thinner than for pharmaceutical antibiotics or antivirals. People use it as an adjunct for mild self-limited illness, as long-term prophylaxis for recurrent HSV or urinary tract infection, and as a complementary strategy. Serious infections can become dangerous when appropriate medical care is delayed.
Key Research Papers
- Markin D, Duek L, Berdicevsky I (2003). In vitro antimicrobial activity of olive leaves. Mycoses 46(3-4):132-136. — PubMed PMID: 12870202
- Heinze JE et al. (1975). Specificity of the antiviral agent calcium elenolate. Antimicrobial Agents and Chemotherapy. — PubMed PMID: 53031
- Renis HE (1969). In vitro antiviral activity of calcium elenolate. Antimicrobial Agents and Chemotherapy. — PubMed PMID: 5396483
- Soler-Rivas C, Espín JC, Wichers HJ (2000). Oleuropein and related compounds. Journal of the Science of Food and Agriculture 80(7):1013-1023. — doi:10.1002/(SICI)1097-0010(20000515)80:7<1013::AID-JSFA571>3.0.CO;2-C
- Sudjana AN et al. (2009). Antimicrobial activity of commercial Olea europaea (olive) leaf extract. International Journal of Antimicrobial Agents. — PubMed PMID: 19135874
- Pereira AP et al. (2007). Phenolic compounds and antimicrobial activity of olive (Olea europaea L. Cv. Cobrançosa) leaves. Molecules. — PubMed PMID: 17873849
- Bisignano G et al. (1999). On the in-vitro antimicrobial activity of oleuropein and hydroxytyrosol. Journal of Pharmacy and Pharmacology. — PubMed PMID: 10504039
- Lee-Huang S et al. (2003). Anti-HIV activity of olive leaf extract (OLE) and modulation of host cell gene expression by HIV-1 infection and OLE treatment. Biochemical and Biophysical Research Communications. — PubMed PMID: 12878215
- Micol V et al. (2005). The olive leaf extract exhibits antiviral activity against viral haemorrhagic septicaemia rhabdovirus (VHSV). Antiviral Research. — PubMed PMID: 15869811
- Omar SH (2010). Oleuropein in olive and its pharmacological effects. Scientia Pharmaceutica. — PubMed PMID: 21179340
- Tafesh A et al. (2011). Synergistic antibacterial effects of polyphenolic compounds from olive mill wastewater. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 21647315
- Lee-Huang S et al. (2007). Discovery of small-molecule HIV-1 fusion and integrase inhibitors oleuropein and hydroxytyrosol: Part I. fusion [corrected] inhibition. Biochemical and Biophysical Research Communications 354(4):872-878. — PubMed PMID: 17275783
- Renis HE (1975). Inactivation of myxoviruses by calcium elenolate. Antimicrobial Agents and Chemotherapy 8(2):194-199. — PubMed PMID: 1180544
- Zhao G, Yin Z, Dong J (2009). Antiviral efficacy against hepatitis B virus replication of oleuropein isolated from Jasminum officinale L. var. grandiflorum. Journal of Ethnopharmacology 125(2):265-268. — PubMed PMID: 19580857
- Toulabi T et al. (2022). The efficacy of olive leaf extract on healing herpes simplex virus labialis: A randomized double-blind study. Explore (NY) 18(3):287-292. — PubMed PMID: 33541815
- Gaizeh Al-Hallak MA, Hsaian JA, Aljoujou AA (2024). Evaluating the effectiveness of topical olive leaf extract emulgel in managing recurrent herpes labialis: a randomized controlled clinical study. Scientific Reports 14(1):29989. — PubMed PMID: 39623211
- Anheyer M, Cramer H, Ostermann T, Längler A, Anheyer D (2025). Herbal Medicine for Treating Herpes Labialis: A Systematic Review. Journal of Integrative and Complementary Medicine 31(11):946-954. — PubMed PMID: 40526027
- Muthuri SG et al. (2014). Effectiveness of neuraminidase inhibitors in reducing mortality in patients admitted to hospital with influenza A H1N1pdm09 virus infection: a meta-analysis of individual participant data. Lancet Respiratory Medicine 2(5):395-404. — PubMed PMID: 24815805
- Jefferson T et al. (2014). Neuraminidase inhibitors for preventing and treating influenza in adults and children. Cochrane Database of Systematic Reviews 2014(4):CD008965. — PubMed PMID: 24718923