Olive Leaf for Cardiovascular Health and Blood Pressure
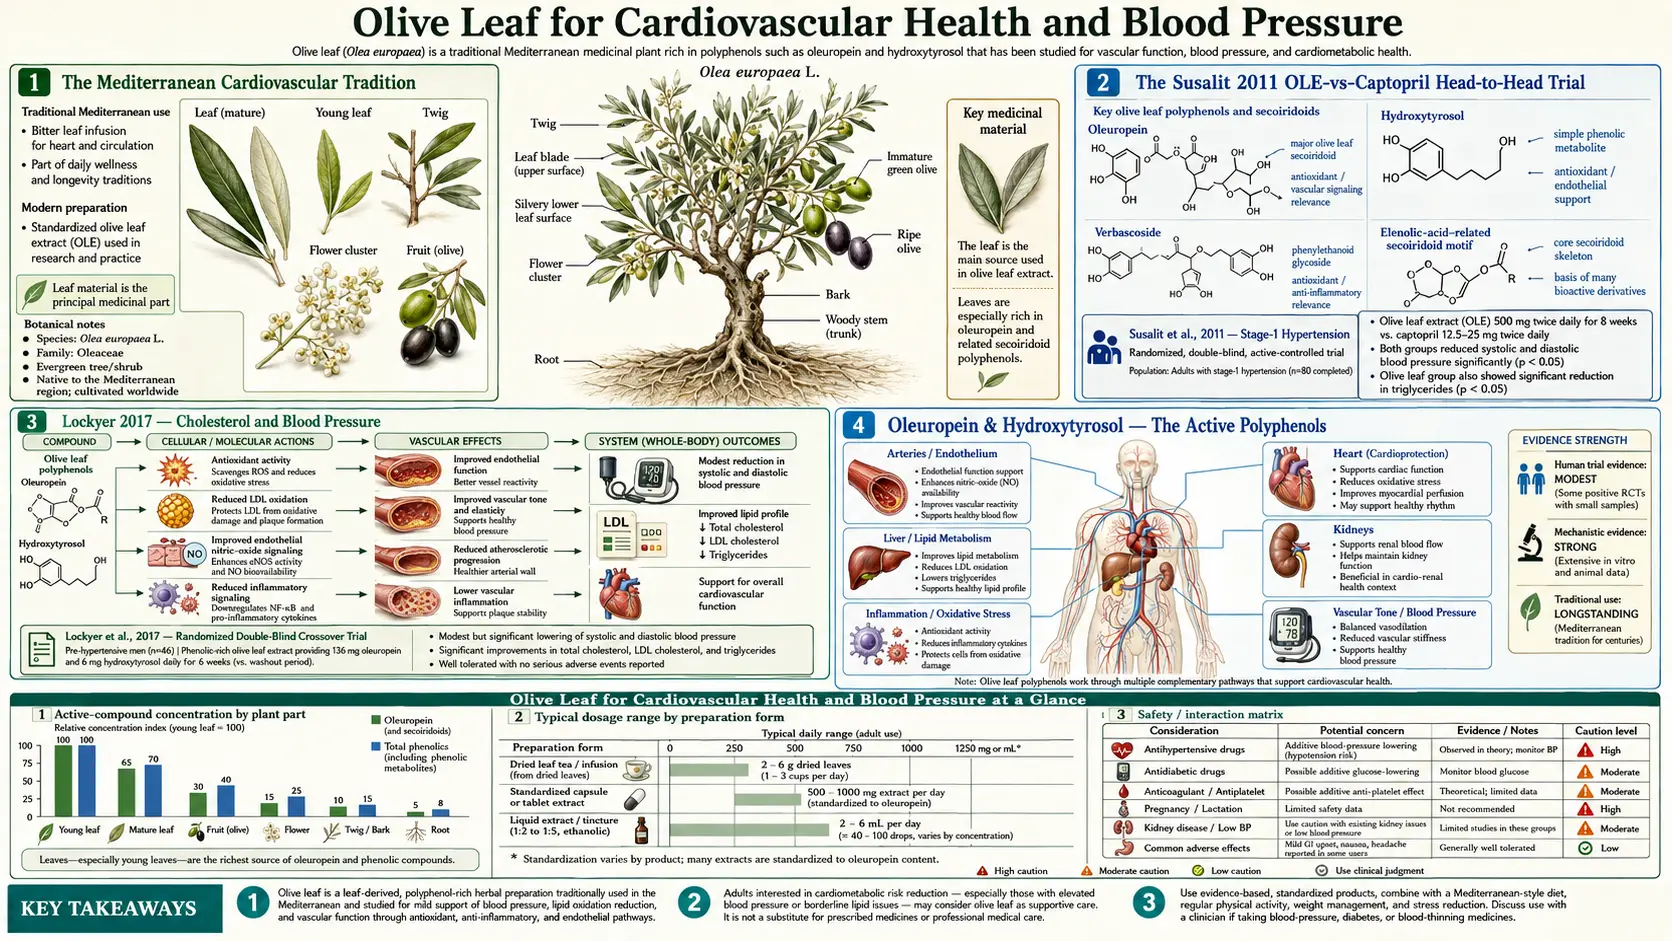
Olive leaf (Olea europaea) is one of the few herbal therapeutics with a head-to-head clinical trial against a first-line antihypertensive pharmaceutical. The 2011 Susalit trial randomized 179 patients with stage-1 hypertension to either standardized olive leaf extract (OLE 500 mg twice daily; the batch used held 19.9% oleuropein) or captopril 12.5-25 mg twice daily for 8 weeks. Blood pressure reduction was statistically equivalent between the two arms — approximately 11.5 mmHg systolic and 4.8 mmHg diastolic in both groups — while the OLE group also showed a meaningful reduction in triglycerides that captopril did not produce. This is a remarkable result: a polyphenol-rich leaf extract from a Mediterranean tree matched an angiotensin-converting enzyme inhibitor (ACE inhibitor) on its primary endpoint and beat it on a secondary lipid endpoint (LDL cholesterol). This deep-dive walks through the mechanism (oleuropein and hydroxytyrosol as the active polyphenols, ACE-inhibition and vasodilatory pathways), the pivotal clinical trials, the comparative advantage over the olive fruit itself, and the doses used in the trials in borderline and stage-1 hypertension.
Table of Contents
- The Mediterranean Cardiovascular Tradition
- The Susalit 2011 OLE-vs-Captopril Head-to-Head Trial
- Lockyer 2017 — Cholesterol and Blood Pressure
- Oleuropein & Hydroxytyrosol — The Active Polyphenols
- ACE Inhibition and the Renin-Angiotensin System
- Endothelial Nitric Oxide and Vasodilation
- Lipid Effects (Low-Density Lipoprotein Oxidation, Triglycerides)
- Olive Leaf vs Extra-Virgin Olive Oil — Polyphenol Content
- Practical Dosing and Standardization
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Mediterranean Cardiovascular Tradition
The olive tree has been cultivated around the Mediterranean basin for at least 6,000 years, and the medicinal use of its leaves predates the modern characterization of olive oil's cardiovascular benefits by several millennia. Egyptian, Greek, and later Arab physicians used olive leaf decoctions for fever, for what they called "weakness of the heart," and for skin and wound infections. The cardiovascular indication is documented in Galen, Avicenna, and Maimonides.
The modern epidemiologic story begins with Ancel Keys' Seven Countries Study in the 1950s and 1960s, which identified the Mediterranean dietary pattern as protective against coronary heart disease. The original explanatory model centered on monounsaturated fats from olive oil. As analytical chemistry improved, attention shifted to the polyphenols — specifically oleuropein and hydroxytyrosol — that account for the bitter, astringent taste of fresh-pressed extra-virgin olive oil and that are largely absent from refined olive oils. The PREDIMED trial in Spain (its 2013 report was withdrawn and replaced by the corrected Estruch et al. 2018, NEJM) assigned 7,447 adults at high cardiovascular risk to a Mediterranean diet supplemented with extra-virgin olive oil, one supplemented with nuts, or a reduced-fat control diet; after a median of 4.8 years the olive-oil group had fewer major cardiovascular events than the control group (hazard ratio 0.69, 95% CI 0.53–0.91).
Olive leaf extract sits in an interesting position relative to this story. The leaf contains the same dominant polyphenol (oleuropein) at much higher concentration than the fruit — fresh olive leaves are typically 6-9% oleuropein by dry weight, while extra-virgin olive oil is approximately 0.005-0.05% oleuropein equivalents. A 500 mg dose of OLE standardized to 18% oleuropein delivers roughly 90 mg of oleuropein — the equivalent of several liters of high-quality olive oil. This concentration is what makes pharmaceutical-comparable trial results possible from a leaf extract.
The Susalit 2011 OLE-vs-Captopril Head-to-Head Trial
The pivotal clinical trial for OLE in hypertension is Susalit E et al. (2011), published in Phytomedicine. This was an 8-week, double-blind, randomized, parallel-group trial in Indonesia, after a 4-week run-in, of 179 adults with stage-1 hypertension (systolic blood pressure (BP) 140-159 mmHg) who were either untreated or already taking blood-pressure medicine. 148 completed it (72 on OLE, 76 on captopril), 83% were women, and average starting blood pressure was about 149/94 mmHg.
Participants were randomized to one of two arms:
- OLE arm — 500 mg twice daily of a standardized olive leaf extract (16–24% oleuropein; the batch used held 19.9%)
- Captopril arm — 12.5 mg twice daily initially, up-titrated to 25 mg twice daily if needed after 2 weeks
Primary endpoint was change in systolic blood pressure at 8 weeks. Secondary endpoints included diastolic blood pressure, fasting lipid panel, and tolerability.
Results at 8 weeks:
- Systolic blood pressure reduction: −11.5 mmHg (OLE) vs −13.7 mmHg (captopril). Difference not statistically significant.
- Diastolic blood pressure reduction: −4.8 mmHg (OLE) vs −6.4 mmHg (captopril). Difference not statistically significant.
- Triglycerides: fell significantly within the OLE group but not within the captopril group. A 2021 meta-analysis of the trial data (Ismail and colleagues) found no significant difference from captopril in total cholesterol, HDL cholesterol or triglycerides; the one significant difference was LDL cholesterol, 6 mg/dL lower on OLE (95% CI −11.5 to −0.5).
- Adverse events: dry cough (a known captopril class effect) reported in captopril arm but not in OLE arm.
- Dropouts: 18 of 90 people left the OLE arm (8 for not taking the tablets, 6 for “ineffective therapy”, 1 for an adverse effect, 3 for other reasons) and 13 of 89 left the captopril arm (8 for not taking the tablets, 2 for ineffective therapy, 3 for other reasons).
The authors concluded that OLE 500 mg twice daily was similarly effective in lowering systolic and diastolic blood pressure in stage-1 hypertension as captopril at 12.5–25 mg twice daily. The 2021 meta-analysis by Ismail and colleagues found that the blood-pressure difference between the two arms was not significant either way, and rated the certainty of this evidence as low. (de Bock 2013, sometimes cited alongside Susalit, is a separate 12-week crossover trial of 46 overweight middle-aged men that found no effect on 24-hour blood pressure or the lipid profile; Lockyer and colleagues' olive leaf paper in Nutrition and Aging is a narrative review, not a meta-analysis.) The trial does not directly answer the question of OLE's effect in stage-2 hypertension (160+/100+ mmHg), and OLE has not been compared to other antihypertensive classes (calcium channel blockers, thiazides, angiotensin receptor blockers (ARBs)) in similar head-to-head designs.
A 2025 meta-analysis (Lachovicz and colleagues) found only 3 trials, with 248 people, that met its criteria. Over all doses, olive leaf extract lowered systolic pressure by about 6 mmHg (−6.03 mmHg) from before to after treatment; the diastolic change (−2.38 mmHg) was not significant. In the trials that used 1,000 mg a day, systolic and diastolic pressure fell by about 11.5 and 4.7 mmHg (−11.45 and −4.65 mmHg). The authors list variable trial quality among the limitations and call for larger studies to confirm efficacy and safety.
Lockyer 2017 — Cholesterol and Blood Pressure
Lockyer S et al. (2017), published in the European Journal of Nutrition, complements the Susalit trial with a focus on the lipid effects. This was a randomized, double-blind, controlled 6-week crossover trial of 60 prehypertensive men (systolic 121-140, diastolic 81-90). Participants received either OLE providing 136 mg/day oleuropein and 6 mg hydroxytyrosol, or a polyphenol-free control, in 6-week periods separated by a 4-week washout.
Findings at end of OLE phase compared to placebo phase:
- Daytime ambulatory systolic blood pressure: −3.95 mmHg (p = 0.027); 24-hour systolic −3.33 mmHg; daytime diastolic −3.00 mmHg; 24-hour diastolic −2.42 mmHg (all statistically significant)
- Total cholesterol: −0.32 mmol/L (approximately −12 mg/dL)
- Low-density lipoprotein (LDL) cholesterol: −0.19 mmol/L (approximately −7 mg/dL)
- Triglycerides: −0.18 mmol/L (approximately −16 mg/dL)
- Vascular function (assessed by digital volume pulse-derived measures): not affected; other inflammation markers (apart from a fall in interleukin-8) and glucose metabolism were not affected either
The Lockyer trial adds two things: a blood pressure effect at a lower oleuropein dose than in the Susalit extract (136 mg/day), and a lipid effect in a second trial. It found no change in vascular function. The smaller absolute blood pressure effect in Lockyer (vs Susalit) is expected because Lockyer enrolled prehypertensive rather than frankly hypertensive participants — antihypertensive effects are typically proportional to baseline blood pressure.
The largest trial so far (Lamti and colleagues, 2025, Tunisia) gave olive leaf extract (307 people) or placebo (314 people) for 12 weeks to 621 people already being treated for high blood pressure. 24-hour systolic pressure fell by 6.4 mmHg on the extract and 1.5 mmHg on placebo. Blood sugar, triglycerides, C-reactive protein (CRP, a marker of inflammation) and body weight also fell on the extract, the lipid profile improved, and no significant adverse events were reported.
Not every trial agrees. In a 2026 Belgian trial (Lauwers and colleagues), 56 adults with systolic pressure of 130 mmHg or higher took 440 mg of an olive extract (about 124 mg oleuropein) or placebo daily for 8 weeks. Systolic pressure fell in both groups (−8.3 vs −7.3 mmHg), and the difference was not significant; total cholesterol, LDL and apo B also fell in both groups with no significant difference. The authors note that the published results on olive polyphenols and blood pressure conflict.
Oleuropein & Hydroxytyrosol — The Active Polyphenols
Oleuropein is the principal phenolic glycoside of Olea europaea. Chemically, it is a secoiridoid ester of elenolic acid and hydroxytyrosol, glycosylated with a glucose moiety. The molecule is what gives unripe olives and fresh olive leaves their characteristic intense bitter taste; the curing process for table olives is essentially a controlled deglycosylation of oleuropein to make the fruit palatable.
After oral ingestion, oleuropein is partially hydrolyzed in the stomach and small intestine by intestinal microbiota and host enzymes, releasing hydroxytyrosol (also called 3,4-dihydroxyphenylethanol or DOPET). Hydroxytyrosol is the smaller, more bioavailable, and arguably more cardiovascularly active downstream metabolite. The European Food Safety Authority (EFSA) granted a health claim in 2011 for "olive oil polyphenols contribute to the protection of blood lipids from oxidative stress" specifically based on hydroxytyrosol content, requiring at least 5 mg hydroxytyrosol and derivatives per 20 g of olive oil to make the claim.
Oleuropein and hydroxytyrosol together account for the vast majority of olive leaf's biological activity. Other phenolic constituents of olive leaf (tyrosol, verbascoside, luteolin glycosides, rutin, apigenin glycosides, ligstroside) contribute additional antioxidant capacity but are present in much smaller quantities. A well-standardized OLE product is essentially an oleuropein delivery system.
ACE Inhibition and the Renin-Angiotensin System
One mechanism behind OLE's blood pressure effect parallels the mechanism of pharmaceutical angiotensin-converting enzyme inhibitors (ACE inhibitors) like captopril, lisinopril, and enalapril. Angiotensin-converting enzyme (ACE) is a zinc-dependent metalloprotease that cleaves the inactive decapeptide angiotensin I to the potent vasoconstrictor angiotensin II. Pharmaceutical angiotensin-converting enzyme inhibitors lower blood pressure by reducing the supply of angiotensin II, which in turn:
- Reduces direct arteriolar vasoconstriction
- Reduces aldosterone-mediated sodium retention
- Reduces sympathetic nervous system activation
- Increases bradykinin levels (the mechanism of the captopril cough)
In vitro assays of olive leaf extract show measurable ACE-inhibitory activity, though substantially less potent than the synthetic drugs at equimolar concentrations. The test-tube study that isolated the active compound (Hansen and colleagues, 1996) found that oleuropein itself, as found in the leaf, showed no significant ACE inhibition. A breakdown product called oleacein was a strong inhibitor (IC50 26 µM, the concentration that halves the enzyme's activity), and oleuropein and four related glycosides blocked ACE by 64–95% only after an enzyme had first split them. The clinical effect in humans is presumably the sum of weak ACE inhibition plus the other mechanisms described below (endothelial nitric oxide, oxidative stress reduction, direct vasodilation). The trials so far, lasting 6–12 weeks, have not reported the characteristic ACE-inhibitor side effects, and the largest (Lamti 2025, 621 patients) reported no significant adverse events; trials of this size and length cannot rule out rare effects such as angioedema.
Endothelial Nitric Oxide and Vasodilation
A second blood-pressure mechanism is direct effects on the vascular endothelium. The endothelium synthesizes nitric oxide (NO) from L-arginine via endothelial NO synthase (eNOS), and NO diffuses to vascular smooth muscle to activate guanylate cyclase, raise cGMP, and induce vasodilation. Endothelial dysfunction — reduced NO bioavailability — is one of the earliest measurable abnormalities in hypertension, atherosclerosis, diabetes, and aging.
Oleuropein and hydroxytyrosol both upregulate eNOS expression and enhance NO release from cultured endothelial cells. The mechanism appears to involve both direct activation of eNOS via phosphorylation at Ser1177 (an Akt-mediated event) and reduction of NO scavenging by superoxide (the antioxidant effect, see the Antioxidant deep-dive). Loss of NO bioavailability is a key driver of vascular stiffness and pulse-wave velocity changes; the Lockyer trial above, however, found that its digital-volume-pulse-derived vascular function measures were not affected.
This NO-mediated vasodilatory effect is mechanistically distinct from ACE inhibition, and it may explain why the OLE blood pressure effect appears comparable to angiotensin-converting enzyme inhibitors even though the in vitro ACE inhibition is much weaker than the pharmaceutical agents — the additional NO pathway contributes substantially to the in vivo effect.
Lipid Effects (Low-Density Lipoprotein Oxidation, Triglycerides)
The triglyceride and cholesterol effects observed in both Susalit and Lockyer trials are mechanistically anchored in two phenomena:
- Low-density lipoprotein oxidation protection — hydroxytyrosol is one of the most efficient inhibitors of low-density lipoprotein oxidation among dietary polyphenols. Oxidized low-density lipoprotein is the form that is taken up by macrophage scavenger receptors to form the foam cells of atherosclerotic plaque, and oxidation of low-density lipoprotein is a rate-limiting step in atherogenesis. The European Food Safety Authority health claim mentioned above (5 mg hydroxytyrosol per 20 g olive oil) is specifically based on this protection of low-density lipoprotein from oxidation. OLE delivers substantially more hydroxytyrosol equivalents per dose than dietary olive oil.
- Hepatic lipogenesis suppression — oleuropein and hydroxytyrosol modulate the SREBP-1c transcription factor that controls hepatic fatty acid synthesis, reducing de novo lipogenesis and triglyceride secretion. This is the proposed mechanism for the triglyceride reductions seen in some OLE trials; others, such as de Bock 2013 and the 2026 Belgian trial (Lauwers), found no significant lipid difference from placebo.
The magnitude of the lipid effect from OLE alone is modest (single-digit mg/dL reductions in low-density lipoprotein, low double-digits in triglycerides) and would not substitute for high-intensity statin therapy in a patient with established coronary disease or familial hypercholesterolemia. Its relevance is greatest for people with borderline or mildly elevated lipids and stage-1 hypertension, where the trials measured a combined blood pressure-plus-lipid effect.
The broadest summary so far is a 2026 GRADE-rated meta-analysis of 30 randomized trials with 1,726 people (Mansouri and colleagues). Olive leaf supplements lowered total cholesterol, triglycerides, LDL cholesterol, apolipoprotein B and oxidized LDL, raised apolipoprotein A1, and lowered the inflammation marker TNF-alpha, systolic and diastolic blood pressure, body weight and BMI. They had no significant effect on blood-sugar markers. The certainty of the evidence ranged from very low to high, depending on the outcome.
Olive Leaf vs Extra-Virgin Olive Oil — Polyphenol Content
A common patient question is whether more olive oil could take the place of an olive leaf extract. The answer depends on the specific outcome of interest and the practical limits of olive oil consumption.
Quantitative polyphenol comparison (oleuropein-equivalents per gram, approximate):
- Fresh olive leaves (dry weight basis): 60-90 mg/g (6-9%)
- Standardized OLE capsule (18% oleuropein): 180 mg/g
- Extra-virgin olive oil (top-tier, fresh, unfiltered): 0.5-1.5 mg/g
- Standard supermarket extra-virgin olive oil: 0.05-0.5 mg/g
- Refined "light" or "pure" olive oil: <0.05 mg/g (negligible)
To match the ~180 mg oleuropein delivered by 1 g of OLE capsule (i.e., the ~90 mg in a single OLE 500 mg capsule), one would need to consume approximately 360 mL of even high-polyphenol extra-virgin olive oil daily — far more than is practical and well above caloric reasonableness (about 3,200 kcal of just oil). This calculation explains why OLE is the format that produces pharmaceutical-comparable blood pressure effects: it delivers a clinically meaningful polyphenol dose in a form that does not require unreasonable caloric intake.
The flip side is that olive oil provides additional benefits beyond polyphenols — the monounsaturated fat itself (oleic acid) has favorable effects on insulin sensitivity, postprandial inflammation, and bile acid composition. Traditional Mediterranean eating uses ample extra-virgin olive oil in cooking and on salads; olive leaf extract is a separate, concentrated source of the same polyphenols, which is what the blood pressure and lipid trials above tested. See our Olive Oil page for the dietary-fat side of the story.
Practical Dosing and Standardization
The OLE doses used in the published cardiovascular trials:
- Standard antihypertensive dose: 500 mg twice daily (1,000 mg total) of OLE standardized to 16–24% oleuropein (the batch used held 19.9%). This is the regimen used in the Susalit trial.
- Lower maintenance / prehypertensive dose: 500 mg once daily of similarly standardized extract, the dose used in a 2008 study of borderline-hypertensive twins (Perrinjaquet-Moccetti and colleagues).
- Stacking with other lifestyle interventions: OLE response is potentiated by sodium reduction (DASH-style diet), increased potassium intake (leafy greens, citrus), regular aerobic exercise, and weight loss in overweight patients. All of these address the same blood-pressure machinery from different angles.
- Time to effect: blood pressure changes are typically measurable at 4 weeks and approach near-maximal effect by 8 weeks. Lipid changes are measurable at 6 weeks. The Susalit trial measured its main result at 8 weeks.
- Monitoring: home blood pressure cuff readings 3-4× per week (morning and evening) provide far more useful data than occasional office readings, and are how an additive drop in blood pressure shows up in people adding OLE to existing antihypertensives.
Quality-control note: oleuropein content in OLE products varies dramatically between brands. Some "olive leaf extract" capsules labeled with no oleuropein percentage may contain 1-2% oleuropein or less — ten-fold less than the products used in clinical trials. Only a label that states the oleuropein percentage and milligram content shows how a product compares with the extracts used in the trials.
Cautions and Drug Interactions
- Additive hypotension with antihypertensives — the most important interaction. In people already on angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, calcium channel blockers, beta blockers, thiazides, or alpha blockers, OLE's blood-pressure lowering adds to the medicine's. Dizziness on standing up and fainting (syncope) are the signs of blood pressure falling too low. The Lamti 2025 trial gave OLE for 12 weeks to people already treated for high blood pressure and reported no significant adverse events.
- Hypoglycemia in diabetics — OLE has independent blood-glucose-lowering effects (see the Blood Sugar deep-dive). In people on insulin or sulfonylureas the glucose-lowering effects add together, and low blood sugar is the risk.
- Pregnancy and lactation — insufficient data for pregnancy safety; traditional use does include olive leaf, but standardized high-dose OLE has not been studied in pregnant women, so there is no safety data for it in pregnancy. Lactation safety also undetermined.
- Surgery — a small risk of low blood pressure during an operation is the reason given for stopping OLE 1-2 weeks before elective surgery.
- Olive allergy (rare) — cross-reactivity is possible. People with a documented allergy to olive pollen or olive fruit are the group at risk of a reaction to OLE.
- Drug interactions of theoretical concern — warfarin (oleuropein has weak antiplatelet effects; the international normalized ratio (INR) blood test is how a change in warfarin's effect shows), cyclosporine and other cytochrome P450 3A4 (CYP3A4) substrates (limited interaction data; blood levels of these drugs are how a change shows). No documented major adverse interactions in the published literature.
Key Research Papers
- Susalit E et al. (2011). Olive (Olea europaea) leaf extract effective in patients with stage-1 hypertension: comparison with Captopril. Phytomedicine 18(4):251-258. — PubMed PMID: 21036583
- Lockyer S et al. (2017). Impact of phenolic-rich olive leaf extract on blood pressure, plasma lipids and inflammatory markers: a randomised controlled trial. European Journal of Nutrition 56(4):1421-1432. — PubMed PMID: 26951205
- Perrinjaquet-Moccetti T et al. (2008). Food supplementation with an olive (Olea europaea L.) leaf extract reduces blood pressure in borderline hypertensive monozygotic twins. Phytotherapy Research 22(9):1239-1242. — PubMed PMID: 18729245
- de Bock M et al. (2013). Olive (Olea europaea L.) leaf polyphenols improve insulin sensitivity in middle-aged overweight men: a randomized, placebo-controlled, crossover trial. PLOS ONE. — PubMed PMID: 23516412
- Hansen K et al. (1996). Isolation of an angiotensin converting enzyme (ACE) inhibitor from Olea europaea and Olea lancea. Phytomedicine. — PubMed PMID: 23194770
- Estruch R et al. (2013). Primary prevention of cardiovascular disease with a Mediterranean diet (PREDIMED). NEJM. — PubMed PMID: 23432189 — Retracted in 2018 (retraction notice: PubMed PMID: 29897867); corrected and republished as PubMed PMID: 29897866
- Lockyer S, Yaqoob P, Spencer JPE, Rowland I (2012). Olive leaf phenolics and cardiovascular risk reduction: physiological effects and mechanisms of action. Nutrition and Aging 1:125-140 (narrative review). — doi:10.3233/NUA-2012-0011
- Khayyal MT et al. (2002). Blood pressure lowering effect of an olive leaf extract (Olea europaea) in L-NAME induced hypertension in rats. Arzneimittelforschung. — PubMed PMID: 12489249
- Visioli F, Romani A, Mulinacci N, Zarini S, Conte D, Vincieri FF, Galli C (1999). Antioxidant and other biological activities of olive mill waste waters. Journal of Agricultural and Food Chemistry 47(8):3397-3401. — PubMed PMID: 10552663
- EFSA Panel on Dietetic Products, Nutrition and Allergies (2011). Scientific Opinion on the substantiation of health claims related to polyphenols in olive and protection of LDL particles from oxidative damage. EFSA Journal. — PubMed
- Romero M et al. (2016). Antihypertensive effects of oleuropein-enriched olive leaf extract in spontaneously hypertensive rats. Food and Function. — PubMed PMID: 26593388
- Ismail MA, Norhayati MN, Mohamad N (2021). Olive leaf extract effect on cardiometabolic profile among adults with prehypertension and hypertension: a systematic review and meta-analysis. PeerJ 9:e11173. — PubMed PMID: 33868820
- Lachovicz R, Ferro-Lebres V, Almeida-de-Souza J, Pereira JA (2025). Efficacy of olive leaf extract in improving blood pressure in pre-hypertensive and hypertensive individuals: a systematic review and meta-analysis. Phytotherapy Research. — PubMed PMID: 40325976
- Lamti F, Trabelsi I, Dhaoui R, et al. (2025). Efficacy of olive leaf extracts in controlling blood pressure in hypertensive patients: a double-blind randomized clinical trial. Journal of Hypertension 43(11):1878-1884. — PubMed PMID: 40990594
- Lauwers S, Breynaert A, Verlaet A, Fransen E, Bringmans T, Roth L, Tuenter E, Bosmans J, Hermans N (2026). Evaluation of the effect of olive extracts on blood pressure and cardiovascular health markers in adults: findings from a double-blind, placebo-controlled, randomised trial. PLOS ONE 21(3):e0344278. — PubMed PMID: 41805711
- Mansouri F, Mardani M, Rucci C, Bordoni L, Gabbianelli R (2026). A GRADE-assessed systematic review and meta-analysis of randomized controlled trials evaluating the effects of olive leaf or olive pomace supplementation on cardiometabolic and anthropometric health markers. Nutrition, Metabolism and Cardiovascular Diseases 36(10):104821. — PubMed PMID: 42303499
PubMed Topic Searches
Connections
- All Herbs
- Olive Leaf Benefits Hub
- Olive Leaf Overview
- OLE Antimicrobial & Antiviral
- OLE Antioxidant & Anti-Aging
- OLE Blood Sugar
- Hypertension
- Olive Oil
- Celery Juice for Blood Pressure
- Garlic
- Hibiscus
- Magnesium
- Potassium
- Cardiology
- Vitamin C
- Hydroxytyrosol — the olive phenol oleuropein is hydrolysed into, and the European Food Safety Authority-recognised active.
- History