Olive Leaf for Antioxidant and Anti-Aging Effects
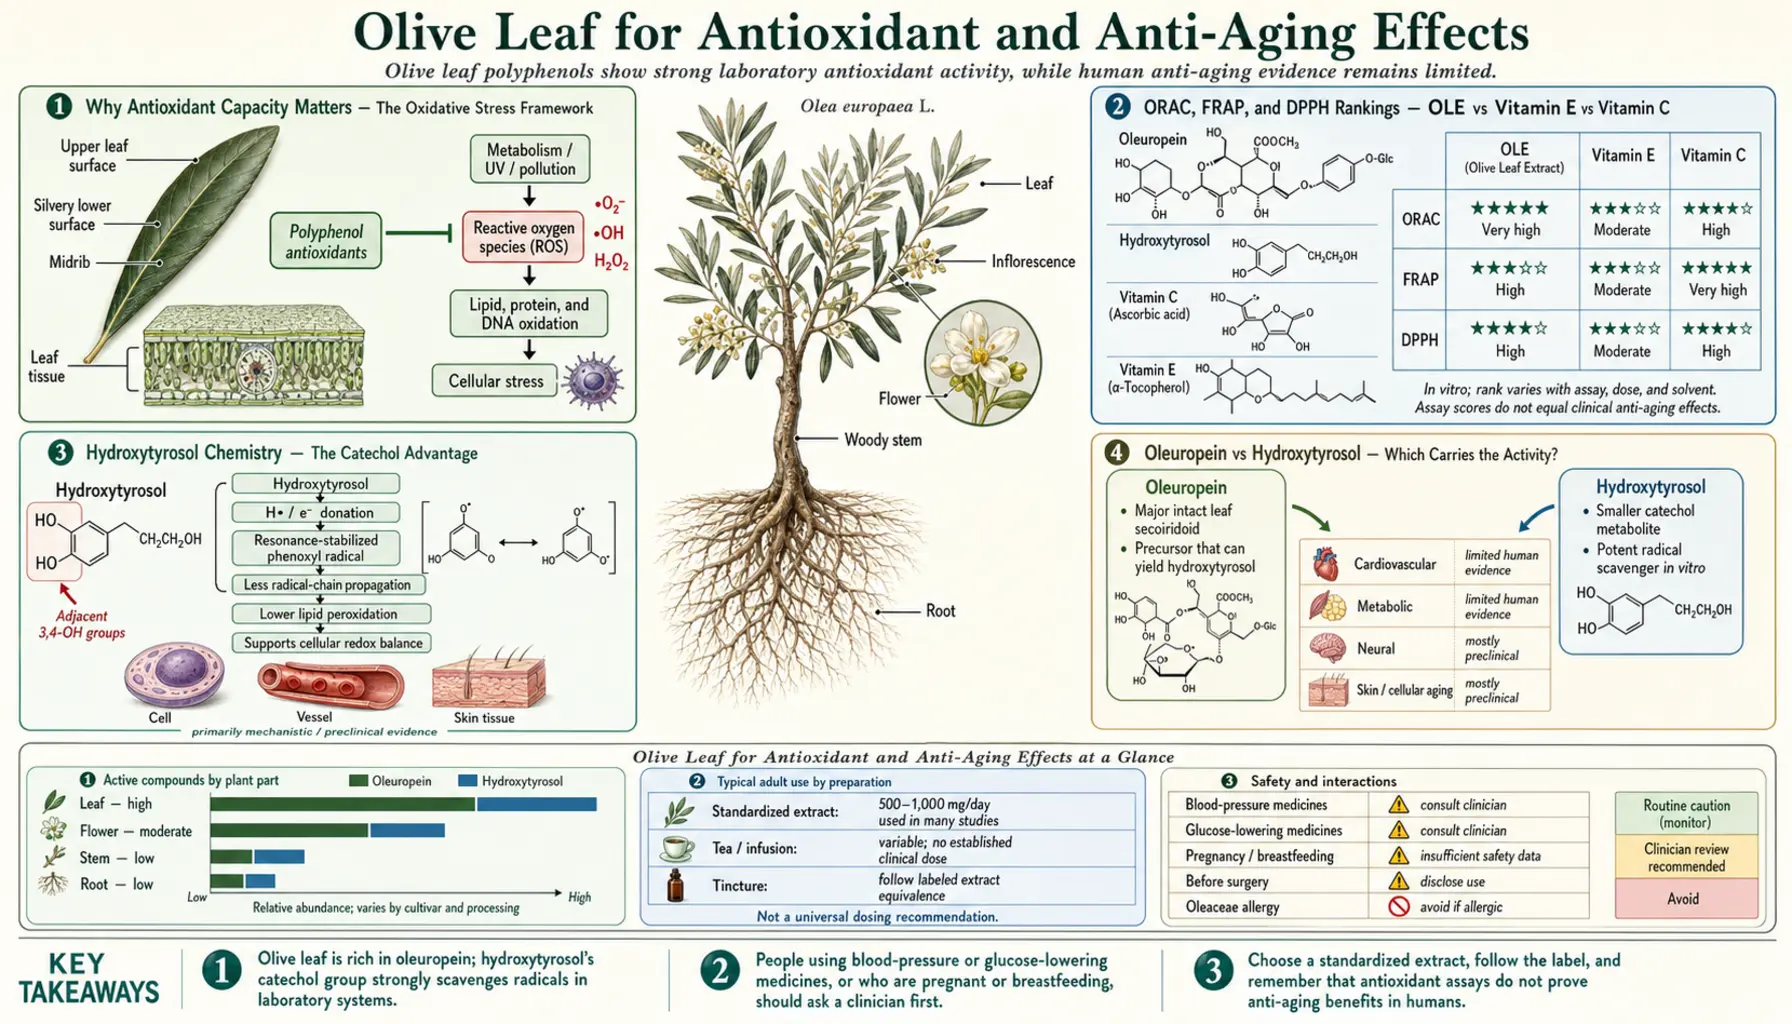
Among the polyphenols of the olive tree, oleuropein and hydroxytyrosol are consistently ranked as the two most potent antioxidants — outperforming alpha-tocopherol (Vitamin E), ascorbic acid (Vitamin C), and even most flavonoids on standard in vitro assays such as ORAC, FRAP, and DPPH radical scavenging. Hydroxytyrosol in particular has an unusual molecular structure (an ortho-dihydroxyphenyl group attached to an ethanol arm) that allows it to donate two hydrogens to neutralize peroxyl and hydroxyl radicals while forming a stable, non-reactive ortho-quinone product — a chemistry shared with catechol-class molecules but rare among dietary polyphenols. This deep-dive walks through the comparative antioxidant ranking, the mitochondrial protection mechanism (membrane stabilization, reduced cytochrome c release, attenuated apoptosis under oxidative stress), the difference between olive leaf and extra-virgin olive oil polyphenol content for antioxidant purposes, and what is and is not known about aging markers including telomere length, mitochondrial bioenergetics, and skin photoaging.
Table of Contents
- Why Antioxidant Capacity Matters — The Oxidative Stress Framework
- ORAC, FRAP, and DPPH Rankings — OLE vs Vitamin E vs Vitamin C
- Hydroxytyrosol Chemistry — The Catechol Advantage
- How Oleuropein and Hydroxytyrosol Share the Activity
- Mitochondrial Protection and Bioenergetics
- The Nrf2 / Phase II Pathway and Endogenous Antioxidant Upregulation
- Leaf vs Extra-Virgin Olive Oil — Antioxidant Delivery
- Aging Biomarkers (Telomere Length, Mitochondrial Function, Skin)
- Brain Aging and Neuroprotection
- Dosing and Antioxidant Stacking
- What Human Trials of Olive Leaf Extract Have Found
- Key Research Papers
- Connections
- Featured Videos
Why Antioxidant Capacity Matters — The Oxidative Stress Framework
Aerobic metabolism is fundamentally a controlled fire. Mitochondria reduce molecular oxygen to water through the electron transport chain, with the energy released captured as adenosine triphosphate (ATP). The reduction is not perfectly clean — approximately 0.5-2% of electrons leak prematurely from complexes I and III and form superoxide anion (O2-) and other reactive oxygen species (ROS). These reactive oxygen species are signal molecules at low concentration (they participate in immune defense, hormetic stress responses, and redox-sensitive transcription factor regulation) but damaging at higher concentration. They oxidize membrane lipids, denature proteins, and mutate DNA.
The body maintains a complex antioxidant defense system to handle the inevitable reactive oxygen species production:
- Endogenous enzymes — superoxide dismutase (SOD), catalase, glutathione peroxidase, glutathione reductase, thioredoxin, peroxiredoxins
- Endogenous small molecules — reduced glutathione (GSH), ubiquinol (CoQ10H2), uric acid, bilirubin
- Dietary antioxidants — ascorbic acid (Vitamin C), alpha-tocopherol (Vitamin E), beta-carotene and other carotenoids, polyphenols (including oleuropein and hydroxytyrosol), selenium-containing compounds
Oxidative stress — the imbalance where reactive oxygen species production exceeds antioxidant capacity — is the leading mechanistic candidate for many age-related diseases including cardiovascular disease, neurodegeneration, cancer, diabetes complications, and skin photoaging. Whether reducing oxidative stress through dietary or supplemental antioxidants actually slows aging or reduces disease has been the subject of decades of mixed evidence; large randomized trials of isolated antioxidant supplements (the Alpha-Tocopherol, Beta-Carotene Cancer Prevention (ATBC) Study, the Beta-Carotene and Retinol Efficacy Trial (CARET), and the Selenium and Vitamin E Cancer Prevention Trial (SELECT)) have been disappointing or even harmful. The current consensus is that polyphenol-rich whole-food approaches (Mediterranean diet, leafy greens, berries) outperform isolated antioxidant pills, possibly because of synergistic effects and because polyphenols additionally upregulate the body's endogenous antioxidant machinery rather than passively donating an electron and being depleted.
This last mechanism is where olive leaf extract (OLE) distinguishes itself.
ORAC, FRAP, and DPPH Rankings — OLE vs Vitamin E vs Vitamin C
Three standard in vitro assays of antioxidant capacity:
- Oxygen Radical Absorbance Capacity (ORAC) — measures hydrogen-atom-transfer to peroxyl radical, with Trolox (a water-soluble Vitamin E analog) as reference
- FRAP (Ferric Reducing Antioxidant Power) — measures single-electron-transfer to ferric ion, with ascorbic acid as reference
- DPPH (1,1-diphenyl-2-picrylhydrazyl) radical scavenging — measures direct radical quenching capacity in alcoholic solution
Relative antioxidant capacities of the major dietary antioxidants, normalized to Trolox-equivalents per micromole (Trolox itself, the reference compound, is 1.0 by definition):
- Hydroxytyrosol: 3.0-4.5× Trolox
- Oleuropein: 2.5-3.5× Trolox
- Quercetin: 2.5-3.0× Trolox
- Epigallocatechin gallate (EGCG, green tea): 2.0-3.5× Trolox
- Resveratrol: 2.0× Trolox
- Ascorbic acid (Vitamin C): 1.0-1.2× Trolox
- Alpha-tocopherol (Vitamin E): 1.0× Trolox
- Beta-carotene: 0.5-0.8× Trolox (lipid-phase-specific; performs differently in different assays)
Hydroxytyrosol consistently lands in the top tier of dietary antioxidants — three to four times more potent per mole than Vitamin E in standard radical-quenching assays. The European Union's authorised health claim for olive polyphenols, based on a 2011 European Food Safety Authority (EFSA) opinion on protection of low-density lipoprotein (LDL) particles from oxidative damage, rests on people eating olive oil rather than on this test-tube potency: it reads “Olive oil polyphenols contribute to the protection of blood lipids from oxidative stress” and covers olive oil, not olive leaf extract.
One caveat: in vitro oxygen radical absorbance capacity and FRAP rankings do not always translate to in vivo antioxidant capacity because bioavailability, tissue distribution, and metabolism all differ between compounds. Hydroxytyrosol's bioavailability after oral OLE ingestion is reasonably good (the glucoside ester forms are deconjugated in the gut), supporting clinical translation of the in vitro potency.
Hydroxytyrosol Chemistry — The Catechol Advantage
Hydroxytyrosol's structure is 3,4-dihydroxyphenylethanol — a benzene ring with two adjacent hydroxyl groups (the catechol moiety) and an ethanol side chain. This ortho-dihydroxyl catechol substructure is also found in epinephrine, dopamine, and several other endogenous and dietary catechol compounds, and it is the structural reason for the high antioxidant potency.
The chemistry of radical quenching:
- A free radical (reactive oxygen species) abstracts a hydrogen atom from one of the catechol hydroxyl groups, forming a phenoxyl radical on hydroxytyrosol
- The phenoxyl radical is stabilized by resonance delocalization across the aromatic ring — this is what makes the molecule a "good" antioxidant; the intermediate radical is not itself reactive enough to propagate damage
- A second free radical abstracts the second hydroxyl hydrogen, converting the catechol to an ortho-quinone (a fully oxidized stable form)
- The ortho-quinone product is not a free radical and does not propagate oxidative damage
This two-electron antioxidant capacity is the key advantage over single-hydroxyl antioxidants like Vitamin E (tocopherol has one phenolic hydroxyl). One molecule of hydroxytyrosol can neutralize two radical molecules; one molecule of Vitamin E can typically neutralize one (and then must be regenerated by Vitamin C or another reductant before it can quench another radical).
Catechol antioxidants do have one liability: the ortho-quinone product can be reactive under some conditions (it can form Michael adducts with cellular nucleophiles, including glutathione, cysteine residues in proteins, and DNA bases). At physiologic doses this is not a concern because the body has efficient pathways for ortho-quinone disposal (catechol-O-methyltransferase, and NAD(P)H:quinone oxidoreductase 1 (NQO1), where NAD(P)H stands for reduced nicotinamide adenine dinucleotide (phosphate)). At pharmacologic doses far beyond what OLE delivers, this could theoretically matter; in practice it has not been a clinical concern in OLE trials.
How Oleuropein and Hydroxytyrosol Share the Activity
Oleuropein is the larger parent molecule and is the dominant phenolic in olive leaf extract by mass. Hydroxytyrosol is the smaller hydrolysis product released when oleuropein is broken down by host or microbial enzymes. The biological activity is divided between them in a context-dependent way:
- In vitro radical quenching — both have high activity; hydroxytyrosol slightly higher on a molar basis
- Direct antimicrobial activity — oleuropein and elenolic acid (also released by hydrolysis) carry most of this activity
- Angiotensin-converting enzyme (ACE) inhibition — oleuropein appears slightly more potent in vitro
- Endothelial nitric oxide (NO) upregulation — hydroxytyrosol appears slightly more potent
- Nrf2 / phase II enzyme induction — hydroxytyrosol is the active species
- Mitochondrial protection — hydroxytyrosol is the active species
- Low-density lipoprotein oxidation protection — both contribute; the EU health claim based on the EFSA opinion is anchored to hydroxytyrosol and its derivatives in olive oil
The practical implication is that OLE is essentially a hydroxytyrosol prodrug. Oleuropein delivered orally undergoes partial hydrolysis in the stomach and small intestine, releasing hydroxytyrosol that is then absorbed and reaches plasma. Some intact oleuropein also crosses the intestinal wall and contributes to plasma polyphenol activity, but much of the downstream biology is mediated by hydroxytyrosol.
As a point of comparison, an OLE product standardized to 18% oleuropein delivers approximately 90 mg oleuropein per 500 mg capsule, which translates to approximately 15-20 mg of hydroxytyrosol-equivalent activity after intestinal hydrolysis. This is roughly the same hydroxytyrosol exposure as 40-50 g of high-polyphenol extra-virgin olive oil.
Mitochondrial Protection and Bioenergetics
One of the most interesting modern findings about hydroxytyrosol is its specific affinity for the mitochondrial inner membrane. The molecule is small, amphipathic (water-soluble enough to dissolve in cytoplasm, lipid-soluble enough to partition into membranes), and accumulates preferentially in mitochondria after cellular uptake.
Inside the mitochondrion, hydroxytyrosol does several things relevant to aging and chronic disease:
- Quenches inner-membrane reactive oxygen species at the source — electrons leak from complex I and complex III of the electron transport chain to form superoxide. Hydroxytyrosol's membrane localization places it precisely where this leakage occurs, allowing direct quenching before the reactive oxygen species damages mitochondrial lipids (cardiolipin), proteins, or mitochondrial DNA (mtDNA).
- Stabilizes the mitochondrial membrane and prevents cytochrome c release — the apoptotic cascade in oxidative-stress-induced cell death depends on mitochondrial outer membrane permeabilization (MOMP) and cytochrome c release into the cytoplasm. Hydroxytyrosol stabilizes the membrane and attenuates this release, reducing apoptosis under stress conditions.
- Upregulates mitochondrial biogenesis — hydroxytyrosol activates peroxisome proliferator-activated receptor gamma coactivator 1-alpha (PGC-1alpha), the master transcriptional coactivator of mitochondrial biogenesis, increasing mitochondrial number and capacity. This is a similar mechanism to that of exercise and caloric restriction, two of the few interventions with strong evidence for extending healthspan.
- Supports cardiolipin integrity — cardiolipin is the signature phospholipid of the mitochondrial inner membrane, and oxidative damage to cardiolipin is an early step in many forms of mitochondrial dysfunction. Hydroxytyrosol's membrane antioxidant action protects cardiolipin specifically.
The clinical translation of mitochondrial protection is harder to measure than blood pressure, but the mechanism predicts benefit in conditions where mitochondrial dysfunction is central: type 2 diabetes, several neurodegenerative diseases, ischemia-reperfusion injury, certain chemotherapy-induced toxicities, and the general phenomenon of aging itself. Animal data support these predictions; human data are limited but emerging.
The Nrf2 / Phase II Pathway and Endogenous Antioxidant Upregulation
Beyond direct radical quenching, hydroxytyrosol activates the Nrf2 (nuclear factor erythroid 2-related factor 2) transcription factor pathway. Under basal conditions Nrf2 is held in the cytoplasm by its binding partner Keap1 (Kelch-like ECH-associated protein 1) and is constitutively ubiquitinated and degraded. When the cell encounters mild oxidative or electrophilic stress — or when hydroxytyrosol (a mild electrophile via its ortho-quinone intermediate) reaches the cell — Keap1 is modified and releases Nrf2, which translocates to the nucleus, binds the antioxidant response element (ARE) in promoter regions, and induces transcription of the phase II antioxidant gene battery:
- NAD(P)H:quinone oxidoreductase 1 (NQO1)
- Heme oxygenase-1 (HO-1)
- Glutathione S-transferases (GSTs)
- Glutamate-cysteine ligase (rate-limiting for glutathione synthesis)
- Thioredoxin and thioredoxin reductase
- Glutathione peroxidase
The direct evidence for this step cited on this page comes from a laboratory study of human liver cancer cells (HepG2) grown in a dish: hydroxytyrosol raised the expression and activity of glutathione peroxidase, glutathione reductase and glutathione S-transferase, moved Nrf2 into the cell nucleus, and protected the cells against an oxidizing chemical (Martín 2010). Whether an olive leaf capsule does the same inside a person is not known.
This mechanism is the "hormetic" antioxidant effect: a mild pro-oxidant stimulus triggers the cell to upregulate its own much larger endogenous antioxidant capacity. The result is sustained antioxidant capacity that outlasts the initial polyphenol stimulus. The same Nrf2-activating mechanism is shared with sulforaphane from broccoli, curcumin from turmeric, epigallocatechin gallate from green tea, and many other dietary polyphenols.
This is the leading hypothesis for why the Mediterranean diet polyphenol package (including OLE's contribution) produces durable cardiovascular and metabolic benefits, while isolated single-antioxidant supplements (high-dose Vitamin E, beta-carotene) have largely failed in trials. The polyphenols are not just radical quenchers; they are signal molecules that upregulate the body's own antioxidant machinery.
Leaf vs Extra-Virgin Olive Oil — Antioxidant Delivery
From an antioxidant-delivery perspective, olive leaf extract and extra-virgin olive oil have complementary roles:
Extra-virgin olive oil (EVOO):
- Modest hydroxytyrosol content (0.5-15 mg per 20 g serving for highest-quality fresh EVOO)
- Polyphenol content is lipid-phase-delivered, which favors uptake into chylomicrons and incorporation into membranes
- Additionally provides monounsaturated fat (oleic acid) with independent metabolic benefits
- Realistically delivered as a 1-2 tablespoon serving (15-30 mL) several times daily, giving cumulative polyphenol delivery in a hormetic-dose range
Olive leaf extract (OLE):
- Concentrated oleuropein delivery (90+ mg per 500 mg capsule of properly standardized product)
- Allows pharmaceutical-comparable dosing without caloric burden
- Bioavailability of the released hydroxytyrosol is good
- Appropriate when targeting a specific clinical effect (blood pressure (BP) reduction, prophylaxis, antimicrobial use)
The European Union allows its olive-polyphenol health claim only for olive oil that contains at least 5 mg of hydroxytyrosol and its derivatives (such as the oleuropein complex and tyrosol) per 20 g of olive oil, and the label has to say that the effect is obtained with a daily intake of 20 g of olive oil. The claim does not cover olive leaf extract capsules.
A combined approach pairs EVOO in cooking and on salads (1-3 tablespoons daily) with an OLE capsule when there is a specific clinical target; the 2025 trial in postmenopausal women described below used 250 mg of OLE a day. The reasoning given for combining them is that OLE's capsule form delivers polyphenols in a different absorption matrix than EVOO does, and that the cumulative hydroxytyrosol exposure is what drives Nrf2 activation and the durable antioxidant response.
Aging Biomarkers (Telomere Length, Mitochondrial Function, Skin)
Direct human evidence that OLE slows biological aging is limited but suggestive across several markers:
- Skin photoaging — topical hydroxytyrosol formulations reduce ultraviolet-induced oxidative damage, MMP-1 (collagenase) activity, and wrinkle formation in human and animal studies. Oral OLE's contribution to skin aging is mechanistically plausible (skin polyphenol accumulation from blood) but not as well-quantified.
- Mitochondrial bioenergetics — the mitochondrial findings for hydroxytyrosol come from animal and cell studies: in diabetic db/db mice, 8 weeks of hydroxytyrosol at 10 and 50 mg/kg raised the levels of mitochondrial respiratory chain complexes I, II and IV in the brain (Zheng 2015). A benefit to mitochondrial function in people taking OLE is not established. The mouse result is consistent with the PGC-1alpha activation discussed above.
- Telomere length and telomerase — preliminary evidence (mostly in vitro and in animal models) suggests that polyphenol-rich Mediterranean dietary patterns are associated with longer leukocyte telomeres. Hydroxytyrosol specifically has been shown to activate telomerase in some cell models. Whether OLE-driven changes in telomere biology translate to extended healthspan in humans is open.
- Hepatic steatosis (fatty liver) regression — OLE reduces hepatic triglyceride accumulation in animal models of diet-induced non-alcoholic fatty liver disease (NAFLD), and the limited human data are consistent. Fatty liver is increasingly considered a biomarker of metabolic aging.
- Glycation and AGE formation — hydroxytyrosol inhibits the non-enzymatic glycation of proteins and reduces advanced glycation end-product (AGE) formation. AGE accumulation drives much of the visible and functional decline of skin, connective tissue, and vascular wall with aging.
- A 2025 placebo-controlled trial in postmenopausal women — 65 healthy women aged 45-70 took 250 mg OLE or a dummy pill daily for 12 weeks. Blood markers of tissue aging (elastin, collagen, hydroxyproline, matrix metalloproteinase-2, and pentosidine, a glycation end-product) and fasting glucose showed no statistically significant change once the results were corrected for multiple testing. In a small skin subgroup (26 women), the number of skin pores fell in the OLE group between weeks 6 and 12 and was lower than with placebo at week 12 (Lasfar 2025).
The honest framing: OLE is not a "longevity drug" with rigorous human evidence. It is a polyphenol package with mechanistic alignment to several established aging pathways and with safety adequate for long-term use. Where OLE is used for healthy aging, it sits alongside other evidence-aligned interventions (Mediterranean diet, regular aerobic and resistance exercise, sleep optimization, social engagement) and is not expected to be the single dominant factor.
Brain Aging and Neuroprotection
Brain tissue is particularly vulnerable to oxidative damage for three reasons: it has high metabolic activity (and therefore high reactive oxygen species generation), it is rich in oxidation-vulnerable polyunsaturated fatty acids in neuronal membranes, and it has relatively low endogenous antioxidant capacity compared to liver. Many neurodegenerative conditions involve oxidative stress as either a primary driver or a downstream amplifier of the underlying pathology.
Hydroxytyrosol crosses the blood-brain barrier and accumulates in brain tissue at meaningful concentrations, particularly in cortical and hippocampal regions. Animal studies (in laboratory rodents, not people) show:
- Reduced beta-amyloid aggregation and improved cognitive function in mouse models of Alzheimer's-like disease
- Improved brain mitochondrial function in diabetic db/db mice: 8 weeks of hydroxytyrosol at 10 and 50 mg/kg raised mitochondrial respiratory chain complexes and complex I activity and lowered protein oxidation, apparently through activation of AMP-activated protein kinase (Zheng 2015)
- Reduced dopaminergic neuron loss in parkinsonism models induced by the toxin MPTP (1-methyl-4-phenyl-1,2,3,6-tetrahydropyridine)
- Reduced ischemia-reperfusion damage after experimental stroke
- Preserved hippocampal long-term potentiation (LTP) and spatial memory in chronic cerebral hypoperfusion models
Human data for neuroprotection from OLE specifically is limited. The Mediterranean diet pattern (which includes substantial dietary olive polyphenols) has been associated with reduced incidence of Alzheimer's disease and mild cognitive impairment in multiple cohort studies (Scarmeas, Singh meta-analysis), but attributing the effect specifically to olive polyphenols vs the broader dietary package is difficult. The Scarmeas 2006 study, for example, followed 2,258 people in New York and measured adherence to the whole Mediterranean diet, not olive leaf extract: those in the highest third of adherence had a hazard ratio for Alzheimer's disease of 0.60 compared with the lowest third.
When OLE is discussed for cognitive aging, including by people with a strong family history of neurodegenerative disease, it is as one part of a wider pattern that also includes a Mediterranean-pattern diet, regular aerobic exercise, social and cognitive engagement, and treatment of modifiable cardiovascular risk factors; no dose for this use has been established in human trials. See our Neurology page for the broader cognitive aging discussion.
Dosing and Antioxidant Stacking
- Doses described: 500 mg OLE standardized to 18-20% oleuropein, once or twice daily, is the dose often described for antioxidant use; the 2025 trial in postmenopausal women used 250 mg OLE a day for 12 weeks (Lasfar 2025)
- Stacking with other polyphenols: OLE is sometimes combined with resveratrol, curcumin, green tea epigallocatechin gallate, and quercetin for a "polyphenol package" effect. The Nrf2-activating mechanism is shared, and additive activation has been demonstrated in cell models.
- Stacking with established antioxidants: Vitamin C, Vitamin E, alpha-lipoic acid, and selenium are sometimes taken alongside OLE for broad antioxidant support. No documented adverse interactions.
- Stacking with mitochondrial supports: coenzyme Q10 (CoQ10) (ubiquinol), pyrroloquinoline quinone (PQQ), and creatine address related mitochondrial bioenergetic pathways.
- Timing: with meals improves polyphenol absorption (food fat aids uptake). Splitting the dose (morning and evening) provides more constant plasma levels than single dosing.
One caveat about high-dose isolated antioxidant supplementation worth repeating: the ATBC and CARET trials showed that high-dose isolated beta-carotene increased lung cancer risk in smokers, and the SELECT trial showed that high-dose Vitamin E supplementation slightly increased prostate cancer risk. These cautions do not appear to apply to OLE at commonly used doses, but they do underscore the principle that "more antioxidant" is not always better and that isolated single-compound megadosing can disrupt physiologic reactive oxygen species signaling. OLE at the commonly used 500-1,000 mg/day range is well-tolerated and has not shown any signal of paradoxical harm in long-term users.
What Human Trials of Olive Leaf Extract Have Found
A 2026 systematic review and meta-analysis gathered 11 randomized controlled trials in adults that compared olive leaf extract or oleuropein with a placebo or control: 4 short-term and 7 continuous-intake trials. The short-term crossover studies gave mixed results on blood sugar and insulin after meals, too varied to pool. In the longer, parallel-group trials, the pooled results showed no statistically or clinically significant effect on blood sugar (glycemic) or blood fat (lipid) measures. Evidence on markers of inflammation was scarce and of low certainty. The authors concluded that the current evidence does not support clinical recommendations for OLE supplementation aimed at health benefits, and that further high-quality trials are needed (Câmara Rocha Menezes 2026).
The 2025 trial in postmenopausal women described under aging biomarkers likewise found no statistically significant change in blood markers of tissue aging after correction for multiple testing, with an exploratory drop in skin pore number in a small subgroup (Lasfar 2025).
Key Research Papers
- Visioli F, Romani A, Mulinacci N, Zarini S, Conte D, Vincieri FF, Galli C (1999). Antioxidant and other biological activities of olive mill waste waters. Journal of Agricultural and Food Chemistry. — PubMed PMID: 10552663
- Tuck KL, Hayball PJ (2002). Major phenolic compounds in olive oil: metabolism and health effects. Journal of Nutritional Biochemistry. — PubMed PMID: 12550060
- Covas MI et al. (2006). The effect of polyphenols in olive oil on heart disease risk factors: a randomized trial. Annals of Internal Medicine. — PubMed
- EFSA Panel on Dietetic Products, Nutrition and Allergies (2011). Scientific Opinion on the substantiation of health claims related to polyphenols in olive and protection of LDL particles from oxidative damage. EFSA Journal. — doi:10.2903/j.efsa.2011.2033
- European Commission (2012). Commission Regulation (EU) No 432/2012 of 16 May 2012 establishing a list of permitted health claims made on foods, other than those referring to the reduction of disease risk and to children's development and health (Annex: olive oil polyphenols). — Regulation (EU) No 432/2012, Annex
- Martín MA, Ramos S, Granado-Serrano AB, Rodríguez-Ramiro I, Trujillo M, Bravo L, Goya L (2010). Hydroxytyrosol induces antioxidant/detoxificant enzymes and Nrf2 translocation via extracellular regulated kinases and phosphatidylinositol-3-kinase/protein kinase B pathways in HepG2 cells. Molecular Nutrition & Food Research. — PubMed PMID: 20166143
- Hagiwara K et al. (2011). Olive polyphenol hydroxytyrosol prevents bone loss. European Journal of Pharmacology. — PubMed PMID: 21539839
- Zheng A et al. (2015). Hydroxytyrosol improves mitochondrial function and reduces oxidative stress in the brain of db/db mice: role of AMP-activated protein kinase activation. British Journal of Nutrition. — PubMed PMID: 25885653
- Bertelli M et al. (2020). Hydroxytyrosol: a natural compound with promising pharmacological activities. Journal of Biotechnology. — PubMed PMID: 31884046
- Robles-Almazan M et al. (2018). Hydroxytyrosol: bioavailability, toxicity, and clinical applications. Food Research International. — PubMed PMID: 29433260
- Bulotta S et al. (2014). Beneficial effects of the olive oil phenolic components oleuropein and hydroxytyrosol: focus on protection against cardiovascular and metabolic diseases. Journal of Translational Medicine. — PubMed PMID: 25086598
- Scarmeas N et al. (2006). Mediterranean diet and risk for Alzheimer's disease. Annals of Neurology. — PubMed PMID: 16622828
- Pantano D et al. (2017). Oleuropein aglycone and polyphenols from olive mill waste water ameliorate cognitive deficits and neuropathology. British Journal of Clinical Pharmacology. — PubMed PMID: 27131215
- Lasfar A, van Stratum SLM, Imperatrice M, van Kalkeren CAJ, Scheijen JLJM, Schalkwijk CG, La Torre D, Troost FJ (2025). Effects of olive leaf extract supplementation on systemic markers of tissue aging and remodeling in postmenopausal women: a randomized controlled trial with exploratory skin outcomes. Frontiers in Nutrition. — PubMed PMID: 41340653
- Câmara Rocha Menezes R, Peres KK, da Mata IR, Morelo Dal Bosco S, Garavaglia J, Dallegrave E (2026). Metabolic and inflammatory effects of oleuropein and olive leaf extract: a systematic review and meta-analysis. Food & Function. — PubMed PMID: 41848522
PubMed Topic Searches
Connections
- All Herbs
- Olive Leaf Benefits Hub
- Olive Leaf Overview
- OLE Cardiovascular
- OLE Antimicrobial
- OLE Blood Sugar
- Olive Oil
- Vitamin C
- Vitamin E
- Resveratrol
- Curcumin
- Quercetin
- Green Tea
- Neurology
- Cardiology
- Hydroxytyrosol — the oleuropein metabolite that carries the Nrf2 induction and mitochondrial protection described on this page.
- History