⚠ Evidence warning: Clinical trials or other evidence do not support the claims that pediatric acute-onset neuropsychiatric syndrome (PANS/PANDAS) rates are elevated in Ehlers-Danlos syndrome and that the teen flare is usually partly reversible once growth slows. This page keeps it as a report of what people, websites or other media say.
Pediatric Ehlers-Danlos Syndrome (EDS) and Transition of Care
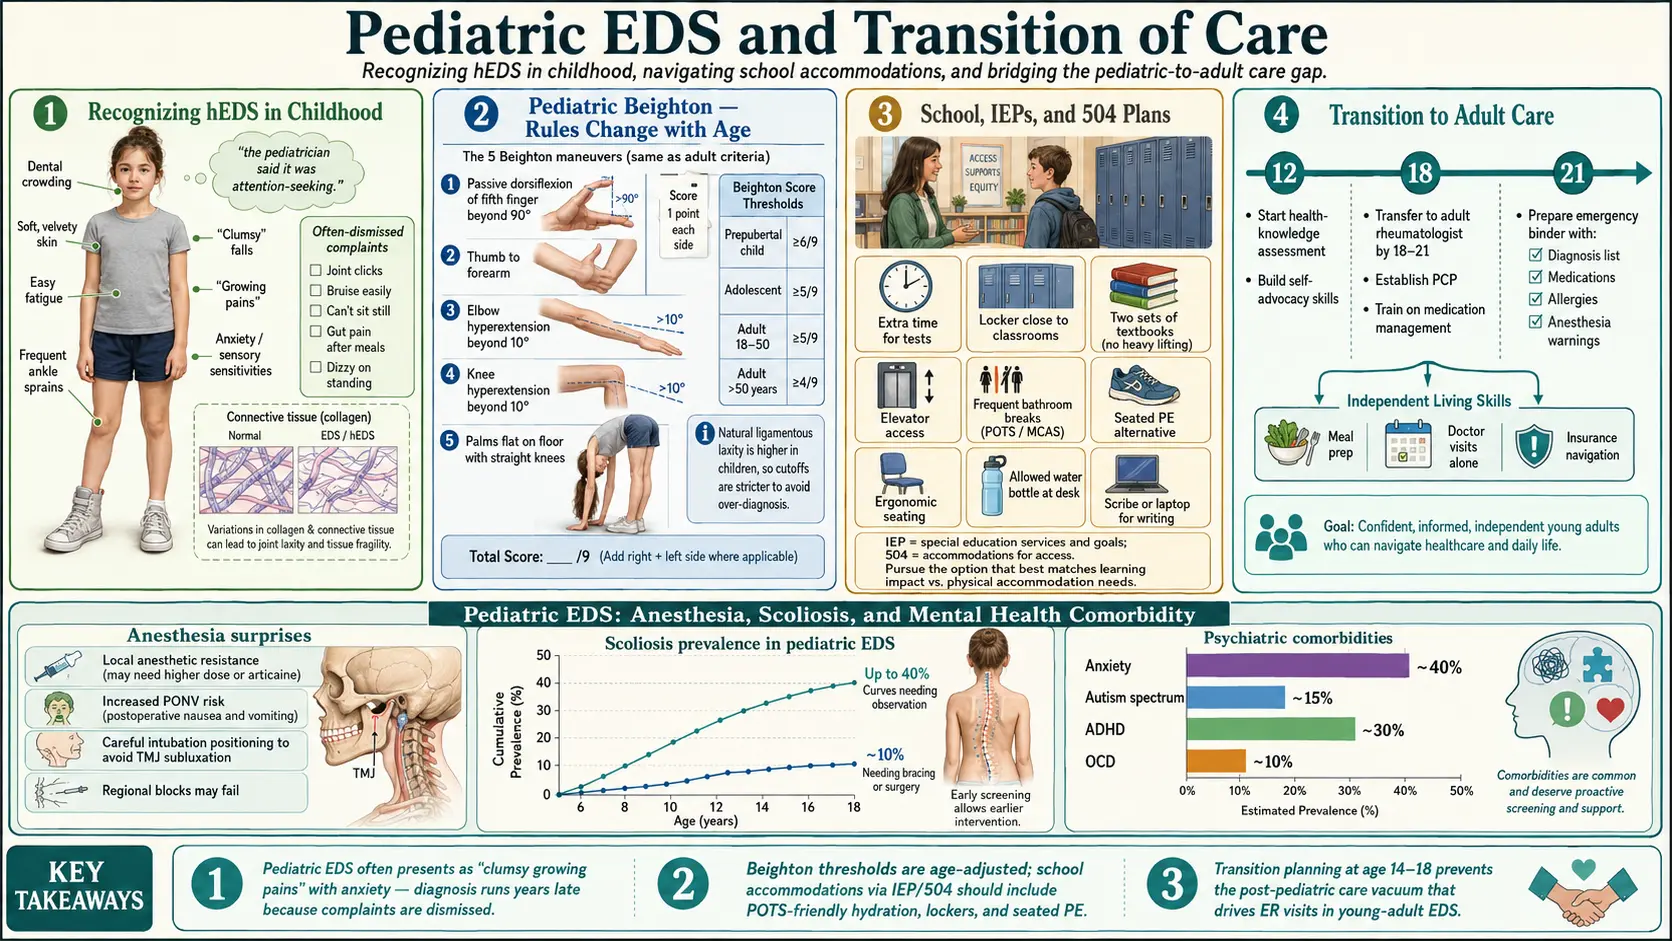
Table of Contents
- Recognizing Hypermobile Ehlers-Danlos Syndrome in Childhood and Adolescence
- Common Complaints That Get Dismissed
- Pediatric Beighton — Why the Rules Change with Age
- Establishing the Diagnosis in a Child
- Anesthesia, Dental, and Surgical Surprises
- Scoliosis Screening
- School, IEPs, and 504 Plans
- Growth Spurts and the Teen Flare
- Mental Health and Neurodevelopmental Overlap
- Managing a Pediatric Ehlers-Danlos Syndrome Family
- The Transition to Adult Care
- Independent Living Skills
- College, Sports, and Career Planning
- Emergency Preparedness
- Key Research Papers
- Connections
- Featured Videos
Recognizing Hypermobile Ehlers-Danlos Syndrome in Childhood and Adolescence
For decades pediatricians have used the phrase "benign joint hypermobility of childhood" to reassure parents that a bendy toddler will grow out of it. Many do. A meaningful minority do not — they grow into teenagers with hypermobile Ehlers-Danlos syndrome and the full constellation of pain, fatigue, dysautonomia, and gastrointestinal (GI) symptoms that goes with it. The word "benign" can delay a useful diagnosis by ten or fifteen years.
Early clues, often overlooked, include:
- Delayed motor milestones. Late walkers (after 15 months), children who skip crawling, toddlers who tire quickly on playgrounds.
- W-sitting. Sitting on the floor with legs folded behind in a W shape. Comfortable for hypermobile hips because the joints splay passively instead of requiring muscular support.
- "Floppy" posture. Slumping into chairs, draping over furniture, leaning against walls while standing in line.
- Frequent sprains and subluxations. Ankles that "roll" repeatedly, shoulders that pop out during routine play, fingers that bend backward alarmingly.
- "Growing pains" at night that do not resolve. Real growing pains fade by age 10-12. Ehlers-Danlos syndrome (EDS) pain intensifies through puberty.
- Flat feet and persistent toe-walking. Arches that collapse under weight; tippy-toe walking that continues past age 3 despite typical development otherwise.
- Poor handwriting. Grip instability makes the pencil wobble; fine-motor fatigue comes quickly and looks like laziness.
- Fatigue out of proportion to activity. A twenty-minute grocery run followed by a two-hour nap.
None of these is diagnostic alone. Taken together in a child with hypermobile joints and a family history of "clumsy," "bendy," or chronically painful relatives, they warrant a formal evaluation.
Common Complaints That Get Dismissed
Before a child with hypermobile Ehlers-Danlos syndrome gets an accurate diagnosis, their symptoms are often reframed as behavioral or psychological. Parents hear, in sequence, some combination of: growing pains, conversion disorder, school avoidance, anxiety, malingering, Munchausen by proxy. This is not because individual clinicians are cruel. It is because the symptom pattern — multi-system, fluctuating, invisible on routine imaging, worse on days with a social trigger — looks exactly like a somatic presentation to someone who does not know Ehlers-Danlos syndrome exists.
Families describe keeping a written symptom log with dates, photographing subluxations, bruises, and skin findings, bringing the same parent to every visit, and asking for every recommendation and differential to be written in the chart. This is not adversarial; it is how a medical record gets built that survives being handed off to the next provider who will read the last five lines and form an opinion in thirty seconds.
Pediatric Beighton — Why the Rules Change with Age
The Beighton score is the standard bedside measure of joint hypermobility: nine points awarded for specific maneuvers (fifth-finger hyperextension, thumb-to-forearm, elbow and knee hyperextension, palms-to-floor). In adults, five of nine signals generalized hypermobility. In children, the same score means much less.
Young children are naturally bendy. Their collagen is still maturing, and normal preschoolers routinely score 7 or 8 of 9. As the child grows, ligaments stiffen. The cutoff for "abnormal" hypermobility therefore has to tighten with age:
- Prepubertal children (up to about age 12): six or more of nine.
- Postpubertal adolescents and adults: five or more of nine.
- Adults over 50: four or more of nine (collagen continues to stiffen with age).
The Bulbena scale is an alternative developed in Spain. Its 1992 authors built it from patients at a rheumatology outpatient clinic in Barcelona, for screening studies and rheumatology clinics; that report says nothing about children, and the 2023 pediatric working group notes that criteria developed for adults are hard to use in children. It uses ten signs, some of which (passive dorsiflexion of the foot, hip external rotation) some clinicians describe as easier to elicit in a squirming four-year-old than the adult Beighton maneuvers. Clinicians use either tool, and a specific score in the chart says more than just "hypermobile" or "not hypermobile."
Establishing the Diagnosis in a Child
Since 2023 an international pediatric framework sorts hypermobile children by four things: joint score (Beighton 6 of 9 or more), skin and tissue changes, muscle and joint complications, and core related conditions. This gives 8 subgroups: 4 of pediatric generalized joint hypermobility and 4 of pediatric generalized hypermobility spectrum disorders. The label hypermobile Ehlers-Danlos syndrome is reserved for biologically mature adolescents who meet the 2017 criteria; the rarer Ehlers-Danlos types may be diagnosed at any age.
Before that framework, a working hypermobile Ehlers-Danlos syndrome diagnosis in a child usually took three elements, and clinicians still draw on them:
- Age-adjusted Beighton or Bulbena in the hypermobile range.
- Symptoms consistent with the condition — chronic pain in multiple joints, repeated sprains or subluxations, fatigue, skin that feels soft or stretchy, a family history of similar problems.
- Exclusion of other heritable connective-tissue disorders — most importantly Marfan syndrome, Loeys-Dietz syndrome, and the rarer Ehlers-Danlos syndrome subtypes (classical, vascular, kyphoscoliotic). This is the job of a pediatric geneticist.
Families describe a pediatric geneticist referral as the single most valuable visit. The geneticist will take a detailed family history, examine skin extensibility and scarring, measure arm-span-to-height ratio, inspect palate and teeth, and — crucially — decide whether genetic testing is indicated. Most children with suspected hypermobile Ehlers-Danlos syndrome do not need a DNA test, because no gene has been consistently linked to hypermobile Ehlers-Danlos syndrome. Genetic testing is indicated when:
- Skin shows classical-EDS features: fish-mouth scars on knees and elbows, doughy feel, marked stretchiness → test for COL5A1, COL5A2.
- Family history includes arterial aneurysm, arterial rupture, bowel perforation, or sudden death in a young relative → test for COL3A1 (vascular Ehlers-Danlos syndrome). Vascular disease is the reason clinicians regard this test as essential when the family history fits.
- Severe early-onset scoliosis with thin blue sclerae → test for PLOD1 (kyphoscoliotic Ehlers-Danlos syndrome).
- Marfan-like body habitus → test for FBN1 and the Loeys-Dietz gene panel.
A negative panel does not rule out hypermobile Ehlers-Danlos syndrome; it rules out the subtypes you would not want to miss.
Anesthesia, Dental, and Surgical Surprises
Children with Ehlers-Danlos syndrome come up against the healthcare system most often for routine things — tonsillectomies, ear tubes, dental work, broken arms — and that is exactly where unexpected complications show up. Two patterns recur:
- Local anesthetic failure. Lidocaine for a dental cavity or a laceration repair sometimes wears off in ten minutes, or never fully numbs the area. The child is labeled dramatic. The failure is real: a 2026 study tested lidocaine injected into the forearm skin of 135 people (91 with Ehlers-Danlos syndrome, 44 healthy). At 5 minutes there was no difference; at 15 minutes 60% vs 84% were still numb, and at 30 minutes 53% vs 80%, which fits numbing that wears off early. The abstract gives no ages, so it may not apply directly to children. Some propose that Ehlers-Danlos syndrome tissue metabolizes or distributes local agents differently, but the cause is not known, and many families describe the same pattern across generations. Options families raise in advance are a larger volume, longer-acting agents (bupivacaine), or a regional block if the procedure warrants it.
- Prolonged bleeding and bruising. Platelet counts are usually normal, but capillary fragility and connective-tissue laxity cause extended oozing and impressive bruises after minor procedures, so this history matters to a surgeon beforehand. Some practitioners describe pre-op screening for von Willebrand disease, on the view that it is overrepresented in Ehlers-Danlos syndrome cohorts. In a study of 141 patients, von Willebrand tests and platelet counts were normal in all. There, 41.7% had an abnormal bleeding score, and platelet function abnormalities tracked bleeding risk (odds ratio 5.19 with more than three abnormalities).
Dental issues are their own chapter. Expect: a high-arched palate, crowding that often requires orthodontics, delayed or ectopic tooth eruption, gum recession, and fragile oral tissue that tears on routine suction. Families describe looking for a pediatric dentist who has seen Ehlers-Danlos syndrome before and is willing to work slowly.
Scoliosis Screening
Scoliosis is more common in hypermobile Ehlers-Danlos syndrome and much more common in kyphoscoliotic Ehlers-Danlos syndrome. Clinicians who follow these children describe a spinal exam at each well-child visit through adolescence, with an Adams forward-bend test and a scoliometer reading when curvature is suspected. Curves that progress rapidly during a growth spurt are referred promptly to pediatric orthopedics; bracing is most effective when started early in a skeletally immature spine. Scoliosis in an Ehlers-Danlos syndrome child is also a reason for the geneticist to revisit the differential — severe early scoliosis shifts the probability toward kyphoscoliotic Ehlers-Danlos syndrome or a Marfan-spectrum diagnosis.
School, IEPs, and 504 Plans
School is where chronic illness meets bureaucracy. Two legal tools exist in the United States:
- An IEP (Individualized Education Program), under the federal Individuals with Disabilities Education Act (IDEA), applies when the medical condition interferes with learning and specialized instruction is needed.
- A 504 Plan, under the Rehabilitation Act, applies when a student needs accommodations to access a regular curriculum — this is the usual route for Ehlers-Danlos syndrome families.
Accommodations families commonly request in writing:
- Modified PE or adapted PE — no contact sports, no trampolines, no full-speed sprints; swimming and stationary bike are usually safe.
- Unlimited bathroom access without asking (gastrointestinal and bladder urgency are real).
- Permission to carry a water bottle and snacks everywhere (blood sugar and postural orthostatic tachycardia syndrome (POTS) salt/fluid needs).
- Extra time on handwritten assignments and tests; access to a laptop, speech-to-text, or a note-taker when dysgraphia is significant.
- An elevator key in multi-story buildings.
- Permission for fidget tools, compression garments, braces, and seat cushions.
- A flexible attendance policy acknowledging medically excused absences.
- Two sets of textbooks — one at home, one in the classroom — so a heavy backpack does not aggravate shoulder and spine pain.
Chronic absenteeism is the norm, not an aberration. When a brick-and-mortar schedule becomes unsustainable, options include hybrid schedules, homebound instruction (usually triggered by a physician letter stating 15+ days of expected absence), online public charter schools, and college dual-enrollment. At college, students register with Disability Services (sometimes called Disabled Students Programs and Services or the Office of Accessibility), and doing so before classes begin avoids waiting until after the first failing grade.
Growth Spurts and the Teen Flare
The single most predictable feature of pediatric Ehlers-Danlos syndrome is the teen flare. Between roughly ages 13 and 15, during the rapid adolescent growth spurt, pain often escalates sharply. Joints that were bendy and slightly achy at age 10 become unstable and intensely painful at 14. Fatigue deepens. Postural orthostatic tachycardia syndrome frequently emerges for the first time as cardiovascular volume fails to keep up with the newly longer body. Gastrointestinal symptoms appear or worsen. Mental-health distress peaks alongside the physical one.
This is not regression or somatization; it is the predictable intersection of rapid skeletal growth, incomplete muscular support for newly long limbs, and adolescent cardiovascular/hormonal change. The flare is usually partially reversible once growth slows in the late teens, provided the child reaches that point with intact physical therapy habits, adequate mental-health support, and a functioning care team.
Mental Health and Neurodevelopmental Overlap
A growing research literature describes elevated rates of attention-deficit/hyperactivity disorder (ADHD), autism spectrum, anxiety, depression, and pediatric acute-onset neuropsychiatric syndrome (PANS) or pediatric autoimmune neuropsychiatric disorders associated with streptococcal infections (PANDAS) in Ehlers-Danlos syndrome cohorts compared with the general population. The mechanisms are not fully understood; proposed links include shared connective-tissue effects on the central nervous system, chronic dysautonomia altering arousal regulation, and the sheer cumulative weight of chronic pain and medical invalidation on a developing brain. In a study of 109 neurodivergent adults, not children, 51% had joint hypermobility compared with 20% in the general population, and the number of hypermobile joints mediated the link with dizziness on standing and with pain.
Practically, this means two things. First, an Ehlers-Danlos syndrome diagnosis does not exclude — and often accompanies — a neurodevelopmental diagnosis, and each has its own evaluation and support. Second, the anxiety and depression that show up in Ehlers-Danlos syndrome teens are usually reactive — a reasonable response to pain, lost activities, missed school, and years of being disbelieved. A pediatric pain psychologist familiar with chronic illness is far more useful than a generalist who will default to "your symptoms are caused by anxiety." Cognitive-behavioral therapy and acceptance-and-commitment therapy have both been studied in pediatric chronic pain and both help when delivered by someone who takes the physical illness seriously.
Managing a Pediatric Ehlers-Danlos Syndrome Family
Having a chronically ill child reshapes an entire household. Common patterns:
- Parent exhaustion. One parent — usually but not always the mother — becomes the full-time medical project manager: appointments, insurance appeals, IEP meetings, prescription refills, advocacy phone calls. Burnout is the rule.
- Sibling dynamics. Healthy siblings alternately feel ignored, resentful, guilty, and frightened. They may become precociously caretaking or act out to get the share of attention their brother or sister receives automatically.
- Marital stress. Parents frequently disagree on how sick the child really is, how much to restrict activity, when to push and when to rest, and how to divide the caretaking labor.
Parent forums run by Ehlers-Danlos patient organizations are described by families as a practical, unglamorous source of help: other parents who have been there, script templates for school letters, insurance-appeal strategies, and honest talk about marriage and sibling issues. Some families also use a family therapist (for household dynamics, not the child's Ehlers-Danlos syndrome) and respite care when available.
The Transition to Adult Care
Nothing in pediatric Ehlers-Danlos syndrome falls through the cracks more reliably than the handoff from pediatric to adult care. The standard transition window is age 16 to 22, and families and clinics describe planning it from age 14, not scrambling in the waiting room on someone's eighteenth birthday.
A good transition includes:
- A warm handoff: the pediatric provider communicates directly with the adult provider, not just via chart notes.
- A written medical summary: diagnoses, medication list with doses and tried-and-failed history, subspecialist contacts, physical therapy program, flare pattern, what works and what does not.
- An adult primary care physician who is at minimum Ehlers-Danlos syndrome-aware (willing to learn) if not Ehlers-Danlos syndrome-experienced. A short list can usually be crowdsourced from local Ehlers-Danlos syndrome online support groups.
- Subspecialty re-establishment — adult rheumatology, cardiology for postural orthostatic tachycardia syndrome, gastrointestinal, pain management. Some pediatric subspecialists see patients up to age 21; others cut off at 18.
- Insurance planning. In the United States, a young adult can remain on a parent's health plan until age 26 under the Affordable Care Act, but employer-sponsored plans vary, and dependent disability extensions require paperwork filed before the 26th birthday. Marketplace plans, Medicaid (income-based), and Supplemental Security Income and Social Security Disability Insurance (disability-based) are the fallback options.
Some pediatric clinics use a formal transition tool, which walks family and teen through the skills the adolescent needs before the handoff.
Independent Living Skills
The functional skills a healthy teen picks up by osmosis often have to be explicitly taught to a chronically ill one, because their parents have been doing everything medical on their behalf. Target skills to transfer gradually through high school:
- Medication self-management — ordering refills, using a pill organizer, tracking side effects.
- Scheduling and attending appointments alone; knowing when to bring a parent as a second set of ears.
- Reading an insurance card, understanding deductibles and copays, calling member services when a claim is denied.
- Deciding when and how to disclose a disability to an employer or a professor. Disclosure is legally optional in most settings but practically necessary to obtain accommodations.
- Driving modifications — grip aids on the steering wheel, prioritizing power steering when car-shopping, knowing when a shoulder subluxation makes driving unsafe for the day.
College, Sports, and Career Planning
Many clinicians regard sports at the college level as a poor fit for a body with hypermobile Ehlers-Danlos syndrome. An 18-study meta-analysis found a significantly higher risk of knee injury in hypermobile participants playing contact sports (odds ratio 4.69, range 1.33 to 16.52) and no increased risk of ankle injury. Low-impact activities — swimming, recumbent cycling, rowing on a machine with attention to form, Pilates — can be continued for life. Contact sports, heavy running, and gymnastics cause a trajectory of injury that the connective tissue does not recover from the way a typical athlete's does.
Career planning benefits from early honesty about which jobs are sustainable. People with the condition and those who work with them commonly describe as favorable: remote-eligible roles, knowledge work with flexible hours, creative fields that allow recovery days, teaching at levels that permit sitting, research and analytical work, medical and mental-health fields (many Ehlers-Danlos syndrome patients become excellent clinicians). And as difficult: nursing floor work, retail standing, restaurant and hospitality, construction, long-haul driving, surgery, any work with rigid eight-hour schedules and no flexibility for flares. Fertility and reproductive choices belong in the same conversation early — see the Pregnancy and Ehlers-Danlos syndrome page for details on genetic counseling, pregnancy risk by subtype, and timing decisions.
Emergency Preparedness
Many Ehlers-Danlos syndrome teens and young adults carry an emergency contact card in their wallet and a copy in their phone's medical ID. A typical card lists:
- Full diagnosis and subtype, with the name and contact of the diagnosing physician.
- Current medications with doses.
- Known allergies and anesthetic issues.
- Two emergency contacts with relationship noted.
- Any cardiac or vascular imaging results that would change ER management (for classical or vascular Ehlers-Danlos syndrome patients especially).
- A short statement: "If I present confused or with chest, abdominal, or head pain, please consider Ehlers-Danlos syndrome-related vascular or spinal emergencies and contact my specialist."
For families with vascular Ehlers-Danlos syndrome, a hospitalization plan — which hospital, which surgeon, which vascular team — is something clinicians describe working out in advance, not deciding in an ambulance.
Key Research Papers
- Tinkle B, et al. Hypermobile Ehlers-Danlos syndrome (a.k.a. Ehlers-Danlos syndrome Type III and Ehlers-Danlos syndrome hypermobility type): Clinical description and natural history. Am J Med Genet C Semin Med Genet. 2017;175(1):48-69. — doi:10.1002/ajmg.c.31538
- Scheper MC, et al. Children with generalised joint hypermobility and musculoskeletal complaints: state of the art on diagnostics, clinical characteristics, and treatment. Biomed Res Int. 2013;2013:121054. — PubMed PMID: 23971021
- Kovacic K, et al. Joint hypermobility: a common association with complex functional gastrointestinal disorders. J Pediatr. 2014;165(5):973-8. — doi:10.1016/j.jpeds.2014.07.021
- Pacey V, et al. Generalized joint hypermobility and risk of lower limb joint injury during sport: a systematic review with meta-analysis. Am J Sports Med. 2010;38(7):1487-97. — doi:10.1177/0363546510364838
- Tofts LJ, Simmonds J, Schwartz SB, et al. Pediatric joint hypermobility: a diagnostic framework and narrative review. Orphanet J Rare Dis. 2023;18(1):104. — PubMed PMID: 37143135
- Bourne KM, Thai S, Lei LY, et al. Patients with Ehlers-Danlos syndrome experience reduced effectiveness of lidocaine local anesthetic: a randomized cross-over clinical trial. Reg Anesth Pain Med. 2026. — PubMed PMID: 41775498
- Artoni A, Bassotti A, Abbattista M, et al. Hemostatic abnormalities in patients with Ehlers-Danlos syndrome. J Thromb Haemost. 2018;16(12):2425-2431. — PubMed PMID: 30312027
- Csecs JLL, Iodice V, Rae CL, et al. Joint Hypermobility Links Neurodivergence to Dysautonomia and Pain. Front Psychiatry. 2021;12:786916. — PubMed PMID: 35185636
- Bulbena A, Duró JC, Porta M, et al. Clinical assessment of hypermobility of joints: assembling criteria. J Rheumatol. 1992;19(1):115-22. — PubMed PMID: 1556672
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on pediatric Ehlers-Danlos syndrome recognition, management, and the transition to adult care:
- PubMed: Pediatric Ehlers-Danlos and joint hypermobility
- PubMed: Beighton score age adjustment in children
- PubMed: Bulbena hypermobility scale
- PubMed: EDS and local anesthetic resistance
- PubMed: Hypermobility and pediatric scoliosis
- PubMed: EDS school accommodations and 504 plans
- PubMed: EDS, autism, and ADHD overlap
- PubMed: Pediatric-to-adult care transition in chronic illness
- PubMed: Joint hypermobility and pediatric dysautonomia
Connections
- Rheumatology
- Ehlers-Danlos Syndrome
- Hypermobile Ehlers-Danlos Syndrome and 2017 Diagnostic Criteria
- Classical and Vascular Ehlers-Danlos Syndrome
- Craniocervical Instability and AAI
- Gastrointestinal Involvement in Ehlers-Danlos Syndrome
- Postural Orthostatic Tachycardia Syndrome, Mast Cell Activation Syndrome and the Ehlers-Danlos Syndrome Triad
- Pain Management in hEDS
- Physical Therapy and Joint Protection
- Pregnancy and Ehlers-Danlos Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome-MCAS-EDS Triad
- Mast Cell Activation Syndrome
- Fibromyalgia
- Chronic Fatigue Syndrome
- Migraine
- Chronic Pain
- Anxiety