⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a Beighton threshold of 4 is often applied to adult men, that pectus excavatum or carinatum is a supporting skeletal finding, that physiatry is often a better first stop than rheumatology, and that patient-assistance pricing caps genetic panel costs around $100 to $250. This page keeps it as a report of what people, websites or other media say.
Hypermobile Ehlers-Danlos Syndrome (EDS) and the 2017 Diagnostic Criteria
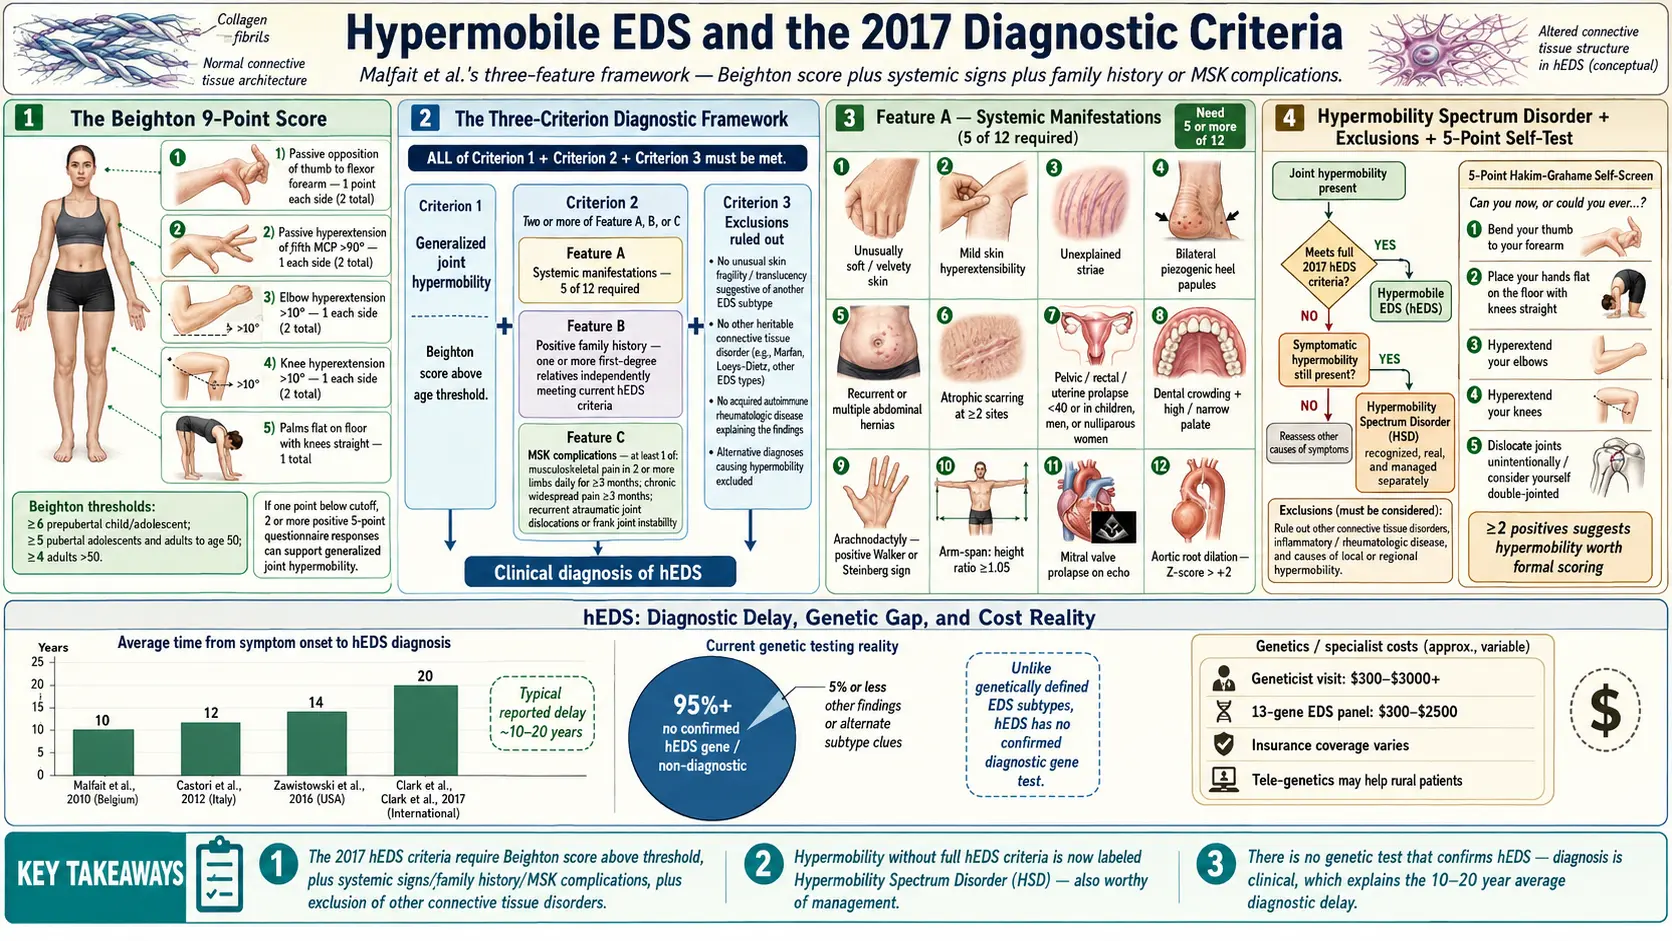
Table of Contents
- What Hypermobile Ehlers-Danlos Syndrome Is — and Why It Is Different
- The Beighton 9-Point Score
- Age- and Sex-Adjusted Beighton Thresholds
- Historical GJH vs. hEDS — The Shift in Terminology
- The 2017 hEDS Diagnostic Criteria (Malfait et al.)
- Feature A — Systemic Manifestations
- Feature B (Family History) and Feature C (MSK Complications)
- The Exclusion Criterion — Ruling Out Other Disorders
- Hypermobility Spectrum Disorder (HSD)
- The Criteria Controversy
- Self-Assessment at Home — The 5-Point Questionnaire
- Finding a Knowledgeable Provider
- What the Genetic Test Gap Means
- Classical Ehlers-Danlos Syndrome (cEDS) as a Contrast
- Cost Reality — Geneticist Visits and Panels
- Key Research Papers
- Connections
- Featured Videos
What Hypermobile Ehlers-Danlos Syndrome Is — and Why It Is Different
Hypermobile Ehlers-Danlos Syndrome (hEDS) is the most common subtype of Ehlers-Danlos syndrome (EDS), accounting for an estimated 80–90% of all Ehlers-Danlos syndrome cases. It is also the only one of the thirteen currently recognized Ehlers-Danlos syndrome subtypes without an identified gene. Classical Ehlers-Danlos syndrome has pathogenic variants in COL5A1 and COL5A2. Vascular Ehlers-Danlos syndrome is tied to COL3A1. Kyphoscoliotic, arthrochalasia, dermatosparaxis, and the other rarer subtypes each have molecular signatures that a lab can confirm from a blood or saliva sample. hEDS does not — not yet.
That single fact shapes everything about how hEDS is diagnosed, doubted, studied, and funded. Without a gene, there is no confirmatory test. The diagnosis is made from the patient's body and history against a published clinical checklist. It is a diagnosis of pattern-recognition and exclusion, which puts enormous weight on the clinician seeing it and the criteria being used.
The current rulebook is the 2017 International Classification of the Ehlers-Danlos Syndromes, published by Malfait and colleagues, with a companion paper by Castori and colleagues explaining the framework. These two papers replaced the older 1998 Villefranche criteria and, deliberately, made hEDS harder to diagnose than it had been. The rationale was scientific — a tighter clinical definition would produce cleaner research cohorts, which would speed up the hunt for the gene — but the human cost has been substantial. Many patients with obviously loose joints, chronic pain, frequent subluxations, and a textbook family tree now fall outside the strict boundary.
The Beighton 9-Point Score
The Beighton score is a quick bedside test of generalized joint hypermobility (GJH). It scores nine maneuvers, one point each, for a maximum of 9:
- Passive hyperextension of the 5th finger beyond 90 degrees — 1 point per hand, 2 total.
- Passive apposition of the thumb to the flexor side of the forearm — 1 point per hand, 2 total.
- Active hyperextension of the elbow beyond 10 degrees — 1 point per elbow, 2 total.
- Active hyperextension of the knee beyond 10 degrees — 1 point per knee, 2 total.
- Forward flexion of the trunk with knees fully extended so that palms rest flat on the floor — 1 point (not bilateral).
The elbow and knee hyperextension is measured with a goniometer (a hinged joint-angle ruler) rather than judged by eye — the 10-degree cutoff matters, and it is easy to over- or under-call without one. Many patients score the points they do not remember scoring; hypermobile people tend to assume their range of motion is normal because it is the only range they have ever had.
Age- and Sex-Adjusted Beighton Thresholds
The 2017 criteria recognize that joint laxity decreases with age. A 45-year-old who can no longer put her palms on the floor may have scored 8 out of 9 as a teenager. The thresholds for meeting the GJH requirement of hEDS, as the 2017 checklist states them, are:
- Children before puberty and adolescents: ≥6 out of 9.
- Men and women from puberty to age 50: ≥5 out of 9.
- Men and women over the age of 50: ≥4 out of 9.
- Adult men at any age: the threshold is often functionally applied as ≥4 given that men score lower than women on average at every age.
The checklist gives the same three cut-offs for men and women; it has no separate threshold for men.
If the current Beighton score is one point below the cut-off for the person's age, the checklist allows the 5-point questionnaire (see self-assessment below) as a historical supplement: two or more "yes" answers then meet the joint-hypermobility criterion, even in a now-stiffer adult body. A score two or more points below the cut-off is not rescued by the questionnaire.
Historical GJH vs. hEDS — The Shift in Terminology
Before 2017, the field used a simpler hierarchy: benign joint hypermobility syndrome for people with loose joints and pain but no other systemic findings, and hEDS (then called Ehlers-Danlos syndrome-hypermobility type or Ehlers-Danlos syndrome Type III) for people with more body-wide involvement. The line between them was blurry, and the same patient could carry either label depending on which clinic she walked into.
The 2017 rewrite drew a sharper line. Generalized joint hypermobility (GJH) became an objective, measurable finding — a Beighton score above the age-adjusted threshold. hEDS became a specific multi-system syndrome with a checklist. Patients who fall between the two — hypermobile with symptoms but not quite meeting the full hEDS checklist — moved into a new umbrella called Hypermobility Spectrum Disorder (HSD).
The 2017 hEDS Diagnostic Criteria (Malfait et al.)
To receive an hEDS diagnosis under the current rules, a patient must meet all three of the following criteria simultaneously:
- Criterion 1 — Generalized joint hypermobility (GJH). Beighton score at or above the age-adjusted threshold, or — if the score is exactly one point below that threshold — two or more "yes" answers on the 5-point questionnaire to establish historical GJH.
- Criterion 2 — Two or more of Feature A, Feature B, or Feature C (described below).
- Criterion 3 — Exclusion. Three prerequisites, all of which must be met: no unusual skin fragility; exclusion of other heritable and acquired connective tissue disorders, including autoimmune rheumatologic conditions; and exclusion of other diagnoses that can cause joint hypermobility through low muscle tone (hypotonia) or loose connective tissue.
All three must be satisfied. Missing any one of the three means the patient does not meet the hEDS definition, regardless of how hypermobile or how symptomatic she is.
Feature A — Systemic Manifestations
Feature A is a list of twelve body-wide signs of abnormal connective tissue. The patient must have at least five of them to count Feature A as "present." Several items count only within limits written into the checklist itself (who the sign counts in, which sides of the body, how it is measured). The twelve signs, in the checklist's terms, are:
- Unusually soft or velvety skin.
- Mild skin hyperextensibility (the skin lifts away from the forearm more than usual, but springs back).
- Unexplained striae (stretch marks, white or red — striae distensae or rubae) at the back, groins, thighs, breasts and/or abdomen. This item counts only in adolescents, men or women before puberty who have no history of significant gain or loss of body fat or weight.
- Bilateral piezogenic papules of the heel — small fat herniations that bulge out when standing.
- Recurrent or multiple abdominal hernias.
- Atrophic scarring in at least two sites, without the truly papery (papyraceous) and/or brown-stained (hemosideric) scars seen in classical Ehlers-Danlos syndrome.
- Pelvic floor, rectal, and/or uterine prolapse. This item counts only in children, men or women who have never given birth (nulliparous women), and only without a history of morbid obesity or another known medical condition that predisposes to prolapse.
- Dental crowding and a high or narrow palate.
- Arachnodactyly (long, slender fingers) — defined by a positive wrist sign (Walker sign) on both sides, a positive thumb sign (Steinberg sign) on both sides, or both.
- Arm-span-to-height ratio ≥1.05.
- Mitral valve prolapse (mild or greater), based on strict echocardiographic criteria.
- Aortic root dilatation with a Z-score >+2.
A pectus excavatum or carinatum is also a supporting skeletal finding.
Five of twelve is a fairly demanding bar, and many hypermobile patients who look obviously "connective-tissue different" score three or four.
Feature B (Family History) and Feature C (MSK Complications)
Feature B is simple: a positive family history, meaning one or more first-degree relatives (parent, full sibling, or child) independently meets the hEDS criteria. "Family members who seem bendy" does not count — the relative has to meet the full 2017 checklist. This is one of the most restrictive parts of the criteria, because in many families the oldest known affected member was diagnosed before 2017 under older rules, or was never evaluated at all.
Feature C is the musculoskeletal burden of disease. It is met by any of the following:
- Musculoskeletal pain in two or more limbs, recurring daily, for at least three months.
- Chronic widespread pain for three or more months.
- Recurrent joint dislocations or frank joint instability in the absence of trauma, defined as either three or more atraumatic dislocations in the same joint, or two or more atraumatic dislocations in two different joints occurring at different times.
Feature C is often the easiest for symptomatic adults to meet and the hardest for children, whose pain may be dismissed as "growing pains" and whose subluxations may not yet have happened enough times to count.
The Exclusion Criterion — Ruling Out Other Disorders
Criterion 3 requires the clinician to actively exclude other conditions that can mimic hEDS. The 2017 checklist lists three prerequisites, all of which must be met: the absence of unusual skin fragility (which points toward other types of Ehlers-Danlos syndrome); exclusion of other heritable and acquired connective tissue disorders, including autoimmune rheumatologic conditions; and exclusion of other diagnoses that cause joint hypermobility through low muscle tone (hypotonia) or loose connective tissue. In practice, this means ruling out:
- Other Ehlers-Danlos syndrome subtypes — especially classical Ehlers-Danlos syndrome (COL5A1, COL5A2) and vascular Ehlers-Danlos syndrome (COL3A1), which have specific genetic tests. A multi-gene connective-tissue panel is the standard way to exclude them in one sweep.
- Marfan syndrome (FBN1 variants), which shares the tall, long-limbed, high-palate phenotype but is driven by fibrillin-1 defects and carries an aortic-dissection risk profile of its own.
- Loeys-Dietz syndrome (LDS) — caused by variants in the TGF-β signaling pathway genes (TGFBR1, TGFBR2, SMAD3, TGFB2, TGFB3) — which also presents with hypermobility, skin findings, and vascular risk.
- Skeletal dysplasias such as osteogenesis imperfecta, including its milder forms (COL1A1, COL1A2), which can overlap symptomatically.
- Neuromuscular disorders such as Bethlem myopathy, which the checklist names as an example of a condition that can cause joint hypermobility through low muscle tone.
- Rheumatoid arthritis and other inflammatory arthritides, which can produce joint pain, swelling, and instability from a different mechanism.
- Acquired connective tissue disease such as lupus or rheumatoid arthritis. These do not automatically rule hEDS out. In a person who has one, the 2017 checklist allows an additional diagnosis of hEDS only if both Feature A and Feature B are met, and Feature C (chronic pain and/or instability) cannot be counted toward the diagnosis.
The checklist states that these exclusions may be based on history, physical examination and/or molecular genetic testing, as indicated.
In practice, exclusion is done with a combination of a genetic panel, an echocardiogram to screen for aortic root dilatation, basic labs (antinuclear antibody (ANA), complete blood count (CBC), inflammatory markers), and a careful clinical exam.
Hypermobility Spectrum Disorder (HSD)
Hypermobility Spectrum Disorder (HSD) is the diagnostic umbrella for hypermobile patients with clinical problems who do not meet the full 2017 hEDS checklist. It was introduced in 2017 specifically to catch this group. HSD has four recognized variants:
- Generalized HSD (G-HSD) — Beighton-positive GJH with musculoskeletal complications but not enough Feature A items, no qualifying family history, and no confirmed diagnosis of another Ehlers-Danlos syndrome subtype.
- Peripheral HSD (P-HSD) — hypermobility limited to the hands and feet, with symptoms.
- Localized HSD (L-HSD) — hypermobility of a single joint or small joint group, with symptoms.
- Historical HSD (H-HSD) — self-reported historical GJH plus current musculoskeletal symptoms, when current Beighton is below threshold and historical GJH is established via the 5-point questionnaire.
The critical point for patients: HSD and hEDS are managed identically. Physical therapy, pacing, pain management, joint protection, and screening for the Ehlers-Danlos syndrome-adjacent conditions (postural orthostatic tachycardia syndrome (POTS), mast cell activation syndrome (MCAS), gastrointestinal (GI) dysmotility) are the same regardless of which label applies. The label is a research and communication tool, not a treatment-determining distinction.
The Criteria Controversy
The 2017 criteria were designed to shrink the hEDS population in order to make gene-hunting feasible. That goal was reasonable. The side effect, which researchers openly acknowledge, is that many patients with clinically obvious Ehlers-Danlos syndrome-type connective tissue involvement no longer qualify for the hEDS label.
Common ways patients "fail out" of the criteria:
- No family history. The affected parent died young, was never tested, or refuses to be evaluated. Without a confirmed first-degree relative, Feature B is unmet.
- Feature A short by one or two. Four of the twelve systemic signs instead of five — very common in younger patients whose striae, prolapse, or valve changes have not yet appeared.
- Beighton just under threshold in a now-stiffer adult, with incomplete historical documentation.
- Mixed phenotype that looks partly like classical Ehlers-Danlos syndrome on skin exam but has a negative COL5 panel.
These patients are real, their symptoms are real, and their response to Ehlers-Danlos syndrome-aware care is real. Under the current rules, HSD is the label that fits most of them, and the care described for hEDS — physical therapy referrals, genetics follow-up, cardiology screening, postural orthostatic tachycardia syndrome and mast cell activation syndrome workups — is the same care described for HSD in the section above. In practice, some insurers and some clinicians treat HSD as a lesser diagnosis. That is a policy gap, not a medical one.
Self-Assessment at Home — The 5-Point Questionnaire
The Hakim and Grahame 5-point questionnaire is a validated screen that can be done at the kitchen table. Two or more "yes" answers suggests generalized joint hypermobility. The questions below are worded as they appear in the 2017 checklist:
- Can you now (or could you ever) place your hands flat on the floor without bending your knees?
- Can you now (or could you ever) bend your thumb to touch your forearm?
- As a child, did you amuse your friends by contorting your body into strange shapes or could you do the splits?
- As a child or teenager, did your shoulder or kneecap dislocate on more than one occasion?
- Do you consider yourself double-jointed?
Two or more "yes" answers is the cutoff. In the 2003 study that built the questionnaire (212 hypermobile women attending London hypermobility clinics plus healthy volunteers, then a second group of 170 cases and 50 controls), a "yes" to any two questions gave a sensitivity of 84% in both groups and a specificity of 89% and 80%; overall it sorted 84% of cases and controls correctly. This is a screening tool, not a diagnosis: the diagnosis itself rests on the full 2017 checklist above, which uses the questionnaire only when the Beighton score is one point short.
Finding a Knowledgeable Provider
Ehlers-Danlos syndrome is under-taught in medical school. Most rheumatologists see one or two hEDS patients per year and may not know the 2017 criteria by heart. A smaller group has made hypermobility its focus. Routes people use to find one:
- The Ehlers-Danlos Society Healthcare Professionals Directory (ehlers-danlos.com) lists clinicians worldwide who self-identify as Ehlers-Danlos syndrome-knowledgeable and have agreed to see Ehlers-Danlos syndrome patients.
- Physical medicine and rehabilitation (PM&R) doctors, also called physiatrists, are another route. Physiatry (PM&R) is often a better first stop than rheumatology. Hypermobility is a musculoskeletal-function problem, not an inflammatory-arthritis problem, and physiatrists work with joint mechanics and physical therapy dosing. Pain and rehabilitation physicians who focus on hypermobility are widely discussed in the patient community.
- Clinical geneticists — the specialty of several of the researchers who wrote the 2017 criteria — diagnose and follow the Ehlers-Danlos syndromes.
- Academic Ehlers-Danlos syndrome clinics have emerged at several major university medical centers and children's hospitals, and at the U.S. National Institutes of Health (NIH). Waits are long — often 6 to 18 months — and these clinics see many complex multi-system cases.
- Local physical therapists with advanced hypermobility training fill the day-to-day gap. Approaches used with hypermobile patients include hypermobility-specific strengthening programs, the Levine protocol for postural orthostatic tachycardia syndrome, and joint protection training.
People who have been through these visits describe bringing a completed Beighton self-score, a timeline of dislocations and subluxations, a family tree sketch, and a list of associated symptoms (orthostatic intolerance, irritable bowel syndrome-type gastrointestinal complaints, skin findings, dental crowding). The encounter is short, and that preparation is what makes it useful.
What the Genetic Test Gap Means
There is currently no genetic test that confirms hEDS. A negative Ehlers-Danlos syndrome gene panel does not rule hEDS out, and a positive panel rules it in only for one of the other subtypes. Several active research threads are trying to close the gap:
- The HEDGE study (Hypermobile Ehlers-Danlos syndrome Genetic Evaluation), coordinated by the Ehlers-Danlos Society, has enrolled thousands of strictly-criteria-meeting hEDS patients for whole-genome sequencing. Candidate variants are emerging but none has yet been validated for clinical use.
- Kallikrein genes and KLK15. In 2025 a research team read the protein-coding genes (whole-exome sequencing) of 200 people with hEDS and found rare and low-frequency variants in 14 of the 15 kallikrein (KLK) genes, including one repeated KLK15 change (p.Gly226Asp) that ran in several families. Mice carrying that change developed hEDS-like features in their tendons and heart valves. The authors describe hEDS as involving matrix remodeling and immune signaling beyond collagen. This is a research finding, not yet a diagnostic test.
- COL5 subtype overlap. A subset of patients with COL5A1 variants present clinically more like hEDS than like textbook classical Ehlers-Danlos syndrome — soft stretchy skin and hypermobility without the wide atrophic scars. These cases blur the line between the two subtypes and hint that the gene-phenotype map is not one-to-one.
- TNXB heterozygous variants. Biallelic TNXB loss causes a rare recessive Ehlers-Danlos syndrome. Recent work suggests that heterozygous (single-copy) TNXB variants may contribute to a hEDS-like phenotype in some patients, although the penetrance and clinical significance are still being worked out.
- Mast cell and complement gene variants. Because hEDS so often travels with mast cell activation syndrome and dysautonomia, investigators are examining whether the unifying biology lies partly outside the collagen genes.
Until the gene is found, hEDS will remain a clinical diagnosis. That is not a failure of the patient; it is a current limitation of the science.
Classical Ehlers-Danlos Syndrome (cEDS) as a Contrast
Classical Ehlers-Danlos syndrome is worth understanding briefly because it is the closest cousin of hEDS and the most common reason for a genetic exclusion panel. Under the 2017 criteria, a clinical diagnosis of cEDS requires the major criterion of skin hyperextensibility plus atrophic scars, together with either generalized joint hypermobility or at least three of nine minor criteria (easy bruising, soft doughy skin, fragile skin, molluscoid pseudotumors, subcutaneous spheroids, hernia, epicanthal folds, joint complications, and a positive first-degree family history). Confirmation requires a pathogenic variant in COL5A1 or COL5A2, and in a small fraction of cases a specific COL1A1 arginine-to-cysteine substitution.
A 2024 review by specialists from European Ehlers-Danlos services states that gene-panel testing with massively parallel sequencing is now the gold standard to confirm the monogenic Ehlers-Danlos syndrome types such as cEDS, but that a thorough clinical assessment — medical history, family history and physical examination — remains important, and that where no gene change can be found, a clinical diagnosis can still guide management and surveillance.
The defining difference is the skin. cEDS skin splits easily with minor trauma and heals into wide, thin, papery scars — classically on the knees, elbows, shins, and forehead. hEDS skin may be soft, velvety, and mildly stretchy, but it does not usually produce the wide atrophic scarring. A careful skin exam can separate the two in most cases; a COL5 panel closes the question.
Cost Reality — Geneticist Visits and Panels
Pursuing a formal diagnosis has a price tag. Typical U.S. costs in 2026 dollars:
- Clinical geneticist consultation: roughly $300–$800 out of pocket if uncovered, less with insurance. Many academic centers bill a separate genetic-counselor fee on top. Telegenetics visits are increasingly available and generally cheaper.
- Targeted Ehlers-Danlos syndrome gene panel (covering COL5A1, COL5A2, COL3A1, COL1A1, COL1A2, TNXB, and the rarer kyphoscoliotic and arthrochalasia genes): roughly $500–$1,500.
- Broader connective-tissue panel (adding Marfan and Loeys-Dietz genes, osteogenesis imperfecta expansion, cutis laxa genes, and others): roughly $1,500–$3,000.
- Whole-exome or whole-genome sequencing, if the panel is negative and clinical suspicion remains high: $1,000–$3,000 depending on the lab and whether trio testing (patient plus both parents) is included.
- Echocardiogram for aortic root measurement: $800–$2,500 billed, often fully covered by insurance when ordered for heritable connective tissue evaluation.
Insurance coverage has improved since 2017 but remains inconsistent. Commercial genetic-testing laboratories offer Ehlers-Danlos syndrome panels, and several bill insurance directly or offer patient-assistance pricing that lowers the out-of-pocket cost below the list price, capping out-of-pocket costs around $100–$250 regardless of the list price. A patient-assistance quote can be requested by the ordering clinician before the test is run.
A final note on expectations. Because hEDS has no gene yet, a negative panel does not rule hEDS out — it only rules out the subtypes it tests for. Patients sometimes walk into a genetics visit hoping for a definitive "yes, you have hEDS" result and walk out with a clinical diagnosis, a negative panel, and the same chronic symptoms. That is, oddly, a successful visit: the exclusion criterion of the 2017 rules has been met, and Ehlers-Danlos syndrome-aware care can proceed.
Key Research Papers
- Malfait F, Francomano C, Byers P, et al. The 2017 international classification of the Ehlers-Danlos syndromes. Am J Med Genet C Semin Med Genet. 2017;175(1):8–26. — doi:10.1002/ajmg.c.31552
- Castori M, Tinkle B, Levy H, Grahame R, Malfait F, Hakim A. A framework for the classification of joint hypermobility and related conditions. Am J Med Genet C Semin Med Genet. 2017;175(1):148–157. — doi:10.1002/ajmg.c.31539
- Hakim AJ, Grahame R. A simple questionnaire to detect hypermobility: an adjunct to the assessment of patients with diffuse musculoskeletal pain. (5-point questionnaire reference.) Int J Clin Pract. 2003;57(3):163–166. — PubMed PMID: 12723715
- Tinkle B, Castori M, Berglund B, et al. Hypermobile Ehlers-Danlos syndrome (a.k.a. Ehlers-Danlos syndrome Type III and Ehlers-Danlos syndrome hypermobility type): clinical description and natural history. Am J Med Genet C Semin Med Genet. 2017;175(1):48–69. — doi:10.1002/ajmg.c.31538
- The Ehlers-Danlos Society. Diagnostic criteria for hypermobile Ehlers-Danlos syndrome (hEDS) — checklist of the 2017 criteria of Malfait et al. 2017. — hEDS diagnostic checklist (PDF)
- van Dijk FS, Angwin C, Demirdas S, Ghali N, Zschocke J. Clinical diagnosis of the monogenic Ehlers-Danlos syndromes. Med Genet. 2024;36(4):225–234. — PubMed PMID: 39629459
- Gensemer C, Petrucci T, Beck T, et al. KLK15 alters connective tissues in hypermobile Ehlers-Danlos syndrome. iScience. 2025;28(9):113343. — PubMed PMID: 40949095
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on hypermobile Ehlers-Danlos syndrome diagnosis, criteria, and associated conditions:
- PubMed: Hypermobile EDS and the 2017 diagnostic criteria
- PubMed: Beighton score and joint hypermobility assessment
- PubMed: Hypermobility Spectrum Disorder (HSD) definition and management
- PubMed: Genetic basis of hEDS and the HEDGE study
- PubMed: TNXB variants and hypermobile EDS phenotype
- PubMed: COL5A1 classical EDS and hEDS phenotype overlap
- PubMed: Hakim 5-point questionnaire for joint hypermobility
- PubMed: HEDS, POTS, and MCAS comorbidity
Connections
- Rheumatology
- Ehlers-Danlos Syndrome
- Classical and Vascular Ehlers-Danlos Syndrome
- Craniocervical Instability and AAI
- Gastrointestinal Involvement in Ehlers-Danlos Syndrome
- Postural Orthostatic Tachycardia Syndrome, Mast Cell Activation Syndrome and the Ehlers-Danlos Syndrome Triad
- Pain Management in hEDS
- Pediatric Ehlers-Danlos Syndrome and Transition of Care
- Physical Therapy and Joint Protection
- Pregnancy and Ehlers-Danlos Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Mast Cell Activation Syndrome
- Fibromyalgia
- Chronic Pain
- Chronic Fatigue Syndrome
- Osteoporosis
- Collagen