Gastrointestinal (GI) Involvement in Ehlers-Danlos Syndrome (EDS)
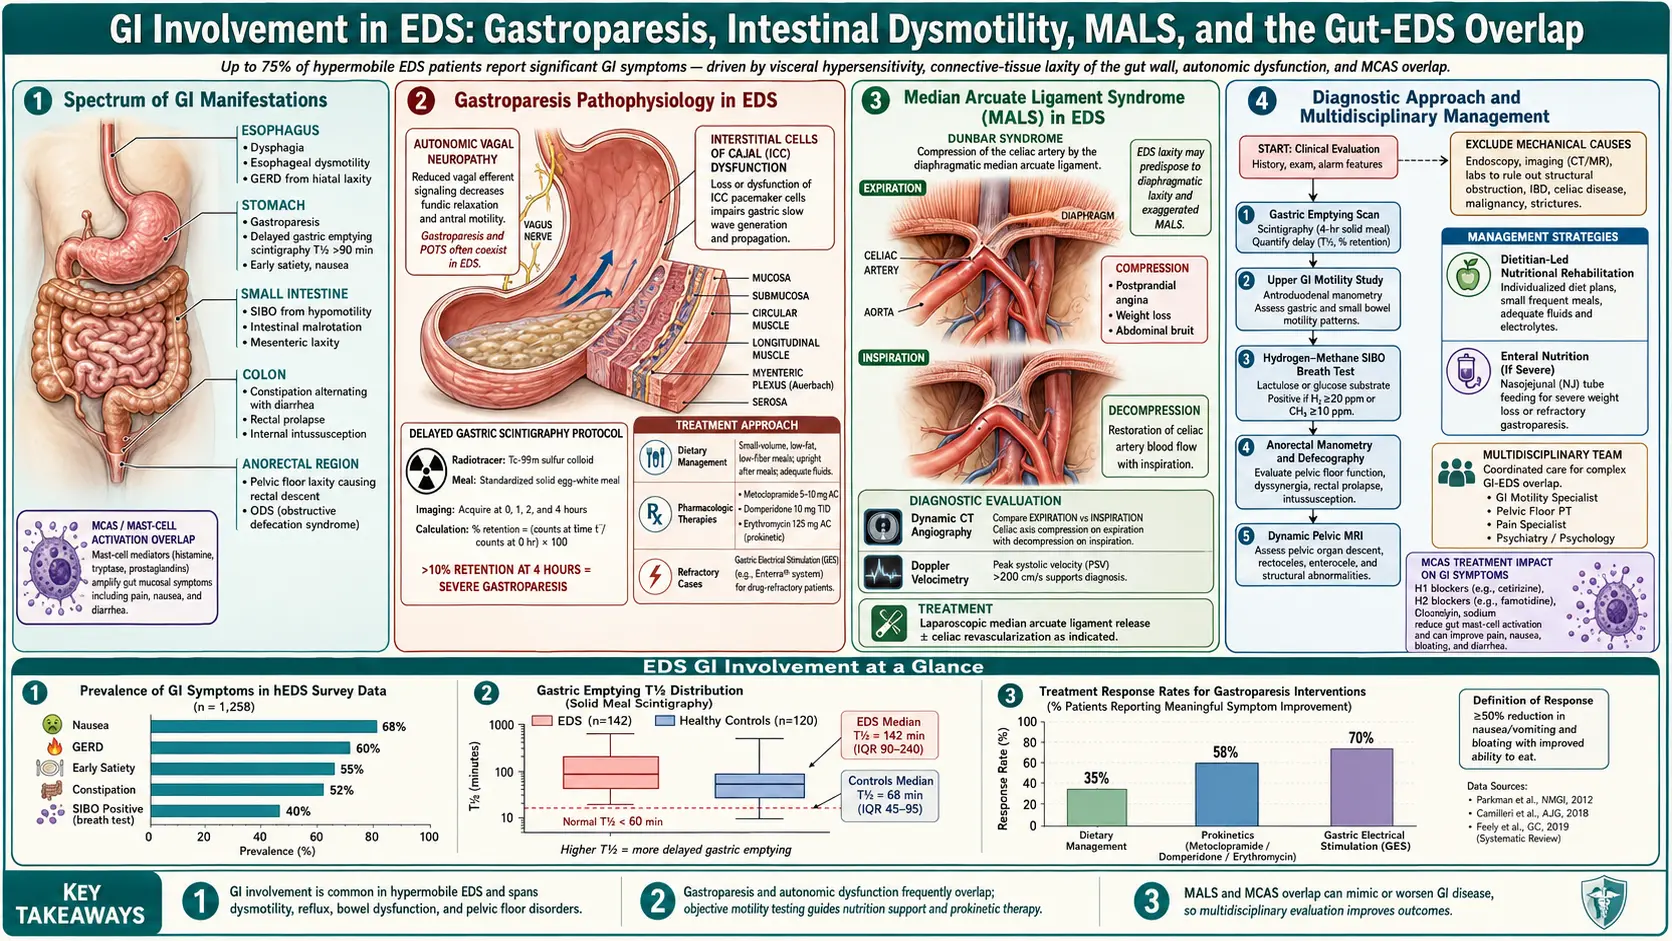
Table of Contents
- Why the Ehlers-Danlos Syndrome Gut Struggles
- Gastroparesis — The Stomach That Won’t Empty
- Small Intestinal Bacterial Overgrowth Overlap
- Irritable Bowel Syndrome-Type Symptoms & Functional Dyspepsia
- Gastroesophageal Reflux Disease, Hiatal Hernia, and Proton Pump Inhibitor Cautions
- Organ Prolapse and Hernias
- Early Diverticular Disease
- The Dysautonomic Gut — Postural Orthostatic Tachycardia Syndrome Effects
- Mast Cell Gastrointestinal Symptoms
- Eosinophilic Esophagitis and Gastritis
- Median Arcuate Ligament Syndrome (MALS)
- Superior Mesenteric Artery Syndrome
- Dysmotility Workup
- Nutrition Strategies
- vEDS and Spontaneous Bowel Rupture
- Surgery & Anesthesia Considerations
- Building Your Care Team
- Key Research Papers
- Connections
- Featured Videos
Why the Ehlers-Danlos Syndrome Gut Struggles
If you have Ehlers-Danlos syndrome and your gut is a daily problem — you are not imagining it, and you are not alone. Studies of hypermobile Ehlers-Danlos syndrome (hEDS) and other EDS cohorts consistently find gut problems: in a 20-year Mayo Clinic review of 687 EDS patients, 56% had gastrointestinal manifestations (Nelson 2015), and in a French questionnaire study of 134 EDS patients, 84% met the Rome III criteria for a functional bowel disorder (Zeitoun 2013). Fikree and colleagues at Queen Mary University of London (Wingate Institute) reported in 2014 that a third (33%) of 552 patients newly referred to gastroenterology clinics had joint hypermobility syndrome, and that these patients had more heartburn, water brash and fullness after meals than the others. Gastrointestinal (GI) complaints are the second most common reason, after joint pain, that hEDS patients seek medical care.
The reason is mechanical and neurological at once. Your gut is a long tube of smooth muscle wrapped in collagen-rich connective tissue, suspended by collagen-rich ligaments, and coordinated by an autonomic nervous system that also happens to be dysregulated in most Ehlers-Danlos syndrome patients. When the collagen scaffold is faulty, the tube stretches, sags, and empties unevenly. When the autonomic wiring is off, the tube’s peristaltic rhythm breaks down. You end up with a gut that is simultaneously too floppy and too slow.
This article walks through every layer of that dysfunction — from the stomach that won’t empty to the pelvic floor that won’t hold — and what actually helps.
Gastroparesis — The Stomach That Won’t Empty
Gastroparesis is delayed gastric emptying in the absence of mechanical obstruction. In plain language: your stomach is a bag that has forgotten how to squeeze on schedule. Food sits. You feel full after three bites. An hour later you are nauseous. Two hours later you are still full. By dinner you feel bloated from breakfast.
The classic Ehlers-Danlos syndrome gastroparesis picture:
- Early satiety — full after small amounts.
- Postprandial bloating and nausea — worst 30–90 minutes after eating.
- Upper abdominal fullness that does not respond to bowel movements.
- Unintentional weight loss in moderate-to-severe cases.
- Reflux symptoms as undigested food sits and pressurizes the lower esophageal sphincter.
The diagnostic gold standard is the 4-hour gastric emptying scintigraphy scan. You eat a standardized egg-white meal labeled with technetium-99m, and a camera tracks how much remains in your stomach at 1, 2, and 4 hours. More than 10% retention at 4 hours is abnormal — the cut-off described in the 2022 American College of Gastroenterology (ACG) gastroparesis guideline — and higher retention means a more severe delay. The older 90-minute version of this test is unreliable; the ACG guideline states that the scan should ideally run to 4 hours unless more than 90% of the meal has emptied at 3 hours.
Treatment That Actually Helps
Meal structure is the first lever, and often the most effective one:
- Small frequent meals — five or six small plates a day beat three large ones. Meals of 300–400 calories are a common target.
- Small-particle diet — the 2022 ACG guideline recommends that dietary management of gastroparesis include a small particle diet (food broken down into small particles) to increase the chance of symptom relief and improve stomach emptying (conditional recommendation, low-quality evidence).
- Soft and liquid phase during flares — smoothies, soups, yogurt, mashed vegetables, protein shakes. Liquids empty faster than solids and faster than fat.
- Lower fat and lower fiber during bad weeks — both slow gastric emptying. This is the one situation where low fiber is therapeutic.
- Upright posture for 60–90 minutes after eating — gravity helps.
Prokinetics are drugs that nudge the stomach to squeeze. None are perfect, and each has trade-offs:
- Metoclopramide — the U.S. Food and Drug Administration-approved option. Effective, but carries a black-box warning for tardive dyskinesia (a sometimes-irreversible movement disorder) if used continuously beyond 12 weeks, which is why it is often given in short courses or intermittent pulses.
- Erythromycin — an antibiotic that, at low doses, acts as a motilin-receptor agonist and drives a strong stomach contraction. The catch: tachyphylaxis (loss of effect) within 4–6 weeks of daily use. Most motility specialists dose it in pulses — two weeks on, two weeks off — or only before the largest meal of the day.
- Prucalopride — a 5-HT4 agonist originally approved for chronic constipation; off-label use for gastroparesis is growing, especially when constipation coexists.
- Domperidone — not approved for sale in the U.S. for human use. The U.S. Food and Drug Administration (FDA) states that it "cannot be legally compounded for humans"; it is available only through an FDA expanded-access investigational new drug application (IND) for patients 12 and older with certain gut conditions, including gastroparesis, whose standard treatments have failed. The FDA lists its serious risks as cardiac arrhythmias, cardiac arrest and sudden death, and in 2023 reviewed reports of neuropsychiatric events (such as agitation, anxiety and suicidal thoughts) after stopping or tapering domperidone used for breast-milk supply. It is often described as working about as well as metoclopramide with less risk of movement disorders. Requires baseline electrocardiogram (ECG) because of QT-prolongation potential.
Non-drug adjuncts that some patients find useful: ginger (250–1000 mg before meals), peppermint oil capsules, and acupressure at the P6 (Neiguan) point on the inner wrist. A German nine-herb digestive formula is also used; the 2022 ACG guideline recommends against herbal therapies, this formula among them, for treating gastroparesis (conditional recommendation, low-quality evidence), and a 2009 study cited by the guideline found that the formula’s effects "are not based on acceleration of gastric emptying".
Small Intestinal Bacterial Overgrowth Overlap
Small intestinal bacterial overgrowth is so common in hEDS that some motility clinics now screen for it routinely. Studies place small intestinal bacterial overgrowth (SIBO) in more than 50% of hEDS patients — several times the general-population rate. The mechanism is mechanical: slow small-bowel transit gives bacteria time to settle and multiply where they don’t belong.
The overlap with gastroparesis is direct — the stomach empties slowly, the small bowel receives intermittent boluses, and the migrating motor complex (the housekeeping wave that sweeps the gut clean between meals) runs weak or absent. Bacteria ferment carbohydrates, produce hydrogen and methane, and you bloat within 30 minutes of eating anything starchy or sweet.
Diagnosis is a 3-hour lactulose or glucose breath test. Treatment begins with rifaximin (550 mg three times daily for 14 days), often combined with neomycin or metronidazole if methane predominates. Relapse is common — which is why Ehlers-Danlos syndrome patients often cycle through multiple protocols and benefit from prokinetics and elemental diets between rounds.
For a full small intestinal bacterial overgrowth workup, see the small intestinal bacterial overgrowth overview, the Rifaximin Protocols deep dive, and the Elemental Diet deep dive.
Irritable Bowel Syndrome-Type Symptoms & Functional Dyspepsia
Many hEDS patients carry an irritable bowel syndrome (IBS) label from earlier in their medical journey — alternating constipation and diarrhea, bloating that waxes with stress, cramping relieved by a bowel movement. That irritable bowel syndrome label is often correct, but it is incomplete: the underlying driver is frequently a combination of dysmotility, small intestinal bacterial overgrowth, autonomic dysfunction, and mast-cell reactivity, any of which is individually treatable.
Zeitoun and colleagues (2013) surveyed 134 French EDS patients by questionnaire (80.6% with the hypermobility form): 84% met the Rome III criteria for a functional bowel disorder, 48% for irritable bowel syndrome and 36% for functional constipation, and 68.7% reported reflux disease — frequencies the authors judged higher than previously assessed.
Functional dyspepsia — upper abdominal discomfort, early satiety, postprandial distress — overlaps heavily with mild gastroparesis and is often treated as the same problem. If the 4-hour scintigraphy is normal but symptoms are classic, a prokinetic is sometimes tried anyway, and many patients are reported to improve.
Full workup and subtype-directed therapy live on the irritable bowel syndrome hub, including the Rome IV subtype breakdown and the irritable bowel syndrome Medications Guide.
Gastroesophageal Reflux Disease, Hiatal Hernia, and Proton Pump Inhibitor Cautions
Reflux symptoms are common in hEDS — 68.7% of EDS patients in the French questionnaire study reported reflux disease. The lower esophageal sphincter (LES) is a collagen-reinforced ring; when the collagen is faulty, the ring is lax. Stomach contents reflux easily, especially if gastroparesis is also pressurizing the stomach from below. Hiatal hernia — where the upper stomach slides through the diaphragm into the chest — is more common in Ehlers-Danlos syndrome than in the general population, for the same connective-tissue reason.
Measured reflux tells a different story. A 2026 study from two London tertiary centres (529 patients tested for swallowing or reflux symptoms) found that people with hEDS or hypermobility spectrum disorder were no more likely than other patients to have reflux disease confirmed by 24-hour pH-impedance testing (26.3% vs 33.0%), or to have oesophageal motility problems; burning felt without measurable excess acid reflux (functional heartburn) was the most common diagnosis in them (62.5%).
Symptoms include heartburn, regurgitation, chronic cough, hoarseness, chest pain that mimics cardiac pain, and dental erosion. Long-standing untreated reflux raises the risk of Barrett’s esophagus — a precancerous change in the esophageal lining. Some clinicians use endoscopic screening every 3–5 years when reflux has been ongoing for more than a decade.
Proton Pump Inhibitor Trade-Offs
Proton-pump inhibitors (omeprazole, pantoprazole, esomeprazole) work well for reflux but are not benign long-term. In Ehlers-Danlos syndrome patients specifically, two concerns loom larger than in the general population:
- Calcium absorption. Proton pump inhibitors (PPIs) reduce gastric acid, which reduces ionization of dietary calcium. Ehlers-Danlos syndrome patients already trend toward lower bone density; adding a proton pump inhibitor compounds the risk. With long-term proton pump inhibitor use, calcium citrate (which absorbs acid-independently) is often used rather than calcium carbonate.
- Small intestinal bacterial overgrowth risk. Gastric acid is the first line of defense against bacterial overgrowth. Suppressing it for years raises the chance of small intestinal bacterial overgrowth in a gut that is already mechanically vulnerable.
The approach commonly described: a proton pump inhibitor at the lowest effective dose, H2 blockers (famotidine) for milder reflux, raising the head of the bed 6–8 inches, no food in the three hours before lying down, and a review every 6–12 months of whether the proton pump inhibitor is still needed.
Organ Prolapse and Hernias
Collagen holds organs where they belong. When the collagen is faulty, gravity and pressure eventually win. A 2017 review by Fikree and colleagues describes structural problems in EDS such as hiatus hernias, visceroptosis (sagging abdominal organs), rectoceles and rectal prolapse.
- Rectal prolapse — the rectum slides through the anus, especially with straining. Can occur decades earlier than in non-EDS patients.
- Uterine prolapse and cystocele — common postpartum and post-menopause, but also seen in nulliparous young women with hEDS.
- Internal intussusception — the rectum telescopes into itself, causing incomplete evacuation, pelvic pressure, and the sensation of a blockage that won’t pass. Diagnosed by defecography (magnetic resonance imaging (MRI) or fluoroscopic).
- Hernias — umbilical, inguinal, incisional. All heal poorly because the surrounding tissue is friable. Surgical repair in Ehlers-Danlos syndrome patients has a higher recurrence rate, and mesh is often preferred over suture repair alone.
Pelvic-floor physical therapy is the first-line conservative treatment for prolapse. Surgical repair is reserved for symptomatic cases and is generally done by surgeons familiar with Ehlers-Danlos syndrome tissue fragility.
Early Diverticular Disease
Diverticula are small out-pouchings of the colon wall where the muscle layer is thin. In the general population, they are rare before age 40. In Ehlers-Danlos syndrome, earlier-onset diverticular disease is well-documented — sometimes appearing in patients in their 20s and 30s. The mechanism is the same connective-tissue weakness that produces hernias and prolapse, now applied to the colonic wall itself.
Symptoms range from intermittent left-lower-quadrant pain to frank diverticulitis (fever, tenderness, elevated white count). Imaging workup (computed tomography, CT) is identical to non-EDS diverticulitis, but the diagnosis is worth considering earlier in a young patient when Ehlers-Danlos syndrome is known.
The Dysautonomic Gut — Postural Orthostatic Tachycardia Syndrome Effects
The gut is an autonomic organ. When the autonomic nervous system misbehaves — as it does in the majority of hEDS patients with postural orthostatic tachycardia syndrome (POTS) — gut motility suffers directly. A 2013 review by Chelimsky and Chelimsky of the autonomic nervous system in functional gut disorders notes that limited data show orthostatic intolerance, such as reflex fainting and postural tachycardia syndrome, in a large subset of people with these disorders.
The postural orthostatic tachycardia syndrome-driven gut picture includes:
- Gastric stasis worsened by upright posture — blood pools in the lower body, splanchnic perfusion drops, and gastric squeeze weakens.
- Slow colonic transit and constipation — the migrating motor complex is sympathetically driven; sympathetic dysregulation slows the housekeeping wave.
- Postprandial hypotension — eating shunts blood to the gut, and an Ehlers-Danlos syndrome-POTS patient can feel faint, foggy, or profoundly fatigued for an hour after meals.
- Paradoxical diarrhea when sympathetic surges trigger urgent evacuation.
Volume loading (salt, fluids, compression garments) and postural orthostatic tachycardia syndrome-directed therapy often improve gut symptoms as a side effect — which is why the Ehlers-Danlos syndrome triad needs to be managed as a single system, not three separate problems.
Mast Cell Gastrointestinal Symptoms
Mast cells line the gut from the mouth to the anus. When they degranulate inappropriately — the hallmark of mast cell activation syndrome — the gastrointestinal tract is often the first place symptoms appear.
Typical mast cell activation syndrome (MCAS) gastrointestinal picture:
- Abdominal cramping within 15–60 minutes of eating certain foods (high-histamine foods are common triggers).
- Sudden-onset diarrhea, sometimes with flushing and heart racing.
- Bloating, nausea, and early satiety that wax and wane without obvious pattern.
- Food sensitivities that shift over time — a food tolerated yesterday triggers a reaction today.
Treatment layers H1 blockers (cetirizine, loratadine, fexofenadine) with H2 blockers (famotidine) and adds oral cromolyn sodium 100–200 mg 15–30 minutes before meals for direct stabilization of gut mast cells. A low-histamine diet and a low-FODMAP diet often overlap and are worth a structured trial under a dietitian’s guidance.
Eosinophilic Esophagitis and Gastritis
Eosinophilic esophagitis (EoE) and eosinophilic gastritis are increasingly recognized in Ehlers-Danlos syndrome cohorts, particularly in patients who also have atopic disease and mast cell activation syndrome features. Symptoms include food impaction, difficulty swallowing solids, chest pain with eating, and persistent reflux unresponsive to standard proton pump inhibitor therapy. Diagnosis requires endoscopy with multiple biopsies; treatment is usually topical swallowed steroids (budesonide or fluticasone), elimination diets, or biologics (dupilumab) in refractory cases.
Median Arcuate Ligament Syndrome (MALS)
MALS is compression of the celiac artery by the median arcuate ligament of the diaphragm. In people with normal connective tissue, the ligament sits clear of the artery. In Ehlers-Danlos syndrome, the shifted tissue geometry — combined with weight loss from gastroparesis — allows the ligament to pinch the vessel during expiration.
The classic MALS picture:
- Epigastric pain triggered by eating, often starting 15–30 minutes into a meal.
- Post-prandial nausea, weight loss, fear of eating.
- An epigastric bruit heard on exam, louder during expiration.
Screening is by mesenteric duplex ultrasound with inspiratory/expiratory maneuvers — a noninvasive test that measures celiac-artery flow velocity. Confirmation uses computed tomography or MR angiography. Treatment of symptomatic, imaging-confirmed MALS is laparoscopic release of the median arcuate ligament, sometimes combined with celiac ganglion neurolysis. Outcomes in Ehlers-Danlos syndrome cohorts are more variable than in the general population, and patient selection matters — MALS anatomy is common, but symptomatic MALS is rarer.
Superior Mesenteric Artery Syndrome
SMA syndrome is compression of the third part of the duodenum between the aorta behind it and the superior mesenteric artery in front of it. Normally, a fat pad keeps the two vessels apart. Weight loss, scoliosis, or loss of abdominal muscle tone (all common in Ehlers-Danlos syndrome) narrows the angle and pinches the duodenum.
Symptoms: post-prandial epigastric pain, vomiting of partially digested food, bloating that improves lying on the left side or in a knee-chest position, and further weight loss that worsens the anatomy in a vicious cycle. Diagnosis is by computed tomography with oral contrast showing the narrowed aortomesenteric angle. Treatment begins with nutritional rehabilitation (sometimes via NJ tube to restore the fat pad); surgical bypass (duodenojejunostomy) is reserved for refractory cases.
Dysmotility Workup
When symptoms don’t fit neatly into one category, a full motility panel sorts out what is happening where:
- Gastric emptying scintigraphy — 4-hour protocol, as described above.
- Whole-gut transit scintigraphy — measures transit through stomach, small bowel, and colon in a single study.
- Wireless motility capsule — a swallowable sensor that records pH, pressure, and temperature as it traverses the gastrointestinal tract, giving segmental transit times without radiation.
- Anorectal manometry and balloon expulsion test — for patients with constipation or incomplete evacuation to distinguish slow transit from pelvic floor dysfunction.
- Defecography — magnetic resonance imaging or fluoroscopic imaging of defecation to identify rectocele, intussusception, or pelvic descent.
- Breath testing — lactulose or glucose for small intestinal bacterial overgrowth; lactose, fructose for sugar malabsorption.
Insurance often balks at these studies. Approval is more likely when each symptom and failed treatment is documented in the chart, and a motility specialist’s referral helps considerably.
Nutrition Strategies
Eating is a project in moderate-to-severe Ehlers-Danlos syndrome gastrointestinal disease. The hierarchy of intervention:
- Small frequent meals — five or six small plates, never large ones.
- Liquid nutrition as needed — oral nutrition drinks, including plant-based formulas, for calorie insurance when solid food is failing.
- Elemental diet during flares — pre-digested amino-acid formulas (commercial elemental formulas or homemade versions) that require no digestion and starve small intestinal bacterial overgrowth bacteria. Typically run 2–3 weeks. See the Elemental Diet deep dive for protocols and cost strategies.
- NG or NJ tube feeding — for short- to medium-term failure-to-thrive situations.
- PEG (gastric) or PEG-J (jejunal) tubes — reserved for severe chronic cases where oral nutrition cannot maintain weight and hydration. Used by a minority of patients with severe gastroparesis or chronic intestinal pseudo-obstruction.
Overlap diets matter. A patient with hEDS + mast cell activation syndrome + small intestinal bacterial overgrowth may benefit from a combined low-histamine + low-FODMAP approach — but only for limited periods, and with a dietitian’s help, because combined restriction diets are nutritionally risky.
How often diet becomes a problem: in a 2024 UK study of 680 people with hEDS or hypermobility spectrum disorder, 62.1% had changed their diet in the past year and 62.3% regularly skipped meals. About 31.7% of those who had changed their diet needed nutrition support, and a positive screen for avoidant/restrictive food intake disorder (ARFID) — specifically fear of eating — raised the odds of needing it about five-fold (odds ratio 4.97).
vEDS and Spontaneous Bowel Rupture
Vascular Ehlers-Danlos syndrome (vEDS) is a separate and more dangerous subtype. The hallmark is fragility of arteries and hollow organs. Spontaneous sigmoid colon rupture is a recognized catastrophic event in vEDS, sometimes with little or no warning beyond abdominal pain.
Sudden severe abdominal pain in a vEDS patient is a sign hospitals treat as an emergency, needing urgent imaging (computed tomography) and surgical evaluation. Elective colonoscopy in vEDS is approached with great caution; many vEDS clinicians avoid it unless absolutely necessary because of perforation risk.
Details of vEDS management live on the Classical and Vascular Ehlers-Danlos syndrome page.
Surgery & Anesthesia Considerations
Any surgery in an Ehlers-Danlos syndrome patient is higher-stakes than in a non-EDS patient. Gastrointestinal surgery is no exception.
- Tissue friability. Sutures tear, tissue pulls apart, and anastomoses leak more often than in the general population. Surgeons familiar with Ehlers-Danlos syndrome use smaller, more frequent sutures, longer healing times, and mesh where appropriate.
- Longer hospital stays. Recovery is slower than in non-EDS patients.
- Elective-surgery thresholds are higher. Surgeons familiar with Ehlers-Danlos syndrome tend not to operate for marginal indications and weigh cosmetic or convenience procedures carefully.
- Bariatric surgery carries particular risk — anastomotic leaks, staple-line dehiscence, and internal hernias are all more common.
Anesthesia considerations specific to Ehlers-Danlos syndrome:
- Local anesthetic (lidocaine) is often reported to be less effective or shorter-acting in Ehlers-Danlos syndrome patients. This is patient-reported and partly supported by case literature. For this reason dentists and minor-procedure providers are often told in advance.
- Epidural and spinal anesthesia may require higher volumes or longer durations to achieve adequate block.
- Cervical spine instability in some hEDS patients makes intubation riskier, so the anesthesia team is usually told in advance.
- Autonomic lability (postural orthostatic tachycardia syndrome-type) responds poorly to anesthetic-induced vasodilation; larger blood-pressure swings are common.
Building Your Care Team
No single clinician manages all of this. The realistic roster:
- Gastrointestinal motility specialist — a gastroenterologist with specific training in dysmotility, small intestinal bacterial overgrowth, and functional gut disorders. Motility-focused clinics exist at most academic medical centers.
- Registered dietitian familiar with low-FODMAP, low-histamine, gastroparesis diets, and elemental feeding. Essential for navigating restrictive overlap diets without nutritional deficiency.
- Primary care physician willing to coordinate — the one person who holds the full picture and makes sure nothing falls through the cracks.
- Pain psychology or gastrointestinal-focused behavioral health — not because the pain is psychological, but because chronic gastrointestinal disease is exhausting and evidence-based cognitive strategies reduce symptom severity.
- Pelvic-floor physical therapist for prolapse, incomplete evacuation, or pelvic descent.
- Ehlers-Danlos syndrome-aware rheumatologist or geneticist to anchor the systemic picture.
You are the general contractor on this project. Keep a single document with every test result, every medication trial, every flare, and every referral — and bring it to every appointment. The gastroenterologist who sees you for 20 minutes cannot reconstruct a decade of dysfunction; your notes can.
Key Research Papers
- Fikree A, Chelimsky G, Collins H, Kovacic K, Aziz Q. Gastrointestinal involvement in the Ehlers-Danlos syndromes. Am J Med Genet C Semin Med Genet. 2017;175(1):181-187. — PubMed PMID: 28186368
- Nelson AD, Mouchli MA, Valentin N, Deyle D, Pichurin P, Acosta A, Camilleri M. Ehlers Danlos syndrome and gastrointestinal manifestations: a 20-year experience at Mayo Clinic. Neurogastroenterol Motil. 2015;27(11):1657-1666. — doi:10.1111/nmo.12665
- Zeitoun JD, Lefèvre JH, de Parades V, Séjourné C, Sobhani I, Coffin B, Hamonet C. Functional digestive symptoms and quality of life in patients with Ehlers-Danlos syndromes: results of a national cohort study on 134 patients. PLoS One. 2013;8(11):e80321. — doi:10.1371/journal.pone.0080321
- Fikree A, Grahame R, Aktar R, Farmer AD, Hakim AJ, Morris JK, Knowles CH, Aziz Q. A prospective evaluation of undiagnosed joint hypermobility syndrome in patients with gastrointestinal symptoms. Clin Gastroenterol Hepatol. 2014;12(10):1680-1687. — PubMed PMID: 24440216
- Butt MF, Dervin H, Hoshino S, Yazaki E, Gerard P, Sweis R, Sifrim D, Aziz Q, Zárate-López N, Fikree A. Esophageal Dysmotility and Gastroesophageal Reflux Disease Risk in Hypermobile Ehlers-Danlos Syndrome. Clin Gastroenterol Hepatol. 2026. — PubMed PMID: 42119906
- Camilleri M, Kuo B, Nguyen L, Vaughn VM, Petrey J, Greer K, Yadlapati R, Abell TL. ACG Clinical Guideline: Gastroparesis. Am J Gastroenterol. 2022;117(8):1197-1220. — PubMed PMID: 35926490
- Chelimsky G, Chelimsky TC. Gastrointestinal manifestations of pediatric autonomic disorders. Semin Pediatr Neurol. 2013;20(1):27-30. — PubMed PMID: 23465771
- Topan R, Pandya S, Williams S, Ruffle JK, Zarate-Lopez N, Aziz Q, Fikree A. Comprehensive Assessment of Nutrition and Dietary Influences in Hypermobile Ehlers-Danlos Syndrome-A Cross-Sectional Study. Am J Gastroenterol. 2024;119(4):727-738. — PubMed PMID: 37970870
- Chelimsky G, et al. Gastrointestinal dysfunction in autonomic disorders. Neurogastroenterol Motil. 2014. — Search PubMed
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on Ehlers-Danlos syndrome-related gastrointestinal disease:
- PubMed: Ehlers-Danlos and gastrointestinal involvement
- PubMed: Hypermobile EDS and gastroparesis
- PubMed: Ehlers-Danlos and small intestinal bacterial overgrowth
- PubMed: Ehlers-Danlos and irritable bowel syndrome
- PubMed: Ehlers-Danlos, hiatal hernia, and GERD
- PubMed: Median arcuate ligament syndrome and EDS
- PubMed: Superior mesenteric artery syndrome
- PubMed: Vascular EDS and bowel rupture
- PubMed: Mast cell activation and gastrointestinal disease
- PubMed: POTS and gastrointestinal motility
Connections
- Rheumatology
- Ehlers-Danlos Syndrome
- Hypermobile Ehlers-Danlos Syndrome and 2017 Diagnostic Criteria
- Classical and Vascular Ehlers-Danlos Syndrome
- Craniocervical Instability and AAI
- Postural Orthostatic Tachycardia Syndrome, Mast Cell Activation Syndrome and the Ehlers-Danlos Syndrome Triad
- Pain Management in hEDS
- Pediatric Ehlers-Danlos Syndrome and Transition of Care
- Physical Therapy and Joint Protection
- Pregnancy and Ehlers-Danlos Syndrome
- Small Intestinal Bacterial Overgrowth
- Rifaximin Protocols
- Elemental Diet for Small Intestinal Bacterial Overgrowth
- Irritable Bowel Syndrome
- Irritable Bowel Syndrome Rome IV Subtypes
- Gastroesophageal Reflux Disease
- Postural Orthostatic Tachycardia Syndrome
- Irritable Bowel Syndrome
- Gastroesophageal Reflux Disease (GERD)
- Postural Orthostatic Tachycardia Syndrome (POTS)
- Mast Cell Activation Syndrome (MCAS)
- Gastroenterology