⚠ Evidence warning: Clinical trials or other evidence do not support the claim that excision by an expert surgeon gives clearly better and longer-lasting pain relief than ablation, with long-term recurrence under 20%. This page keeps it as a report of what people, websites or other media say.
Laparoscopy: Excision vs. Ablation for Endometriosis
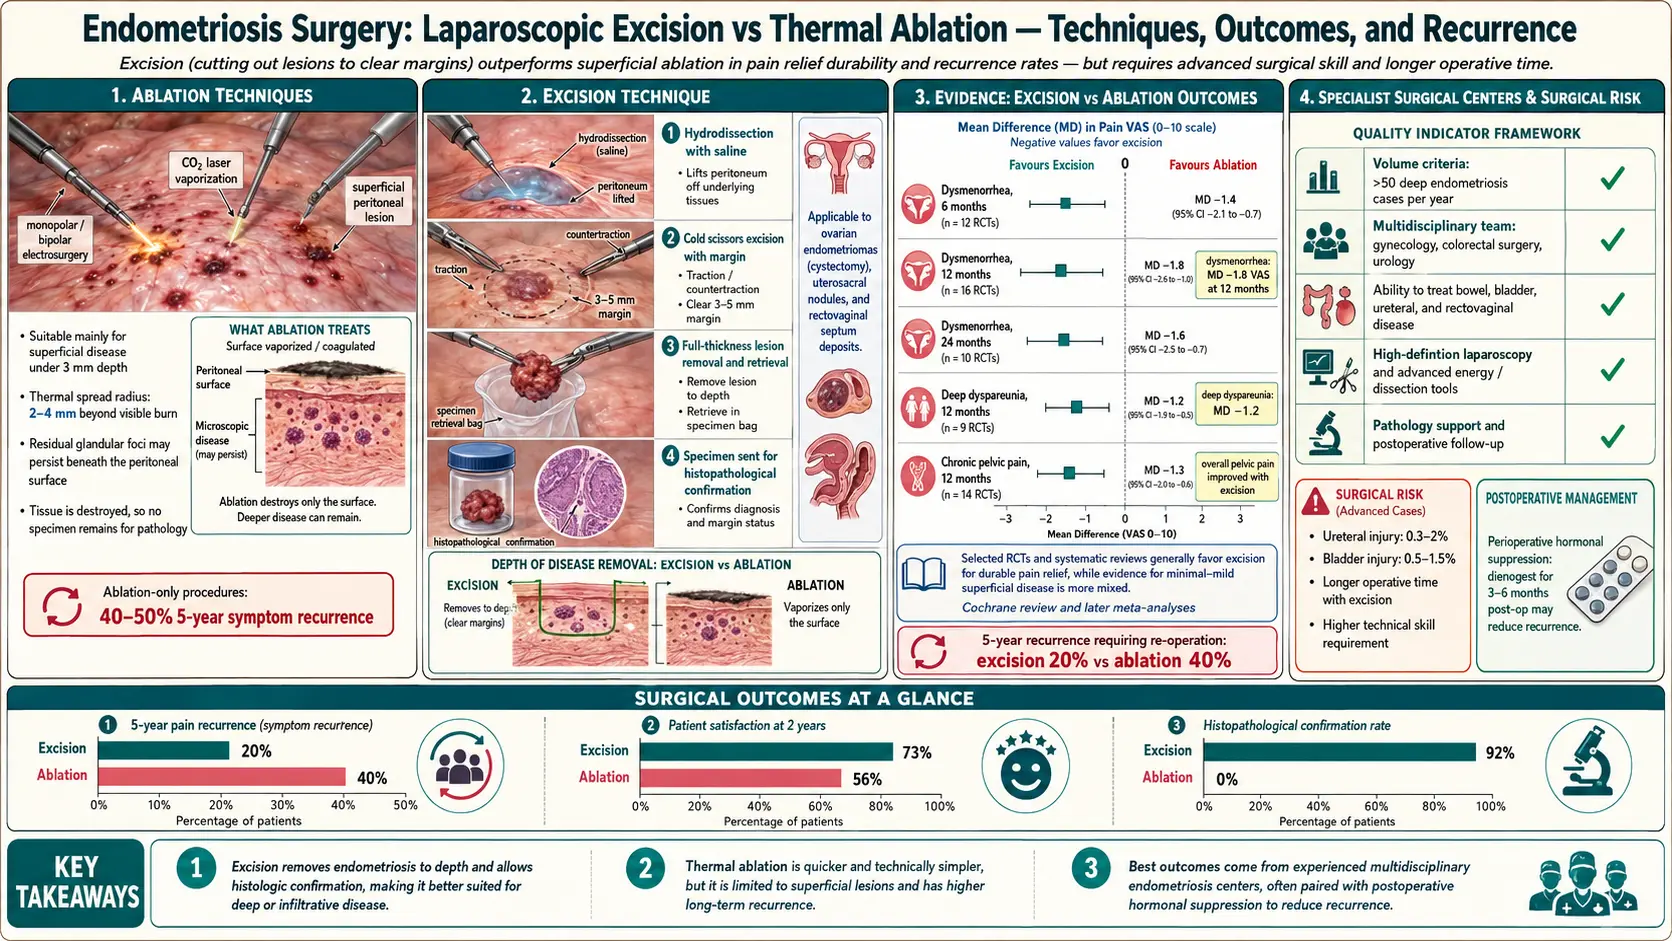
Table of Contents
- The Distinction — Excision vs. Ablation
- Why the Difference Matters
- The Evidence
- Recurrence Rates
- The “Generalist Gyn” Problem
- Finding an Excision Surgeon
- The “See and Treat” Approach
- Surgical Approach — Laparoscopy, Robotic, Multi-Disciplinary
- Pre-Op Preparation
- What Happens in Surgery
- Recovery
- After Excision — Pain, Suppression, Expectations
- When Recurrence Happens
- Hysterectomy — When It Is Actually Indicated
- Risks of Excision
- Costs and Insurance
- Key Research Papers
- Connections
- Featured Videos
The Distinction — Excision vs. Ablation
Two operations share the name “laparoscopy for endometriosis,” and they are not the same surgery. The choice between them is a central decision in endometriosis surgery.
Excision — sometimes called LAPEX (laparoscopic excision), wide excision, or deep excision — means the surgeon cuts the endometriosis lesion out. Using scissors, a CO2 laser in cutting mode, an ultrasonic surgical device, or a plasma-energy device, the surgeon traces around the lesion, slices beneath it, and removes the diseased tissue along with a margin of normal-looking tissue underneath. The specimen is placed in a bag and sent to pathology for confirmation. What is left behind is a clean defect in the peritoneum or organ surface, which is usually left to heal by secondary intention.
Ablation — also called fulguration, coagulation, or vaporization — means the surgeon destroys the surface of the lesion with heat. The tools are monopolar or bipolar cautery, argon beam, laser in vaporization mode, or a helium plasma device. The visible dark spot turns white, brown, or charred. Nothing is removed; nothing is sent to pathology. The surgery is faster, technically easier, and carries a lower intra-operative risk profile — which is exactly why it is still the most common procedure performed for endometriosis in the United States.
Both operations are done through the same 5–12 mm trocar ports. From the outside you cannot tell which one you received. From the inside, the distinction decides whether your disease is actually gone or just painted over.
Why the Difference Matters
Endometriosis is not a skin disease. Lesions extend below the visible surface. Pathology studies that serially section excised specimens find endometrial glands and stroma reaching 2 to 5 millimeters below what the eye sees on the peritoneum, and more than a centimeter deep in classic deep-infiltrating endometriosis (DIE) of the cul-de-sac, uterosacral ligaments, bowel, or bladder.
Ablation energy penetrates a tiny fraction of that. Superficial cautery destroys roughly 0.5 to 1 millimeter of tissue; even aggressive vaporization reaches 2–3 millimeters at best, and doing so on a bowel serosa or ureter invites injury. Burning the top of a deep lesion leaves the bulk of the disease alive underneath, where it continues to bleed, scar, and produce inflammatory cytokines each cycle. The visible “powder-burn” marking vanishes. The pain does not.
A 2026 randomized study measured this directly. In 34 patients, 153 endometriosis lesions were each ablated with one of three energy types and then cut out for testing under the microscope: 20 (13%) of the ablated lesions still contained endometriosis — 10 (20%) after electrical diathermy, 4 (8%) after argon beam coagulation and 6 (12%) after CO2 laser, a difference between the three that was not statistically significant. The authors concluded that excision is able to remove disease left behind after ablation.
This is the mechanical reason so many women report that a laparoscopy “helped for a few months and then the pain came back worse.” The disease never left. It regrew from a base that was never removed.
The Evidence
The evidence comparing excision with ablation has been building for two decades. The key landmarks:
Healey 2010 randomized controlled trial (RCT). Melbourne-based surgeon Martin Healey randomized 178 women with stage II–IV endometriosis to laparoscopic excision or ablation. The operations were done by supervised trainee gynecologists as primary surgeons. At 12 months there was no significant difference between ablation and excision in the fall in overall pain scores; the authors noted non-significant trends for pain with sex (dyspareunia) and pain with bowel movements (dyschezia). At the five-year follow-up (Healey 2014), all pain scores had fallen in both groups; excision gave a significantly greater reduction in pain with sex, and more women in the ablation group were still taking medical treatment for endometriosis. The authors concluded that excision is more effective than ablation “in some limited areas such as deep dyspareunia.” This remains the most-cited head-to-head trial.
Wright 2005 randomized trial. A small UK trial randomized women with mild endometriosis and chronic pelvic pain to excision or ablation. At 6 months both methods gave good symptom relief and less pelvic tenderness for most participants, “irrespective of the treatment modality”; two participants did not improve or got worse.
Riley 2019 randomized trial. In a trial at a single academic hospital, 73 women with minimal to mild (superficial) endometriosis were randomized during robot-assisted laparoscopy to excision (37) or ablation (36). The authors concluded that excision and ablation showed similar effectiveness for pain from superficial endometriosis; the only significant difference between the groups was in pain with sex at 6 months, which improved in the ablation group.
Cochrane review 2020. A Cochrane review of laparoscopic surgery for endometriosis included 14 randomized trials with 1,563 women. Compared with diagnostic laparoscopy only (looking without treating), it found it uncertain whether laparoscopic surgery reduces overall pain. For ablation compared with excision, it found “insufficient evidence to determine whether there was a difference in overall pain, measured at 12 months” (1 trial, 103 women, very low quality evidence). It found moderate quality evidence that laparoscopic surgery increases the rate of ongoing pregnancies in the womb confirmed by ultrasound compared with diagnostic laparoscopy only (odds ratio 1.89; 3 trials, 528 women); no study looked at live births.
Burks 2021 meta-analysis. A review of 4 randomized trials (346 women) with minimal to mild endometriosis found no significant difference between excision and ablation in period pain (dysmenorrhea), pain with bowel movements (dyschezia) or pain with sex (dyspareunia), either in the fall in pain scores from before surgery to 12 months or in pain scores at 12 months and beyond. The authors wrote that larger randomized trials with longer follow-up are needed for definitive conclusions.
Yeung 2014 review. In a 2014 narrative review, Patrick Yeung Jr wrote that rates of recurrence of endometriosis depend on how completely surgery removes the disease. The figure often cited by excision surgeons and patient communities — long-term recurrence under 20% after expert excision, compared with 40–60% reported for mixed or ablation-based groups — does not appear in that review’s abstract.
ESHRE 2022 Guideline. The European Society of Human Reproduction and Embryology (ESHRE) endometriosis guideline states that, when surgery is performed, clinicians “may consider excision instead of ablation of endometriosis to reduce endometriosis-associated pain” — a weak recommendation. For deep endometriosis, the guideline group “decided not to make any conclusions or recommendations on the techniques to be applied,” and it recommends that women with deep endometriosis are referred to a centre of expertise (a good-practice point). It recommends against hormone treatment before surgery to improve the immediate outcome of surgery for pain (strong recommendation) and states that women may be offered hormone treatment after surgery (weak recommendation).
Taken together: the randomized trials and reviews did not show an overall pain difference between excision and ablation at 12 months, and one trial found a greater benefit from excision for deep pain with sex at five years (Healey 2014). The ESHRE guideline gives excision a weak “may consider” recommendation, makes no recommendation on technique for deep disease, and recommends referral of deep endometriosis to a centre of expertise.
ESPriT2 trial. A UK trial whose protocol was published in 2023 plans to randomize 400 women from up to 70 National Health Service hospitals. Women with chronic pelvic pain in whom only isolated superficial peritoneal endometriosis is found at laparoscopy are randomized to surgical removal (by excision, ablation or both, as the surgeon prefers) or to diagnostic laparoscopy alone, to test whether removing this most common type of endometriosis reduces pain at 12 months.
Recurrence Rates
Recurrence is the honest metric. It is also the one generalist practices do not quote you pre-operatively.
- Ablation, generalist surgeon: roughly 20% symptomatic recurrence within the first year and 40–50% within five years. Repeat surgery rates in large cohorts reach 30–60% at ten years.
- Excision, high-volume specialist: published long-term series report under 20% recurrence at five to seven years, and about half of those recurrences are de novo disease in new locations rather than true regrowth of incompletely excised lesions.
- Excision, low-volume generalist: intermediate outcomes that blur into the ablation numbers. “Excision” on the op note does not guarantee an expert technique.
The surgeon’s experience predicts the result far more than the brand of the instrument in their hand.
The “Generalist Gyn” Problem
Most obstetrician-gynecologists finish residency comfortable with hysterectomy, tubal ligation, ovarian cystectomy, and superficial ablation of visible endometriosis spots. They have not been trained to dissect a ureter free of fibrotic endometriosis, shave an implant off the rectal serosa, or resect a segment of bladder. Those skills require a post-residency minimally invasive gynecologic surgery (MIGS) fellowship or years of high-volume endometriosis practice.
That training gap is the real reason ablation is still so common. A generalist faced with stage III or IV disease at the time of surgery has three options: abort and refer, do a superficial burn and close, or attempt a dissection beyond their comfort level. Many choose option two. The operative report reads “endometriosis identified and ablated.” The patient wakes up told the surgery was a success. The disease sits intact underneath the char.
This is not an accusation of bad faith. It is the predictable result of a specialty where true endometriosis surgeons are rare and referral networks are weak. The burden of finding the right surgeon falls on the patient.
Finding an Excision Surgeon
There are a small number of reliable ways to identify surgeons whose practice is dedicated to endometriosis excision:
- A large private online patient education group maintains a vetted list of excision surgeons worldwide. Inclusion requires submitting operative reports and patient outcome data for review. The list is the single most-used patient-community resource in the United States.
- A surgeon-directory platform requires blind video review of excision surgeries by other specialists before listing. It is newer and smaller than the online group’s list but overlaps heavily.
- AAGL Fellowship directory. The AAGL (aagl.org) maintains a list of MIGS fellowship graduates. Not all MIGS fellows specialize in endometriosis, but the baseline training is appropriate.
- Academic endometriosis centers. Specialist excision centers and some university hospitals run high-volume excision programs with multidisciplinary teams.
The screening question excision-focused patient communities put first at a consult is: “What percentage of your surgical practice is endometriosis excision?” Those communities look for a number above 75%, and contrast it with a general gynecologist who does four endometriosis cases a year among hundreds of hysterectomies. Their follow-up questions: How many excisions are performed per year? (Their benchmark: 100+.) Is excised tissue sent to pathology? (They treat yes as essential.) Does a colorectal surgeon and urologist work in the same operating room when needed? (Yes for suspected deep disease.) What is the conversion-to-laparotomy rate? (Low single digits.)
The “See and Treat” Approach
Historically, women were sent for a “diagnostic laparoscopy” the surgeon peeked, confirmed endometriosis, took a biopsy, and closed. The treatment was scheduled as a separate surgery months later. This is now considered obsolete and harmful. Every laparoscopy carries anesthesia and surgical risk; doing two when one would suffice doubles that risk for no benefit.
The modern standard is see and treat: the pre-operative consent authorizes the surgeon to excise any endometriosis found during the same procedure. A consent for diagnosis only does not cover treating the disease found during that operation. Patients seeking excision commonly ask for combined diagnosis-and-treatment consent and for written confirmation that the surgeon is prepared to excise (not ablate) whatever is found, up to and including bowel shaving, ureterolysis, and disc resection if the team is qualified.
Surgical Approach — Laparoscopy, Robotic, Multi-Disciplinary
Standard laparoscopy uses three to five small incisions: a 10–12 mm umbilical port for the camera and 5 mm working ports in the lower abdomen. It is the default for nearly all endometriosis surgery. Pain, recovery time, and cosmetic outcome are all better than open surgery (laparotomy), and exposure of the pelvis is arguably superior because of the magnified camera view.
Robotic laparoscopy (robot-assisted surgery) is marketed aggressively but is not inherently better for endometriosis. It offers the surgeon wristed instruments and 3D vision, which some find helpful for fine suturing, but it also removes tactile feedback and costs more per case. Outcomes in head-to-head series are similar to standard laparoscopy in experienced hands, so the surgeon’s experience matters more than the robot.
Laparotomy (a single larger incision) is now reserved for rare catastrophic cases — massive frozen pelvis, hemorrhage, or extensive bowel involvement where minimally invasive dissection is unsafe. A surgeon who defaults to laparotomy for routine endometriosis is behind the standard of care.
Multi-disciplinary teams are the differentiator at expert centers. Deep disease frequently involves the bowel, bladder, or ureter, and a gynecologist operating solo is not the right person to resect a segment of rectum or reimplant a ureter. High-volume endometriosis programs schedule a colorectal surgeon on standby for bowel involvement and a urologist for bladder or ureteric disease. Asking whether this is arranged pre-operatively is a legitimate and expected question.
Pre-Op Preparation
Pre-operative instructions vary by surgeon, but most include some combination of:
- Mechanical bowel prep (polyethylene glycol solution or similar the day before surgery) when bowel involvement is suspected on imaging or symptoms. An empty bowel is easier to mobilize and reduces contamination if a resection becomes necessary.
- Clear-liquid diet the day before; nothing by mouth after midnight.
- Stopping nonsteroidal anti-inflammatory drugs (NSAIDs) (ibuprofen, naproxen, aspirin) 5–7 days pre-op, to reduce bleeding risk. Acetaminophen is usually allowed.
- Stopping anticoagulants on a set schedule — warfarin, direct oral anticoagulants (DOACs) (apixaban, rivaroxaban), and P2Y12 inhibitors all have specific hold intervals.
- Hormonal pre-treatment is controversial. Some surgeons prescribe a short course of gonadotropin-releasing hormone (GnRH) agonist or continuous progestin pre-op to quiet the disease; others argue this shrinks lesions just enough to make them harder to see and excise completely. The 2022 ESHRE guideline recommends against prescribing hormone treatment before surgery to improve the immediate outcome of surgery for pain in women with endometriosis (a strong recommendation). Surgeons differ in their preference and reasoning.
- Showering with chlorhexidine the night before and the morning of surgery, to reduce skin flora.
What Happens in Surgery
Under general anesthesia, a Foley catheter is placed to keep the bladder empty. The umbilical trocar goes in first, the abdomen is insufflated with CO2, and a 5 or 10 mm camera is introduced. Additional 5 mm working ports are placed in the lower abdomen under direct vision.
The surgeon performs a systematic survey of the peritoneum: anterior and posterior cul-de-sac, uterosacral ligaments, broad ligament, ovarian fossae, bladder dome, appendix, cecum, sigmoid, diaphragm, and upper abdomen. Lesions are mapped and photographed. Ovarian endometriomas are drained and the cyst wall stripped. Deep lesions are dissected out with scissors or laser, with meticulous hemostasis. The ureter is identified and traced along its pelvic course wherever dissection approaches it. Any bowel or bladder disease is handled by the appropriate specialist.
Coexisting fibroids, ovarian cysts, or adhesions are addressed in the same operation when safe. Excised tissue is extracted through the umbilical port in a specimen bag and sent to pathology. Copious irrigation, a final hemostasis check, port closure, and the patient goes to recovery.
Recovery
For straightforward excision without bowel resection, most patients are discharged the same day or after one overnight stay. Bowel-resection cases usually stay two to four nights.
- Days 1–3: shoulder-tip pain from residual CO2 gas, abdominal soreness, sometimes nausea. Walking short distances starts immediately.
- Week 1: fatigue dominates. Most people off work. Bowel function returning.
- Weeks 2–3: most return to desk-based work. Driving resumes once off narcotics and able to brake hard without guarding.
- Weeks 4–6: lifting and vigorous exercise resume gradually. Pelvic rest (no tampons, no penetrative intercourse) is standard for 4–6 weeks.
- Week 6: post-op visit, review of pathology, discussion of next steps.
Warning signs that need urgent call-back: fever over 101°F, worsening abdominal pain after day 3, unrelenting nausea and vomiting, inability to urinate, or rectal bleeding. Ureteric or bowel injuries sometimes declare themselves 3–7 days post-op and require prompt recognition.
After Excision — Pain, Suppression, Expectations
Most women who have true wide excision by an expert surgeon report significant and durable pain improvement, often dramatic. Published patient-reported outcomes show 60–80% reporting much better pain at one to two years. Dyspareunia, dyschezia, and cyclic pain all respond.
A minority do not get the relief they expected, and this is important to understand before surgery so you are not devastated after. Reasons include:
- Coexisting adenomyosis (see the Adenomyosis Overlap article) — excision of external endometriosis does nothing for disease inside the uterine wall.
- Pelvic floor dysfunction and central sensitization — the nervous system has been in a pain loop for years and the pain pattern persists after the peripheral disease is gone. This is the major reason some patients feel let down post-op. See the Pelvic Floor & Central Sensitization article.
- Incomplete excision — the surgeon was not expert enough, or disease was microscopic and missed.
- Irritable bowel or interstitial cystitis overlap, which share the same pelvic-nerve distribution.
Whether to continue hormonal suppression after a complete excision is debated. Purist excisionists argue that if the surgery was truly complete, no medical suppression is needed and none should be pushed. Others prescribe continuous combined hormonal contraception or progestins to reduce the chance of de novo disease. A middle course between the two is to monitor symptoms for three to six months post-op and add suppression only if pain recurs or imaging shows new lesions. The 2022 ESHRE guideline states that women may be offered hormone treatment after surgery to improve its immediate outcome for pain (weak recommendation); after surgery for an ovarian endometrioma in women not immediately seeking pregnancy, it recommends long-term hormone treatment (for example, combined hormonal contraceptives) to prevent the endometrioma and its symptoms from coming back (strong recommendation).
When Recurrence Happens
Persistent or recurrent pain after excision demands a careful re-evaluation rather than a reflex second surgery. Steps in order:
- Review the prior operative report and pathology. Was it truly excision or was ablation done under the label “excision”?
- Assess pelvic floor, adenomyosis, bladder, and bowel as alternative pain drivers.
- Consider medical management escalation — GnRH antagonists (elagolix, relugolix), progestins, or continuous combined hormonal contraception.
- If imaging or symptoms point to a clear surgical target, a second excision by a high-volume specialist is reasonable. Outcomes in expert second-look surgery are generally good.
What is rarely reasonable is a third or fourth ablation by a generalist. Each repeat surgery adds adhesions without treating the underlying disease.
Hysterectomy — When It Is Actually Indicated
Hysterectomy is widely and incorrectly sold as a “cure” for endometriosis. It is not. Endometriosis is, by definition, tissue that grows outside the uterus — removing the uterus does not remove the disease. Women who have had hysterectomies without proper excision routinely continue to have pain, sometimes worse.
Hysterectomy is appropriately indicated when:
- There is coexisting adenomyosis causing severe dysmenorrhea and menorrhagia that has failed other treatment. Hysterectomy is definitive for adenomyosis.
- The patient has completed childbearing and has fibroids, abnormal bleeding, or other uterine pathology in addition to endometriosis.
- Cervical or uterine pathology in its own right warrants removal.
The 2022 ESHRE guideline states that clinicians can consider hysterectomy (with or without removal of the ovaries) with removal of all visible endometriosis lesions in women who no longer wish to conceive and did not respond to more conservative treatments (a weak recommendation), and that women should be informed that hysterectomy “will not necessarily cure the symptoms or the disease.” When hysterectomy is performed, the guideline group prefers a total hysterectomy. On keeping the ovaries, it states that “the long-term consequences of early menopause and possible need for hormone replacement therapy should be considered”; bilateral oophorectomy drops endogenous estrogen to menopausal levels and brings its own long-term bone, cardiovascular, and cognitive consequences. Ovary-sparing hysterectomy plus excision is the modern standard for women in whom hysterectomy is appropriate.
Risks of Excision
All abdominal surgery carries risk, and endometriosis excision in particular dissects near structures that are expensive to injure. Honest risks:
- Bowel injury — serosal tear, enterotomy, or delayed perforation. Roughly 1–2% in high-volume centers, higher in low-volume practices.
- Ureteric injury — transection, thermal damage, or stricture. Under 1% in expert hands; higher when disease is dense on the pelvic sidewall.
- Bladder injury — cystotomy, usually recognized and repaired intra-operatively.
- Bleeding requiring transfusion — uncommon but not rare in extensive dissection.
- Adhesion formation — probably lower with excision than with cautery because the raw surfaces are clean, but adhesions still occur.
- Persistent pain — not truly a surgical complication, but the most emotionally difficult outcome when it happens.
- Anesthesia risks — standard and low in healthy patients.
All of these rates are lower — often several-fold lower — when the operating surgeon does hundreds of these cases a year. Volume is protective.
Costs and Insurance
Here is where the system breaks down. Excision specialists have long exit ramps from insurance networks because reimbursement for a complex 6-hour excision is often set by insurers at the same rate as a 45-minute ablation. Going out-of-network is a rational business response but leaves patients paying significant out-of-pocket costs — often $15,000 to $40,000 for surgeon fees alone, with facility and anesthesia billed separately and often in-network.
Ways patients cover the cost:
- Single-case agreement (SCA) with the insurer. When a patient documents that no in-network surgeon in the area is qualified to excise deep endometriosis, many insurers agree to pay the out-of-network surgeon at in-network rates. The surgeon’s billing office usually has templates and experience with this process.
- Superbill submitted for out-of-network reimbursement. Even when not paid in full, it counts toward the out-of-network deductible and maximum.
- Health savings account (HSA) and flexible spending account (FSA) funds can pay eligible expenses. Surgery and anesthesia are qualifying expenses.
- Financing: medical financing plans offer deferred-interest terms. Under those terms, a balance not paid within the deferred period is often charged interest back to day one.
- Payment plans: most specialty practices will structure 12–24-month direct payment plans for self-pay patients.
- Facility fees: the same surgeon operating at an ambulatory surgery center rather than a hospital can save 30–50% on facility charges.
Patient advocates describe it as unjust that appropriate surgical care for a disease affecting roughly one in ten women is priced out of reach for most families. Patient advocacy organizations continue to push for parity coverage. In the meantime, knowing the tactics above is the difference between getting the right surgery and settling for the wrong one.
Key Research Papers
- Healey M, Ang WC, Cheng C. Surgical treatment of endometriosis: a prospective randomized double-blinded trial comparing excision and ablation. Fertil Steril. 2010;94(7):2536–2540. — doi:10.1016/j.fertnstert.2010.02.044
- Yeung P Jr. The laparoscopic management of endometriosis in patients with pelvic pain. Obstet Gynecol Clin North Am. 2014;41(3):371–383. — doi:10.1016/j.ogc.2014.05.002
- Becker CM, Bokor A, Heikinheimo O, et al. ESHRE guideline: endometriosis. Hum Reprod Open. 2022;2022(2):hoac009. — doi:10.1093/hropen/hoac009
- Healey M, Cheng C, Kaur H. To excise or ablate endometriosis? A prospective randomized double-blinded trial after 5-year follow-up. J Minim Invasive Gynecol. 2014;21(6):999–1004. — PubMed PMID: 24768960
- Wright J, Lotfallah H, Jones K, Lovell D. A randomized trial of excision versus ablation for mild endometriosis. Fertil Steril. 2005;83(6):1830–1836. — PubMed PMID: 15950657
- Riley KA, Benton AS, Deimling TA, Kunselman AR, Harkins GJ. Surgical Excision Versus Ablation for Superficial Endometriosis-Associated Pain: A Randomized Controlled Trial. J Minim Invasive Gynecol. 2019;26(1):71–77. — PubMed PMID: 29609032
- Bafort C, Beebeejaun Y, Tomassetti C, Bosteels J, Duffy JM. Laparoscopic surgery for endometriosis. Cochrane Database Syst Rev. 2020;10(10):CD011031. — PubMed PMID: 33095458
- Burks C, Lee M, DeSarno M, Findley J, Flyckt R. Excision versus Ablation for Management of Minimal to Mild Endometriosis: A Systematic Review and Meta-analysis. J Minim Invasive Gynecol. 2021;28(3):587–597. — PubMed PMID: 33310168
- Mackenzie SC, Stephen J, Williams L, et al. Effectiveness of laparoscopic removal of isolated superficial peritoneal endometriosis for the management of chronic pelvic pain in women (ESPriT2): protocol for a multi-centre randomised controlled trial. Trials. 2023;24(1):425. — PubMed PMID: 37349849
- Namaky DD, Carrel-Lammert M, Hoehn J, Yeung J. Histologic Comparison of Ablative Techniques for Endometriosis: A Randomized Trial. J Minim Invasive Gynecol. 2026;33(8):1195–1201. — PubMed PMID: 41525928
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on surgical management of endometriosis:
- PubMed: Excision versus ablation for endometriosis
- PubMed: Laparoscopic excision of deep infiltrating endometriosis
- PubMed: Endometriosis recurrence after excision
- PubMed: Bowel endometriosis and colorectal surgery
- PubMed: Ureteral endometriosis and laparoscopic management
- PubMed: Robotic versus conventional laparoscopy for endometriosis
- PubMed: Hysterectomy outcomes in endometriosis
- PubMed: Surgeon volume and outcomes in endometriosis surgery
Connections
- Reproductive Medicine
- Adenomyosis Overlap
- Pelvic Floor Therapy and Central Sensitization
- Endometriosis
- Diagnosis Delay and Imaging
- Hormonal Therapy Options
- Endo Belly and Gut Connection
- Fertility and Endometriosis
- Diet and Lifestyle
- Bladder and Bowel Endometriosis
- Infertility
- Uterine Fibroids
- Chronic Pain
- Ovarian Cysts
- Interstitial Cystitis
- Full Body Magnetic Resonance Imaging
- Polycystic Ovary Syndrome
- Vitamin D3
- Magnesium