Endometriosis Diagnosis Delay and Imaging
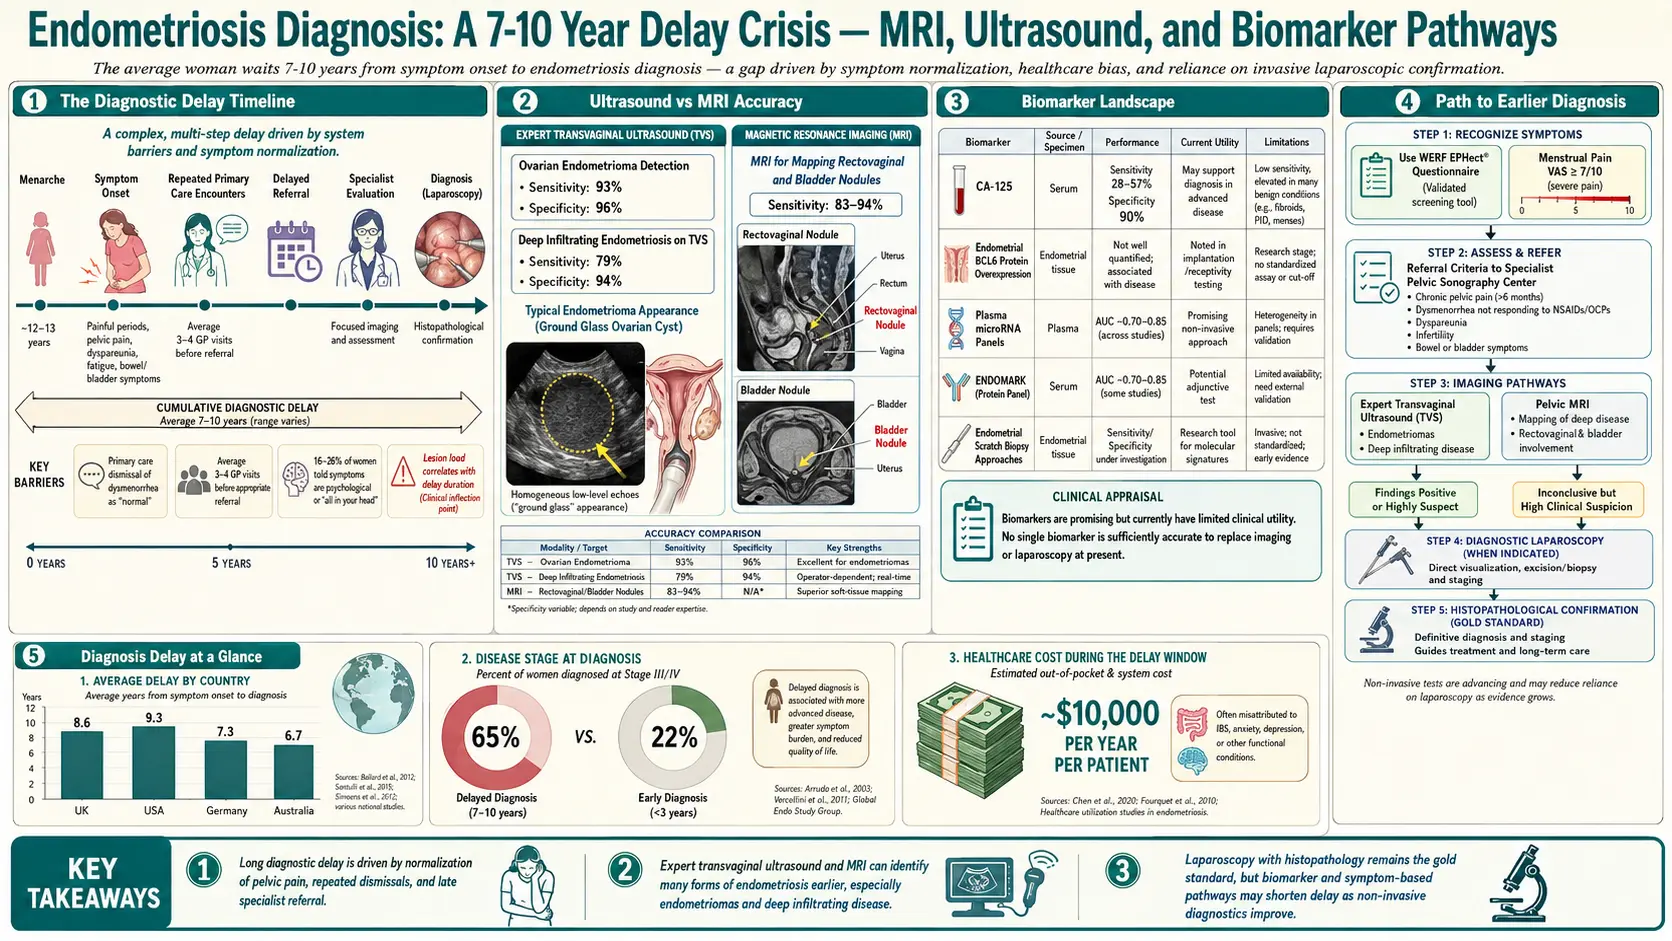
Table of Contents
- The 4–11 Year Diagnostic Delay — Why It Happens
- What Endometriosis Is — In Plain Language
- Clinical Diagnosis and Empirical Treatment
- Transvaginal Ultrasound
- Dynamic "Sliding Sign" Ultrasound
- Magnetic Resonance Imaging with Pelvic Endometriosis Protocol
- Diagnostic Laparoscopy — the Traditional Gold Standard
- CA-125 — Why It Is Not a Screening Test
- Emerging Biomarkers
- Wording Patients Use at Gynecology Appointments
- How Patients Find an Excision Specialist
- Symptom Tracking to Build Your Case
- When Patients Seek a New Clinician
- What to Expect After Diagnosis
- Red Flags for Urgent Workup
- Key Research Papers
- Connections
- Featured Videos
If your pain has been dismissed for years, you are not alone — and you are not exaggerating. A 2019 expert review describes a well-established delay of 4 to 11 years from first symptom to surgical diagnosis of endometriosis, not because the disease is rare but because the system normalizes menstrual pain and because the tools to see endometriosis require specialist training. This article is a practical map through the diagnostic process.
The 4–11 Year Diagnostic Delay — Why It Happens
A 2019 expert call to action describes “the well-established delay of 4-11 years” between first symptom onset and surgical diagnosis of endometriosis — 4 to 11 years. Some cohorts report longer. The delay has four compounding causes.
Symptoms are dismissed as "normal period pain." Dysmenorrhea is framed as something to tolerate. Pain that keeps you home from school or work is not normal; pain that makes you vomit is not normal; pain that pain medication does not touch is not normal. Each of those is a reason for imaging and referral, not reassurance.
Pain normalization inside the patient. If you have hurt since your first period, you have no baseline for a pain-free cycle. Patients routinely under-report on a 1–10 scale because their personal 5 is what most people would call a 9.
The primary care gap. Most pelvic pain first lands in front of a general practitioner. Endometriosis is barely covered in medical school. The symptom pattern gets rerouted to ibuprofen, birth control pills, and "come back if it gets worse." Worse is rarely defined.
Multiple mis-diagnoses before the right one. The symptom map of endometriosis overlaps with several common conditions, and patients are often told they have one of them first:
- Irritable bowel syndrome (IBS) — because bowel symptoms flare with the cycle, especially if bowel endometriosis is present.
- Interstitial cystitis / painful bladder syndrome — because bladder endometriosis or referred pelvic pain causes urinary urgency.
- Pelvic inflammatory disease (PID) — because the pain is deep and cyclic, and clinicians default to infection.
- Anxiety, depression, or "somatization" — the oldest and most damaging misdiagnosis. Pain plus female plus negative imaging often produces a psychiatric referral instead of a surgical one.
- Ovarian cysts of unclear origin — endometriomas get drained or watched without anyone naming the underlying disease.
You may have been told several of these. None of them rule out endometriosis, and several (especially irritable bowel syndrome and interstitial cystitis) commonly coexist with it.
A 2025 meta-analysis of 10 studies weighed where the delay comes from. Patient-related factors showed a significant pooled effect (standardized mean difference, SMD 1.94), with delays in seeking medical attention contributing most; provider-related factors, including misdiagnosis and reliance on non-specific tests, also had a substantial pooled effect (SMD 2.00). System factors such as referral pathways and geographic differences could not be analyzed separately for lack of data. The authors point to public education to combat symptom normalization and stigmatization, more comprehensive provider training, and streamlined diagnostic pathways as ways to close the gap.
What Endometriosis Is — In Plain Language
Endometriosis is tissue that behaves like the lining of the uterus but grows outside it — on the ovaries, fallopian tubes, bowel, bladder, peritoneum (the sheet that lines the pelvic cavity), and, less commonly, the diaphragm, lungs, or surgical scars. With every menstrual cycle, these deposits respond to the same hormonal signals as the uterine lining: they inflame, bleed, and provoke scarring in tissues that have no way to shed blood. Over years, the inflammation produces adhesions (bands of scar tissue gluing organs together) and deep infiltrating lesions that invade the bowel wall, ureters, or rectovaginal space.
Two ideas about endometriosis still circulate in clinics and among relatives, and both are wrong.
"Just get pregnant — that cures it." Pregnancy sometimes pauses symptoms because ovulation stops and estrogen patterns shift, but the disease does not disappear. Many patients flare harder postpartum. Endometriosis is also a leading cause of infertility, so "get pregnant" is often not an option without reproductive assistance — and having a child is not a treatment for a disease.
"Just have a hysterectomy." Endometriosis is, by definition, tissue outside the uterus. Removing the uterus does not remove the disease. Hysterectomy with ovary removal can help if adenomyosis (a separate condition involving the uterine muscle) is also present, but it does not cure endometriosis and is not an appropriate first-line treatment, especially for young patients. The correct surgery is excision of the implants themselves.
Clinical Diagnosis and Empirical Treatment
Modern guidelines, including the European Society of Human Reproduction and Embryology (ESHRE) 2022 Endometriosis Guideline, no longer require surgical confirmation before starting treatment. If your symptom pattern fits — severe dysmenorrhea, cyclic pelvic pain, dyspareunia (pain with sex), cyclic bowel or bladder pain, infertility — a clinician can make a clinical diagnosis and begin empirical treatment with nonsteroidal anti-inflammatory drugs (NSAIDs) and hormonal therapy. This is a legitimate starting point and it shortens the delay.
That guideline contains 109 recommendations, based on papers published up to 1 December 2020, and its authors state that it “outlines the diagnostic process for endometriosis, which challenges laparoscopy and histology as gold standard diagnostic tests.”
What clinical diagnosis is not: a reason to refuse imaging or surgery when symptoms fail to respond. If three to six months of a first-line hormonal regimen does not improve your pain, the next step is advanced imaging and a surgical referral — not another brand of pill.
Transvaginal Ultrasound
Transvaginal ultrasound (TVUS) is the first-line imaging study. It is cheap, widely available, and safe. What it sees depends almost entirely on who is doing the scan.
What a standard TVUS can show:
- Endometriomas (ovarian "chocolate cysts") — highly characteristic homogeneous low-level echoes, often called the "ground-glass" appearance. A 2016 Cochrane review found transvaginal ultrasound detected endometriomas with a sensitivity of 0.93 and a specificity of 0.96 (eight studies, 765 participants); for magnetic resonance imaging the figures were 0.95 and 0.91 (three studies, 179 participants).
- Hydrosalpinx (fluid-filled fallopian tubes) — a common coexisting finding.
- Adenomyosis features in the uterine wall (asymmetric thickening, myometrial cysts, linear striations).
What a standard TVUS cannot show:
- Peritoneal (superficial) endometriosis — these flat implants on the pelvic sidewalls are invisible on routine imaging. A negative ultrasound does not rule out endometriosis. Full stop. In the same Cochrane review, no imaging test met the criteria to replace diagnostic surgery, or to serve as a triage test, for pelvic endometriosis.
- Small deep infiltrating lesions outside the routine scan zones.
A specialist endometriosis sonographer performing a targeted scan can see much more: deep infiltrating lesions in the rectovaginal septum, uterosacral ligament nodules, bladder-wall disease, and bowel involvement. These scans take 30–60 minutes and follow the International Deep Endometriosis Analysis (IDEA) consensus protocol. Most general radiology practices do not offer this. The scan goes by names such as "advanced pelvic ultrasound for endometriosis" or "IDEA-protocol transvaginal ultrasound", and it is offered mainly at specialist centers.
Dynamic "Sliding Sign" Ultrasound
The sliding sign is a real-time maneuver performed during a specialist ultrasound. The sonographer uses gentle pressure with the probe to watch whether the anterior rectal wall slides freely against the back of the uterus and cervix. In a normal pelvis, the two surfaces glide apart. In a pelvis with deep infiltrating endometriosis, adhesions fix them together — the sliding sign is negative, meaning the organs are stuck.
A negative sliding sign is a strong predictor of pouch of Douglas obliteration, the frozen-pelvis pattern surgeons need to know about before they operate. It also correlates with bowel involvement and predicts more complex surgery. In skilled hands this single maneuver maps the geography of your disease before anyone opens you up — and is the best argument for traveling to a specialist center.
A 2022 meta-analysis of eight studies, using laparoscopy as the reference, measured how well the sliding sign on transvaginal ultrasound performs. For pouch of Douglas obliteration (938 patients) the pooled sensitivity was 88% and specificity 94%; for bowel involvement (963 patients) sensitivity was 81% and specificity 95%. The authors conclude that the sign has good diagnostic performance in women with suspected endometriosis.
Magnetic Resonance Imaging with Pelvic Endometriosis Protocol
Pelvic magnetic resonance imaging (MRI) is the second imaging tool. It is ordered when ultrasound is suggestive but incomplete, when deep infiltrating disease is suspected, or when surgical planning requires a roadmap. A generic pelvic magnetic resonance imaging is not the same as a dedicated endometriosis protocol. The dedicated study is called a pelvic magnetic resonance imaging with endometriosis protocol, and it includes:
- Thin-section T2-weighted sequences through the entire pelvis.
- Fat-suppressed T1 sequences to detect blood products in implants.
- Vaginal and rectal opacification gel in some centers to improve contrast at the cul-de-sac and rectovaginal septum.
- A radiologist with endometriosis-specific experience reading the study.
What magnetic resonance imaging shows well: deep infiltrating endometriosis, rectovaginal and uterosacral nodules, bladder-wall lesions, bowel involvement (with measurement of depth of invasion), endometriomas, adenomyosis, and adhesion patterns. It is especially valuable for surgical planning because it shows the ureters and can flag hydronephrosis from ureteral compression.
What magnetic resonance imaging does not reliably show: superficial peritoneal endometriosis — the same blind spot as ultrasound. A clean magnetic resonance imaging in a patient with classic symptoms still does not rule out disease. Surgery remains necessary when imaging is negative but symptoms persist.
Diagnostic Laparoscopy — the Traditional Gold Standard
Laparoscopy is minimally invasive surgery in which a camera is inserted through a small incision near the navel and the pelvis is inspected directly. It has long been treated as the gold standard for diagnosing endometriosis — a status the ESHRE 2022 guideline now challenges — and it is the only test that can see superficial peritoneal disease. Visual appearance is confirmed by biopsy of representative lesions.
Modern practice follows a "see and treat" approach: at the same surgery that confirms the diagnosis, a trained surgeon excises the implants. This is not a quick look-and-close procedure — it is therapeutic as well as diagnostic. For this reason, a diagnostic laparoscopy done by a surgeon qualified to do the excision can confirm and treat in one operation. Being diagnosed by a general gynecologist, closed back up, and then referred on means going through two surgeries. See Excision vs Ablation for why the surgeon's technique matters as much as the fact of surgery.
Laparoscopy is not risk-free — it is a general-anesthesia operation with the usual surgical risks — but in experienced hands it is same-day or overnight, and recovery is measured in weeks, not months.
CA-125 — Why It Is Not a Screening Test
CA-125 (cancer antigen 125) is a blood protein that can be raised in endometriosis — but also in normal menstruation, ovulation, pregnancy, fibroids, PID, and ovarian cancer. A 2016 meta-analysis (14 studies, 2,920 participants, cut-off 30 units/mL) found a pooled specificity of 93% but a sensitivity of only 52%. In plain words: a raised result points strongly toward endometriosis (the authors call it a good “rule-in” test), but it picked up only 52% of the cases. Sensitivity was 63% in moderate or severe endometriosis and 24% in minimal disease. A negative test, the authors write, “is unable to rule out endometriosis.” Its sensitivity is too low for screening. Other uses include tracking a known endometrioma or evaluating an ovarian mass for cancer risk. "Your CA-125 is normal so you probably do not have endometriosis" is a wrong statement.
Emerging Biomarkers
Several blood and menstrual-effluent tests are in development and marketed directly to patients. They remain investigational.
- Menstrual effluent cell diagnostics — cells and molecular markers from menstrual blood. Sensitivity and specificity are still being established.
- MicroRNA panels — plasma microRNA (miRNA) signatures with reasonable accuracy in research cohorts; commercial versions exist.
- Proteomic panels — combinations of inflammatory markers under study.
A positive emerging biomarker result does not replace imaging or laparoscopy, and a negative result does not rule out endometriosis when symptoms fit.
Wording Patients Use at Gynecology Appointments
Specific, unambiguous language changes the conversation at an appointment. Clinicians hear "painful periods" dozens of times a week. They do not dismiss it on purpose — they triage, and specific wording places a patient in the high-acuity pile.
Opening lines patients use:
- "My pain is a seven out of ten or higher during my period, and pain medication does not touch it."
- "I have tried [ibuprofen 800 mg around the clock / combined oral contraceptives / progestin-only pill] for [X] months with no meaningful improvement."
- "I am missing [X] days of work or school per month because of this pain. That is not sustainable."
- "Pain with intercourse has become a regular problem. So has cyclic bowel pain / urinary pain / pain radiating to my leg or rectum."
- "I want to be evaluated for endometriosis. I would like a pelvic ultrasound and, if that is inconclusive, a referral to a gynecologic surgeon who performs laparoscopic excision of endometriosis."
For period pain (dysmenorrhea), the prescription ibuprofen tablet label gives a dose of 400 mg every 4 hours as necessary, states that in controlled pain trials doses greater than 400 mg were no more effective than the 400 mg dose, and sets 3,200 mg as the maximum total daily dose.
Questions patients ask when a clinician declines:
- "Can you document in my chart that you declined to order imaging / refer me, and your reasoning?"
- "What else could explain this symptom pattern? I want to understand why you are ruling endometriosis out."
- "I would like a second opinion. Please provide a referral."
Some patients bring a written symptom log (see section 12) and a partner, parent, or friend. A request for imaging and specialist referral is consistent with current guidelines.
How Patients Find an Excision Specialist
The difference between a general gynecologist and a trained endometriosis excision surgeon is enormous — disease recurrence and reoperation rates differ by orders of magnitude. There is no single certifying body that identifies qualified surgeons, so patients have built informal registries.
- Online patient groups — some private online patient groups maintain crowdsourced lists of surgeons; joining can require answering a short screening. Such lists are widely used in the patient community.
- Peer-review directories — online directories in which surgeons submit surgical videos for peer review by endometriosis specialists.
- AAGL (American Association of Gynecologic Laparoscopists) — a professional society that maintains a certification in minimally invasive gynecologic surgery. The certification is not endometriosis-specific.
- Insurance and travel. Many excision specialists are out-of-network. A "single case agreement" with your insurer can sometimes bring costs down. Travel is common, the cost is real, but so is the difference in outcome.
Symptom Tracking to Build Your Case
A two- or three-cycle journal turns a vague complaint into a data set. Entries recorded by date, rather than from memory, typically cover:
- Phase of cycle (day 1 = first day of bleeding).
- Pain scale 0–10, at morning, midday, evening.
- Location — pelvic, low back, rectal, leg, shoulder (diaphragmatic endometriosis), chest.
- Bowel symptoms — diarrhea, constipation, pain with bowel movement, rectal bleeding (any blood is a red flag, see section 15).
- Bladder symptoms — urgency, pain with urination, blood in urine (especially if cyclic).
- Sex — pain with deep penetration, pain after.
- Missed work or school days, emergency room (ER) visits, unscheduled urgent-care visits.
- Medications tried and whether they helped.
A phone app or a paper notebook can hold the record; what matters is dates and numbers. "I had pain" is easy to dismiss. "Pain scored 8/10 on days 24–28 of five consecutive cycles, unresponsive to 800 mg ibuprofen every six hours, causing three ER visits since January" is not. (For comparison, the prescription ibuprofen tablet label gives 400 mg every 4 hours as necessary for period pain, with 3,200 mg as the maximum total daily dose.)
When Patients Seek a New Clinician
Situations that lead patients to stop trying to win over the current clinician and start over with a new one include:
- Repeat misdiagnoses without resolution. If you have been told "irritable bowel syndrome" or "anxiety" by two clinicians and nothing has improved, those labels are not working.
- Dismissive language. "All women have cramps," "you are too young to have real pain," "you just need to relax" — language that many patients take as a signal to move on rather than persuade.
- Refusal to order imaging or refer despite a clearly documented failure of first-line therapy.
- No plan for reassessment after empirical treatment — if no one has told you when to come back or what success would look like, you are being managed by inertia.
Second and third opinions are not rude. They are the standard of care for any complex diagnosis. A good gynecologist will welcome a fresh set of eyes on a difficult case.
What to Expect After Diagnosis
Diagnosis is a milestone, not an endpoint. Endometriosis is a chronic illness. Even after successful excision, many patients need ongoing care: hormonal suppression to slow recurrence, pelvic floor physical therapy for the central sensitization untreated pain produces, mental-health support, and sometimes a second surgery years later.
What changes at diagnosis is that you finally have a name, a community, a care team that knows what they are looking at, and a plan. The pain may not disappear in a week, but the gaslighting stops. See Pelvic Floor Therapy and Hormonal Therapy Options for the next stage.
Red Flags for Urgent Workup
Most endometriosis symptoms evolve slowly and can be worked up over weeks. A small set of findings warrants immediate evaluation, not a scheduled appointment weeks out.
- Acute severe pelvic pain different from your usual pattern — could signal endometrioma rupture, ovarian torsion, or ectopic pregnancy. Emergency department.
- Rectal bleeding, especially cyclic — bowel endometriosis invading the mucosa, or a separate gastrointestinal (GI) problem. Either way, needs evaluation this week.
- Cyclic hematuria (blood in urine timed with the period) — classic for bladder endometriosis. Needs urology and imaging.
- New-onset severe dyspareunia after previously tolerable intercourse — new lesion growth, especially in the rectovaginal space.
- Flank pain with decreased urine output — rare but serious; may indicate ureteral obstruction from deep infiltrating disease. Needs urgent imaging.
- Cyclic shoulder pain or shortness of breath — diaphragmatic or thoracic endometriosis. Less common but real.
Key Research Papers
- Agarwal SK, et al. Clinical diagnosis of endometriosis: a call to action. Am J Obstet Gynecol. 2019. — doi:10.1016/j.ajog.2018.12.039 (Expert call to action proposing a clinical-diagnosis approach.)
- Bazot M, Daraï E. Diagnosis of deep endometriosis: clinical examination, ultrasonography, magnetic resonance imaging, and other techniques. Fertil Steril. 2017. — doi:10.1016/j.fertnstert.2017.10.026
- Chapron C, et al. Oral contraceptives and endometriosis: the past use of oral contraceptives for treating severe primary dysmenorrhea is associated with endometriosis, especially deep infiltrating endometriosis. Hum Reprod. 2011. — doi:10.1093/humrep/der156
- Becker CM, et al. ESHRE guideline: endometriosis. Hum Reprod Open. 2022. — doi:10.1093/hropen/hoac009
- Hirsch M, Duffy J, Davis CJ, Nieves Plana M, Khan KS, International Collaboration to Harmonise Outcomes and Measures for Endometriosis. Diagnostic accuracy of cancer antigen 125 for endometriosis: a systematic review and meta-analysis. BJOG. 2016;123(11):1761-1768. — PubMed PMID: 27173590
- Nisenblat V, Bossuyt PM, Farquhar C, Johnson N, Hull ML. Imaging modalities for the non-invasive diagnosis of endometriosis. Cochrane Database Syst Rev. 2016;2(2):CD009591. — PubMed PMID: 26919512
- Alcázar JL, Eguez PM, Forcada P, Ternero E, Martínez C, Pascual MÁ, Guerriero S. Diagnostic accuracy of sliding sign for detecting pouch of Douglas obliteration and bowel involvement in women with suspected endometriosis: systematic review and meta-analysis. Ultrasound Obstet Gynecol. 2022;60(4):477-486. — PubMed PMID: 35289968
- Li W, Feng H, Ye Q. Factors contributing to the delayed diagnosis of endometriosis-a systematic review and meta-analysis. Front Med (Lausanne). 2025;12:1576490. — PubMed PMID: 40766070
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on endometriosis diagnosis, imaging, and clinical delay:
- PubMed: Endometriosis diagnostic delay
- PubMed: Transvaginal ultrasound for endometriosis
- PubMed: MRI of deep infiltrating endometriosis
- PubMed: Laparoscopy and endometriosis diagnosis
- PubMed: Sliding sign and pouch of Douglas obliteration
- PubMed: CA-125 and endometriosis screening limits
- PubMed: Endometriosis microRNA biomarkers
- PubMed: Endometriosis excision versus ablation outcomes
Connections
- Reproductive Medicine
- Laparoscopy: Excision vs Ablation
- Hormonal Therapy Options
- Pelvic Floor Therapy and Central Sensitization
- Endometriosis
- Infertility
- Ovarian Cysts
- Endo Belly and Gut Connection
- Fertility and Endometriosis
- Diet and Lifestyle
- Adenomyosis Overlap
- Bladder and Bowel Endometriosis
- Polycystic Ovary Syndrome
- Uterine Fibroids
- Chronic Pain
- Interstitial Cystitis
- Full Body Magnetic Resonance Imaging
- Inflammatory Markers
- Irritable Bowel Syndrome