⚠ Evidence warning: Clinical trials or other evidence do not support the claims that quercetin, resveratrol, A2 or goat milk and household chemical swaps ease endometriosis. This page keeps it as a report of what people, websites or other media say.
Diet and Lifestyle Approaches for Endometriosis
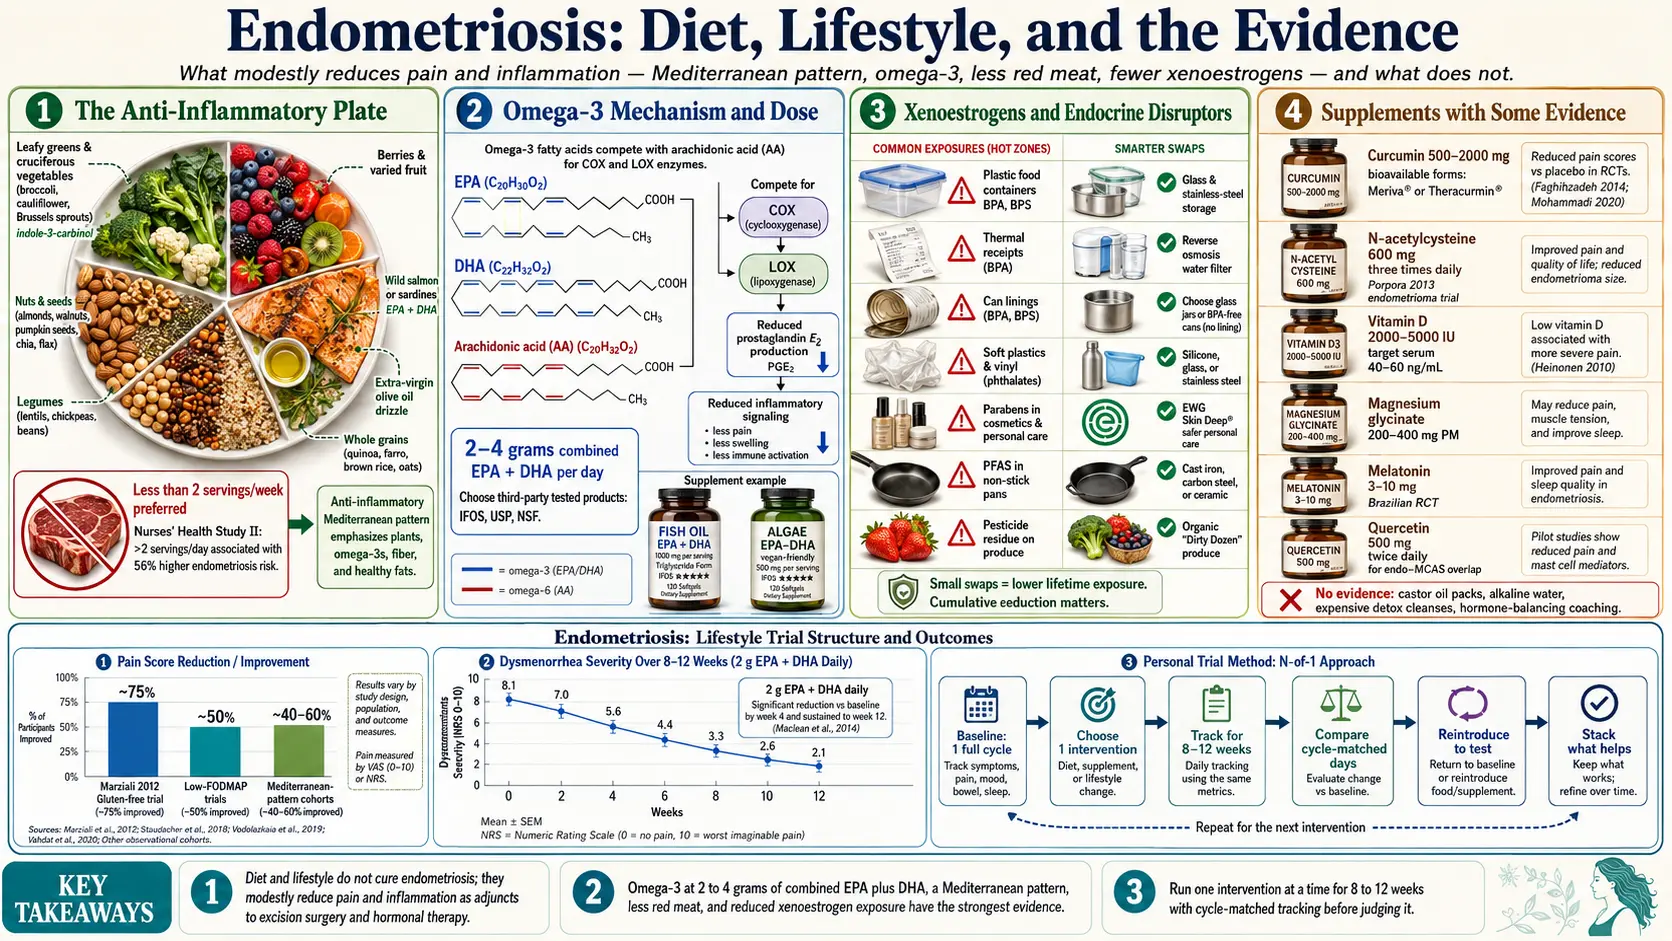
Table of Contents
- What Diet and Lifestyle Can — and Can't — Do
- The Anti-Inflammatory / Mediterranean Framework
- Omega-3 Fatty Acids
- Red Meat and Inflammation
- Dairy
- Gluten
- Low-FODMAP Eating and Bowel Symptoms
- Xenoestrogens and Endocrine Disruptors
- Alcohol
- Caffeine
- Supplements with Some Evidence
- Exercise
- Yoga and Mind-Body Work
- Sleep
- Stress Reduction
- Environmental Exposures
- What Doesn't Have Evidence
- How to Structure a Personal Lifestyle Trial
- Key Research Papers
- Connections
- Featured Videos
What Diet and Lifestyle Can — and Can't — Do
The internet is loud on this subject, and much of what it says is wrong. Diet and lifestyle changes do not cure endometriosis. They do not dissolve adhesions, shrink deep infiltrating lesions on the bowel or ureter, or remove the need for excision surgery and hormonal therapy in patients who need them. Anyone selling you a protocol that promises to reverse endo is selling you hope, not medicine.
What the evidence actually supports is narrower but worthwhile: in some patients, specific changes modestly reduce pain, dysmenorrhea intensity, and systemic inflammation. They improve general health outcomes that matter across a lifelong condition, and they give you a sense of agency. In the research, diet and lifestyle are adjuncts sitting alongside excision surgery, appropriate hormonal suppression, pelvic-floor therapy, and pain management — not replacements.
The diet studies on this page ran for 3 to 12 months. Endo symptoms fluctuate across cycles, so a single good or bad month says almost nothing; a daily 0–10 pain record kept alongside cycle phase gives data rather than impressions.
The Anti-Inflammatory / Mediterranean Framework
Of the diets studied, the Mediterranean pattern has the deepest evidence base of any diet studied in endometriosis and inflammatory conditions generally. Core emphases:
- Vegetables — 5+ servings daily, varied colors, with leafy greens featured. Cruciferous vegetables (broccoli, cauliflower, cabbage, Brussels sprouts) contribute indole-3-carbinol and sulforaphane, which support estrogen metabolism.
- Fruit — 2–3 servings daily, berries emphasized for polyphenol density.
- Extra-virgin olive oil as the primary fat, 2–4 tablespoons daily.
- Fatty fish (wild salmon, sardines, mackerel, herring) 2–3 times weekly for eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA).
- Nuts and seeds — a small handful daily (walnuts, almonds, flax, chia).
- Legumes — lentils, chickpeas, beans several times per week.
- Whole grains if tolerated (oats, quinoa, brown rice, farro).
- Limited red meat, processed meat, refined sugar, and ultra-processed packaged foods.
In cohort studies, women eating closest to this pattern report lower dysmenorrhea scores and lower C-reactive protein (CRP). In a 2023 study of 35 women with endometriosis, 3 to 6 months on a Mediterranean diet were followed by lower scores for painful intercourse (dyspareunia) and painful bowel movements (dyschezia), and pain tracked with blood markers of oxidative stress; the study had no comparison group.
A 2026 randomised trial tested the diet directly. It enrolled 140 women aged 18–45 whose endometriosis stayed painful despite hormone treatment; half received coaching on the Mediterranean diet and aerobic exercise every 4 months on top of hormone treatment, and half received no extra lifestyle advice. After 12 months, non-menstrual pelvic pain fell more in the coached group (−1.60 against −0.74 points on a 0–10 scale), as did painful bowel movements, and 47% against 27% reported that their overall health had improved; depression and quality-of-life scores did not change significantly.
Studies like these ran for 3–12 months. Any benefit is cumulative and slow, the way cardiovascular benefit is.
Omega-3 Fatty Acids
Omega-3s are the single most evidence-backed nutrient intervention in painful periods. Marine-sourced eicosapentaenoic acid and docosahexaenoic acid compete with arachidonic acid for the enzymes that produce inflammatory prostaglandins — the same prostaglandins that drive the cramping of dysmenorrhea and the pelvic inflammation of endo.
Doses commonly described by practitioners: 2–4 grams of combined eicosapentaenoic acid+docosahexaenoic acid per day. Labels matter here — a "1,000 mg fish oil" capsule may contain only 300 mg of actual eicosapentaenoic acid+docosahexaenoic acid. Independent third-party testing programmes check fish oils for oxidation and heavy metals.
Key trials: Harel et al. 1996 gave 42 adolescents with painful periods fish oil at 1,080 mg eicosapentaenoic acid + 720 mg docosahexaenoic acid daily for 2 months in a crossover trial with placebo; their menstrual symptom score fell from 69.9 to 44.0. Rahbar et al. 2012, a crossover trial in 95 women aged 18–22, found omega-3 supplementation significantly reduced primary dysmenorrhea severity versus placebo, and the women needed fewer ibuprofen rescue tablets while taking it. Both trials studied primary dysmenorrhea (period pain without an underlying disease), not endometriosis. Multiple subsequent trials have replicated the pain-reduction signal.
For vegans and strict vegetarians, an algae-based eicosapentaenoic acid/docosahexaenoic acid supplement supplies the same end product without fish. Flax, chia, and walnuts provide alpha-linolenic acid (ALA), which the body converts to eicosapentaenoic acid/docosahexaenoic acid only at about 5–10% efficiency — fine as dietary background but not enough on its own to reach the doses used in the trials. The trials ran 2–3 months. High-dose fish oil can add to the bleeding effect of blood-thinning drugs (anticoagulants).
Red Meat and Inflammation
The best prospective data on food and endo risk comes from the Nurses' Health Study II. Analyzing over 81,000 women followed for 22 years, Yamamoto and colleagues (Harris group) found that women eating more than 2 servings of red meat per day had roughly a 56% higher risk of laparoscopically confirmed endometriosis compared to those eating one serving or less per week (Am J Obstet Gynecol 2018). Intakes of poultry, fish, shellfish, and eggs were not linked to endometriosis risk.
Why? Three plausible mechanisms, none definitively proven but all biologically reasonable:
- Arachidonic acid — concentrated in red and processed meat, this omega-6 fatty acid feeds the same prostaglandin pathways that omega-3s dampen.
- Heme iron — abundant in red meat, heme iron is pro-oxidant and may contribute to oxidative stress in peritoneal fluid, which is already iron-heavy in endo patients from retrograde menstruation.
- Insulin-like growth factor 1 (IGF-1) and insulin response — higher red-meat diets raise insulin-like growth factor 1, a hormone that may promote proliferation of endometrial-like tissue.
The lowest-risk group in that study ate one serving of red meat a week or less, and fish, poultry, and eggs were not linked to risk; legumes are another common protein swap. The study did not compare vegetarian diets. The data show a dose-response, not an all-or-nothing.
Dairy
Dairy is the most over-prescribed elimination in the endo patient community, and the evidence is genuinely mixed. Some cohort studies show a modest protective association between dairy and endo (higher calcium and vitamin D intake), while others show the opposite or nothing.
Separately, there is the A1 vs A2 casein hypothesis: most Western cow milk contains a mix of A1 and A2 beta-casein variants, and A1 digestion releases beta-casomorphin-7 (BCM-7), an opioid-like peptide that, according to proponents of this hypothesis, can drive gut inflammation in susceptible people. A2-only milk (from certain breeds), goat milk, and sheep milk largely avoid A1 casein, and some people with endometriosis report fewer gut symptoms with them. This is a promising but under-studied area.
Many patients report real benefit from a 4–6 week dairy elimination followed by structured reintroduction. Endo belly, bloating, or cramping that improve off dairy and flare on reintroduction point to dairy as a trigger for that person; when nothing changes, cutting dairy only lowers calcium, vitamin D, and protein intake.
Gluten
The most-cited endo-specific gluten study is Marziali et al. 2012, which followed 207 women with severe, painful endometriosis on a 12-month gluten-free diet. About 75% reported significant improvement in pelvic pain versus baseline, with improvements in physical functioning, mental health, and social role domains. The study was retrospective and uncontrolled, so expectation effects and concurrent lifestyle changes can't be separated out — but the effect size was large.
The broader debate is about non-celiac gluten sensitivity, a real but fuzzy entity where patients without celiac disease or wheat allergy still respond to gluten removal. Some of that may be wheat fructans (a FODMAP, short for fermentable oligosaccharides, disaccharides, monosaccharides and polyols) rather than gluten per se. For an individual, the mechanism matters less than whether removing it makes a difference.
A common approach described by practitioners is strict gluten-free eating for 4–6 weeks, tracking pain and gastrointestinal (GI) symptoms, followed by a blinded reintroduction (a family member prepares identical-looking gluten and gluten-free foods) if symptoms clearly improved. When nothing changes, whole-grain gluten foods are nutritionally valuable and not intrinsically harmful. Celiac blood tests work only while a person is still eating gluten; going gluten-free first invalidates the test.
Low-FODMAP Eating and Bowel Symptoms
Bowel symptoms such as bloating and painful bowel movements are common in endometriosis, and the low-FODMAP diet — which cuts down on fermentable sugars and fibres found in foods such as wheat, onions, garlic, beans, some fruits and milk — has been tried for them. A 2026 review pooled three small studies (90 women, average age 34, followed for about 3.5 months on average) and linked the low-FODMAP diet with better scores on an endometriosis quality-of-life questionnaire, including its pain section. The authors call the result hypothesis-generating: it needs confirmation in larger, well-designed randomised trials.
Xenoestrogens and Endocrine Disruptors
Endometriosis is an estrogen-dependent disease, and a growing body of evidence implicates environmental endocrine disruptors in its pathogenesis. The main offenders:
- Bisphenol A (BPA) and bisphenol S (BPS) — in polycarbonate plastics, thermal receipts, the linings of most food cans.
- Phthalates — in soft plastics, vinyl shower curtains, synthetic fragrances, many cosmetics.
- Parabens — preservatives in lotions, shampoos, makeup.
- Per- and polyfluoroalkyl substances (PFAS, "forever chemicals") — non-stick cookware, water-resistant fabrics, fast-food wrappers, contaminated drinking water.
- Pesticide residues — especially organochlorines and certain fungicides on conventional produce.
Household steps people commonly take to lower exposure: storing food in glass or stainless steel, especially hot or fatty foods, and not microwaving food in plastic; a reverse-osmosis or activated-carbon water filter certified for PFAS removal; checking personal care products in a skin-product ingredient database run by an environmental advocacy group; buying organic versions of the produce that ranks highest on a published pesticide-residue list; and replacing worn non-stick pans with cast iron or stainless steel. Zero exposure is not achievable — the aim of these swaps is a lower lifetime dose.
Alcohol
Alcohol modestly raises circulating estrogen by reducing liver clearance and may interfere with progesterone production. Meta-analyses show a small positive association with endo risk, strongest at higher intakes.
Some practitioners suggest under 7 drinks per week, with several alcohol-free days. Many patients report doing particularly poorly with alcohol during the luteal phase (week before menstruation), and some leave alcohol out entirely in that window to see whether their worst days soften.
Caffeine
Observational evidence on caffeine and endo is inconsistent — some studies show a small risk increase at heavy intake, others nothing. Caffeine does transiently raise cortisol and can worsen anxiety, sleep, and pelvic-floor muscle tension in sensitive patients.
Responses vary: some people find coffee flares their symptoms and cut back or switch to decaf or green tea; others notice no effect. The evidence does not support a universal prohibition.
Supplements with Some Evidence
Listed in rough order of evidence strength. Starting several at once makes it impossible to tell which one helped — five begun on a Monday and a better Friday leave the cause unknown.
- Curcumin — 500–2,000 mg daily is the range commonly used, usually as an enhanced-absorption form (paired with piperine, bound to phospholipids, or another enhanced-absorption preparation). Standard turmeric powder absorbs poorly. Small trials show reductions in pelvic pain and inflammatory markers.
- N-acetylcysteine (NAC) — 600 mg three times daily is a commonly described dose. In Porpora et al. 2013, an observational cohort study, N-acetylcysteine or no treatment was offered to 92 women with ovarian endometriomas, who chose for themselves (no randomisation and no placebo). After 3 months the average cyst diameter shrank slightly with N-acetylcysteine (−1.5 mm) and grew without it (+6.6 mm), and 24 treated women against 1 untreated cancelled their planned surgery (laparoscopy), mostly because cysts shrank or disappeared or pain eased.
- Vitamin D — some practitioners aim for a blood level of 25-hydroxyvitamin D of 40–60 ng/mL, using 2,000–5,000 international units (IU) daily guided by blood tests. For comparison, the Institute of Medicine (IOM) 2011 report set the Recommended Dietary Allowance at 600 IU a day for ages 1–70, which corresponds to a blood level of at least 20 ng/mL; it found higher levels were not consistently linked with greater benefit, with risks at both low and high levels for some outcomes; and it set the tolerable upper intake level at 4,000 IU a day from age 9 — below the top of that practitioner range. Linked to reduced pelvic pain in several small trials.
- Magnesium glycinate — 200–400 mg evening. Reduces dysmenorrhea in meta-analyses, supports sleep, helps pelvic-floor relaxation. Glycinate is gentle on the gut.
- Melatonin — a 2013 Brazilian randomized controlled trial (RCT) in 40 women at 10 mg nightly for 8 weeks showed reductions in pelvic pain, dysmenorrhea, and dyschezia versus placebo: daily pain fell 39.8% and period pain 38.0% compared with placebo, sleep quality improved, and the risk of needing a painkiller fell by 80%. Lower doses, such as 3 mg, were not tested in this trial.
- Quercetin — 500 mg twice daily is a commonly used amount. Practitioners describe it as a mast-cell stabilizer, useful with the endo–mast cell activation syndrome (MCAS) overlap (histamine flares, flushing, food sensitivities), and often pair it with bromelain for absorption.
- Resveratrol — 100–500 mg daily is the range commonly used. Preliminary evidence only; practitioners describe it as optional.
Supplements matter most for people on hormonal therapy, on blood thinners (anticoagulants), or facing surgery: fish oil and some other supplements can add to the bleeding effect of blood thinners and to bleeding during an operation, which is why surgical teams commonly ask for most supplements to be stopped 10–14 days before surgery.
Exercise
Regular moderate exercise reduces inflammatory prostaglandins, improves insulin sensitivity, and speeds gut transit (which helps the liver excrete conjugated estrogen rather than recirculate it through the enterohepatic pathway). Exercise also down-regulates central pain sensitization over months.
Programmes commonly described: 3–5 sessions per week, 30+ minutes each, mixing cardiovascular work (walking, swimming, cycling) with resistance training (2 sessions weekly of full-body strength work). Intensity in these programmes is tolerable, not punishing — high-intensity workouts the week before your period may flare symptoms for some patients, and some switch to walking or yoga on their worst days.
Pelvic pain during exercise is commonly handled by adjusting the load rather than stopping; a pelvic-floor physical therapist (PT) can modify loading and address the muscle dysfunction driving the pain.
Yoga and Mind-Body Work
A 2017 Brazilian randomized controlled trial by Gonçalves and colleagues divided 40 women with endometriosis between an 8-week yoga program (28 women, two 90-minute sessions a week) and a no-yoga control group (12 women). Daily pain was significantly lower in the yoga group, and several quality-of-life areas improved more than in the control group, although quality of life improved in both groups. The evidence is modest in size but real.
Styles commonly described as the best fit: restorative yoga, yin, gentle hatha, and the Saraswati School-style programs developed specifically for pelvic pain. Practitioners generally steer away from hot yoga and strongly compressive poses during flares. Slow diaphragmatic breathing (box breathing, 4–7–8 breathing), meditation apps (including some made specifically for pain), and progressive muscle relaxation all contribute modestly to pain reduction through the vagal/parasympathetic pathway.
Sleep
Sleep is the cheapest, most effective anti-inflammatory intervention you have. Adults with chronic pain conditions who sleep less than 6 hours report measurably higher pain scores and higher inflammatory markers (C-reactive protein, interleukin-6) than those sleeping 7–9 hours.
Basics that matter:
- Consistent bed and wake times, including weekends.
- Dark, cool bedroom (65–68°F).
- Last caffeine by early afternoon.
- Screens off 60–90 minutes before bed, or use blue-light reduction.
- Magnesium glycinate or melatonin as pharmacologic help.
- Pain treated at bedtime — heat, nonsteroidal anti-inflammatory drugs (NSAIDs) if appropriate, positioning pillows — rather than lying awake with it.
Obstructive sleep apnea and restless legs are diagnosable and treatable; left untreated, sleep disorders can cancel out most other interventions.
Stress Reduction
Chronic stress elevates cortisol, which in turn modulates inflammatory cytokines and amplifies pain perception in the central nervous system. Endo patients also carry a heavy load of medical trauma — years of dismissal, delayed diagnosis, failed treatments, painful exams. That trauma is real and deserves direct attention.
Evidence-based approaches:
- Mindfulness-based stress reduction (MBSR) — 8-week structured programs with measurable effects on chronic pelvic pain.
- Cognitive behavioral therapy for chronic illness — not about convincing you the pain isn't real; it's about reducing the amplifying effect of catastrophizing and anxiety on pain signaling.
- Therapy with a clinician experienced in medical trauma or chronic illness — eye movement desensitization and reprocessing (EMDR) or somatic therapy are options used when medical procedures, pelvic exams, or past dismissals are still dysregulating.
Seeing a therapist does not mean your pain is psychological. It means you are treating the part of the nervous system that turns volume up on every signal.
Environmental Exposures
Beyond the xenoestrogen categories above, people commonly make a few household-level swaps gradually:
- Cleaning products — fragrance-free, low-volatile organic compound (VOC) options, or plain vinegar and baking soda.
- Unscented personal care — "fragrance" on a label is an umbrella term for undisclosed chemicals, often including phthalates.
- Alternatives to BPA-lined cans — cartons, glass jars, cooked dried beans, and frozen tomatoes.
- Air quality — a high-efficiency particulate air (HEPA) purifier in the bedroom and good kitchen ventilation modestly reduce indoor VOC load.
The largest wins are the kitchen (plastics, cans, water) and personal care. The rest is incremental.
What Doesn't Have Evidence
A candid list of popular recommendations that currently lack good data in endo:
- Expensive "hormone-balancing" coaching protocols. Diet and lifestyle do not reverse endometriosis (see the top of this page).
- DIM (diindolylmethane) without a specific evidence base for endo — mechanistic, not clinical.
- Castor oil packs — zero randomized controlled trial evidence in endo. Harmless, but not a treatment.
- Homeopathic preparations and alkaline/structured water products.
- Expensive "liver detox" cleanses — your liver already detoxifies; these are typically high-sugar, low-protein.
- "Endometriosis diet" coaching packages for hundreds of dollars monthly. The underlying principles are the Mediterranean pattern, which is free.
By contrast, the approaches on this page with research behind them include excision surgery, pelvic-floor physical therapy, omega-3 fish oil, and Mediterranean-style everyday groceries.
How to Structure a Personal Lifestyle Trial
Because endo fluctuates, almost any intervention can look like it works in the first month. The self-testing method commonly described has these steps:
- One intervention at a time. Not three. One.
- A baseline of one full cycle before changing anything, tracking daily pain (0–10), bleeding days, bowel and bladder symptoms, mood, sleep hours.
- 8–12 weeks per intervention — roughly two to three full menstrual cycles, enough signal to distinguish from noise.
- Cycle-matched comparisons, not weekday averages: day 1 of one period against day 1 of the next.
- Reintroduction as the test for elimination diets. Improvement without a flare on reintroduction may be coincidence.
- Gradual stacking. Something that works is kept, and the next candidate added.
- Dropping what doesn't help. No dead rules carried around: if three months of strict gluten-free did nothing and reintroduction flared nothing, gluten is not the issue for that person.
This approach is unglamorous, but it separates real personal responses from noise. Over a year or two, most patients assemble a short list of interventions that genuinely move their symptoms — usually some combination of omega-3s, magnesium, vitamin D repletion, a reduced red-meat Mediterranean pattern, regular movement, and attention to sleep and stress. That short list is worth far more than any influencer protocol.
Key Research Papers
- Yamamoto A, Harris HR, Vitonis AF, Chavarro JE, Missmer SA. A prospective cohort study of meat and fish consumption and endometriosis risk. American Journal of Obstetrics and Gynecology. 2018;219(2):178.e1–178.e10. — PubMed PMID: 29870739
- Porpora MG, et al. A promise in the treatment of endometriosis: an observational cohort study on ovarian endometrioma reduction by N-acetylcysteine. Evidence-Based Complementary and Alternative Medicine. 2013. — doi:10.1155/2013/240702
- Marziali M, et al. Gluten-free diet: a new strategy for management of painful endometriosis related symptoms? Minerva Chirurgica. 2012;67(6):499–504. (PubMed PMID: 23334113)
- ESHRE Endometriosis Guideline Group. ESHRE guideline: endometriosis. Human Reproduction Open. 2022. — doi:10.1093/hropen/hoac009
- Harel Z, Biro FM, Kottenhahn RK, Rosenthal SL. Supplementation with omega-3 polyunsaturated fatty acids in the management of dysmenorrhea in adolescents. American Journal of Obstetrics and Gynecology. 1996;174(4):1335–1338. — PubMed PMID: 8623866
- Rahbar N, Asgharzadeh N, Ghorbani R. Effect of omega-3 fatty acids on intensity of primary dysmenorrhea. International Journal of Gynaecology and Obstetrics. 2012;117(1):45–47. — PubMed PMID: 22261128
- Gonçalves AV, Barros NF, Bahamondes L. The Practice of Hatha Yoga for the Treatment of Pain Associated with Endometriosis. Journal of Alternative and Complementary Medicine. 2017;23(1):45–52. — PubMed PMID: 27869485
- Schwertner A, Conceição Dos Santos CC, Costa GD, et al. Efficacy of melatonin in the treatment of endometriosis: a phase II, randomized, double-blind, placebo-controlled trial. Pain. 2013;154(6):874–881. — PubMed PMID: 23602498
- Ross AC, Manson JE, Abrams SA, et al. The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. Journal of Clinical Endocrinology and Metabolism. 2011;96(1):53–58. — PubMed PMID: 21118827
- Cirillo M, Argento FR, Becatti M, et al. Mediterranean Diet and Oxidative Stress: A Relationship with Pain Perception in Endometriosis. International Journal of Molecular Sciences. 2023;24(19):14601. — PubMed PMID: 37834048
- Donati A, Giola F, Privitera G, et al. Diet and physical activity coaching for well-being and pain reduction in patients with symptomatic endometriosis: a randomized-controlled clinical trial. European Journal of Obstetrics, Gynecology, and Reproductive Biology. 2026;326:115381. — PubMed PMID: 42632337
- Rabelo AA, Oliveira JFCE, Rios JR, et al. Effects of a Low-FODMAP Diet on Symptoms and Quality of Life in Women With Endometriosis: A Systematic Review and Meta-Analysis. Journal of Human Nutrition and Dietetics. 2026;39(5):e70353. — PubMed PMID: 42876029
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on diet, supplements, and lifestyle in endometriosis:
- PubMed: Red meat and endometriosis risk
- PubMed: Omega-3 fatty acids and dysmenorrhea
- PubMed: N-acetylcysteine and ovarian endometrioma
- PubMed: Vitamin D and endometriosis
- PubMed: Gluten-free diet and endometriosis
- PubMed: Bisphenol A, phthalates, and endometriosis
- PubMed: Curcumin and endometriosis
- PubMed: Melatonin and endometriosis pelvic pain
Connections
- Reproductive Medicine
- Endometriosis
- Omega-3 Fatty Acids
- Magnesium Glycinate
- Turmeric
- Quercetin
- Laparoscopy: Excision vs Ablation
- Diagnosis Delay and Imaging
- Hormonal Therapy Options
- Pelvic Floor Therapy and Central Sensitization
- Endo Belly and Gut Connection
- Fertility and Endometriosis
- Adenomyosis Overlap
- Vitamin D3
- Gluten-Free Diet Practical Guide
- Iron
- Magnesium
- N-Acetylcysteine
- Ultra Processed Foods