Interstitial Lung Disease
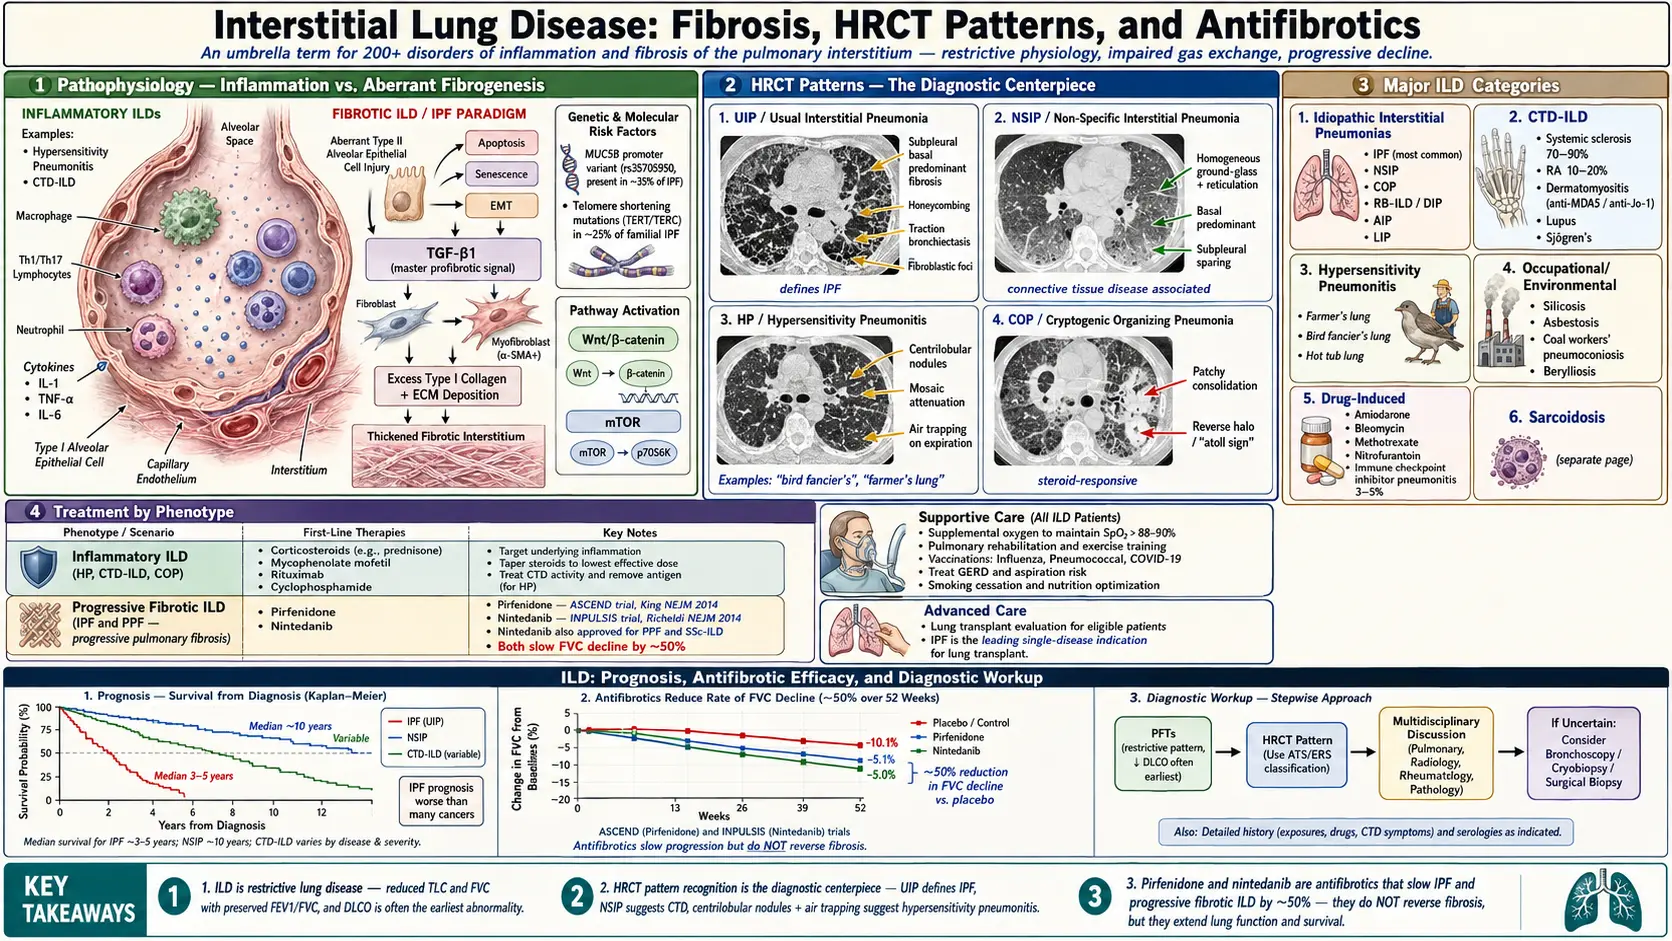
Table of Contents
- Overview
- Epidemiology
- Pathophysiology — Fibrosis Mechanisms
- Etiology and Risk Factors
- Clinical Presentation
- Diagnosis — Pulmonary Function Tests, High-Resolution CT, Bronchoscopy, Surgical Biopsy
- Treatment
- Complications
- Prognosis
- Prevention
- Recent Research and Advances
- Key Research Papers
- Connections
- Featured Videos
1. Overview
Interstitial lung disease (ILD) is an umbrella term encompassing over 200 distinct disorders characterized by diffuse inflammation and/or fibrosis of the pulmonary interstitium — the tissue and space surrounding alveoli, capillaries, and bronchioles. Though structurally the interstitium is the primary target, ILDs invariably affect alveolar epithelium, capillary endothelium, and airspaces as well. The result is progressive impairment of gas exchange and lung mechanics, leading to restrictive physiology, hypoxemia, and functional decline.
The most clinically significant ILD is idiopathic pulmonary fibrosis (IPF), the prototype of the progressive fibrosing ILDs. Other major categories include connective tissue disease-associated ILD (CTD-ILD), hypersensitivity pneumonitis (HP), sarcoidosis, occupational/environmental ILDs, and drug-induced ILD. Accurate classification is critical because prognosis and treatment vary substantially among subtypes.
2. Epidemiology
The prevalence of all ILDs combined is estimated at 80–100 per 100,000 in the United States. IPF, the most common idiopathic IIP, has an estimated prevalence of 14–43 per 100,000 and incidence of 7–16 per 100,000 per year. IPF is predominantly a disease of older males (>60 years), with a strong association with cigarette smoking.
CTD-ILD is the most common ILD category overall; systemic sclerosis (SSc) is complicated by ILD in 70–90% of patients (though progressive disease in ~15%), and rheumatoid arthritis ILD affects approximately 10–20% of rheumatoid arthritis (RA) patients. Hypersensitivity pneumonitis accounts for up to 15% of ILD diagnoses in tertiary centers. Occupational ILDs (silicosis, asbestosis, coal worker's pneumoconiosis) remain significant public health concerns globally.
Drug-induced ILD is increasingly recognized with >350 implicated medications (bleomycin, amiodarone, methotrexate, nitrofurantoin, immune checkpoint inhibitors). ILD incidence is increasing, partly reflecting improved recognition and an aging population.
3. Pathophysiology — Fibrosis Mechanisms
The mechanisms underlying ILD vary by subtype, but converge on two principal processes: alveolar inflammation and/or aberrant fibrogenesis.
Inflammatory ILDs (e.g., Hypersensitivity Pneumonitis, CTD-ILD)
Repetitive exposure to antigenic or injurious stimuli triggers innate and adaptive immune responses. Alveolar macrophages, T lymphocytes (particularly Th1/Th17 in HP), and neutrophils accumulate in the interstitium. Macrophage-derived cytokines (interleukin-1 (IL-1), tumor necrosis factor-alpha, interleukin-6 (IL-6)) amplify inflammation. In some cases, inflammation resolves; in others, it progresses to fibrosis via TGF-beta-mediated activation of fibroblasts and myofibroblasts.
Fibrotic ILDs — IPF Paradigm
IPF is driven by aberrant alveolar epithelial repair rather than primary inflammation. Repetitive micro-injuries (cigarette smoke, viral infections, gastroesophageal reflux microaspiration, mechanical stress in susceptible individuals) trigger abnormal type II alveolar epithelial cell (AEC II) responses: apoptosis, senescence, and epithelial-mesenchymal transition (EMT). Key molecular mechanisms:
- TGF-beta1 signaling: The master profibrotic mediator. Activates fibroblasts to differentiate into alpha-SMA-positive myofibroblasts, which produce excess extracellular matrix (ECM) — particularly type I collagen. Myofibroblasts are remarkably resistant to apoptosis.
- Wnt/beta-catenin pathway: Activated in IPF; promotes fibroblast proliferation and matrix production.
- Mechanistic target of rapamycin (mTOR) pathway: Regulates fibroblast metabolism and autophagy; potential therapeutic target.
- Telomere biology: Telomere shortening mutations (TERT, TERC) found in ~25% of familial IPF and ~3% of sporadic IPF; impairs AEC II renewal capacity.
- Mucin gene variants: MUC5B promoter polymorphism (rs35705950) is the strongest genetic risk factor for IPF; in the 2011 study that identified it, the minor allele had a frequency of 38% among people with IPF against 9% among controls (these are allele frequencies, not the share of patients carrying it), with odds ratios for IPF of 9.0 for one copy and 21.8 for two copies; mechanism involves abnormal mucus production impairing mucociliary defense.
Histologically, IPF demonstrates the usual interstitial pneumonia (UIP) pattern: temporally heterogeneous fibrosis (alternating areas of fibrosis and near-normal lung), fibroblastic foci (leading edges of active fibrosis), honeycomb changes (cystic airspace remodeling) predominantly in the subpleural, basal lung.
4. Etiology and Risk Factors
ILDs are classified by etiology:
Idiopathic Interstitial Pneumonias (IIPs)
- IPF (UIP pattern) — most common; progressive; no known cause
- Nonspecific interstitial pneumonia (NSIP) — often CTD-associated; better prognosis than IPF
- Cryptogenic organizing pneumonia (COP) — patchy consolidation; steroid-responsive
- Respiratory bronchiolitis-ILD (RB-ILD) / Desquamative interstitial pneumonia (DIP) — smoking-related
- Acute interstitial pneumonia (AIP/Hamman-Rich syndrome) — rapid progression; poor prognosis
- Lymphoid interstitial pneumonia (LIP) — often CTD or human immunodeficiency virus-associated
Connective Tissue Disease-Associated ILD
- Systemic sclerosis (NSIP or UIP pattern)
- Rheumatoid arthritis (UIP most common)
- Polymyositis/dermatomyositis (NSIP; anti-synthetase syndrome: anti-Jo-1; anti-MDA5 marks a separate dermatomyositis group)
- Systemic lupus erythematosus, Sjogren's syndrome, mixed connective tissue disease (MCTD)
Hypersensitivity Pneumonitis
- Farmer's lung (thermophilic Actinomycetes)
- Bird fancier's lung (avian proteins)
- Hot tub lung (nontuberculous mycobacteria)
- Isocyanate-induced HP (occupational)
Occupational and Environmental ILDs
- Silicosis (crystalline silica) — accelerated silicosis risk with sandblasting, hydraulic fracturing. Silicosis is also being reported in workers who cut engineered stone ("quartz") countertops: California counted 592 cases from January 2019 through June 2026, with 65 lung transplants and 31 deaths. In an earlier California series of 52 men, the median age was 45, and diagnosis was delayed in 30 (58%), most often because of a first diagnosis of bacterial pneumonia or tuberculosis
- Asbestosis (tremolite, chrysotile asbestos)
- Coal workers' pneumoconiosis
- Berylliosis (chronic beryllium disease)
- Hard metal lung disease (cobalt)
Drug-Induced ILD
- Amiodarone, bleomycin, methotrexate, nitrofurantoin, cyclophosphamide
- Immune checkpoint inhibitors (pembrolizumab, nivolumab): pneumonitis in 3–5% of treated patients
- Tyrosine kinase inhibitors (gefitinib, erlotinib)
Risk Factors for ILD in General
- Cigarette smoking (IPF, RB-ILD, DIP, combined pulmonary fibrosis and emphysema)
- Age >50 years (IPF predominantly a disease of the elderly)
- Male sex (IPF)
- Family history (familial IPF; telomerase gene mutations)
- Gastroesophageal reflux (microaspiration)
- Occupational/environmental antigen exposure
5. Clinical Presentation
ILD typically presents with an insidious onset of symptoms, often leading to significant delay in diagnosis (median 1–2 years for IPF).
Symptoms:
- Progressive exertional dyspnea (hallmark; present in virtually all patients)
- Dry, nonproductive cough (IPF); productive cough may suggest HP or infection
- Fatigue, weight loss (particularly CTD-ILD, malignancy-associated ILD)
- Constitutional symptoms (fever, myalgias) in inflammatory ILDs (HP, COP, acute ILD)
- Hemoptysis — uncommon; suggests diffuse alveolar hemorrhage or malignancy
- Extrapulmonary features: joint symptoms (CTD), skin changes (scleroderma, DM), sicca symptoms (Sjogren's), proximal muscle weakness (myositis)
Physical examination findings:
- Fine, "velcro-like" inspiratory crackles at lung bases (IPF, asbestosis, UIP pattern)
- Absence of crackles in NSIP, HP (mid-field crackles possible)
- Digital clubbing (30–50% of IPF; rare in other IIPs)
- Cyanosis (late disease)
- Signs of pulmonary hypertension (loud P2, RV heave, peripheral edema) in advanced disease
- Skin, joint, or mucosal findings suggesting underlying CTD
- "Mechanic's hands" (anti-synthetase syndrome), Raynaud's phenomenon (SSc, MCTD)
6. Diagnosis — Pulmonary Function Tests, High-Resolution CT, Bronchoscopy, Surgical Biopsy
Pulmonary Function Tests (PFTs)
The hallmark of ILD is a restrictive ventilatory defect:
- Reduced total lung capacity (TLC <80% predicted)
- Reduced FVC with preserved or elevated FEV1/FVC ratio
- Reduced diffusing capacity for carbon monoxide (DLCO) — often the earliest abnormality; reflects impaired alveolar-capillary membrane function
- Reduced lung compliance (increased work of breathing)
- Combined obstructive-restrictive pattern in combined pulmonary fibrosis and emphysema (CPFE): "normal" TLC despite fibrosis, with markedly reduced DLCO
FVC decline of ≥10% or DLCO decline ≥15% over 6–12 months predicts disease progression and mortality in IPF.
High-Resolution CT (HRCT)
The cornerstone of ILD diagnosis. Computed tomography (CT) patterns guide diagnosis and can obviate surgical biopsy:
- UIP pattern (IPF): Bilateral, peripheral, basal-predominant honeycombing with or without peripheral traction bronchiectasis; absence of features suggesting alternative diagnosis. Typical UIP on HRCT is diagnostic of IPF in the correct clinical context.
- NSIP pattern: Bilateral, symmetric, basal ground-glass opacity and reticulation; subpleural sparing (classic); traction bronchiectasis in fibrotic NSIP.
- Organizing pneumonia: Bilateral peripheral and/or peribronchial consolidation; migratory nature.
- Hypersensitivity pneumonitis: Upper/mid-lobe predominant ground-glass opacity; centrilobular nodules; air trapping on expiratory computed tomography (mosaic attenuation); fibrosis in chronic HP mimicking UIP/NSIP.
- Sarcoidosis: Perilymphatic nodules along bronchovascular bundles; upper lobe predominance; lymphadenopathy.
- Desquamative IP/RB-ILD: Diffuse ground-glass opacity; upper lobe centrilobular nodules (RB-ILD).
Bronchoscopy with Bronchoalveolar Lavage (BAL)
BAL cellular analysis provides diagnostic clues:
- Lymphocytosis (>40%): HP, sarcoidosis, NSIP, COP
- Neutrophilia: IPF, acute exacerbation of ILD, bacterial infection
- Eosinophilia: Eosinophilic pneumonia, drug-induced ILD
- Hemosiderin-laden macrophages: Diffuse alveolar hemorrhage
- Transbronchial biopsy: useful for sarcoidosis, HP, COP; inadequate tissue for UIP/NSIP pattern characterization
- Cryobiopsy: larger samples than conventional forceps; intermediate between transbronchial and surgical biopsy; growing role in ILD diagnosis
Surgical Lung Biopsy (SLB)
Video-assisted thoracoscopic surgery (VATS) biopsy provides the largest tissue samples and remains the gold standard for histopathologic diagnosis when HRCT is non-diagnostic. Samples are usually taken from multiple lobes. Operative mortality and morbidity risk are weighed against diagnostic benefit; surgical biopsy may be deferred in elderly, physiologically compromised patients or where the clinical and CT picture is sufficiently diagnostic.
Serological Testing
- Antinuclear antibody (ANA), anti-dsDNA, anti-Scl-70, anti-centromere, RF, anti-CCP — screen for CTD-ILD
- Anti-synthetase antibodies (Jo-1, PL-7, PL-12, EJ, OJ) — inflammatory myopathy-ILD; anti-MDA5, a separate dermatomyositis antibody, is tested alongside them. A 2026 Singapore cohort found anti-MDA5 dermatomyositis and anti-synthetase syndrome both carried a high burden of ILD but differed in skin signs, risk of rapidly progressive ILD and survival
- Specific immunoglobulin G (IgG) precipitins (avian, thermophilic bacteria) — HP serologies
- ACE level — sarcoidosis (low sensitivity/specificity; ~75%/90%)
- KL-6 (Krebs von den Lungen-6): Elevated in IPF and other fibrotic ILDs; used in Japan as a biomarker
- SP-D, SP-A: Surfactant proteins; prognostic biomarkers in IPF
Multidisciplinary Discussion (MDD)
Integration of clinical, radiological, and pathological data in a dedicated ILD multidisciplinary team (pulmonologist, thoracic radiologist, pathologist) is the recommended diagnostic approach and demonstrably improves diagnostic accuracy and inter-observer agreement.
7. Treatment
Treatment is highly ILD-subtype-specific. Inflammatory ILDs may respond to immunosuppression; fibrotic ILDs (particularly IPF) do not benefit and may worsen with corticosteroids.
Idiopathic Pulmonary Fibrosis
- Nintedanib (tyrosine kinase inhibitor targeting FGFR, PDGFR, VEGFR): INPULSIS trials showed reduction in FVC decline by ~50%; approved for IPF and progressive fibrosing ILDs
- Pirfenidone (anti-fibrotic, anti-inflammatory, anti-oxidant): ASCEND and CAPACITY trials showed reduction in FVC decline; approved for IPF
- Nerandomilast (a pill that blocks the enzyme phosphodiesterase 4; first US approval 2025; the US label covers adults with idiopathic and progressive pulmonary fibrosis and lists no contraindications): in FIBRONEER-IPF, 1,177 people with IPF, most already on nintedanib or pirfenidone, lost 114.7 ml of lung capacity (FVC) over 52 weeks on 18 mg twice daily against 183.5 ml on placebo. Diarrhea affected 41.3% against 16.0%. In FIBRONEER-ILD, 1,176 people with progressive pulmonary fibrosis lost 98.6 ml on 18 mg against 165.8 ml on placebo
- Antifibrotics do not improve lung function; they slow progression
- Immunosuppression is not a treatment for IPF in current practice (prednisone + azathioprine + N-acetylcysteine shown to be harmful in PANTHER-IPF)
- Comorbidities treated alongside IPF: gastroesophageal reflux disease (GERD; omeprazole treats reflux symptoms, while the 2022 guideline conditionally recommends against antacid medication for the purpose of improving breathing outcomes in IPF), pulmonary hypertension, obstructive sleep apnea
- Pulmonary rehabilitation
- Supplemental oxygen for resting or exertional hypoxemia
- Lung transplantation for eligible patients (bilateral preferred; median post-transplant survival ~5 years in IPF)
- Palliative care and advance care planning
CTD-ILD
- SSc-ILD: Nintedanib (SENSCIS trial: 44% reduction in FVC decline); mycophenolate mofetil; cyclophosphamide; tocilizumab for rapidly progressive SSc-ILD
- RA-ILD: Mycophenolate mofetil, azathioprine; rituximab for refractory cases. Methotrexate has been held back over a feared ILD risk, but a case-control study of 410 people with rheumatoid arthritis ILD and 673 with rheumatoid arthritis without ILD found methotrexate use was not associated with an increased risk (adjusted odds ratio 0.43, 95% CI 0.26–0.69), and ILD was detected later in people who had used it (11.4 against 4.0 years)
- Inflammatory myopathy-ILD: High-dose corticosteroids + calcineurin inhibitor (tacrolimus) for anti-synthetase syndrome; rituximab for refractory cases
- Glucocorticoids (steroids): the 2023 American College of Rheumatology and American College of Chest Physicians guideline strongly recommends against them in systemic sclerosis ILD, both as first treatment and after progression, and conditionally recommends them as first treatment in the other autoimmune rheumatic diseases
Progressive Pulmonary Fibrosis
The 2022 ATS/ERS/JRS/ALAT guideline defines progressive pulmonary fibrosis in a person with an ILD other than IPF as at least two of three findings within the past year, with no other explanation: worsening symptoms, progression on imaging, and progression on lung function tests. It conditionally recommends nintedanib and asks for more research on pirfenidone.
Hypersensitivity Pneumonitis
- Antigen avoidance — the most important intervention; can result in stabilization or improvement in early HP
- Systemic corticosteroids (prednisone 0.5–1 mg/kg/day) for acute/subacute HP with significant respiratory compromise; tapered over 4–6 months
- Mycophenolate mofetil, azathioprine for steroid-sparing in chronic HP
- Nintedanib for progressive fibrosing chronic HP (INBUILD trial data support use in progressive fibrosis regardless of underlying ILD subtype)
Organizing Pneumonia
- Prednisone 0.75–1 mg/kg/day for 4–6 weeks, then taper over 6–12 months; rapid clinical and radiological response typical
- Relapse common (30–50%) upon steroid tapering; re-treat with corticosteroids
8. Complications
- Acute exacerbation of IPF (AE-IPF): Sudden, unexplained acceleration of respiratory failure superimposed on stable IPF; bilateral new ground-glass opacities; in-hospital mortality 50–80%; may be triggered by infection, aspiration, procedures, or be idiopathic. Older definitions required an unidentifiable cause; a 2016 international working group proposed a revised definition with diagnostic criteria and a new framework for sudden breathing deterioration in IPF
- Pulmonary hypertension: Develops in 30–85% of IPF patients; worsens prognosis; inhaled treprostinil (INCREASE trial) recently approved for PH-ILD
- Lung cancer: Risk elevated in IPF (particularly squamous cell and adenocarcinoma); cigarette smoking synergism; annual low-dose computed tomography screening recommended
- Venous thromboembolism: Elevated risk; prophylaxis in hospitalized ILD patients
- Infections: Opportunistic infections with immunosuppressive therapy; pneumocystis jirovecii prophylaxis with significant immunosuppression
- Pneumothorax: Spontaneous pneumothorax from ruptured honeycomb cysts; can precipitate acute respiratory failure
- Gastroesophageal reflux disease: Common comorbidity in IPF; microaspiration may perpetuate fibrosis. Earlier guidelines suggested antacid therapy to improve breathing outcomes; the 2022 guideline conditionally recommends against antacid medication and antireflux surgery for that purpose, while noting they may be appropriate for reflux symptoms themselves
- Depression and anxiety: Common; impair quality of life and exercise capacity; warrant specific attention and palliative support
9. Prognosis
Prognosis is highly subtype-dependent:
- IPF: Median survival 2–5 years from diagnosis without antifibrotic therapy; antifibrotics extend survival but do not cure the disease. 5-year survival approximately 20–40%. FVC <70% predicted and DLCO <40% predicted are associated with significantly worse prognosis. In a further analysis of the pooled FIBRONEER trials (mean follow-up 16.7 months), the hazard ratio for death on nerandomilast 18 mg twice daily against placebo was 0.57 (95% CI 0.41–0.78). Time to death was a secondary measure, and the trials' key secondary endpoint was not met, so this result does not settle whether the drug extends life.
- NSIP (idiopathic): Better prognosis than IPF; 5-year survival ~70–80% for cellular NSIP; fibrotic NSIP ~45–90% depending on extent of fibrosis.
- CTD-ILD: Variable; SSc-ILD 10-year survival ~55%; RA-ILD median survival ~2–3 years from ILD diagnosis in studies (better in recent cohorts with modern therapy).
- COP: Excellent prognosis with corticosteroid treatment; 5-year survival >80%.
- Chronic HP: Variable; fibrotic HP with UIP pattern behaves similarly to IPF; non-fibrotic HP with antigen avoidance may improve or stabilize.
The GAP (Gender, Age, Physiology) Index and staging system (incorporating FVC and DLCO) has been validated to predict 1-, 2-, and 3-year mortality in IPF and other fibrotic ILDs.
10. Prevention
- Smoking cessation: Reduces risk of IPF, RB-ILD, DIP, and combined pulmonary fibrosis and emphysema
- Occupational exposure reduction: Engineering controls, personal protective equipment (N95 respirators), regulatory exposure limits for silica, asbestos, beryllium, and other fibrogenic dusts
- Medical surveillance programs for workers with recognized occupational ILD risks
- Antigen avoidance in HP-susceptible individuals (bird fanciers, farmers)
- Drug-induced ILD prevention: Baseline pulmonary evaluation before initiating fibrogenic drugs; monitoring protocols for bleomycin (cumulative dose), amiodarone, methotrexate
- Gastroesophageal reflux disease management: Aggressive acid suppression has been used to minimize microaspiration in IPF patients; the 2022 guideline conditionally recommends against antacid medication for the purpose of improving breathing outcomes in IPF
- Genetic counseling for familial IPF with identified causative mutations
11. Recent Research and Advances
INBUILD Trial: Demonstrated that nintedanib reduces FVC decline in progressive fibrosing ILDs other than IPF (including NSIP, HP, RA-ILD, SSc-ILD), establishing the concept of a common progressive fibrosis phenotype amenable to antifibrotic therapy regardless of specific ILD diagnosis.
Inhaled Treprostinil (INCREASE Trial): Approved in 2021 for pulmonary hypertension associated with ILD; a significant advance as the first approved therapy specifically for PH-ILD, demonstrating improvement in six-minute walk distance and reduction in clinical worsening.
Inhaled Treprostinil in IPF Itself (TETON Trials): The pooled TETON-1 and TETON-2 trials randomized 1,191 people with IPF. At 52 weeks the median change in lung capacity (FVC) was -45.4 ml on inhaled treprostinil against -161.7 ml on placebo; 41 people (6.9%) died against 56 (9.4%). Cough was the most common side effect.
Cryobiopsy: Transbronchial cryobiopsy is gaining acceptance as a less invasive alternative to surgical lung biopsy. Meta-analyses show comparable diagnostic yield with lower morbidity, though pneumothorax and bleeding rates require attention. The 2022 guideline conditionally regards transbronchial cryobiopsy as an acceptable alternative to surgical lung biopsy "in centers with appropriate expertise".
Genomic and Transcriptomic Profiling: Gene expression profiling of transbronchial biopsy samples (a less invasive procedure than surgery, though still a biopsy) can distinguish UIP from non-UIP patterns, potentially reducing need for surgical biopsy. One molecular classifier, validated in 49 patients, identified UIP with 88% specificity and 70% sensitivity. The 2022 guideline made no recommendation for or against genomic classifier testing.
Senescence and Epigenetic Targeting: Senolytic agents (navitoclax, dasatinib + quercetin) targeting senescent AEC II cells are in early-phase clinical trials for IPF. Epigenetic modifications (histone deacetylase inhibition) represent another emerging therapeutic strategy.
Artificial Intelligence in HRCT: Deep learning algorithms can identify UIP and NSIP patterns on HRCT with accuracy approaching expert thoracic radiologists, and can quantify fibrosis extent to track progression.
Glucagon-like peptide-1 Receptor Agonists in ILD: Preliminary data suggests metabolic comorbidities (obesity, diabetes) accelerate ILD progression; glucagon-like peptide-1 agonists may have anti-fibrotic properties beyond glycemic control.
Key Research Papers
- Raghu G, et al. Idiopathic Pulmonary Fibrosis (an Update) and Progressive Pulmonary Fibrosis in Adults: An Official ATS/ERS/JRS/ALAT Clinical Practice Guideline. Am J Respir Crit Care Med. 2022;205(9):e18–e47. — doi:10.1164/rccm.202202-0399ST
- Travis WD, et al. An Official American Thoracic Society/European Respiratory Society Statement: Update of the International Multidisciplinary Classification of the Idiopathic Interstitial Pneumonias. Am J Respir Crit Care Med. 2013;188(6):733–748. — doi:10.1164/rccm.201308-1483ST
- Richeldi L, et al. (INPULSIS). Efficacy and Safety of Nintedanib in Idiopathic Pulmonary Fibrosis. N Engl J Med. 2014;370(22):2071–2082. — doi:10.1056/NEJMoa1402584
- King TE, et al. (ASCEND). A Phase 3 Trial of Pirfenidone in Patients with Idiopathic Pulmonary Fibrosis. N Engl J Med. 2014;370(22):2083–2092. — doi:10.1056/NEJMoa1402582
- Flaherty KR, et al. (INBUILD). Nintedanib in Progressive Fibrosing Interstitial Lung Diseases. N Engl J Med. 2019;381(18):1718–1727. — doi:10.1056/NEJMoa1908681
- Distler O, et al. (SENSCIS). Nintedanib for Systemic Sclerosis–Associated Interstitial Lung Disease. N Engl J Med. 2019;380(26):2518–2528. — doi:10.1056/NEJMoa1903076
- Raghu G, et al. Diagnosis of Idiopathic Pulmonary Fibrosis: An Official ATS/ERS/JRS/ALAT Clinical Practice Guideline. Am J Respir Crit Care Med. 2018;198(5):e44–e68. — doi:10.1164/rccm.201807-1255ST
- Ley B, et al. A multidimensional index and staging system for idiopathic pulmonary fibrosis. Ann Intern Med. 2012;156(10):684–691. — doi:10.7326/0003-4819-156-10-201205150-00004
- Cottin V, et al. Combined pulmonary fibrosis and emphysema: a distinct underrecognised entity. Eur Respir J. 2005;26(4):586–593. — doi:10.1183/09031936.05.00021005
- Idiopathic Pulmonary Fibrosis Clinical Research Network. Prednisone, azathioprine, and N-acetylcysteine for pulmonary fibrosis (PANTHER-IPF). N Engl J Med. 2012;366(21):1968–1977. — doi:10.1056/NEJMoa1113354
- Waxman A, et al. (INCREASE). Inhaled Treprostinil in Pulmonary Hypertension Due to Interstitial Lung Disease. N Engl J Med. 2021;384(4):325–334. — doi:10.1056/NEJMoa2008470
- Spagnolo P, Rossi G, Cavazza A, et al. Hypersensitivity Pneumonitis: A Comprehensive Review. J Investig Allergol Clin Immunol. 2015;25(4):237–250. — PubMed PMID: 26310038
- Seibold MA, et al. A common MUC5B promoter polymorphism and pulmonary fibrosis. N Engl J Med. 2011;364(16):1503–1512. — doi:10.1056/NEJMoa1013660
- Collard HR, et al. Acute Exacerbation of Idiopathic Pulmonary Fibrosis: An International Working Group Report. Am J Respir Crit Care Med. 2016;194(3):265–275. — doi:10.1164/rccm.201604-0801CI
- Johannson KA, Collard HR. Acute exacerbation of idiopathic pulmonary fibrosis: a proposal. Curr Respir Care Rep. 2013;2(4):233–240. — doi:10.1007/s13665-013-0065-x
- Juge PA, Lee JS, Lau J, et al. Methotrexate and rheumatoid arthritis associated interstitial lung disease. Eur Respir J. 2021;57(2). — PubMed PMID: 32646919
- Chua CG, Fan Z, Phua HP, et al. A comparison of clinical phenotype and outcomes in anti- melanoma differentiation-associated protein 5 dermatomyositis and anti-synthetase syndrome in a multiethnic cohort in Singapore. Front Med (Lausanne). 2026;13:1969582. — PubMed PMID: 42935629
- Raghu G, Flaherty KR, Lederer DJ, et al. Use of a molecular classifier to identify usual interstitial pneumonia in conventional transbronchial lung biopsy samples: a prospective validation study. Lancet Respir Med. 2019;7(6):487–496. — PubMed PMID: 30948346
- Richeldi L, Azuma A, Cottin V, et al. Nerandomilast in Patients with Idiopathic Pulmonary Fibrosis. N Engl J Med. 2025;392(22):2193–2202. — PubMed PMID: 40387033
- Maher TM, Assassi S, Azuma A, et al. Nerandomilast in Patients with Progressive Pulmonary Fibrosis. N Engl J Med. 2025;392(22):2203–2214. — PubMed PMID: 40388329
- Oldham JM, Assassi S, Azuma A, et al. Effect of nerandomilast on survival in patients with pulmonary fibrosis. Eur Respir J. 2026. — PubMed PMID: 42532543
- Nathan SD, Smith P, Deng C, et al. Combined results of the TETON-1 and TETON-2 Trials of Inhaled Treprostinil for Idiopathic Pulmonary Fibrosis. Am J Respir Crit Care Med. 2026. — PubMed PMID: 42776606
- Johnson SR, Bernstein EJ, Bolster MB, et al. 2023 American College of Rheumatology (ACR)/American College of Chest Physicians (CHEST) Guideline for the Treatment of Interstitial Lung Disease in People with Systemic Autoimmune Rheumatic Diseases. Arthritis Rheumatol. 2024;76(8):1182–1200. — PubMed PMID: 38978310
- Heinzerling A, Flattery J, Cummings KJ, et al. Silicosis among Workers Fabricating Engineered Stone ("Quartz") Countertops in California, 2019-2026. NEJM Evid. 2026;5(9):EVIDpha2600187. — PubMed PMID: 42584953
- Fazio JC, Gandhi SA, Flattery J, et al. Silicosis Among Immigrant Engineered Stone (Quartz) Countertop Fabrication Workers in California. JAMA Intern Med. 2023;183(9):991–998. — PubMed PMID: 37486642
PubMed Topic Searches
The following PubMed topic searches surface the current peer-reviewed literature on Interstitial Lung Disease. Each link opens a live PubMed query; results update as new papers are indexed.
- PubMed: Search: interstitial lung disease
- PubMed: Search: idiopathic pulmonary fibrosis
- PubMed: Search: pirfenidone pulmonary fibrosis
- PubMed: Search: nintedanib pulmonary fibrosis
- PubMed: Search: hypersensitivity pneumonitis
- PubMed: Search: nonspecific interstitial pneumonia
- PubMed: Search: cryptogenic organizing pneumonia
- PubMed: Search: connective tissue disease interstitial lung
- PubMed: Search: ILD high resolution CT
- PubMed: Search: lung transplantation pulmonary fibrosis
- PubMed: Search: progressive pulmonary fibrosis
- PubMed: Search: ILD bronchoalveolar lavage
Connections
- Pulmonology
- Sarcoidosis
- Pulmonary Hypertension
- Rheumatoid Arthritis
- Acute Respiratory Distress Syndrome
- Vitamin D3
- Shortness of Breath
- Chronic Cough
- Pneumonia
- Pulmonary Embolism
- Lupus
- Sjogren's Syndrome
- Fatigue
- Heart Failure
- Quercetin
- Cancer
- Diabetes
- Chronic Obstructive Pulmonary Disease
- Inflammatory Markers
- Lung Cancer
- Rheumatoid Arthritis
- Pulmonary Fibrosis — the scarring end-stage pattern shared by the progressive fibrosing ILDs, including IPF.