⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a triptan taken early in an attack gives meaningful vertigo relief and that vestibular rehabilitation produces clinically meaningful improvements in vestibular migraine. This page keeps it as a report of what people, websites or other media say.
Vestibular Migraine
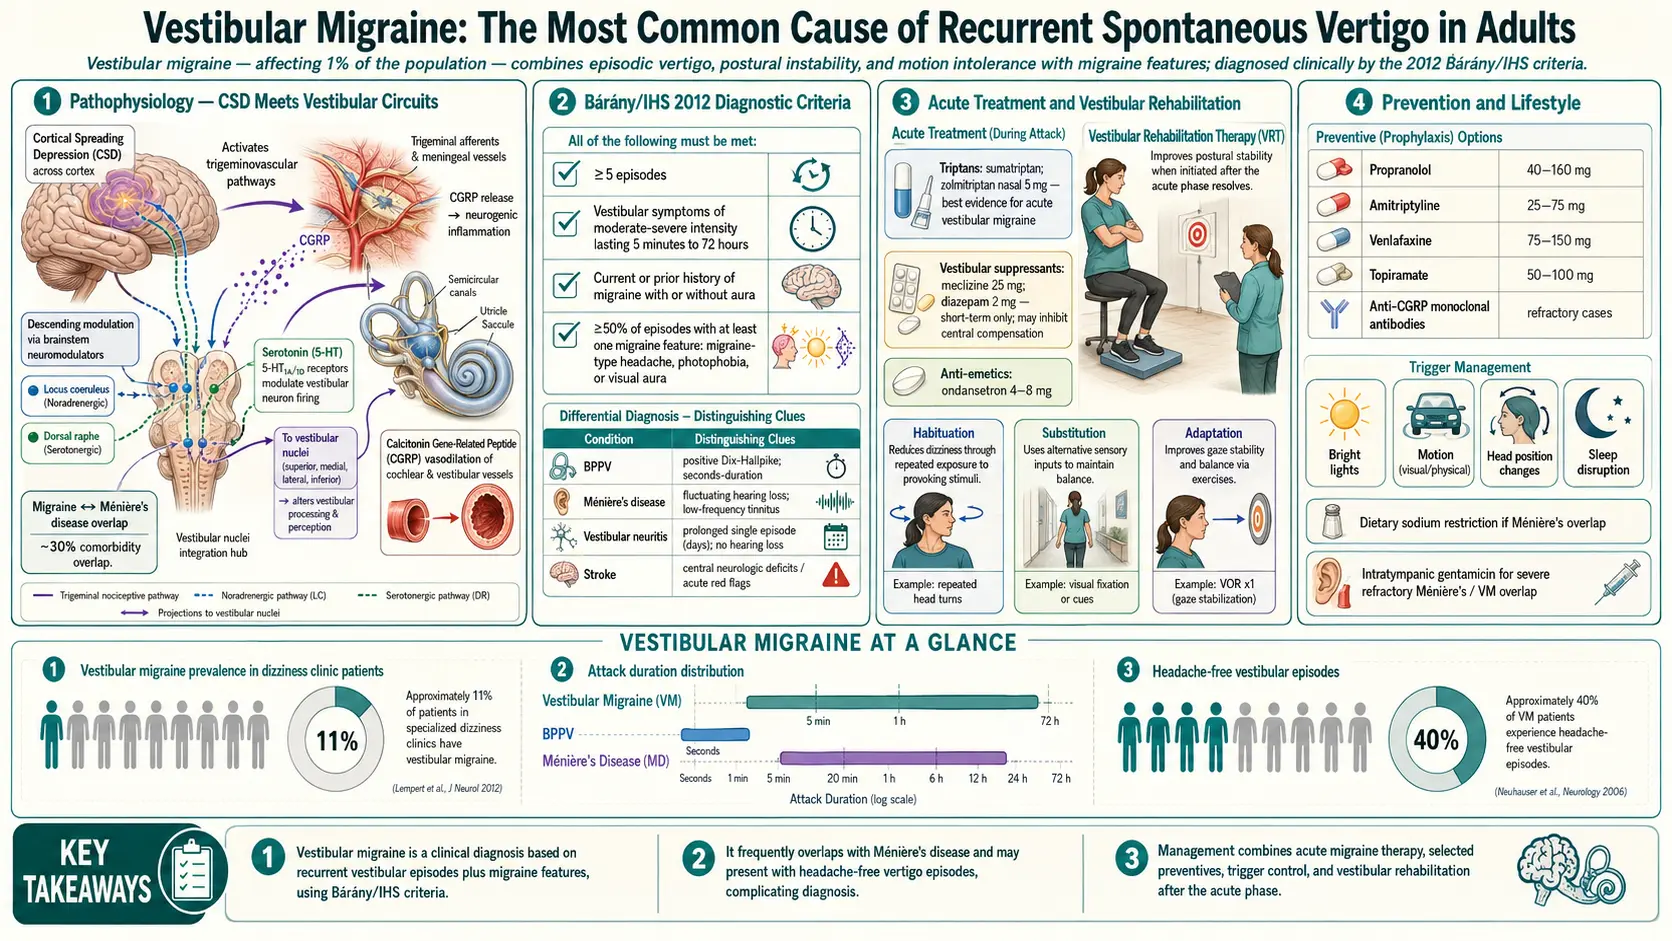
Table of Contents
- What Vestibular Migraine Is
- How Common — and How Often Missed
- The Official Criteria (Bárány & ICHD-3)
- What the Attacks Actually Feel Like
- Attacks Without Head Pain
- What Else It Could Be
- Testing — What to Expect
- Stopping an Attack in Progress
- Preventive Medications
- Vestibular Rehabilitation Therapy
- Visual Motion Desensitization
- Triggers and Daily Habits
- When PPPD Shows Up Too
- The Postural Orthostatic Tachycardia Syndrome Overlap Trap
- Key Research Papers
- Connections
- Featured Videos
What Vestibular Migraine Is
Vestibular migraine is the dizzy cousin of the classic headache. Instead of — or sometimes in addition to — a throbbing one-sided head pain, the migraine brain generates episodes of vertigo, unsteadiness, and motion intolerance that can last anywhere from five minutes to three days. If you have ever spent an afternoon convinced the room was pitching like a boat while your partner insisted the room was perfectly still, you know the feeling. It is not an ear problem. It is not anxiety. It is a migraine attack that decided to express itself through the balance system instead of the pain system.
The condition has been under the medical radar for decades. Most patients go through two or three ENTs, a cardiologist, and a psychiatrist before a neurologist finally puts the label on it. That matters, because once it has a name, it has a treatment playbook — and most of it is borrowed straight from classic migraine management.
How Common — and How Often Missed
Vestibular migraine affects roughly 1% of the adult population over a lifetime: a 2006 survey of a representative sample of 4,869 German adults found a lifetime prevalence of 0.98% and a 12-month prevalence of 0.89% ( PubMed PMID: 17000973). That makes it the most common neurological cause of recurrent spontaneous vertigo. In a 2001 German study of 200 consecutive patients at a specialty dizziness clinic it accounted for 7% of patients (and 9% of 200 patients at a migraine clinic) ( PubMed PMID: 11222783) — more than Meniere's disease and more than BPPV in some case series.
Despite being common, it is massively under-diagnosed. In the 2006 Neuhauser population study in Germany, two thirds of people with vestibular migraine had consulted a doctor, but only 20% of those had been given the diagnosis ( PubMed PMID: 17000973). The usual fate is a label of "anxiety," "inner ear infection," "chronic sinus problem," or simply "we can't find anything wrong with you." The average patient waits years for a correct answer.
Women are affected roughly three times more often than men, and the peak age of onset clusters in the thirties and forties — often in people who had classic migraine as teenagers, lost the headaches for a decade, and now have dizziness instead. Many patients also have a first-degree relative with migraine.
The Official Criteria (Bárány & ICHD-3)
In 2012 the Bárány Society (the international vestibular-research body) and the International Headache Society jointly published formal diagnostic criteria. Vestibular migraine was placed in the appendix of the International Classification of Headache Disorders, 3rd edition (ICHD-3, 2013 and 2018), the section the International Headache Society uses as a first step for new disorders. In 2022 the two societies re-published the criteria with a literature update and left the 2012 rules unchanged ( PubMed PMID: 34719447). A diagnosis of definite vestibular migraine requires:
- At least five episodes of vestibular symptoms of moderate or severe intensity.
- Each episode lasting between 5 minutes and 72 hours.
- A current or prior history of migraine with or without aura, by ICHD criteria.
- During at least 50% of the episodes, at least one migraine feature: a migraine-type headache (one-sided, throbbing, moderate-severe, worsened by activity), photophobia and phonophobia, or a visual aura.
- Symptoms not better explained by another vestibular or headache disorder.
The "50% of episodes" rule is what trips up so many patients. You do not need headache with every attack. You just need migraine features with at least half of them — and the features can be any combination of headache, light sensitivity, sound sensitivity, or visual aura. There is also a looser "probable vestibular migraine" category for patients who meet some but not all points. Probable vestibular migraine is not in the ICHD; the 2022 criteria paper says it may be added to a later version once more evidence has accumulated. Treatment reviews have included people in both categories (the 2023 Cochrane reviews below covered adults with definite or probable vestibular migraine).
What the Attacks Actually Feel Like
Vestibular migraine does not look like one thing. Different attacks in the same person can feel completely different. The common varieties:
- Internal vertigo. A sensation that you are spinning, tilting, rocking, or floating even though you are sitting still. Often described as "being on a boat" or "walking on a trampoline."
- External vertigo. The room spins around you. Less common in vestibular migraine than in BPPV or Meniere's, but it happens.
- Positional vertigo. Symptoms triggered or worsened by head position changes — rolling over in bed, looking up to a shelf, tilting to tie a shoe.
- Motion sensitivity. Car rides, elevators, escalators, and walking on uneven ground set off symptoms. Many patients describe feeling "seasick on land."
- Visual motion intolerance. Grocery-store aisles, scrolling on a phone, busy wallpaper patterns, optical-flow scenes in movies, or driving in the rain all trigger dizziness. This is one of the most specific features.
- Imbalance and gait unsteadiness. A sense of veering, needing to touch walls, or "walking drunk."
- Non-spinning dizziness. Lightheadedness, woozy-head, cognitive fog, and the sense that your brain is running through syrup.
Attacks last anywhere from 5 minutes to 72 hours. Roughly a third of patients have short attacks (minutes to a few hours), a third medium (several hours to a day), and a third longer multi-day events. Between attacks most people feel completely normal — although a meaningful subset develop persistent low-grade dizziness that becomes its own problem (see PPPD).
Attacks Without Head Pain
Here is the single most important fact for under-diagnosed patients: in at least 30% of vestibular-migraine attacks there is no headache at all. Some patients go years with dizzy spells and never have a simultaneous headache, which is why ENTs, cardiologists, and psychiatrists keep striking out — nobody connects the dots to migraine. In the 2006 German population survey, only 24% of people with vestibular migraine always had a headache with their vertigo ( PubMed PMID: 17000973).
What tips it off in headache-free attacks is the other migraine features: light sensitivity that makes you want to close the blinds, sound sensitivity that makes normal conversation feel like an assault, visual aura (zigzag lines, shimmering spots, tunnel vision), food cravings or aversions, nausea, and a post-attack "migraine hangover" of fatigue and foggy thinking for a day or two afterward. When any of those travel with the dizzy spells, they are the features that point clinicians toward vestibular migraine.
What Else It Could Be
Before settling on vestibular migraine, a good workup rules out the look-alikes:
- BPPV (benign paroxysmal positional vertigo). Loose crystals (otoconia) in the inner ear cause brief, intense spinning with specific head positions — usually rolling over in bed or looking up. Attacks last under a minute and are reliably triggered. The Dix-Hallpike maneuver at the bedside diagnoses it, and an Epley maneuver fixes it in one or two visits. BPPV can coexist with vestibular migraine, and when both are present each is treated.
- Meniere's disease. Episodes of vertigo lasting 20 minutes to 12 hours, accompanied by low-frequency hearing loss, ear fullness, and tinnitus. An audiogram during or shortly after an attack shows the characteristic low-frequency sensorineural hearing loss that vestibular migraine does not. See the vertigo and Meniere's page for the full breakdown.
- PPPD (persistent postural-perceptual dizziness). A chronic, daily dizziness triggered by upright posture, self-motion, and visual motion, lasting three months or longer. Often develops after a vestibular-migraine attack, a concussion, or a vestibular-neuritis episode. PPPD and vestibular migraine commonly coexist.
- Posterior-circulation transient ischemic attack (TIA) or stroke. Sudden-onset vertigo with additional neurological symptoms (double vision, slurred speech, numbness, weakness, trouble walking) that persist rather than come and go. This is an emergency. Isolated vertigo without other neurological features is rarely stroke, but new-onset severe vertigo in anyone over 60 with vascular risk factors is treated by hospitals as urgent and usually imaged.
- Vestibular neuritis / labyrinthitis. A one-time, days-to-weeks episode of severe constant vertigo following a viral illness. It does not recur in the typical migraine pattern.
- Medication and alcohol effects. Many drugs cause dizziness, so a review of the medication list is part of the workup before migraine is blamed.
Testing — What to Expect
Vestibular migraine is a clinical diagnosis. There is no blood test, no imaging finding, no electrophysiology result that confirms it. Testing is done mainly to rule out the mimics above. The workup usually includes some combination of:
- Audiogram (hearing test). Essential for excluding Meniere's disease. Vestibular migraine audiograms are typically normal; Meniere's shows low-frequency sensorineural hearing loss.
- VNG (videonystagmography). Records eye movements in response to positional changes, warm/cold water in the ears (caloric testing), and visual targets. Often normal between attacks in vestibular migraine; may show minor non-specific findings.
- VEMP (vestibular evoked myogenic potentials). Measures how the inner-ear otolith organs respond to sound. Usually normal in vestibular migraine; can help distinguish from Meniere's and superior canal dehiscence.
- Video head impulse test (vHIT). Rapid head turns with eye-tracking goggles check each of the six semicircular canals. Usually normal in vestibular migraine.
- Magnetic resonance imaging (MRI) of the brain (with attention to posterior fossa). Ordered once to rule out structural causes — acoustic neuroma, Chiari malformation, multiple sclerosis plaques, or posterior-fossa tumors. Typically normal in vestibular migraine.
- Electrocardiogram (ECG) and orthostatic vitals. If the dizziness has a lightheaded flavor that happens on standing, clinicians check for orthostatic hypotension or postural orthostatic tachycardia syndrome (POTS) before assuming migraine.
The frustrating and liberating truth: most of these tests come back normal. That is the diagnostic signature. Normal ear testing plus a personal or family history of migraine plus episodic dizzy spells with migraine features equals vestibular migraine.
Stopping an Attack in Progress
Acute-attack treatment is the weakest part of the vestibular-migraine playbook. Evidence is thin and mostly extrapolated from headache migraine: a 2023 Cochrane review found no placebo-controlled trials for any attack treatment other than triptans ( PubMed PMID: 37042545). What is commonly tried:
- Triptans (sumatriptan, rizatriptan, zolmitriptan). Evidence is very limited. Some patients and clinicians report vertigo relief when a triptan is taken early in the attack, but the placebo-controlled trials did not show a clear difference from placebo. The 2023 Cochrane review found only two placebo-controlled trials (133 people), one of rizatriptan 10 mg and one of zolmitriptan 2.5 mg. Triptans may make little or no difference to how many people’s vertigo improves within two hours (risk ratio 0.84, 95% CI 0.66 to 1.07), and the evidence was rated very low certainty ( PubMed PMID: 37042545). Clinicians often try them in people who already respond to triptans for classic migraines. The standard triptan cautions are uncontrolled high blood pressure and coronary disease. See the triptans and gepants page.
- Anti-emetics. The most reliably helpful class. Promethazine (12.5–25 mg), ondansetron (4–8 mg), and prochlorperazine all reduce nausea and have mild vestibular-suppressant effect. They also help you sleep through the attack, which is often the fastest route to ending it.
- Meclizine (12.5–25 mg). An over-the-counter antihistamine with vestibular-suppressant properties. Works for many patients for short attacks. It is generally kept for short-term use — chronic vestibular suppression blocks the brain's natural adaptation and can make symptoms worse.
- Nonsteroidal anti-inflammatory drugs (NSAIDs). Naproxen or ibuprofen early in an attack sometimes aborts the cascade, particularly if headache is part of the picture.
- Rest in a dark, quiet room. Unglamorous but effective. Closing your eyes removes visual motion input and lets the vestibular system settle.
Gepants (rimegepant, ubrogepant) have not been formally studied in vestibular migraine but are used empirically in clinics, often when triptans have failed or cannot be used.
Preventive Medications
When attacks are frequent (more than two to four per month), long, or disabling, clinicians usually consider a daily preventive. The menu mirrors classic migraine preventives:
- Topiramate (25–100 mg daily, titrated up over weeks). Clinicians commonly start with it. Can cause cognitive slowing, tingling, and weight loss.
- Propranolol (40–160 mg daily, divided or long-acting). A beta-blocker with strong migraine-prevention evidence. Sometimes chosen when anxiety or high blood pressure is also present. Fatigue and a lower heart-rate response during exercise are known side effects.
- Amitriptyline or nortriptyline (10–50 mg at night). Tricyclic antidepressants at low doses. Helpful if sleep or comorbid tension-type headache is part of the picture.
- Venlafaxine (37.5–150 mg daily). A serotonin-norepinephrine reuptake inhibitor used in vestibular migraine, often when anxiety or depression coexist. The 2023 Cochrane review found no placebo-controlled trials of it in vestibular migraine.
- Flunarizine (5–10 mg at night). A calcium-channel blocker that is first-line in Europe but not available in the US. It is one of only two drugs tested in controlled trials for vestibular migraine (against no treatment, in 79 people), but that evidence was rated very low certainty.
- CGRP monoclonal antibodies (erenumab, fremanezumab, galcanezumab) and gepants. Originally studied in classic migraine; small series suggest benefit in vestibular migraine as well. See the CGRP inhibitors page.
- Supplements. Magnesium (400 mg glycinate daily), riboflavin (400 mg daily), and Coenzyme Q10 (100 mg three times daily) have reasonable evidence in migraine generally. See the magnesium and riboflavin page.
A 2023 Cochrane review found only three trials of preventive drugs against placebo or no treatment in vestibular migraine (209 people): one of metoprolol 95 mg daily against placebo (130 people), and two of flunarizine 10 mg daily against no treatment (79 people). All of the evidence was low or very low certainty, the reviewers could draw no meaningful conclusions from the numbers, and no trial evidence was found for the other drug groups. So it is not known from trials whether any preventive drug works for vestibular migraine; these drugs are used because they are established for headache migraine and the two conditions are believed to share the same underlying mechanism ( PubMed PMID: 37073858).
Preventives are usually given an eight-to-twelve-week trial at an adequate dose before judging whether they work. Switching too early is described as the most common reason preventives "fail." A headache/dizziness diary kept during trials often makes the signal clearer in retrospect than day to day.
Vestibular Rehabilitation Therapy
If medications are half the answer, vestibular rehabilitation therapy (VRT) is the other half — and it is routinely under-prescribed. VRT is a structured physical-therapy program delivered by a PT or audiologist trained in vestibular disorders. The goal is to teach your brain to recalibrate when the balance signals from the inner ear, the eyes, and the body (proprioception) disagree.
A typical program runs eight to twelve weeks, with in-person sessions once or twice weekly plus daily home exercises. The work falls into three buckets:
- Habituation exercises. Deliberately, repeatedly exposing yourself to the positions and motions that provoke dizziness, in small doses, so the brain eventually stops over-reacting. Example: the Cawthorne-Cooksey protocol, a graded sequence starting with simple eye movements in bed and progressing to standing, walking, bending, and ball-throwing while moving.
- Gaze stabilization. VOR-x1 and VOR-x2 exercises: staring at a thumb or a letter on the wall while turning your head side-to-side or up-and-down, gradually faster. Retrains the vestibulo-ocular reflex so the visual world stays stable when you move.
- Balance and gait training. Standing on foam, tandem walking, walking with head turns, eyes-closed balance work. Rebuilds the somatosensory and visual contributions that compensate when the vestibular system is glitchy.
Vestibular rehabilitation therapy produced clinically meaningful improvements in dizziness, balance, and quality of life across vestibular disorders, including vestibular migraine. A 2018 review of six studies by Alghadir and Anwer found that earlier studies reported improvements in headache and migraine-related disability with vestibular rehabilitation, but concluded that it is “difficult to provide conclusive evidence” that it reduces vestibular symptoms in vestibular migraine, and called for more randomized trials ( PubMed PMID: 29946294). A 2023 Cochrane review of non-drug prevention found only three small trials against placebo or no treatment (319 people): one of a probiotic, one of cognitive behavioural therapy and one of vestibular rehabilitation (40 people). All the evidence was low or very low certainty, and the authors were “unsure whether any of these interventions may be effective” ( PubMed PMID: 37042522). The single strongest predictor of success is described as daily home practice — skipping the homework kills the effect. Referrals usually go specifically to a "vestibular-trained physical therapist" (not just any PT).
Visual Motion Desensitization
If grocery stores, scrolling phones, busy patterns, or driving in rain are triggers, a specific subset of VRT called visual motion desensitization is used. Therapists use moving optokinetic stripe patterns, VR headsets, or videos of train rides and grocery-store aisles. The patient watches, lets the discomfort rise, and stays with it until it settles — building tolerance the way exposure therapy builds tolerance in anxiety.
A cheap at-home version people describe: two minutes of a first-person rollercoaster video with the volume off, once or twice a day, stopping before genuine sickness sets in and progressing slowly. This is habituation, not punishment — pushing past severe symptoms backfires.
Triggers and Daily Habits
Vestibular-migraine triggers overlap almost completely with classic migraine triggers:
- Sleep. Both sleep deprivation and sleeping in trigger attacks. A consistent schedule — same bedtime and wake time seven days a week — is the usual approach.
- Stress (and the let-down after stress). Saturday-morning and vacation-day attacks are classic.
- Dehydration and skipped meals. Steady water intake and regular meals matter more than any specific food.
- Hormonal shifts. Many women note flares around menstruation. See the menstrual-migraine page.
- Dietary triggers. Aged cheeses, red wine, cured meats, chocolate, MSG-heavy foods, and artificial sweeteners are common culprits but vary wildly by person. See the diet-triggers page for a structured elimination approach.
- Weather and barometric pressure changes. Real but unavoidable; noting them in a diary helps anticipate high-risk days.
- Visual overload. Long screen hours, fluorescent lighting, busy visual environments. Blue-light filters and breaks every 20–30 minutes help some patients.
- Caffeine. Steady moderate intake is fine; the problem is variability. Skipping your usual cup or doubling it both provoke attacks.
When PPPD Shows Up Too
Persistent postural-perceptual dizziness (PPPD) is a chronic, daily, non-spinning dizziness that often moves in after a vestibular-migraine attack and refuses to leave. The defining features are three months or more of daily symptoms, worse when upright, worse with self-motion, and worse in visually complex environments. The brain gets stuck in a high-alert balance-scanning mode and cannot stand down.
Treatments studied for PPPD include selective serotonin reuptake inhibitor (SSRI) or serotonin-norepinephrine reuptake inhibitor (SNRI) medication (sertraline, escitalopram, venlafaxine at migraine-preventive doses), vestibular rehabilitation with a focus on visual-motion desensitization, and cognitive behavioral therapy targeting the hypervigilance. The evidence is limited: a 2023 Cochrane review found no placebo-controlled randomized trial of these medicines in PPPD that met its rules, and a 2025 meta-analysis favored an SSRI combined with vestibular rehabilitation over either one alone; no trial has tested all three together. Treating any underlying vestibular migraine at the same time matters — unchecked migraine attacks keep re-seeding the PPPD pattern.
Dizziness labelled "anxiety" that is clearly worse in big open stores and on escalators fits the PPPD pattern, which is diagnosed by clinicians who recognize the syndrome.
The Postural Orthostatic Tachycardia Syndrome Overlap Trap
This is the single most common mis-attribution in dizzy-patient land. postural orthostatic tachycardia syndrome (POTS) and vestibular migraine share enormous phenotypic overlap: both produce dizziness, fatigue, brain fog, exercise intolerance, and headache, and both disproportionately affect women in their thirties. Many patients have both. Some have only one but end up treated for the wrong one.
The distinguishing questions:
- Does standing up reliably make it worse within minutes? Postural orthostatic tachycardia syndrome, yes. Vestibular migraine, usually no.
- Does lying down quickly fix it? Postural orthostatic tachycardia syndrome, yes. Vestibular migraine, not particularly.
- Is the dizziness spinning or lightheaded? Vestibular migraine is usually spinning or rocking. Postural orthostatic tachycardia syndrome is usually lightheaded — the kind that precedes a faint.
- Does your heart race when you stand? A sustained ≥ 30 bpm increase within 10 minutes of standing (≥ 40 for teenagers) is the postural orthostatic tachycardia syndrome criterion. It can be checked at home with a pulse oximeter or fitness watch.
- Do visual-motion environments (grocery stores, scrolling) make it worse? Strong vestibular-migraine signal.
- Does salt and fluid loading help? Postural orthostatic tachycardia syndrome, dramatically. Vestibular migraine, negligibly.
When both are present, both are treated. Beta-blockers like propranolol are one of the lucky drugs that help each condition, which makes the decision tree less fraught. See the postural orthostatic tachycardia syndrome subtypes page for how to tease apart the flavors of dysautonomia when the overlap is stubborn.
Key Research Papers
- Lempert T, et al. Vestibular migraine: diagnostic criteria. Bárány Society / International Headache Society consensus. J Vestib Res. 2012. — doi:10.3233/VES-2012-0453
- Neuhauser H, et al. The interrelations of migraine, vertigo, and migrainous vertigo. Neurology. 2001. — doi:10.1212/WNL.56.4.436
- Furman JM, Marcus DA, Balaban CD. Vestibular migraine: clinical aspects and pathophysiology. Lancet Neurol. 2013;12(7):706-15. — doi:10.1016/s1474-4422(13)70107-8
- Alghadir AH, Anwer S. Effects of Vestibular Rehabilitation in the Management of a Vestibular Migraine: A Review. Front Neurol. 2018;9:440. — PubMed PMID: 29946294
- Neuhauser HK, Radtke A, von Brevern M, Feldmann M, Lezius F, Ziese T, Lempert T. Migrainous vertigo: prevalence and impact on quality of life. Neurology. 2006;67(6):1028-33. — PubMed PMID: 17000973
- Lempert T, Olesen J, Furman J, Waterston J, Seemungal B, Carey J, Bisdorff A, Versino M, Evers S, Kheradmand A, Newman-Toker D. Vestibular migraine: Diagnostic criteria. J Vestib Res. 2022;32(1):1-6. — PubMed PMID: 34719447
- Webster KE, Dor A, Galbraith K, Haj Kassem L, Harrington-Benton NA, Judd O, Kaski D, Maarsingh OR, MacKeith S, Ray J, Van Vugt VA, Burton MJ. Pharmacological interventions for acute attacks of vestibular migraine. Cochrane Database Syst Rev. 2023;4(4):CD015322. — PubMed PMID: 37042545
- Webster K, Dor A, Galbraith K, Kassem LH, Harrington-Benton N, Judd O, Kaski D, Maarsingh O, MacKeith S, Ray J, Van Vugt V, Burton M. Pharmacological interventions for prophylaxis of vestibular migraine. Cochrane Database Syst Rev. 2023;2023(4):CD015187. — PubMed PMID: 37073858
- Webster KE, Dor A, Galbraith K, Haj Kassem L, Harrington-Benton NA, Judd O, Kaski D, Maarsingh OR, MacKeith S, Ray J, Van Vugt VA, Burton MJ. Non-pharmacological interventions for prophylaxis of vestibular migraine. Cochrane Database Syst Rev. 2023;4(4):CD015321. — PubMed PMID: 37042522
- Webster KE, Harrington-Benton NA, Judd O, Kaski D, Maarsingh OR, MacKeith S, Ray J, Van Vugt VA, Burton MJ. Pharmacological interventions for persistent postural-perceptual dizziness (PPPD). Cochrane Database Syst Rev. 2023;3(3):CD015188. — PubMed PMID: 36906836
- Zheng Y, Guo Z, Liu X, et al. Effect of conservative therapy for persistent postural-perceptual dizziness: a systematic review and meta-analysis. Front Psychiatry. 2025;16:1676218. — PubMed PMID: 41244873
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on vestibular migraine diagnosis, treatment, and comorbidities:
- PubMed: Vestibular migraine diagnosis and Barany criteria
- PubMed: Vestibular migraine preventive treatment
- PubMed: Vestibular migraine acute treatment with triptans
- PubMed: Vestibular rehabilitation therapy in migraine
- PubMed: Vestibular migraine and persistent postural-perceptual dizziness
- PubMed: Vestibular migraine versus Meniere's disease
- PubMed: Vestibular migraine and POTS overlap
- PubMed: Flunarizine for vestibular migraine
Connections
- Pain & Allergy
- Postural Orthostatic Tachycardia Syndrome
- Migraine Overview
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Magnesium, Riboflavin, and Supplements
- Menstrual Migraine and Hormonal Triggers
- Diet Triggers and Elimination Protocol
- CGRP Inhibitors and Preventives
- Triptans and Gepants — Acute Treatment
- Vertigo and Meniere's Disease
- Chronic Migraine and Medication Overuse
- Aura and Visual Disturbances
- Mast Cell Activation Syndrome
- Chronic Fatigue Syndrome
- Dizziness
- Anxiety
- Magnesium
- Tinnitus
- Migraine in Pregnancy and Breastfeeding
- Headache — the head-pain symptom that is absent from at least 30% of vestibular-migraine attacks.