Menstrual Migraine and Hormonal Triggers
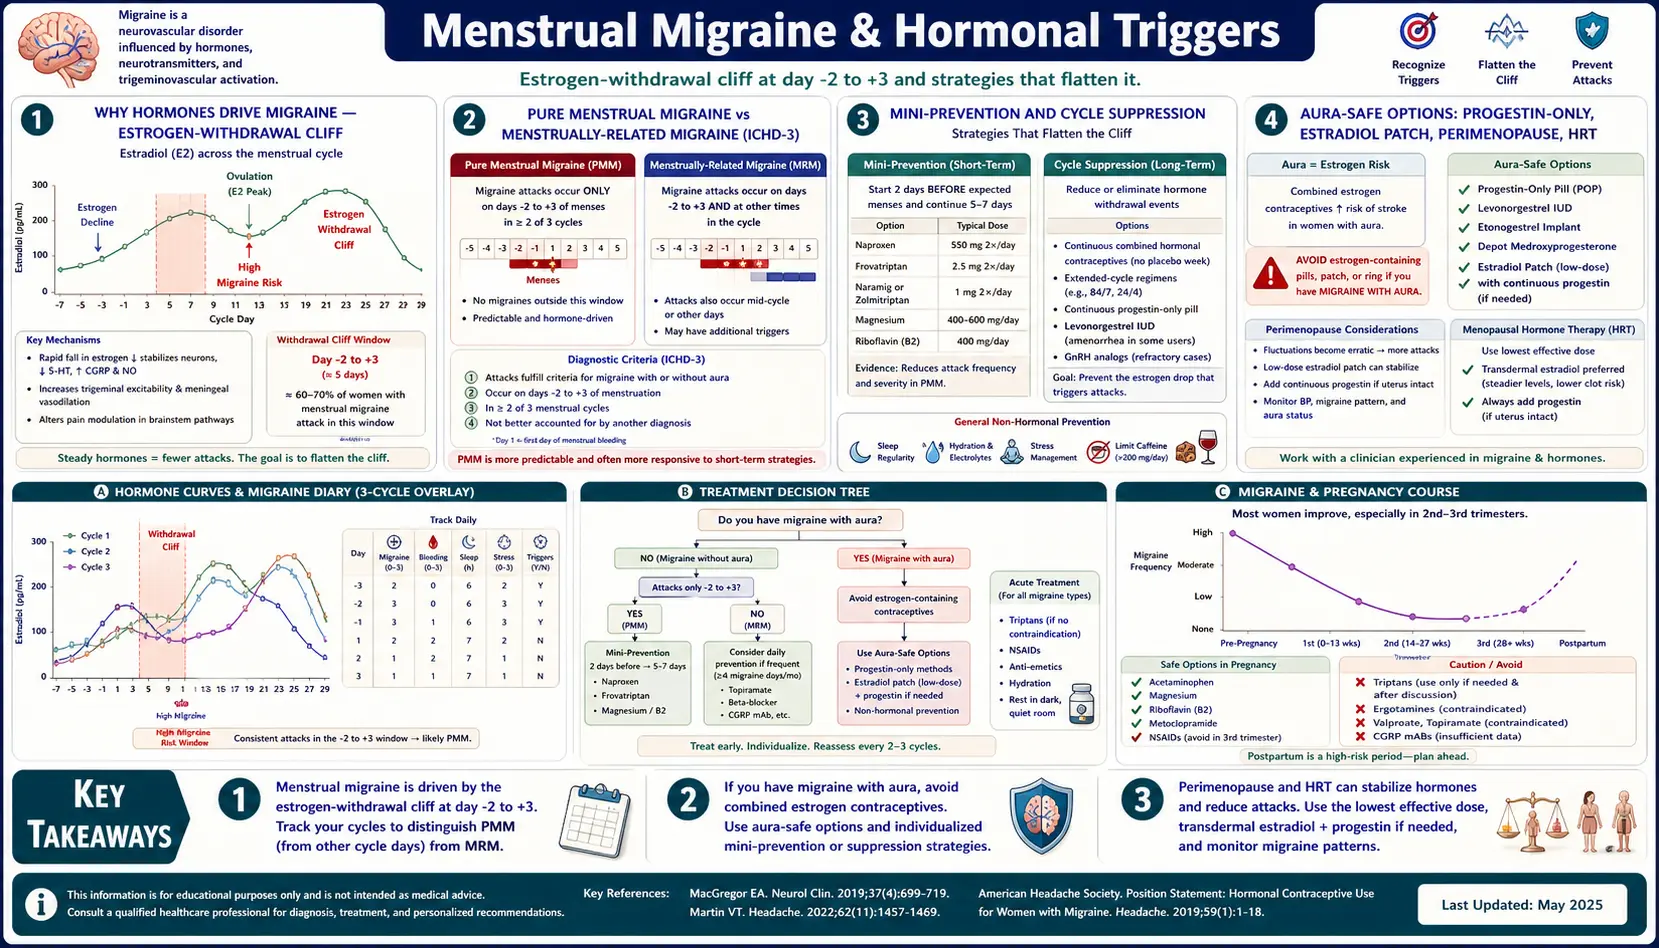
Table of Contents
- Why Hormones Drive Migraine
- The Estrogen-Withdrawal Hypothesis
- Pure Menstrual Migraine vs. Menstrually-Related Migraine
- The Headache Diary — Three Cycles to a Diagnosis
- Short-Term ("Mini") Prevention Around Your Period
- Continuous-Dose Contraceptives — Suppressing the Cycle
- The Aura Problem and Stroke Risk
- Progestin-Only Options for Aura Patients
- Transdermal Estradiol — MacGregor's Add-Back Strategy
- Perimenopause — When It Gets Worse Before It Gets Better
- Hormone Replacement Therapy Decisions — Transdermal, Body-Identical, Cyclic vs. Continuous
- Surgical Menopause and Oophorectomy
- Pregnancy, Postpartum, and Breastfeeding
- Endometriosis, Adenomyosis, Polycystic Ovary Syndrome, Thyroid, and PMDD
- The Steps Described for Menstrual Migraine, in Order
- Key Research Papers
- Connections
- Featured Videos
Why Hormones Drive Migraine
Before puberty, boys and girls get migraine at roughly the same rate. After puberty, women outnumber men about three to one. The gap opens the year estrogen begins cycling and narrows again after menopause. That single epidemiological fact tells you almost everything you need to know: migraine in women is, to a large extent, a hormonally-driven disease.
About 60% of women with migraine notice attacks clustered around their period. For roughly 10–14%, every single attack is tied to the menstrual window. Menstrual attacks tend to be longer, more severe, less responsive to the usual acute medications, and more likely to recur within 24 hours. They are not in your head, not imagined, and not a character flaw — they are a predictable neurobiological response to a hormone that is falling out from under your brain once a month.
The good news: because menstrual migraine is predictable, it is one of the few migraine subtypes where you can schedule prevention. You know the enemy's arrival date. That changes the strategy.
The Estrogen-Withdrawal Hypothesis
The dominant explanation for why periods trigger migraine is the estrogen-withdrawal hypothesis, articulated most clearly by British headache specialist Anne MacGregor. The idea is straightforward. During the late luteal phase (the week before your period), estrogen levels are relatively high. Two to three days before bleeding begins, estrogen plummets. That steep drop — not the low level itself — is what destabilizes the trigeminovascular system and lowers the migraine threshold.
Evidence supporting this model:
- In MacGregor's 2006 study, 38 women with regular cycles were followed for three cycles with daily urine hormone tests and a fertility monitor. Attacks were significantly more frequent than expected in the late luteal/early follicular phase, when estrogen was falling, and less frequent while estrogen was rising. The authors concluded that this supports a perimenstrual (not post-ovulation) estrogen-withdrawal trigger, and that rising estrogen appears to give some protection.
- Attacks cluster in the narrow window from two days before bleeding (day -2) to three days after it starts (day +3) — exactly the interval of steepest estrogen decline.
- Supplemental estrogen during that window has given mixed trial results: in one trial attacks fell while estrogen gel was used but rose again once it stopped, and another trial of an estradiol patch found no difference from placebo (see the estradiol patch section).
- The pill-free week of a standard 21/7 oral contraceptive produces the same estrogen cliff and triggers "withdrawal" migraine in many users.
- Pregnancy, when estrogen rises steadily and stays high, generally improves migraine dramatically by the second trimester.
- Surgical menopause with abrupt estrogen loss often worsens migraine before it eventually settles.
The estrogen-withdrawal model does not explain every menstrual attack — prostaglandin surges from the endometrium, serotonin fluctuations, and CGRP sensitivity all play roles — but it explains enough to drive real treatment decisions.
Pure Menstrual Migraine vs. Menstrually-Related Migraine
The International Classification of Headache Disorders, third edition (ICHD-3), splits menstrual migraine into two categories that sound similar but matter clinically.
Pure menstrual migraine without aura (PMM) — ICHD-3 code A1.1.1. Attacks occur only during the perimenstrual window (days -2 to +3) in at least two of every three cycles, and at no other time of the month. Roughly 10–14% of women with migraine meet this definition. PMM is the cleanest target: if your brain only fires during that five-day window, you only need prevention for five days a month.
Menstrually-related migraine without aura (MRM) — ICHD-3 code A1.1.2. Attacks occur reliably during the perimenstrual window and at other times throughout the cycle. This is far more common — about 35–50% of female migraine patients. Mini-prevention can still help, but you usually need a background preventive too.
The distinction matters because PMM often responds beautifully to short-term ("mini") prevention alone, while MRM usually needs a layered approach: daily preventive plus targeted perimenstrual coverage.
Both definitions specifically exclude aura. Menstrual attacks with aura exist but are less common and sit in a different risk category because of the stroke and contraceptive implications discussed below.
The Headache Diary — Three Cycles to a Diagnosis
Before your doctor can prescribe mini-prevention, you both need to know whether your migraines are actually menstrually linked. Memory is unreliable. A three-month headache diary is.
Track, every day:
- Cycle day (day 1 = first day of full bleeding, not spotting).
- Headache: yes / no, and if yes the severity (0–10) and duration.
- Aura: yes / no, and type (visual, sensory, speech).
- Medications taken and whether they worked.
- Other triggers — sleep loss, skipped meals, red wine, weather fronts, stress.
Free options include headache-diary apps or a plain paper calendar. After three complete cycles, laying the headache days over the cycle days shows the pattern: a clear cluster in the day -2 to +3 window is the menstrual pattern described above. A written record of this kind also gives a clinician the pattern at a glance.
Short-Term ("Mini") Prevention Around Your Period
Mini-prevention means starting a medication two days before your expected period and continuing for five to seven days through the high-risk window. You take nothing the rest of the month. In Silberstein's 2004 trial of 546 women, menstrual migraine occurred during the 6-day window in 67% of cycles on placebo, 52% on frovatriptan 2.5 mg once daily and 41% on 2.5 mg twice daily; both doses also shortened and softened the attacks that did occur, and side effects were similar to placebo. The approach keeps cumulative drug exposure low.
The evidence-based regimens:
- Frovatriptan 2.5 mg twice daily for 6 days, starting day -2. This is the best-studied option — Silberstein's 2004 trial established the protocol and it remains first-line. Frovatriptan's 26-hour half-life (the longest of any triptan) is what makes it suitable for scheduled dosing.
- Naratriptan 1 mg twice daily for 5 days, starting day -2. Similar concept, shorter half-life, slightly less robust evidence but often cheaper and available as generic.
- Naproxen 550 mg twice daily for 6–7 days, starting day -2. Non-hormonal, inexpensive, and additionally useful if you also have menstrual cramps or heavy bleeding. It is sometimes paired with a proton pump inhibitor in people with a history of reflux or gastritis.
- Zolmitriptan 2.5 mg two or three times daily for 5 days is an alternative if frovatriptan is unavailable or not covered.
Mini-prevention works only if your cycles are reasonably predictable (within two or three days). If your cycles are irregular, you will miss the window half the time. In that case, cycle suppression (see below) is usually a better approach.
A practical tactic: keep a rescue acute medication (a second triptan, a gepant like ubrogepant or rimegepant, or a ditan like lasmiditan) on hand for breakthrough attacks that punch through mini-prevention. See the triptans and gepants article for acute-treatment choices.
A 2024 meta-analysis of 26 randomized trials in menstrual migraine (Khoo and colleagues) found that triptans, with or without other painkillers, beat placebo for both treating and preventing menstrual attacks. Sumatriptan and lasmiditan gave the best pain relief at 2 hours and 24 hours. For prevention, frovatriptan was the most effective of the triptans at stopping headaches from coming back, while the CGRP antibodies erenumab and galcanezumab cut headache days per month more than the triptans did.
Continuous-Dose Contraceptives — Suppressing the Cycle
If the estrogen-withdrawal hypothesis is correct, the cleanest solution is to stop the withdrawal from happening. Continuous-dose combined oral contraceptives (COCs) do exactly that: you skip the placebo/pill-free week and take active pills every day, eliminating the monthly estrogen drop.
Options that work:
- Continuous monophasic COC — any standard low-dose (20–30 mcg ethinyl estradiol) monophasic pill, taken 365 days a year, skipping the placebo week. Extended-cycle and continuous levonorgestrel/ethinyl estradiol packs are sold pre-packaged for this pattern, but any monophasic generic can be used continuously at a fraction of the cost.
- Extended-cycle COC — 84 active days then a 7-day break, or 84 active plus 7 days of low-dose estrogen. Fewer withdrawal windows per year (four instead of thirteen) but does not eliminate them.
- Vaginal ring (etonogestrel/ethinyl estradiol) used continuously, changing the ring every 3–4 weeks without a ring-free week.
Calhoun's 2017 review of hormonal contraception and migraine with aura focused on estrogen dose: it reported that studies consistently show no increase in stroke risk with today's very low-dose combined pills containing 20–25 mcg ethinyl estradiol, and that continuous ultra-low-dose formulations (10–15 mcg) may even reduce how often aura occurs. The review also notes that current guidelines still restrict these pills in migraine with aura. Continuous dosing prevents the monthly estrogen cliff; cyclic dosing recreates it every month.
Critical caveat: under current guidelines, combined (estrogen-containing) contraceptives are used only in women with migraine without aura. The next section explains the aura restriction.
The Aura Problem and Stroke Risk
Migraine with aura roughly doubles the baseline ischemic stroke risk in young women. Combined oral contraceptives, by raising estrogen-mediated clotting factors, add their own modest stroke risk. When you stack them, the combined risk rises enough that the World Health Organization, the American College of Obstetricians and Gynecologists, and the U.S. Centers for Disease Control and Prevention (CDC) all classify combined hormonal contraceptives as contraindicated (category 4) in women with migraine with aura. Smoking on top of this is the tripwire that turns a small absolute risk into a meaningful one.
What this means in practice:
- If you have any aura — visual zigzags, scotomas, sensory tingling, speech disturbance — combined pills, combined patches, and combined vaginal rings are off the table for migraine prevention.
- A single lifetime aura episode counts.
- Progestin-only methods and transdermal-estradiol add-back (different from a contraceptive patch) are the remaining hormonal options.
See the aura article for how to identify whether what you experience meets the diagnostic definition.
Progestin-Only Options for Aura Patients
Progestin-only contraception carries no measurable added stroke risk and is safe in migraine with aura. Several forms exist, and any of them — when they successfully suppress ovulation and therefore suppress the cyclic estrogen drop — can reduce menstrual migraine frequency.
- Desogestrel 75 mcg daily — a "newer-generation" progestin-only pill that reliably suppresses ovulation in most users. Often the first choice for aura patients who want a daily oral option. A different progestin-only pill contains drospirenone 4 mg.
- Levonorgestrel intrauterine system (a hormonal intrauterine device, IUD) — five to eight years of protection. Does not suppress ovulation in everyone but drastically reduces menstrual bleeding and prostaglandin load, which helps many women.
- Depot medroxyprogesterone acetate — injection every 12 weeks. Reliably suppresses ovulation. Long-term use is linked to loss of bone density, and some users gain weight.
- Etonogestrel implant — three years, small rod in the upper arm. Suppresses ovulation in most cycles.
Progestin-only methods do not have the same clean dose-response relationship with migraine that combined pills do, so results vary from woman to woman. Some women get dramatic relief; a smaller fraction get worse (usually because of irregular spotting that amounts to continuous mini-withdrawal events). Three to four months is the usual period allowed before a method is judged.
Transdermal Estradiol — MacGregor's Add-Back Strategy
For women with regular cycles and clear PMM who either cannot take combined contraceptives (because of aura) or who simply want to preserve their cycle, MacGregor developed an elegant alternative: leave the natural cycle alone, but plug the estrogen cliff with a short course of transdermal estradiol around the period.
The classic regimen:
- Apply a 100 mcg estradiol patch two days before expected period onset (day -2).
- Leave it in place for seven days, replacing at the standard patch interval (twice-weekly patches require a change mid-course).
- Remove on day +5. Resume normal cycle.
Lower doses (50 or 75 mcg) have been trialed and appear less effective than 100 mcg, and even the 100 mcg dose has a mixed trial record (below). Gel formulations (1.5 mg estradiol gel daily during the window) are an alternative when patches irritate the skin or detach. This approach is not contraceptive — it does not prevent pregnancy — and it is not universally covered by U.S. insurance. It is the most physiologically targeted hormonal approach to PMM, but the trials below show it does not reliably work.
What the trials found. In MacGregor's own 2006 crossover trial (35 women analysed), estradiol gel applied from the tenth day after a home fertility monitor showed peak fertility until the second full day of bleeding cut migraine days by 22% while the gel was used, and those attacks were milder. But in the 5 days after the gel stopped, migraine rose by 40% compared with placebo: the estrogen drop was delayed, not avoided, and the benefit was offset. A 2011 Swedish crossover trial of a 100 mcg-per-day estradiol patch for two weeks around the period (27 women) found no difference from placebo in the number or severity of attacks, although both estradiol and placebo did better than before treatment. How to avoid the rebound (for example by using estradiol for longer) has not been worked out.
Perimenopause — When It Gets Worse Before It Gets Better
Many women assume menopause means migraine relief. Eventually, yes. But the four to ten years of perimenopause that precede the final period are often the worst migraine years of a woman's life, and nobody warns patients about it.
The physiology: during perimenopause, ovarian follicles become erratic. Estrogen does not gradually decline — it swings wildly, sometimes higher than normal, sometimes crashing. Every crash is an estrogen-withdrawal event, and crashes can happen multiple times per cycle rather than once. Progesterone production also falls unpredictably, which amplifies the swings. Cycles shorten, lengthen, skip entirely, then return with a vengeance.
Patterns patients commonly report:
- Migraines that used to be monthly become weekly or near-daily.
- Previously reliable mini-prevention stops working because cycles are no longer predictable.
- Hot flashes, night sweats, and sleep disruption independently lower the migraine threshold.
- A sudden increase in migraine frequency in a woman in her forties is often the first clue perimenopause has started, months or years before any cycle irregularity.
Average age at menopause in the U.S. is 51. If your migraines are getting worse in your early-to-mid forties, perimenopause is almost certainly part of the picture. The workup is clinical — follicle-stimulating hormone (FSH) levels are unreliable during perimenopause because they fluctuate as much as estrogen does — but a pattern of worsening migraine plus hot flashes, sleep disruption, or cycle change is enough to act on.
Hormone Replacement Therapy Decisions — Transdermal, Body-Identical, Cyclic vs. Continuous
Hormone replacement therapy (HRT, now often called MHT — menopausal hormone therapy) can stabilize perimenopausal and postmenopausal migraine, but the form of hormone replacement therapy matters enormously for headache outcomes.
- Transdermal estradiol is strongly preferred over oral estrogen. Oral estrogen passes through the liver, produces erratic blood levels, and in many women triggers more migraine, not less. Transdermal patches or gels deliver steady estradiol directly into the bloodstream and avoid the first-pass effect.
- Body-identical (micronized) progesterone — taken as capsules — is generally better tolerated than synthetic progestins (medroxyprogesterone, norethindrone) for migraine patients. It also aids sleep, a secondary migraine benefit.
- Continuous combined hormone replacement therapy (daily estrogen + daily progesterone) is usually preferable to cyclic hormone replacement therapy for migraine. Cyclic regimens deliberately recreate a monthly withdrawal bleed, which can re-trigger menstrual migraine in women who had finally escaped it.
- Dose matters. Prescribers commonly start low (25–37.5 mcg patch) and raise the dose only as needed. Higher doses reduce flushing and sleep disruption but can reignite migraine.
- Aura caveat remains relevant. Transdermal estradiol in physiologic (menopausal) doses does not carry the stroke risk of a combined oral contraceptive — the dose is roughly a quarter to a sixth — and is generally considered acceptable in women with migraine with aura, though guidance varies. The category 4 restriction described above applies to combined hormonal contraceptives, not to menopausal-dose estradiol.
Surgical Menopause and Oophorectomy
Removal of both ovaries — bilateral oophorectomy — is a hormonal catastrophe for most migraine patients. Overnight, estrogen crashes from premenopausal levels to zero, with no taper. Migraine typically worsens dramatically in the weeks and months after surgery, and may not resettle for a year or more.
If you have migraine and are considering oophorectomy (for endometriosis, ovarian masses, cancer risk, or another indication), bring the topic up explicitly with your surgeon and headache specialist before the operation. Starting transdermal estradiol on the day of surgery and continuing it at least until the natural age of menopause (~51) blunts the crash and is usually appropriate even in women who would otherwise be ambivalent about hormone replacement therapy. Hysterectomy without oophorectomy does not cause this problem because the ovaries continue to function.
Pregnancy, Postpartum, and Breastfeeding
Pregnancy is, for most migraine patients, a reprieve. The data:
- First trimester: mixed. Roughly a third get better, a third unchanged, a third worse. Nausea and sleep disruption from pregnancy itself can confuse the picture.
- Second trimester: 50–80% of women experience dramatic improvement or complete remission. Estrogen is high, steady, and rising. This is the honeymoon.
- Third trimester: improvement usually continues, though late-pregnancy sleep disruption, reflux, and back pain can trigger attacks unrelated to hormones.
- Postpartum: estrogen plummets within 24–72 hours of delivery. Roughly 30–40% of women have a migraine within the first week postpartum, and the first four to six weeks are a high-risk window. Sleep deprivation on top of the estrogen crash is a double hit.
- Breastfeeding generally extends the reprieve because lactation suppresses ovulation and keeps estrogen stable at a lower but flat level. Migraines often return when breastfeeding ends or menses resumes.
Acute medications during pregnancy: acetaminophen is first-line. Metoclopramide (antiemetic with migraine-aborting properties) is generally considered safe. In 2020 the U.S. Food and Drug Administration (FDA) warned that nonsteroidal anti-inflammatory drugs (NSAIDs) used at about 20 weeks of pregnancy or later may cause rare but serious kidney problems in the unborn baby, leading to low amniotic fluid; the ductus-arteriosus concern is added in the third trimester. Triptans — particularly sumatriptan, which has the largest registry data — are not formally approved but are widely used when benefits outweigh risks; large observational cohorts have not shown clear harm. Ergotamine and dihydroergotamine (DHE) are contraindicated. Gepants and CGRP monoclonal antibodies lack pregnancy data and are generally stopped before conception.
Breastfeeding-safe acute options: acetaminophen, ibuprofen (preferred nonsteroidal anti-inflammatory drug (NSAID) while nursing because of its short half-life and low milk transfer), sumatriptan (minimal transfer, considered compatible), eletriptan (even lower transfer). Aspirin is not on the nursing-compatible list because of Reye-syndrome concerns in the infant. The LactMed database (free, U.S. National Institutes of Health, NIH) is the authoritative source when a specific drug comes up.
Endometriosis, Adenomyosis, Polycystic Ovary Syndrome, Thyroid, and PMDD
Menstrual migraine rarely travels alone. The conditions that cluster with it share hormonal machinery, and treating one often helps the others.
- Endometriosis — women with endometriosis have roughly twice the rate of migraine. The same prostaglandin surge that drives endometriosis pain contributes to menstrual headache. Cycle-suppressing hormonal therapy can address both. See the endometriosis overview and the hormonal therapy options deep-dive.
- Adenomyosis — endometrial tissue embedded in the uterine muscle. Causes heavy, painful periods with a high prostaglandin load. Often goes undiagnosed for years. Magnetic resonance imaging (MRI) or transvaginal ultrasound makes the diagnosis. Treatment overlaps with endometriosis and almost always helps menstrual migraine.
- Polycystic ovary syndrome (PCOS) — the irregular cycles of polycystic ovary syndrome make mini-prevention nearly impossible because you cannot predict the window. Restoring cycle regularity with a combined pill (in the absence of aura) or cycle suppression often unlocks other migraine strategies.
- Thyroid disease — hypothyroidism, particularly autoimmune (Hashimoto's), is overrepresented in chronic migraine cohorts. Thyroid-stimulating hormone (TSH), free T4, and thyroid antibodies are a reasonable screen in anyone with a new escalation of migraine frequency. See the Hashimoto's overview and the pregnancy and Hashimoto's deep-dive, which is also relevant to anyone navigating postpartum migraine.
- Premenstrual dysphoric disorder (PMDD) — severe mood, anxiety, and irritability in the luteal phase. The neurobiology overlaps with menstrual migraine (altered serotonin and gamma-aminobutyric acid (GABA) sensitivity to progesterone metabolites). Selective serotonin reuptake inhibitors (SSRIs) used luteal-phase-only (days 14–28) treat PMDD and may reduce menstrual migraine severity as a bonus.
The Steps Described for Menstrual Migraine, in Order
The list below gathers, in order, the steps the research and guidelines on this page describe. Which steps fit depends on cycle regularity, aura and life stage.
- Three-cycle headache diary. It confirms the pattern and whether aura is present.
- Basic labs commonly checked: complete blood count (CBC), ferritin (heavy periods can cause iron deficiency, which lowers the migraine threshold), thyroid-stimulating hormone + free T4, vitamin D, and sometimes thyroid antibodies.
- Magnesium glycinate 400–600 mg daily and riboflavin 400 mg daily are the amounts described for these supplements — both have randomized-trial evidence in general migraine prevention and a low side-effect profile. See the supplements article.
- Regular cycles and PMM: mini-prevention with frovatriptan 2.5 mg twice daily for 6 days starting day -2 (the regimen tested by Silberstein), or naproxen 550 mg twice daily as a non-hormonal alternative.
- Irregular cycles, or mini-prevention not working, and no aura: continuous-dose combined contraception.
- Aura present: progestin-only options (desogestrel, levonorgestrel intrauterine system) or MacGregor's transdermal estradiol add-back around menses, whose trial results are mixed.
- Perimenopause: transdermal hormone replacement therapy (body-identical progesterone, continuous rather than cyclic), with a CGRP preventive as an option for background control.
- Attacks still frequent despite the above: a daily background preventive — a CGRP monoclonal antibody, atogepant, topiramate, or a beta-blocker. See the CGRP and preventives article.
- Medication overuse. Under the International Classification of Headache Disorders (ICHD-3), regular use of triptans or of combination painkillers on 10 or more days a month for more than 3 months can cause medication-overuse headache — headache on 15 or more days a month that usually, but not always, settles once the overuse stops. See the medication-overuse article.
Menstrual migraine is not a character of your cycle you are stuck with. It is a specific, well-characterized neurobiological event with specific, well-characterized interventions. Most women who work through this list in order find a combination that cuts their attack frequency at least in half, often more.
Key Research Papers
- MacGregor EA, Frith A, Ellis J, Aspinall L, Hackshaw A. Incidence of migraine relative to menstrual cycle phases of rising and falling estrogen. Neurology. 2006;67(12):2154-2158. — doi:10.1212/01.wnl.0000233888.18228.19
- Silberstein SD, Elkind AH, Schreiber C, Keywood C. A randomized trial of frovatriptan for the intermittent prevention of menstrual migraine. Neurology. 2004;63(2):261-269. — doi:10.1212/01.wnl.0000134620.30129.d6
- Calhoun AH. Hormonal Contraceptives and Migraine With Aura-Is There Still a Risk? Headache. 2017;57(2):184-193. — PMID: 27774589
- Sacco S, Merki-Feld GS, Ægidius KL, et al. Hormonal contraceptives and risk of ischemic stroke in women with migraine: a consensus statement from the European Headache Federation (EHF) and the European Society of Contraception and Reproductive Health (ESC). J Headache Pain. 2017;18(1):108. — PMID: 29086160
- MacGregor EA, Frith A, Ellis J, Aspinall L, Hackshaw A. Prevention of menstrual attacks of migraine: a double-blind placebo-controlled crossover study. Neurology. 2006;67(12):2159-2163. — PMID: 17190936
- Almén-Christensson A, Hammar M, Lindh-Åstrand L, Landtblom AM, Brynhildsen J. Prevention of menstrual migraine with perimenstrual transdermal 17-β-estradiol: a randomized, placebo-controlled, double-blind crossover study. Fertil Steril. 2011;96(2):498-500.e1. — PMID: 21704313
- Khoo CC, Liu CC, Lu M, Huang YC, Weng HY. Acute and preventive treatment of menstrual migraine: a meta-analysis. J Headache Pain. 2024;25(1):143. — PMID: 39227797
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on menstrual migraine and the hormonal interventions discussed above:
- PubMed: Menstrual migraine and estrogen withdrawal
- PubMed: Frovatriptan short-term prevention
- PubMed: Naproxen for menstrual migraine
- PubMed: Continuous-dose oral contraceptives and migraine
- PubMed: Migraine with aura, stroke risk, and oral contraceptives
- PubMed: Transdermal estradiol for menstrual migraine
- PubMed: Perimenopause and migraine
- PubMed: Hormone replacement therapy and migraine
- PubMed: Pregnancy, trimester effects, and migraine
- PubMed: Postpartum and breastfeeding-safe migraine treatment
- PubMed: Endometriosis and migraine comorbidity
- PubMed: PMDD, serotonin, and menstrual migraine
Connections
- Pain & Allergy
- Endometriosis
- Endometriosis — Hormonal Therapy Options
- Chronic Migraine and Medication Overuse
- Magnesium, Riboflavin, and Supplements
- CGRP Inhibitors and Preventives
- Triptans and Gepants — Acute Treatment
- Aura and Visual Disturbances
- Hashimoto's Thyroiditis
- Pregnancy and Hashimoto's
- Migraine Overview
- Perimenopause
- Polycystic Ovary Syndrome
- Diet Triggers and Elimination Protocol
- Vestibular Migraine
- Menopause and Hormone Replacement Therapy
- Migraine in Pregnancy and Breastfeeding
- Stroke
- Perimenopause Symptom Tracker and Hormonal Testing
- Reproductive Medicine