⚠ Evidence warning: Clinical trials or other evidence do not support the attack-reduction figures given for regular meals and elimination diets, the Buchholz protocol's reported clinic response rate, and practitioners' low-histamine and ketogenic routines. This page keeps it as a report of what people, websites or other media say.
Diet Triggers and the Migraine Elimination Protocol
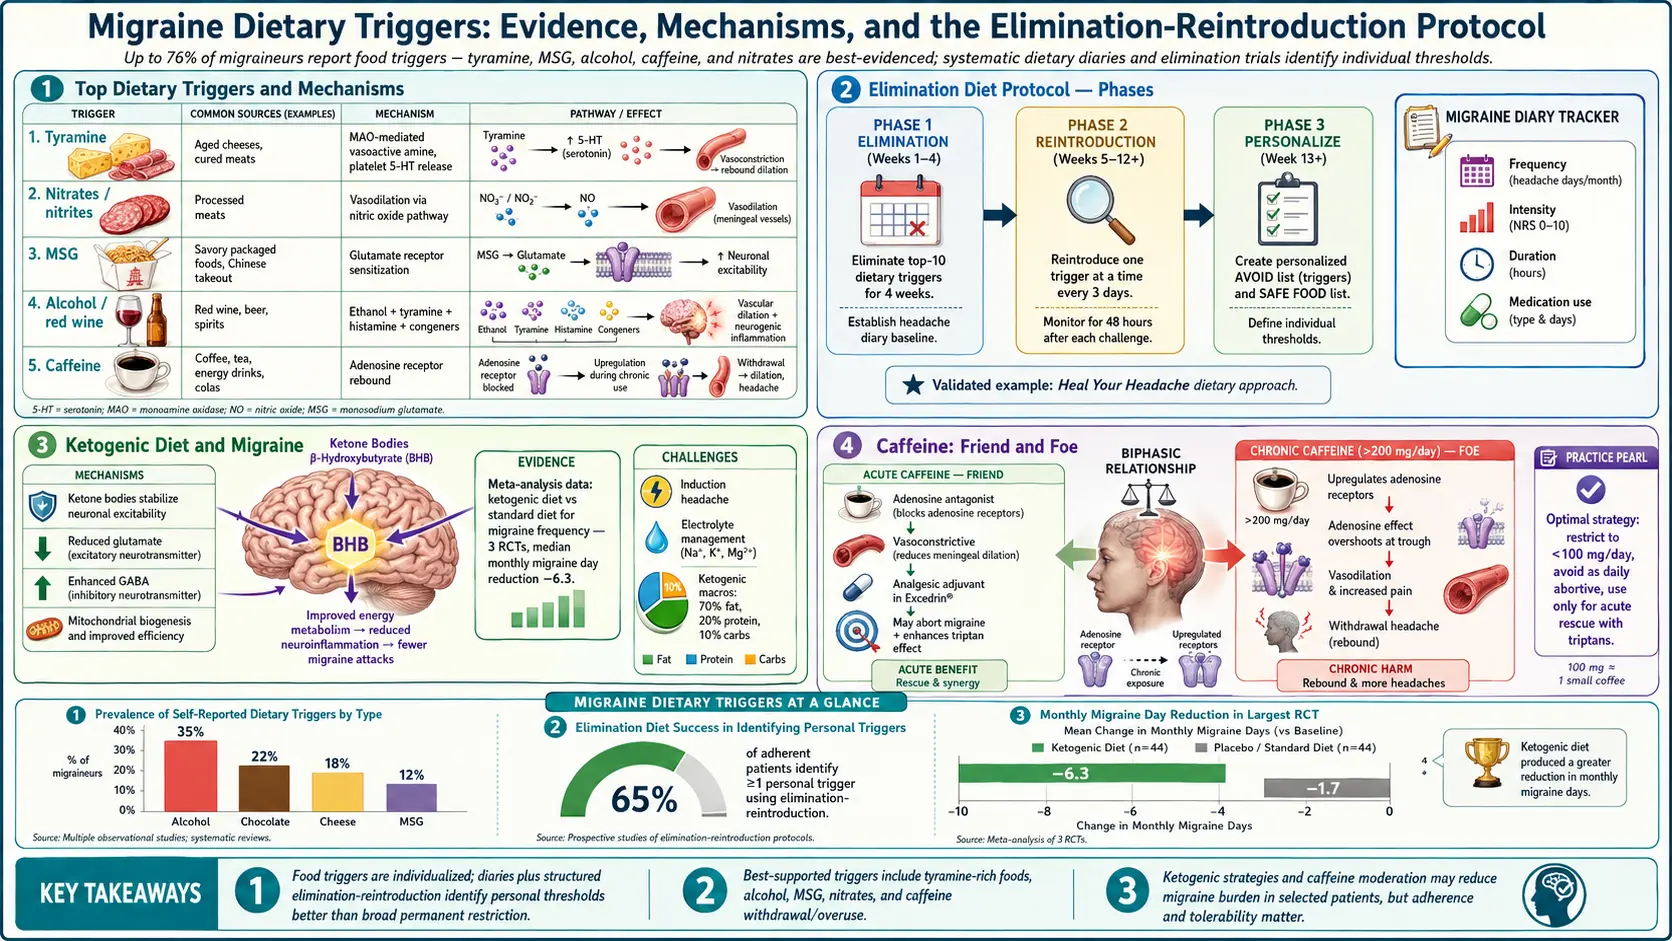
Table of Contents
- The Trigger Problem: Why Most Lists Are Wrong
- Prodromal Cravings vs. Real Triggers
- The Honest Evidence List
- Skipped Meals and Dehydration: The Real #1
- Alcohol — The One Nearly Everyone Agrees On
- Aged Cheeses, Cured Meats, and Tyramine
- MSG, Aspartame, and the Debated Additives
- Caffeine: Both Sides of the Blade
- Histamine, Mast Cell Activation Syndrome, and the Overlap
- The Buchholz "Heal Your Headache" Protocol
- Ketogenic and Low-Carb Therapy
- How to Run a Proper N-of-1 Elimination
- Food Sensitivity Tests — What Works and What Doesn't
- Migraine Diary Best Practices
- Sample Meal Plan for the Strict Phase
- Setting Realistic Expectations
- Key Research Papers
- Connections
- Featured Videos
The Trigger Problem: Why Most Lists Are Wrong
If you have searched "migraine food triggers," you have met The List. Every headache clinic pamphlet, every magazine article, every supplement-selling blog prints more or less the same lineup: chocolate, cheese, red wine, citrus, nuts, bananas, onions, processed meat, MSG, aspartame, caffeine. The lists are usually identical because they all copy from one another, and they all trace back to a small number of observational studies from the 1970s and 1980s in which patients reported a food had preceded an attack.
The problem is that self-reported triggers are a notoriously unreliable source of evidence. Attacks are common, cravings are common, and when the two coincide the brain builds a story. When researchers actually provoke migraine patients with suspected food triggers in blinded studies — giving capsules of chocolate extract, tyramine, or aspartame that the patient cannot distinguish from placebo — the trigger reproduces an attack only a minority of the time, and often no more often than the placebo capsule does.
This does not mean diet is irrelevant. It means the popular trigger list is wildly over-inclusive, and most patients who try to avoid twenty foods at once end up with anxiety, disordered eating, and no reduction in attacks. The honest literature supports a much shorter list, plus a careful self-experiment to find your own pattern.
Prodromal Cravings vs. Real Triggers
This is the single most important concept in food-trigger research, and the one most patients have never heard.
A migraine attack does not start with pain. It starts with the prodrome — a phase of neurological changes that begins six to forty-eight hours before the headache itself. Prodromal symptoms include yawning, neck stiffness, mood changes, increased urination, fatigue, irritability, heightened sensitivity to light and sound, and, crucially, food cravings. The hypothalamus, which is already misbehaving during the prodrome, drives cravings for sweet, salty, or fatty foods.
So the classic story — "I ate chocolate and three hours later my migraine started" — is almost always backward. The migraine had already started (prodromally) and the brain, in its prodromal state, reached for the chocolate. The chocolate is an early symptom, not the cause. Peter Goadsby and colleagues showed with electronic diaries (97 patients) that premonitory symptoms reliably precede attacks: patients correctly predicted their migraine headaches from 72% of diary entries that recorded such symptoms, most often tiredness, poor concentration and a stiff neck.
The same is often true of bananas, citrus, cheese, and sweets. The useful question before a food goes on a personal trigger list is whether the person was already feeling "off" before eating it. If so, the food is probably a flag, not a cause.
The Honest Evidence List
Here is what the research actually supports, ranked by the strength and consistency of evidence. Effect sizes are for responders — not everyone reacts to every item.
- Skipped meals / prolonged fasting — the most reproducible trigger across decades of studies. Attacks can follow a missed breakfast or a delayed lunch by two to six hours.
- Dehydration — consistently listed by patients and supported by provocation studies.
- Alcohol, especially red wine and dark spirits — roughly 30–60% of migraine patients identify alcohol as a trigger, and blinded studies support it for wine.
- Caffeine withdrawal — a skipped or delayed usual dose can trigger an attack within 18–24 hours.
- Excess caffeine — above roughly 200–400 mg/day, it can both trigger attacks and drive medication-overuse headache.
- Aged cheeses and cured meats (tyramine, nitrates) — plausible mechanism, modest effect size, probably real in a subset.
- MSG — MSG dissolved in liquid triggered headache in several provocation studies, which a 2016 review ranked, with caffeine withdrawal, as the strongest evidence for any dietary trigger. Real in some individuals.
- Aspartame — one of the more controversial. Two provocation studies were positive and two negative.
- Histamine-rich foods — matters mostly for people who also have mast cell activation syndrome (MCAS) or histamine intolerance (see below).
- Chocolate, citrus, bananas, nuts, onions — these sit on every popular list, but blinded provocation evidence is weak-to-absent. Most are probably prodromal cravings being misread as triggers.
Skipped Meals and Dehydration: The Real #1
The brain of a migraineur runs hot and hungry. Blood glucose dipping for a few hours, or water intake running low across a morning, is enough to tip a susceptible brain toward an attack. This is consistent across every age, every country, every version of the diagnostic criteria.
The routine usually described for this:
- A meal within one hour of waking, with protein (eggs, yogurt, leftovers) — not just carbs, which cause a faster dip.
- No more than four to five waking hours without food. A protein bar, nuts, or jerky covers days when a meal slips.
- Roughly 2 to 2.5 liters (8–10 cups) of water daily, more in hot weather or during exercise. Electrolyte drinks help on heavy-sweat days.
- Long "intermittent fasting" protocols are a known risk: fasting is a trigger, and 16-hour fasts can provoke attacks in migraine brains. Whether they do for one person shows up only in a diary.
As a clinical estimate rather than a study result, people who get only this right often cut attack frequency by 20–30% without changing another trigger.
Alcohol — The One Nearly Everyone Agrees On
Alcohol is the most consistently reported dietary trigger in migraine, and unlike chocolate or cheese, it survives blinded provocation testing. The likely mechanisms are a mixture:
- Ethanol itself is vasoactive and a direct inducer of headache in susceptible people.
- Congeners — the chemical byproducts of fermentation and aging — are higher in darker drinks (red wine, whisky, brandy) and lower in clear spirits (vodka, gin).
- Sulfites in red wine are often blamed. The mechanism is plausible but not cleanly proven.
- Tannins and histamine in red wine may add to the effect.
- Dehydration and sleep disruption from any drinking contribute indirectly.
In practice: red wine is the single most common alcoholic offender. White wine, champagne, and dark spirits are intermediate. Clear spirits (vodka, gin, tequila) paired with plenty of water cause the fewest attacks in most patients. For people in whom any amount reliably triggers attacks, not drinking is the only way to remove this trigger — alcohol is dispensable.
Aged Cheeses, Cured Meats, and Tyramine
Tyramine is a vasoactive amine produced when bacteria or molds break down the amino acid tyrosine. It accumulates in aged, cured, or fermented foods: cheddar, Stilton, Parmesan, blue cheese, salami, pepperoni, prosciutto, aged pâtés, soy sauce, miso, sauerkraut, and some broad beans. Nitrates and nitrites in cured meats (hot dogs, bacon, deli ham) are a separate concern and act through nitric oxide pathways, a well-known headache trigger.
A low-tyramine diet favors fresh proteins (fresh meat, fresh fish, eggs), fresh cheese (cottage cheese, ricotta, fresh mozzarella), and foods eaten within 24–48 hours of cooking. The plan leaves out leftovers older than two days, especially protein leftovers, because tyramine builds in the fridge.
Effect size is modest. Clinicians report improvement in a subset of patients on a low-tyramine plan, not a uniform benefit. The plan is commonly described as a six-week trial focused on the biggest-hit items (aged cheese, cured meat, old leftovers) rather than every trace source.
MSG, Aspartame, and the Debated Additives
Monosodium glutamate (MSG) is umami-tasting free glutamate used in Chinese and Southeast Asian cooking, many soups, bouillons, processed snacks, and fast food. Some patients react reliably; many do not. A 2016 review found that MSG dissolved in liquid triggered headache in several provocation studies; its strongest evidence is for MSG given that way. The self-test commonly described is two to four weeks of strict avoidance, then a rechallenge with a clear dose (for example, a heavily seasoned broth eaten on an empty stomach). "Glutamate-free" is impossible — free glutamate occurs naturally in parmesan, tomatoes, mushrooms, and aged proteins — but added MSG is avoidable.
Aspartame is the artificial sweetener in many diet sodas and sugar-free products. A 2016 review counted two positive and two negative provocation studies of aspartame. For people who drink diet soda daily and have frequent migraines, the self-test commonly described is a one-month break; water, unsweetened sparkling water, or stevia-sweetened drinks are the usual substitutes.
Sucralose and stevia have not been implicated consistently, though individual reactions are always possible.
Caffeine: Both Sides of the Blade
Caffeine is the most contradictory migraine substance. It is a component of acute migraine treatments (some over-the-counter migraine tablets contain 65 mg of caffeine each). Taken acutely, it can abort a developing attack by constricting cerebral vessels and enhancing analgesic absorption. Taken chronically at high doses, it drives medication-overuse headache and makes preventives work less well. And a missed or delayed daily dose can provoke a withdrawal headache within 18–24 hours that is indistinguishable from a migraine attack.
The limits commonly described:
- A daily cap of about 200 mg — roughly one strong mug of coffee or two cups of brewed tea.
- Steady timing. The same dose at the same time every day, including weekends, sidesteps the withdrawal headache of a late or missed dose.
- Quitting gradually. A taper of about 25% per week over a month is the usual way to sidestep withdrawal attacks.
- Caffeine-containing painkillers (over-the-counter combination tablets) used more than twice a week tip into medication overuse. The chronic migraine and medication-overuse article has details.
Histamine, Mast Cell Activation Syndrome, and the Overlap
Histamine is the chemical your mast cells release during allergic reactions — but it is also present in many foods, and a subset of migraine patients appear to be sensitive to dietary histamine. This overlaps heavily with Mast Cell Activation Syndrome (MCAS) and histamine intolerance. If your migraines come with flushing, itching, hives, gastrointestinal (GI) cramping, rapid heart rate, or reactions to heat, exercise, or alcohol on top of the headache, histamine is a possible factor.
High-histamine foods include aged cheese, cured meat, wine and beer, fermented foods (sauerkraut, kimchi, kombucha), tomatoes, spinach, eggplant, avocado, and leftover protein (especially fish). Some foods are not themselves high in histamine but trigger mast cells to release it — strawberries, citrus, chocolate, shellfish.
The usual test is a structured low-histamine diet for four to eight weeks. A meaningful drop in migraine frequency points to histamine as part of the picture; practitioners then describe staying low-histamine, or taking a daily H1 antihistamine such as cetirizine or loratadine, as a long-term approach. No change suggests histamine is not the issue, and the restriction then serves no purpose.
The Buchholz "Heal Your Headache" Protocol
Neurologist David Buchholz's Heal Your Headache (2002) popularized a 6-week strict elimination diet that has become a standard first pass for motivated migraine patients. The protocol avoids, from day one:
- Caffeine (all sources, fully out — not tapered)
- Chocolate
- MSG and hydrolyzed vegetable protein
- Processed meats and anything nitrate/nitrite-cured
- Aged cheese (anything except fresh mozzarella, ricotta, cottage cheese, cream cheese)
- Nuts and peanut butter
- Certain fruits (citrus, bananas, raspberries, red plums, avocados, dried fruits with sulfites)
- Onions (small amounts of cooked onion sometimes tolerated)
- Aspartame
- Alcohol (especially red wine)
- Yogurt and sour cream (cultured dairy)
After six weeks of strict avoidance, foods are reintroduced one at a time, every three to four days, with a diary. Buchholz's reported response rate in his clinic was high, though the protocol has never been subjected to a rigorous randomized trial. It is cheap, safe, and over-inclusive — meaning many of the eliminated foods probably are not your personal triggers, but finding out takes the reintroduction phase. It works as a wide net that the reintroduction phase then narrows.
Ketogenic and Low-Carb Therapy
A growing body of small trials suggests that ketogenic diets — very low carbohydrate (under 50 g/day), moderate protein, high fat, enough to produce blood ketones — can reduce migraine frequency in a substantial minority of patients. The proposed mechanism is improved brain energy metabolism via ketone bodies, plus anti-inflammatory effects. Di Lorenzo and colleagues (2019) tested a different version in 35 overweight or obese people with episodic migraine: a very-low-calorie ketogenic diet against a very-low-calorie non-ketogenic diet, one month each in random order. On the ketogenic month they had 3.73 fewer migraine days, and 74% (26 of 35) cut their migraine days by at least half, against 9% (3 of 35) on the non-ketogenic month. A 2023 systematic review pooled 10 studies of ketogenic approaches in migraine — very-low-calorie ketogenic, modified Atkins and classic ketogenic diets, and a beta-hydroxybutyrate supplement. All showed an overall reduction in migraine, but the studies came mostly from Italy, differed widely, and measured ketosis inconsistently, so the review called for better randomized trials.
The practical caveats are real. Ketogenic diets are restrictive, socially difficult, and often cause a rocky "keto flu" first week that can itself include headaches. They clash with the regular-meals pattern unless meals are planned carefully. And they are hard to sustain for years. Most migraine clinicians who use keto therapeutically run it for three to six months as a trial, judge the response, then decide whether to continue, taper to a moderate low-carb pattern, or abandon it.
Practitioners who use it describe enough calories, extra sodium and magnesium, and at least eight weeks before judging the result. They report that attacks often spike in week one and drop in weeks four through eight.
How to Run a Proper N-of-1 Elimination
An "N-of-1" trial means you are the only subject — you run a careful self-experiment to find your own triggers. Done right, it is the single most useful dietary tool a migraine patient owns. Done wrong, it becomes a six-month spiral of restriction with no conclusions.
The steps usually described:
- A long enough baseline. Six to eight weeks of strict avoidance. Shorter trials miss the effect because migraine frequency is highly variable week-to-week.
- A written list, not vibes. The Buchholz, low-histamine, or low-tyramine lists serve as starting templates, written on paper and kept in view on the fridge.
- Enough calories. Under-eating is itself a trigger. Most restricted phases fail because the patient is accidentally running a fast as well as an elimination.
- Hydration and sleep. If these are off, the elimination is contaminated.
- A daily diary (see below).
- One food reintroduced every three days, not one per day. The reason is that food-triggered attacks often take 24–48 hours to appear, so back-to-back reintroductions confuse the data.
- A real serving on each reintroduction day — a full wedge of aged cheese, a glass of red wine, not a nibble.
- 72 hours of logged outcomes before the next food is added.
- An attack after two of three reintroductions marks that food as a probable personal trigger.
- No attack in three tries means the food is not a trigger; keeping it out of the diet costs quality of life for no gain.
Food Sensitivity Tests — What Works and What Doesn't
Patients frequently arrive at neurology offices with printouts from commercial immunoglobulin G (IgG) food sensitivity panels. The bad news: immunoglobulin G food sensitivity tests are not validated. The American Academy of Allergy, Asthma & Immunology and most national allergy societies recommend against them. Immunoglobulin G antibodies to food simply reflect exposure — if you eat eggs, you have immunoglobulin G antibodies to eggs. They do not predict symptoms.
Small studies (notably Alpay 2010 in Cephalalgia) have suggested benefit from immunoglobulin G-guided elimination in migraine. In that blinded crossover trial of 30 people with migraine without aura, headache days fell from an average of 10.5 to 7.5, and migraine attacks from 9.0 to 6.2, during the six-week elimination diet compared with the six-week baseline. A 2016 review counted 2 of 3 randomized trials of immunoglobulin G-based elimination diets reporting fewer headaches. But the effect is most plausibly explained by the fact that any structured elimination helps a subset of people — the immunoglobulin G panel is just an elaborate random-list generator. The result is often a 20-food restriction built on a shaky scientific foundation.
Skin prick testing and immunoglobulin E (IgE) blood testing (allergist-ordered) are different — they measure true immunoglobulin E-mediated allergy. These are useful for suspected anaphylaxis, urticaria, or oral allergy syndrome. They are not the right tool for migraine triggers; immunoglobulin E allergy and migraine food triggers are different biological mechanisms.
Reactions to mammalian meat, delayed hives, unexplained gastrointestinal distress, or recurrent idiopathic anaphylaxis can point to Alpha-Gal Syndrome — a tick-induced immunoglobulin E allergy to mammalian meat that can present atypically.
Migraine Diary Best Practices
The diary is the data. Without it, memory keeps the attacks that fit the current theory and drops the ones that don't. A good diary has five fields per day:
- Date / day of cycle (for menstruating patients — essential for picking up menstrual patterns).
- Sleep (hours, quality).
- Meals and approximate times — with a note on any newly reintroduced food.
- Hydration (rough liters).
- Headache — yes/no, severity 0–10, duration, medication taken, prodromal symptoms noted.
Migraine diary apps or a plain paper notebook all work. What matters is consistency: daily entries, even on no-headache days. A monthly review looks for patterns across sleep, meals, cycle, weather, and foods. The pattern usually takes two to three months to emerge — migraine is statistical, not linear.
Sample Meal Plan for the Strict Phase
One week of Buchholz-style, low-histamine-aware, non-skipped-meal eating:
Breakfast (within one hour of waking): Scrambled eggs with fresh mozzarella and cooked spinach (spinach left out on a low-histamine plan). Rice toast or gluten-free toast. Water with lemon (lemon left out on a low-histamine plan). Decaf herbal tea if wanted.
Mid-morning snack: Fresh apple, rice cakes with sunflower seed butter (not peanut), or a hard-boiled egg.
Lunch: Fresh chicken breast (cooked and eaten the same day), brown rice or quinoa, roasted carrots and zucchini, olive oil and fresh herbs. A small side salad with olive oil (tomatoes left out on a low-histamine plan). Water.
Afternoon snack: Fresh pear, plain rice crackers, or a small bowl of cottage cheese with blueberries.
Dinner: Fresh-cooked salmon or turkey, sweet potato, steamed broccoli, butter or olive oil. Fresh fruit for dessert.
Evening: Chamomile or peppermint tea. No chocolate, no wine, no aged cheese, no cured meat, no leftovers from more than 24 hours ago.
Boring? Yes. That is the point — it is a diagnostic instrument, not a lifestyle. The plan runs for six weeks to collect data, then foods are reintroduced methodically.
Setting Realistic Expectations
Here is the forecast commonly given from clinical experience (these percentages are estimates; none of the papers cited below reports them):
- About 30–40% of patients who do a strict elimination carefully find at least one meaningful personal trigger.
- Typical attack-frequency reduction in these responders is 20–30% — useful, not miraculous.
- A smaller subset (perhaps 10–15%) are strong responders and cut attacks in half or more.
- Another 40–50% find no reliable food triggers and gain little from dietary restriction.
- Most patients benefit more from the "structure" side — regular meals, hydration, sleep, caffeine discipline — than from eliminating specific foods.
Diet is a real lever. It is not the lever. A proper preventive strategy usually stacks: dietary structure (meals + hydration) + targeted elimination of your personal triggers + sleep hygiene + supplements like magnesium and riboflavin (see the supplements article) + a conventional preventive drug or a calcitonin gene-related peptide (CGRP) monoclonal antibody if frequency is still high. Anyone selling dietary change alone as a cure for frequent migraine is overselling.
Key Research Papers
- Martin VT, Vij B. Diet and headache: Part 1. Headache. 2016;56(9):1543-1552. — doi:10.1111/head.12953
- Martin VT, Vij B. Diet and headache: Part 2. Headache. 2016;56(9):1553-1562. — doi:10.1111/head.12952
- Hindiyeh NA, Zhang N, Farrar M, et al. The role of diet and nutrition in migraine triggers and treatment: a systematic literature review. Headache. 2020;60(7):1300-1316. — doi:10.1111/head.13836
- Rockett FC, de Oliveira VR, Castro K, et al. Dietary aspects of migraine trigger factors. Nutr Rev. 2012;70(6):337-356. — doi:10.1111/j.1753-4887.2012.00468.x
- Di Lorenzo C, Pinto A, Ienca R, et al. A randomized double-blind, cross-over trial of very low-calorie diet in overweight migraine patients: A possible role for ketones? Nutrients. 2019;11(8):1742. — doi:10.3390/nu11081742
- Giffin NJ, Ruggiero L, Lipton RB, et al. Premonitory symptoms in migraine: an electronic diary study. Neurology. 2003;60(6):935-940. — doi:10.1212/01.wnl.0000052998.58526.a9
- Alpay K, Ertas M, Orhan EK, et al. Diet restriction in migraine, based on IgG against foods: a clinical double-blind, randomised, cross-over trial. Cephalalgia. 2010;30(7):829-837. — doi:10.1177/0333102410361404
- Neri LCL, Ferraris C, Catalano G, et al. Ketosis and migraine: a systematic review of the literature and meta-analysis. Front Nutr. 2023;10:1204700. — doi:10.3389/fnut.2023.1204700
PubMed Topic Searches
PubMed topic searches for further reading on migraine, diet, and the elimination approach:
- PubMed: Migraine food triggers
- PubMed: Migraine prodrome and food craving
- PubMed: Migraine elimination diet
- PubMed: Migraine, tyramine, and aged cheese
- PubMed: Migraine and histamine intolerance
- PubMed: Migraine and ketogenic diet
- PubMed: Migraine and caffeine withdrawal
- PubMed: Migraine and IgG food sensitivity testing
- PubMed: Migraine, fasting, and skipped meals
Connections
- Pain & Allergy
- Mast Cell Activation Syndrome
- Alpha-Gal Syndrome
- Magnesium, Riboflavin, and Supplements
- Low-Histamine Diet
- Migraine Overview
- Elimination Diet
- Chronic Migraine and Medication Overuse
- Menstrual Migraine and Hormonal Triggers
- CGRP Inhibitors and Preventives
- Triptans and Gepants — Acute Treatment
- Vestibular Migraine
- Aura and Visual Disturbances
- Small Intestinal Bacterial Overgrowth
- MSG
- Aspartame
- Magnesium
- Sulfites
- Fermented Foods
- Headache — the general symptom page: primary versus secondary types, causes, and red flags.