Human Immunodeficiency Virus (HIV)/Acquired Immunodeficiency Syndrome (AIDS) (Human Immunodeficiency Virus / Acquired Immunodeficiency Syndrome)
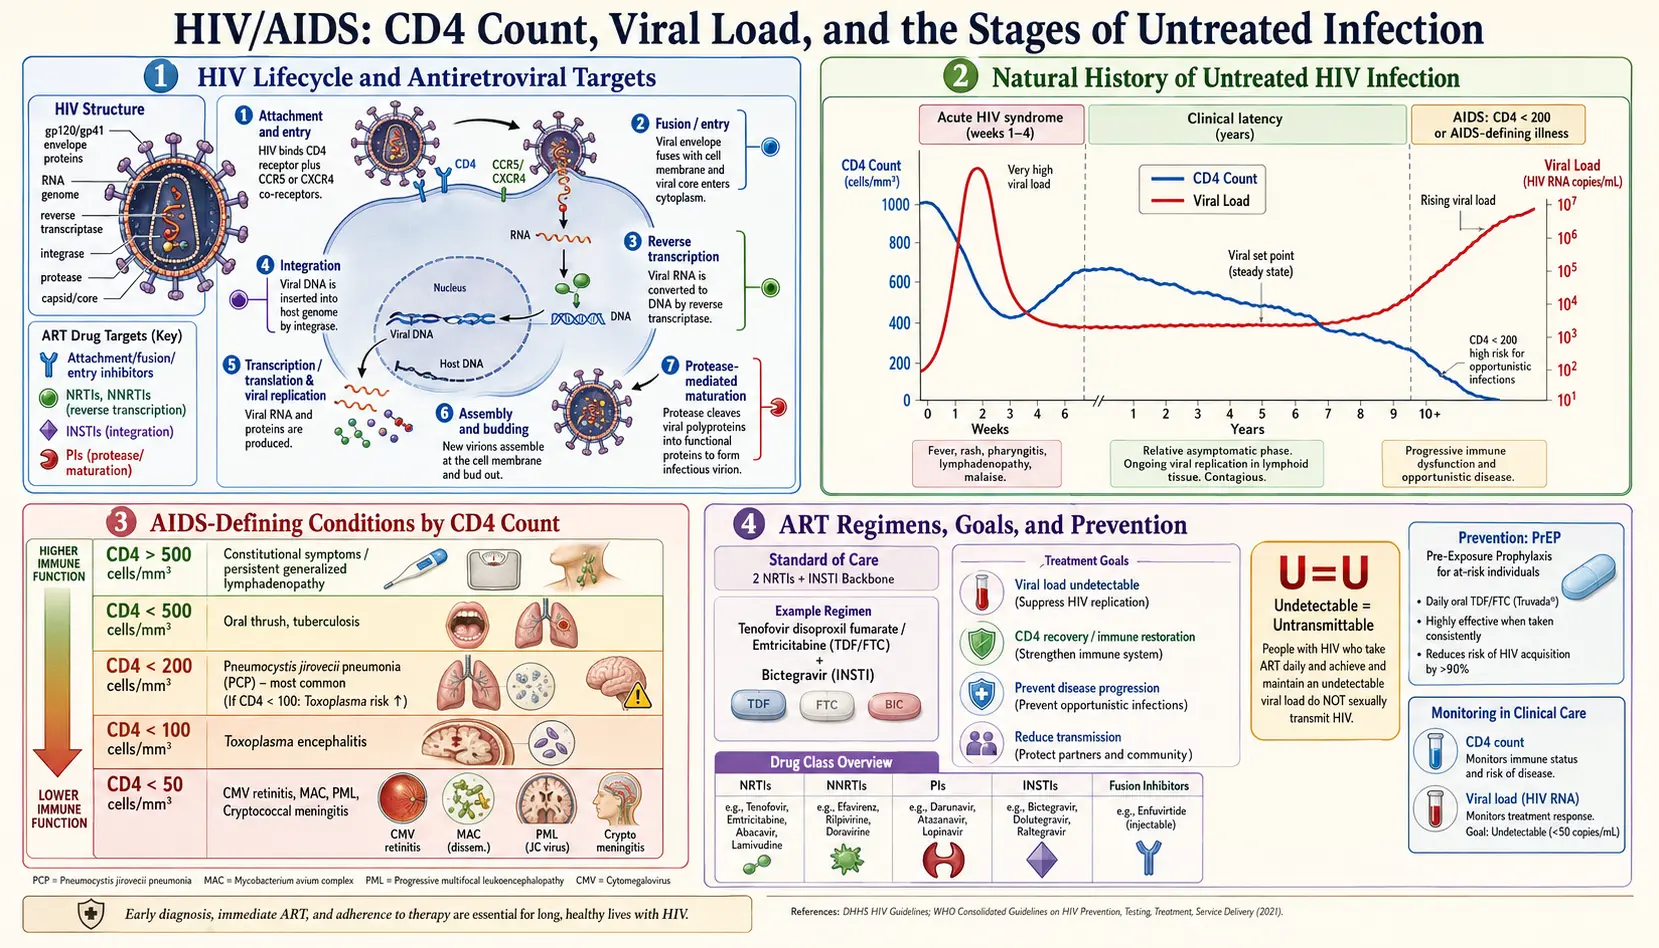
Table of Contents
1. Overview
Human Immunodeficiency Virus (HIV) is a lentivirus belonging to the Retroviridae family that infects and progressively depletes CD4+ T-lymphocytes, macrophages, and dendritic cells — the critical mediators of cell-mediated immunity. Acquired Immunodeficiency Syndrome (AIDS) represents the final, advanced stage of human immunodeficiency virus infection, defined by a CD4+ count below 200 cells/mm³ or the presence of one or more acquired immunodeficiency syndrome-defining illnesses in a human immunodeficiency virus-infected individual.
Human immunodeficiency virus was first identified in 1983 by researchers at the Institut Pasteur (HIV-1) and subsequently characterized as a retrovirus encoding reverse transcriptase, integrase, and protease — enzymes that have become the primary targets of antiretroviral therapy (ART). Without treatment, median time from human immunodeficiency virus acquisition to acquired immunodeficiency syndrome is approximately 10 years; with modern ART, life expectancy approaches that of the human immunodeficiency virus-negative population.
Two distinct viral types are recognized: HIV-1 (globally predominant, more virulent) and HIV-2 (largely confined to West Africa, slower progression, intrinsically resistant to non-nucleoside reverse transcriptase inhibitors). HIV-1 is further classified into four groups (M, N, O, P) and multiple subtypes (clades A–K), with clade B predominating in North America and Western Europe.
2. Epidemiology
As of 2023, UNAIDS estimates approximately 39.9 million people are living with human immunodeficiency virus globally, with sub-Saharan Africa bearing the greatest burden (roughly 25.9 million). Eastern and Southern Africa alone account for more than 54% of all people living with human immunodeficiency virus. However, the fastest-growing epidemics are now in Eastern Europe, Central Asia, and parts of Asia-Pacific.
- Incidence: Approximately 1.3 million new infections occurred in 2023, a 59% reduction from the peak of 3.2 million in 1995.
- Mortality: acquired immunodeficiency syndrome-related deaths numbered approximately 630,000 in 2023, down from a peak of 2.1 million in 2004.
- Treatment coverage: 29.8 million of those living with human immunodeficiency virus (approximately 75%) were accessing ART as of 2023.
- United States: Approximately 1.2 million people live with human immunodeficiency virus; roughly 13% are unaware of their infection. Gay, bisexual, and other men who have sex with men (MSM) account for about 67% of new diagnoses.
Demographic disparities are profound: Black/African American individuals represent approximately 13% of the US population but account for 42% of new human immunodeficiency virus diagnoses. Transgender women face human immunodeficiency virus prevalence rates of 14–22% in high-burden settings. Globally, adolescent girls and young women (aged 15–24) in sub-Saharan Africa account for 20% of new human immunodeficiency virus infections despite comprising only 10% of the population.
Transmission routes include sexual contact (vaginal, anal, oral — anal intercourse carries the highest per-act risk at approximately 1.4% receptive, 0.11% insertive), sharing of contaminated injection equipment (approximately 0.67% per-act risk), vertical transmission from mother to child (during pregnancy, labor/delivery, or breastfeeding), and — rarely — receipt of contaminated blood products or needlestick injuries in healthcare workers.
3. Pathophysiology
Human immunodeficiency virus's life cycle proceeds through several discrete steps, each of which represents a therapeutic target:
- Attachment and co-receptor binding: The viral envelope glycoprotein gp120 binds to CD4 on host T-cells, macrophages, and dendritic cells. Subsequent conformational change enables binding to chemokine co-receptors CCR5 (R5-tropic strains, dominant in early infection) or CXCR4 (X4-tropic, associated with disease progression), or both (dual-tropic).
- Fusion: gp41-mediated membrane fusion enables viral core entry into the cytoplasm.
- Reverse transcription: Viral RNA is reverse-transcribed into double-stranded DNA by human immunodeficiency virus reverse transcriptase, an error-prone enzyme that introduces ~1 mutation per replication cycle, generating enormous viral diversity.
- Integration: Viral DNA (provirus) is transported into the nucleus and integrated into host chromosomal DNA by human immunodeficiency virus integrase — establishing a permanent reservoir.
- Transcription and translation: Host cellular machinery transcribes viral genes; precursor polyproteins are synthesized.
- Assembly, budding, and maturation: Viral protease cleaves precursor polyproteins into functional structural and enzymatic components; mature, infectious virions bud from the cell membrane.
CD4+ T-cell depletion occurs via direct viral cytopathic effects, immune-mediated killing of infected cells, chronic immune activation, and pyroptosis — a form of inflammatory programmed cell death triggered by abortive human immunodeficiency virus infection of resting CD4+ cells. The resulting immunodeficiency is compounded by chronic systemic inflammation driven by microbial translocation across a damaged gut epithelium (human immunodeficiency virus enteropathy), generating a persistent pro-inflammatory milieu that accelerates cardiovascular, renal, and neurocognitive disease even in virologically suppressed patients on ART.
Viral reservoirs — long-lived resting CD4+ T-cells, macrophages, and potentially astrocytes — harbor integrated provirus and are impervious to ART, representing the principal barrier to cure. The gut-associated lymphoid tissue (GALT) is seeded within days of transmission and represents the largest anatomical compartment of human immunodeficiency virus replication.
4. Etiology and Risk Factors
Human immunodeficiency virus infection is caused exclusively by the HIV-1 or HIV-2 retrovirus. Key risk factors for acquisition include:
- Sexual behavior: Unprotected receptive anal intercourse (highest per-act risk), multiple sexual partners, concurrent partnerships, sexually transmitted infections (particularly genital ulcer disease), and lack of male circumcision (for penile human immunodeficiency virus acquisition).
- Injection drug use: Sharing needles, syringes, or other drug preparation equipment.
- Mother-to-child transmission (MTCT): Maternal viral load, duration of membrane rupture, breastfeeding, and maternal CD4 count are key determinants.
- Occupational exposure: Percutaneous needlestick injuries in healthcare workers (average risk 0.23% per incident).
- Biological susceptibility factors: Absence of CCR5-Δ32 homozygosity (a naturally protective mutation), high genital inflammation, microbiome dysbiosis, concurrent STIs.
- Socioeconomic and structural determinants: Poverty, gender inequality, criminalization of same-sex behavior, limited healthcare access, and stigma each independently amplify population-level risk.
5. Clinical Presentation
U.S. Centers for Disease Control and Prevention Staging System (2014 Revised Classification)
Human immunodeficiency virus infection is classified into three stages based on CD4+ T-lymphocyte count and clinical criteria:
- Stage 1: CD4 count ≥500 cells/mm³, no acquired immunodeficiency syndrome-defining condition.
- Stage 2: CD4 count 200–499 cells/mm³, no acquired immunodeficiency syndrome-defining condition.
- Stage 3 (acquired immunodeficiency syndrome): CD4 count <200 cells/mm³ OR presence of an acquired immunodeficiency syndrome-defining illness regardless of CD4 count.
Clinical Phases
Acute human immunodeficiency virus infection (Fiebig stages I–VI): Occurs 2–4 weeks post-exposure. Approximately 40–90% of newly infected individuals develop acute retroviral syndrome — a mononucleosis-like illness featuring fever, lymphadenopathy, pharyngitis, rash (maculopapular, trunk-predominant), myalgia, arthralgia, headache, and occasionally aseptic meningitis or encephalitis. Viral load peaks at 10⁶–10⁷ copies/mL; CD4 count transiently drops. Plasma HIV RNA (NAAT) is detectable before human immunodeficiency virus antibodies, creating a seronegative window period of approximately 10–33 days.
Chronic human immunodeficiency virus infection (clinical latency): Persistent generalized lymphadenopathy may occur. CD4 count declines at a median rate of 50–100 cells/mm³ per year in the absence of treatment. Patients are generally asymptomatic but infectious. Human immunodeficiency virus-associated conditions (e.g., oral candidiasis, hairy leukoplakia, herpes zoster, idiopathic thrombocytopenic purpura, seborrheic dermatitis) may emerge as CD4 count falls below 500 cells/mm³.
Acquired immunodeficiency syndrome: CD4 <200 cells/mm³ or acquired immunodeficiency syndrome-defining illnesses including Pneumocystis jirovecii pneumonia (PCP), cerebral toxoplasmosis, cryptococcal meningitis, cytomegalovirus (CMV) retinitis, Mycobacterium avium complex (MAC), Kaposi sarcoma, primary central nervous system (CNS) lymphoma, human immunodeficiency virus wasting syndrome, and human immunodeficiency virus encephalopathy/dementia.
6. Diagnosis
The U.S. Centers for Disease Control and Prevention (CDC) and U.S. Preventive Services Task Force (USPSTF) recommend opt-out human immunodeficiency virus screening for all individuals aged 13–64 years in healthcare settings, and more frequent testing (at least annually) for persons at higher risk.
Recommended Diagnostic Algorithm (U.S. Centers for Disease Control and Prevention 2014)
- Fourth-generation combination HIV-1/2 antigen/antibody immunoassay (Ag/Ab combo test): Detects both human immunodeficiency virus p24 antigen and antibodies to HIV-1 and HIV-2. Sensitivity >99.9%; detects infection as early as 18 days post-exposure. This is the recommended initial test.
- HIV-1/HIV-2 antibody differentiation immunoassay: Performed on all reactive Ag/Ab combo specimens to distinguish HIV-1 from HIV-2 antibodies.
- HIV-1 nucleic acid test (NAT/NAAT): Performed if Ag/Ab combo is reactive but differentiation assay is negative or indeterminate — confirms acute HIV-1 infection and establishes plasma viral load baseline.
Monitoring Parameters
- CD4+ T-cell count: Prognostic marker; guides prophylaxis thresholds (e.g., PCP prophylaxis at CD4 <200, MAC prophylaxis at CD4 <50). Target: >500 cells/mm³ on ART.
- Human immunodeficiency virus plasma viral load (RNA PCR): Therapeutic response marker. Target: undetectable (<20–50 copies/mL) within 24 weeks of ART initiation. Measured at baseline, 2–4 weeks after ART initiation, every 4–8 weeks until undetectable, then every 3–6 months.
- Resistance testing: Genotypic resistance testing (HIV-1 reverse transcriptase, protease, integrase sequencing) at baseline before ART initiation, and with virologic failure.
- HIV-1 tropism assay (Trofile/genotypic prediction): Required before use of CCR5 antagonists (maraviroc).
- Additional baseline labs: Complete blood count, comprehensive metabolic panel, urinalysis, hepatitis B virus (HBV) serology (HBsAg, anti-HBs, anti-HBc), hepatitis C virus (HCV) antibody, syphilis serology, gonorrhea/chlamydia NAATs, tuberculin skin test or IGRA, chest radiograph, toxoplasma immunoglobulin G (IgG), cytomegalovirus immunoglobulin G, varicella immunoglobulin G, fasting lipid panel, glucose, hemoglobin A1c (HbA1c), urinary protein-to-creatinine ratio.
7. Treatment
Current guidelines (DHHS, EACS, WHO) recommend ART for all human immunodeficiency virus-infected individuals, regardless of CD4 count, to prevent acquired immunodeficiency syndrome progression, reduce transmission risk (Treatment as Prevention, TasP), and decrease non-AIDS morbidity driven by chronic inflammation.
Antiretroviral Drug Classes
- Nucleoside/nucleotide reverse transcriptase inhibitors (NRTIs): Tenofovir alafenamide (TAF), tenofovir disoproxil fumarate (TDF), emtricitabine (FTC), abacavir (ABC), lamivudine (3TC), zidovudine (ZDV).
- Non-nucleoside reverse transcriptase inhibitors (NNRTIs): Rilpivirine, efavirenz, doravirine, etravirine, nevirapine.
- Integrase strand transfer inhibitors (INSTIs): Bictegravir, dolutegravir, raltegravir, elvitegravir/cobicistat, cabotegravir.
- Protease inhibitors (PIs): Darunavir/ritonavir, atazanavir/ritonavir, lopinavir/ritonavir.
- CCR5 antagonists: Maraviroc (for R5-tropic virus only).
- Fusion inhibitors: Enfuvirtide (injectable, reserved for salvage).
- Post-attachment inhibitors: Ibalizumab (for multidrug-resistant human immunodeficiency virus).
- Capsid inhibitors: Lenacapavir (long-acting injectable, approved 2022 for heavily treatment-experienced patients).
Preferred Initial Regimens (DHHS 2024)
- Bictegravir/TAF/FTC (Biktarvy) — single-tablet, once daily; high barrier to resistance; preferred for most treatment-naive adults.
- Dolutegravir + TAF/FTC (or TDF/FTC) — highly effective; preferred in pregnancy (dolutegravir + TDF/FTC or ABC/3TC).
- Dolutegravir/rilpivirine (Juluca) — two-drug maintenance regimen; requires viral suppression, CD4 >200, no prior NNRTI resistance, no hepatitis B virus coinfection.
- Cabotegravir + rilpivirine IM (Cabenuva) — long-acting injectable given monthly or every 2 months; approved for virologically suppressed adults.
Opportunistic Infection Prophylaxis
- PCP: TMP-SMX DS once daily (primary prophylaxis if CD4 <200 cells/mm³ or history of oropharyngeal candidiasis).
- Toxoplasmosis: TMP-SMX DS once daily (if CD4 <100 and toxoplasma immunoglobulin G positive).
- MAC: Azithromycin 1200 mg weekly (if CD4 <50 and not on suppressive ART).
- Cryptococcus: Fluconazole prophylaxis in settings with high prevalence and CD4 <100.
- Tuberculosis (LTBI): Isoniazid 300 mg daily × 9 months (or rifapentine-based 3-month regimen) for all human immunodeficiency virus+ with positive IGRA/TST.
8. Complications
Acquired immunodeficiency syndrome-defining conditions (selected): Pneumocystis jirovecii pneumonia, cerebral toxoplasmosis, cryptococcal meningitis, cytomegalovirus retinitis/colitis, MAC disseminated infection, Kaposi sarcoma (HHV-8), primary central nervous system lymphoma, progressive multifocal leukoencephalopathy (JC virus), cryptosporidiosis, human immunodeficiency virus wasting syndrome, human immunodeficiency virus-associated dementia.
Non-AIDS complications (driven by chronic immune activation even on suppressive ART): Cardiovascular disease (2–3× increased risk of myocardial infarction (MI); human immunodeficiency virus-associated accelerated atherosclerosis), chronic kidney disease (human immunodeficiency virus-associated nephropathy, FSGS, ART nephrotoxicity), liver disease (hepatitis C virus/hepatitis B virus coinfection, non-alcoholic fatty liver disease (NAFLD), cirrhosis), neurocognitive impairment (human immunodeficiency virus-associated neurocognitive disorders, HAND), osteopenia/osteoporosis, metabolic syndrome, non-AIDS malignancies (anal cancer, lung cancer, Hodgkin lymphoma, hepatocellular carcinoma — all increased), and immune reconstitution inflammatory syndrome (IRIS) following ART initiation.
Drug toxicities: TDF — renal tubular dysfunction, Fanconi syndrome, reduced bone mineral density; ABC — hypersensitivity reaction (human leukocyte antigen-B*57:01 screening mandatory before use); NNRTIs — hepatotoxicity, rash, central nervous system symptoms; PIs — dyslipidemia, lipodystrophy, insulin resistance, QTc prolongation; dolutegravir — insomnia, weight gain; cabotegravir — injection site reactions.
9. Prognosis
Prognosis has been transformed by effective ART. A 20-year-old human immunodeficiency virus-positive individual initiating ART with a CD4 count >350 cells/mm³ now has a projected life expectancy of approximately 70–73 years — approaching that of the general population. Key prognostic determinants include:
- CD4 nadir: Lower nadir is associated with increased risk of non-AIDS complications even after viral suppression.
- Viral suppression: Undetectable viral load is the strongest predictor of favorable outcome.
- Adherence: >95% adherence is associated with durable viral suppression; modern single-tablet regimens have substantially simplified adherence.
- Comorbidities: Concurrent hepatitis C virus, hepatitis B virus, tuberculosis, or substance use disorder worsens prognosis.
- Timing of ART initiation: Earlier initiation (START trial, 2015) reduces serious illness and death even at CD4 >500.
Untreated human immunodeficiency virus has a median survival from acquired immunodeficiency syndrome diagnosis of approximately 1–3 years. In resource-limited settings where ART access remains constrained, mortality remains substantial. The concept of Undetectable = Untransmittable (U=U) is now established: persons with plasma HIV RNA consistently <200 copies/mL have effectively zero risk of sexual transmission.
10. Prevention
Biomedical Prevention
- Pre-exposure prophylaxis (PrEP): Daily oral TDF/FTC (Truvada) or TAF/FTC (Descovy, for AMAB only) reduces human immunodeficiency virus acquisition by >99% with consistent use. Long-acting injectable cabotegravir (CAB-LA) every 8 weeks has demonstrated superiority over oral TDF/FTC in the HPTN 083 and 084 trials (86–89% reduction vs. oral PrEP).
- Post-exposure prophylaxis (PEP): Must be initiated within 72 hours of potential exposure; 28-day course of preferred regimen (TDF/FTC + dolutegravir or raltegravir). Highly effective if started promptly.
- Treatment as Prevention (TasP): ART achieving viral suppression eliminates sexual transmission (PARTNER studies, HPTN 052).
- Voluntary medical male circumcision (VMMC): Reduces female-to-male human immunodeficiency virus transmission by approximately 60%.
- Prevention of MTCT (PMTCT): Universal ART in pregnant women reduces MTCT to <2% (from ~30% without intervention).
- Harm reduction: Needle/syringe programs, medication-assisted treatment (methadone, buprenorphine) for opioid use disorder, naloxone distribution.
Behavioral and Structural Prevention
- Consistent and correct condom use, human immunodeficiency virus testing and counseling, partner notification, and treatment of STIs.
- Decriminalization of human immunodeficiency virus non-disclosure and same-sex behavior; addressing gender-based violence and structural poverty.
11. Recent Research and Advances
- Long-acting injectables: Lenacapavir (subcutaneous, every 6 months) combined with injectable broadly neutralizing antibodies is under evaluation in the PURPOSE 1 and 2 PrEP trials, with PURPOSE 1 demonstrating 100% efficacy in women (2024 interim analysis).
- Functional cure strategies: "Kick-and-kill" (latency reversing agents + immune-mediated clearance), gene therapy (CCR5 knockout via CRISPR), and shock-and-kill approaches are in clinical trials. The "Berlin patient" (allogeneic CCR5-Δ32 bone marrow transplant), "London patient," and several subsequent cases demonstrate proof-of-concept for human immunodeficiency virus eradication.
- Broadly neutralizing antibodies (bNAbs): VRC01, 3BNC117, 10-1074, and combinations are in trials for treatment and prevention. bNAbs targeting the CD4 binding site, V3-glycan, and MPER epitopes show promise.
- Reservoir quantification: Intact proviral DNA assay (IPDA) has replaced total HIV DNA as the preferred measure of replication-competent reservoir size.
- Dolutegravir in pregnancy: WHO now recommends dolutegravir-based ART throughout pregnancy following reassuring data from the Tsepamo study clarifying the initial neural tube defect signal.
- Weight gain on INSTI-based ART: Ongoing investigation of mechanisms (off-target MC4R antagonism by dolutegravir/bictegravir) and mitigation strategies.
Key Research Papers
- UNAIDS. Global HIV & AIDS Statistics — Fact Sheet 2024. unaids.org
- Panel on Antiretroviral Guidelines for Adults and Adolescents. Guidelines for the Use of Antiretroviral Agents in Adults and Adolescents with HIV. DHHS 2024. https://clinicalinfo.hiv.gov/en/guidelines/adult-and-adolescent-arv
- Cohen MS, Chen YQ, McCauley M, et al. Prevention of HIV-1 infection with early antiretroviral therapy (HPTN 052). N Engl J Med. 2011;365:493–505. — doi:10.1056/NEJMoa1105243
- The INSIGHT START Study Group. Initiation of antiretroviral therapy in early asymptomatic HIV infection. N Engl J Med. 2015;373:795–807. — doi:10.1056/NEJMoa1506816
- Rodger AJ, Cambiano V, Bruun T, et al. Risk of HIV transmission through condomless sex in serodifferent gay couples (PARTNER): final results of a multicentre, prospective, observational study. Lancet. 2019;393:2428–2438. — doi:10.1016/S0140-6736(19)30418-0
- Landovitz RJ, Donnell D, Clement ME, et al. Cabotegravir for HIV prevention in cisgender men and transgender women (HPTN 083). N Engl J Med. 2021;385:595–608. — doi:10.1056/NEJMoa2101016
- Bekker LG, et al. Twice-yearly lenacapavir for HIV prevention in women (PURPOSE 1). N Engl J Med. 2024 (interim results). — doi:10.1056/NEJMoa2407001
- Günthard HF, Calvez V, Paredes R, et al. European AIDS Clinical Society (EACS) Guidelines Version 12.0. HIV Med. 2023;24:S1–S201. — Search PubMed
- Finzi D, Hermankova M, Pierson T, et al. Identification of a reservoir for HIV-1 in patients on highly active antiretroviral therapy. Science. 1997;278:1295–1300. — doi:10.1126/science.278.5341.1295
- Riddler SA, Haubrich R, DiRienzo AG, et al. Class-sparing regimens for initial treatment of HIV-1 infection (ACTG 5142). N Engl J Med. 2008;358:2095–2106. — doi:10.1056/NEJMoa074609
- Cihlar T, Fordyce M. Current status and prospects of HIV treatment. Curr Opin Virol. 2016;18:50–56. — doi:10.1016/j.coviro.2016.03.004
- Deeks SG, Lewin SR, Havlir DV. The end of AIDS: HIV infection as a chronic disease. Lancet. 2013;382:1525–1533. — doi:10.1016/S0140-6736(13)61809-7
- Saez-Cirion A, Pancino G. HIV controllers: a heterogeneous group of HIV-infected individuals with spontaneous control of viral replication. Cell Mol Immunol. 2013;10:15–26. — doi:10.1038/cmi.2012.51
- Chu C, Selwyn PA. Complications of HIV infection: a systems-based approach. Am Fam Physician. 2011;83:395–406. https://www.aafp.org/pubs/afp/issues/2011/0215/p395.html
- CDC. Revised recommendations for HIV testing of adults, adolescents, and pregnant women in health-care settings. MMWR Recomm Rep. 2006;55(RR-14):1–17. https://www.cdc.gov/mmwr/preview/mmwrhtml/rr5514a1.htm
PubMed Topic Searches
The following PubMed topic searches retrieve current peer-reviewed literature on human immunodeficiency virus/acquired immunodeficiency syndrome. Each link opens a live PubMed query so you always see the most recent publications.
- PubMed: HIV review
- PubMed: Antiretroviral therapy HIV outcomes
- PubMed: HIV pre-exposure prophylaxis PrEP
- PubMed: HIV tenofovir emtricitabine
- PubMed: HIV viral load undetectable untransmittable
- PubMed: HIV mother to child transmission prevention
- PubMed: HIV long acting injectable cabotegravir
- PubMed: HIV cure Berlin patient stem cell
- PubMed: HIV opportunistic infection prophylaxis
- PubMed: HIV tuberculosis coinfection
- PubMed: HIV integrase inhibitor dolutegravir
- PubMed: HIV vaccine development trial
Connections
- Infectious Disease
- Tuberculosis
- Hepatitis C
- Hepatitis B
- Immune Boosting
- Zinc
- N-Acetylcysteine
- Vitamin D3
- Echinacea
- Meningitis
- Lymphoma
- Cancer
- Pneumonia
- Complete Blood Count
- Comprehensive Metabolic Panel
- Kidney Disease
- Cardiovascular Disease
- Cervical Cancer
- Herpes Simplex
- Bacterial Vaginosis
- Yeast Infections
- Benacerraf, Dausset & Snell — human leukocyte antigen-B*57:01 screening before abacavir — pharmacogenomics' cleanest win
- Ochoa & Kornberg — tenofovir and the chain-terminating drugs that jam viral copying