Lymphoma
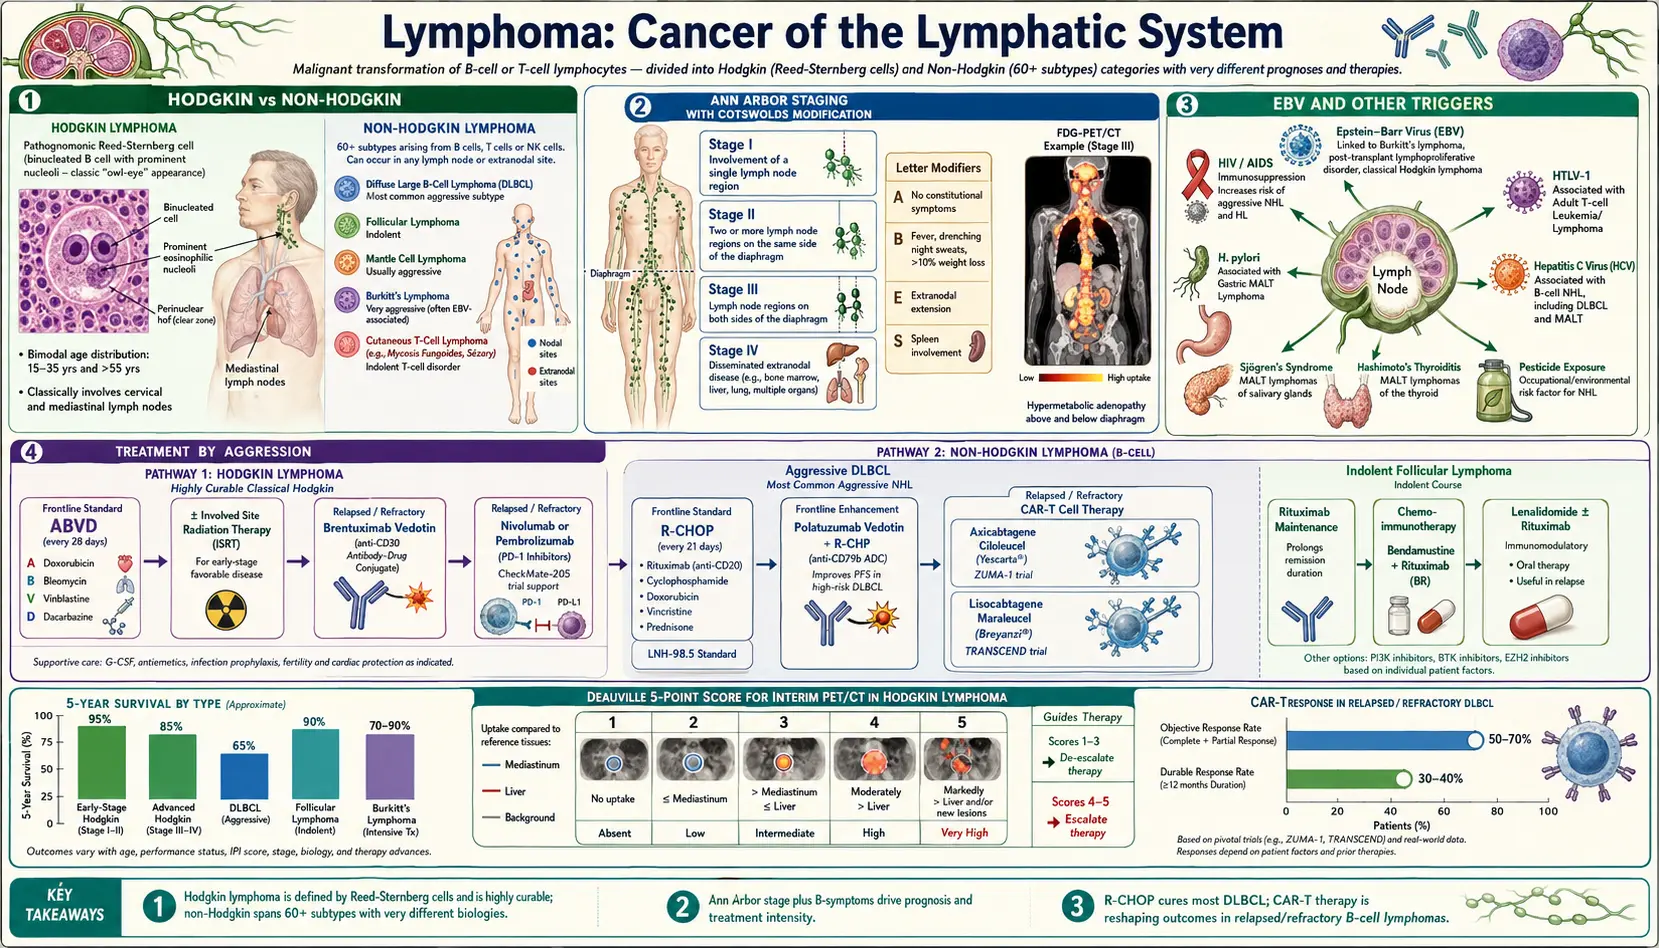
Table of Contents
What Lymphoma Is
Lymphoma is a type of cancer that begins in the lymphatic system, which is part of the body's immune system. It affects lymphocytes, a type of white blood cell that helps the body fight infections.
Types of Lymphoma
1. Hodgkin Lymphoma (HL)
- Distinctive feature: Presence of Reed-Sternberg cells, which are large, abnormal cells.
- Commonly affects: Often seen in young adults and those over 55.
2. Non-Hodgkin Lymphoma (NHL)
- Varied subtypes: Includes several different subtypes based on the specific type of lymphocyte affected (B cells or T cells).
- Commonly affects: More common than Hodgkin lymphoma and can occur at any age.
These type names follow the World Health Organization classification. Its 5th edition (2022) reorganized the lymphoid cancers into a hierarchy, changed some names and diagnostic criteria, deleted some entities, added new ones, and included inherited conditions that predispose to these cancers.
Causes and Risk Factors
The exact cause of lymphoma is not fully understood, but certain risk factors have been identified:
- Weakened immune system: Individuals with weakened immune systems, such as those with human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS) or on immunosuppressant drugs, are at higher risk.
- Infections: Certain infections like Epstein-Barr virus (EBV) and human T-cell leukemia/lymphoma virus (HTLV) are linked to higher risk.
- Age: Hodgkin lymphoma is more common in young adults and older individuals, while non-Hodgkin lymphoma risk increases with age.
- Gender: Some types of lymphoma are more common in men than women.
- Family history: A family history of lymphoma can increase the risk.
- Chemicals at work: A 2023 meta-analysis of 51 studies linked occupational exposure to carcinogens with non-Hodgkin lymphoma (overall odds ratio 1.27, 95% confidence interval 1.04–1.55), mainly pesticides, benzene and trichlorethylene, and mainly in agricultural work.
Symptoms of Lymphoma
Common signs and symptoms include:
- Swollen lymph nodes: Often in the neck, armpits, or groin.
- Persistent fatigue
- Unexplained weight loss
- Fever and night sweats
- Itchy skin
- Shortness of breath or coughing
Diagnosis and Treatment
Diagnosis
Diagnosing lymphoma involves a variety of tests and procedures:
- Physical examination: To check for swollen lymph nodes or spleen.
- Biopsy: A sample of lymph node tissue is examined for cancer cells.
- Imaging tests: Such as computed tomography (CT), magnetic resonance imaging (MRI), or positron emission tomography (PET) scans to identify affected areas.
- Blood tests: To check for abnormal levels of cells or markers.
Treatment Options
Treatment depends on the type and stage of lymphoma and may include:
- Chemotherapy: Drugs that kill cancer cells, usually combined with an antibody drug; this remains the backbone of first treatment.
- Radiation therapy: Often used in early-stage Hodgkin lymphoma or combined with chemotherapy.
- Immunotherapy: Utilizes the body's immune system to target cancer cells.
- Targeted therapy: Drugs designed to target specific abnormalities in cancer cells.
- Stem cell transplant: Replaces damaged bone marrow with healthy stem cells, often used for aggressive types or relapsed lymphoma.
Results From Recent Trials
- Advanced Hodgkin lymphoma, teenagers and adults: In a 2024 trial with 970 people aged 12 or older with stage III or IV disease, 92% of those given nivolumab with doxorubicin, vinblastine and dacarbazine were free of progression at 2 years, against 83% with brentuximab vedotin and the same three drugs. Only 7 patients received radiation.
- Advanced Hodgkin lymphoma, adults aged 60 or under: In the HD21 trial (1,482 people), the regimen of brentuximab vedotin, etoposide, cyclophosphamide, doxorubicin, dacarbazine and dexamethasone (BrECADD) caused less treatment-related illness than an escalated regimen of bleomycin, etoposide, doxorubicin, cyclophosphamide, vincristine, procarbazine and prednisone (eBEACOPP): 42% vs 59%. At 4 years 94.3% vs 90.9% were free of progression, and 98.6% vs 98.2% were alive.
- Diffuse large B-cell lymphoma, first treatment: In the POLARIX trial (879 people with intermediate- or high-risk disease), replacing vincristine with polatuzumab vedotin in the standard regimen raised 2-year progression-free survival from 70.2% to 76.7%. Survival at 2 years did not differ (88.7% vs 88.6%).
- Large B-cell lymphoma, first relapse: In the ZUMA-7 trial (359 people whose disease resisted first treatment or came back within 12 months), axicabtagene ciloleucel, a chimeric antigen receptor (CAR) T-cell therapy made from the patient's own immune cells, gave complete responses in 65% vs 32% with standard care. Event-free survival at 24 months was 41% vs 16%; estimated 2-year survival at an interim analysis was 61% vs 52%. Grade 3 or higher neurologic events occurred in 21%.
- Diffuse large B-cell lymphoma, later relapse: Bispecific antibodies are a newer kind of drug that brings T cells to the tumor cells. In a phase 2 study of glofitamab, 154 treated patients who had already had at least two earlier treatments, 39% had a complete response, and 78% of those responses were still ongoing at 12 months. Cytokine release syndrome, an immune overreaction, occurred in 63%.
Prognosis
The prognosis for lymphoma varies based on factors such as the type (Hodgkin or non-Hodgkin), stage at diagnosis, and the patient’s overall health. Advances in treatment have significantly improved survival rates for many forms of lymphoma.
Two trial figures give a sense of scale, though they describe trial volunteers and are not a general prognosis: 98.6% of adults aged 60 or under with advanced Hodgkin lymphoma were alive at 4 years on BrECADD in the HD21 trial, and about 88.6% of people with intermediate- or high-risk diffuse large B-cell lymphoma were alive at 2 years in the POLARIX trial.
Key Research Papers
Historical Background
Hodgkin lymphoma was first described by English physician Thomas Hodgkin in 1832, who identified the distinctive pattern of lymph node enlargement in autopsy specimens. The identification of Reed-Sternberg cells by Dorothy Reed and Carl Sternberg around 1900 provided the histological hallmark of Hodgkin disease. Non-Hodgkin lymphomas were later classified as a separate group, with Henry Rappaport’s classification system in 1966 being an early milestone.
- Younes A, Gopal AK, Smith SE, et al. Results of a pivotal phase II study of brentuximab vedotin for patients with relapsed or refractory Hodgkin’s lymphoma. J Clin Oncol. 2012;30(18):2183-2189. — doi:10.1200/JCO.2011.38.0410
- Schmitz R, Wright GW, Huang DW, et al. Genetics and pathogenesis of diffuse large B-cell lymphoma. N Engl J Med. 2018;378(15):1396-1407. — doi:10.1056/NEJMoa1801445
- Neelapu SS, Locke FL, Bartlett NL, et al. Axicabtagene ciloleucel CAR T-cell therapy in refractory large B-cell lymphoma. N Engl J Med. 2017;377(26):2531-2544. — doi:10.1056/NEJMoa1707447
- Shanbhag S, Ambinder RF. Hodgkin lymphoma: a review and update on recent progress. CA Cancer J Clin. 2018;68(2):116-132. — doi:10.3322/caac.21438
- Ansell SM, Lesokhin AM, Borrello I, et al. PD-1 blockade with nivolumab in relapsed or refractory Hodgkin’s lymphoma. N Engl J Med. 2015;372(4):311-319. — doi:10.1056/NEJMoa1411087
- Coiffier B, Thieblemont C, Van Den Neste E, et al. Long-term outcome of patients in the LNH-98.5 trial, the first randomized study comparing R-CHOP to standard CHOP in DLBCL. Blood. 2010;116(12):2040-2045. — doi:10.1182/blood-2010-03-276246
- Swerdlow SH, Campo E, Pileri SA, et al. The 2016 revision of the World Health Organization classification of lymphoid neoplasms. Blood. 2016;127(20):2375-2390. — doi:10.1182/blood-2016-01-643569
- Younes A, Santoro A, Shipp M, et al. Nivolumab for classical Hodgkin’s lymphoma after failure of both autologous stem-cell transplantation and brentuximab vedotin: a multicentre, multicohort, single-arm phase 2 trial. Lancet Oncol. 2016;17(9):1283-1294. — doi:10.1016/S1470-2045(16)30167-X
- A predictive model for aggressive non-Hodgkin’s lymphoma. International Non-Hodgkin’s Lymphoma Prognostic Factors Project. N Engl J Med. 1993;329(14):987-994. — doi:10.1056/NEJM199309303291402
- Sehn LH, Gascoyne RD. Diffuse large B-cell lymphoma: optimizing outcome in the context of clinical and biologic heterogeneity. Blood. 2015;125(1):22-32. — doi:10.1182/blood-2014-05-577189
- Armitage JO, Gascoyne RD, Lunning MA, Cavalli F. Non-Hodgkin lymphoma. The Lancet. 2017;390(10091):298-310. — doi:10.1016/S0140-6736(16)32407-2
- Abramson JS, Palomba ML, Gordon LI, et al. Lisocabtagene maraleucel for patients with relapsed or refractory large B-cell lymphomas (TRANSCEND NHL 001): a multicentre seamless design study. The Lancet. 2020;396(10254):839-852. — doi:10.1016/S0140-6736(20)31366-0
- Herrera AF, LeBlanc M, Castellino SM, et al. Nivolumab+AVD in advanced-stage classic Hodgkin's lymphoma. N Engl J Med. 2024;391(15):1379-1389. — PubMed PMID: 39413375
- Borchmann P, Ferdinandus J, Schneider G, et al. Assessing the efficacy and tolerability of PET-guided BrECADD versus eBEACOPP in advanced-stage, classical Hodgkin lymphoma (HD21): a randomised, multicentre, parallel, open-label, phase 3 trial. Lancet. 2024;404(10450):341-352. — PubMed PMID: 38971175
- Tilly H, Morschhauser F, Sehn LH, et al. Polatuzumab vedotin in previously untreated diffuse large B-cell lymphoma. N Engl J Med. 2022;386(4):351-363. — PubMed PMID: 34904799
- Locke FL, Miklos DB, Jacobson CA, et al. Axicabtagene ciloleucel as second-line therapy for large B-cell lymphoma. N Engl J Med. 2022;386(7):640-654. — PubMed PMID: 34891224
- Dickinson MJ, Carlo-Stella C, Morschhauser F, et al. Glofitamab for relapsed or refractory diffuse large B-cell lymphoma. N Engl J Med. 2022;387(24):2220-2231. — PubMed PMID: 36507690
- Alaggio R, Amador C, Anagnostopoulos I, et al. The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Lymphoid Neoplasms. Leukemia. 2022;36(7):1720-1748. — PubMed PMID: 35732829
- Francisco LFV, da Silva RN, Oliveira MA, et al. Occupational exposures and risks of non-Hodgkin lymphoma: a meta-analysis. Cancers (Basel). 2023;15(9):2600. — PubMed PMID: 37174074
PubMed Topic Searches
The following PubMed topic searches surface the current peer-reviewed literature on Lymphoma. Each link opens a live PubMed query; results update as new papers are indexed.
- PubMed: Search: lymphoma
- PubMed: Search: Hodgkin lymphoma
- PubMed: Search: non Hodgkin lymphoma
- PubMed: Search: diffuse large B cell lymphoma
- PubMed: Search: follicular lymphoma
- PubMed: Search: mantle cell lymphoma
- PubMed: Search: lymphoma rituximab
- PubMed: Search: lymphoma CAR T cell therapy
- PubMed: Search: lymphoma PET CT staging
- PubMed: Search: lymphoma Ann Arbor staging
- PubMed: Search: lymphoma checkpoint inhibitor
- PubMed: Search: cutaneous T cell lymphoma
Connections
- Oncology
- Cancer Overview
- Leukemia
- Multiple Myeloma
- Metastatic Cancers
- Turmeric
- Vitamin D3
- Anemia
- Reishi Mushroom
- Turkey Tail Mushroom
- Gerson Therapy Cancer Treatment
- Complete Blood Count
- Thyroid Disorders
- Sarcoma
- Fatigue
- Shortness of Breath
- Pesticides
- Sjogrens Syndrome
- Silver Nanoparticles
- Mononucleosis
- Non-Hodgkin Lymphoma — the largest lymphoma group, over 60 distinct subtypes.
- Primary Central Nervous System Lymphoma (PCNSL) — the rare form confined to the brain, spinal cord and eyes.
- Cryoglobulinemia — chronic clonal B-cell expansion that can progress to frank B-cell lymphoma.
- Hodgkin Lymphoma — the Reed-Sternberg-cell subtype with a bimodal age peak and cure rates above 85% in early-stage disease.
- Cold Agglutinin Disease — a cold-antibody hemolytic anemia driven by an underlying clonal B-cell lymphoproliferative process.
- Discussed in depth on these pages: H. pylori, Peptic Ulcers, and Gastritis