⚠ Evidence warning: Clinical trials or other evidence do not support the claim that parathyroid surgery lowers long-term deaths from heart disease and new cases of high blood pressure. This page keeps it as a report of what people, websites or other media say.
Hyperparathyroidism
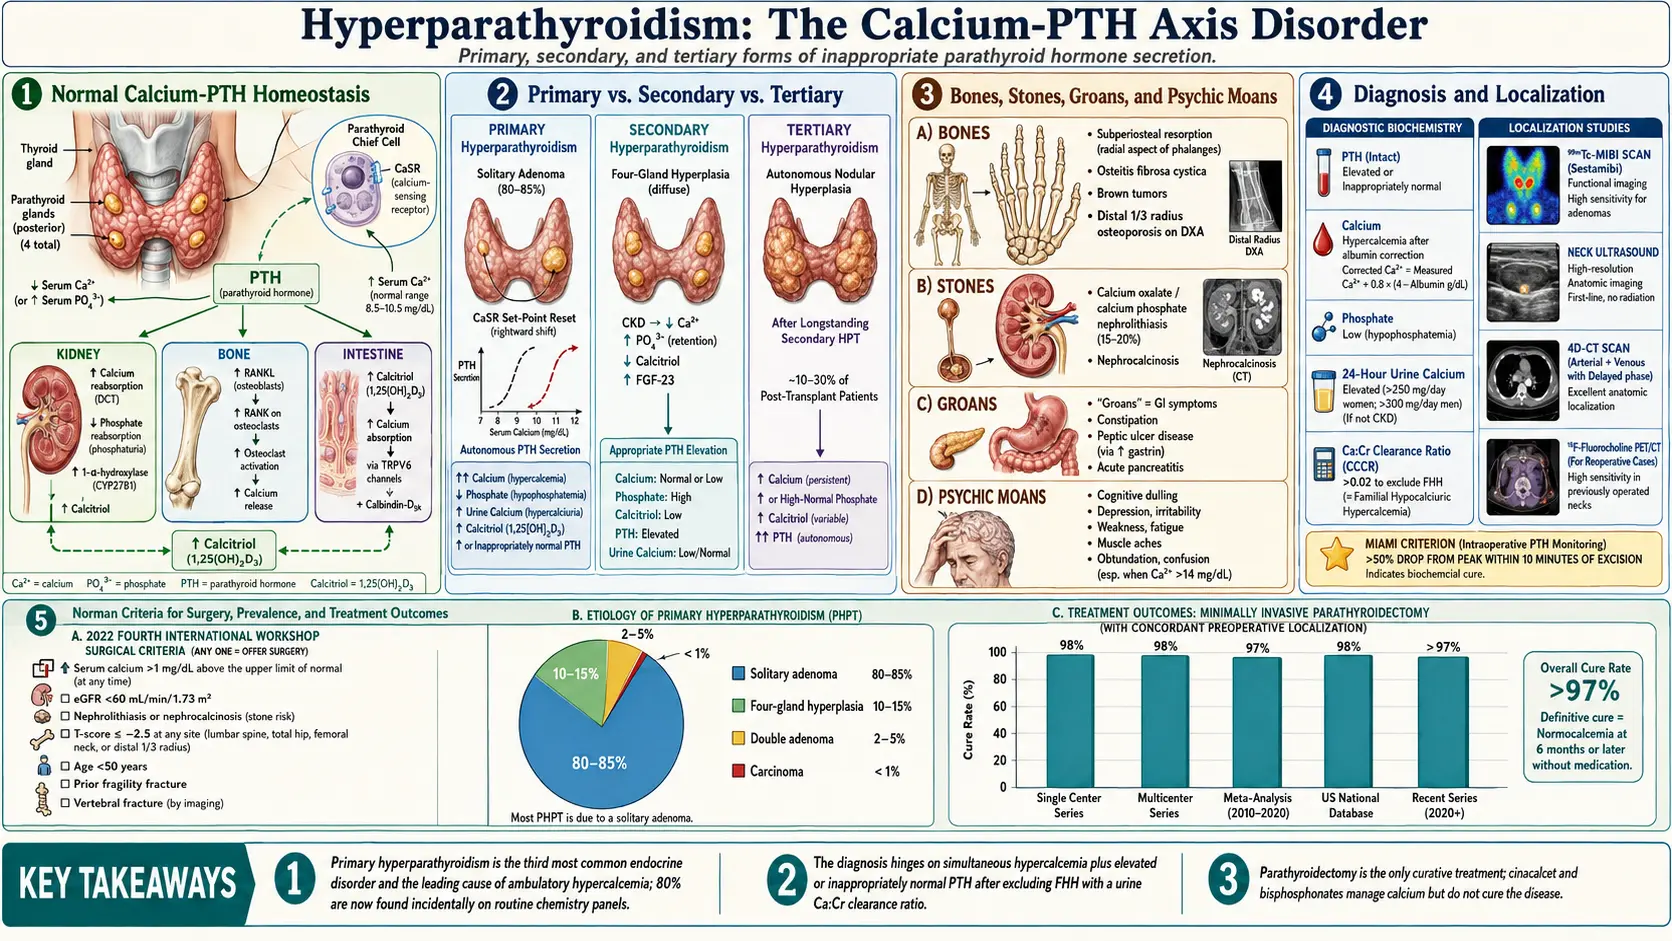
Table of Contents
1. Overview
Hyperparathyroidism means the small parathyroid glands in the neck make too much parathyroid hormone (PTH) for the amount of calcium in the blood. This hormone's job is to keep blood calcium steady, so the condition is a disorder of calcium balance (calcium homeostasis): the hormone stays high even when the blood calcium level calls for less of it. There are three main forms, named for what drives the problem and for where the feedback loop between calcium and parathyroid hormone breaks down:
- Primary hyperparathyroidism (PHPT): One or more abnormal parathyroid glands make too much hormone on their own and no longer respond to blood calcium (autonomous, calcium-independent secretion). The glands' calcium-sensing receptor (CaSR), the switch that normally turns the hormone down, is reset to a higher level, so blood calcium is high (hypercalcemia) and the hormone is inappropriately high at the same time.
- Secondary hyperparathyroidism (SHPT): The glands grow (compensatory hyperplasia) and make extra hormone as a reaction to something else: low blood calcium (hypocalcemia), vitamin D deficiency, or phosphate building up in the body — most commonly with chronic kidney disease (CKD). Here the high hormone is an appropriate, reactive response, and high blood calcium is absent until late stages.
- Tertiary hyperparathyroidism: After years of secondary hyperparathyroidism the glands begin to run on their own. It typically appears after a successful kidney transplant, when the enlarged glands keep producing too much hormone and blood calcium goes high even though the original trigger has been corrected. It marks the step from reactive to autonomous hormone secretion.
Primary hyperparathyroidism is the third most common hormone (endocrine) disorder after diabetes and thyroid disease, and it is the leading cause of high blood calcium in people who are not in hospital (ambulatory patients). Its picture has changed dramatically since routine blood testing arrived: from a disease of "bones, stones, groans, and psychic moans" to a condition overwhelmingly without symptoms, found by chance on routine chemistry panels.
2. Epidemiology
Primary hyperparathyroidism has a population prevalence of approximately 0.1–0.3% (1–3 per 1000 adults), with an annual incidence in a study of 3.5 million members of a Southern California health plan (1995 to 2010) averaging 66 cases per 100,000 person-years in women (range 34–120) and 25 in men (range 13–36). Incidence rose with age to 196 in women and 95 in men at ages 70–79. It was highest in Black patients (92 women, 46 men), followed by white patients (81, 29), Asian patients (52, 28) and Hispanic patients (49, 17). Prevalence tripled over the study period, from 76 to 233 per 100,000 women and from 30 to 85 per 100,000 men.
- Sex distribution: primary hyperparathyroidism has a striking female predominance, with a female-to-male ratio of 3–4:1. The predominance is most pronounced in postmenopausal women, who account for the majority of cases.
- Age at presentation: Peak incidence occurs in the fifth and sixth decades. However, primary hyperparathyroidism can occur at any age, including in children and adolescents (raising concern for hereditary forms).
- Incidental discovery: Approximately 80% of primary hyperparathyroidism cases in high-income countries are now diagnosed incidentally on routine laboratory screening, without classic symptoms of hypercalcemia. This proportion was less than 20% prior to the introduction of automated serum chemistry analyzers in the 1970s.
- Post-radiation incidence: Previous therapeutic or inadvertent neck irradiation increases primary hyperparathyroidism risk 2–5-fold, with a latency period of 20–50 years.
- Secondary hyperparathyroidism: Virtually universal in patients with advanced chronic kidney disease (glomerular filtration rate (GFR) less than 30 mL/min/1.73 m²), affecting essentially 100% of dialysis-dependent patients to varying degrees. Vitamin D deficiency-related secondary hyperparathyroidism is extremely common globally, given the high prevalence of vitamin D deficiency.
- Normocalcemic primary hyperparathyroidism: An emerging entity where parathyroid hormone is persistently elevated with consistently normal (not merely low-normal) albumin-corrected or ionized calcium, in the absence of secondary causes. Prevalence estimated at 0.4–1.0% in community populations.
3. Pathophysiology
Each form of hyperparathyroidism disrupts the loop between calcium and parathyroid hormone at a different point.
Normal Calcium-Parathyroid Hormone Homeostasis
Extracellular ionized calcium is maintained within a narrow range (1.15–1.35 mmol/L) through the integrated actions of parathyroid hormone, calcitriol (1,25-dihydroxyvitamin D), and calcitonin, acting on bone, kidney, and intestine.
The Calcium-sensing receptor — a G-protein-coupled receptor of Family C expressed on parathyroid chief cells and renal tubular cells — is the central sensor of ionized calcium. When extracellular Ca²⁺ rises, calcium-sensing receptor activates phospholipase C, generating inositol trisphosphate (IP₃) and diacylglycerol (DAG), which suppress parathyroid hormone gene transcription, parathyroid hormone mRNA stability, parathyroid hormone vesicle exocytosis, and parathyroid chief cell proliferation. Conversely, hypocalcemia releases this inhibition, prompting rapid parathyroid hormone secretion from pre-formed secretory granules (within seconds to minutes), increased parathyroid hormone gene expression (within minutes to hours), and parathyroid cellular proliferation (over days to weeks).
Parathyroid hormone exerts its effects through PTH1R, a Gs-coupled receptor:
- Kidney: Stimulates 1α-hydroxylase in proximal tubular cells, converting 25(OH)D to active calcitriol. Increases calcium reabsorption in the distal tubule. Inhibits phosphate reabsorption in the proximal tubule (phosphaturic effect), reducing serum phosphate.
- Bone: Intermittent parathyroid hormone stimulates osteoblast activity and bone formation (the basis of teriparatide therapy). Continuous parathyroid hormone excess activates osteoclasts via the RANK-RANKL axis (osteoblasts upregulate RANKL under parathyroid hormone stimulation), driving net bone resorption, hypercalcemia, and hypercalciuria.
- Intestine: Indirectly increases calcium and phosphate absorption through calcitriol-mediated upregulation of TRPV6 and calbindin-D9k in enterocytes.
Primary Hyperparathyroidism Pathophysiology
In primary hyperparathyroidism, the calcium-sensing receptor set-point is reset to a higher level in the abnormal gland(s), requiring a higher calcium concentration to suppress parathyroid hormone secretion. The sigmoid calcium-parathyroid hormone response curve is shifted rightward. The result is autonomous parathyroid hormone secretion producing:
- Hypercalcemia (from enhanced bone resorption and increased intestinal absorption via calcitriol)
- Hypophosphatemia (from parathyroid hormone-mediated phosphaturia)
- Hypercalciuria (from filtered calcium load exceeding the renal threshold, despite parathyroid hormone-stimulated distal tubular reabsorption)
- Elevated calcitriol (from parathyroid hormone-driven 1α-hydroxylase activity in the kidney)
- Subperiosteal bone resorption, osteitis fibrosa cystica (in severe/prolonged disease)
Molecular mechanisms of autonomous parathyroid hormone secretion include somatic mutations in the MEN1 gene (encoding menin, a tumor suppressor) in up to 20–30% of sporadic adenomas, and cyclin D1 gene rearrangement (with the parathyroid hormone gene promoter) in 5% — driving unregulated cell proliferation.
Secondary Hyperparathyroidism Pathophysiology
In chronic kidney disease, secondary hyperparathyroidism is driven by multiple converging stimuli:
- Hyperphosphatemia: Reduced glomerular filtration rate impairs renal phosphate excretion. Elevated phosphate directly suppresses 1α-hydroxylase and stimulates parathyroid hormone secretion. Phosphate also stimulates parathyroid cell proliferation. Fibroblast growth factor 23 (FGF-23), secreted by osteocytes in response to hyperphosphatemia, further suppresses 1α-hydroxylase and increases 24-hydroxylase activity, depleting calcitriol.
- Calcitriol deficiency: Loss of functional nephrons reduces 1α-hydroxylase capacity. Calcitriol normally suppresses parathyroid hormone gene transcription by binding the vitamin D receptor (VDR) — calcitriol deficiency removes this suppression. Calcitriol also upregulates calcium-sensing receptor expression; its deficiency reduces calcium-sensing receptor density, increasing the set-point for calcium-mediated parathyroid hormone suppression.
- Hypocalcemia: Calcitriol deficiency reduces intestinal calcium absorption, contributing to hypocalcemia which directly stimulates parathyroid hormone secretion via calcium-sensing receptor.
- Klotho deficiency: Klotho (a co-receptor for fibroblast growth factor 23) is expressed in the kidney and parathyroid gland. Chronic kidney disease reduces renal Klotho expression, impairing fibroblast growth factor 23 signaling and contributing to fibroblast growth factor 23 resistance and phosphate accumulation. Parathyroid Klotho deficiency impairs direct fibroblast growth factor 23-mediated parathyroid hormone suppression.
- Parathyroid hyperplasia: Chronic stimulation leads to diffuse hyperplasia, then nodular hyperplasia. Nodular hyperplasia contains monoclonal cell populations with reduced calcium-sensing receptor and vitamin D receptor expression — transitioning toward autonomous secretion (tertiary hyperparathyroidism).
Tertiary Hyperparathyroidism
After renal transplantation or correction of the underlying stimulus, most patients experience gradual resolution of secondary hyperparathyroidism. However, 10–30% develop persistent hypercalcemia due to autonomous parathyroid hormone secretion from hyperplastic glands. The monoclonal nodular hyperplasia that develops in secondary hyperparathyroidism is associated with somatic loss of calcium-sensing receptor expression and genetic alterations mirroring those in primary adenomas (MEN1 mutations, cyclin D1 overexpression). Gland weight and degree of nodular transformation predict the likelihood of autonomous function persisting after transplant.
4. Etiology and Risk Factors
Primary Hyperparathyroidism
- Solitary parathyroid adenoma: The most common cause (80–85% of primary hyperparathyroidism). Typically involves a single gland with monoclonal expansion. The contralateral gland is suppressed. Size ranges from a few millimeters to several centimeters.
- Multigland disease (four-gland hyperplasia): Accounts for 10–15% of primary hyperparathyroidism. All four glands are enlarged. More common in hereditary forms (MEN1, MEN2A, HPT-JT). Requires subtotal parathyroidectomy or total parathyroidectomy with autotransplantation.
- Double adenoma: Two separate adenomas in distinct glands; accounts for 2–5% of cases. Intraoperative parathyroid hormone monitoring is essential to confirm adequate resection.
- Parathyroid carcinoma: Rare (less than 1% of primary hyperparathyroidism); suspected when calcium is greater than 14 mg/dL, parathyroid hormone is markedly elevated (often greater than 5× upper limit of normal), and a firm, adherent neck mass is palpable. Associated with mutations in CDC73 (HRPT2), encoding parafibromin.
- Prior neck irradiation: Increases risk of primary hyperparathyroidism through radiation-induced parathyroid adenoma formation.
- Lithium therapy: Raises the calcium-sensing receptor set-point for calcium-mediated parathyroid hormone suppression, producing biochemical changes mimicking primary hyperparathyroidism. Prevalence of lithium-induced primary hyperparathyroidism is 3–6% of chronically treated patients; removal of the drug may normalize calcium in some.
Hereditary Forms of Primary Hyperparathyroidism
- Multiple Endocrine Neoplasia Type 1 (MEN1): Autosomal dominant; loss-of-function mutations in the MEN1 tumor suppressor gene (chromosome 11q13). Primary hyperparathyroidism is the earliest and most penetrant manifestation (95% lifetime risk), preceding pancreatic neuroendocrine tumors and pituitary adenomas. Characterized by four-gland hyperplasia and high recurrence rates after surgery. First-degree relatives have a 50% risk of the disease and can often be identified by a gene test. A 2025 consensus statement of the American Association of Clinical Endocrinology lists annual blood-test (biochemical) screening for people carrying the mutation or with an immediate family history; MEN1 features have appeared as early as age 5 and primary hyperparathyroidism as early as age 8, so some have suggested screening in early childhood.
- Multiple Endocrine Neoplasia Type 2A (MEN2A): Autosomal dominant; gain-of-function mutations in the RET proto-oncogene. Primary hyperparathyroidism occurs in 20–30% of MEN2A patients (compared to 95–100% for medullary thyroid carcinoma and 50% for pheochromocytoma). Typically mild hypercalcemia.
- Hyperparathyroidism-Jaw Tumor Syndrome (HPT-JT): Autosomal dominant; mutations in CDC73 (HRPT2). Associated with parathyroid adenomas (often cystic), ossifying fibromas of the jaw, renal tumors. Higher risk of parathyroid carcinoma (15–20%).
- Familial Isolated Hyperparathyroidism (FIHP): primary hyperparathyroidism without other endocrinopathy. Heterogeneous genetics; some cases harbor MEN1, CDC73, or CASR mutations.
- Familial Hypocalciuric Hypercalcemia (FHH): Autosomal dominant loss-of-function mutations in CASR (type 1), GNA11 (type 2), or AP2S1 (type 3). The calcium-sensing receptor set-point is reset in both the parathyroid gland and the kidney, resulting in mild hypercalcemia, modestly elevated or normal parathyroid hormone, and paradoxically low urine calcium (calcium-to-creatinine clearance ratio less than 0.01). Familial hypocalciuric hypercalcemia is benign and does not require surgery — distinguishing it from primary hyperparathyroidism is critical to avoid unnecessary parathyroidectomy.
Secondary and Tertiary Hyperparathyroidism Risk Factors
- Chronic kidney disease (the dominant cause of secondary hyperparathyroidism)
- Vitamin D deficiency (very common; dietary insufficiency, inadequate sun exposure, malabsorption syndromes)
- Malabsorption syndromes: celiac disease, Crohn disease, bariatric surgery, short bowel syndrome
- Pseudo-hypoparathyroidism (target organ resistance to parathyroid hormone)
- Long-term anticonvulsant therapy (induces CYP450-mediated vitamin D catabolism)
5. Clinical Presentation
Asymptomatic Primary Hyperparathyroidism
Most people with primary hyperparathyroidism in high-income countries have no obvious symptoms when it is found. A high calcium result on a routine blood panel starts the search. These people may still have vague complaints — tiredness, slowed thinking, low mood, constipation — that they do not mention and may not recognize as part of an illness until after successful surgery to remove the gland (parathyroidectomy).
Classic Symptomatic Primary Hyperparathyroidism
The mnemonic "bones, stones, groans, and psychic moans" encapsulates the classic syndrome of symptomatic primary hyperparathyroidism:
"Bones" — skeletal manifestations:
- Osteitis fibrosa cystica: the classic bone disease of severe, longstanding primary hyperparathyroidism. Bone is eaten away just under its outer surface (subperiosteal resorption), seen most clearly on the thumb-side edge of the middle bones of the index and middle fingers — a pattern that is pathognomonic (specific to this disease) on X-ray. There is also bone pain, brown tumors (bone cavities filled with fibrous tissue), and a "salt-and-pepper" look to the skull on X-ray.
- Thinning bones (osteopenia and osteoporosis): in primary hyperparathyroidism the dense outer bone (cortical bone, as at the forearm near the wrist, the distal radius) suffers more than the spongy inner bone (trabecular bone, as in the lower spine). Postmenopausal osteoporosis mainly affects the spongy sites.
- Subperiosteal resorption, intracortical tunneling, and endosteal scalloping on skeletal radiographs.
- Bones that break with little force (pathologic fractures) in severe disease.
"Stones" — nephrolithiasis and nephrocalcinosis:
- Kidney stones (nephrolithiasis) occur in 15–20% of primary hyperparathyroidism patients; most are calcium oxalate stones, though calcium phosphate stones are more characteristic. Repeated stones, particularly calcium phosphate stones, are a recognized reason to screen for primary hyperparathyroidism.
- Calcium settling throughout the kidney tissue (nephrocalcinosis) may cause kidney function to worsen over time.
- Typical signs: severe flank pain from a stone (renal colic), blood in the urine (hematuria), a blocked urinary tract.
"Groans" — gastrointestinal manifestations:
- Nausea, vomiting, loss of appetite and constipation — the most common gut symptoms of high blood calcium, caused by weaker contraction of the smooth muscle of the gut.
- Stomach and duodenal ulcers (peptic ulcer disease): high blood calcium stimulates gastrin secretion. Association with Zollinger-Ellison syndrome (gastrinoma) is characteristic of MEN1.
- Sudden inflammation of the pancreas (acute pancreatitis): classically associated with blood calcium above 12 mg/dL. Calcium activates trypsinogen intrapancreatically. Chronic pancreatitis and pancreatic calcifications may occur.
"Psychic moans" — neuropsychiatric manifestations:
- Trouble thinking, poor concentration and memory problems — often subtle.
- Depression, anxiety, irritability.
- Sluggishness, tiredness and general weakness.
- Severe high blood calcium (greater than 14 mg/dL) produces drowsiness, stupor and coma — this is hypercalcemic crisis.
Hypercalcemic Crisis
A medical emergency that hospitals treat as urgent: blood calcium typically greater than 14 mg/dL with confusion, severe nausea and vomiting, passing large amounts of urine (polyuria), great thirst (polydipsia), and dehydration (volume depletion). Can be precipitated by dehydration, immobilization, or intercurrent illness. May occur in previously asymptomatic primary hyperparathyroidism.
Secondary Hyperparathyroidism (Chronic Kidney Disease)
- Renal osteodystrophy: a spectrum of skeletal disorders in chronic kidney disease including osteitis fibrosa cystica (high-turnover, parathyroid hormone-driven), adynamic bone disease (low-turnover), osteomalacia, and mixed uremic osteodystrophy.
- Vascular and soft tissue calcification: medial calcification of arteries (Mönckeberg's), cardiac valvular calcification, and calciphylaxis (calcific uremic arteriolopathy — painful, ischemic skin lesions with very high mortality).
- Bone pain, fractures, skeletal deformities (particularly in pediatric chronic kidney disease).
- Pruritus (calcium-phosphate product deposition in skin).
- Cardiovascular morbidity: left ventricular hypertrophy, cardiac fibrosis, arrhythmias.
6. Diagnosis
Initial Biochemical Evaluation
The biochemical hallmark of primary hyperparathyroidism is the combination of hypercalcemia with an elevated or inappropriately normal intact parathyroid hormone (iPTH). The simultaneous interpretation of both values is essential:
- Serum total calcium: Correct for albumin: corrected calcium = measured calcium + 0.8 × (4.0 − albumin [g/dL]). Ionized calcium measurement is more reliable in critically ill patients or those with significant protein abnormalities.
- Intact parathyroid hormone: Measured by two-site immunoradiometric assay (IRMA) or immunochemiluminescent assay (ICMA). In primary hyperparathyroidism, parathyroid hormone is elevated in 85–90% of cases and "inappropriately normal" (within the upper portion of the reference range) in the remaining 10–15%, given that any parathyroid hormone secretion in the presence of hypercalcemia is inappropriate.
- Serum phosphate: Low-normal or frankly low in primary hyperparathyroidism (parathyroid hormone-induced phosphaturia). Elevated in chronic kidney disease-related secondary hyperparathyroidism.
- 24-hour urine calcium: Often elevated. The 2014 workshop cut-off was greater than 400 mg/day; the 2022 Fifth International Workshop uses above 250 mg/24 hours in women and above 300 mg/24 hours in men, and in a 2025 cohort of 125 asymptomatic patients 49.6% were above these lower cut-offs. Critical for calculating the calcium-to-creatinine clearance ratio to exclude familial hypocalciuric hypercalcemia (ratio less than 0.01 strongly suggests familial hypocalciuric hypercalcemia).
- Urine calcium-to-creatinine clearance ratio: (Urine Ca × Serum Cr) / (Serum Ca × Urine Cr). Values greater than 0.02 support primary hyperparathyroidism; values less than 0.01 support familial hypocalciuric hypercalcemia.
- 25-hydroxyvitamin D: Measured to exclude vitamin D deficiency as a cause of secondary parathyroid hormone elevation or to identify co-existing deficiency complicating primary hyperparathyroidism. Vitamin D deficiency is usually repleted before parathyroid hormone levels are interpreted.
- Serum alkaline phosphatase (bone-specific): Elevated in high-turnover states; useful for monitoring skeletal disease activity.
- Serum creatinine and estimated glomerular filtration rate (eGFR): To assess renal function and exclude chronic kidney disease as a cause of secondary hyperparathyroidism.
Differential Diagnosis of Hypercalcemia
Hypercalcemia with elevated parathyroid hormone essentially confirms primary hyperparathyroidism (once familial hypocalciuric hypercalcemia is excluded). Hypercalcemia with suppressed parathyroid hormone (less than 20 pg/mL) indicates a parathyroid hormone-independent mechanism:
- Malignancy: The most common cause of hypercalcemia in hospitalized patients. Mechanisms include parathyroid hormone-related protein secretion (humoral hypercalcemia of malignancy — squamous cell carcinoma, renal cell carcinoma, breast cancer), osteolytic bone metastases (multiple myeloma, breast cancer), and ectopic 1,25(OH)₂D production (lymphomas).
- Granulomatous diseases: Sarcoidosis, tuberculosis, histoplasmosis, berylliosis — autonomous extrarenal 1α-hydroxylase activity in activated macrophages produces excess calcitriol.
- Vitamin D toxicity: Excessive supplementation or granulomatous disease.
- Thiazide diuretics: Reduce renal calcium excretion; mild hypercalcemia; the drug is usually stopped and calcium re-checked before the result is attributed to primary hyperparathyroidism.
- Milk-alkali syndrome: Excessive calcium carbonate ingestion; elevated calcium, metabolic alkalosis, renal insufficiency.
- Immobilization: Accelerated bone resorption; most significant in Paget disease, high-turnover states.
- Adrenal insufficiency, hyperthyroidism, acromegaly.
Localization Studies (Preoperative Imaging)
Localization studies are performed only after biochemical diagnosis of primary hyperparathyroidism is confirmed — their purpose is surgical planning, not diagnosis. The standard approach combines two complementary modalities:
- Sestamibi (99mTc-MIBI) scintigraphy: Sestamibi preferentially accumulates in mitochondria-rich parathyroid adenomas and is retained longer than in normal thyroid tissue (differential washout). Sensitivity 80–85% for solitary adenomas; lower for multigland disease. May be combined with single-photon emission computed tomography (SPECT) or SPECT/CT for three-dimensional localization.
- Ultrasound of the neck: Sensitivity 70–80% for parathyroid adenomas. Operator-dependent; inferior for ectopic, retrotracheal, or retroesophageal glands. Complements sestamibi well when both localize to the same region (concordant localization), which is optimal before minimally invasive parathyroidectomy.
- Four-dimensional computed tomography (CT) (4D-CT): Multiplanar computed tomography with arterial, venous, and delayed phases exploits the hypervascular enhancement pattern of parathyroid adenomas. Sensitivity 70–90%; superior to sestamibi for multigland disease and ectopic locations. Radiation exposure is a consideration in young patients.
- Magnetic resonance imaging (MRI): Useful for persistent/recurrent primary hyperparathyroidism after failed surgery and for ectopic mediastinal glands. Sensitivity approximately 70–80% for adenomas.
- Choline positron emission tomography (PET)/computed tomography: Emerging as the highest-sensitivity localization study (greater than 90%) for primary hyperparathyroidism, including multigland disease and ectopic glands. Not universally available; may be particularly valuable in reoperative settings. Fluorocholine ([¹⁸F]-choline) positron emission tomography/computed tomography is increasingly endorsed in guidelines. Its U.S. Food and Drug Administration status could not be confirmed: the agency's public label and drug-approval databases return no fluorocholine product, and a 2023 case report described it as outside Food and Drug Administration approval.
- Selective venous sampling for parathyroid hormone: Reserved for reoperative cases when non-invasive localization has failed. Catheterization of neck and mediastinal veins with parathyroid hormone gradient mapping to lateralize or localize a remnant or missed gland.
Bone Density Assessment
Dual-energy X-ray absorptiometry (DXA) measuring bone mineral density at the lumbar spine, total hip, femoral neck, and distal one-third radius (the cortical site most affected by primary hyperparathyroidism) is recommended by the workshop guidelines for all patients with primary hyperparathyroidism. The distal radius result is critical — isolated radius osteoporosis at the 1/3 site is a recognized surgical indication.
Criteria for Surgery (Fourth International Workshop 2013, Updated 2022)
The Fourth International Workshop on Asymptomatic primary hyperparathyroidism (2013), subsequently updated in guidelines published in 2022, recommends parathyroidectomy when any of the following criteria are met in an otherwise asymptomatic patient:
- Serum calcium: Greater than 1.0 mg/dL (0.25 mmol/L) above the upper limit of normal.
- Renal criteria:
- 24-hour urine calcium above 250 mg in women or above 300 mg in men (Fifth International Workshop, 2022). The 2014 version listed greater than 400 mg/day AND increased stone risk by biochemical stone risk analysis (supersaturation indices).
- Nephrolithiasis or nephrocalcinosis by imaging (X-ray, ultrasound, or computed tomography)
- Estimated glomerular filtration rate less than 60 mL/min/1.73 m²
- Skeletal criteria:
- T-score at or below −2.5 at lumbar spine, total hip, femoral neck, or distal one-third radius
- Prior fragility fracture
- Vertebral fracture on imaging (spine X-ray, computed tomography, magnetic resonance imaging, or dual-energy X-ray absorptiometry vertebral fracture assessment)
- Age: Less than 50 years (surgery recommended because of longer expected lifespan and disease-related bone loss and complications).
When none of these criteria are met, some patients still prefer surgery, and the decision is made person by person. Observation with monitoring is the usual course for those who decline surgery or have significant operative risk.
Intraoperative Parathyroid Hormone Monitoring (Miami Protocol)
Rapid intraoperative parathyroid hormone (IOPTH) assay — parathyroid hormone has a half-life of 3–5 minutes — allows real-time confirmation of complete hyperfunctioning gland removal. The Miami Criterion (most widely used), as its authors state it: a parathyroid hormone drop of 50% or more from the highest of either the pre-incision or the pre-excision level, at 10 minutes after gland excision; in 341 patients it correctly predicted the calcium level after surgery in 329. This confirms cure and enables minimally invasive parathyroidectomy under local anesthesia through a small cervical incision, avoiding bilateral neck exploration.
7. Treatment
Surgical Management of Primary Hyperparathyroidism
In everyday words: surgery to remove the overactive gland or glands (parathyroidectomy) is the only cure for primary hyperparathyroidism. It is the treatment of choice for people with symptoms and for people without symptoms who meet the surgical criteria. Medicines can lower calcium or protect bone but do not cure the disease. Secondary hyperparathyroidism is treated mainly by controlling phosphate and vitamin D, adding calcimimetic drugs when needed, and surgery only in severe cases.
- Minimally invasive parathyroidectomy (MIP): The preferred surgical approach in patients with concordant preoperative localization (sestamibi and ultrasound agreeing on a single adenoma). Involves excision of the localized adenoma through a focused incision under local or general anesthesia, guided by intraoperative parathyroid hormone monitoring. Cure rates exceed 97% with experienced surgeons. Less surgical morbidity, shorter hospitalization, and better cosmesis compared to bilateral neck exploration.
- Bilateral neck exploration (BNE): The traditional approach, in which all four parathyroid glands are identified and assessed. Required when preoperative localization fails or is discordant, when multigland disease (MEN1, MEN2A) is suspected, or when intraoperative parathyroid hormone does not meet criteria after single-gland excision. Cure rates: 95–98%.
- Subtotal parathyroidectomy: Removal of 3.5 glands, leaving a well-vascularized half-gland remnant (approximately 50 mg of tissue) in situ. Used for four-gland hyperplasia, particularly in secondary hyperparathyroidism and MEN1.
- Total parathyroidectomy with autotransplantation: All four glands removed; parathyroid tissue (60–80 mg) is minced and implanted in the non-dominant brachioradialis muscle or subcutaneous forearm fat. Permits easy access for removal if autonomous function develops, without re-entering the neck. Used in MEN1 and severe secondary hyperparathyroidism.
- Complications of parathyroid surgery:
- Hypocalcemia (transient in 10–30%, permanent in less than 1%): "hungry bone syndrome" — rapid mineral uptake by skeleton after parathyroid hormone removal; may require prolonged calcium and calcitriol supplementation.
- Recurrent laryngeal nerve injury (transient in 1–5%, permanent in less than 1%).
- Hypoparathyroidism (permanent in less than 1% with single adenoma excision; higher with bilateral neck exploration).
- Cure rates and recurrence: Biochemical cure (normocalcemia) is achieved in 95–99% of operations performed by high-volume surgeons. Recurrence occurs in 1–5% over 10 years for sporadic primary hyperparathyroidism; substantially higher (25–50%) in MEN1.
Medical Management of Primary Hyperparathyroidism
For patients who decline surgery, are poor surgical candidates, or do not meet surgical criteria:
- Cinacalcet (calcimimetic): An allosteric positive modulator of the calcium-sensing receptor — increases receptor sensitivity to extracellular calcium, suppressing parathyroid hormone secretion. Effectively normalizes serum calcium in 70–80% of primary hyperparathyroidism patients. Does not improve bone mineral density (unlike surgery). The U.S. Food and Drug Administration label covers hypercalcemia in adults with primary hyperparathyroidism for whom parathyroidectomy would be indicated on the basis of serum calcium levels, but who are unable to undergo parathyroidectomy. Label dosing: 30, 60 or 90 mg twice daily, and 90 mg three or four times daily as necessary. Adverse effects: nausea, hypocalcemia.
- Bisphosphonates (alendronate, risedronate, zoledronic acid): Improve bone mineral density at the lumbar spine and femoral neck in primary hyperparathyroidism; do not lower serum calcium or parathyroid hormone significantly. Used in patients with osteoporosis who are not surgical candidates, and generally not used when estimated glomerular filtration rate is less than 30 mL/min.
- Denosumab: an inhibitor of receptor activator of nuclear factor kappa-B ligand (RANKL); substantially increases bone mineral density in primary hyperparathyroidism. Not U.S. Food and Drug Administration-approved for this indication but used off-label; particularly useful in patients with renal impairment precluding bisphosphonates. Rebound hypercalcemia upon discontinuation is a concern.
- Hydration: Fluid intake of 2–3 L/day reduces nephrolithiasis risk and maintains renal calcium excretion.
- Dietary calcium: Modest dietary calcium restriction (1000–1200 mg/day) is described as reasonable; severe restriction paradoxically stimulates parathyroid hormone secretion and may worsen bone resorption. Dietary calcium is not eliminated.
- Vitamin D replacement: If 25(OH)D is less than 20 ng/mL, gradual repletion with vitamin D3 (800–2000 international units (IU)/day) is described, with careful calcium and parathyroid hormone monitoring. Vitamin D deficiency independently stimulates parathyroid hormone and may worsen the biochemical phenotype.
- Thiazide diuretics and lithium both raise serum calcium, so they are usually withheld when clinically possible.
Management of Hypercalcemic Crisis
- Aggressive intravenous (IV) saline hydration (300–500 mL/hour initially, then 100–200 mL/hour) to expand volume and promote calciuresis.
- Loop diuretics (furosemide) only after adequate volume repletion to prevent further volume contraction.
- Intravenous bisphosphonate: zoledronic acid 4 mg intravenous over 15 minutes; onset of calcium-lowering effect in 24–48 hours, peak at 4–7 days.
- Calcitonin: 4 international units/kg under the skin or into a muscle every 12 hours; rapid onset (4–6 hours) but tachyphylaxis within 48–72 hours due to receptor downregulation. Useful as a bridge while awaiting bisphosphonate effect.
- Denosumab: 60–120 mg under the skin if bisphosphonate is contraindicated (estimated glomerular filtration rate less than 30 mL/min).
- Glucocorticoids: effective for vitamin D-mediated hypercalcemia (sarcoidosis, vitamin D toxicity, lymphoma); not effective for primary hyperparathyroidism.
- Hemodialysis with low-calcium dialysate: reserved for life-threatening hypercalcemia with severe renal failure.
- Emergency parathyroidectomy: for refractory hypercalcemic crisis with confirmed primary hyperparathyroidism and adequate anesthetic risk.
Management of Secondary Hyperparathyroidism in Chronic Kidney Disease
Kidney Disease: Improving Global Outcomes guidelines (2017) target parathyroid hormone levels of 2–9 times the upper limit of normal in dialysis-dependent patients (to avoid adynamic bone disease from over-suppression).
- Phosphate control: Dietary phosphate restriction; phosphate binders (calcium-based: calcium carbonate, calcium acetate; non-calcium-based: sevelamer, lanthanum carbonate, sucroferric oxyhydroxide) for patients on dialysis or with serum phosphate greater than 4.6 mg/dL in non-dialysis chronic kidney disease.
- Vitamin D repletion: Nutritional vitamin D (ergocalciferol, cholecalciferol) for patients with 25(OH)D below 30 ng/mL with chronic kidney disease stages 3–5 not on dialysis.
- Active vitamin D (calcitriol) or vitamin D analogs: Paricalcitol, doxercalciferol — suppress parathyroid hormone transcription with less risk of hypercalcemia and hyperphosphatemia than calcitriol. Indicated when parathyroid hormone is persistently elevated above those targets despite nutrition-focused vitamin D repletion.
- Cinacalcet: calcium-sensing receptor positive allosteric modulator; lowers parathyroid hormone, calcium, and phosphate in secondary hyperparathyroidism. The EVOLVE trial failed to show a significant reduction in cardiovascular events in dialysis patients, though post-hoc analyses suggested benefit. Used in combination with vitamin D analogs for refractory secondary hyperparathyroidism.
- Etelcalcetide: intravenous calcimimetic administered thrice-weekly with hemodialysis; demonstrated superior parathyroid hormone suppression versus cinacalcet in a head-to-head randomized trial of 683 hemodialysis patients (more than a 30% reduction in 68.2% versus 57.7%).
- Parathyroidectomy for secondary hyperparathyroidism: Indicated for severe, refractory secondary hyperparathyroidism (intact parathyroid hormone persistently greater than 800 pg/mL with hypercalcemia or hyperphosphatemia or both) unresponsive to medical therapy; symptomatic bone disease; or calciphylaxis. Subtotal or total parathyroidectomy with autotransplantation performed.
8. Complications
- Nephrolithiasis and nephrocalcinosis: Present in 15–20% of primary hyperparathyroidism; recurrence is high without surgical correction. Chronic nephrocalcinosis leads to chronic kidney disease.
- Osteoporosis and fractures: primary hyperparathyroidism preferentially reduces cortical bone density. Hip and distal radius fracture risk is 2–3-fold elevated. Vertebral fractures occur despite relatively preserved trabecular bone mineral density on dual-energy X-ray absorptiometry (clinical vertebral fracture assessment is essential).
- Cardiovascular disease: Epidemiologic associations include hypertension, left ventricular hypertrophy, endothelial dysfunction, and increased arterial stiffness. Hypertension is present in 40–65% of primary hyperparathyroidism patients. Whether these effects are reversed by parathyroidectomy remains controversial; observational data suggest modest blood pressure reduction postoperatively.
- Neurocognitive impairment: Depression, anxiety, cognitive dysfunction, and impaired quality of life are associated with primary hyperparathyroidism and may improve after parathyroidectomy, though the evidence for neuropsychiatric benefit is less robust than for nephrolithiasis and bone disease.
- Gastrointestinal complications: Peptic ulceration, pancreatitis. Pancreatitis risk correlates with degree of hypercalcemia.
- Renal insufficiency: Hypercalcemia causes renal vasoconstriction, tubular injury, and nephrocalcinosis — collectively reducing glomerular filtration rate. Severe or prolonged primary hyperparathyroidism can produce permanent chronic kidney disease. Guidelines list reduced kidney function as a reason for surgery, yet an observational study of 43,697 US veterans found that surgery did not change the chance of losing half of kidney function (10.8% versus 12.0% at 10 years; hazard ratio 0.98). Those under 60 did see a reduced hazard (0.75).
- Hypertensive crisis and arrhythmias: Severe hypercalcemia shortens the QT interval and can precipitate ventricular arrhythmias. Bradycardia and first-degree atrioventricular block may occur.
- Calciphylaxis (in secondary hyperparathyroidism): Life-threatening with mortality up to 60–80%. Characterized by painful, rapidly progressive ischemic skin necrosis from calcium-phosphate deposition in arterioles. Requires urgent intervention including parathyroidectomy in some patients.
- Parathyroid carcinoma: Extremely rare. Aggressive course with local invasion, recurrence, and metastases. Treatment is complete surgical excision; palliative options include cinacalcet for refractory hypercalcemia.
9. Prognosis
- Surgical cure: Parathyroidectomy is curative in 95–99% of sporadic primary hyperparathyroidism cases. Post-operatively, serum calcium normalizes within 24–48 hours, and bone mineral density improves significantly over 3–5 years — particularly at the lumbar spine and femoral neck. Renal stones do not recur in the majority. Quality of life improves in most dimensions including energy, mood, and cognitive function.
- Asymptomatic primary hyperparathyroidism without surgery: Approximately 25–33% of monitored patients develop indications for surgery within 10 years. Serum calcium is stable in the majority without progressive hypercalcemia. Some reports describe ongoing silent bone loss and neurocognitive decline even in the "stable" group, and this has been used as an argument for early surgical referral. The 2022 Fifth International Workshop guidelines, as summarized in 2023, state that impaired neurocognitive function, poor quality of life or cardiovascular symptoms cannot be an indication for parathyroidectomy, for lack of clear data that surgery improves them.
- Surgery versus observation in mild disease: The one long randomized trial (191 people at eight Scandinavian centers, followed until 2018) found similar deaths (24 with surgery, 20 with observation) and similar heart, stroke, cancer, fracture and kidney-stone events (52 versus 49). The authors conclude that surgery "does not appear to reduce morbidity or mortality in mild" primary hyperparathyroidism and saw no adverse effects of observation for at least a decade.
- Fractures in older adults: Among 210,206 older US adults with primary hyperparathyroidism, those who had surgery had fewer fractures (10.2% versus 13.7%; adjusted hazard ratio 0.78; hip fracture 0.76). This is observational and differs from the randomized result in mild disease.
- MEN1-related primary hyperparathyroidism: High recurrence rate (25–50% over 10 years) despite adequate initial surgery. Lifelong surveillance required. Life expectancy is primarily determined by the associated pancreatic neuroendocrine tumors.
- Secondary/tertiary hyperparathyroidism: Prognosis is largely driven by the underlying renal disease. Adequate parathyroid hormone control with guideline-targeted therapy reduces skeletal morbidity and may reduce cardiovascular calcification progression. Parathyroidectomy for refractory secondary hyperparathyroidism improves skeletal outcomes and quality of life.
- Parathyroid carcinoma: 5-year survival is approximately 78–85% for completely resected cases (a National Cancer Data Base review of 733 patients reported overall survival of 82.3% at 5 years and 66% at 10 years); drops to 50% with metastatic disease. Local recurrence is frequent, requiring reoperation.
10. Prevention
- Primary prevention of primary hyperparathyroidism: No established preventive strategies for sporadic primary hyperparathyroidism. Neck radiation exposure is a known risk, which is the reason for shielding during radiographic procedures and limits on therapeutic irradiation to the neck. Genetic counseling for first-degree relatives of patients with MEN1, MEN2A, or HPT-JT.
- Prevention of secondary hyperparathyroidism: Early correction of vitamin D deficiency in at-risk populations; appropriate dietary phosphate management beginning in chronic kidney disease stages 3–4; early nephrology referral for progressive chronic kidney disease to initiate parathyroid hormone surveillance and timely treatment before advanced secondary hyperparathyroidism develops.
- Monitoring asymptomatic primary hyperparathyroidism: Annual serum calcium, creatinine/estimated glomerular filtration rate, 24-hour urine calcium; bone mineral density by dual-energy X-ray absorptiometry every 1–2 years; renal imaging (ultrasound or computed tomography) at baseline and as clinically indicated. Spine imaging for vertebral fracture assessment as part of initial and follow-up evaluation.
- Bone protection: Measures described for patients under surveillance are calcium intake of 1000–1200 mg/day (dietary sources preferred over supplements), vitamin D sufficiency (25(OH)D greater than 30 ng/mL), weight-bearing exercise, and smoking cessation.
- Genetic screening: Germline genetic testing for MEN1, CDC73, CASR, GNA11, and AP2S1 mutations is an option described for patients with primary hyperparathyroidism before age 40, multigland disease, recurrent primary hyperparathyroidism, parathyroid carcinoma, jaw tumors, or a family history of hypercalcemia or endocrine neoplasia.
11. Recent Research
- Fluorocholine positron emission tomography/computed tomography: Multiple prospective studies confirm that [¹⁸F]-choline positron emission tomography/computed tomography has superior sensitivity (85–95%) compared to sestamibi SPECT/CT for localizing parathyroid adenomas, including multigland disease and ectopic glands. Its U.S. Food and Drug Administration status could not be confirmed (see Localization Studies above), and updated guidelines now recommend it as a second-line or first-line localization study in reoperative settings.
- Normocalcemic primary hyperparathyroidism: The 2022 international workshop guidelines include updated guidance for normocalcemic primary hyperparathyroidism — a phenotype with consistently normal albumin-corrected and ionized calcium but persistently elevated parathyroid hormone after exclusion of secondary causes. Long-term observational data indicate that 20–40% of normocalcemic primary hyperparathyroidism patients develop hypercalcemia (transitioning to symptomatic primary hyperparathyroidism), and skeletal and renal complications parallel those of hypercalcemic primary hyperparathyroidism. Surgical indications for normocalcemic primary hyperparathyroidism remain under active investigation.
- Etelcalcetide outcomes in chronic kidney disease-mineral and bone disorder: A 2017 randomized trial and real-world data report etelcalcetide superiority over cinacalcet for parathyroid hormone suppression in hemodialysis patients with secondary hyperparathyroidism. Cardiovascular and mortality outcome data from long-term registries are maturing.
- Cardiovascular effects of primary hyperparathyroidism cure: Parathyroidectomy has been reported to reduce long-term cardiovascular mortality and incident hypertension rates compared to surveillance alone. The one long randomized trial, in mild disease, found similar deaths and similar cardiovascular events with surgery and with observation (see Prognosis).
- Robotics and minimally invasive endoscopy: Robot-assisted transoral endoscopic parathyroid surgery and video-assisted lateral neck approaches are being refined to further minimize cosmetic impact and operative morbidity while maintaining cure rates comparable to traditional minimally invasive parathyroidectomy.
- Novel calcimimetics and parathyroid hormone-lowering agents: Upacicalcet is a second-generation intravenous calcimimetic. Two phase 3 trials in 768 hemodialysis patients, published in 2026, found a 30% or greater parathyroid hormone reduction in 42.1% and 43.5% on upacicalcet versus 16.8% and 17.4% on placebo; low calcium readings were more frequent on the drug (below 7.5 mg/dL in 31% and 45% versus 12% and 19%). Small-molecule calcium-sensing receptor activators remain in clinical development for secondary hyperparathyroidism in chronic kidney disease. Encaleret works the other way: it is an oral calcilytic, which blocks the calcium-sensing receptor, and it is studied in autosomal dominant hypocalcemia type 1 (a low-calcium disease) and post-surgical hypoparathyroidism; no encaleret trial in familial hypocalciuric hypercalcemia was found.
- Bone microarchitecture in primary hyperparathyroidism: High-resolution peripheral quantitative computed tomography (HR-pQCT) studies demonstrate trabecular microarchitectural deterioration in primary hyperparathyroidism patients with normal dual-energy X-ray absorptiometry bone mineral density, revealing subclinical skeletal disease invisible to conventional dual-energy X-ray absorptiometry. This may refine surgical indications in the future.
Key Research Papers
- Bilezikian JP, Khan AA, Silverberg SJ, et al. Evaluation and management of primary hyperparathyroidism: summary statement and guidelines from the fifth international workshop. J Bone Miner Res. 2022;37(11):2293-2314. — doi:10.1002/jbmr.4677
- Insogna KL. Primary hyperparathyroidism. N Engl J Med. 2018;379(11):1050-1059. — doi:10.1056/NEJMcp1714213
- Silverberg SJ, Clarke BL, Peacock M, et al. Current issues in the presentation of asymptomatic primary hyperparathyroidism: proceedings of the fourth international workshop. J Clin Endocrinol Metab. 2014;99(10):3580-3594. — doi:10.1210/jc.2014-1415
- Udelsman R, Åkerström G, Biagini C, et al. The surgical management of asymptomatic primary hyperparathyroidism: proceedings of the fourth international workshop. J Clin Endocrinol Metab. 2014;99(10):3595-3606. — doi:10.1210/jc.2014-2000
- Eastell R, Brandi ML, Costa AG, et al. Diagnosis of asymptomatic primary hyperparathyroidism: proceedings of the fourth international workshop. J Clin Endocrinol Metab. 2014;99(10):3570-3579. — doi:10.1210/jc.2014-1414
- Walker MD, Silverberg SJ. Primary hyperparathyroidism. Nat Rev Endocrinol. 2018;14(2):115-125. — doi:10.1038/nrendo.2017.104
- Marcocci C, Cetani F. Clinical practice. Primary hyperparathyroidism. N Engl J Med. 2011;365(25):2389-2397. — doi:10.1056/NEJMcp1106636
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD-MBD Update Work Group. KDIGO 2017 clinical practice guideline update for the diagnosis, evaluation, prevention, and treatment of chronic kidney disease-mineral and bone disorder (CKD-MBD). Kidney Int Suppl. 2017;7(1):1-59. — doi:10.1016/j.kisu.2017.04.001
- Kuo EJ, Al-Alusi MA, Du L, et al. Surgery for primary hyperparathyroidism: adherence to consensus guidelines in an academic health system. Ann Surg. 2019;269(1):158-162. — doi:10.1097/sla.0000000000002474
- Blanchard C, Mirallié E, Mathonnet M. Sporadic primary hyperparathyroidism. J Visc Surg. 2010;147(5):e285-e295. — doi:10.1016/j.jviscsurg.2010.08.018
- Asare EA, Sturgeon C, Winchester DJ, et al. Parathyroid carcinoma: an update on treatment outcomes and prognostic factors from the National Cancer Data Base (NCDB). Ann Surg Oncol. 2015;22(12):3990-3995. — doi:10.1245/s10434-015-4672-3
- Thanseer N, Bhadada SK, Sood A, et al. Comparative effectiveness of ultrasonography, 99mTc-sestamibi, and 18F-fluorocholine PET/CT in detecting parathyroid adenomas in patients with primary hyperparathyroidism. Clin Nucl Med. 2017;42(12):e491-e497. — doi:10.1097/rlu.0000000000001845
- Zafereo M, Yu J, Angelos P, et al. American Head and Neck Society Endocrine Surgery Section update on parathyroid imaging for surgical candidates with primary hyperparathyroidism. Head Neck. 2019;41(7):2398-2409. — doi:10.1002/hed.25781
- Marcocci C, Bollerslev J, Khan AA, Shoback DM. Medical management of primary hyperparathyroidism: proceedings of the fourth international workshop on the management of asymptomatic primary hyperparathyroidism. J Clin Endocrinol Metab. 2014;99(10):3607-3618. — doi:10.1210/jc.2014-1417
- Block GA, Bushinsky DA, Cheng S, et al. Effect of etelcalcetide vs cinacalcet on serum parathyroid hormone in patients receiving hemodialysis with secondary hyperparathyroidism: a randomized clinical trial. JAMA. 2017;317(2):156-164. — doi:10.1001/jama.2016.19468
- Thakker RV, Newey PJ, Walls GV, et al. Clinical practice guidelines for multiple endocrine neoplasia type 1 (MEN1). J Clin Endocrinol Metab. 2012;97(9):2990-3011. — doi:10.1210/jc.2012-1230
- Pretorius M, Lundstam K, Heck A, et al. Mortality and morbidity in mild primary hyperparathyroidism: results from a 10-year prospective randomized controlled trial of parathyroidectomy versus observation. Ann Intern Med. 2022;175(6):812-819. — doi:10.7326/M21-4416
- Seib CD, Meng T, Suh I, et al. Risk of fracture among older adults with primary hyperparathyroidism receiving parathyroidectomy vs nonoperative management. JAMA Intern Med. 2022;182(1):10-18. — doi:10.1001/jamainternmed.2021.6437
- Seib CD, Ganesan C, Furst A, et al. Estimated effect of parathyroidectomy on long-term kidney function in adults with primary hyperparathyroidism. Ann Intern Med. 2023;176(5):624-631. — doi:10.7326/M22-2222
- Yeh MW, Ituarte PH, Zhou HC, et al. Incidence and prevalence of primary hyperparathyroidism in a racially mixed population. J Clin Endocrinol Metab. 2013;98(3):1122-1129. — doi:10.1210/jc.2012-4022
- Carneiro DM, Solorzano CC, Nader MC, Ramirez M, Irvin GL 3rd. Comparison of intraoperative iPTH assay (QPTH) criteria in guiding parathyroidectomy: which criterion is the most accurate? Surgery. 2003;134(6):973-979. — PubMed PMID: 14668730
- Kochman M. Primary hyperparathyroidism: clinical manifestations, diagnosis and evaluation according to the Fifth International Workshop guidelines. Reumatologia. 2023;61(4):256-263. — doi:10.5114/reum/170705
- Bisceglia N, Malagrino M, Cantone C, et al. Trabecular bone score as a possible new surgical recommendation in patients with asymptomatic primary hyperparathyroidism. J Endocrinol Invest. 2025;48(8):1819-1828. — doi:10.1007/s40618-025-02590-9
- Badier JR, Suthar PP, Singh JS, Jhaveri MD. Role of 18F-fluorocholine positron emission tomography (PET)/computed tomography (CT) in diagnosis of elusive parathyroid adenoma. Cureus. 2023;15(11):e48892. — doi:10.7759/cureus.48892
- Kendrick J, Ketteler M, Wolf M, et al. Efficacy and safety of upacicalcet in hemodialysis patients with secondary hyperparathyroidism: two randomized clinical trials. J Am Soc Nephrol. 2026. — doi:10.1681/ASN.0000001285
- Gafni RI, Hartley IR, Roszko KL, et al. Efficacy and safety of encaleret in autosomal dominant hypocalcemia type 1. N Engl J Med. 2023;389(13):1245-1247. — doi:10.1056/NEJMc2302708
- Del Rivero J, Gangi A, Annes JP, et al. American Association of Clinical Endocrinology consensus statement on management of multiple endocrine neoplasia type 1. Endocr Pract. 2025;31(4):403-418. — doi:10.1016/j.eprac.2025.02.001
PubMed Topic Searches
The following PubMed topic searches aggregate the current peer-reviewed literature. Each link opens a live PubMed query — results update as new studies are indexed.
- PubMed: Primary hyperparathyroidism
- PubMed: Secondary hyperparathyroidism
- PubMed: Parathyroid adenoma
- PubMed: Parathyroidectomy
- PubMed: Hypercalcemia
- PubMed: Vitamin D hyperparathyroidism
- PubMed: Bisphosphonate hypercalcemia
- PubMed: Cinacalcet calcimimetic
- PubMed: Sestamibi parathyroid scan
- PubMed: MEN1 MEN2 parathyroid
- PubMed: Chronic kidney disease parathyroid
- PubMed: Osteoporosis hyperparathyroidism
Connections
- Endocrinology
- Calcium Control: Parathyroid Hormone, Vitamin D & Your Blood Level — interactive animation
- Calcium
- Osteoporosis
- Vitamin D3
- Thyroid Disorders
- Magnesium
- Phosphorus
- Vitamin K
- Kidney Disease
- Estimated Glomerular Filtration Rate
- Creatinine
- Hypertension
- Pancreatitis
- Depression
- Pheochromocytoma
- Sarcoidosis
- Bisphosphonates
- Addison's Disease
- Primary Hyperparathyroidism — the autonomous adenoma-driven form: parathyroid hormone-calcium diagnostics, surveillance criteria, and parathyroidectomy.
- Cushing's Syndrome