Clostridioides difficile Infection
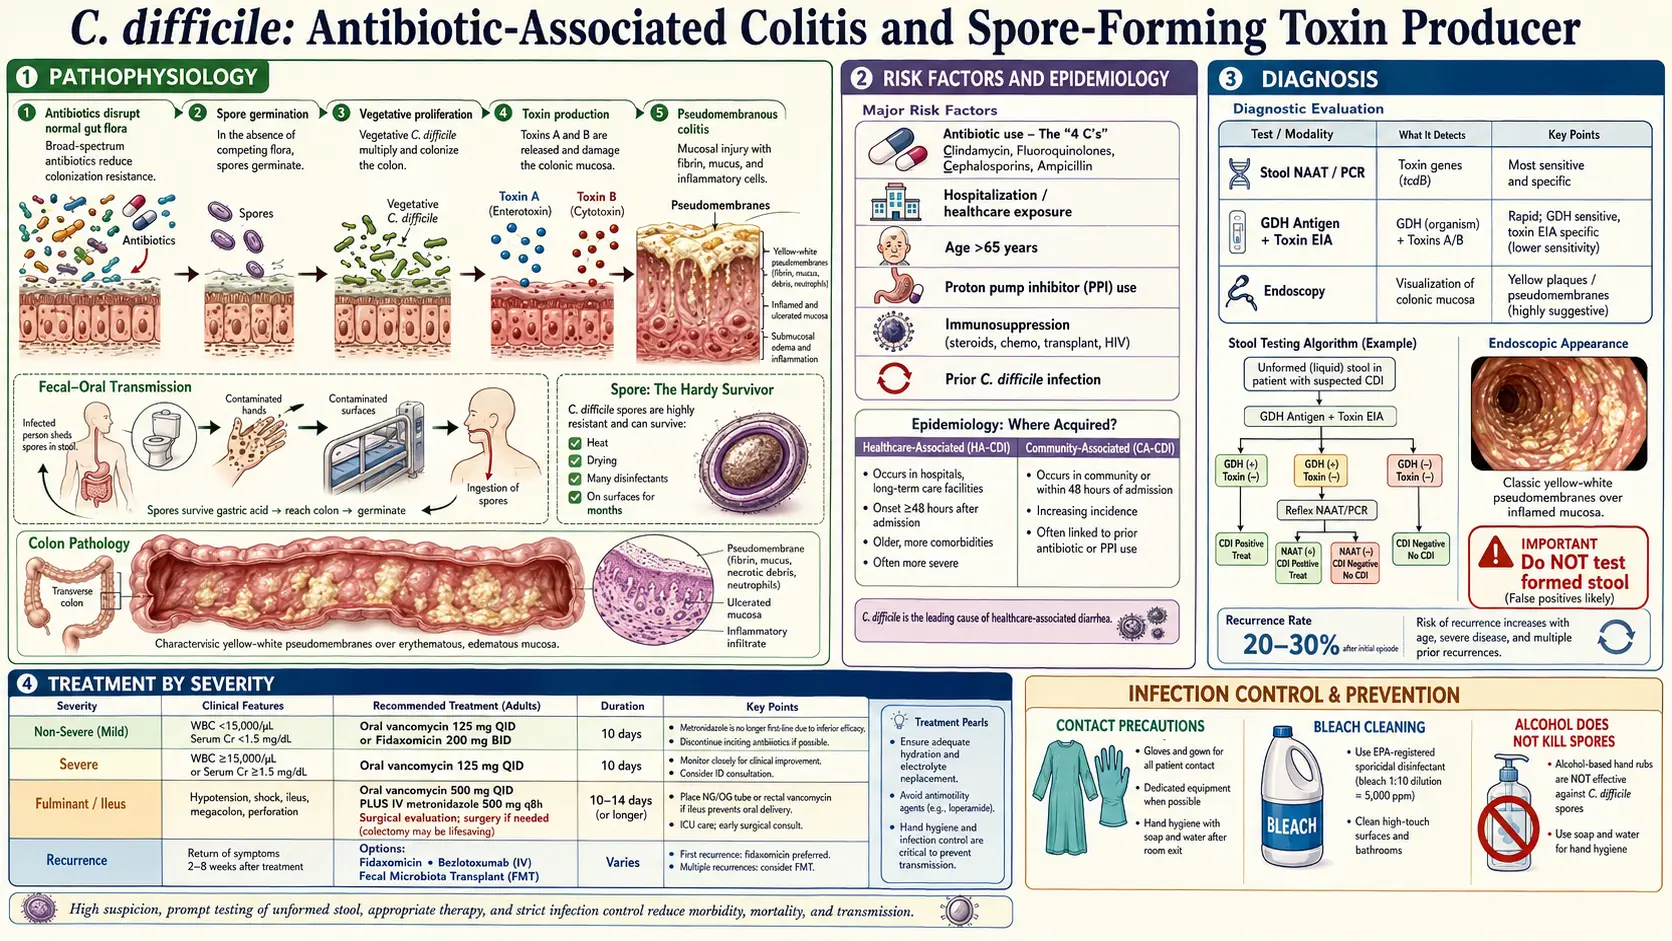
Clostridioides difficile infection (CDI) — formerly classified as Clostridium difficile — is the leading cause of healthcare-associated infectious diarrhea in developed nations and an increasingly prevalent community-acquired pathogen. It represents a major global public health challenge, with approximately 500,000 cases annually in the United States alone, and is associated with substantial morbidity, mortality, and healthcare expenditure.
Table of Contents
1. Overview
Clostridioides difficile is an obligate anaerobic, spore-forming, gram-positive bacillus that colonizes the human colon and produces potent exotoxins responsible for the clinical syndrome of Clostridioides difficile infection. The organism was first isolated in 1935 by Hall and O'Toole, who noted it as a commensal in neonatal gut flora and designated it "difficile" for the difficulty encountered in its cultivation. Its pathogenic significance was not fully appreciated until 1978, when it was identified as the causative agent of antibiotic-associated pseudomembranous colitis.
Clostridioides difficile infection occurs when disruption of the normal gut microbiota — most commonly by antibiotic use — allows colonization by toxigenic C. difficile strains, with subsequent toxin production causing mucosal damage and the characteristic clinical syndrome. The spectrum of disease ranges from mild self-limited diarrhea to fulminant colitis with systemic inflammatory response, toxic megacolon, and death.
Nomenclature: The organism was reclassified from Clostridium difficile to Clostridioides difficile in 2016 based on phylogenetic analysis, though the abbreviation CDI and the colloquial term "C. diff" remain in widespread clinical use.
2. Epidemiology
Clostridioides difficile infection is the most common healthcare-associated infection in US hospitals, surpassing methicillin-resistant Staphylococcus aureus (MRSA) in incidence. A Centers for Disease Control and Prevention (CDC) surveillance study (Lessa 2015) estimated about 453,000 infections in the United States in 2011 and about 29,300 deaths within 30 days of diagnosis (deaths associated with the infection, not all of them caused by it). Direct healthcare costs exceed $6 billion per year.
The epidemiology of Clostridioides difficile infection has undergone a significant transformation since the early 2000s, driven by the emergence of the hypervirulent NAP1/BI/ribotype 027 strain (C. difficile ribotype 027, CDT-027). This strain is characterized by:
- Production of binary toxin (CDT) in addition to toxins A and B
- Deletion in the tcdC gene (negative regulator of toxin production), resulting in markedly elevated toxin output
- A variant form of toxin B with altered receptor binding
- High-level fluoroquinolone resistance (mutations in gyrA and gyrB)
- Increased sporulation efficiency, facilitating environmental persistence and transmission
- Higher rates of severe disease, complications, and mortality compared to non-027 strains
The NAP1/ribotype 027 strain has spread internationally and caused major nosocomial outbreaks in North America and Europe. However, its dominance has waned in some regions, with ribotype 078 and 244 emerging as significant strains, particularly in community-acquired Clostridioides difficile infection.
A later CDC study from the same 10 U.S. surveillance sites (Guh 2020) estimated 476,400 cases nationally in 2011 and 462,100 in 2017. After adjusting for the more sensitive DNA-based tests (nucleic acid amplification tests, NAATs) now widely used, the total number of cases fell by 24% from 2011 to 2017 and healthcare-associated cases fell by 36%, while community-associated cases did not change. Hospitalizations for the infection fell by 24%; first recurrences and in-hospital deaths did not change significantly.
Community-acquired CDI (CA-CDI) — defined as Clostridioides difficile infection occurring in outpatients or within 48 hours of admission with no hospitalization in the preceding 12 weeks — now accounts for approximately 30–40% of all Clostridioides difficile infection cases. CA-CDI patients tend to be younger, have fewer comorbidities, and demonstrate lower rates of recurrence, though the overall incidence is rising.
Clostridioides difficile infection predominantly affects older adults; persons aged ≥65 years account for more than 80% of Clostridioides difficile infection-related deaths. Institutional settings (hospitals, long-term care facilities) remain the highest-risk environments due to high antibiotic use, immunocompromised populations, and environmental contamination with spores.
3. Pathophysiology
Organism Biology and Spore Formation
The pathogenicity of C. difficile is critically dependent on its ability to form highly resistant endospores. Spores are metabolically dormant, resistant to standard disinfectants (including alcohol-based hand gels), heat, and desiccation, and can survive on environmental surfaces for months to years. Spores are ingested via the fecal-oral route, transit the acidic stomach environment unharmed, and germinate in the small intestine under the influence of bile acids — specifically, primary bile acids (taurocholate) trigger germination while secondary bile acids (deoxycholate, lithocholate produced by normal gut flora) inhibit it. This bile acid ecology partly explains why antibiotic-induced reduction of secondary bile acid-producing flora facilitates Clostridioides difficile infection.
Microbiome Disruption and Colonization Resistance
The healthy adult gut microbiota provides robust colonization resistance against C. difficile through multiple mechanisms: competition for nutrients and mucosal binding sites, production of short-chain fatty acids (SCFAs) and secondary bile acids that inhibit C. difficile growth, stimulation of mucosal immunoglobulin A (IgA) secretion, and direct bacteriocin production. Antibiotic disruption — particularly broad-spectrum agents — depletes this protective consortium, allowing C. difficile spores (acquired from the environment or endogenous reservoir) to germinate and proliferate to pathogenic densities.
Toxin A and Toxin B
The cardinal virulence determinants of pathogenic C. difficile strains are two large clostridial toxins encoded on the pathogenicity locus (PaLoc): a 19.6-kb chromosomal element containing tcdA (toxin A), tcdB (toxin B), and three regulatory genes (tcdC, tcdE, tcdR).
Toxin A (TcdA) is a 308-kDa glucosyltransferase enterotoxin. It binds to cell surface receptors (including the carbohydrate moiety on Gal-alpha-1-3-Gal-beta-1-4-GlcNAc), is internalized by endocytosis, and translocates its glucosyltransferase domain into the cytoplasm, where it mono-O-glucosylates and thereby inactivates Rho-family GTPases (RhoA, Rac1, Cdc42). Rho GTPase inactivation disrupts the actin cytoskeleton, breaks tight junctions, increases intestinal permeability, and triggers apoptosis. Toxin A also activates macrophages and mast cells to release proinflammatory cytokines (tumor necrosis factor-alpha, interleukin-1, interleukin-6, IL-8) and stimulates substance P release from enteric neurons, amplifying the inflammatory response and causing fluid hypersecretion.
Toxin B (TcdB) is a 270-kDa cytotoxin, approximately 1,000-fold more potent than Toxin A on a molar basis in cell culture assays. It employs a similar glucosyltransferase mechanism targeting Rho GTPases but uses different cell surface receptors: PVRL3 (nectin-3), FZD1, FZD2, and FZD7 (Frizzled receptors). TcdB is now regarded as the primary virulence factor, as strains producing only TcdB (TcdA-/TcdB+) retain full virulence in humans while TcdA+/TcdB- strains cause minimal disease.
The net effect of toxin A and B activity on colonocytes includes: loss of epithelial barrier integrity, inflammatory infiltration (predominantly neutrophilic) of the lamina propria, submucosal edema, vascular congestion, mucosal ulceration, and the formation of pseudomembranes — raised yellow-white plaques composed of fibrin, mucin, neutrophils, and cellular debris that are pathognomonic of pseudomembranous colitis.
Binary Toxin (CDT)
Approximately 6–10% of clinical C. difficile strains (including ribotype 027 and 078) produce a third toxin, binary toxin CDT, encoded outside the PaLoc on a separate chromosomal element (cdt locus). CDT is an ADP-ribosyltransferase toxin (related to C. perfringens iota toxin) consisting of two components: CDTa (enzymatic) and CDTb (binding/translocation). It ADP-ribosylates G-actin, disrupting actin polymerization and causing unique protrusions (microtubule-based tentacle-like extensions) on the cell surface that dramatically enhance C. difficile adherence. CDT is associated with increased virulence and mortality in epidemiological studies, though its precise contribution to disease relative to TcdA and TcdB is under ongoing investigation.
Host Immune Response
Serum immunoglobulin G (IgG) antibody titers against toxins A and B are strongly protective against Clostridioides difficile infection severity and recurrence. Infants commonly carry C. difficile as asymptomatic colonizers in part due to absence of toxin receptors and high levels of maternally transferred immunoglobulin G. Adults with high anti-toxin A immunoglobulin G levels are significantly less likely to experience recurrent Clostridioides difficile infection after initial treatment, a finding that motivated the development of monoclonal antibody therapy (bezlotoxumab).
4. Etiology and Risk Factors
Antibiotic Exposure
Antibiotic use is the single most important modifiable risk factor for Clostridioides difficile infection. Any antibiotic can predispose to Clostridioides difficile infection, but the highest-risk agents include:
- Fluoroquinolones (ciprofloxacin, levofloxacin, moxifloxacin): Particularly implicated in the emergence and spread of hypervirulent ribotype 027. The fluoroquinolone resistance of NAP1 provides a selective survival advantage during fluoroquinolone therapy.
- Clindamycin: Historically the most strongly associated antibiotic; classic teaching mnemonic for Clostridioides difficile infection risk.
- Broad-spectrum cephalosporins (ceftriaxone, cefotaxime, cefepime): Major disruptors of anaerobic gut flora.
- Broad-spectrum penicillins with/without beta-lactamase inhibitors (amoxicillin-clavulanate, piperacillin-tazobactam): High-risk due to broad anaerobic coverage.
- Carbapenems: Among the most disruptive of anaerobic colonization resistance.
Risk is proportional to the number of antibiotic courses, duration of therapy, and spectrum of activity. Clostridioides difficile infection can occur during antibiotic therapy or up to 8–12 weeks after discontinuation. The 4-week period following antibiotic cessation carries the highest risk.
Patient-Related Risk Factors
- Advanced age (≥65 years): Impaired immune response (reduced immunoglobulin G production against C. difficile toxins), altered gut flora diversity, high rates of antibiotic use and hospitalization.
- Hospitalization and healthcare exposure: Environmental contamination with spores, density of colonized/infected patients, shared equipment. Duration of hospitalization correlates directly with Clostridioides difficile infection risk.
- Proton pump inhibitors (PPIs): proton pump inhibitors reduce gastric acid, potentially allowing more spores to survive transit to the colon. Multiple meta-analyses demonstrate a 1.5–3-fold increased Clostridioides difficile infection risk with proton pump inhibitor (PPI) use, though causality remains debated given confounding by indication.
- Inflammatory bowel disease (IBD): Patients with inflammatory bowel disease have a 3–5 fold increased Clostridioides difficile infection risk. Clostridioides difficile infection in the setting of inflammatory bowel disease carries substantially higher rates of colectomy, complications, and mortality. Clostridioides difficile infection can mimic or trigger inflammatory bowel disease flares, complicating diagnosis.
- Immunosuppression: Solid organ and hematopoietic stem cell transplant recipients, patients on systemic corticosteroids or immunomodulatory agents, and those receiving cancer chemotherapy have heightened susceptibility and often atypical presentations.
- Renal failure: Chronic kidney disease is an independent risk factor, possibly through altered bile acid metabolism and immune dysregulation.
- Prior Clostridioides difficile infection: The strongest predictor of recurrent Clostridioides difficile infection; risk increases with each subsequent episode (25% after first, 50% after second, >60% with three or more episodes).
- Nasogastric tube use, gastrointestinal surgery: Disrupt gastrointestinal (GI) physiology and promote spore ingestion.
- Malnutrition and low serum albumin: Markers of impaired immunity and associated with more severe disease.
5. Clinical Presentation
Spectrum of Disease
Clinical manifestations of Clostridioides difficile infection span a broad spectrum from asymptomatic colonization to life-threatening fulminant colitis:
Mild to Moderate Clostridioides Difficile Infection
- Diarrhea: The hallmark symptom — typically watery, foul-smelling, 3 or more loose/unformed stools per 24-hour period. Stools may contain mucus but frank blood is uncommon in uncomplicated Clostridioides difficile infection (visible blood in the stool points toward other diagnoses).
- Abdominal cramping: Lower abdominal cramping and bloating, often preceding or accompanying diarrhea.
- Low-grade fever: Present in approximately 30–40% of cases.
- Constitutional symptoms: Mild nausea, anorexia, and malaise are common.
- Leukocytosis: WBC of 10,000–20,000 cells/mm³ is typical; a disproportionate leukocytosis (>20,000–30,000 cells/mm³) without other explanation is a warning sign of severe or complicated Clostridioides difficile infection.
Severe Clostridioides Difficile Infection
The IDSA/SHEA 2017 Clinical Practice Guidelines define severe Clostridioides difficile infection by either of the following criteria:
- Serum creatinine ≥1.5 mg/dL (new elevation or worsening from baseline)
- WBC ≥15,000 cells/mm³
Additional features suggesting severity include: serum albumin <3.0 g/dL, age >65 years, temperature >38.5°C, intensive care unit admission, and immunocompromised state. Severe Clostridioides difficile infection carries substantially higher rates of complications and 30-day mortality.
Fulminant Clostridioides Difficile Infection
Defined by the IDSA/SHEA guidelines as Clostridioides difficile infection with any of the following: hypotension or shock, ileus, or toxic megacolon. Formerly designated "severe complicated Clostridioides difficile infection," fulminant Clostridioides difficile infection represents the most life-threatening presentation:
- Ileus: Colonic dysmotility may paradoxically reduce or eliminate diarrhea despite severe underlying disease; absence of diarrhea does not exclude Clostridioides difficile infection in the appropriate clinical context.
- Toxic megacolon: Colonic dilatation (>6 cm on plain radiograph, or >9 cm for cecum) with systemic toxicity (fever, tachycardia, leukocytosis, hypovolemia). Risk of perforation and death is high without urgent intervention.
- Septic shock: Refractory hypotension despite adequate resuscitation, multi-organ dysfunction.
- Markedly elevated WBC: Often >30,000–50,000 cells/mm³; extreme leukemoid reaction (>50,000 cells/mm³) has been reported with ribotype 027 strains.
Recurrent Clostridioides Difficile Infection
Recurrent Clostridioides difficile infection (rCDI) is defined as recurrence of symptoms within 8 weeks of completing treatment for a prior episode with documented microbiological cure (negative test). It is essential to distinguish recurrence (re-infection with the same or different strain, or relapse from persistent spores) from treatment failure (persistent symptoms without symptomatic resolution). First recurrence occurs in approximately 20–25% of patients; subsequent recurrences become progressively more frequent, creating a vicious cycle of dysbiosis and re-infection.
6. Diagnosis
Accurate diagnosis of Clostridioides difficile infection requires both clinical assessment and laboratory confirmation. The IDSA/SHEA guidelines limit testing to patients with clinically significant diarrhea (≥3 unformed stools in 24 hours) who have no other identifiable cause. They strongly discourage testing people without symptoms or formed stool specimens, because it leads to overdiagnosis and unnecessary treatment of colonized individuals.
Laboratory Testing
The optimal diagnostic strategy is an area of ongoing debate and institutional variation. The key assays are:
- Nucleic acid amplification test (NAAT) / PCR: Detects tcdB (and other PaLoc genes) with sensitivity >95% and specificity >97%. Highly sensitive but cannot distinguish active infection from asymptomatic colonization in patients with positive toxin-encoding genes but absent toxin production. The high sensitivity of polymerase chain reaction (PCR) contributes to overdiagnosis and overtreatment when used as a standalone test.
- Enzyme immunoassay (EIA) for glutamate dehydrogenase (GDH): GDH is a metabolic enzyme produced by all C. difficile strains (toxigenic and non-toxigenic). High sensitivity (~90%) but low specificity; used as a screening test in multistep algorithms. A negative GDH reliably excludes Clostridioides difficile infection.
- Enzyme immunoassay for toxins A and B (EIA): Direct detection of free toxin in stool, with specificity ~95–98% but limited sensitivity (~75–85%). Positive toxin EIA in the appropriate clinical context has high positive predictive value. Importantly, a positive toxin EIA correlates better with clinically significant disease than polymerase chain reaction alone.
- Cell cytotoxicity neutralization assay (CCNA): The historical gold standard — detects the cytopathic effect of toxin B on cell monolayers, neutralized by antitoxin serum. Sensitivity ~90%, specificity ~98–99%, but requires 24–48 hours and specialized laboratory infrastructure. Largely replaced by NAAT in clinical practice.
- Toxigenic culture: Anaerobic culture of stool followed by toxin testing of isolated colonies. The absolute gold standard for sensitivity but requires 5–7 days; primarily a research and epidemiological tool.
The IDSA/SHEA 2017 guidelines endorse either of two preferred diagnostic approaches:
- Multistep algorithm: GDH EIA + toxin EIA as initial screen; discordant results reflexed to NAAT. This approach maximizes specificity and avoids overdiagnosis.
- NAAT alone (or NAAT + toxin EIA): Acceptable if only patients meeting strict clinical criteria for testing are tested. NAAT alone as a population-wide screening test is discouraged.
Endoscopy
Colonoscopy or flexible sigmoidoscopy is not routinely required for Clostridioides difficile infection diagnosis but may be necessary in select circumstances:
- Clinical suspicion is high but stool tests are repeatedly negative (ileus preventing diarrhea)
- Urgent diagnosis required when tests cannot be completed rapidly
- Evaluation for alternative diagnoses (inflammatory bowel disease, ischemic colitis, cytomegalovirus (CMV) colitis)
Pseudomembranes — raised, confluent, yellow-white plaques 2–10 mm in diameter overlying hyperemic and edematous mucosa — are pathognomonic for pseudomembranous colitis on endoscopy. They are present in approximately 50% of Clostridioides difficile infection cases; their absence does not exclude Clostridioides difficile infection. Biopsies demonstrate the characteristic "summit" or "volcanic" lesion on histology.
Imaging
Computed tomography (CT) of the abdomen and pelvis with intravenous contrast is the preferred imaging modality for suspected complicated Clostridioides difficile infection. Characteristic findings include:
- Pancolonic or segmental colonic wall thickening (>4 mm)
- "Accordion sign" — alternating bands of oral contrast trapped between thickened folds on computed tomography
- Pericolonic fat stranding
- Ascites (in severe cases)
- Colonic dilatation (>6 cm) suggesting toxic megacolon
- Free air indicating perforation
7. Treatment
General Principles
Stopping the antibiotic(s) that triggered the infection, when that is clinically possible, by itself resolves the diarrhea in approximately 15–23% of Clostridioides difficile infection patients. Fluid and electrolyte replacement is critical, particularly in elderly patients. Antiperistaltic agents (loperamide, opioids) are contraindicated in Clostridioides difficile infection as they can precipitate toxic megacolon. Hospitals place patients with the infection on contact precautions (see Prevention).
Antibiotic Treatment — IDSA/SHEA 2017 Guidelines and 2021 Focused Update
Two generations of U.S. guidelines from the Infectious Diseases Society of America (IDSA) and the Society for Healthcare Epidemiology of America (SHEA) cover treatment, and they differ on which antibiotic comes first:
- 2017 guidelines (McDonald et al.): either vancomycin or fidaxomicin for a first episode, non-severe or severe (but not fulminant), with either drug preferred over metronidazole — a strong recommendation.
- 2021 focused update (Johnson et al.): for a first episode, fidaxomicin is suggested rather than a standard course of vancomycin (conditional recommendation, moderate certainty of evidence), because more trial data confirmed fewer recurrences with fidaxomicin; vancomycin remains an acceptable alternative. For recurrent episodes, fidaxomicin (standard or extended-pulsed regimen) is suggested rather than a standard vancomycin course (conditional recommendation, low certainty evidence). It also added bezlotoxumab for patients with a recurrence within the last 6 months (conditional recommendation, very low certainty of evidence) — a drug withdrawn from the market in January 2025 (see below).
A "conditional" recommendation in this system means most patients in that situation would want the suggested option but many would not; a "strong" one means nearly all would. The regimens by episode type:
- Non-severe Clostridioides difficile infection (initial episode): Fidaxomicin 200 mg orally twice daily for 10 days is suggested over vancomycin in the 2021 focused update (conditional recommendation, moderate certainty of evidence) due to lower recurrence rates (approximately 15% vs. 25–27% with vancomycin). Vancomycin 125 mg orally four times daily for 10 days remains an acceptable alternative (2017: strong recommendation, high quality evidence). Metronidazole 500 mg orally three times daily for 10 days is now considered an alternative only when fidaxomicin and vancomycin are unavailable (weak recommendation), reflecting inferior efficacy in recent trials.
- Severe Clostridioides difficile infection (initial episode): Vancomycin 125 mg orally four times daily for 10 days (strong recommendation, high quality evidence). Fidaxomicin 200 mg orally twice daily for 10 days is an equally acceptable alternative (strong recommendation, moderate quality evidence). Metronidazole is not recommended for severe Clostridioides difficile infection.
- Fulminant Clostridioides difficile infection: Vancomycin 500 mg orally or via nasogastric tube four times daily, plus metronidazole 500 mg intravenously every 8 hours (strong recommendation, moderate quality evidence). In the setting of ileus or colonic dilatation, vancomycin enemas (500 mg in 100 mL saline every 6 hours via retention enema) are added in the guideline to reach adequate drug levels in the colon. The guideline calls for early surgical consultation for patients with fulminant Clostridioides difficile infection.
Fidaxomicin
Fidaxomicin is a macrocyclic antibiotic with a narrow spectrum of activity highly specific for C. difficile. Its key pharmacological advantages over vancomycin include: minimal systemic absorption (99.5% of the dose remains in the colonic lumen), negligible impact on the intestinal microbiota beyond C. difficile, and bactericidal activity that persists after the dosing interval (post-antibiotic effect). Two pivotal phase III randomized controlled trials (OPCDT-3 and OPCDT-4) demonstrated clinical cure rates equivalent to vancomycin but significantly lower recurrence rates, particularly for non-NAP1 strains. For NAP1/ribotype 027 strains, fidaxomicin's recurrence advantage is attenuated but not eliminated. The primary limitation of fidaxomicin is cost.
Recurrent Clostridioides Difficile Infection
- First recurrence: The 2017 guideline lists a standard vancomycin course when metronidazole was used for the initial episode. When a standard vancomycin course was used, it lists fidaxomicin or a vancomycin tapered/pulsed regimen (e.g., 125 mg four times daily for 10–14 days, then twice daily for 7 days, then once daily for 7 days, then every 2–3 days for 2–8 weeks) (IDSA 2017 weak recommendation, low quality evidence). The 2021 focused update suggests fidaxomicin (standard or extended-pulsed) rather than standard vancomycin for recurrences, with tapered and pulsed vancomycin or a standard vancomycin course as acceptable alternatives for a first recurrence.
- Second or subsequent recurrences: Vancomycin tapered/pulsed regimen OR vancomycin followed by rifaximin 400 mg three times daily for 20 days (weak recommendation). The 2017 guideline recommends fecal microbiota transplantation (FMT) for patients with multiple recurrences who have failed appropriate antibiotic treatment (strong recommendation, moderate quality evidence), citing cure rates exceeding 85–90%.
Bezlotoxumab (Withdrawn in 2025)
Bezlotoxumab is a fully human IgG1 monoclonal antibody targeting C. difficile toxin B, approved by the U.S. Food and Drug Administration (FDA) in 2016 as an adjunct to standard antibiotic therapy to reduce Clostridioides difficile infection recurrence in high-risk adult patients. It was withdrawn from the market by its sole supplier on January 31, 2025 (Arya 2025), so it is no longer a current treatment option. In the pivotal MODIFY I and MODIFY II trials (2,655 adults in total), bezlotoxumab (10 mg/kg intravenous (IV) single dose) given with antibiotics lowered the 12-week recurrence rate from 28% with placebo to 17% in MODIFY I, and from 26% to 16% in MODIFY II — a relative risk reduction of approximately 40%. Benefit was concentrated in high-risk subgroups: age ≥65 years, immunocompromised status, severe Clostridioides difficile infection, and Clostridioides difficile infection due to ribotype 027 strains.
Bezlotoxumab acts by direct high-affinity neutralization of toxin B, preventing toxin B-mediated mucosal damage and dampening the inflammatory cascade that perpetuates dysbiosis. Actoxumab (anti-toxin A monoclonal) did not add benefit when combined with bezlotoxumab. A caution note: bezlotoxumab was associated with a higher rate of heart failure exacerbations in patients with underlying cardiac disease in the MODIFY trials (heart failure AE: 12.7% bezlotoxumab vs. 4.8% placebo). The FDA warning, quoted in the 2021 guideline, reads: "in patients with a history of congestive heart failure (CHF), bezlotoxumab should be reserved for use when the benefit outweighs the risk."
After the withdrawal, a 2025 commentary (Arya et al.) described the two other ways now used to prevent recurrence: oral vancomycin prophylaxis and fecal microbiota-based therapies. In a systematic review it cites (11 retrospective studies and 1 randomized trial, with considerable differences between studies), oral vancomycin prophylaxis was linked to fewer recurrences than no prophylaxis (6.4% vs. 19.2%), with the greatest benefit in patients who had an infection within 90 days of the hospital admission. The authors note that routine prophylaxis has not been established as standard of care because the evidence is limited, and that long or repeated oral vancomycin may further disturb the gut bacteria.
Fecal Microbiota Transplantation (FMT)
FMT involves transfer of processed stool from a healthy screened donor into the gastrointestinal tract of the recipient, with the goal of restoring a diverse and protective microbiome. It is the most effective treatment for recurrent Clostridioides difficile infection, with clinical cure rates of 85–92% in randomized controlled trials and up to 90–95% in large case series, far exceeding antibiotic therapy alone. FMT is recommended by IDSA/SHEA for patients with ≥2 recurrences of Clostridioides difficile infection (three or more Clostridioides difficile infection episodes total).
Delivery routes include: colonoscopy (most widely used in the US, allows direct visualization of mucosa), nasojejunal tube or enema (for patients unable to tolerate colonoscopy), and upper gastrointestinal routes (nasoduodenal or esophagogastroduodenoscopy via pylorus). Capsulized frozen FMT preparations have demonstrated non-inferiority to colonoscopic delivery in randomized trials, substantially simplifying administration.
Donor screening protocols are rigorous (stool culture, ova and parasites, C. difficile testing, and serological testing for bloodborne pathogens) to minimize transmission risk. In 2019, two immunocompromised FMT recipients in two separate clinical trials developed bloodstream infection with extended-spectrum beta-lactamase (ESBL)-producing E. coli traced by genome sequencing to the same inadequately screened donor, and one of them died (DeFilipp 2019), prompting U.S. Food and Drug Administration to strengthen donor screening requirements, including expanded multi-drug-resistant organism testing and updated exclusion criteria for recent gastrointestinal symptoms.
The U.S. Food and Drug Administration approved the first standardized FMT product, fecal microbiota, live-jslm (RBX2660), in November 2022 for prevention of Clostridioides difficile infection recurrence following antibiotic treatment in adults ≥18 years, followed by fecal microbiota spores, live-brpk (SER-109) — the first oral FMT capsule product — approved in April 2023. These regulatory approvals mark a pivotal transition from investigational to standardized microbiome-based therapeutics.
Surgical Management
Surgery is reserved for fulminant Clostridioides difficile infection refractory to medical management, or with complications (perforation, toxic megacolon failing medical therapy). Subtotal colectomy with end ileostomy has traditionally been the procedure of choice and carries 30-day mortality of 35–80% when performed for fulminant Clostridioides difficile infection in extremis. Loop ileostomy with colonic lavage (Neal procedure) is a less morbid alternative that preserves the colon: an ileostomy is created, the colon is lavaged with polyethylene glycol via the ileostomy, and anterograde vancomycin flushes are administered through the ileostomy postoperatively. A study at one university hospital system (Neal 2011) treated 42 patients this way and found lower mortality than in an equal number of earlier patients treated there with colectomy (19% vs. 50%); it compared against these historical patients and was not a randomized trial, and patient selection criteria for this approach remain an area of ongoing refinement.
Early surgical consultation — ideally when serum lactate >5 mmol/L, WBC >50,000/mm³, or clinical deterioration is evident — is associated with improved outcomes. Delay in surgical referral until hemodynamic collapse significantly worsens prognosis.
8. Complications
Toxic Megacolon
Transmural colonic inflammation leads to functional obstruction, massive dilatation (>6 cm), and systemic toxicity. Plain abdominal radiograph demonstrates markedly dilated, often featureless colon. Management includes bowel rest, nasogastric decompression, urgent colonoscopic decompression (with extreme caution given perforation risk), maximal medical Clostridioides difficile infection therapy, and urgent surgical consultation. Perforation risk with toxic megacolon is approximately 20–30%, carrying mortality up to 60%.
Colonic Perforation
Transmural necrosis or toxic megacolon can lead to free perforation with fecal peritonitis, septic shock, and death. Requires emergency laparotomy. In-hospital mortality exceeds 50% in most case series.
Dehydration, Electrolyte Imbalance, and Acute Kidney Injury
Profuse diarrhea leads to hypovolemia, hyponatremia, hypokalemia, and prerenal or intrinsic acute kidney injury (AKI). Acute kidney injury is both a criterion for severe Clostridioides difficile infection and an independent predictor of mortality. Aggressive intravenous fluid resuscitation and electrolyte repletion are essential, while avoiding nephrotoxic agents.
Reactive Arthritis
A rare post-infectious complication (<1% of Clostridioides difficile infection cases) characterized by asymmetric oligoarthritis involving large joints, typically occurring 2–6 weeks after Clostridioides difficile infection. It is thought to be immune-mediated rather than a direct joint infection. Usually self-limited but may require nonsteroidal anti-inflammatory drugs (NSAIDs) or short-course corticosteroids.
Recurrent Clostridioides Difficile Infection
Recurrence is the most clinically significant complication of Clostridioides difficile infection. Each recurrent episode further disrupts the gut microbiome, perpetuating a cycle of dysbiosis and susceptibility. Recurrent Clostridioides difficile infection is associated with progressive decline in quality of life, healthcare utilization, functional status, and mortality, particularly in elderly patients.
Clostridioides Difficile Infection in Special Populations
Inflammatory bowel disease patients with Clostridioides difficile infection have threefold higher rates of colectomy and fivefold higher in-hospital mortality compared to Clostridioides difficile infection patients without inflammatory bowel disease. Telling Clostridioides difficile infection apart from an inflammatory bowel disease flare matters, and inflammatory bowel disease patients presenting with a disease flare are tested for concurrent Clostridioides difficile infection.
Immunocompromised patients (transplant recipients, human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), chemotherapy) may present with atypical features, prolonged course, and reduced inflammatory markers despite severe disease. A high index of suspicion is warranted.
Pregnancy: Clostridioides difficile infection during pregnancy is rare but associated with adverse maternal and fetal outcomes. Oral vancomycin (minimally absorbed) is preferred; metronidazole is avoided in the first trimester due to teratogenicity concerns, though data are limited.
9. Prognosis
Prognosis in Clostridioides difficile infection is highly variable and depends on disease severity, patient characteristics, and adequacy of treatment:
- Mortality: Overall 30-day all-cause mortality attributable to Clostridioides difficile infection is approximately 5–10% in hospitalized patients. In fulminant Clostridioides difficile infection requiring surgery, 30-day mortality ranges from 35–80%. Mortality in elderly intensive care unit (ICU) patients with severe Clostridioides difficile infection may exceed 30%.
- Recurrence: First recurrence rate is 20–25%, rising to 40–65% with two or more prior episodes. Recurrence is not predicted by antibiotic choice in most studies but by host factors: advanced age, ongoing antibiotic use, immunosuppression, and prior Clostridioides difficile infection episodes.
- Long-term sequelae: Survivors of severe Clostridioides difficile infection may have persistent gut dysbiosis, increased susceptibility to other infections, reduced quality of life, irritable bowel syndrome-like symptoms, and functional decline.
Validated severity scoring tools include the ATLAS score (age, treatment with systemic antibiotics, leukocyte count, albumin, and serum creatinine) and the IDSA/SHEA severity classification. The PSEP (Predictors of Severe and Severe Complicated Clostridioides difficile infection) model incorporates admission WBC, serum creatinine, albumin, age, and intensive care unit status. These tools aid in stratifying patients who require closer monitoring and escalated therapy.
10. Prevention
Antibiotic Stewardship
Antibiotic stewardship programs (ASPs) are the most effective institutional intervention for reducing Clostridioides difficile infection incidence. Core ASP strategies include: restriction of high-risk antibiotics (fluoroquinolones, clindamycin, broad-spectrum cephalosporins and carbapenems) without appropriate indications; de-escalation to narrower-spectrum agents when culture and sensitivity data are available; shortened antibiotic courses; and minimizing prophylactic antibiotic use. Robust evidence supports that ASP implementation reduces Clostridioides difficile infection rates by 20–50% in hospital settings.
Infection Control and Environmental Decontamination
C. difficile spores are resistant to standard alcohol-based hand sanitizers and quaternary ammonium-based disinfectants. Key infection control measures include:
- Contact precautions: Gown and gloves for all contacts with Clostridioides difficile infection patients; private room or cohorting of Clostridioides difficile infection patients.
- Hand hygiene with soap and water: Mechanical removal of spores by friction; alcohol hand gel alone is inadequate for Clostridioides difficile infection prevention. Infection-control practice requires handwashing with soap and water after contact with Clostridioides difficile infection patients or their environment.
- Sodium hypochlorite (bleach) disinfection: Sporicidal agents such as 1:10 dilution bleach solution or commercially available hypochlorite-based products are required for environmental decontamination of rooms occupied by Clostridioides difficile infection patients. Standard quaternary ammonium compounds are not sporicidal and are inadequate.
- Enhanced terminal cleaning: Thorough terminal cleaning of rooms after Clostridioides difficile infection patient discharge, including high-touch surfaces (bed rails, call buttons, infusion pumps), using sporicidal agents.
- Duration of precautions: SHEA guidelines recommend maintaining contact precautions for at least 48 hours after diarrhea resolution; some institutions extend precautions for the duration of hospitalization given environmental spore persistence.
- Ultraviolet-C light disinfection: Pulsed xenon ultraviolet-C technology is increasingly used as an adjunct to manual cleaning; shown to reduce environmental C. difficile contamination when implemented alongside standard precautions.
Prophylactic Measures
- Probiotics: Meta-analyses suggest Lactobacillus and Saccharomyces boulardii-containing preparations may reduce Clostridioides difficile infection incidence when administered concurrently with antibiotics, but evidence quality is moderate and recommendations are not universal. The PLACIDE trial (a large UK RCT) did not demonstrate benefit in elderly patients. Routine probiotic prophylaxis is not currently recommended by IDSA/SHEA.
- Vancomycin prophylaxis: Oral vancomycin 125 mg twice daily during and for 5 days after subsequent antibiotic courses is increasingly used in patients with multiple prior Clostridioides difficile infection episodes, based on observational data and small randomized controlled trials (RCTs) demonstrating reduced recurrence rates. This practice is gaining acceptance in expert guidelines though formal recommendation strength remains moderate.
- Proton pump inhibitor deprescribing: Reviewing and discontinuing unnecessary proton pump inhibitors in hospitalized patients reduces Clostridioides difficile infection risk and is a component of antimicrobial stewardship bundles.
11. Recent Research
- U.S. Food and Drug Administration-approved microbiome therapeutics: The approval of fecal microbiota, live-jslm (RBX2660) in 2022 and fecal microbiota spores, live-brpk (SER-109 oral capsules) in 2023 represents a landmark shift toward standardized microbiome-based therapies, replacing largely unregulated donor-specific FMT with quality-controlled pharmaceutical products. Ongoing studies are evaluating optimal indications, dosing, and long-term durability.
- Live biotherapeutic products (LBPs): Beyond traditional FMT, defined microbial consortia comprising specific bacterial species (e.g., VE303, a consortium of eight Clostridia species) are being investigated. Phase II data for VE303 demonstrated significant reduction in rCDI compared to placebo: in that trial (79 adults at high risk of recurrence, 27 sites in the U.S. and Canada; Louie 2023), capsules were taken once daily for 14 days, and recurrence by week 8 was 13.8% with the high dose, 37.0% with the low dose and 45.5% with placebo. The authors state that a larger phase 3 trial is needed to confirm these findings.
- Ribotype ecology and evolution: Genomic surveillance studies using whole-genome sequencing (WGS) have demonstrated that most Clostridioides difficile infection cases arise from distinct environmental acquisitions rather than patient-to-patient transmission in modern hospital settings, challenging traditional nosocomial transmission paradigms and suggesting community reservoirs (food supply, domestic animals) warrant greater attention.
- Bezlotoxumab real-world effectiveness: Post-approval registries and cohort studies have confirmed the real-world benefit of bezlotoxumab in reducing rCDI among high-risk patients, with greatest benefit in those with ≥1 prior Clostridioides difficile infection episode, age ≥65, and ribotype 027 infection. The drug was withdrawn from the market on January 31, 2025.
- Extended-pulsed fidaxomicin (EXTEND regimen): The EXTEND trial (Guery 2018; 364 hospitalized adults aged 60 and older at 86 European hospitals) compared fidaxomicin 200 mg twice daily on days 1–5, then once daily on alternate days on days 7–25, with standard vancomycin (125 mg four times daily for 10 days). Sustained cure 30 days after the end of treatment was 70% (124 of 177) with extended-pulsed fidaxomicin vs. 59% (106 of 179) with vancomycin, suggesting post-treatment microbiome colonization resistance can be restored with prolonged low-dose exposure. The 2021 IDSA/SHEA focused update lists the extended-pulsed regimen among its fidaxomicin options for recurrent episodes.
- Gut microbiome-based biomarkers: Research is identifying specific microbiome signatures (loss of Lachnospiraceae, Ruminococcaceae; expansion of Proteobacteria) that predict Clostridioides difficile infection recurrence, paving the way for microbiome-guided therapeutic decision-making.
Key Research Papers
- McDonald LC, Gerding DN, Johnson S, et al. Clinical Practice Guidelines for Clostridium difficile Infection in Adults and Children: 2017 Update by the Infectious Diseases Society of America (IDSA) and Society for Healthcare Epidemiology of America (SHEA). Clin Infect Dis. 2018;66(7):e1-e48. — doi:10.1093/cid/cix1085
- Lessa FC, Mu Y, Bamberg WM, et al. Burden of Clostridium difficile infection in the United States. N Engl J Med. 2015;372(9):825-834. — doi:10.1056/NEJMoa1408913
- Gerding DN, Johnson S, Rupnik M, Aktories K. Clostridium difficile binary toxin CDT: mechanism, epidemiology, and potential clinical importance. Gut Microbes. 2014;5(1):15-27. — doi:10.4161/gmic.26854
- Janoir C. Virulence factors of Clostridium difficile and their role during infection. Anaerobe. 2016;37:13-24. — doi:10.1016/j.anaerobe.2015.10.009
- Wilcox MH, Gerding DN, Poxton IR, et al. Bezlotoxumab for prevention of recurrent Clostridium difficile infection. N Engl J Med. 2017;376(4):305-317. — doi:10.1056/NEJMoa1602615
- Cornely OA, Crook DW, Esposito R, et al. Fidaxomicin versus vancomycin for infection with Clostridium difficile in Europe, Canada, and the USA: a double-blind, non-inferiority, randomised controlled trial. Lancet Infect Dis. 2012;12(4):281-289. — doi:10.1016/S1473-3099(11)70374-7
- van Nood E, Vrieze A, Nieuwdorp M, et al. Duodenal infusion of donor feces for recurrent Clostridium difficile. N Engl J Med. 2013;368(5):407-415. — doi:10.1056/NEJMoa1205037
- Feuerstadt P, Louie TJ, Lashner B, et al. SER-109, an oral microbiome therapy for recurrent Clostridioides difficile infection. N Engl J Med. 2022;386(3):220-229. — doi:10.1056/NEJMoa2106516
- Khanna S, Gerding DN. Current and future trends in Clostridioides (Clostridium) difficile infection management. Anaerobe. 2019;58:95-102. — doi:10.1016/j.anaerobe.2019.04.010
- Neal MD, Alverdy JC, Hall DE, Simmons RL, Zuckerbraun BS. Diverting loop ileostomy and colonic lavage: an alternative to total abdominal colectomy for the treatment of severe, complicated Clostridium difficile associated disease. Ann Surg. 2011;254(3):423-429. — doi:10.1097/SLA.0b013e31822ade48
- Surawicz CM, Brandt LJ, Binion DG, et al. Guidelines for diagnosis, treatment, and prevention of Clostridium difficile infections. Am J Gastroenterol. 2013;108(4):478-498. — doi:10.1038/ajg.2013.4
- Rao K, Malani PN. Diagnosis and treatment of Clostridioides (Clostridium) difficile infection in adults in 2020. JAMA. 2020;323(14):1403-1404. — doi:10.1001/jama.2019.3849
- Crobach MJT, Vernon JJ, Loo VG, et al. Understanding Clostridium difficile colonization. Clin Microbiol Rev. 2018;31(2):e00021-17. — doi:10.1128/CMR.00021-17
- Warny M, Pepin J, Fang A, et al. Toxin production by an emerging strain of Clostridium difficile associated with outbreaks of severe disease in North America and Europe. Lancet. 2005;366(9491):1079-1084. — doi:10.1016/S0140-6736(05)67420-X
- Kyne L, Warny M, Qamar A, Kelly CP. Association between antibody response to toxin A and protection against recurrent Clostridium difficile diarrhoea. Lancet. 2001;357(9251):189-193. — doi:10.1016/S0140-6736(00)03592-3
- Debast SB, Bauer MP, Kuijper EJ; European Society of Clinical Microbiology and Infectious Diseases. European Society of Clinical Microbiology and Infectious Diseases: update of the treatment guidance document for Clostridium difficile infection. Clin Microbiol Infect. 2014;20 Suppl 2:1-26. — doi:10.1111/1469-0691.12418
- Tixier EN, Verheyen E, Ungaro RC, Grinspan AM. Faecal microbiota transplant decreases mortality in severe and fulminant Clostridioides difficile infection in critically ill patients. Aliment Pharmacol Ther. 2019;50(10):1094-1099. — doi:10.1111/apt.15526
- Gerding DN, Muto CA, Owens RC. Treatment of Clostridium difficile infection. Clin Infect Dis. 2008;46 Suppl 1:S32-42. — doi:10.1086/521860
- Johnson S, Lavergne V, Skinner AM, et al. Clinical Practice Guideline by the Infectious Diseases Society of America (IDSA) and Society for Healthcare Epidemiology of America (SHEA): 2021 Focused Update Guidelines on Management of Clostridioides difficile Infection in Adults. Clin Infect Dis. 2021;73(5):e1029-e1044. — doi:10.1093/cid/ciab549
- Guery B, Menichetti F, Anttila VJ, et al. Extended-pulsed fidaxomicin versus vancomycin for Clostridium difficile infection in patients 60 years and older (EXTEND): a randomised, controlled, open-label, phase 3b/4 trial. Lancet Infect Dis. 2018;18(3):296-307. — doi:10.1016/S1473-3099(17)30751-X
- Arya R, Zimmet AN, Holubar M, Alegria W. Navigating recurrent Clostridioides difficile infection without Bezlotoxumab: potential challenges ahead. Antimicrob Steward Healthc Epidemiol. 2025;5(1):e332. — doi:10.1017/ash.2025.10144
- DeFilipp Z, Bloom PP, Torres Soto M, et al. Drug-Resistant E. coli Bacteremia Transmitted by Fecal Microbiota Transplant. N Engl J Med. 2019;381(21):2043-2050. — doi:10.1056/NEJMoa1910437
- Guh AY, Mu Y, Winston LG, et al. Trends in U.S. Burden of Clostridioides difficile Infection and Outcomes. N Engl J Med. 2020;382(14):1320-1330. — doi:10.1056/NEJMoa1910215
- Louie T, Golan Y, Khanna S, et al. VE303, a Defined Bacterial Consortium, for Prevention of Recurrent Clostridioides difficile Infection: A Randomized Clinical Trial. JAMA. 2023;329(16):1356-1366. — doi:10.1001/jama.2023.4314
PubMed Topic Searches
The following PubMed topic searches retrieve current peer-reviewed literature on Clostridium difficile. Each link opens a live PubMed query so you always see the most recent publications.
- PubMed: Clostridium difficile infection review
- PubMed: Clostridioides difficile fidaxomicin vs vancomycin
- PubMed: Fecal microbiota transplantation C difficile
- PubMed: C difficile recurrence risk factors
- PubMed: Proton pump inhibitor C difficile risk
- PubMed: C difficile epidemiology hospital acquired
- PubMed: Bezlotoxumab C difficile recurrence
- PubMed: C difficile toxin A toxin B pathogenesis
- PubMed: IDSA SHEA C difficile guideline
- PubMed: Saccharomyces boulardii C difficile probiotic
- PubMed: C difficile antibiotic stewardship
- PubMed: Ribotype 027 Clostridium difficile
Connections
- Infectious Disease
- Inflammatory Bowel Disease
- Probiotics
- Oral Microbiome
- Gut Healing
- Oregano
- Goldenseal
- Bone Broth
- Silver Nanoparticles
- Irritable Bowel Syndrome
- Gut-Brain Axis
- Staphylococcus Aureus
- Inflammatory Markers
- Bloating
- Gut Microbiome
- Parasites
- Kidney Disease
- Creatinine
- Sepsis
- Immune Boosting