Human Parasites: Common Infections, Symptoms, Testing, and Treatment
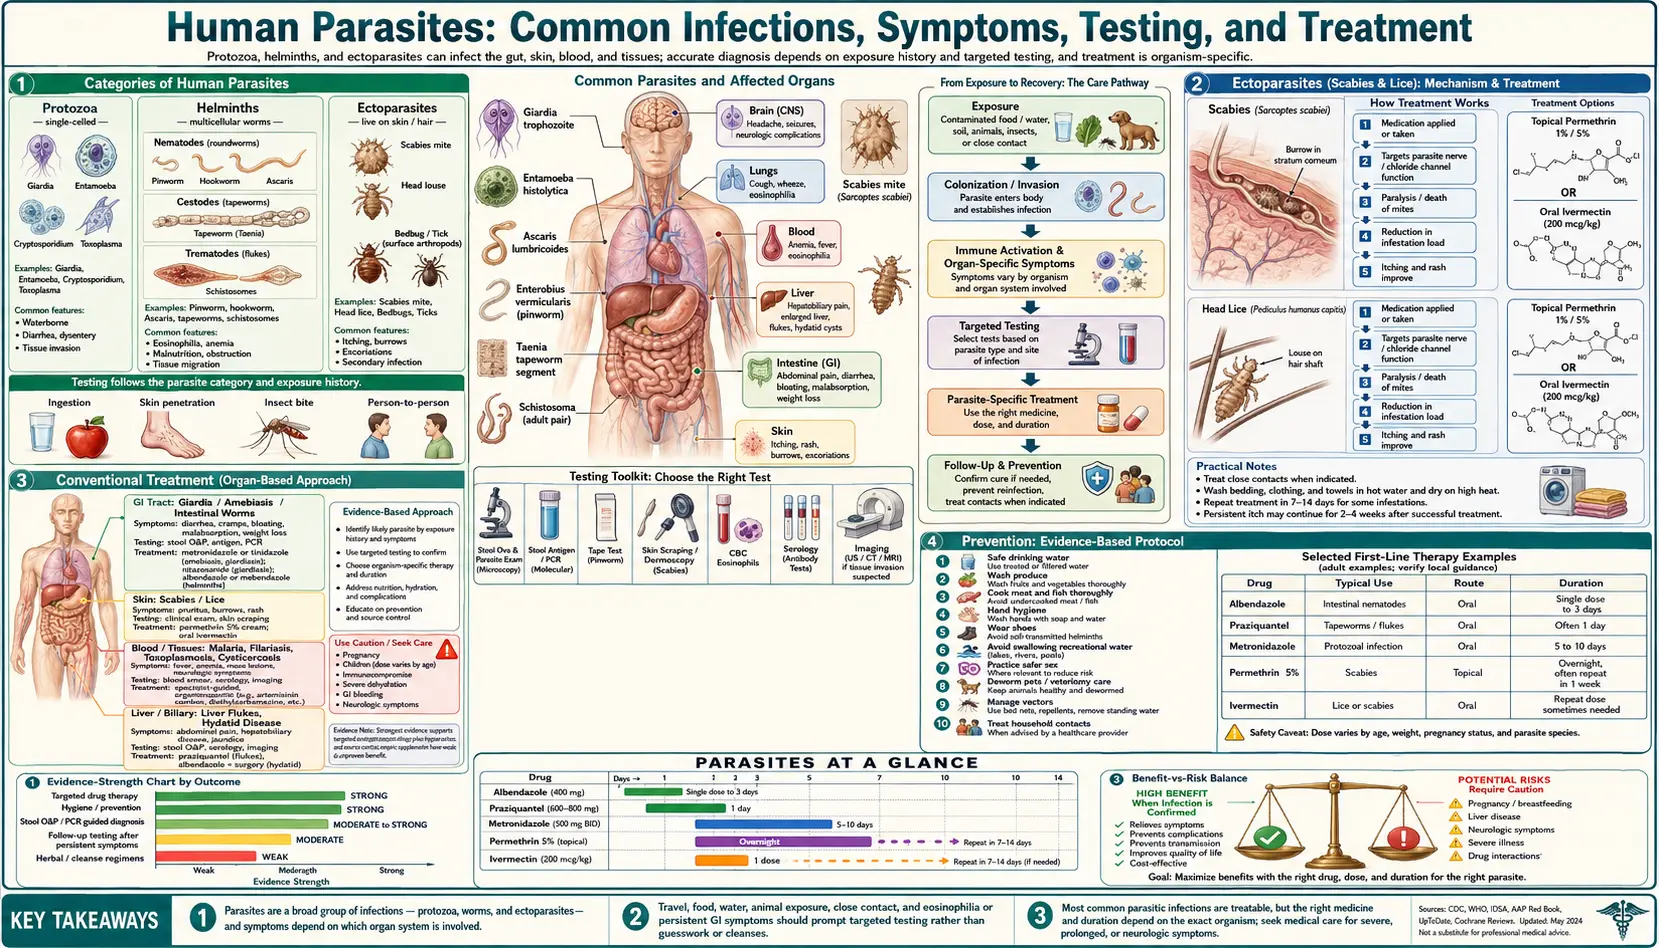
Parasites are organisms that live on or in another organism (the host) and depend on the host for survival, often at the host's expense. Globally, parasitic infections remain a major source of disease — the World Health Organization estimates that more than 1.5 billion people carry intestinal worms, hundreds of millions are affected by malaria, and tens of millions live with chronic infections like Chagas, schistosomiasis, and toxoplasmosis. Even in high-income countries with safe water and food, sub-clinical parasitic infections are more common than most people realize, particularly among travelers, immigrants, immunocompromised patients, dog and cat owners, and those who consume undercooked meat or unwashed produce.
This page is an overview hub. It covers what parasites are, the most common categories you may encounter, signs and symptoms, how testing actually works (and why it often misses), conventional and naturopathic treatment options, and prevention. For drug-specific information, see the Fenbendazole page; for botanical antiparasitic options, the Herbs section.
Table of Contents
Categories of Human Parasites
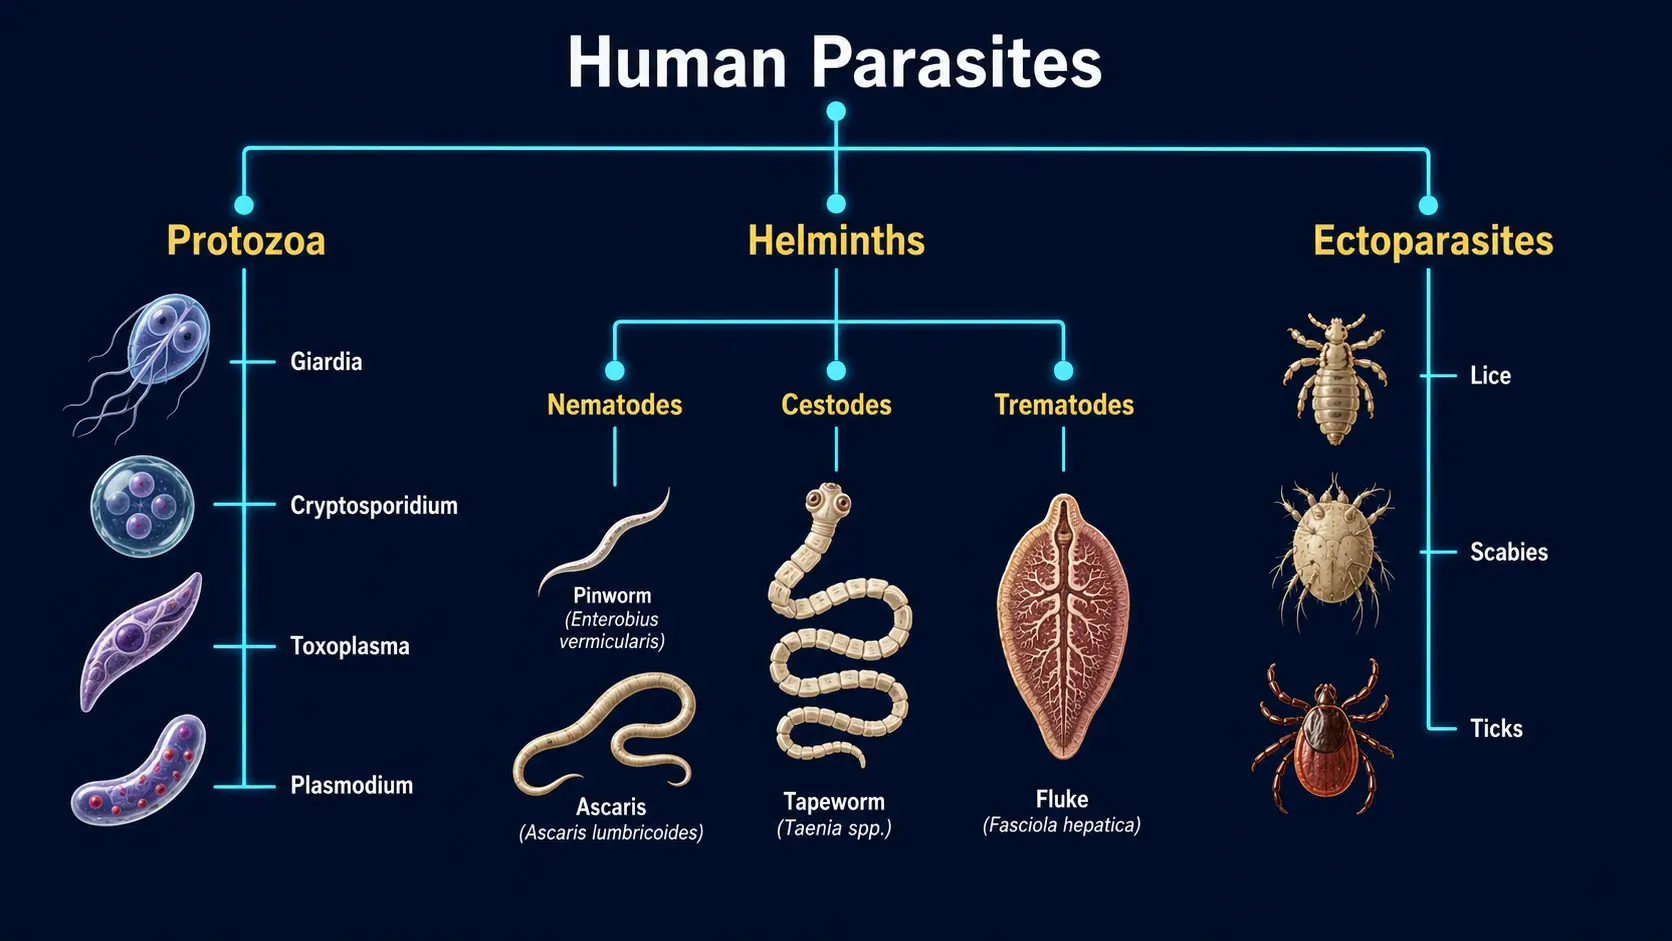
Human parasites fall into three broad biological categories, and several common species in each:
- Protozoa — single-celled organisms; reproduce inside the host. Examples: Giardia lamblia, Cryptosporidium, Entamoeba histolytica, Blastocystis, Toxoplasma gondii, Plasmodium (malaria).
- Helminths — multicellular worms. Three subgroups: roundworms (nematodes), flatworms (cestodes / tapeworms), and flukes (trematodes).
- Ectoparasites — live on the skin surface. Examples: lice, scabies mites, bed bugs, ticks (when feeding).
Protozoa
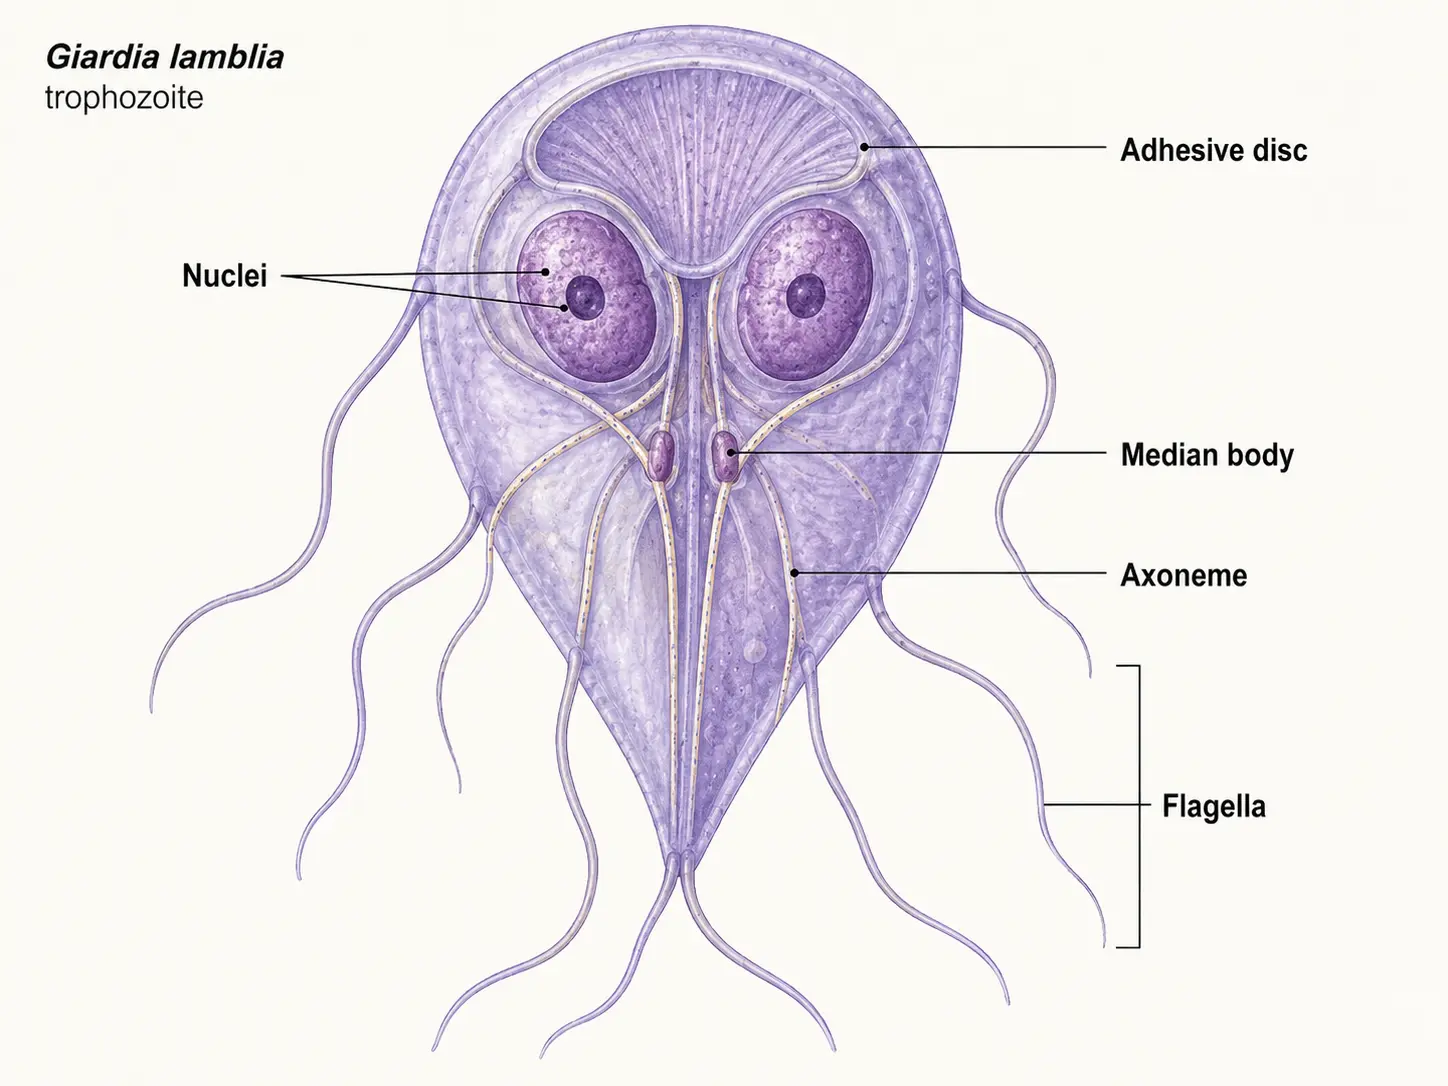
Giardia lamblia
The most common waterborne protozoan in the developed world. Acquired from contaminated water (lakes, streams, well water) or person-to-person fecal-oral spread (daycare settings). Causes "beaver fever": chronic diarrhea, foul-smelling stools, bloating, gas, fatigue, and malabsorption. Diagnosis is by stool antigen (more sensitive) or stool ova-and-parasite microscopy (less sensitive). First-line treatment: tinidazole or metronidazole; nitazoxanide for resistant cases.
Cryptosporidium parvum
Another waterborne protozoan; resistant to chlorination, which is why municipal outbreaks still occur. Causes profuse watery diarrhea. Self-limited in immunocompetent adults but can be life-threatening in human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS). Diagnosis: stool antigen, modified acid-fast staining. Nitazoxanide is the only U.S. Food and Drug Administration-approved treatment.
Entamoeba histolytica
Causes amebic dysentery (bloody diarrhea), liver abscess. Acquired from contaminated water or food, particularly in tropical and subtropical regions. Diagnosis: stool antigen / polymerase chain reaction (PCR) (microscopy alone confuses pathogenic E. histolytica with non-pathogenic E. dispar). Treatment: metronidazole followed by a luminal agent (paromomycin or iodoquinol) to clear cyst-stage organisms.
Blastocystis spp
Common gut commensal that can become symptomatic in some hosts — chronic diarrhea, abdominal pain, urticaria. Causality is debated; many people carry Blastocystis without symptoms. Treatment is controversial; metronidazole or nitazoxanide can be tried in symptomatic cases. Often co-occurs with small intestinal bacterial overgrowth (SIBO) and irritable bowel syndrome (IBS).
Toxoplasma gondii
Acquired from undercooked meat or cat feces (litter box, garden soil). About 30% of the world's adults are seropositive. Usually asymptomatic in immunocompetent hosts but can cause flu-like illness, lymphadenopathy, eye disease, and serious problems in pregnancy (congenital toxoplasmosis) and immunocompromise. Diagnosis: serology. Treatment: pyrimethamine + sulfadiazine + leucovorin in symptomatic cases. In pregnancy, the CDC lists spiramycin for infections acquired and diagnosed before 18 weeks when infection of the fetus is not documented or suspected, and pyrimethamine + sulfadiazine + leucovorin (folinic acid) for infections acquired at or after 18 weeks or when the fetus is known or suspected to be infected.
Plasmodium spp (malaria)
Mosquito-borne; the leading cause of parasite-related death worldwide. Symptoms include cyclic fever, chills, headache, and severe complications including cerebral malaria. Diagnosis: blood smear, rapid antigen tests, polymerase chain reaction. Treatment depends on species and resistance patterns: artemisinin combination therapies are first-line in most settings.
Helminths (Worms)
Roundworms (nematodes)
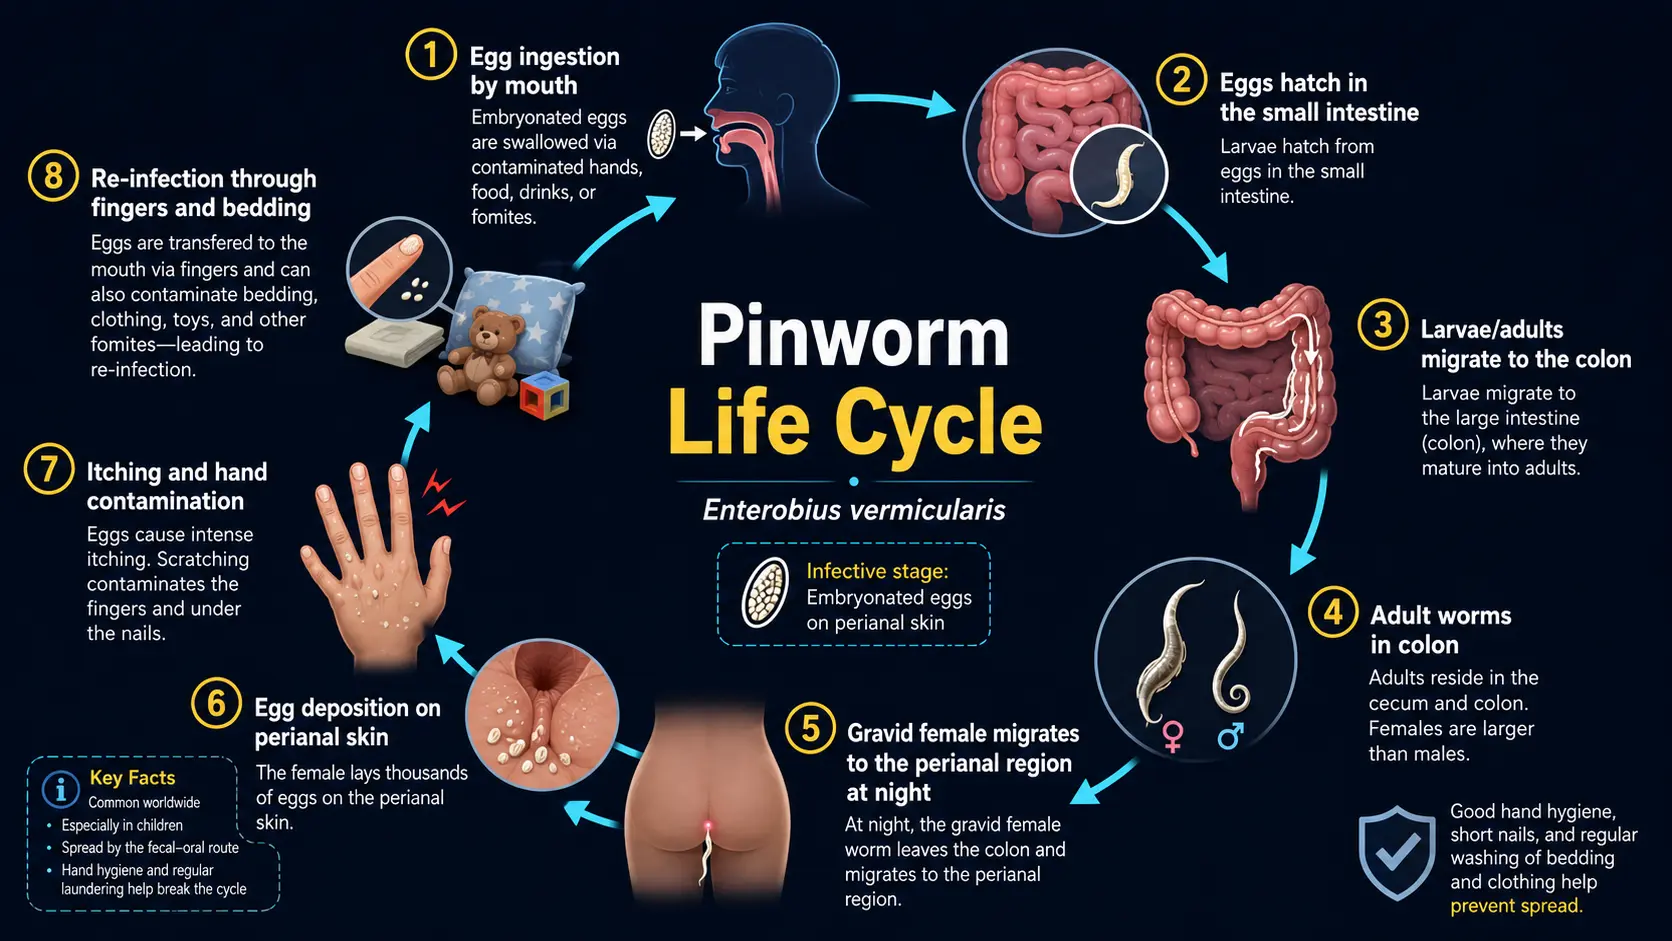
- Pinworm (Enterobius vermicularis) — the most common parasitic worm in the US. Children are the primary host; nighttime perianal itching is the classic symptom. Diagnosis: tape test. Treatment: mebendazole or albendazole; the CDC advises treating everyone in the household and caregivers at the same time, with two doses given two weeks apart.
- Roundworm (Ascaris lumbricoides) — the largest intestinal worm; can grow to 35 cm. Acquired from contaminated soil; common in tropical regions. Most carriers are asymptomatic; heavy loads cause gastrointestinal (GI) symptoms and rare obstruction. Treatment: albendazole or mebendazole.
- Hookworm (Necator americanus, Ancylostoma duodenale) — penetrates skin from contaminated soil. Causes iron-deficiency anemia from chronic blood loss in the gut. Treatment: albendazole or mebendazole + iron repletion.
- Whipworm (Trichuris trichiura) — tropical regions; usually asymptomatic, heavy infections cause dysentery and rectal prolapse in children. Treatment: albendazole + ivermectin combination is more effective than albendazole alone.
- Strongyloides stercoralis — auto-infective; can persist for decades. Highly dangerous in immunocompromise (hyperinfection syndrome). Diagnosis: serology + stool. Treatment: ivermectin.
- Trichinella spiralis — from undercooked pork or wild game. Causes muscle pain, fever, periorbital edema, eosinophilia. Diagnosis: serology, muscle biopsy. Treatment: albendazole + steroids in heavy infection.
Flatworms / tapeworms (cestodes)
- Beef tapeworm (Taenia saginata) and pork tapeworm (Taenia solium) — the intestinal tapeworms come from undercooked beef or pork. Cysticercosis, in which pork tapeworm larvae lodge in brain and muscle, comes from swallowing pork tapeworm eggs passed in the feces of a person who carries the tapeworm; the CDC states that eating pork cannot give you cysticercosis. Treatment: praziquantel.
- Fish tapeworm (Diphyllobothrium latum) — from raw or undercooked freshwater fish; competes for vitamin B12. Treatment: praziquantel.
- Echinococcus granulosus (hydatid disease) — from dogs and livestock; forms cysts in liver and lung. Treatment: surgical or PAIR procedure + albendazole.
Flukes (trematodes)
- Schistosoma spp — freshwater snail intermediate host; dermatologic, gastrointestinal, urinary tract, and chronic liver/bladder disease. Treatment: praziquantel.
- Liver flukes (Fasciola, Clonorchis, Opisthorchis) — from undercooked freshwater fish or contaminated watercress. Treatment: triclabendazole for Fasciola, against which praziquantel is ineffective (the U.S. triclabendazole label covers fascioliasis); praziquantel for Clonorchis and Opisthorchis, which its U.S. label covers.
Ectoparasites
- Head/body/pubic lice — permethrin, malathion, ivermectin lotion
- Scabies (Sarcoptes scabiei) — intensely itchy skin burrows; permethrin cream or oral ivermectin
- Bed bugs (Cimex lectularius) — not a true infection; itchy bites; environmental control is the treatment
- Ticks — vectors for Lyme disease, Rocky Mountain spotted fever, anaplasmosis, babesiosis, alpha-gal syndrome (a meat allergy from Lone Star tick saliva — see Alpha-Gal Syndrome)
Symptoms and Red Flags
Parasitic infections can be asymptomatic, mild, or severe. Common chronic symptoms in patients who turn out to have a parasite:
- Chronic, intermittent diarrhea or alternating diarrhea and constipation
- Persistent abdominal pain, bloating, gas
- Foul-smelling, greasy, or floating stools (suggests fat malabsorption from giardia or other small-bowel infection)
- Unexplained weight loss
- Fatigue out of proportion to lifestyle
- Chronic urticaria (hives), itching, or unexplained rashes
- Iron-deficiency anemia in someone with adequate dietary intake (think hookworm or whipworm)
- Eosinophilia on complete blood count (CBC) (helminth infections particularly)
- Nighttime perianal itching (pinworm)
- Teeth grinding in children (sometimes attributed to pinworm)
- Travel history with onset of new gastrointestinal or systemic symptoms
Red flags warranting prompt medical evaluation: bloody diarrhea, fever, severe abdominal pain, jaundice, neurologic symptoms (seizures, focal deficits — possible neurocysticercosis), eye involvement (toxoplasmosis), respiratory symptoms with eosinophilia (Strongyloides hyperinfection), or any acute symptoms in an immunocompromised patient.
Testing: What's Available and What Misses
Parasite diagnosis is harder than most patients expect. The traditional "ova and parasites" stool exam (O&P) requires three specimens collected on different days and examined microscopically. Even at competent labs the sensitivity for many organisms is only 50–75% per single specimen. Modern alternatives are more sensitive:
- Stool antigen tests — widely available for Giardia, Cryptosporidium, and Entamoeba histolytica; sensitivities of 85–95% on a single specimen
- Multiplex polymerase chain reaction stool panels — cover 22+ pathogens including parasites, bacteria, viruses; sensitivities > 95%; not yet standard at every hospital
- Serology — for tissue-invasive parasites that may not appear in stool: Strongyloides, Toxoplasma, Trichinella, Schistosoma, Cysticercus, Toxocara, Echinococcus
- Tape test — pinworm (perianal cellulose tape pressed against the skin in the morning before bathing)
- Blood smear — malaria, babesiosis, microfilariae
- Imaging — computed tomography (CT) or magnetic resonance imaging (MRI) for neurocysticercosis, hydatid cysts, liver abscess
- Eosinophilia + immunoglobulin E (IgE) elevation on routine bloodwork — supporting evidence for helminth infection but non-specific
When three O&P exams are negative but the clinical suspicion remains high, antigen testing, multiplex polymerase chain reaction, and serology are the more sensitive options listed above — the older test misses many organisms.
Conventional Treatment
The major antiparasitic drug families:
- Benzimidazoles — albendazole, mebendazole, fenbendazole (veterinary, but used off-label). Disrupt parasite microtubules. Broad nematode coverage; some helminths.
- Avermectins — ivermectin. Disrupts glutamate-gated chloride channels in parasites. Effective against Strongyloides, scabies, lice, river blindness, lymphatic filariasis.
- 5-nitroimidazoles — metronidazole, tinidazole, secnidazole. Anaerobic protozoa: Giardia, amebiasis, trichomoniasis.
- Praziquantel — the standard drug for tapeworms (cestodes) and for flukes (trematodes) such as schistosomes, but ineffective against Fasciola liver flukes (Sprague 2024). Its U.S. label covers schistosomiasis and the Clonorchis/Opisthorchis liver flukes, and lists it as contraindicated in cysticercosis of the eye (ocular cysticercosis) and together with strong CYP3A-inducing drugs such as rifampin, which keep praziquantel from reaching effective levels.
- Nitazoxanide — broad-spectrum: Cryptosporidium, Giardia, helminths; well-tolerated.
- Pyrantel pamoate — sold over-the-counter (OTC) in the US as pinworm medicine; pinworm and roundworm.
- Antimalarials — artemisinin combinations, atovaquone-proguanil, chloroquine (where still effective), primaquine.
For most outpatient parasitic infections in the US, a confirmed diagnosis followed by a single targeted course is curative. Empiric treatment without diagnosis is occasionally appropriate (pinworm in symptomatic households, traveler's diarrhea in some settings) but generally suboptimal — the wrong drug for the wrong organism doesn't work.
Naturopathic and Botanical Approaches
Several traditional botanicals show in-vitro and limited clinical antiparasitic activity. Practitioners use them as adjuncts to conventional treatment, for sub-clinical dysbiosis, or in cases where targeted antiparasitic drugs are contraindicated. Most of the published research on them is laboratory and animal work.
- Black seed (Nigella sativa) — thymoquinone has demonstrated activity against Schistosoma, Giardia, and tapeworm in animal models
- Garlic (Allium sativum) — allicin shows activity against Giardia and Entamoeba in vitro
- Pau d'arco (Tabebuia impetiginosa) — lapachol has historical use for parasitic and fungal infections
- Wormwood (Artemisia absinthium) — the historical anti-helminthic; artemisinin (from Artemisia annua) is the basis of modern anti-malarials
- Black walnut hull (Juglans nigra) — juglone has anti-parasitic activity; traditional in herbal protocols
- Cloves (Syzygium aromaticum) — eugenol; included in classic three-herb anti-parasitic combinations
- Pumpkin seeds (Cucurbita pepo) — cucurbitin; folk remedy for tapeworms
- Goldenseal (Hydrastis canadensis) — berberine has activity against Giardia and Entamoeba
- Cumin (Cuminum cyminum) — gut antimicrobial activity
- Probiotics — specific strains (Saccharomyces boulardii in particular) reduce Giardia symptoms and shedding
- Berberine-containing herbs — goldenseal, barberry; activity against Giardia, Entamoeba
Fenbendazole — A Note on Off-Label Use
Fenbendazole is a benzimidazole antiparasitic approved for veterinary use. It has gained significant attention online for off-label human use, including for helminth infections and in unproven cancer protocols. The page Fenbendazole covers what is and isn't established about safety, dosing, and the limits of the evidence. Fenbendazole is not approved by the U.S. Food and Drug Administration for human use. Published case reports describe drug-induced liver injury in people who took veterinary fenbendazole on their own: an 80-year-old woman with lung cancer, who was also receiving the cancer drug pembrolizumab, developed severe liver injury after a month of fenbendazole, which cleared up after she stopped it (Yamaguchi 2021); a 67-year-old woman developed jaundice from biopsy-confirmed severe liver injury, and her liver tests returned to normal 3 months after she stopped (Thakurdesai 2024). Yellowing of the skin or eyes (jaundice) is a sign of liver injury that hospitals treat as urgent. Because a drug for one parasite may not work on another, the confirmed diagnosis decides which drug fits.
Prevention
- Thorough cooking of meat — pork, beef, fish, wild game (U.S. Department of Agriculture (USDA) temperatures: pork and beef 145°F, ground meat 160°F, poultry 165°F, fish 145°F)
- Handwashing after handling raw meat, after using the bathroom, after gardening, after handling pets, and before food prep
- Washing fruits and vegetables, especially leafy greens, herbs, and produce eaten raw
- Water from safe sources; filtering or boiling suspect water; iodine or chlorine for backcountry use
- Swallowed water from lakes, rivers, and swimming pools is a route of infection (especially while traveling)
- Litter box hygiene — the FDA’s advice for pregnant women is to have someone else change the litter box if possible, or else to wear disposable gloves and wash hands with soap and warm water afterwards; it advises changing the box daily, because the parasite does not become infectious until one to five days after it is shed
- Insect protection in endemic regions: DEET / picaridin, permethrin-treated clothing, bed nets
- Annual deworming for pets following veterinary protocols
- Children with confirmed pinworm: the CDC advises treating the infected person, caregivers and everyone in the household at the same time with the same two-dose treatment, the second dose two weeks after the first, and washing night clothes, underwear, towels and bedding often in hot water (at least 130°F); many families also vacuum
- Travelers returning from tropical regions with new symptoms: the travel history is a key clue that points to parasite testing (see the symptoms and testing sections above)
Key Research Papers
- Intestinal parasites diagnosis and treatment — PubMed search
- Giardia treatment options — PubMed search
- Albendazole and mebendazole for helminths — PubMed search
- Ivermectin for Strongyloides and scabies — PubMed search
- Multiplex stool PCR sensitivity — PubMed search
- Blastocystis and pathogenicity debate — PubMed search
- Botanical antiparasitic activity — PubMed search
- Eosinophilia and helminth infection — PubMed search
- Sprague DJ, Park SK, Gramberg S, Bauer L, Rohr CM, Chulkov EG, Smith E, Scampavia L, Spicer TP, Haeberlein S, Marchant JS. Target-based discovery of a broad-spectrum flukicide. Nat Struct Mol Biol. 2024;31(9):1386–1393. — PubMed PMID: 38714890
- Yamaguchi T, Shimizu J, Oya Y, Horio Y, Hida T. Drug-induced liver injury in a patient with nonsmall cell lung cancer after the self-administration of fenbendazole based on social media information. Case Rep Oncol. 2021;14(2):886–891. — PubMed PMID: 34248555
- Thakurdesai A, Rivera-Matos L, Nagra N, Busch B, Mais DD, Cave MC. Severe drug-induced liver injury due to self-administration of the veterinary anthelmintic medication, fenbendazole. ACG Case Rep J. 2024;11(5):e01354. — PubMed PMID: 38706451
External Authoritative Resources
Connections
- All Remedies
- Tu Youyou — artemisinin, malaria, and the 2015 Nobel Prize
- Fenbendazole
- Garlic
- Goldenseal
- Black Seed
- Cumin
- Barberry
- Pau d'Arco
- Berberine (Herb)
- Probiotics
- Small Intestinal Bacterial Overgrowth
- Alpha-Gal Syndrome
- Anemia
- Complete Blood Count
- Gut Healing
- Detox Protocols
- Malaria
- Abdominal Pain
- Oregano
- Conditions on this site that reference this page: Clostridioides difficile Infection · Tick-Borne Co-Infections
- Mimosa Pudica
Featured Videos