NAD+ Precursors Compared: Niacin vs Niacinamide vs NR vs NMN
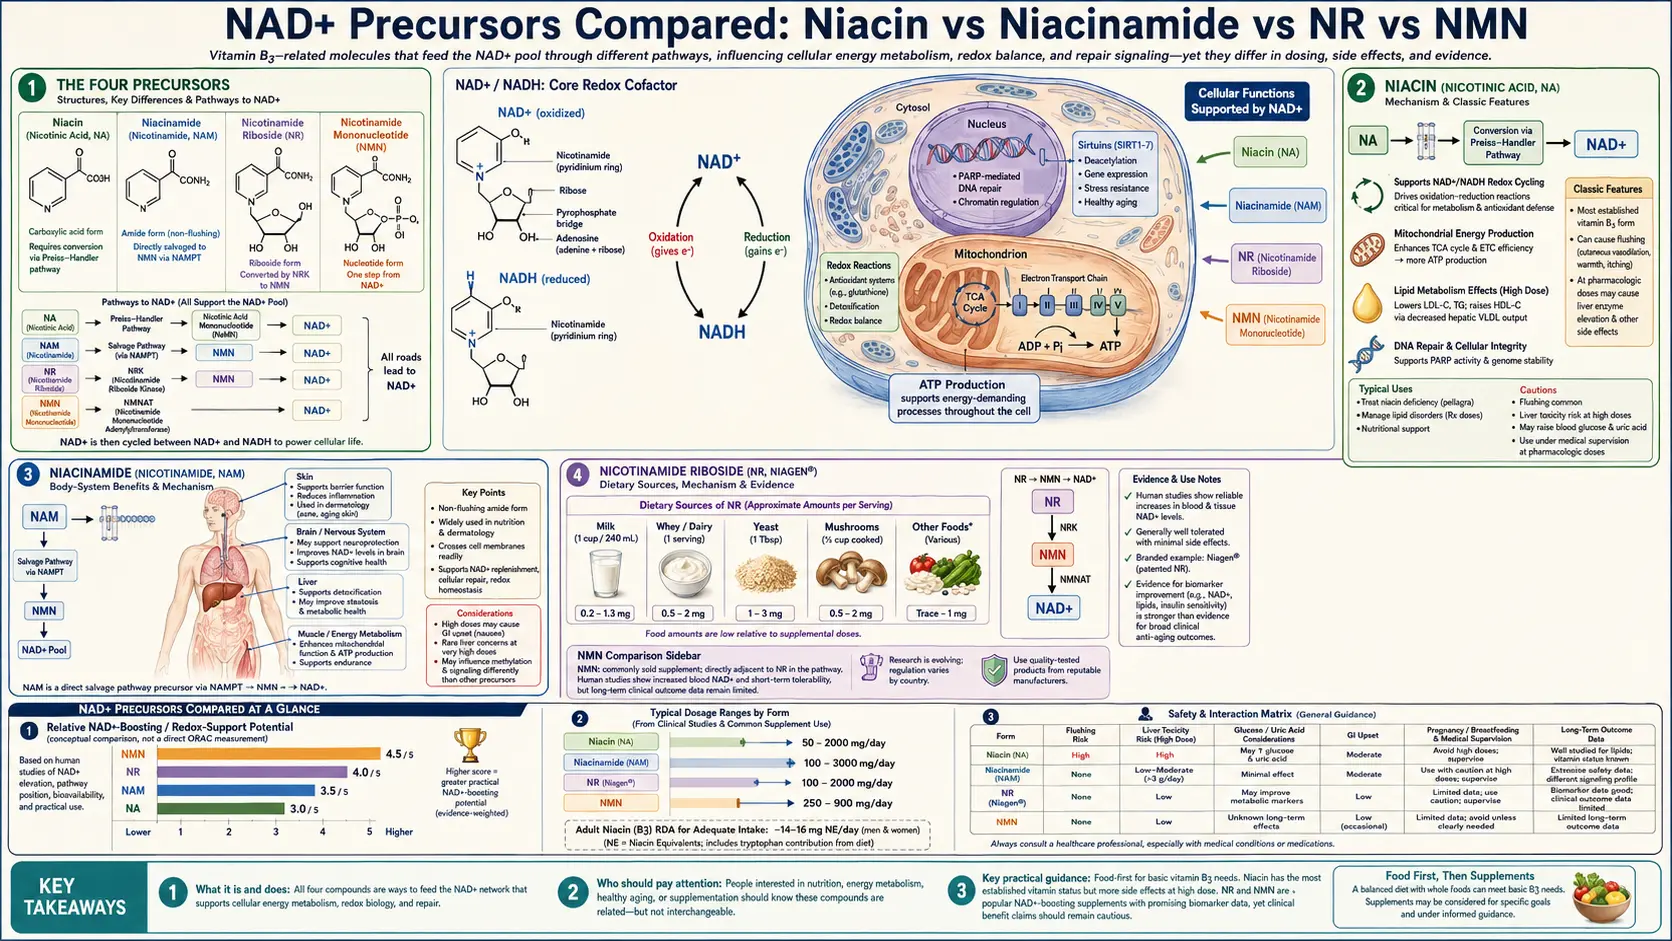
Four molecules can serve as NAD+ precursors in human supplementation: nicotinic acid (niacin, NA), nicotinamide (niacinamide, NAM), nicotinamide riboside (NR), and nicotinamide mononucleotide (NMN). They are all forms of vitamin B3 in the broadest sense, but they differ substantially in absorption, tissue distribution, methylation cost, side-effect profile, regulatory history, and the strength of their clinical evidence. This deep-dive walks through each molecule, the Brenner-vs-Sinclair NR-vs-NMN debate, the FDA's 2022 exclusion of NMN and its September 2025 reversal, why niacin produces vasodilator flushing while NR and NMN do not, the methylation-cofactor concern, how much NAD+ each raises, and what the trials found for each goal.
Table of Contents
- The Four Precursors
- Niacin (Nicotinic Acid, NA)
- Niacinamide (Nicotinamide, NAM)
- Nicotinamide Riboside (NR)
- Nicotinamide Mononucleotide (NMN)
- Side-by-Side Comparison Table
- The Niacin Flush — Why It Happens and Why NR/NMN Are Flush-Free
- The Methylation Cofactor Debate (Brenner Critique)
- The Sinclair NMN Advocacy
- The FDA NMN Exclusion (2022) and Reversal (2025)
- How Much NAD+ Each Precursor Raises
- What the Trials Found, by Goal
- Safety Findings
- Key Research Papers
- Connections
- Featured Videos
The Four Precursors
All four NAD+ precursors share the same downstream destination: incorporation into the cellular NAD+ pool, where they support the electron transport chain, sirtuin activity, PARP DNA repair, and CD38 signaling. They differ in the steps required to get there.
Schematic of the salvage pathway from each precursor to NAD+:
- Niacin (NA) — enters the Preiss-Handler pathway: NA + PRPP → nicotinic acid mononucleotide (NaMN) via NAPRT; NaMN + ATP → nicotinic acid adenine dinucleotide (NaAD) via NMNAT; NaAD + glutamine → NAD+ via NAD synthase
- Niacinamide (NAM) — enters the salvage pathway: NAM + PRPP → NMN via NAMPT (the rate-limiting enzyme); NMN + ATP → NAD+ via NMNAT
- Nicotinamide riboside (NR) — phosphorylated by NR kinase (NRK1, NRK2): NR + ATP → NMN; NMN + ATP → NAD+ via NMNAT
- Nicotinamide mononucleotide (NMN) — converted directly: NMN + ATP → NAD+ via NMNAT (most direct route)
This is why NMN is sometimes called "one step from NAD+": NMN bypasses the NAMPT and NRK steps and feeds directly into the final NMNAT-catalyzed conversion. Whether this directness matters in practice depends on whether NMN can enter cells intact, which is contested (see Brenner critique below); in mice, most oral NMN and NR is converted by gut bacteria to nicotinic acid before it feeds NAD+ synthesis (Yaku and colleagues, 2025).
Niacin (Nicotinic Acid, NA)
Niacin is the oldest and best-characterized of the four. Nicotinic acid was identified as the anti-pellagra factor in 1937 (Conrad Elvehjem's laboratory), building on Joseph Goldberger's earlier public-health work showing pellagra was dietary, and it has been a recognized vitamin (vitamin B3) ever since. The pharmaceutical-grade prescription form has been in clinical use for over 60 years, primarily for dyslipidemia.
Clinical effects
- Lowers LDL cholesterol by 10–25% at 1–3 g/day
- Raises HDL cholesterol by 15–35% (the most effective HDL-raising agent known)
- Lowers triglycerides by 20–50%
- Lowers Lp(a) by 20–30% (one of the few interventions that meaningfully lowers Lp(a))
- Treats pellagra (the niacin-deficiency syndrome of dermatitis, diarrhea, dementia, death)
- Raises NAD+ (via the Preiss-Handler pathway)
Drawbacks
- The niacin flush — intense cutaneous vasodilation, burning, and pruritus lasting 30–60 minutes, mediated by GPR109A receptor activation on dermal Langerhans cells and prostaglandin D2 release. Becomes more tolerable with chronic use. In a crossover trial in 148 healthy men, aspirin 650 mg taken 30 minutes before or together with 2,000 mg of extended-release niacin reduced the share who flushed from 77% to 53–61% (Cefali and colleagues, 2007).
- Hepatotoxicity — rare at standard doses but a real risk with sustained-release formulations and at >3 g/day
- Hyperglycemia — can worsen glucose control in diabetics
- Hyperuricemia — can precipitate gout attacks
- The cardiovascular outcome trials of niacin (AIM-HIGH, HPS2-THRIVE) found no added benefit when niacin was added to statins, despite the lipid changes — in AIM-HIGH, 3,414 patients with cardiovascular disease, the trial was stopped early for lack of efficacy
Niacin raises NAD+ through the Preiss-Handler pathway; flushing is the side effect most often reported. See our Vitamin B3 (Niacin) page and Niacin & Cholesterol for the lipid-focused discussion, and Pellagra for the deficiency syndrome.
Niacinamide (Nicotinamide, NAM)
Niacinamide (the amide form of nicotinic acid) is the form found in most multivitamins and B-complex supplements at the official RDA-level dose of 14–16 mg/day. It also has a long history as a high-dose supplement for specific clinical purposes:
- Type 1 diabetes prevention (historical) — in the ENDIT trial, 552 relatives of people with type 1 diabetes who had islet-cell antibodies took high-dose nicotinamide or placebo for 5 years; diabetes developed at the same rate in both groups (Gale and colleagues, 2004)
- Skin cancer prevention — in the ONTRAC trial (New England Journal of Medicine), 386 people who had had at least two non-melanoma skin cancers in the previous 5 years took 500 mg nicotinamide twice daily or placebo for 12 months; the rate of new non-melanoma skin cancers was 23% lower with nicotinamide, with no benefit after it was stopped
- Topical skin care — widely used in cosmetics at 5% concentration for barrier function and pigmentation
- Raises NAD+ via the salvage pathway through NAMPT (the rate-limiting enzyme)
Advantages
- Cheapest of the four precursors (cents per gram)
- No flushing (no GPR109A activation)
- Generally well tolerated up to 1.5–3 g/day
Drawbacks
- In a 2026 randomized comparison in 65 healthy adults, 14 days of NR or NMN comparably increased circulating NAD+, while nicotinamide did not (Christen and colleagues, 2026)
- NAM inhibits SIRT1 in the test tube as a reaction product — it is both a precursor for NAD+ synthesis and a product of NAD+-consuming reactions — but in cells it can act as a stimulator (Hwang and Song, 2017). This is a theoretical concern more than a documented clinical issue
- Hepatotoxicity at sustained doses >3 g/day
For raising circulating NAD+, nicotinamide was the one precursor in the 2026 comparison that did not do so.
Nicotinamide Riboside (NR)
Nicotinamide riboside was characterized as an NAD+ precursor by Charles Brenner's lab in 2004 (Bieganowski and Brenner, 2004). It is the nucleoside form of NAM — nicotinamide attached to a ribose sugar but without the phosphate group. NR was later patented and sold as a branded supplement, the first commercial NAD+ precursor with a strong intellectual-property position.
Advantages reported
- More human trials than NMN — more human trials have used NR than NMN, because NR has been studied clinically for longer; the Martens 2018 trial (30 randomized, 24 completed, NR 1,000 mg/day) is a foundational safety study
- Raises blood NAD+ in the trials that measured it, at 1,000–2,000 mg/day in most trials
- No flushing
- Pharmacokinetics characterized in mice and humans (Trammell and colleagues, 2016)
Drawbacks reported
- Requires two enzymatic steps to NAD+ (NRK phosphorylation then NMNAT adenylylation), so it is technically more "upstream" than NMN
- Like NMN, raises the theoretical methylation-cofactor concern at chronic high doses through nicotinamide methylation by NNMT
- Clinical results so far are small, mixed or absent: NR did not change muscle mitochondrial bioenergetics in older men (Elhassan and colleagues, 2019) or improve insulin sensitivity in obese men (Dollerup and colleagues, 2018)
The human evidence base for NR is larger and longer than NMN's.
Nicotinamide Mononucleotide (NMN)
NMN is NR plus a phosphate — the immediate precursor of NAD+ in the salvage pathway. NMN became commercially prominent in the late 2010s; the FDA has said it is aware of evidence that NMN was marketed as a dietary supplement in the United States as early as 2017. Mouse experiments, including the 12-month study from Shin-ichiro Imai's laboratory (Mills and colleagues, 2016) and work from David Sinclair's laboratory, reported improvements in age-related measures, and Sinclair's public advocacy drove consumer interest.
Advantages reported
- One step from NAD+ in the salvage pathway, so theoretically the most direct precursor
- Slc12a8 — a 2019 mouse study reported this gene encodes an NMN transporter in the small intestine (Grozio and colleagues, 2019); this was disputed (Schmidt and Brenner, 2019)
- Raises blood NAD+ in every trial that measured it; trials have used 250 to 2,000 mg/day, most often 250 to 900 mg; in the 2026 comparison the rise was comparable to NR's
- No flushing
- Mouse data — 12 months of NMN improved weight gain, energy metabolism, physical activity, insulin sensitivity and eye function in mice (Mills and colleagues, 2016); that study did not report a lifespan result
- Since 29 September 2025 the FDA no longer considers NMN excluded from the US dietary-supplement definition (see below)
Drawbacks reported
- Smaller human evidence base than NR — the human trials are fewer and short (14 days to 24 weeks)
- Brenner critique on bioavailability — the argument is that NMN must be dephosphorylated extracellularly to NR before cellular uptake, in which case oral NMN and oral NR end up doing the same thing biochemically
- Supplement quality, including whether a product contains the amount of NMN on its label, is not checked by the FDA before sale
- Like NR, raises the theoretical methylation-cofactor concern at chronic high doses
- FDA regulatory history: excluded in 2022, reversed in 2025 (see below)
Side-by-Side Comparison Table
| Property | Niacin (NA) | Niacinamide (NAM) | NR | NMN |
|---|---|---|---|---|
| Steps to NAD+ | 3 (Preiss-Handler) | 2 (salvage) | 2 | 1 |
| Doses studied | 1–3 g/day in lipid studies; 1,500–2,000 mg/day in AIM-HIGH | 500 mg twice daily (ONTRAC); 1.2 g/m² (ENDIT) | Mostly 1,000–2,000 mg/day | 250–2,000 mg/day, most often 250–900 mg |
| Vasodilator flush | Yes (significant) | No | No | No |
| Effect on lipids | Lowers LDL/TG; raises HDL | Minimal | Minimal | Minimal |
| Methylation cost | Low (NA does not pass through NAM in the same way) | Moderate | Moderate-high | Moderate-high |
| Human RCT evidence | Extensive (lipid trials; less on NAD+ outcomes) | Moderate (skin cancer; deficiency) | More trials than NMN | Growing; meta-analyses have pooled 8 to 15 trials |
| FDA status (US) | Dietary supplement; prescription forms for lipids | Dietary supplement | Dietary supplement | Excluded Oct/Nov 2022; not excluded since 29 Sept 2025; a new dietary ingredient |
| Main human findings | Lipid changes; no added cardiovascular benefit on top of statins (AIM-HIGH, HPS2-THRIVE) | Fewer new skin cancers in high-risk patients (ONTRAC); did not prevent type 1 diabetes (ENDIT); did not raise blood NAD+ in a 2026 comparison | Raises blood NAD+; clinical effects small, mixed or absent | Raises blood NAD+; one positive insulin-sensitivity trial; other clinical effects small, mixed or absent |
The Niacin Flush — Why It Happens and Why NR/NMN Are Flush-Free
The flush is mediated by a specific receptor: GPR109A (also called HM74A or HCAR2), a G-protein coupled receptor expressed on dermal Langerhans cells, adipocytes, immune cells, and some neurons. Niacin (nicotinic acid) is the GPR109A agonist. When niacin binds the receptor on dermal Langerhans cells, phospholipase A2 is activated, arachidonic acid is released, and cyclooxygenase-1 produces prostaglandin D2 (PGD2). PGD2 then activates DP1 and DP2 receptors on cutaneous vasculature, producing the characteristic vasodilation, warmth, redness, and pruritus.
Two important consequences flow from this mechanism:
- NR and NMN do not activate GPR109A because GPR109A is specific to the nicotinic acid (carboxylic acid) form. Nicotinamide and its derivatives (NAM, NR, NMN) have the amide instead of the carboxylic acid and do not bind GPR109A. Hence they do not flush.
- Aspirin reduces the niacin flush because COX-1 inhibition reduces PGD2 production. In a crossover trial in 148 healthy men, aspirin 650 mg taken 30 minutes before or with extended-release niacin reduced flushing incidence, intensity and duration (Cefali and colleagues, 2007). Tolerance also develops with chronic dosing.
Approaches described for reducing the flush include low starting doses (100–250 mg) increased gradually, aspirin, extended-release formulations (which spread the flush over time but are associated with higher hepatotoxicity risk), and the "no-flush" form inositol hexaniacinate, for which data on lipid and NAD+ effects are mixed.
NR and NMN raise NAD+ without the GPR109A flush.
The Methylation Cofactor Debate (Brenner Critique)
Charles Brenner has been the most prominent voice raising the concern that chronic high-dose NMN or NR supplementation depletes the body's methyl donor pool. The mechanism:
- NAD+-consuming enzymes (sirtuins, PARPs, CD38) release nicotinamide (NAM) as a byproduct of their reactions
- NAM inhibits sirtuins in the test tube (in cells it can act as a stimulator)
- To prevent this feedback inhibition, the body methylates NAM (via N-methyltransferase, NNMT) to N1-methylnicotinamide (1-MNA), which is then excreted
- Each NAM methylation consumes one methyl group from S-adenosylmethionine (SAM)
- SAM is the universal methyl donor for hundreds of methylation reactions including DNA methylation, neurotransmitter synthesis, phospholipid synthesis, creatine synthesis, and homocysteine remethylation
- High-dose chronic NMN or NR supplementation is proposed to increase the methylation demand, potentially depleting SAM
- SAM depletion, if it occurred, could elevate homocysteine, alter DNA methylation patterns, and affect neurotransmitter synthesis
The clinical evidence:
- Methyl-donor depletion has not been measured in the NMN trials found for this page; the concern remains theoretical.
- In the NR-SAFE trial, 20 people with Parkinson's disease took NR at 3,000 mg/day or placebo for four weeks; serum homocysteine rose slightly at first in the NR group while the methyl-donor pool stayed intact (Berven and colleagues, 2023).
Some writers propose co-supplementing a methyl donor such as TMG (trimethylglycine, also called betaine), which donates methyl groups to homocysteine to remethylate it to methionine, the precursor of SAM. Whether this changes any outcome in NMN or NR users has not been tested in a published trial found for this page.
The Sinclair NMN Advocacy
David Sinclair's public advocacy for NMN over NR has been one of the most consequential factors in the consumer NAD+ market. Sinclair has said in interviews that he takes about 1 g of NMN daily himself, along with resveratrol, metformin, a statin and vitamin D. He has consistently framed NMN as the more "direct" precursor.
The case for NMN over NR (Sinclair-aligned):
- NMN is one step closer to NAD+ in the salvage pathway than NR
- A 2019 mouse study reported the Slc12a8 transporter takes up NMN directly in the intestine (disputed)
- Much of the mouse data on aging is NMN-centric
- NMN raised muscle insulin sensitivity in prediabetic women (Yoshino Science 2021)
The case for NR over NMN (Brenner-aligned):
- Larger and longer human evidence base for NR specifically
- Argument that NMN must be dephosphorylated to NR before cellular uptake (making them equivalent)
- NR has been studied clinically for longer, and NR has not faced an exclusion like NMN's 2022 one
What the evidence shows: both raise blood NAD+ in the trials that measured it, both have been well tolerated at the doses studied in short trials, and superiority of one over the other has not been established. In the 2026 head-to-head comparison, 14 days of NR or NMN comparably increased circulating NAD+ (Christen and colleagues, 2026; most authors employees of a food and nutrition company). Researchers on both sides have disclosed commercial ties: Sinclair co-founded a company developing a pharmaceutical-grade NMN, and Brenner has advised a company that sells NR.
For the broader Sinclair lab program, see Longevity & Sirtuins.
The FDA NMN Exclusion (2022) and Reversal (2025)
In the United States, NMN's status as a dietary supplement ingredient has been reversed once. The primary documents are FDA letters in public dockets on regulations.gov; the full account, with quotations, is on the site's page FDA Reverses Course: NMN Allowed in Dietary Supplements (2025).
Timeline
- The law — the Food, Drug, and Cosmetic Act excludes from the definition of a dietary supplement any article that was authorized for investigation as a new drug, with substantial clinical investigations instituted and made public, before it was marketed as a supplement or food (the "race to market" clause of section 201(ff)(3)(B)).
- 11 October 2022 — the FDA wrote to a company that had filed a new dietary ingredient notification for NMN that NMN is excluded, because "NMN was not marketed as a dietary supplement, except unlawfully without an NDI notification, or as a food before FDA authorized it for investigation as a new drug." The drug investigation concerned was a drug developer's NMN candidate known by a code name.
- 4 November 2022 — a supplemental response followed, and similar letters went to other firms that had filed NMN notifications.
- March and May 2023 — a dietary-supplement trade association and a natural-health advocacy group filed a citizen petition (docket FDA-2023-P-0872), amended in December 2024; a second trade association filed another petition in May 2023.
- 29 September 2025 — the FDA granted the first petition in part and concluded that NMN "is not excluded from the definition of dietary supplement." The reason was a change in legal interpretation: the agency no longer requires that earlier marketing have been lawful, only that the product was actually sold as a supplement or food in the United States, and it stated that it was "aware of evidence that NMN was marketed as a dietary supplement in the United States as early as 2017," before the drug authorization.
Status as of October 2026
- The September 2025 letter is the agency's final response to the petition; no later primary FDA document reviewed for this page withdraws or changes it. Reports of later FDA letters to individual NMN ingredient makers were not confirmed in a primary document for this page.
- NMN remains a new dietary ingredient, so a supplement containing it generally requires a new dietary ingredient notification to the FDA at least 75 days before marketing, and the letter rejected the argument that "self-GRAS" status removes that requirement.
- The letter states that it is not a safety finding.
- Outside the United States, regulation differs by country; it was not verified against primary documents for this page and is not summarized here.
Supplement quality, including whether a product contains the amount of NMN on its label, is not checked by the FDA before sale.
How Much NAD+ Each Precursor Raises
What the human data show about raising blood NAD+:
- Niacin (NA) — raises NAD+ through the Preiss-Handler pathway; flushing is its most reported side effect
- Niacinamide (NAM) — in the 2026 comparison in 65 healthy adults, 14 days of nicotinamide did not increase circulating NAD+ (Christen and colleagues, 2026)
- NR — raised blood NAD+ in the trials that measured it; comparable to NMN in the 2026 comparison
- NMN — raised blood NAD+ in the trials that measured it; in a dose-ranging trial in 80 healthy middle-aged adults, blood NAD+ was highest at 600 and 900 mg (Yi and colleagues, 2023)
Laboratory work in the 2026 human comparison, and a 2025 mouse study, point to gut-bacterial conversion of oral NR and NMN to nicotinic acid as a main route by which they raise NAD+ (Yaku and colleagues, 2025; Christen and colleagues, 2026). No trial found for this page has shown that any dose of NR or NMN produces a lasting clinical benefit, and no trial has tested combining NR or NMN with intermittent niacin.
What the Trials Found, by Goal
The human evidence for each goal the precursors are discussed for:
By goal
- Blood lipids — niacin lowers LDL and triglycerides and raises HDL, but added to statins it did not reduce cardiovascular events (AIM-HIGH, HPS2-THRIVE)
- Pellagra or niacin deficiency — niacin or niacinamide are the treatments for the deficiency syndrome
- Skin cancer in high-risk patients — niacinamide 500 mg twice daily lowered new non-melanoma skin cancers by 23% over 12 months (ONTRAC)
- Raising NAD+ for healthspan or longevity — NR and NMN raise blood NAD+; no human trial has shown a slowing of aging, and no study has measured lifespan in people
- Cognition — NMN (Igarashi 2022) and NR (Orr 2024) trials did not find a cognitive effect
- Blood pressure — in the Martens 2018 NR trial, blood pressure was exploratory and the changes were not significant after correction for multiple comparisons
- Exercise capacity — in 48 recreational runners, several aerobic measures rose more with NMN at 600 and 1,200 mg/day than with placebo, while VO2max did not change (Liao 2021); in a 2026 trial, NMN at 1,200 mg/day abolished the exercise-induced rise in muscle mitochondrial content
- Insulin sensitivity — NMN 250 mg/day raised muscle insulin sensitivity in 25 women with prediabetes (Yoshino 2021); NR at 2,000 mg/day did not in 40 obese men (Dollerup 2018); meta-analyses of NMN trials found no effect on fasting glucose, insulin, HbA1c or lipids
Tolerance findings
- Flushing — caused by niacin, not reported with NR or NMN
- Glucose-lowering medicines — the effect of NR or NMN in people taking insulin or sulfonylureas has not been studied in the trials found for this page
- Liver — liver toxicity is reported with high-dose and sustained-release niacin
- Gout — niacin raises uric acid and can precipitate gout attacks
- Statins — niacin added to statins did not improve cardiovascular outcomes in trials (AIM-HIGH, HPS2-THRIVE); no interaction between NR/NMN and statins was reported in the trials found for this page
Methylation
- TMG is often proposed alongside chronic high-dose NR or NMN to offset methylation cost; the depletion has not been measured in NMN trials found for this page
Decisions about supplements, especially for people with medical conditions or taking prescription medicines, belong with a clinician.
Safety Findings
- Niacin and the liver — sustained-release formulations and doses above 3 g/day carry a real risk of liver toxicity.
- Niacin and diabetes — niacin can raise blood glucose in people with diabetes.
- Niacin and gout — niacin raises uric acid and can precipitate gout attacks.
- Niacinamide above 3 g/day — liver toxicity has been reported at high doses; SIRT1 inhibition has been shown in the test tube, not in people.
- NR/NMN and methylation — a theoretical concern at chronic high doses; not measured in NMN trials found for this page.
- NMN supplement quality — supplement quality, including whether a product contains the amount of NMN on its label, is not checked by the FDA before sale.
- NR/NMN and glucose-lowering medicines — NMN raised muscle insulin sensitivity in one trial; its effect in people taking insulin or sulfonylureas has not been studied.
- The cancer question — mouse and cell studies report that NMN or NR promoted some cancers or chemotherapy resistance; there are no human data; see Longevity & Sirtuins.
- Pregnancy/breastfeeding — the B3 RDA in pregnancy (18 mg) is a nutritional requirement; the safety of high-dose NR or NMN in pregnancy has not been studied.
- Long-term safety — multi-year effects of any of these precursors at supraphysiologic doses are not yet characterized in humans.
Key Research Papers
- Bieganowski, P., Brenner, C. (2004). Discoveries of Nicotinamide Riboside as a Nutrient and Conserved NRK Genes Establish a Preiss-Handler Independent Route to NAD+ in Fungi and Humans. Cell 117(4), 495–502. — PubMed PMID: 15137942
- Martens, C.R., et al. (2018). Chronic Nicotinamide Riboside Supplementation Is Well-Tolerated and Elevates NAD+ in Healthy Middle-Aged and Older Adults. Nature Communications 9(1), 1286. — doi:10.1038/s41467-018-03421-7
- Grozio, A., et al. (2019). Slc12a8 Is a Nicotinamide Mononucleotide Transporter. Nature Metabolism 1(1), 47–57. — PubMed PMID: 31131364
- Yoshino, J., Baur, J.A., Imai, S. (2018). NAD+ Intermediates: The Biology and Therapeutic Potential of NMN and NR. Cell Metabolism 27(3), 513–528. — doi:10.1016/j.cmet.2017.11.002
- Yoshino, M., et al. (2021). Nicotinamide Mononucleotide Increases Muscle Insulin Sensitivity in Prediabetic Women. Science 372(6547), 1224–1229. — doi:10.1126/science.abe9985
- Pencina, K.M., et al. (2023). MIB-626, an Oral Formulation of a Microcrystalline Unique Polymorph of Beta-Nicotinamide Mononucleotide, Increases Circulating NMN and NAD in a Randomized Clinical Trial. Journals of Gerontology: Series A 78(1), 90–96. — doi:10.1093/gerona/glac049
- Trammell, S.A., et al. (2016). Nicotinamide Riboside Is Uniquely and Orally Bioavailable in Mice and Humans. Nature Communications 7, 12948. — PubMed PMID: 27721479
- Chen, A.C., et al. (2015). A Phase 3 Randomized Trial of Nicotinamide for Skin-Cancer Chemoprevention (ONTRAC). New England Journal of Medicine 373(17), 1618–1626. — PubMed PMID: 26488693
- AIM-HIGH Investigators (2011). Niacin in Patients with Low HDL Cholesterol Levels Receiving Intensive Statin Therapy. New England Journal of Medicine 365(24), 2255–2267. — PubMed PMID: 22085343
- HPS2-THRIVE Collaborative Group (2014). Effects of Extended-Release Niacin with Laropiprant in High-Risk Patients. New England Journal of Medicine 371(3), 203–212. — PubMed PMID: 25014686
- Hwang, E.S., Song, S.B. (2017). Nicotinamide Is an Inhibitor of SIRT1 in Vitro, But Can Be a Stimulator in Cells. Cellular and Molecular Life Sciences 74, 3347–3362. — PubMed PMID: 28417163
- Yang, X., et al. (2025). An Updated Review on the Mechanisms, Pre-Clinical and Clinical Comparisons of Nicotinamide Mononucleotide (NMN) and Nicotinamide Riboside (NR). Food Frontiers 6(2), 630–643. (Not indexed in PubMed; volume, issue and author initial corrected.) — doi:10.1002/fft2.511
- U.S. Food and Drug Administration, Human Foods Program (2025). Response letter to citizen petition on the regulatory status of beta-nicotinamide mononucleotide (NMN), signed 29 September 2025. Docket No. FDA-2023-P-0872. — regulations.gov FDA-2023-P-0872-2754
- U.S. Food and Drug Administration (2022). Letters of 11 October and 4 November 2022 concluding that NMN is excluded from the dietary supplement definition (NDI 1259). — regulations.gov FDA-2022-S-0023-0051
- Gale, E.A., et al. (2004). European Nicotinamide Diabetes Intervention Trial (ENDIT): A Randomised Controlled Trial of Intervention Before the Onset of Type 1 Diabetes. Lancet 363, 925–931. — PubMed PMID: 15043959
- Cefali, E.A., et al. (2007). Aspirin Reduces Cutaneous Flushing After Administration of an Optimized Extended-Release Niacin Formulation. International Journal of Clinical Pharmacology and Therapeutics 45(2), 78–88. — PubMed PMID: 17323787
- Mills, K.F., et al. (2016). Long-Term Administration of Nicotinamide Mononucleotide Mitigates Age-Associated Physiological Decline in Mice. Cell Metabolism 24(6), 795–806. — PubMed PMID: 28068222
- Dollerup, O.L., et al. (2018). A Randomized Placebo-Controlled Clinical Trial of Nicotinamide Riboside in Obese Men: Safety, Insulin-Sensitivity, and Lipid-Mobilizing Effects. American Journal of Clinical Nutrition 108, 343–353. — PubMed PMID: 29992272
- Schmidt, M.S., Brenner, C. (2019). Absence of Evidence That Slc12a8 Encodes a Nicotinamide Mononucleotide Transporter. Nature Metabolism 1, 660–661. — PubMed PMID: 32694648
- Elhassan, Y.S., et al. (2019). Nicotinamide Riboside Augments the Aged Human Skeletal Muscle NAD+ Metabolome and Induces Transcriptomic and Anti-inflammatory Signatures. Cell Reports 28, 1717–1728. — PubMed PMID: 31412242
- Liao, B., et al. (2021). Nicotinamide Mononucleotide Supplementation Enhances Aerobic Capacity in Amateur Runners: A Randomized, Double-Blind Study. Journal of the International Society of Sports Nutrition 18(1), 54. — PubMed PMID: 34238308
- Igarashi, M., et al. (2022). Chronic Nicotinamide Mononucleotide Supplementation Elevates Blood Nicotinamide Adenine Dinucleotide Levels and Alters Muscle Function in Healthy Older Men. npj Aging 8, 5. — PubMed PMID: 35927255
- Yi, L., et al. (2023). The Efficacy and Safety of β-Nicotinamide Mononucleotide (NMN) Supplementation in Healthy Middle-Aged Adults. GeroScience 45(1), 29–43. — PubMed PMID: 36482258
- Berven, H., et al. (2023). NR-SAFE: A Randomized, Double-Blind Safety Trial of High Dose Nicotinamide Riboside in Parkinson's Disease. Nature Communications 14, 7793. — PubMed PMID: 38016950
- Orr, M.E., et al. (2024). A Randomized Placebo-Controlled Trial of Nicotinamide Riboside in Older Adults With Mild Cognitive Impairment. GeroScience 46, 665–682. — PubMed PMID: 37994989
- Chen, F., et al. (2024). Effects of Nicotinamide Mononucleotide on Glucose and Lipid Metabolism in Adults: A Systematic Review and Meta-analysis of Randomised Controlled Trials. Current Diabetes Reports 25, 4. — PubMed PMID: 39531138
- Yaku, K., et al. (2025). Nicotinamide Riboside and Nicotinamide Mononucleotide Facilitate NAD+ Synthesis via Enterohepatic Circulation. Science Advances 11, eadr1538. — PubMed PMID: 40117359
- Christen, S., et al. (2026). The Differential Impact of Three Different NAD+ Boosters on Circulatory NAD and Microbial Metabolism in Humans. Nature Metabolism 8, 62–73. — PubMed PMID: 41540253
- Yang, D.L., et al. (2026). Anti-Inflammatory Effects of Nicotinamide Mononucleotide (NMN) in Human Skeletal Muscle After BFR-Exercise. Journal of the International Society of Sports Nutrition 23, 2632284. — PubMed PMID: 41705654
- Yang, W., et al. (2026). Safety and Metabolism-Related Outcomes of Oral Nicotinamide Mononucleotide Supplementation in Adults: A Systematic Review and Meta-Analysis. Nutrients 18(14), 2251. — PubMed PMID: 42514320
PubMed Topic Searches
Connections
- NAD+ & NMN Overview
- NAD+ Benefits Hub
- NAD+ for Longevity & Sirtuins
- NAD+ for Cognition
- NAD+ for Energy & Mitochondria
- Vitamin B3 (Niacin)
- Niacin & Cholesterol
- Pellagra & Niacin Deficiency
- All Antioxidants
- CoQ10
- NAC
- Glutathione
- Alpha Lipoic Acid
- Methylene Blue
- Longevity Protocols
- Cholesterol Management
- Cardiovascular Disease
- Insulin Resistance
- History