Niacin and Cholesterol Management
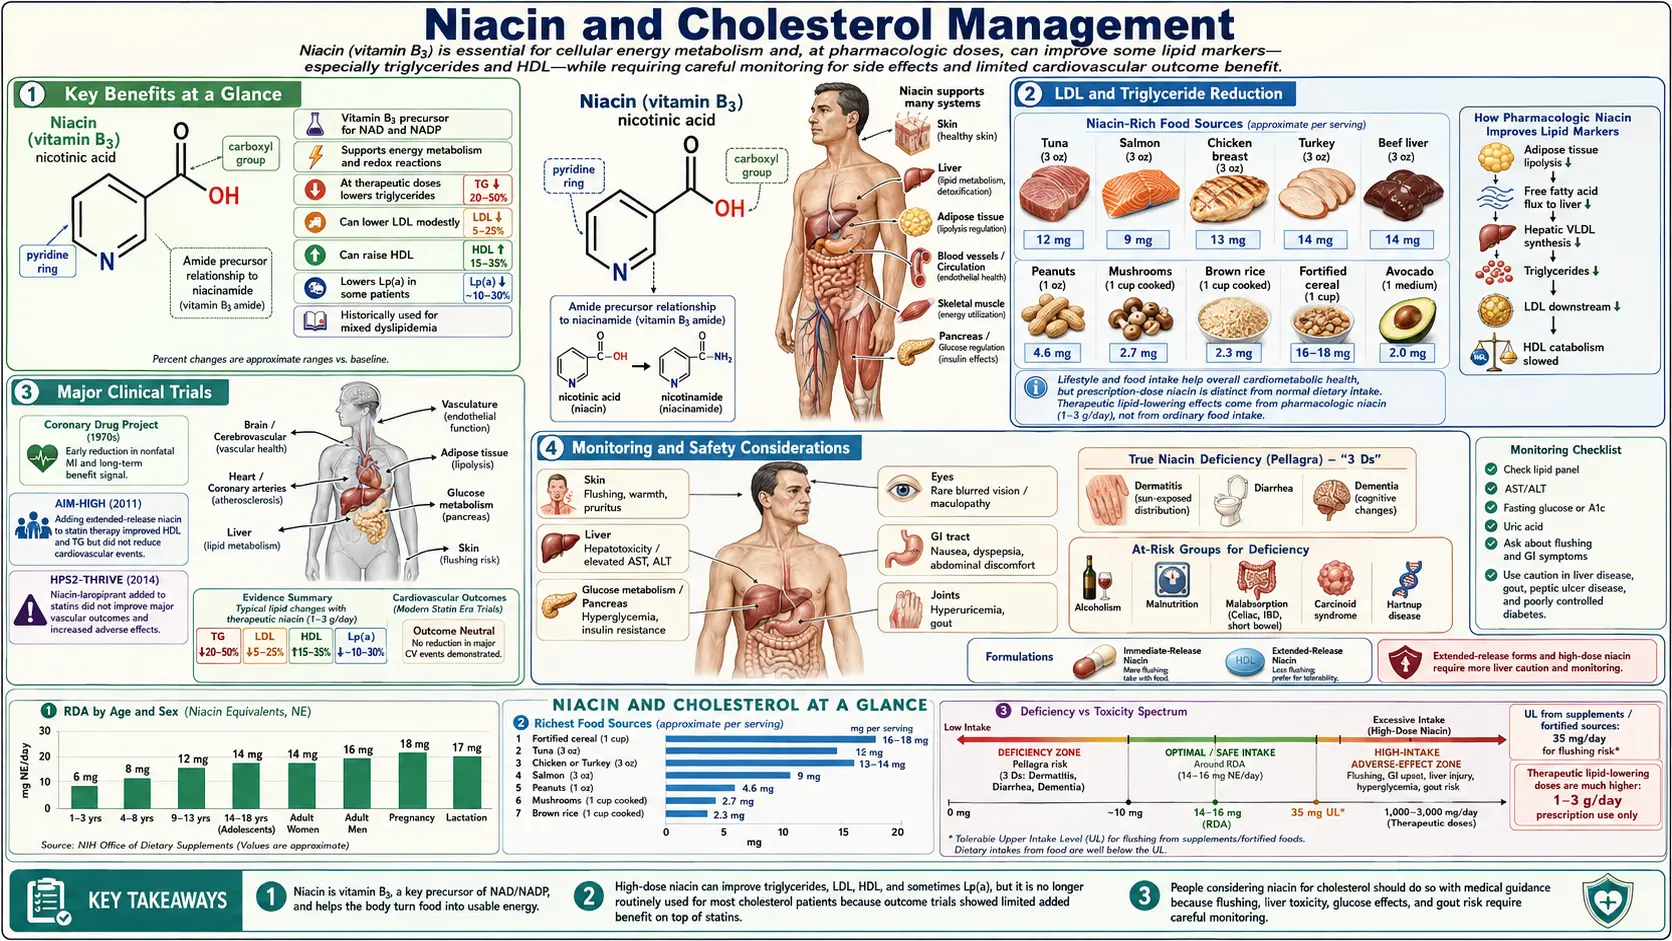
Niacin (vitamin B3) has a long and distinguished history in lipid management, dating back to the 1950s when it became the first lipid-lowering agent shown to reduce cardiovascular events. Despite the rise of statins and other modern therapies, niacin remains one of the most effective agents for raising high-density lipoprotein (HDL) cholesterol and continues to occupy an important, if debated, role in cardiovascular medicine.
Table of Contents
- Key Benefits at a Glance
- Nicotinamide Adenine Dinucleotide and NADP+ Biochemistry
- High-Density Lipoprotein-Raising Mechanism
- Low-Density Lipoprotein and Triglyceride Reduction
- The GPR109A Receptor and Niacin Flush
- Extended-Release vs. Immediate-Release Niacin
- Major Clinical Trials
- Current Clinical Recommendations
- Comparison with Statins
- Monitoring and Safety Considerations
- Key Research Papers
- Connections
- Featured Videos
Key Benefits at a Glance
- Raises high-density lipoprotein cholesterol 15–35% — more than statins or fibrates; cholesteryl ester transfer protein (CETP) inhibitors raise it further (anacetrapib by 104% in the 2017 REVEAL trial).
- Lowers low-density lipoprotein (LDL) cholesterol 5–25% via inhibition of hepatic DGAT2 and reduced very-low-density lipoprotein (VLDL) output.
- Reduces triglycerides 20–50% through suppression of adipocyte lipolysis and hepatic very-low-density lipoprotein assembly.
- Lowers lipoprotein(a) 10–30% — one of very few agents that meaningfully reduces this genetically determined risk factor.
- Shifts low-density lipoprotein to larger, less atherogenic particles improving overall lipoprotein profile.
- Long outcome history — the Coronary Drug Project (1975) showed 27% fewer nonfatal MIs and 11% lower 15-year mortality on immediate-release niacin.
- Cost-effective compared to newer PCSK9 inhibitors for select indications.
- Useful in statin-intolerant patients when alternative lipid-lowering therapy is required.
Nicotinamide Adenine Dinucleotide and NADP+ Biochemistry
Niacin serves as the precursor to two essential coenzymes that drive hundreds of metabolic reactions throughout the body:
- Nicotinamide adenine dinucleotide (NAD+) — functions primarily as an electron carrier in catabolic (energy-releasing) reactions, including glycolysis, the citric acid cycle, and mitochondrial oxidative phosphorylation. Nicotinamide adenine dinucleotide is also a critical substrate for sirtuins, poly(ADP-ribose) polymerases (PARPs), and CD38, linking niacin status to DNA repair, gene expression, and cellular aging.
- Nicotinamide adenine dinucleotide phosphate (NADP+) — the phosphorylated form participates in anabolic (biosynthetic) reactions, including fatty acid synthesis, cholesterol synthesis, and the regeneration of reduced glutathione, a key cellular antioxidant.
The dual roles of nicotinamide adenine dinucleotide and NADP+ in both energy metabolism and lipid biosynthesis explain why niacin status has far-reaching effects on cholesterol homeostasis. When pharmacological doses of niacin are administered, the surplus availability of these coenzymes shifts hepatic lipid metabolism in ways that produce measurable changes in circulating lipoproteins.
High-Density Lipoprotein-Raising Mechanism
Niacin is one of the most effective drugs in routine use for raising high-density lipoprotein cholesterol. At therapeutic doses (1,000 to 2,000 mg per day), niacin can increase high-density lipoprotein cholesterol (HDL-C) levels by 15 to 35 percent, surpassing the high-density lipoprotein-raising capacity of statins and fibrates. CETP inhibitors raise it further: in the 2017 REVEAL trial of 30,449 patients, anacetrapib raised mean high-density lipoprotein cholesterol by 43 mg/dL, a relative difference of 104%.
The mechanisms by which niacin elevates high-density lipoprotein include:
- Reduced hepatic uptake of apolipoprotein A-I (apoA-I) — niacin decreases the clearance of apoA-I, the primary protein component of high-density lipoprotein particles, without affecting the synthetic rate. This results in longer circulating half-life of high-density lipoprotein particles.
- Inhibition of cholesteryl ester transfer protein (CETP) activity — niacin reduces the transfer of cholesteryl esters from high-density lipoprotein to very-low-density lipoprotein and low-density lipoprotein, preserving cholesterol content within high-density lipoprotein particles.
- Increased ABCA1 expression — niacin upregulates the adenosine triphosphate-binding cassette transporter A1, promoting cholesterol efflux from peripheral tissues to nascent high-density lipoprotein particles, a critical step in reverse cholesterol transport.
Low-Density Lipoprotein and Triglyceride Reduction
Beyond its high-density lipoprotein effects, niacin produces clinically meaningful reductions in atherogenic lipoproteins:
- Low-density lipoprotein cholesterol reduction of 5 to 25 percent — niacin inhibits diacylglycerol acyltransferase 2 (DGAT2) in hepatocytes, reducing triglyceride synthesis and consequently decreasing the production of very-low-density lipoprotein, the precursor to low-density lipoprotein.
- Triglyceride reduction of 20 to 50 percent — by inhibiting adipocyte lipolysis through the GPR109A receptor, niacin reduces the flux of free fatty acids to the liver, limiting the substrate available for hepatic triglyceride synthesis.
- Lipoprotein(a) reduction of 10 to 30 percent — niacin remains one of the very few agents capable of lowering Lp(a), an independent and genetically determined risk factor for atherosclerotic cardiovascular disease. The mechanism involves reduced hepatic synthesis of apolipoprotein(a).
The GPR109A Receptor and Niacin Flush
The GPR109A receptor (also known as HM74A or HCAR2) is a G-protein-coupled receptor expressed on adipocytes, immune cells, and dermal Langerhans cells. Niacin binds this receptor with high affinity, and this interaction mediates both therapeutic and adverse effects:
- Adipocyte effects — activation of GPR109A on fat cells inhibits hormone-sensitive lipase, reducing lipolysis and lowering circulating free fatty acid levels. This is a primary mechanism for triglyceride and very-low-density lipoprotein reduction.
- Flush mechanism — activation of GPR109A on dermal Langerhans cells triggers the release of prostaglandin D2 (PGD2) and prostaglandin E2 (PGE2), which act on dermal blood vessels to cause vasodilation. This produces the characteristic niacin flush: warmth, redness, tingling, and itching of the skin, most prominent on the face, neck, and upper trunk.
Managing the Niacin Flush
The flush is the most common reason patients discontinue niacin therapy. Strategies to reduce flushing include:
- Aspirin pre-treatment — taking 325 mg of aspirin 30 minutes before niacin blocks prostaglandin synthesis and can reduce flush severity by 30 to 40 percent.
- Gradual dose titration — starting at 250 to 500 mg daily and increasing slowly over 4 to 8 weeks allows tachyphylaxis (tolerance) to develop.
- Taking niacin with food — consuming niacin with a meal, particularly one containing some fat, slows absorption and reduces peak plasma levels.
- Flush triggers — the extended-release niacin label states that alcohol, hot drinks and spicy foods taken around the time of a dose may increase flushing and itching.
- Extended-release formulations — these produce a more gradual rise in plasma niacin levels, reducing flush intensity compared to immediate-release forms.
Extended-Release vs. Immediate-Release Niacin
The formulation of niacin significantly affects both its efficacy profile and its side effect burden:
- Immediate-release (crystalline) niacin — produces rapid, high peak plasma levels that preferentially activate the GPR109A pathway. This formulation causes the most intense flushing but carries the lowest risk of hepatotoxicity. It is the form used in the Coronary Drug Project, the trial that first demonstrated cardiovascular benefit.
- Extended-release (ER) niacin — absorbed more slowly, producing lower peak levels and reduced flushing. Extended-release niacin is sold as a prescription product. The slower absorption shifts metabolism toward the amidation pathway, which can increase the risk of hepatotoxicity at high doses.
- Sustained-release (SR) niacin — older over-the-counter formulations with very slow absorption. These carry the highest risk of hepatotoxicity and are generally not recommended for lipid management. Cases of fulminant hepatic failure have been reported, particularly when patients switch from IR to SR niacin at equivalent doses.
The three things sold as “niacin” that will not do this
This is the most common and most expensive mistake readers make, so it gets its own section.
- “Flush-free” or “no-flush” niacin is inositol hexanicotinate — six niacin molecules bound to an inositol core. It does not flush because it is barely broken down into free nicotinic acid in the body, and for exactly that reason it does not change lipids either. A published case report follows a coronary-disease patient who bought flush-free niacin instead of the prescribed extended-release product, saw no significant change in his lipids, and got the expected response only after switching. On this evidence, a product promising the lipid benefit without the flush delivers neither.
- Niacinamide (nicotinamide) does not lower cholesterol. It is an excellent form for treating and preventing pellagra, it is the form studied in dermatology for skin-cancer chemoprevention, and it does not flush — because it does not activate GPR109A. It is not a lipid drug, and a supplement labeled “vitamin B3” is very often this form.
- Ordinary dietary niacin is not the drug. The Recommended Dietary Allowance (RDA) is 16 mg NE per day for adult men and 14 mg for women. The lipid effect requires 1,500–2,000 mg — roughly a hundred times that, which is a pharmacological dose that no diet reaches. Foods rich in niacin — liver, tuna, salmon, sardines, chicken and turkey breast, beef, pork, eggs, peanuts, sunflower seeds, mushrooms, avocado, brown rice and other whole grains — are worth eating for many reasons, but eating them is not a low-dose version of this therapy.
Drug interactions worth knowing
- Statins — combining niacin with a statin raises the risk of myopathy and, rarely, rhabdomyolysis. The risk is dose-dependent and was concentrated in the Chinese participants of HPS2-THRIVE, who had roughly a ten-fold higher myopathy rate than European participants on the same regimen. The label calls for watching for muscle pain, tenderness or weakness, particularly in the first months and after any dose increase; muscle pain with dark urine is a sign of rhabdomyolysis that hospitals treat as urgent.
- Bile-acid sequestrants (cholestyramine, colestipol, colesevelam) bind niacin in the gut. The label lists taking the sequestrant at least 4 to 6 hours before niacin.
- Blood-pressure medication and alcohol both amplify niacin’s vasodilation, and the combination can produce genuine dizziness or a faint on standing. Alcohol also worsens flushing and adds to liver risk.
- Diabetes medication — niacin raises fasting glucose and hemoglobin A1c, so insulin or oral agent doses often need revisiting after a niacin dose increase.
- Allopurinol and gout therapy — niacin competes with uric acid for renal excretion and can precipitate an attack in someone already prone to one.
- Anticoagulants and antiplatelets — the excess bleeding seen in HPS2-THRIVE is a reason for extra caution rather than a proven interaction, but it belongs on the list.
Major Clinical Trials
Coronary Drug Project (1975)
The Coronary Drug Project randomized 8,341 men aged 30 to 64 with a prior myocardial infarction to one of five lipid-influencing drugs or placebo. Immediate-release niacin at 3 g/day reduced definite nonfatal recurrent myocardial infarction (MI) by about 27 percent — but, as the investigators stated plainly, it did not reduce total mortality during the trial. The famous mortality result came later: when the surviving men were traced at a mean of 15 years, nearly 9 years after the drug had been stopped, all-cause mortality in the niacin group was 11 percent lower than placebo (52.0% versus 58.2%, P=0.0004). That is a genuine and much-cited finding, and it is also a long-term follow-up of an open cohort, in an era with no statins, no angiotensin-converting enzyme inhibitors (ACE inhibitors), and far less revascularization. It established niacin as a legitimate cardiovascular therapy decades before the statin era; it does not establish that adding niacin to modern therapy helps, which is exactly the question the two trials below were built to answer.
AIM-HIGH Trial (2011)
The Atherothrombosis Intervention in Metabolic Syndrome with Low high-density lipoprotein/High Triglycerides trial tested whether adding extended-release niacin (1,500 to 2,000 mg/day) to simvastatin in patients with established cardiovascular disease would reduce events. All 3,414 patients received simvastatin 40–80 mg (plus ezetimibe if needed) to hold low-density lipoprotein between 40 and 80 mg/dL. Niacin did what it is supposed to do to the lipid panel: median high-density lipoprotein rose from 35 to 42 mg/dL, triglycerides fell from 164 to 122 mg/dL, and low-density lipoprotein fell further still. The trial was nonetheless stopped after a mean of 3 years for lack of efficacy — no incremental benefit over statin therapy alone, and a numerically higher rate of ischemic stroke in the niacin arm that did not reach statistical significance. Two fair criticisms are usually raised: the control group received a token 50 mg of immediate-release niacin to mimic flushing and preserve blinding, and background low-density lipoprotein control was already excellent, leaving little room to improve. Neither criticism produces a benefit that was not there.
HPS2-THRIVE Trial (2014)
The Heart Protection Study 2 – Treatment of high-density lipoprotein to Reduce the Incidence of Vascular Events enrolled over 25,000 patients and tested extended-release niacin combined with laropiprant (a prostaglandin D2 receptor antagonist to reduce flushing) added to statin therapy. Over a median 3.9 years, low-density lipoprotein was 10 mg/dL lower and high-density lipoprotein 6 mg/dL higher on niacin — and major vascular events were not reduced (13.2% versus 13.7%; rate ratio 0.96, 95% confidence interval (CI) 0.90–1.03, P=0.29). What the trial did find was harm, at a scale that ends the argument for routine use: serious disturbances of diabetes control (absolute excess 3.7 percentage points), new diabetes diagnoses (1.3 points), and — unexpectedly — excess infection (1.4 points) and excess bleeding (0.7 points), alongside gastrointestinal (1.0), musculoskeletal (0.7) and skin (0.3) events. The honest caveat is that this trial tested niacin plus laropiprant, and laropiprant cannot be fully exonerated; but laropiprant had shown no such signal in its own earlier studies, the excess infection and bleeding are consistent with what niacin does, and no trial has since shown that niacin alone is safe in this setting. The manufacturer withdrew the combination product worldwide after these results.
Current Clinical Recommendations
In light of the AIM-HIGH and HPS2-THRIVE results, the role of niacin in lipid management has been substantially narrowed:
- Not a first-line therapy — statins remain the cornerstone of lipid-lowering treatment for cardiovascular risk reduction.
- Limited add-on role — niacin is sometimes used in patients with persistent dyslipidemia despite maximally tolerated statin therapy, particularly those with low high-density lipoprotein, elevated triglycerides, or elevated Lp(a).
- Statin-intolerant patients — niacin may serve as an alternative in patients who cannot tolerate any statin, though newer agents such as PCSK9 inhibitors and bempedoic acid have largely supplanted this role.
- Lp(a) reduction — until specific Lp(a)-lowering therapies (such as antisense oligonucleotides) become widely available, niacin remains one of the few options for patients with markedly elevated Lp(a).
Comparison with Statins
Understanding the distinct profiles of niacin and statins helps clarify their respective roles:
- Low-density lipoprotein reduction — statins are far superior, achieving 30 to 55 percent low-density lipoprotein reduction compared to niacin's 5 to 25 percent.
- High-density lipoprotein elevation — niacin is superior, raising high-density lipoprotein by 15 to 35 percent compared to statins' 5 to 15 percent.
- Triglyceride reduction — both are effective; niacin may achieve modestly greater reductions in patients with very high triglycerides.
- Lp(a) lowering — niacin lowers Lp(a) by 10 to 30 percent; statins have minimal or no effect and may slightly increase Lp(a) levels.
- Cardiovascular outcome evidence — statins have overwhelming outcome trial evidence supporting their use; niacin's outcome data are mixed, with early positive results (Coronary Drug Project) not confirmed in the modern statin-treated population.
- Safety profile — statins are generally well-tolerated with myalgia as the most common complaint; niacin carries risks of flushing, hepatotoxicity, hyperglycemia, hyperuricemia, and gastrointestinal disturbance.
Monitoring and Safety Considerations
Therapeutic doses of niacin come with regular laboratory monitoring:
- Liver function tests — the extended-release niacin label lists checking liver enzymes (transaminases) before treatment begins, every 6 to 12 weeks for the first year and about every 6 months after that, and stopping the drug if they rise to 3 times the upper limit of normal and stay there, or come with nausea, fever or malaise.
- Fasting glucose and hemoglobin A1c — niacin can worsen insulin resistance and glycemic control, particularly in patients with diabetes or prediabetes.
- Uric acid levels — niacin competes with uric acid for renal tubular excretion, potentially precipitating gout in susceptible individuals.
- Lipid panel — rechecked 6 to 8 weeks after each dose adjustment to see the response.
Key Research Papers
- Coronary Drug Project Research Group. Clofibrate and niacin in coronary heart disease. JAMA. 1975;231(4):360-381. — PubMed PMID: 1088963
- Canner PL, Berge KG, Wenger NK, et al. Fifteen year mortality in Coronary Drug Project patients: long-term benefit with niacin. J Am Coll Cardiol. 1986;8(6):1245-1255. — PubMed PMID: 3782631
- Norris RB. “Flush-free niacin”: dietary supplement may be “benefit-free”. Prev Cardiol. 2006;9(1):64-65. — PubMed PMID: 16407706
- AIM-HIGH Investigators. Niacin in patients with low HDL cholesterol levels receiving intensive statin therapy. N Engl J Med. 2011;365(24):2255-2267. — PubMed PMID: 22085343 · doi:10.1056/NEJMoa1107579
- HPS2-THRIVE Collaborative Group. Effects of extended-release niacin with laropiprant in high-risk patients. N Engl J Med. 2014;371(3):203-212. — PubMed PMID: 25014686 · doi:10.1056/NEJMoa1300955
- HPS3/TIMI55–REVEAL Collaborative Group; Bowman L, Hopewell JC, Chen F, et al. Effects of anacetrapib in patients with atherosclerotic vascular disease. N Engl J Med. 2017;377(13):1217-1227. — PubMed PMID: 28847206
- PubMed — Niacin HDL mechanism (topic search)
- PubMed — Niacin and Lipoprotein(a) (topic search)
- PubMed — GPR109A receptor and niacin flushing (topic search)Search PubMed
- PubMed — Niacin hepatotoxicity (topic search)
- NIH Office of Dietary Supplements — Niacin Fact Sheet for Health Professionals
- Linus Pauling Institute — Niacin
- Harvard T.H. Chan School of Public Health — Niacin (Vitamin B3)
Connections
- All Vitamins
- Vitamin B3
- Pellagra and Niacin Deficiency
- Cardiovascular Disease
- Vitamin E and Heart Health
- Vitamin K2 and Arterial Calcification
- Vitamin B6 and Homocysteine
- Magnesium and Heart Health
- Inflammatory Markers
- Lipid Panel
- Metabolic Syndrome
- Insulin Resistance
- Diabetes
- Fasting
- Uric Acid
- Gout
- Vitamin E