Nicotinamide Adenine Dinucleotide (NAD+) & Nicotinamide Mononucleotide (NMN) for Cognition and Brain Health
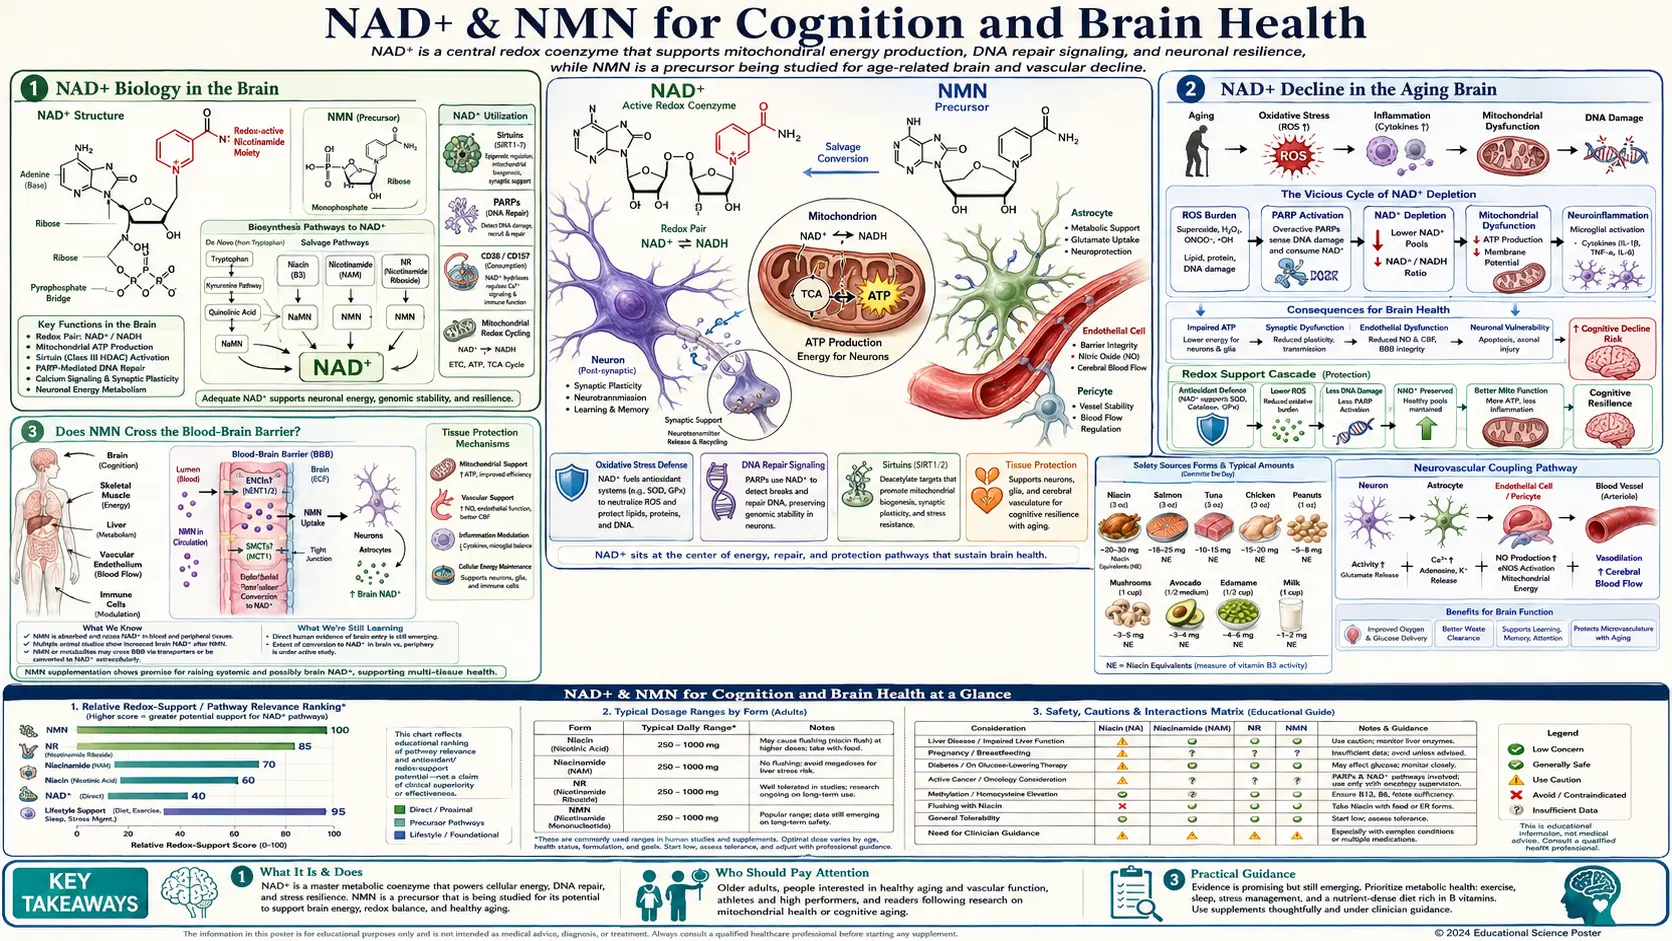
The brain consumes about 20% of total body energy while accounting for only 2% of body weight, making it acutely dependent on the nicotinamide adenine dinucleotide (NAD+)/reduced nicotinamide adenine dinucleotide (NADH) electron-carrier system that powers oxidative phosphorylation in neurons. A magnetic-resonance study in healthy volunteers found lower brain nicotinamide adenine dinucleotide and higher reduced nicotinamide adenine dinucleotide with age, and the mouse evidence for nicotinamide adenine dinucleotide repletion in the brain is extensive. The human cognitive trials, however, are small and short, and none has found a cognitive effect so far: nicotinamide mononucleotide (NMN) and nicotinamide riboside (NR) raise blood nicotinamide adenine dinucleotide, but cognition did not change in the trials that measured it. This deep-dive walks through the brain biology of nicotinamide adenine dinucleotide, the blood-brain barrier question, the mouse studies, the Parkinson's NADPARK pilot, and what the published human trials found.
Table of Contents
- Nicotinamide Adenine Dinucleotide Biology in the Brain
- Nicotinamide Adenine Dinucleotide Decline in the Aging Brain
- Does Nicotinamide Mononucleotide Cross the Blood-Brain Barrier?
- Neurovascular Coupling and Cerebral Blood Flow
- Alzheimer's Mouse Models
- Parkinson's Disease Trials (NADPARK)
- Human Cognitive Trials — What They Found
- Neuroinflammation and Microglia
- The Gut-Brain Axis
- Doses and Timing Used in Trials
- Combinations Discussed — Methylene Blue, B Vitamins, Omega-3
- Safety Findings and Open Questions
- Key Research Papers
- Connections
- Featured Videos
Nicotinamide Adenine Dinucleotide Biology in the Brain
The brain is the most metabolically expensive tissue per gram in the human body. Neurons fire at high frequency, maintain steep ionic gradients across their membranes, and rely almost exclusively on oxidative phosphorylation in mitochondria for adenosine triphosphate (ATP) supply. Every step of this metabolism — glycolysis to pyruvate, pyruvate to acetyl-CoA via pyruvate dehydrogenase, the tricarboxylic acid cycle, the electron transport chain — requires nicotinamide adenine dinucleotide as either a substrate or an electron carrier.
Beyond energy metabolism, nicotinamide adenine dinucleotide in the brain serves additional roles unique to neural tissue:
- Synaptic plasticity — SIRT1 in neurons regulates the expression of brain-derived neurotrophic factor (BDNF), CREB-mediated transcription, and other components of the long-term potentiation machinery that underlies learning and memory.
- Microglial homeostasis — microglia, the brain's resident immune cells, switch between resting (M2-like) and activated (M1-like) states. Nicotinamide adenine dinucleotide availability and SIRT1/SIRT3 activity bias this switching toward the resting, non-inflammatory state.
- Cerebrovascular regulation — endothelial cells lining cerebral microvessels depend on nicotinamide adenine dinucleotide/sirtuin signaling for nitric oxide production and proper neurovascular coupling (the matching of blood flow to local neural activity).
- Amyloid-beta and tau clearance — autophagy, which clears misfolded proteins including amyloid-beta and tau, is partly regulated by SIRT1-mediated deacetylation of autophagy proteins. Reduced nicotinamide adenine dinucleotide silences this pathway.
- Oligodendrocyte function — the cells that produce myelin in the central nervous system depend on SIRT2 (a nicotinamide adenine dinucleotide-dependent sirtuin) for proper myelination.
The implication is that nicotinamide adenine dinucleotide status in the brain influences not just energy production but the structural, vascular, immune, and clearance systems that maintain a healthy brain across decades.
Nicotinamide Adenine Dinucleotide Decline in the Aging Brain
Direct measurement of brain nicotinamide adenine dinucleotide in living humans has historically been difficult because the molecule is rapidly degraded after death and brain biopsy is not done for research. The development of in-vivo magnetic resonance spectroscopy (MRS) techniques sensitive to nicotinamide adenine dinucleotide has begun to fill this gap. A magnetic-resonance method used in healthy volunteers found age-dependent reductions in brain nicotinamide adenine dinucleotide and total nicotinamide adenine dinucleotide (NAD), with an age-dependent increase in reduced nicotinamide adenine dinucleotide (Zhu and colleagues, 2015).
The pattern fits the wider picture: in aged mice, tissue nicotinamide adenine dinucleotide shows a median drop of about 30% (McReynolds and colleagues, 2021); in people, declines with age have been reported in skin, brain and muscle, while blood data are mixed and a 2026 seven-cohort study found whole-blood nicotinamide adenine dinucleotide stable with age (Trętowicz and colleagues, 2026). A frequently quoted figure of a 50% fall by middle age was not found as a measured human result.
The mechanisms proposed for brain nicotinamide adenine dinucleotide decline, mostly from animal studies, mirror the systemic ones:
- Declining NAMPT activity reduces salvage-pathway nicotinamide adenine dinucleotide synthesis.
- Chronic activation of microglia upregulates CD38, which then consumes nicotinamide adenine dinucleotide directly in the extracellular space and indirectly by depleting nicotinamide mononucleotide.
- Accumulating DNA damage in neurons (oxidative damage to mitochondrial and nuclear DNA) activates PARP, which burns through nicotinamide adenine dinucleotide pools.
- Reduced cerebrovascular blood flow may limit precursor delivery to brain tissue.
Raising brain nicotinamide adenine dinucleotide would require precursors that reach the brain in adequate quantities — which raises the central pharmacokinetic question for any nicotinamide mononucleotide cognitive intervention: does nicotinamide mononucleotide cross the blood-brain barrier?
Does Nicotinamide Mononucleotide Cross the Blood-Brain Barrier?
The blood-brain barrier (BBB) is a selective interface formed by tight junctions between cerebrovascular endothelial cells that restricts the passage of most charged or hydrophilic molecules from blood into brain. Nicotinamide mononucleotide, a charged phosphorylated molecule, would naively be expected to be largely excluded from the brain. The published evidence is more nuanced:
- Direct nicotinamide mononucleotide uptake via Slc12a8 — a 2019 mouse study reported that the gene Slc12a8 encodes a nicotinamide mononucleotide transporter highly expressed in the mouse small intestine (Grozio and colleagues, 2019); other researchers argued that the evidence did not show this (Schmidt and Brenner, 2019). Whether such a transporter carries nicotinamide mononucleotide into the brain has not been established.
- Indirect crossing as nicotinamide riboside (NR) or nicotinamide (NAM) — extracellular phosphatases (such as CD73) dephosphorylate nicotinamide mononucleotide to nicotinamide riboside, which then crosses the BBB more easily and is re-phosphorylated inside the brain. Free nicotinamide (NAM) crosses the BBB readily and can be re-incorporated into the brain nicotinamide adenine dinucleotide pool through the salvage pathway.
- Gut microbiota conversion — in a 2025 mouse study, only a small portion of oral nicotinamide mononucleotide and nicotinamide riboside was directly absorbed; most was converted by gut bacteria to nicotinic acid, which then fed nicotinamide adenine dinucleotide synthesis, mainly in the liver (Yaku and colleagues, 2025). A 2026 human study pointed to the same microbial route (Christen and colleagues, 2026).
Which of these routes matters most for the brain is not settled. Mouse studies have reported effects of nicotinamide mononucleotide on the brain after oral or injected dosing (see the sections below), but the transport route is still debated. In people, oral nicotinamide riboside at 1,000 mg a day for 30 days raised brain nicotinamide adenine dinucleotide measured by magnetic-resonance spectroscopy in patients with Parkinson's disease, with wide variation between individuals (Brakedal and colleagues, 2022).
For human cognition, the open question is magnitude: how much oral nicotinamide mononucleotide at the doses used in trials (250–1,000 mg/day in most) raises brain nicotinamide adenine dinucleotide in living people. Direct measurements remain limited.
Neurovascular Coupling and Cerebral Blood Flow
One of the strongest mechanistic stories for nicotinamide mononucleotide in brain health concerns cerebrovascular function, particularly neurovascular coupling. When a brain region becomes active, local blood vessels dilate to deliver more oxygen and glucose — the basis for fMRI BOLD signal. This coupling depends on endothelial nitric oxide (NO) production and on glial signaling to the vasculature.
Tarantini and colleagues (Redox Biology 2019) showed that nicotinamide mononucleotide supplementation in aged mice restored cerebromicrovascular endothelial function and rescued neurovascular coupling responses. The aged mice receiving nicotinamide mononucleotide showed:
- Improved endothelial NO bioavailability in cerebral microvessels
- Restored hyperemic response to neural activation (the coupling itself)
- Better spatial working memory
- Improved gait coordination
The mechanism appears to involve restoration of mitochondrial function in endothelial cells, reduction of mitochondrial reactive oxygen species (ROS) production, and the resulting preservation of nitric oxide signaling. Aged endothelial cells with nicotinamide adenine dinucleotide depletion produce excess superoxide, which scavenges NO and converts it to peroxynitrite — the same mechanism that contributes to systemic endothelial dysfunction with aging. Nicotinamide mononucleotide replenishment reduces the superoxide and restores NO availability.
Cerebral hypoperfusion is one of the earliest detectable abnormalities in Alzheimer's disease and vascular cognitive impairment, which is why researchers see cerebrovascular function as a possible target. Human data are limited: in 20 older adults with mild cognitive impairment, nicotinamide riboside at 1 g a day for 10 weeks did not change cognition, and a reduction in cerebral blood flow in one network would not have survived correction for multiple comparisons (Orr and colleagues, 2024).
Alzheimer's Mouse Models
Nicotinamide mononucleotide and nicotinamide riboside have been tested in several mouse models of Alzheimer's disease (for example Yao and colleagues, 2017; Long and colleagues, 2015; Hou and colleagues, 2018 and 2021). Findings reported across these mouse studies include:
- Reduced amyloid-beta plaque burden in the cortex and hippocampus
- Reduced tau hyperphosphorylation
- Improved performance on the Morris water maze (a hippocampal-dependent spatial learning test)
- Reduced microglial activation and pro-inflammatory cytokine production
- Restored mitochondrial function in cortical neurons
- Reduced neuronal apoptosis in the hippocampal CA1 region
The mechanistic interpretation typically invokes SIRT1 activation: SIRT1 deacetylation of APP (amyloid precursor protein) and BACE1 (the enzyme that cleaves APP to generate amyloid-beta) shifts processing away from the amyloidogenic pathway. SIRT1 deacetylation of tau reduces its propensity to hyperphosphorylate and aggregate. SIRT1 deacetylation of NF-kB reduces microglial pro-inflammatory activation.
The standard caveat applies: Alzheimer's mouse models have a long history of yielding interventions that work beautifully in the mouse and fail in humans. The transgenic mice overexpress mutant human APP at levels far beyond what occurs in sporadic human Alzheimer's, the time course of disease is compressed into months rather than decades, and the inflammatory milieu of aged mouse brain differs substantially from aged human brain. The mouse data show that the SIRT1/nicotinamide adenine dinucleotide axis can influence amyloid biology in mice; they are not evidence that nicotinamide mononucleotide treats Alzheimer's in humans.
Parkinson's Disease Trials (NADPARK)
The NADPARK trial (Brakedal and colleagues, 2022) was a double-blind phase I trial in which 30 newly diagnosed, untreated patients with Parkinson's disease took nicotinamide riboside (NR) 1,000 mg/day or placebo for 30 days. It measured brain nicotinamide adenine dinucleotide by phosphorus magnetic-resonance spectroscopy, nicotinamide adenine dinucleotide-related metabolites in cerebrospinal fluid, cerebral metabolism by PET, and clinical scores.
Results reported in the paper:
- Nicotinamide riboside was well tolerated and produced a significant but variable increase in brain nicotinamide adenine dinucleotide levels and in related metabolites in the cerebrospinal fluid
- Nicotinamide riboside recipients whose brain nicotinamide adenine dinucleotide rose showed altered cerebral metabolism on PET, and this was associated with mild clinical improvement; the trial was a safety and biomarker study, not powered to detect clinical efficacy
- Nicotinamide riboside lowered inflammatory cytokines in serum and cerebrospinal fluid
Two of the authors have filed a patent application on the use of nicotinamide riboside in Parkinson's disease. The follow-up NR-SAFE trial randomized 20 patients to nicotinamide riboside 1,500 mg twice daily (3,000 mg a day) or placebo for four weeks: there were no moderate or severe adverse events, blood nicotinamide adenine dinucleotide rose up to five-fold, and an improvement in total clinical scores was also associated with a shorter interval since the last levodopa dose (Berven and colleagues, 2023). A larger phase 3 trial of nicotinamide riboside in Parkinson's disease has been registered; its results were not found for this page.
The rationale for studying nicotinamide riboside and nicotinamide mononucleotide in Parkinson's disease: dopaminergic neurons in the substantia nigra are particularly vulnerable to mitochondrial dysfunction (complex I deficiency is a known feature of Parkinson's disease), and nicotinamide adenine dinucleotide supports mitochondrial function in laboratory studies. No disease-modifying treatment for Parkinson's disease has yet been proven, and whether nicotinamide riboside could be one is what the larger trials are testing.
Human Cognitive Trials — What They Found
The published human cognitive trials of nicotinamide adenine dinucleotide precursors through 2026 have not found a cognitive effect:
Igarashi 2022 (Nicotinamide Mononucleotide, healthy older men)
Randomized, double-blind, placebo-controlled trial of nicotinamide mononucleotide 250 mg/day for 6 or 12 weeks in healthy men aged 65 or older: 42 men were randomized, and 12-week data were available for 20 (10 per group). Nicotinamide mononucleotide raised whole-blood nicotinamide adenine dinucleotide and its metabolites. Gait speed and left-hand grip improved only nominally, which the authors said needs validation in larger studies; body composition and overall cognitive function on two standard screening tests did not change. The trial was funded by a nicotinamide mononucleotide manufacturer, which supplied the nicotinamide mononucleotide; three authors were its employees.
Nicotinamide Riboside in mild cognitive impairment (Orr 2024)
In 20 older adults with mild cognitive impairment, nicotinamide riboside at 1 g a day for 10 weeks raised blood nicotinamide adenine dinucleotide 2.6-fold but did not change cognition; a reduction in cerebral blood flow in one network would not have survived correction for multiple comparisons. Nicotinamide riboside was supplied by its manufacturer, and one co-author advises that manufacturer.
Other Nicotinamide Mononucleotide trials in older adults
In 108 older Japanese adults given nicotinamide mononucleotide 250 mg/day or placebo for 12 weeks, in the morning or the afternoon, sleep quality was measured with the Pittsburgh Sleep Quality Index, and significant group-by-time interactions were reported only for sit-to-stand time and drowsiness, not for overall sleep quality; sit-to-stand times improved in all four groups, including placebo, and drowsiness improved in both afternoon groups, with the afternoon nicotinamide mononucleotide group showing the largest effect sizes for sit-to-stand and drowsiness (Kim and colleagues, 2022). In a dose-ranging trial in 80 healthy middle-aged adults, six-minute walking distance increased more with nicotinamide mononucleotide than with placebo (Yi and colleagues, 2023; three authors are employees of chemical-manufacturing companies). Neither trial tested cognition as an outcome.
NADPARK (Parkinson's)
Mild clinical improvement in patients whose brain nicotinamide adenine dinucleotide rose, in a 30-patient safety and biomarker trial (see above section).
Summary
Across the available trials, the pattern is:
- Nicotinamide adenine dinucleotide elevation in blood is consistent in every trial that measured it.
- No trial has found a cognitive effect.
- The trials are small (20 to 108 participants), short (6 to 12 weeks), and in cognitively normal or mildly impaired people — which limits what they can detect.
Larger and longer trials in people with cognitive decline have not yet reported.
Neuroinflammation and Microglia
Chronic low-grade neuroinflammation is a feature of essentially every age-related neurodegenerative disease. Microglia, the brain's resident innate immune cells, become progressively more reactive with age, secreting pro-inflammatory cytokines (tumor necrosis factor-α, interleukin-1 beta (IL-1β), interleukin-6 (IL-6)) that damage neurons and disrupt synaptic function. This microglial reactivity is partly driven by, and partly drives, nicotinamide adenine dinucleotide depletion through CD38 upregulation.
Nicotinamide adenine dinucleotide repletion influences neuroinflammation through several mechanisms:
- SIRT1-mediated NF-kB deacetylation — reduces transcription of inflammatory genes in microglia
- SIRT3 mitochondrial support — reduces mitochondrial reactive oxygen species in microglia, which is a major trigger of NLRP3 inflammasome activation
- Restoration of microglial autophagy — clears damaged organelles and pro-inflammatory protein aggregates
- CD38 substrate competition — while CD38 inhibitors more directly target this enzyme, nicotinamide adenine dinucleotide supplementation indirectly mitigates the consequences of CD38 activity
Mouse studies of neuroinflammation (lipopolysaccharide (LPS) challenge, traumatic brain injury, aged brain, Alzheimer's models) report that nicotinamide mononucleotide and nicotinamide riboside reduced microglial activation markers and brain cytokine levels (for example Hou and colleagues, 2021). In people, nicotinamide riboside lowered inflammatory cytokines in cerebrospinal fluid in the NADPARK trial; whether this affects cognition has not been tested.
The Gut-Brain Axis
An emerging strand of research asks whether the gut microbiome takes part in nicotinamide mononucleotide's effects. In mice, gut bacteria convert most oral nicotinamide mononucleotide and nicotinamide riboside to nicotinic acid, which then feeds nicotinamide adenine dinucleotide synthesis, mainly in the liver (Yaku and colleagues, 2025), and a 2026 human comparison pointed to the same microbial route (Christen and colleagues, 2026).
The gut-brain axis is proposed to connect to cognition through:
- Reduced systemic inflammation when the gut barrier is healthy and microbial diversity is preserved
- Production of beneficial short-chain fatty acids (butyrate, propionate) that cross the BBB and influence microglial polarization
- Vagus nerve signaling from gut to brain that modulates anxiety, mood, and cognitive function
- Neurotransmitter precursor metabolism (tryptophan-serotonin, tyrosine-dopamine) influenced by gut bacterial activity
Whether microbial changes contribute to any cognitive effect of nicotinamide mononucleotide has not been shown in people.
Doses and Timing Used in Trials
The brain-related trials described on this page used these regimens; they are the doses tested, not established effective doses, and none produced a cognitive benefit:
Dose
- Nicotinamide mononucleotide 250 mg/day for 6 or 12 weeks in older men (Igarashi 2022) and for 12 weeks in older Japanese adults (Kim 2022); human nicotinamide mononucleotide trials overall have used 250 to 2,000 mg/day
- Nicotinamide riboside 1,000 mg/day for 10 weeks in mild cognitive impairment (Orr 2024) and for 30 days in Parkinson's disease (Brakedal 2022); 3,000 mg/day for 4 weeks in the NR-SAFE safety trial
Timing
- The one trial that compared morning and afternoon nicotinamide mononucleotide found the largest effect sizes for sit-to-stand time and drowsiness in the afternoon nicotinamide mononucleotide group (Kim 2022). Claims that nicotinamide mononucleotide works best in the morning or on an empty stomach have not been supported by trials.
Duration
- The longest nicotinamide mononucleotide trials in a 2026 safety meta-analysis ran 24 weeks; long-term effects are not known.
- Cognitive change was measured with standard tests in the trials; no trial found a change.
Co-supplements discussed
- TMG — proposed as a methyl donor to offset nicotinamide methylation; the depletion it would offset has not been measured in nicotinamide mononucleotide trials found for this page
- Omega-3 (eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA)) — studied separately for brain health; not tested together with nicotinamide mononucleotide
- Vitamin B12, folate, B6 — involved in one-carbon metabolism and homocysteine; not tested together with nicotinamide mononucleotide
For the broader picture on cognition, diet, exercise, and sleep, see our Dementia page and Alzheimer's Disease page. Decisions about supplements belong with a clinician.
Combinations Discussed — Methylene Blue, B Vitamins, Omega-3
None of these combinations with nicotinamide mononucleotide or nicotinamide riboside has been tested for cognitive benefit in a published human trial found for this page. What each is discussed for:
- Methylene blue — can act as an alternative electron carrier that bypasses Complex I in laboratory studies; the combination with nicotinamide mononucleotide has not been formally studied, though some practitioners use it for cognitive decline.
- Vitamin B12 (methylcobalamin) — required for the methylation cycle; discussed alongside higher-dose nicotinamide mononucleotide/nicotinamide riboside because of the theoretical methyl-donor concern.
- Vitamin B6 (P5P) and folate (methylfolate) — involved in one-carbon metabolism and in keeping homocysteine in check.
- Omega-3 eicosapentaenoic acid/docosahexaenoic acid — docosahexaenoic acid is the most abundant polyunsaturated fatty acid in brain phospholipids; eicosapentaenoic acid has anti-inflammatory effects relevant to neuroinflammation.
- Magnesium glycinate or threonate — magnesium L-threonate raised brain magnesium in rat studies and has been studied for synaptic plasticity.
- Lion's Mane mushroom (Hericium erinaceus) — studied for nerve growth factor effects, a different mechanism from nicotinamide mononucleotide.
- Acetyl-L-carnitine — mitochondrial fatty acid transporter and acetyl group donor for acetylcholine synthesis.
Safety Findings and Open Questions
- The size of the evidence — the existing human cognitive trials are small and short and have not found a cognitive effect.
- Prevention versus established disease — the theoretical case for nicotinamide mononucleotide/nicotinamide riboside in cognition is mainly for prevention in healthy middle-aged and older adults; effects in established dementia, including Alzheimer's and Parkinson's, are even less established.
- Methylation cofactor demand — a theoretical concern for chronic high-dose nicotinamide mononucleotide/nicotinamide riboside, not measured in the nicotinamide mononucleotide trials found for this page; in the NR-SAFE trial at 3,000 mg/day, homocysteine rose slightly at first while the methyl-donor pool stayed intact (see Longevity & Sirtuins for more on the Brenner critique).
- Sleep and time of day — some users report that nicotinamide mononucleotide taken late in the day disturbs sleep; in the one trial that compared morning and afternoon intake, the afternoon nicotinamide mononucleotide group showed the largest reduction in drowsiness, and no nicotinamide mononucleotide effect on overall sleep quality was reported (Kim 2022).
- Long-term unknowns — the brain effects of multi-year nicotinamide mononucleotide supplementation have not been characterized in humans.
- Lifestyle evidence — exercise (particularly aerobic and resistance training), Mediterranean-style diet, social engagement, cognitive challenge, and sleep have a far larger evidence base for cognitive protection than any current supplement, including nicotinamide mononucleotide.
Key Research Papers
- Tarantini, S., et al. (2019). Nicotinamide Mononucleotide (NMN) Supplementation Rescues Cerebromicrovascular Endothelial Function and Neurovascular Coupling Responses and Improves Cognitive Function in Aged Mice. Redox Biology 24, 101192. — doi:10.1016/j.redox.2019.101192
- Brakedal, B., et al. (2022). The NADPARK Study: A Randomized Phase I Trial of Nicotinamide Riboside Supplementation in Parkinson's Disease. Cell Metabolism 34(3), 396–407. — PubMed PMID: 35235774
- Igarashi, M., et al. (2022). Chronic Nicotinamide Mononucleotide Supplementation Elevates Blood Nicotinamide Adenine Dinucleotide Levels and Alters Muscle Function in Healthy Older Men. NPJ Aging 8, 5. — PubMed PMID: 35927255
- Hou, Y., et al. (2018). NAD+ Supplementation Normalizes Key Alzheimer's Features and DNA Damage Responses in a New AD Mouse Model. PNAS 115(8), E1876–E1885. — PubMed PMID: 29432159
- Yao, Z., et al. (2017). Nicotinamide Mononucleotide Inhibits JNK Activation to Reverse Alzheimer Disease. Neuroscience Letters 647, 133–140. — PubMed PMID: 28330719
- Lautrup, S., et al. (2019). NAD+ in Brain Aging and Neurodegenerative Disorders. Cell Metabolism 30(4), 630–655. — PubMed PMID: 31577933
- Long, A.N., et al. (2015). Effect of Nicotinamide Mononucleotide on Brain Mitochondrial Respiratory Deficits in an Alzheimer's Disease-Relevant Murine Model. BMC Neurology 15, 19. — PubMed PMID: 25884176
- Grozio, A., et al. (2019). Slc12a8 Is a Nicotinamide Mononucleotide Transporter. Nature Metabolism 1(1), 47–57. — PubMed PMID: 31131364
- Schultz, M.B., Sinclair, D.A. (2016). Why NAD+ Declines During Aging: It's Destroyed. Cell Metabolism 23(6), 965–966. — PubMed PMID: 27304496
- Hou, Y., et al. (2021). NAD+ Supplementation Reduces Neuroinflammation and Cell Senescence in a Transgenic Mouse Model of Alzheimer's Disease via cGAS-STING. PNAS 118, e2011226118. — PubMed PMID: 34497121
- Zhu, X.H., et al. (2015). In Vivo NAD Assay Reveals the Intracellular NAD Contents and Redox State in Healthy Human Brain and Their Age Dependences. PNAS 112, 2876–2881. — PubMed PMID: 25730862
- McReynolds, M.R., et al. (2021). NAD+ Flux Is Maintained in Aged Mice Despite Lower Tissue Concentrations. Cell Systems 12, 1160–1172. — PubMed PMID: 34559996
- Schmidt, M.S., Brenner, C. (2019). Absence of Evidence That Slc12a8 Encodes a Nicotinamide Mononucleotide Transporter. Nature Metabolism 1, 660–661. — PubMed PMID: 32694648
- Kim, M., et al. (2022). Effect of 12-Week Intake of Nicotinamide Mononucleotide on Sleep Quality, Fatigue, and Physical Performance in Older Japanese Adults. Nutrients 14(4), 755. — PubMed PMID: 35215405
- Yi, L., et al. (2023). The Efficacy and Safety of β-Nicotinamide Mononucleotide (NMN) Supplementation in Healthy Middle-Aged Adults. GeroScience 45(1), 29–43. — PubMed PMID: 36482258
- Berven, H., et al. (2023). NR-SAFE: A Randomized, Double-Blind Safety Trial of High Dose Nicotinamide Riboside in Parkinson's Disease. Nature Communications 14, 7793. — PubMed PMID: 38016950
- Orr, M.E., et al. (2024). A Randomized Placebo-Controlled Trial of Nicotinamide Riboside in Older Adults With Mild Cognitive Impairment. GeroScience 46, 665–682. — PubMed PMID: 37994989
- Yaku, K., et al. (2025). Nicotinamide Riboside and Nicotinamide Mononucleotide Facilitate NAD+ Synthesis via Enterohepatic Circulation. Science Advances 11, eadr1538. — PubMed PMID: 40117359
- Christen, S., et al. (2026). The Differential Impact of Three Different NAD+ Boosters on Circulatory NAD and Microbial Metabolism in Humans. Nature Metabolism 8, 62–73. — PubMed PMID: 41540253
- Trętowicz, M.M., et al. (2026). Human Whole-Blood NAD+ Levels Do Not Vary With Age or Lifestyle Interventions. Nature Metabolism 8, 1282–1290. — PubMed PMID: 42135539
PubMed Topic Searches
Connections
- Nicotinamide Adenine Dinucleotide & Nicotinamide Mononucleotide Overview
- Nicotinamide Adenine Dinucleotide Benefits Hub
- Nicotinamide Adenine Dinucleotide for Longevity & Sirtuins
- Nicotinamide Adenine Dinucleotide for Energy & Mitochondria
- Nicotinamide Adenine Dinucleotide Precursors Compared
- Alzheimer's Disease
- Dementia
- Methylene Blue
- All Antioxidants
- Alpha Lipoic Acid for Neuroprotection
- Coenzyme Q10
- Vitamin B3 (Niacin)
- Vitamin B12
- Magnesium
- Longevity Protocols
- Sleep Hygiene
- History