⚠ Evidence warning: Clinical trials or other evidence do not support the claim that thiamine or benfotiamine, with alpha lipoic acid and acetyl-L-carnitine, slows or modifies Alzheimer's disease. This page keeps it as a report of what people, websites or other media say.
Thiamine for Cognitive Function and Alzheimer's Disease
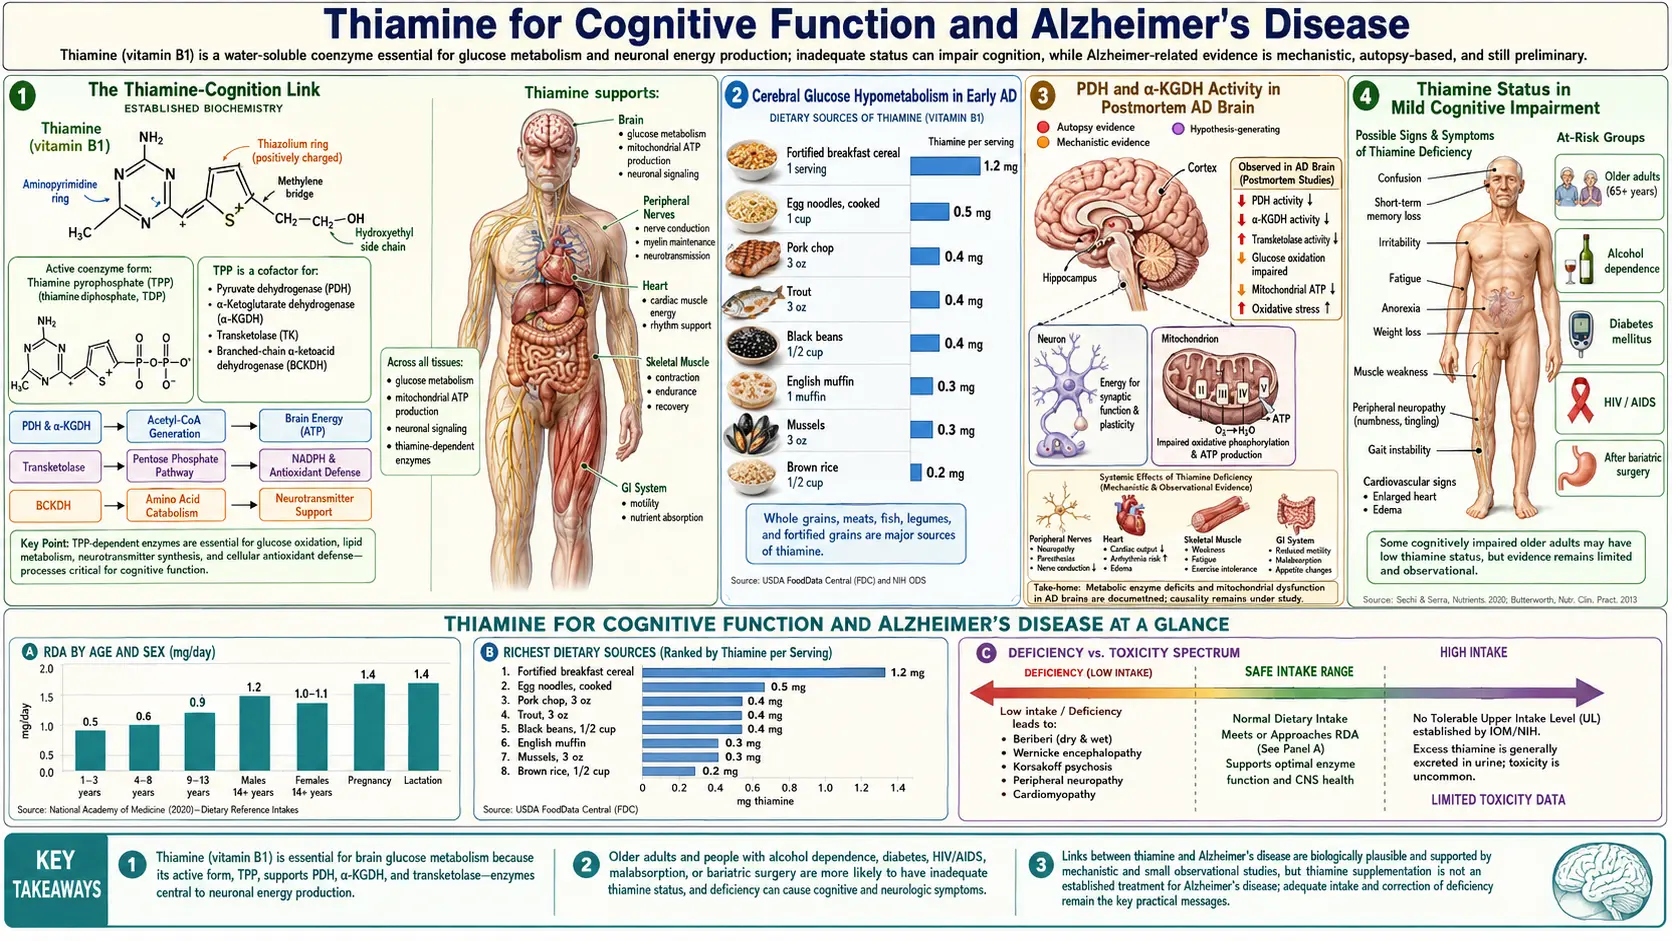
Thiamine deficiency in mild cognitive impairment (MCI) and early Alzheimer's disease is a distinct, separate phenomenon from the full Korsakoff amnesia of acute thiamine collapse. Brain FDG-PET in early AD shows cerebral glucose hypometabolism in the same temporal-parietal regions where postmortem studies show reduced activity of the two thiamine-dependent enzymes pyruvate dehydrogenase (PDH) and α-ketoglutarate dehydrogenase (α-KGDH). This pattern precedes amyloid deposition by years — cerebral energy failure may be a primary driver, not just a downstream consequence. Gibson's 2020 benfotiamine 1-year pilot trial in amnestic MCI and mild AD found a 43% smaller rise in ADAS-Cog scores (not statistically significant) and 77% less worsening on the Clinical Dementia Rating (statistically significant), and a larger phase 2 trial, BenfoTeam (NCT06223360), is under way. This page covers the cerebral-glucose-hypometabolism story, the Gibson trial and its predecessor work, the distinction between subclinical thiamine-related cognitive decline and full Wernicke-Korsakoff, the alcohol-related-cognitive-impairment overlap, and why thiamine + mitochondrial support sits on the same reading list as alpha lipoic acid for cognitive aging.
Table of Contents
- The Thiamine-Cognition Link
- Cerebral Glucose Hypometabolism in Early AD
- PDH and α-KGDH Activity in Postmortem AD Brain
- Thiamine Status in Mild Cognitive Impairment
- The Gibson 2020 Benfotiamine Pilot Trial
- Mechanistic Pathway: From Low TPP to Cognitive Decline
- Alcohol-Related Cognitive Impairment vs Korsakoff
- How This Differs from Wernicke-Korsakoff
- Thiamine + ALA for Cognitive Aging
- Protocols Practitioners Describe for Cognitive Concerns
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Thiamine-Cognition Link
The connection between thiamine and brain function was first established a century ago through the dramatic neuropsychiatric manifestations of severe deficiency — Wernicke encephalopathy and Korsakoff amnestic syndrome. But starting in the 1980s, a separate, more subtle, more common picture began to emerge: subclinical thiamine deficiency contributes to age-related cognitive decline and may play a meaningful role in the early phases of Alzheimer's disease.
This is not the same disease as Korsakoff syndrome. Korsakoff syndrome is the catastrophic dementia that follows acute neurological emergency — it presents abruptly, dramatically, and produces a profound permanent anterograde amnesia. The thiamine-cognition link described here is gradual, subclinical, and clinically resembles the early phases of "normal" aging or mild Alzheimer's disease. The biochemistry is the same (impaired TPP-dependent enzymes) but the dose and timing are different — chronic mild deficiency over years rather than acute severe collapse over weeks.
Three converging lines of evidence support the link:
- FDG-PET imaging — the same temporal-parietal regions that lose glucose uptake in early AD are TPP-enzyme-dependent regions
- Postmortem brain enzyme studies — PDH and α-KGDH activity is reduced in AD-affected brain regions, more than the modest (18–21%) fall in brain TPP measured in one study
- Pilot intervention trials — benfotiamine has shown promising signals in MCI and early AD, with a larger trial underway
The unifying framework: cerebral energy failure (a "brain-as-a-glucose-engine-running-out-of-fuel" story) may be a primary upstream driver of Alzheimer's disease, and thiamine repletion through high-bioavailability forms (benfotiamine, allithiamine) is a candidate disease-modifying intervention. This is in active debate but the supporting evidence base has grown substantially over the past decade.
Cerebral Glucose Hypometabolism in Early AD
FDG-PET (fluorodeoxyglucose positron emission tomography) measures cerebral glucose uptake region by region. In healthy older adults, glucose uptake is roughly uniform across cortical regions. In Alzheimer's disease, distinctive regional patterns of reduced glucose uptake appear, often years before clinical dementia is detectable:
- Posterior cingulate and precuneus — among the earliest regions affected; hypometabolism here can predate clinical AD by 10-15 years in some studies
- Lateral temporal cortex — particularly the temporo-parietal junction
- Parietal association cortex — bilateral, often symmetric
- Lateral prefrontal cortex — later in disease progression
- Relative sparing of primary sensorimotor cortex, occipital cortex, and basal ganglia until late in disease
The pattern is so distinctive that FDG-PET is used clinically to distinguish AD from other dementias (frontotemporal dementia, Lewy body dementia have different regional patterns). Crucially, the hypometabolism appears before significant amyloid plaque deposition becomes visible on amyloid positron emission tomography (PET), and before clinical symptoms become detectable. This temporal precedence raises the question: is impaired glucose metabolism a primary driver of AD, or merely a downstream consequence of amyloid pathology?
The thiamine-cognition framework leans toward the primary-driver interpretation: if TPP-dependent enzymes lose activity, glucose entering the brain cannot be efficiently metabolized to adenosine triphosphate (ATP), regional adenosine triphosphate supply falls, and downstream pathology (synaptic dysfunction, neuronal stress, eventual amyloid and tau deposition) follows. Repleting TPP would, on this model, address the upstream metabolic failure rather than the downstream protein aggregates.
This view is consistent with the otherwise puzzling repeated failure of amyloid-targeting drugs to produce robust clinical benefit in AD trials — if amyloid is downstream of metabolic failure, removing amyloid without addressing the upstream metabolism would predict modest at best clinical benefit, which is exactly what has been observed.
PDH and α-KGDH Activity in Postmortem AD Brain
The pioneering postmortem brain enzyme studies of Gary Gibson and colleagues at the Weill Cornell Burke Neurological Institute documented across several decades of work that:
- α-KGDH activity is reduced in the brains of patients dying with Alzheimer's disease compared to controls — by more than 75% in Gibson's 1988 study and by 57% in Bubber's 2005 study
- PDH activity is reduced, though to a smaller degree — by 41% in the 2005 study, where every change in these mitochondrial enzymes tracked the Clinical Dementia Rating before death (strongest for PDH, correlation r = 0.77)
- The third TPP-dependent enzyme, transketolase, is also reduced — by more than 45% in the 1988 study, which found the decreases in both damaged and relatively undamaged brain areas
- The reductions are most pronounced in the brain regions that show the FDG-PET hypometabolism pattern
- Brain TPP itself is modestly low: in 18 Alzheimer's brains compared with 20 controls (Mastrogiacoma 1996), TPP (thiamine diphosphate) was 18–21% lower in all three cortical areas examined, while free thiamine and the enzymes that make and break down TPP were normal; the authors suggested low brain ATP, which is needed to make TPP, as the cause. The enzyme losses are larger than this TPP drop, suggesting that something beyond simple TPP availability is impairing the enzymes
- The reductions appear early in disease, not just in end-stage tissue
Several mechanisms have been proposed for why these enzymes lose more activity in AD than the modest fall in TPP would explain:
- Oxidative damage to the enzyme proteins themselves — AD brain has elevated markers of oxidative and nitrosative stress, and the lipoamide-dependent enzymes (PDH, α-KGDH, and branched-chain α-ketoacid dehydrogenase (BCKDH)) are particularly susceptible to oxidative inactivation
- Reduced lipoylation — the lipoamide cofactor of these enzymes is depleted in AD brain (interestingly, this is also where alpha lipoic acid mechanism stories intersect)
- Reduced expression of enzyme subunits — transcriptional changes in AD brain reduce production of the enzyme proteins
- Increased demand for repair — functional thiamine deficiency despite normal apparent concentration
The proposed rationale for the Gibson trial: even people with normal blood thiamine might gain from higher-than-normal TPP levels (reachable with benfotiamine or other high-bioavailability forms), by forcing more substrate through the partially-inactivated enzymes.
Thiamine Status in Mild Cognitive Impairment
Several cross-sectional and observational studies have examined thiamine status in patients with mild cognitive impairment (MCI):
- Erythrocyte transketolase activity (the functional thiamine marker) is reduced in patients with MCI compared to age-matched cognitively normal controls in multiple cohorts
- The activation coefficient (the in vitro response to TPP loading) is elevated in MCI, indicating functional thiamine deficiency
- Whole-blood TPP measured by high-performance liquid chromatography (HPLC) shows lower values in MCI patients
- The thiamine-status reduction in MCI is modest in magnitude but consistent in direction across studies
- The thiamine reduction correlates with cognitive scores and with the FDG-PET hypometabolism pattern
It is not yet clear whether thiamine deficiency causes the MCI or whether MCI (with its associated changes in diet, appetite, mood, and brain biochemistry) causes the thiamine deficiency. Both directions are plausible and both are probably operating — a vicious cycle in which subclinical thiamine deficiency drives cognitive decline, which then worsens dietary intake and further reduces thiamine status.
Practitioners who use thiamine in memory care draw a practical conclusion: they check and correct thiamine status in people with MCI or early AD. They point out that supplementation is cheap, its safety record is good, and adequate thiamine status is ordinary supportive care even if any disease-modifying effect turns out to be modest.
The Gibson 2020 Benfotiamine Pilot Trial
The Gibson et al. 2020 study (published in Journal of Alzheimer's Disease) was a randomized, double-blind, placebo-controlled pilot trial of benfotiamine 600 mg/day (300 mg twice daily, per the trial registry NCT02292238) vs placebo for 12 months in 70 people with amnestic MCI or mild AD (34 on benfotiamine, 36 on placebo). The primary outcome was change in the ADAS-Cog (Alzheimer's Disease Assessment Scale - Cognitive subscale). Secondary outcomes were the Clinical Dementia Rating (CDR) and brain glucose uptake on FDG-PET; blood advanced glycation end products (AGE) were an exploratory outcome.
Results:
- Benfotiamine 600 mg/day was well-tolerated; no significant adverse events distinguished it from placebo
- The rise in ADAS-Cog (worsening cognition) was 43% smaller in the benfotiamine group than on placebo; this difference was not statistically significant (p = 0.125)
- Worsening on the Clinical Dementia Rating was 77% smaller on benfotiamine, a statistically significant result (p = 0.034)
- Blood AGE rose less on benfotiamine (p = 0.044)
- The CDR and AGE effects were stronger in patients without the APOEε4 risk allele — suggesting benfotiamine may be more effective in non-genetic AD, or that APOEε4 carriers may need higher doses
- Blood thiamine markers confirmed compliance and adequate absorption
- An exploratory FDG-PET pattern score showed a treatment effect at one year (p = 0.002)
- The study was underpowered to detect a definitive effect but produced sufficient signal to justify a larger phase 2 trial
A larger follow-up trial, BenfoTeam (NCT06223360, phase 2, led by Weill Cornell Medicine), began in March 2024. It enrolled 406 people with early Alzheimer's disease to test benfotiamine (300 mg or 600 mg twice daily) against placebo. It is no longer recruiting, and its estimated completion date is December 2027. (NCT02292238 is the registry entry of the completed 2020 pilot trial.) Results are pending but if positive would represent the first nutritionally-based disease-modifying intervention in AD.
The Gibson trial is an example of how mechanistic and biochemical evidence can drive a rational therapeutic candidate even in the absence of a definitive large trial. Many integrative-medicine and functional-medicine practitioners now recommend benfotiamine 300-600 mg/day for patients with MCI or early AD, based on the favorable risk-benefit balance even pending definitive trial data.
Mechanistic Pathway: From Low TPP to Cognitive Decline
The proposed mechanistic chain from low TPP to cognitive decline runs as follows:
- Reduced intracellular TPP — from inadequate dietary intake, age-related malabsorption, alcohol use, medications that interfere with absorption, or oxidative damage to TPP itself
- Reduced PDH activity — pyruvate cannot efficiently enter the Krebs cycle, glucose is shunted to lactate, cerebral adenosine triphosphate supply drops
- Reduced α-KGDH activity — the rate-limiting Krebs cycle enzyme loses activity, further collapsing adenosine triphosphate production
- Reduced transketolase activity — the pentose phosphate pathway loses flux, generating less reduced nicotinamide adenine dinucleotide phosphate (NADPH) for glutathione recycling and antioxidant defense
- Cerebral energy supply falls — particularly in the temporo-parietal regions that have the highest energy demand and are most vulnerable
- Synaptic dysfunction begins — adenosine triphosphate-dependent vesicle recycling, ion pumping, and neurotransmitter synthesis all suffer
- Oxidative stress rises — both because adenosine triphosphate supply for antioxidant systems falls and because the impaired mitochondria leak more superoxide
- Glutamate excitotoxicity engages — adenosine triphosphate-dependent glutamate uptake fails, N-methyl-D-aspartate (NMDA) receptors fire excessively, calcium floods into neurons
- Cognitive symptoms emerge — first as MCI, then as mild AD, eventually as moderate-to-severe dementia
- Pathologic protein deposition (amyloid, tau) accumulates — possibly secondary to the cumulative metabolic and oxidative stress, possibly through impaired clearance of misfolded proteins
Benfotiamine intervenes early in this chain by driving up intracellular TPP and reactivating the partially-inhibited enzymes. The hope is that this slows or arrests the cascade before it produces irreversible neuronal loss.
Practitioners who follow this framework pair benfotiamine with mitochondrial support like alpha lipoic acid, reasoning that ALA addresses the downstream oxidative-stress and lipoamide-cofactor parts of the same biochemistry that benfotiamine addresses upstream, and they regard the combination as more comprehensive than either alone. No trial has tested the pairing.
Alcohol-Related Cognitive Impairment vs Korsakoff
Chronic alcohol use produces a spectrum of cognitive consequences that includes:
- Subtle executive dysfunction — impaired attention, working memory, decision-making; reversible with abstinence in the early phases
- Mild alcohol-related cognitive impairment — more pronounced but still partially reversible; persists despite abstinence in moderate cases
- Alcohol-related brain damage / alcohol-related dementia — permanent cognitive impairment from cumulative neurotoxicity, frontal lobe atrophy on magnetic resonance imaging (MRI), often partially overlapping with Korsakoff features but not requiring a documented Wernicke episode
- Wernicke-Korsakoff syndrome — the acute-then-chronic catastrophic dementia following acute thiamine collapse, classically with the Wernicke triad followed by Korsakoff amnesia
The first three entities all have a substantial thiamine-deficiency component on top of direct alcohol neurotoxicity. Alcohol impairs thiamine absorption, accelerates urinary loss, depletes liver stores, and substitutes empty calories for thiamine-rich food. Most heavy drinkers have low to borderline thiamine status, and the contribution of thiamine deficiency to alcohol-related cognitive decline is hard to disentangle from direct alcohol neurotoxicity.
In practice, people with a significant alcohol-use history and cognitive concerns are commonly given long-term thiamine supplementation (oral thiamine hydrochloride 100 mg/day or benfotiamine 300 mg/day), particularly during and after abstinence. Some recovery of cognitive function is possible with sustained abstinence + thiamine repletion, even years into chronic alcohol-related cognitive impairment. Continued drinking after thiamine repletion typically does not preserve cognitive function — the direct alcohol neurotoxicity continues regardless.
It is worth noting that alcohol-related cognitive impairment is distinct from Korsakoff syndrome in important ways. Korsakoff is characterized by profound anterograde amnesia, confabulation, and mammillary body atrophy on magnetic resonance imaging — a relatively focal deficit. Alcohol-related dementia tends to be more global, with prominent executive dysfunction, frontal atrophy on magnetic resonance imaging, and impairment across multiple cognitive domains. The two can coexist in the same patient.
How This Differs from Wernicke-Korsakoff
| Feature | Wernicke-Korsakoff | Subclinical Thiamine-Cognition Link |
|---|---|---|
| Onset | Acute, days to weeks | Gradual, months to years |
| Severity of deficiency | Severe, often total store depletion | Mild to moderate, often "low normal" |
| Clinical phenotype | Triad: ophthalmoplegia + ataxia + confusion → profound anterograde amnesia | Resembles MCI / early AD: episodic memory, executive function, processing speed |
| Imaging | Mammillary body atrophy, thalamic atrophy | FDG-PET hypometabolism in temporo-parietal regions |
| Treatment | Parenteral thiamine 500 mg three times daily (TID) acute, then maintenance | Practitioner protocols use oral benfotiamine 300-600 mg/day chronically (600 mg/day in the Gibson trial) and oral thiamine hydrochloride 100 mg/day for prevention |
| Reversibility | Partial; depends on speed of treatment | Possibly modest; mechanism is "slow the decline" rather than "reverse the deficit" |
| Mortality without treatment | ~17-20% | Not directly fatal; contributes to broader cognitive decline mortality |
| Diagnostic approach | Clinical recognition + empirical thiamine; magnetic resonance imaging confirms | Standard cognitive testing + thiamine status (erythrocyte transketolase, whole-blood TPP) |
Both conditions reflect the same biochemistry — impaired TPP-dependent enzyme function — but at very different doses and time scales. Severe acute deficiency produces the Wernicke-Korsakoff phenotype. Chronic mild deficiency over years produces the gradual cognitive decline that resembles aging or early AD. Recognizing the latter requires a different clinical lens than recognizing the former.
Thiamine + ALA for Cognitive Aging
Thiamine and alpha lipoic acid are mechanistically tightly linked in cognitive aging:
- Both target the same enzymes — PDH and α-KGDH both require TPP and lipoamide as cofactors. TPP catalyzes the decarboxylation step; lipoamide (covalently bound to the E2 subunit) carries the acyl group to coenzyme A. If either cofactor is depleted, the enzyme fails. Thiamine repletion drives TPP; lipoic acid drives lipoamide. Together they restore both ends of the cofactor pair.
- Both cross the blood-brain barrier — benfotiamine, allithiamine, and ALA all enter the brain readily, where they can directly support neuronal energy production.
- Both have favorable safety profiles — the combination has been used in integrative cognitive-aging protocols for decades with no significant adverse interaction reported.
- Both can be combined with acetyl-L-carnitine — the Ames-Hagen group at UC Berkeley demonstrated that the ALA + acetyl-L-carnitine combination reversed mitochondrial decline in aged rat brain. Adding benfotiamine to this stack provides the missing TPP support.
- The combination is supported in multiple cognitive-aging protocols — though no trial of the triple combination (benfotiamine + ALA + acetyl-L-carnitine) has been done; its supporters point to the mechanism and to the components' individual evidence bases.
A cognitive-support stack described in integrative practice: benfotiamine 300 mg twice daily (the Gibson trial dose) + alpha lipoic acid 600 mg once daily + acetyl-L-carnitine 1-2 g/day + a comprehensive B-complex + magnesium 200-400 mg/day. Its supporters cite its multiple mechanisms and favorable safety profile; the evidence for the combination specifically rests on mechanistic plausibility rather than head-to-head trial data.
This is not a treatment for established moderate-to-severe AD — the evidence is not strong enough for that claim, and the conventional anti-cholinesterase medications (donepezil, rivastigmine, galantamine) and the newer amyloid-targeting antibodies remain the standard of care. Integrative practitioners describe the benfotiamine + ALA combination as an adjunct for people with MCI, early AD, or cognitive-aging concerns, citing mechanism, safety, and early trial results; the only randomized trial so far tested benfotiamine alone.
Protocols Practitioners Describe for Cognitive Concerns
Integrative and functional-medicine practitioners describe a tiered protocol for people with MCI, early AD, alcohol-related cognitive concerns, or general cognitive-aging interest. Only one element of it, benfotiamine 300 mg twice daily, has been tested in a randomized trial (the Gibson pilot).
Tier 1 (all groups)
- Thiamine HCl 100 mg/day orally, or benfotiamine 300 mg/day for higher bioavailability
- Comprehensive B-complex — ensures adequate B2, B3, B6, B12, folate, biotin (all of which support brain metabolism in coordinated ways)
- Magnesium 200-400 mg/day — required cofactor for thiamine phosphorylation to TPP
- Risk factors addressed — alcohol cessation where relevant, blood-sugar control in diabetes, treatment of sleep apnea where present, regular aerobic exercise
Tier 2 (MCI or early AD)
- Benfotiamine 300 mg twice daily (Gibson trial dose)
- Alpha lipoic acid 600 mg/day (or R-ALA 300 mg/day)
- Acetyl-L-carnitine 1-2 g/day in divided doses
- Omega-3 fatty acids (docosahexaenoic acid (DHA)/eicosapentaenoic acid (EPA)) 2-3 g/day — supports neuronal membrane function
- Vitamin D 2000-4000 international units (IU)/day if levels are low
- B12 (methylcobalamin) 1000-2000 mcg/day if levels are low or borderline
- Hemoglobin A1c (HbA1c) control — the diabetic complications cascade contributes to cognitive decline
Tier 3 (severe baseline disease or strong family history)
- All of Tier 2, plus:
- Fursultiamine (thiamine tetrahydrofurfuryl disulfide, TTFD), an allithiamine-family derivative, 100-300 mg/day — a fat-soluble thiamine derivative that practitioners describe as having the best brain penetration; sometimes used in place of or in addition to benfotiamine for cognitive indications
- Thiamine status testing (erythrocyte transketolase activation coefficient, whole-blood TPP by HPLC) to confirm repletion
- Practitioners report that some people respond well to the protocol and others do not
Its proponents describe the protocol as conservative and supportive rather than aggressive, and as a low-risk way to support the metabolic substrate for brain function. The evidence base does not show that this combination prevents or treats AD.
Cautions
- This is not a substitute for standard AD evaluation and care — a full neurologic evaluation of new cognitive symptoms includes imaging, vascular risk assessment, B12/folate/thyroid screening, and consideration of conventional medications.
- The disease-modifying claim is not yet proven — the Gibson trial showed promising signals but is not definitive. A larger trial is under way. Until it reports, the protocol is supportive rather than proven therapy.
- Mild cognitive impairment has many causes — depression, sleep apnea, medication side effects (anticholinergics, benzodiazepines), thyroid disease, vitamin deficiencies (B12, folate, D), normal pressure hydrocephalus, and others are all possible causes besides AD.
- Severe alcohol use and Wernicke prophylaxis — people with active heavy alcohol use often have hidden (occult) thiamine deficiency, and Wernicke prophylaxis with thiamine by injection (parenteral thiamine) is given before other interventions.
- B6 toxicity from combination products — some products combine benfotiamine with B6 at doses that, taken chronically, can cause B6-induced sensory neuropathy (paradoxically worsening symptoms). The US tolerable upper intake level for vitamin B6 in adults is 100 mg/day.
- Drug interactions are minimal — benfotiamine and ALA do not significantly interact with most cognitive medications (donepezil, memantine, rivastigmine). No significant interaction between them is described.
- Hypoglycemia with diabetes medications — ALA can lower blood glucose; benfotiamine is glucose-neutral. ALA taken with insulin or sulfonylureas adds to their glucose-lowering effect, and low blood sugar can result.
- Magnesium and thiamine — thiamine phosphorylation to TPP requires magnesium. Apparent failure of the protocol may reflect coexisting magnesium deficiency, which is common in older patients.
Key Research Papers
- Gibson GE, Luchsinger JA, Cirio R, et al. (2020). Benfotiamine and Cognitive Decline in Alzheimer's Disease: Results of a Randomized Placebo-Controlled Phase IIa Clinical Trial. J Alzheimers Dis 78(3):989-1010. — PubMed PMID: 33074237
- Gibson GE, Blass JP (2007). Thiamine-dependent processes and treatment strategies in neurodegeneration. Antioxid Redox Signal. — PubMed PMID: 17685850
- Gibson GE et al. (1988). Reduced activities of thiamine-dependent enzymes in the brains and peripheral tissues of patients with Alzheimer's disease. Arch Neurol. — PubMed PMID: 3395256
- Mosconi L et al. (2009). FDG-PET changes in brain glucose metabolism from normal cognition to pathologically verified Alzheimer's disease. Eur J Nucl Med Mol Imaging 36(5):811-22. — PubMed PMID: 19142633
- Pan X et al. (2010). Powerful beneficial effects of benfotiamine on cognitive impairment and beta-amyloid deposition in amyloid precursor protein/presenilin-1 transgenic mice. Brain 133(Pt 5):1342-51. — PubMed PMID: 20385653
- Pan X et al. (2016). Long-term cognitive improvement after benfotiamine administration in patients with Alzheimer's disease. Neurosci Bull 32(6):591-596. — PubMed PMID: 27696179
- Lu'o'ng KV, Nguyen LT (2011). Role of thiamine in Alzheimer's disease. Am J Alzheimers Dis Other Demen 26(8):588-98. — PubMed PMID: 22218733
- Bubber P et al. (2005). Mitochondrial abnormalities in Alzheimer brain: mechanistic implications. Ann Neurol. — PubMed PMID: 15852400
- Mastrogiacoma F et al. (1996). Brain thiamine, its phosphate esters, and its metabolizing enzymes in Alzheimer's disease. Ann Neurol. — PubMed PMID: 8619543
- Ridley NJ et al. (2013). Alcohol-related dementia: an update of the evidence. Alzheimers Res Ther. — PubMed PMID: 23347747
- Sechi G et al. (2016). Advances in clinical determinants and neurological manifestations of B vitamin deficiency in adults. Nutr Rev 74(5):281-300. — PubMed PMID: 27034475
- Karuppagounder SS et al. (2009). Thiamine deficiency induces oxidative stress and exacerbates the plaque pathology in Alzheimer's mouse model. Neurobiol Aging. — PubMed PMID: 18406011
- Benfotiamine in Alzheimer's Disease: A Pilot Study (completed 2020; 71 enrolled). ClinicalTrials.gov registry. — NCT02292238
- A Trial to Evaluate the Safety and Efficacy of Benfotiamine in Patients With Early Alzheimer's Disease (BenfoTeam; 406 enrolled, estimated completion December 2027). ClinicalTrials.gov registry. — NCT06223360
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B1 Overview
- B1 Benefits Hub
- B1 for Wernicke-Korsakoff
- B1 for Beriberi & Cardiac
- Benfotiamine for Diabetic Neuropathy
- Thiamine and Brain Health
- Alpha Lipoic Acid
- ALA for Mitochondria
- ALA for Neuroprotection
- Alzheimer's Disease
- Brain Fog
- Fatigue
- Vitamin B12
- Vitamin B6
- Magnesium
- Detox Protocols
- Deficiency
- Toxicity
- History
- Sources