Thiamine for Beriberi and Cardiac Failure
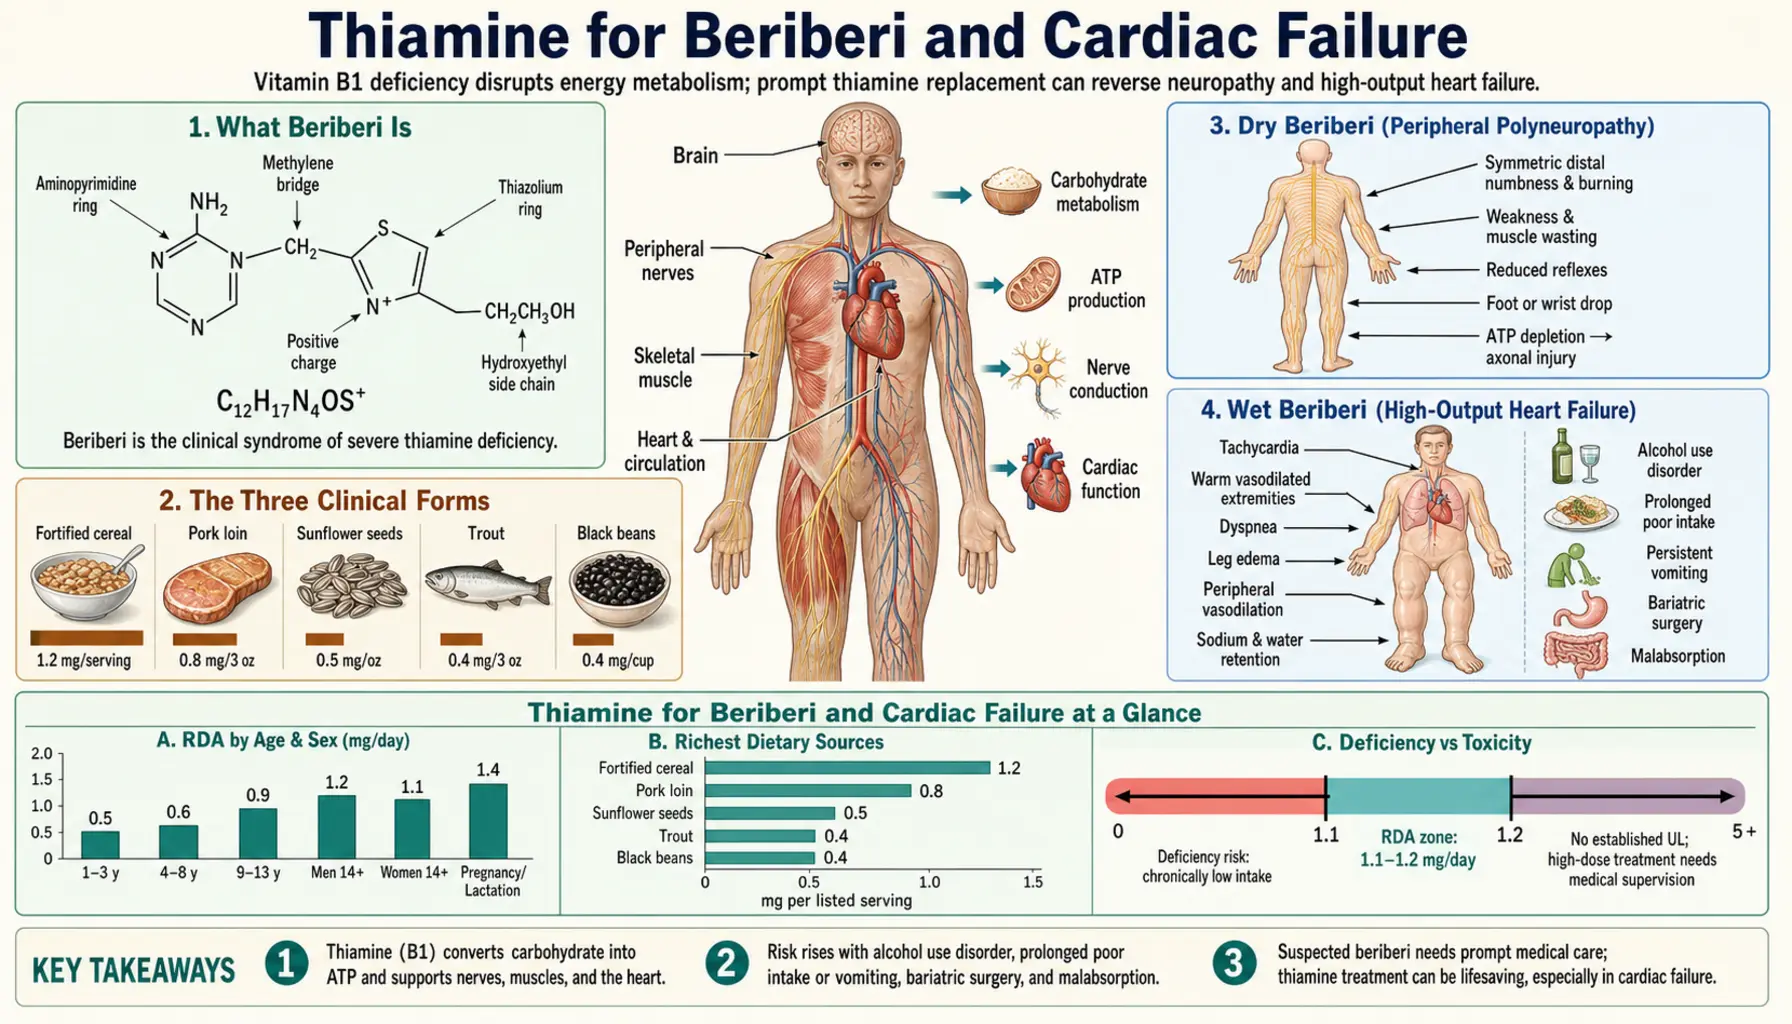
Beriberi is the syndrome of severe thiamine deficiency outside the brain, classically described in three forms: dry beriberi (length-dependent symmetric peripheral polyneuropathy), wet beriberi (high-output congestive heart failure with peripheral edema), and shoshin (acute fulminant cardiovascular collapse with lactic acidosis, often fatal within hours if thiamine is not given parenterally). Historically a disease of Asian rice-polishing populations, beriberi now appears in chronic alcoholics, dialysis patients, hyperemesis gravidarum, post-bariatric surgery, infants of thiamine-deficient mothers, and any patient on prolonged parenteral nutrition without thiamine. The cardiac response to parenteral thiamine is one of the most dramatic in medicine — ejection fraction improves measurably within 24-48 hours, edema clears within days, and the diagnosis is often confirmed by the magnitude and speed of the response. This page covers the three clinical phenotypes, the historical discovery, modern presentations, the biochemical fingerprint (lactic acidosis with high cardiac output), and the parenteral protocol.
Table of Contents
- What Beriberi Is
- The Three Clinical Forms
- Dry Beriberi (Peripheral Polyneuropathy)
- Wet Beriberi (High-Output Heart Failure)
- Shoshin (Acute Fulminant Cardiac Beriberi)
- Historical Discovery: Takaki and Eijkman
- Modern Causes
- The Biochemistry of Cardiac Failure in Thiamine Deficiency
- Diagnosis
- Treatment Protocol
- Response Timeline
- Heart Failure Patients on Loop Diuretics
- Cautions
- Key Research Papers
- Connections
- Featured Videos
What Beriberi Is
Beriberi is the clinical syndrome of severe thiamine deficiency outside the central nervous system. The name comes from the Sinhalese word beri (meaning "weakness," repeated for emphasis), reflecting the profound muscular weakness and exhaustion that characterizes the disease. While Wernicke-Korsakoff syndrome affects the brain, beriberi affects predominantly the peripheral nerves and the heart, though in practice they often coexist because the same patient with the same dietary deficiency manifests both at once.
Beriberi was epidemic across rice-eating populations of East and Southeast Asia from the late 1800s through the 1930s, following the introduction of steam-powered rice mills that produced highly polished white rice stripped of its thiamine-rich outer bran. Naval seamen, prison populations, and rural laborers fed near-exclusively on polished rice developed beriberi by the thousands, and the disease was for decades thought to be infectious. The discovery in the 1880s-1920s that beriberi was caused by absence of a dietary factor (later identified as vitamin B1) was a landmark in the development of the nutritional sciences and led to two Nobel Prizes.
The disease is now rare in high-income countries but is far from extinct. It appears in chronic alcoholics, patients on prolonged parenteral nutrition without thiamine, dialysis patients, hyperemesis gravidarum, post-bariatric surgery, and in refugee and famine populations. Outbreaks have been reported in immigration detention facilities, on commercial fishing vessels, and in any setting where a homogeneous low-thiamine diet is consumed for weeks to months.
The Three Clinical Forms
Classical descriptions divide beriberi into three forms based on which tissue dominates the clinical picture, though in practice patients often have overlapping features:
- Dry beriberi — predominantly a symmetric peripheral polyneuropathy. Cardiac involvement is absent or minor. The disease progresses over weeks to months.
- Wet beriberi — a high-output congestive heart failure with peripheral edema. Peripheral neuropathy is often present but the cardiac picture dominates. Progresses over weeks.
- Shoshin beriberi — the acute fulminant form. Patients present in cardiogenic shock with severe lactic acidosis. Without parenteral thiamine, death occurs within hours to days. The name shoshin is Japanese for "acute damage of the heart."
A fourth entity, infantile beriberi, occurs in breastfed infants of thiamine-deficient mothers and historically caused enormous infant mortality in Asia. It presents acutely with cardiac failure, aphonia (an inability to cry), and seizures, and is rapidly fatal without thiamine. The condition has reappeared sporadically — a 2003 outbreak in Israel was traced to a defective soy-based infant formula that contained no detectable thiamine (below 0.5 µg per gram when tested; Fattal-Valevski 2005).
Dry Beriberi (Peripheral Polyneuropathy)
Dry beriberi is a symmetric, length-dependent, axonal sensorimotor polyneuropathy with prominent autonomic involvement. The typical presentation includes:
- Distal symmetric sensory loss — numbness, tingling, and burning in a stocking-glove distribution, starting in the feet and ascending
- Motor weakness — foot drop, calf weakness, and difficulty climbing stairs; in advanced cases, hand weakness and muscle wasting
- Loss of deep tendon reflexes — ankle reflexes absent early, knee reflexes lost later
- Autonomic features — orthostatic hypotension, gastroparesis, constipation, impaired sweating
- Painful cramps — particularly nocturnal calf cramps and burning foot pain
The differential diagnosis is broad and includes diabetic peripheral neuropathy, alcoholic neuropathy (which itself includes a thiamine-deficiency component), and other nutritional neuropathies. In practice, severe alcoholic neuropathy is largely a beriberi-equivalent picture with overlapping toxic and nutritional mechanisms.
Nerve conduction studies show axonal loss with reduced amplitudes and relatively preserved conduction velocities. Sural nerve biopsy (rarely needed) shows axonal degeneration with secondary myelin loss.
Treatment is parenteral thiamine, but neurological recovery is slower than cardiac recovery. Sensory symptoms often improve over weeks to months. Motor strength returns gradually as axons regenerate (1-2 mm per day from the proximal site of injury). Severe cases may have residual deficits even with optimal treatment, particularly if treatment is delayed.
Wet Beriberi (High-Output Heart Failure)
Wet beriberi is a unique form of cardiac failure that is high-output rather than low-output. The biochemistry: severe thiamine deficiency causes peripheral vasodilation (the mechanism is incompletely understood but likely involves accumulated metabolic acids and impaired smooth muscle metabolism), and the heart compensates by increasing cardiac output to maintain blood pressure. Over time, the high-output state exhausts the cardiac reserve and the heart begins to fail despite an elevated ejection fraction.
Clinical features:
- Marked peripheral edema — bilateral leg swelling, often with anasarca in severe cases
- Tachycardia — resting heart rate typically 100-130 bpm
- Bounding peripheral pulses — reflecting the high cardiac output and warm vasodilated periphery
- Wide pulse pressure — systolic minus diastolic often >60 mmHg
- Dyspnea on exertion progressing to dyspnea at rest
- Right heart failure features — elevated jugular venous pressure, hepatic congestion, ascites in advanced cases
- Often preserved ejection fraction on echocardiography — the heart is failing functionally but the systolic squeeze appears normal or hyperdynamic
- Lactic acidosis on labs — the biochemical fingerprint
The combination of high-output heart failure + lactic acidosis + a normal or hyperdynamic ejection fraction in a malnourished, alcoholic, or otherwise high-risk patient is the picture in which treatment protocols give immediate parenteral thiamine. The differential diagnosis includes other causes of high-output heart failure (severe anemia, hyperthyroidism, arteriovenous fistulae, sepsis) but the response to thiamine is so rapid and dramatic that it often confirms the diagnosis empirically.
Note the contrast with the more common low-output heart failure seen in conventional cardiology practice (reduced ejection fraction, narrow pulse pressure, cool peripheries, low cardiac output). Wet beriberi is the mirror image and is often missed because clinicians do not expect this presentation.
Shoshin (Acute Fulminant Cardiac Beriberi)
Shoshin is the most dramatic and most rapidly fatal form. The Japanese term means "acute damage of the heart" and was used to describe the catastrophic, hours-to-days fatal cardiovascular collapse seen in some severely thiamine-deficient patients. Modern presentations include:
- An alcoholic or otherwise high-risk patient presenting to the emergency department in cardiogenic shock
- Severe lactic acidosis — lactate often >10 mmol/L
- Hypotension with paradoxically warm, well-perfused extremities (the high-output failure pattern persisting into cardiovascular collapse)
- Marked tachycardia with a hyperdynamic precordium
- Echocardiography showing either hyperdynamic LV function with high cardiac output or, in late stages, biventricular dilatation and dysfunction
- Standard heart-failure therapy (diuretics, vasopressors) making the patient worse — this is a useful clinical pearl, because the appropriate treatment is the opposite of what is given in conventional cardiogenic shock
Without parenteral thiamine, shoshin is rapidly fatal. With thiamine, the response is among the most dramatic in medicine: cardiac output often falls toward normal within hours, lactate clears, ejection fraction normalizes within days, and patients who looked moribund can walk out of the hospital within a week. Unexplained cardiogenic shock with profound lactic acidosis in a high-risk patient is the setting in which treatment protocols give empiric intravenous (IV) thiamine (500 mg in the protocol below) before further workup.
A 2026 case report shows how fast this can unfold. A previously healthy 25-year-old man developed refractory shock 2 months into intravenous feeding (parenteral nutrition) for severe pancreatitis; his lactate was 17.4 mmol/L and his heart's ejection fraction 15%. Heart-lung bypass support (venoarterial extracorporeal membrane oxygenation, VA-ECMO) was started within 90 minutes and kept his organs supplied until intravenous thiamine 200 mg every 8 hours, started on day 2, took effect: lactate normalised, ejection fraction rose to 25% within 96 hours, the bypass came off on day 8 and his heart function was fully recovered (55%) by day 10. His thiamine level before treatment was later confirmed low. The authors list prolonged poor intake or intravenous feeding without vitamins, otherwise unexplained high lactate and subtle neurological signs such as double vision as the bedside cues for early intravenous thiamine (Xie 2026).
Historical Discovery: Takaki and Eijkman
The discovery that beriberi was caused by absence of a dietary factor (rather than by infection or toxin) is one of the foundational stories in nutrition science. Two key figures share the credit:
Kanehiro Takaki, a Japanese naval physician, observed in the 1880s that beriberi was crippling the Imperial Japanese Navy — thousands of seamen developed the disease on long voyages, and the case-fatality was high. Takaki noted that British sailors on similar voyages did not develop beriberi, and hypothesized that the difference was in the diet: Japanese sailors ate near-exclusively polished rice, while British sailors ate a mixed diet of meat, bread, and vegetables. In an experimental voyage in 1884, he provisioned the warship Tsukuba with a Western-style diet including meat, condensed milk, vegetables, and barley-supplemented rice. The crew had no cases of beriberi, while a control voyage on polished rice produced 169 cases including 25 deaths. Takaki incorrectly attributed the protection to protein content, but he had nonetheless proven beriberi was diet-related.
Christiaan Eijkman, a Dutch military physician working in the Dutch East Indies (modern Indonesia), made the next critical observation in the 1890s. He was investigating beriberi in chicken coops at his Jakarta laboratory and observed that chickens developed a beriberi-like polyneuritis when fed white polished rice, and that the polyneuritis could be cured or prevented by feeding them unpolished (brown) rice or rice polishings, the bran layer removed in milling (Lanska 2010). His associate Gerrit Grijns correctly interpreted the finding: polished rice was missing a substance present in the bran that was essential for nerve health. The substance was eventually isolated by Casimir Funk in 1911 and named "vitamine" — from "vital amine" — coining the word that became "vitamin."
Eijkman shared the 1929 Nobel Prize in Physiology or Medicine with Frederick Hopkins for the discovery of vitamins. The Asian rice-polishing epidemics ended once the cause was understood, with parboiled rice (which retains thiamine), fortified rice, and dietary diversification eliminating beriberi as a population-scale disease in most of Asia by the mid-20th century.
Modern Causes
Beriberi in modern high-income countries appears in distinct clinical settings:
- Chronic alcoholism — the dominant cause in adults. Alcohol impairs intestinal thiamine absorption, accelerates urinary loss, depletes liver stores, and substitutes empty calories for thiamine-containing foods. The dry, wet, and shoshin forms all occur in alcoholic patients.
- Chronic hemodialysis — thiamine is dialyzed out of plasma each session, and dialysis patients who eat poorly are at chronic risk. Beriberi outbreaks in dialysis units have been reported.
- Bariatric surgery — particularly Roux-en-Y gastric bypass, where the jejunal absorption site is bypassed. Patients who vomit persistently after surgery or who fail to take prescribed supplements can develop beriberi within weeks to months.
- Hyperemesis gravidarum — persistent vomiting in pregnancy depletes thiamine. Wet beriberi and Wernicke encephalopathy in pregnancy have both been reported.
- Prolonged total parenteral nutrition without thiamine — the 1988 intravenous multivitamin shortage in the US produced a cluster of deaths from acute beriberi within weeks. The same trap recurs sporadically when generic TPN is mixed without standard additives.
- Refeeding syndrome — reintroducing carbohydrate to a severely malnourished patient depletes the already-marginal thiamine reserves and can precipitate acute beriberi or Wernicke encephalopathy. The UK NICE guideline on nutrition support in adults (CG32) lists oral thiamine 200-300 mg daily, given immediately before and during the first 10 days of feeding (or a full-dose daily intravenous vitamin B preparation if necessary), for people at high risk of refeeding problems.
- Outbreaks in confined populations — immigration detention, prisons, commercial fishing vessels, refugee camps. Any homogeneous low-thiamine diet eaten for weeks can produce beriberi.
- Infantile beriberi — in breastfed infants of thiamine-deficient mothers or from defective infant formula. The 2003 Israeli soy-formula outbreak caused multiple infant deaths and permanent neurological damage in survivors.
- Heart failure on loop diuretics — furosemide and other loop diuretics accelerate urinary thiamine loss. Many heart-failure patients have a subclinical or low-grade thiamine deficiency on top of their underlying cardiac disease; what the trials of supplementation found is covered below.
The Biochemistry of Cardiac Failure in Thiamine Deficiency
The heart is among the most metabolically active organs per gram of tissue and depends overwhelmingly on aerobic energy production. Roughly two-thirds of cardiac adenosine triphosphate (ATP) comes from oxidation of fatty acids and the remainder from glucose, both of which feed into the Krebs cycle through acetyl-CoA. Both pathways are blocked when thiamine pyrophosphate (TPP) becomes scarce:
- Pyruvate dehydrogenase (PDH) is blocked — glucose-derived pyruvate cannot enter the Krebs cycle and is shunted to lactate, producing the characteristic lactic acidosis.
- α-Ketoglutarate dehydrogenase is blocked — the rate-limiting step of the Krebs cycle itself fails, collapsing adenosine triphosphate production from both glucose and fatty acid oxidation.
- The branched-chain α-keto acid dehydrogenase (BCKDH) is also TPP-dependent and contributes a smaller fraction.
Without adenosine triphosphate, the cardiomyocyte cannot maintain calcium homeostasis or contractile function. The peripheral vasodilation of wet beriberi is mediated by accumulated organic acids (lactate, pyruvate) and impaired smooth-muscle metabolism. Cardiac output rises as the heart attempts to compensate; the elevated cardiac output eventually exhausts the failing cardiac reserve and overt heart failure develops.
The lactic acidosis is the diagnostic fingerprint. Few cardiac conditions produce simultaneously: high cardiac output, normal or hyperdynamic LV ejection fraction, severe lactic acidosis, and warm vasodilated peripheries. Septic shock is in the differential but lacks the hyperdynamic precordium and the chronic risk profile. This combination is the picture in which treatment protocols give immediate empiric intravenous thiamine (500 mg).
The reversibility of cardiac dysfunction is remarkable. Within hours of parenteral thiamine, TPP is regenerated, PDH and α-KGDH reactivate, adenosine triphosphate production resumes, and the cardiac and vascular biochemistry normalizes. Lactate clears, cardiac output falls toward normal, edema mobilizes, and the patient improves visibly day by day.
Diagnosis
Beriberi is largely a clinical diagnosis based on risk factors plus phenotype. Confirmatory testing exists but is rarely available in the timeframe required for treatment decisions:
- Serum thiamine level — available at reference labs but turnaround time is 2-7 days. Useful for retrospective confirmation.
- Erythrocyte transketolase activity — the gold-standard functional marker. A baseline reading + reading after addition of TPP in vitro; an "activation coefficient" >15-20% indicates functional deficiency.
- Whole-blood thiamine pyrophosphate (TPP) by HPLC — the most accurate measure of tissue stores, but turnaround is slow.
- Serum lactate — the biochemical fingerprint of acute deficiency. Elevated lactate in a high-risk patient is a strong clue.
- Response to empirical thiamine — the most useful "test" in practice. A patient who improves dramatically within 24-72 hours of parenteral thiamine had beriberi (or Wernicke), regardless of what the lab eventually shows.
Echocardiography is part of the workup but is non-specific — findings range from a hyperdynamic LV with normal chamber sizes (early wet beriberi) to a dilated cardiomyopathy with biventricular dysfunction (late or shoshin). Right heart catheterization, if performed, shows high cardiac index, low systemic vascular resistance, and elevated right and left filling pressures — the classical "high-output failure" hemodynamic pattern.
The cost of empirical parenteral thiamine is trivial (the drug costs pennies; the administration costs an intravenous nurse minute) and the cost of missed beriberi is death. In high-risk patients with unexplained cardiac failure, lactic acidosis, or peripheral neuropathy, treatment protocols give thiamine first and pursue confirmatory testing in parallel.
Treatment Protocol
The treatment protocol parallels that for Wernicke encephalopathy (and the two conditions often coexist, so treating one treats the other):
- Acute phase — Thiamine 500 mg intravenous three times daily for 3-5 days, infused in 100 mL of saline over 30 minutes per dose
- Step-down — Thiamine 250 mg intravenous or IM daily for an additional 3-5 days
- Maintenance — Thiamine 100 mg orally daily indefinitely (for chronic alcoholics, dialysis patients, post-bariatric patients, often for life)
- Alongside thiamine — magnesium (essential cofactor for TPP synthesis), other B vitamins and electrolytes are replaced, and the underlying cause is addressed (alcohol cessation, nutritional rehabilitation, surgical management of bariatric complications)
In shoshin beriberi with cardiogenic shock, thiamine takes priority over standard heart-failure therapy. Diuretics and vasopressors can worsen the situation in the absence of thiamine repletion. After thiamine is given and the cardiac biochemistry begins to recover, conventional supportive care (gentle diuresis to manage edema, vasopressors as needed for shock that does not resolve) can be added.
Magnesium replacement is critical. Thiamine cannot be converted to TPP without magnesium, and many alcoholic / malnourished patients have profound hypomagnesemia. Apparent "thiamine resistance" (failure to respond to parenteral thiamine) is often actually magnesium deficiency, which is why protocols check and replace magnesium.
Response Timeline
The response to parenteral thiamine in wet beriberi and shoshin is among the most dramatic in clinical medicine:
| Timeframe | Expected Response |
|---|---|
| Hours 0-6 | Lactate begins to fall; hemodynamic instability begins to stabilize |
| Hours 6-24 | Lactate normalizes; tachycardia improves; cardiac output begins to fall toward normal |
| Days 1-3 | Edema begins to mobilize; ejection fraction (if depressed) begins to recover; pulmonary congestion clears |
| Days 3-7 | Substantial recovery of cardiac function and resolution of fluid overload; patient often discharged home on oral thiamine |
| Weeks 1-4 | Cardiac function continues to improve toward normal; peripheral neuropathy begins slow recovery |
| Months 1-12 | Peripheral nerve symptoms continue to improve as axonal regeneration occurs; full recovery often achievable |
The speed of cardiac response is itself often considered diagnostic. A patient with refractory high-output heart failure who improves dramatically within 48 hours of parenteral thiamine had wet beriberi, regardless of what the initial lab panel showed.
Peripheral neuropathy recovers more slowly than cardiac function because nerves must physically regenerate, while cardiac muscle simply needs metabolic support restored. Sensory symptoms improve over weeks; motor strength returns over months. Severe long-standing dry beriberi may have residual deficits even with optimal treatment.
Heart Failure Patients on Loop Diuretics
Loop diuretics (furosemide, bumetanide, torsemide) increase urinary thiamine excretion substantially. A meaningful fraction of chronic heart failure patients on long-term loop diuretic therapy have biochemical evidence of low or borderline thiamine status, even when overt beriberi is absent:
- In a 1995 clinic study, 8 of 38 heart-failure patients on loop diuretics (21%) had biochemical evidence of thiamine deficiency (Brady 1995).
- In a 2006 study of 100 patients in hospital with heart failure, 33% were thiamine-deficient, compared with 12% of 50 people without heart failure (Hanninen 2006).
- A 2015 review pooling 9 studies found thiamine deficiency about 2.5 times as common in people with heart failure as in people without it (odds ratio 2.53) (Jain 2015).
The Schoenenberger 2012 trial was a small crossover study: 9 patients taking diuretics for symptomatic chronic heart failure, with an ejection fraction below 40%, received thiamine 300 mg/day or placebo for 28 days each, with a 6-week break in between. After thiamine, the left ventricular ejection fraction rose from 29.5% to 32.8%, compared with 28.8% on placebo — a modest but statistically significant difference of 3.9 percentage points (p = 0.024). The 2015 review noted that small observational studies and randomised trials suggested supplementation may improve ejection fraction and reduce symptoms (Jain 2015).
Two later pooled analyses of randomised placebo-controlled trials did not confirm a benefit. A 2023 analysis of 6 trials (298 participants) found no significant effect on ejection fraction (p = 0.08), NT-proBNP (a blood marker of heart strain), walking distance, hospitalisation or mortality (p = 0.61); heart rate was the only outcome that changed (Syed 2023). A 2024 analysis of 7 double-blind trials (274 patients with chronic heart failure) found that thiamine corrected thiamine deficiency but did not significantly change ejection fraction (average difference 1.65 percentage points, p = 0.239), heart size, 6-minute walking distance, NT-proBNP or symptom class (He 2024).
The Schoenenberger trial used thiamine 300 mg/day; no heart-failure trial cited here tested benfotiamine, the fat-soluble form of thiamine. Oral thiamine is inexpensive and has no documented chronic toxicity (see Cautions).
Cautions
- Anaphylaxis with intravenous thiamine — rare (<1 per 5 million doses) but reported. Protocols give the first intravenous dose in a monitored setting; the reaction is rare enough that protocols do not treat it as a reason to withhold thiamine.
- Magnesium deficiency blocks the response — thiamine cannot be converted to TPP without magnesium. Apparent "thiamine resistance" is often actually hypomagnesemia.
- Beriberi mimics other diseases — cirrhosis with ascites, septic shock, severe anemia, hyperthyroidism, and AV fistula can all produce overlapping pictures. In uncertain cases, protocols give empiric thiamine while other workup proceeds.
- Standard heart-failure therapy can worsen shoshin beriberi if given before thiamine — vasopressors and aggressive diuresis can precipitate cardiovascular collapse in the volume-depleted thiamine-deficient patient.
- Glucose before thiamine is dangerous — intravenous dextrose in a thiamine-deficient patient can precipitate acute deterioration. Protocols give thiamine first or together with glucose-containing fluids.
- Long-term oral thiamine 100 mg/day is safe — thiamine is water-soluble, has no documented chronic toxicity, and is excreted in urine.
- The underlying cause — sustained recovery requires alcohol cessation, nutritional rehabilitation, addressing the bariatric anastomosis, treating the underlying gastrointestinal (GI) disease, or whatever else drove the deficiency.
Key Research Papers
- Yamasaki H, Tada H, Kawano S, Aonuma K (2010). Reversible pulmonary hypertension, lactic acidosis, and rapidly evolving multiple organ failure as manifestations of shoshin beriberi. Circ J 74(9):1983-1985. — PubMed PMID: 20622473
- Xie X, Deng L, Zhao J, Sun X, Liu L, Pan X, Zhang Y (2026). Fulminant cardiovascular collapse after acute pancreatitis: a case report of non-alcoholic Shoshin beriberi and literature review. AME Case Rep 10:88. — PubMed PMID: 42299383
- Schoenenberger AW et al. (2012). Thiamine supplementation in symptomatic chronic heart failure: a randomized, double-blind, placebo-controlled, cross-over pilot study. Clin Res Cardiol. — PubMed PMID: 22057652
- Sica DA (2007). Loop diuretic therapy, thiamine balance, and heart failure. Congest Heart Fail. — PubMed PMID: 17673878
- Carpenter KJ (2000). Beriberi, white rice, and vitamin B: a disease, a cause, and a cure. University of California Press. — PubMed: Carpenter beriberi history
- Fattal-Valevski A et al. (2005). Outbreak of life-threatening thiamine deficiency in infants in Israel caused by a defective soy-based formula. Pediatrics. — PubMed PMID: 15687431
- Davis RE, Icke GC (1983). Clinical chemistry of thiamin. Adv Clin Chem 23:93-140. — PubMed PMID: 6398618
- Brady JA et al. (1995). Thiamine status, diuretic medications, and the management of congestive heart failure. J Am Diet Assoc. — PubMed PMID: 7722187
- Hanninen SA, Darling PB, Sole MJ, Barr A, Keith ME (2006). The prevalence of thiamin deficiency in hospitalized patients with congestive heart failure. J Am Coll Cardiol 47(2):354-361. — PubMed PMID: 16412860
- Centers for Disease Control (1989). Deaths associated with thiamine-deficient total parenteral nutrition. MMWR. — PubMed PMID: 2492074
- Donnino MW et al. (2010). Thiamine deficiency in critically ill patients with sepsis. J Crit Care. — PubMed PMID: 20646908
- Attaluri P, Castillo A, Edriss H, Nugent K (2018). Thiamine deficiency: an important consideration in critically ill patients. Am J Med Sci 356(4):382-390. — PubMed PMID: 30146080
- Jain A, Mehta R, Al-Ani M, Hill JA, Winchester DE (2015). Determining the role of thiamine deficiency in systolic heart failure: a meta-analysis and systematic review. J Card Fail 21(12):1000-1007. — PubMed PMID: 26497757
- Syed ARS, Syed AA, Akram A, Azam MS, Muzammil MA, Deepak, Ansari AI, Eqbal F, Farooq MH, Khatri M, Kumar S, Kumar N (2023). Does thiamine supplementation affect heart failure? A systematic review and meta-analysis of randomized control trials. Heart Lung 61:37-45. — PubMed PMID: 37126872
- He S, Wang S, Xu T, Wang S, Qi M, Chen Q, Lin L, Wu H, Gan P (2024). Role of thiamine supplementation in the treatment of chronic heart failure: an updated meta-analysis of randomized controlled trials. Clin Cardiol 47(7):e24309. — PubMed PMID: 38940395
- Lanska DJ (2010). Chapter 30: historical aspects of the major neurological vitamin deficiency disorders: the water-soluble B vitamins. Handb Clin Neurol 95:445-476. — PubMed PMID: 19892133
- National Institute for Health and Care Excellence (2006). Nutrition support for adults: oral nutrition support, enteral tube feeding and parenteral nutrition. Clinical guideline CG32, Recommendations. — nice.org.uk/guidance/cg32
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B1 Overview
- B1 Benefits Hub
- B1 for Wernicke-Korsakoff
- Benfotiamine for Diabetic Neuropathy
- B1 for Cognition & Alzheimer's
- Thiamine and Beriberi
- Heart Failure
- Peripheral Neuropathy
- Diabetes
- Fatigue
- Numbness & Tingling
- Edema
- Magnesium
- Alpha-Lipoic Acid for Diabetic Neuropathy
- Detox Protocols
- Deficiency
- Toxicity
- History
- Sources